Buy Rapacan Sirolimus Online for Kidney Transplant Rejection Prevention Lymphangioleiomyomatosis and Tuberous Sclerosis Treatment

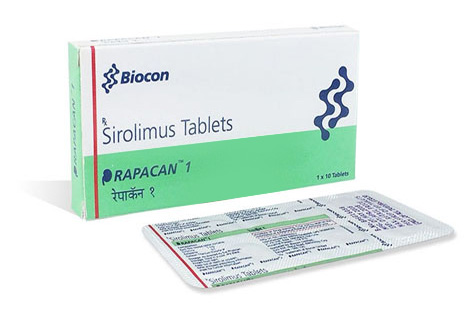
Rapacan (Sirolimus 1mg) represents the Indian Cipla generic version of brand-name Rapamune — the original mTOR inhibitor immunosuppressant derived from a soil-dwelling bacterium discovered on Rapa Nui (Easter Island), the source of the historic name "rapamycin." As a unique mechanistic Target of Rapamycin (mTOR) pathway blocker, Rapacan provides distinctive immunosuppression that complements or replaces traditional calcineurin inhibitors in transplant medicine. The 1 mg oral tablets manufactured by Cipla Limited deliver bioequivalent therapeutic outcomes to brand-name Pfizer Rapamune at substantially lower cost.
Sirolimus works through unique mTOR inhibition mechanism distinct from calcineurin inhibitors like cyclosporine and tacrolimus. The medication binds FK-binding protein 12 (FKBP-12) intracellularly, forming a complex that inhibits the mechanistic Target of Rapamycin (mTOR) — a key kinase regulating cell growth, proliferation, and metabolism. This blocks T-lymphocyte activation and progression from G1 to S phase, preventing immune cell proliferation in response to alloantigen and other stimuli. The mechanism also inhibits smooth muscle cell proliferation (rationale for drug-eluting cardiac stents) and suppresses vascular endothelial growth factor (VEGF) production. The result: kidney transplant 1-year survival exceeds 90%, acute rejection rates drop substantially in combination immunosuppression, lymphangioleiomyomatosis stabilizes preserving lung function, and nephrotoxicity is avoided versus calcineurin inhibitors making sirolimus attractive in renal-sparing protocols.
Rapacan serves the FDA-approved indications of kidney transplant rejection prophylaxis in patients ages 13 years and older, and lymphangioleiomyomatosis (LAM) — a rare progressive lung disease primarily affecting women. The medication is also used in tuberous sclerosis complex (TSC) for related angiomyolipomas; heart and liver transplantation off-label particularly for renal-sparing protocols; graft-versus-host disease (GVHD) prophylaxis after stem cell transplantation; chronic transplant kidney dysfunction; and selected cases requiring calcineurin inhibitor avoidance due to nephrotoxicity, neurotoxicity, or diabetogenic effects.
Rapacan requires once-daily oral dosing at consistent time relative to meals with regular blood level monitoring targeting 5-15 ng/mL trough levels depending on protocol. The medication shows extended 60-hour half-life enabling once-daily dosing. Maximum immunosuppressive effect develops over 4-7 days after dose adjustment. Cipla Limited manufactures Rapacan under WHO-GMP, US FDA, and Indian DCGI quality standards with bioequivalence to brand-name Rapamune documented through standard regulatory studies.
Free prescription
Discrete packaging
Have questions?
Quality Assurance

- Kidney Transplantation: FDA-approved for renal transplant rejection prophylaxis in patients 13 years and older;
- Transplant Rejection Prevention: Long-term mTOR inhibition immunosuppression maintenance preventing rejection episodes;
- Acute Rejection Prevention: Combination immunosuppression substantially reduces acute rejection episodes in first year post-transplant;
- Chronic Rejection Prevention: Long-term maintenance preventing chronic allograft dysfunction and graft loss;
- Renal Sparing Immunosuppression: Calcineurin inhibitor alternative avoiding nephrotoxicity in vulnerable transplant patients;
- Calcineurin Inhibitor Avoidance: Used when cyclosporine or tacrolimus toxicity requires alternative immunosuppression;
- Lymphangioleiomyomatosis: Rare progressive lung disease primarily affecting women treated with FDA-approved mTOR inhibition;
- LAM Disease: Lymphangioleiomyomatosis lung disease stabilized through mTOR pathway suppression;
- Tuberous Sclerosis Complex: Genetic disorder with angiomyolipomas responding to mTOR inhibition therapy;
- Renal Angiomyolipoma: Benign kidney tumors in TSC patients responding to sirolimus tumor reduction;
- Heart Transplantation: Off-label use for cardiac transplant rejection prevention particularly with renal concerns;
- Liver Transplantation: Off-label maintenance immunosuppression for hepatic transplant recipients;
- GVHD Prophylaxis: Off-label prevention of graft-versus-host disease after stem cell transplantation;
- Chronic Allograft Dysfunction: Conversion therapy for transplant kidneys with progressive function decline;
- Coronary Stent Restenosis Prevention: Mechanism behind drug-eluting cardiac stent coatings preventing restenosis;
- Renal Cell Carcinoma: Off-label use for selected RCC cases though related mTOR inhibitors are preferred;
- Autoimmune Disease: Off-label use for refractory autoimmune conditions including SLE and uveitis;
- mTOR Inhibitor Therapy: Mechanism class targeting mechanistic Target of Rapamycin pathway for immune and cell growth control;
- Generic Rapamune Therapy: Bioequivalent generic alternative to brand-name Rapamune at substantially lower cost.
- Less Acute Rejection Episodes: Acute rejection rates drop substantially in first year combination protocols including sirolimus;
- Better Long Term Graft Survival: Chronic allograft dysfunction progression slows with sustained mTOR inhibition;
- Less Calcineurin Nephrotoxicity: Renal-sparing protocols avoid cyclosporine and tacrolimus kidney damage in vulnerable patients;
- Less Calcineurin Neurotoxicity: Tremor and other CNS effects of CNI avoided in sirolimus-based protocols;
- Less New Onset Diabetes Risk: Avoids diabetogenic effects of tacrolimus seen in vulnerable transplant patients;
- Better LAM Lung Function Stabilization: Lymphangioleiomyomatosis progression slows preserving lung function in affected women;
- Less Angiomyolipoma Size: TSC-related renal angiomyolipomas shrink with mTOR inhibition therapy;
- Less TSC Tumor Growth: Tuberous sclerosis-related tumor formations stabilize through mTOR pathway suppression;
- Better Coronary Restenosis Prevention: Drug-eluting cardiac stents coated with sirolimus prevent in-stent restenosis;
- Less Vascular Smooth Muscle Proliferation: Beneficial for stent coating and vascular interventions through mTOR-mediated cell cycle arrest;
- Better GVHD Prevention: Off-label use after stem cell transplant reduces graft-versus-host disease severity;
- Less Calcineurin Inhibitor Side Effects: Avoids multiple CNI-related complications when sirolimus substitution is appropriate;
- Better Renal Cell Carcinoma Response: Selected RCC cases respond to mTOR pathway suppression as targeted therapy;
- Better Combination Immunosuppression: Complementary mechanism enables effective combination with corticosteroids and antimetabolites;
- Better Transplant Recipient Quality of Life: Long-term graft function preserves wellbeing with stable immunosuppression;
- Less Transplant Failure Anxiety: Reliable immunosuppression provides confidence in long-term graft function;
- Better Generic Cost: Substantially lower cost than brand Rapamune makes proven mTOR inhibitor therapy financially accessible;
- Once Daily Convenience: Long half-life enables once-daily dosing without multiple daily administration requirements;
- Better Quality of Life: Daily wellbeing improves dramatically as transplant function preserves and disease stabilizes.
Generic Rapacan (Sirolimus 1 mg) Medication guide:
📌 What Rapacan Is and Rapamycin Discovery Story
Rapacan is a generic sirolimus tablet manufactured by Biocon, India's largest biopharmaceutical company. Sirolimus is also known as rapamycin — the name comes from Rapa Nui, the native name for Easter Island where the compound was first isolated in 1972.
📌 Three anchor facts:
- 🧬 mTOR inhibitor — blocks a master cell growth pathway
- 🫀 Original indication — kidney transplant rejection prophylaxis (FDA 1999)
- 🫁 Expanded indications — lymphangioleiomyomatosis (LAM), tuberous sclerosis (TSC)
Rapacan works through a completely different mechanism than other immunosuppressants. While cyclosporine and tacrolimus inhibit calcineurin, sirolimus blocks the mechanistic target of rapamycin (mTOR) — a signaling hub that regulates cell growth, proliferation, and metabolism.
| Property | Rapacan |
|---|---|
| Active ingredient | Sirolimus (rapamycin) |
| Manufacturer | Biocon, Bangalore India |
| Drug class | mTOR inhibitor; antiproliferative immunosuppressant |
| Standard tablets | 1 mg (sometimes 0.5 mg, 2 mg) |
| Typical dosing | 1-6 mg daily by blood level targeting |
| Half-life | ~62 hours (very long) |
| Reference brand | Rapamune (Pfizer/Wyeth) |
🎯 What Rapacan actually does: blocks mTOR signaling in rapidly dividing cells. In transplant, this prevents T-cell proliferation that drives rejection. In LAM, this suppresses pathologic smooth muscle growth in lungs. In TSC, this shrinks tumors driven by constitutive mTOR activation.
🎯 Clinical indications for Rapacan:
- 🫀 Kidney transplant rejection prophylaxis — original FDA indication
- 🫁 Lymphangioleiomyomatosis (LAM) — rare lung disease in women
- 🧠 Tuberous sclerosis complex (TSC) — brain tumors, angiomyolipomas, skin manifestations
- 🩸 Complex vascular malformations — off-label pediatric and adult use
- ❤️ Drug-eluting coronary stents — prevents restenosis
- 🏃 Research applications — aging, longevity, specific cancers
⚠️ This is a specialist medication requiring supervised use. Rapacan needs blood level monitoring (narrow therapeutic index), lipid management, pneumonitis vigilance, careful drug interaction management (CYP3A4), and specific protocols around surgery (impaired wound healing).
Biocon is India's largest biopharmaceutical company and a global exporter of complex generics. Rapacan represents access to mTOR inhibitor therapy at generic pricing for patients worldwide who need long-term treatment for transplantation or rare diseases.
🏝️ Sirolimus from Easter Island to Transplant Medicine
Few drugs have an origin story as remarkable as sirolimus. The compound was discovered in soil samples from Easter Island (Rapa Nui) collected during a 1964 Canadian scientific expedition. Scientists at Ayerst Research Laboratories isolated it in 1972 from Streptomyces hygroscopicus bacteria.
The name rapamycin honors the island of discovery. The clinical name sirolimus became standard once the drug entered pharmaceutical development.
📅 Rapamycin timeline
- 🏝️ 1964 — Canadian expedition collects soil samples on Easter Island
- 🧫 1972 — Vezina and colleagues isolate rapamycin at Ayerst Labs
- 🍄 Early 1970s — Originally characterized as antifungal
- 🛡️ Late 1970s — Immunosuppressant activity recognized
- 🧬 1990s — Hall and Sabatini discover mTOR protein and pathway
- 🏆 1999 — FDA approves Rapamune for kidney transplant rejection prophylaxis
- ❤️ 2003 — First sirolimus-eluting coronary stent (Cypher)
- 📊 2011 — MILES trial establishes sirolimus for LAM
- 🫁 2015 — FDA approves sirolimus for LAM (first drug ever for LAM)
- 🏆 2017 — Michael Hall awarded Lasker Award for mTOR discovery
- 🌍 Today — Generic sirolimus including Rapacan available worldwide
🏝️ Why the Easter Island origin matters:
- 🌋 Unique soil microbiology of Rapa Nui yielded a novel compound
- 🧪 Streptomyces hygroscopicus produces rapamycin as natural metabolite
- 🏃 Classic natural product drug discovery — like penicillin, streptomycin
- 🏝️ Historical significance — remote island soil led to major pharmaceutical breakthrough
| Era | Clinical use evolution |
|---|---|
| 1972-1990s | Research compound; mechanism being elucidated |
| 1999-2003 | Approved for kidney transplant; combined with calcineurin inhibitors |
| 2003-2011 | Drug-eluting stent era; calcineurin-sparing protocols |
| 2011-today | LAM and TSC approvals; expanding rare disease uses |
| Research frontier | Aging research, longevity, pediatric vascular anomalies |
🧬 The mTOR discovery by Prof. Michael Hall at Basel and Prof. David Sabatini at MIT in the 1990s revealed why rapamycin had such diverse effects. mTOR turned out to be a master regulator of cell growth, metabolism, and proliferation across many tissues — which explains both the drug's broad therapeutic applications and its distinctive side effect profile.
🤔 Why sirolimus remains clinically important:
- 🏆 Unique mechanism — no other oral mTOR inhibitor in widespread use except everolimus
- 🫀 Non-nephrotoxic — alternative to calcineurin inhibitors in transplant
- 🫁 Only FDA-approved therapy for LAM
- 🧠 Standard therapy for TSC manifestations
- 🌍 Generic availability — Rapacan and other Indian generics expand access
The Easter Island story is a reminder that clinical breakthroughs can emerge from unexpected places. A soil sample collected during a scientific expedition to one of the most remote inhabited places on Earth produced a drug that has transformed kidney transplantation, saved lives in LAM, and continues to open new therapeutic frontiers more than 50 years after its original isolation.
🏬 Biocon Context and Indian Generic Sirolimus
Biocon is India's largest biopharmaceutical company and a major producer of complex generics and biosimilars for global markets. Founded in 1978 in Bangalore by Kiran Mazumdar-Shaw, Biocon has grown into a leading supplier of insulin, oncology medications, and complex immunosuppressants including Rapacan sirolimus.
Understanding the manufacturer context matters for complex generic drugs like sirolimus where manufacturing quality directly affects clinical performance.
🏬 Biocon by the numbers
- 📅 Founded — 1978 in Bangalore, India
- 👩 Founder — Kiran Mazumdar-Shaw, pioneering woman entrepreneur
- 🏆 India's largest biopharma by revenue
- 🌍 Global reach — products in 120+ countries
- 🏬 Manufacturing sites — FDA, EMA, PMDA inspected
- 💊 Portfolio — biosimilars, insulin, oncology, immunosuppressants
- 🤝 Biosimilars leader — one of the first global biosimilars
🌍 Why specialist Indian generics matter for sirolimus:
- 💰 Price access — branded Rapamune very expensive long-term
- 🚢 Global export — emerging markets rely on Indian manufacturers
- 🧪 Complex formulation — sirolimus requires sophisticated manufacturing
- 🎯 Narrow therapeutic index — consistent generic quality is essential
- 🤝 Regulatory depth — Biocon products meet FDA/EMA inspection standards
| Sirolimus brand | Manufacturer |
|---|---|
| Rapacan | Biocon India |
| Rapamune | Pfizer / Wyeth (original brand) |
| Siromus | Panacea Biotec India |
| Rapamace | Macleods India |
| Generic sirolimus (US/EU) | Multiple post-patent expiry 2014 |
🎯 Clinical equivalence of Rapacan to Rapamune: same sirolimus molecule, same tablet strength, bioequivalence demonstrated for regulatory approval, same blood level targeting approach. The medication delivers the same mTOR inhibition at generic pricing.
🧪 Quality verification for Rapacan:
- ✅ CDSCO India registration — Indian regulatory approval
- ✅ WHO-GMP certification — good manufacturing practice
- ✅ Bioequivalence — required for generic status
- ✅ Blood level consistency — critical for narrow therapeutic index drugs
- ✅ Export facility inspections — FDA, EMA oversight of Biocon sites
⚠️ Switching between sirolimus brands can sometimes produce small changes in blood levels because of formulation differences. Transplant teams often recheck blood levels after any brand change to confirm therapeutic range is maintained. This is standard practice for narrow therapeutic index drugs.
💰 Price advantage of Indian generics:
- 💰 Branded Rapamune — often $1000+ monthly in US market
- 💰 Indian generic Rapacan — fraction of branded cost
- 💰 Long-term therapy — cost difference compounds over years
- 🌍 Developing markets — access entirely dependent on generic availability
Rapacan represents the broader story of Indian biopharmaceutical manufacturing providing global access to essential complex medications. For patients requiring long-term sirolimus therapy — whether for transplant maintenance, LAM, TSC, or other indications — generic availability has transformed what was once a prohibitively expensive therapy into accessible long-term care.
🧬 How Sirolimus Blocks mTOR Signaling Pathway
Rapacan works by inhibiting mTOR (mechanistic target of rapamycin), a protein kinase that serves as a master regulator of cell growth, proliferation, and metabolism. The mechanism is fundamentally different from calcineurin inhibitors (cyclosporine, tacrolimus) that dominate transplant immunosuppression.
This unique mechanism explains both why sirolimus has broad therapeutic applications across diverse diseases and why it has a distinctive side effect profile including hyperlipidemia, impaired wound healing, and mouth ulcers.
🧬 How sirolimus inhibits mTOR
- 💊 Sirolimus absorbed from gut; distributed widely
- 🧪 Binds immunophilin FKBP12 inside cells
- 🌀 Sirolimus-FKBP12 complex binds mTOR directly
- 🚫 Inhibits mTORC1 (mTOR Complex 1) — the main therapeutic target
- 📉 Downstream effects — reduced protein synthesis, cell growth, proliferation
- 🛡️ Immunosuppression — T and B lymphocytes stop proliferating
- 🧬 Antiproliferative effect — also affects smooth muscle, blood vessels, tumors
🎯 What mTOR does normally:
- 🧬 Integrates growth signals — from nutrients, growth factors, energy status
- 📈 Promotes protein synthesis — when conditions favor growth
- 🔄 Regulates cell cycle progression
- 🏪 Controls autophagy — cellular recycling process
- 🧪 Lipid and glucose metabolism regulation
- 🧫 Immune cell activation downstream of IL-2 and other cytokines
| Immunosuppressant class | Mechanism |
|---|---|
| Calcineurin inhibitors (tacrolimus, cyclosporine) | Block T-cell receptor signaling; nephrotoxic |
| mTOR inhibitors (sirolimus, everolimus) | Block downstream growth signaling; not nephrotoxic |
| Antimetabolites (azathioprine, mycophenolate) | Block DNA synthesis; antiproliferative |
| Corticosteroids (prednisolone) | Broad anti-inflammatory and immunomodulatory |
| Biologics (various) | Target-specific cytokines or receptors |
🎯 Why sirolimus is not nephrotoxic: unlike calcineurin inhibitors that directly damage kidney vasculature over time, sirolimus works through a different pathway that spares kidney function. This makes it uniquely valuable for transplant recipients developing CNI-related kidney damage — conversion to sirolimus can preserve remaining kidney function.
🤔 Why sirolimus has such diverse clinical uses:
- 🧬 mTOR is expressed everywhere — so mTOR inhibition affects many tissues
- 🫁 LAM — mTOR hyperactivation in smooth muscle cells
- 🧠 TSC — genetic mutations constitutively activate mTOR
- ❤️ Vascular smooth muscle — mTOR inhibition prevents restenosis in stents
- 🧬 Cell proliferation generally — antitumor applications in cancer
- 🕚 Aging biology — mTOR implicated in longevity research
⚠️ Why sirolimus has distinctive side effects: because mTOR regulates so many cellular processes, inhibiting it affects many tissues. Hyperlipidemia (metabolism), impaired wound healing (cell proliferation needed for repair), mouth ulcers (rapidly dividing cells of mucosa), and pneumonitis (lung inflammation) all stem from this broad mTOR role.
🏆 The mTOR discovery by Hall and Sabatini in the 1990s transformed cell biology and informs modern pharmacology. The Lasker Award to Michael Hall in 2017 recognized the foundational importance of this work. Clinical use of sirolimus continues to expand as the mTOR pathway reveals new therapeutic opportunities.
💊 Rapacan Dosing by Indication and Blood Levels
Rapacan dosing is indication-specific and blood level targeted. Unlike most oral medications given at fixed doses, sirolimus doses are adjusted based on trough blood level measurements to maintain therapeutic range while avoiding toxicity.
The narrow therapeutic index of sirolimus (small range between effective and toxic levels) makes blood level monitoring essential for safe long-term use.
🎯 Rapacan dosing is tailored by target blood level. Prescribers set a target range for your condition, measure trough levels regularly, and adjust the dose up or down to stay in range.
| Indication | Target trough level | Typical dose range |
|---|---|---|
| Kidney transplant (with CNI) | 4-12 ng/mL | 2-5 mg daily |
| Kidney transplant (CNI-free) | 12-20 ng/mL | 4-10 mg daily |
| Lymphangioleiomyomatosis | 5-15 ng/mL | 2 mg daily typical |
| Tuberous sclerosis complex | 5-15 ng/mL | Weight-based initial titration |
| Pediatric vascular malformations | 5-15 ng/mL | 0.8 mg/m2 twice daily initial |
⚠️ Loading dose considerations:
- 📈 Loading dose often used initially: 6-15 mg once, then daily maintenance
- 🕐 Long half-life (~62 hours) means steady state takes 5-7 days
- 🧪 First blood level check typically at day 5-7
- 🔄 Dose adjustments based on levels, not symptoms
- ⏳ Patience with adjustments — wait at least 5 days for new steady state
🕚 Timing considerations:
- ⏰ Once daily dosing — long half-life supports it
- 🍽️ Consistent timing — same time each day
- 🥕 With or without food — but keep consistent (food changes absorption slightly)
- 🍅 Avoid grapefruit — CYP3A4 interaction raises levels dangerously
- ⏰ At least 4 hours from cyclosporine — cyclosporine raises sirolimus levels when co-administered
| What raises sirolimus levels | What lowers sirolimus levels |
|---|---|
| 🍅 Grapefruit juice | 💊 Rifampin, rifabutin |
| 💊 Azole antifungals (ketoconazole, voriconazole) | 💊 Phenytoin, carbamazepine |
| 💊 Macrolides (erythromycin, clarithromycin) | 🌿 St. John's wort |
| 💊 Protease inhibitors | 💊 Phenobarbital |
| 💊 Cyclosporine (significant interaction) | 🏃 Enzyme inducers generally |
🕚 The sirolimus-cyclosporine interaction deserves specific mention. Co-administration raises sirolimus levels. Standard protocol: take sirolimus 4 hours after cyclosporine to minimize this effect. Blood level monitoring accounts for the remaining interaction.
🎯 Patient responsibilities for safe Rapacan use:
- 📋 Take at same time daily — consistency essential
- 🍅 Avoid grapefruit — critical interaction
- 🤝 Inform all prescribers you take sirolimus
- 💊 Check with pharmacist before new medications
- 🧪 Attend blood level monitoring appointments
- 📱 Pill reminders — crucial for consistent timing
Rapacan dosing represents a classic example of therapeutic drug monitoring in modern medicine. The combination of blood level measurement, careful drug interaction management, and patient adherence produces safe and effective therapy for conditions requiring long-term mTOR inhibition.
🫀 Rapacan in Kidney Transplant Rejection Prevention
Kidney transplant rejection prevention is Rapacan's original and primary FDA-approved indication. The medication prevents T-cell-mediated rejection by blocking mTOR signaling downstream of IL-2 receptor activation.
Modern kidney transplant protocols combine sirolimus with other immunosuppressants in various configurations depending on patient factors, donor characteristics, and center preferences.
🫀 Rapacan in kidney transplantation is used as part of multi-drug immunosuppressive regimens. The specific role varies: some patients start on sirolimus, others convert from calcineurin inhibitors later, and some use it only in specific scenarios.
🎯 Sirolimus roles in kidney transplantation:
- 🔄 Primary maintenance — initial immunosuppression with low-dose CNI
- 🔄 CNI conversion — switching from tacrolimus/cyclosporine for nephrotoxicity
- 🔄 CNI minimization — allows lower CNI dose
- 🚫 CNI-free protocols — sirolimus plus mycophenolate plus steroid
- 🏆 Secondary indication — specific scenarios like post-transplant malignancy
| Scenario | Typical sirolimus role |
|---|---|
| Standard new transplant | Usually tacrolimus-based; sirolimus not routine first-line |
| CNI nephrotoxicity | Convert to sirolimus to preserve kidney function |
| Post-transplant malignancy | Sirolimus has antitumor activity; preferred over CNIs |
| CMV disease recurrence | Sirolimus has anti-CMV effect; sometimes preferred |
| Non-melanoma skin cancer | Switch to sirolimus to reduce new skin cancer rate |
⚠️ Why sirolimus is not routine first-line in modern kidney transplant:
- 📊 Tacrolimus consistently outperforms sirolimus in trials for de novo transplant
- 🩹 Wound healing concerns early post-operative
- 📈 Hyperlipidemia affects most sirolimus users
- 🫀 Proteinuria can develop over time
- 🏫 Rejection rates slightly higher than tacrolimus-based regimens
🎯 When sirolimus conversion becomes attractive:
- 🫀 CNI-related kidney damage — preserving remaining function
- 🏆 Development of skin cancer — antineoplastic effect
- 🏆 Post-transplant lymphoproliferative disease — some benefit
- 🦠 Recurrent CMV disease
- 🏫 Specific center experience — some programs favor earlier conversion
🎯 The CONVERT trial studied sirolimus conversion from cyclosporine in kidney transplant recipients. Results showed preserved kidney function in the sirolimus arm, with trade-offs including more side effects. This informed the current approach of selective rather than routine conversion.
📊 Modern kidney transplant regimen components:
- 💊 Induction — thymoglobulin or basiliximab at transplant
- 💊 Calcineurin inhibitor — tacrolimus (most common) or cyclosporine
- 💊 Antimetabolite — mycophenolate (standard) or azathioprine
- 💊 Corticosteroid — prednisolone, often tapered over months
- 💊 Sirolimus or everolimus — selected cases or specific protocols
🛡️ Monitoring during kidney transplant Rapacan use:
- 🧪 Sirolimus trough levels — weekly initially, then monthly, then every 3 months
- 🧪 Creatinine — kidney function surveillance
- 🧪 Protein in urine — detect sirolimus-related proteinuria
- 🧪 Lipid panel — manage hyperlipidemia
- 🧪 CBC and LFTs — standard immunosuppression monitoring
- 🏥 Transplant clinic every 1-3 months long-term
Kidney transplant immunosuppression with sirolimus requires specialized expertise. Transplant nephrologists coordinate the complex regimens, monitor outcomes, and adjust protocols based on individual patient response. Rapacan is one component of this sophisticated multi-drug approach that has transformed kidney transplantation into a routinely successful intervention.
🫀 Rapacan Calcineurin-Free Protocols for Kidney Function
Calcineurin-free protocols using sirolimus represent one of the most important modern applications of Rapacan in kidney transplantation. These regimens avoid the nephrotoxicity of calcineurin inhibitors (CNIs) by substituting sirolimus for tacrolimus or cyclosporine.
The approach is particularly valuable when CNI nephrotoxicity threatens kidney transplant function or when other CNI-related complications emerge.
🫀 Calcineurin-free sirolimus protocols use the drug's unique non-nephrotoxic profile to preserve kidney function. This is one of the clearest clinical niches for mTOR inhibitors in modern transplant medicine.
🤔 Why CNIs cause nephrotoxicity:
- 🫀 Direct kidney vascular damage — chronic vasoconstriction
- 🌀 Interstitial fibrosis — progressive scarring over years
- 📉 Tubular toxicity — damage to kidney tubule cells
- 📈 Cumulative effect — worsens with duration
- 🤔 Transplant paradox — drug that preserves transplant also damages it
| CNI vs mTOR inhibitor | Comparison |
|---|---|
| Nephrotoxicity | CNI: significant / mTOR inhibitor: minimal |
| Rejection prevention | CNI: superior / mTOR inhibitor: adequate |
| Diabetes risk | Tacrolimus: significant / sirolimus: less |
| Hyperlipidemia | Mild with CNIs / Marked with mTOR |
| Wound healing | Good with CNIs / Impaired with mTOR |
| Cancer risk | Higher with CNIs / Lower with mTOR |
⚠️ When calcineurin-free sirolimus protocols are considered:
- 🫀 Declining kidney function on CNI (rising creatinine)
- 🏆 Development of malignancy post-transplant (especially skin cancer)
- 🫀 Severe CNI toxicity symptoms — tremor, hypertension, hyperglycemia
- 🏫 Specific transplant center philosophy
- 🏆 Previous transplant complication on CNI-based regimen
🔄 Conversion protocol from CNI to sirolimus:
- 📊 Patient selection — stable graft function, low immunologic risk
- 🕚 Timing — typically after 3-6 months post-transplant minimum
- 🔄 Gradual conversion — sirolimus started, CNI tapered over weeks
- 🧪 Close level monitoring — both drugs during overlap
- 📈 Target sirolimus level — higher than when combined with CNI
- 🏥 Transplant specialist supervision throughout
🎯 The CONVERT trial 2009 studied conversion from cyclosporine to sirolimus in stable kidney transplant recipients. Results showed preserved kidney function in the sirolimus group over several years. Trade-offs included more hyperlipidemia and some side effects, but the kidney function benefit was substantial.
🎯 Side effects to manage in calcineurin-free protocols:
- 📈 Hyperlipidemia — often requires statins
- 🩸 Proteinuria — monitor and manage with ACE inhibitor/ARB
- 🤾 Mouth ulcers — dose-dependent
- 📈 Hypertension — manage with usual agents
- 🫁 Rare pneumonitis — monitor pulmonary symptoms
- 📉 Myelosuppression — CBC monitoring
🤔 Not all patients are good candidates for conversion:
- 🚫 High immunologic risk — higher rejection risk on sirolimus
- 🚫 Significant proteinuria at baseline
- 🚫 Severe hyperlipidemia not responsive to statins
- 🚫 Prior sirolimus intolerance
- 🚫 Recent surgery or wound
- 🚫 Pregnancy planning — sirolimus discouraged in pregnancy
Calcineurin-free protocols represent a sophisticated use of Rapacan's unique properties. The approach requires specialist supervision but offers meaningful kidney function preservation for appropriately selected transplant recipients. This is one of the clearest clinical niches where sirolimus provides distinct benefits that other immunosuppressants cannot match.
🫁 Rapacan for Lymphangioleiomyomatosis Rare Lung Disease
Lymphangioleiomyomatosis (LAM) is a rare lung disease that almost exclusively affects women of reproductive age. The disease causes progressive cystic lung destruction leading to respiratory failure. Sirolimus is the first and only FDA-approved therapy for LAM, following the landmark MILES trial.
Before sirolimus, LAM had no effective disease-modifying treatment. The medication has transformed LAM from a progressive terminal disease into a manageable chronic condition for many patients.
🫁 LAM is one of the clearest sirolimus success stories. The medication specifically targets the mTOR hyperactivation driving the disease. For most patients, sirolimus stabilizes or improves lung function that would otherwise decline relentlessly.
🫁 What LAM looks like clinically:
- 👩 Almost exclusively women — usually ages 20-40 at diagnosis
- 😮 Progressive shortness of breath — often misdiagnosed as asthma
- 🫁 Cystic lung disease on CT imaging
- 🤾 Pneumothorax (collapsed lung) — frequent complication
- 💧 Chylous effusions — lymphatic fluid in chest or abdomen
- 🧬 Renal angiomyolipomas — benign kidney tumors
- 🏃 Associated with TSC in some patients (TSC-LAM)
| LAM subtype | Context |
|---|---|
| Sporadic LAM | No TSC; most common form; women only typically |
| TSC-LAM | Occurs in women with tuberous sclerosis complex |
| Isolated LAM in men | Very rare; usually TSC-associated |
📊 The MILES trial 2011 (New England Journal of Medicine):
- 📑 Led by Prof. Francis McCormack at University of Cincinnati
- 📊 89 women with LAM randomized to sirolimus vs placebo
- 🟢 FEV1 stabilized or improved on sirolimus; declined on placebo
- 🟢 Quality of life improved in sirolimus group
- 🏆 Led to FDA approval 2015 — first drug ever approved for LAM
🎯 Standard LAM sirolimus protocol:
- 💊 Starting dose — 2 mg daily
- 🎯 Target trough level — 5-15 ng/mL
- ⏳ Response timeline — weeks to months
- 🕚 Duration — indefinite; benefits lost on discontinuation
- 🏥 Pulmonology specialist — LAM experienced
📊 What sirolimus does in LAM:
- 🛡️ Stabilizes FEV1 — prevents further decline
- 📈 May improve FEV1 modestly in some patients
- 📉 Reduces chylous effusion recurrence
- 🧬 Shrinks angiomyolipomas (renal tumors)
- 😮 Improves symptoms — breathing, exercise tolerance
- 🕚 Benefits require continued therapy — disease progresses if stopped
🎯 The LAM Foundation (Prof. McCormack is Scientific Director) provides patient support, research funding, and clinician education. International registries track long-term outcomes on sirolimus therapy, continuing to expand the evidence base for optimal management.
🫁 Multidisciplinary LAM care team:
- 👨⚕️ Pulmonologist — usually LAM-experienced
- 👨⚕️ Transplant pulmonologist — for severe disease
- 👨⚕️ Nephrologist — for angiomyolipomas
- 👨⚕️ Thoracic surgeon — recurrent pneumothorax management
- 👨⚕️ Genetic counselor — if TSC association
- 👨⚕️ Specialized nurse — coordination and education
🛡️ Monitoring during LAM sirolimus therapy:
- 🧪 Sirolimus trough levels — quarterly after stable
- 🫁 Pulmonary function tests — every 3-6 months
- 🏥 CT scans — periodic to assess cysts and angiomyolipomas
- 🧪 Standard labs — CBC, LFTs, lipids
- 🏥 Pulmonologist review every 3-6 months
LAM treatment with sirolimus is one of the most clearly beneficial applications in rare disease medicine. The combination of a devastating disease, no previous therapy, and a dramatically effective targeted treatment makes this one of the most important mTOR inhibitor indications in modern practice.
🧠 Rapacan in Tuberous Sclerosis Complex Treatment
Tuberous sclerosis complex (TSC) is a genetic disorder causing benign tumors in multiple organs including brain, kidneys, lungs, heart, and skin. The underlying cause is mutations in TSC1 or TSC2 genes, which normally suppress mTOR activity. Loss of TSC function means mTOR is constitutively active — the exact target of sirolimus.
This makes TSC one of the most mechanism-matched indications for sirolimus. The medication directly addresses the molecular pathology.
🧠 TSC mTOR hyperactivation drives tumor growth throughout the body. Sirolimus (and the related everolimus) inhibit this pathway, shrinking tumors and reducing complications. This is targeted therapy at its clearest.
🧠 Common TSC manifestations treated with mTOR inhibitors:
- 🧠 SEGA (subependymal giant cell astrocytoma) — brain tumor causing hydrocephalus
- 🫀 Renal angiomyolipomas — benign kidney tumors; bleeding risk
- 🫁 LAM — occurs in some adult women with TSC
- 🤾 Facial angiofibromas — characteristic skin lesions
- 🧠 Refractory epilepsy — some TSC-associated seizures
- ❤️ Cardiac rhabdomyomas — usually spontaneously regress
- 🧑 Cognitive and behavioral manifestations
| TSC manifestation | mTOR inhibitor role |
|---|---|
| SEGA | First-line therapy; everolimus FDA approved |
| Renal angiomyolipomas | Everolimus or sirolimus; shrinks tumors |
| LAM (in TSC) | Sirolimus standard |
| Refractory epilepsy | Everolimus approved; sirolimus studied |
| Angiofibromas | Topical sirolimus studied; oral less used |
📊 EXIST trials established mTOR inhibitors in TSC:
- 📑 EXIST-1 — everolimus for SEGA; sustained tumor response
- 📑 EXIST-2 — everolimus for renal angiomyolipomas
- 📑 EXIST-3 — everolimus for TSC-associated epilepsy
- 🎯 Everolimus is FDA-approved for these TSC indications
- 🤔 Sirolimus often used off-label with similar efficacy
🎯 Standard TSC sirolimus/mTOR inhibitor approach:
- 💊 Weight-based initial dosing
- 🎯 Target trough level — 5-15 ng/mL typical
- 👶 Pediatric protocols — distinct dosing in children
- 🕚 Duration — usually indefinite; tumors may regrow if stopped
- 🤝 Multidisciplinary TSC specialists
🎯 Prof. David Franz at Cincinnati Children's Hospital participated in EXIST trials and has shaped modern TSC care. His TSC clinic represents the integrated care model that combines genetics, neurology, nephrology, pulmonology, dermatology, and developmental medicine for comprehensive TSC management.
👶 Pediatric TSC considerations:
- 🏫 Diagnosis often in childhood — sometimes antenatal (cardiac rhabdomyomas)
- 🧠 Developmental monitoring — cognitive and behavioral
- ⚡ Early seizure control — critical for outcomes
- 💊 Growth monitoring on mTOR inhibitor therapy
- 🤝 Pediatric subspecialists — neurology, nephrology, cardiology
- 👨👩👦 Family support — genetic counseling, resources
🛡️ Monitoring during TSC sirolimus therapy:
- 🧪 Sirolimus trough levels — targeted to indication
- 🏥 Brain MRI — monitor SEGA response
- 🏥 Kidney imaging — angiomyolipomas size
- 🧪 Lipid panel — hyperlipidemia management
- 🧪 CBC and LFTs
- 👶 Growth charts in children
- 🏥 TSC-experienced specialist every 3-6 months
⚠️ Tumors typically regrow if sirolimus is discontinued. TSC manifestations are driven by underlying genetic mutation, not an acute process. Lifelong therapy is often needed to maintain tumor control, which the family and patient should understand from the outset.
Tuberous sclerosis complex represents one of the clearest mechanism-matched applications of mTOR inhibitor therapy. The combination of genetic understanding, targeted therapy, and multidisciplinary care has substantially improved outcomes for TSC patients across the age spectrum. Rapacan plays an essential role in this transformed approach.
🩸 Rapacan for Vascular Malformations Off-Label Use
Complex vascular anomalies represent an emerging off-label application for sirolimus. These rare conditions involve abnormal lymphatic, venous, or combined vascular tissue growth that can cause disfigurement, pain, bleeding, functional impairment, and life-threatening complications.
mTOR hyperactivation drives many of these malformations, making sirolimus a mechanism-targeted treatment option. The medication is used off-label but with growing evidence base in pediatric and adult practice.
🩸 Sirolimus for vascular anomalies is off-label but increasingly common in specialist practice. The medication shrinks or stabilizes malformations and reduces complications.
🩸 Vascular anomalies that may respond to sirolimus:
- 💧 Kaposiform hemangioendothelioma — aggressive vascular tumor
- 💧 Blue rubber bleb nevus syndrome — multiple venous malformations
- 💧 Complex lymphatic anomalies — generalized lymphatic anomaly, Gorham-Stout
- 💧 Lymphangiomatosis
- 💧 Venous malformations extensive or symptomatic
- 💧 Capillary-lymphatic-venous malformations (Klippel-Trenaunay)
- 💧 PIK3CA-related overgrowth syndromes
| Vascular anomaly type | Sirolimus role |
|---|---|
| Kaposiform hemangioendothelioma | Established therapy; shrinks lesions |
| Complex lymphatic anomalies | Reduces chylous leaks and bleeding |
| Venous malformations | Reduces pain, swelling, bleeding |
| PIK3CA overgrowth syndromes | Growing evidence; alpelisib also studied |
⚠️ Vascular anomaly care requires specialist expertise:
- 🏥 Multidisciplinary vascular anomaly centers — usually at academic hospitals
- 🤝 Combined medical and interventional care
- 👶 Pediatric and adult expertise
- 🏫 Research protocols often involved
- 🏥 Genetic testing may inform therapy choice
🎯 Standard sirolimus approach in vascular anomalies:
- 👶 Pediatric starting dose — 0.8 mg/m2 twice daily typical
- 👨 Adult starting dose — 2 mg daily
- 🎯 Target trough level — 5-15 ng/mL
- ⏳ Response timeline — weeks to months
- 🕚 Duration — often prolonged; tapering attempts possible
📊 What sirolimus can achieve in vascular anomalies:
- 📉 Lesion size reduction — shrinks tumor volume
- 🤚 Pain reduction
- 🩸 Reduced bleeding episodes
- 💧 Reduced chylous leaks in lymphatic anomalies
- 📈 Functional improvement
- 🏃 Return to normal activities for many patients
- ✂️ May avoid or delay surgery
🎯 Specialty vascular anomaly centers at institutions like Boston Children's Hospital, Great Ormond Street London, and other academic centers have pioneered sirolimus use for these conditions. Published case series and prospective trials continue to expand the evidence base and refine protocols.
👶 Pediatric vascular anomaly considerations:
- 👶 Many present in infancy or childhood
- 🏫 Growth and development monitoring
- 🦻 Cosmetic and functional impact
- 👨👩👦 Family support essential
- 🏫 School and social considerations
- 🔄 Long-term follow-up through adolescence
🛡️ Monitoring during vascular anomaly sirolimus:
- 🧪 Sirolimus trough levels
- 🏥 Imaging — MRI typically; monitor lesion response
- 🧪 Standard labs — CBC, LFTs, lipids
- 🤝 Multidisciplinary clinic — dermatology, hematology, surgery, radiology
- 👶 Growth monitoring in children
Vascular anomalies represent an active research frontier for sirolimus. The combination of mechanism-matched therapy (mTOR hyperactivation in affected tissue) and multidisciplinary specialist care has transformed outcomes for patients with these rare and often debilitating conditions. Rapacan continues to be used off-label with growing success in appropriately selected patients.
❤️ Rapacan Drug-Eluting Coronary Stents Historical Role
Drug-eluting coronary stents represent one of sirolimus' most impactful but less publicly recognized applications. The first commercially successful drug-eluting stent (Cypher, approved 2003) used sirolimus to prevent restenosis — the renarrowing of coronary arteries that limited bare-metal stent success.
This application involves local delivery of sirolimus from the stent itself rather than systemic oral therapy, but the underlying mechanism (mTOR inhibition of vascular smooth muscle proliferation) is the same.
❤️ Sirolimus revolutionized interventional cardiology when the Cypher stent demonstrated dramatic reduction in restenosis compared to bare-metal stents. Modern drug-eluting stents remain central to percutaneous coronary intervention worldwide.
❤️ How drug-eluting stents work:
- 🏗️ Metal scaffold props open the artery after angioplasty
- 💊 Drug coating on stent surface
- 🌊 Drug slowly released locally over weeks to months
- 🚫 Blocks smooth muscle proliferation that causes restenosis
- 🏥 Patency maintained at the stent site long-term
| Stent era | Restenosis rate |
|---|---|
| Pre-stent (balloon only) | ~40% |
| Bare-metal stents | ~20-30% |
| First-gen drug-eluting (sirolimus Cypher) | ~5-10% |
| Second/third-gen drug-eluting | Under 5% |
📊 The clinical impact of sirolimus-eluting stents:
- 🟢 Reduced repeat intervention for restenosis
- 🟢 Expanded indications for percutaneous intervention
- 🟢 Reduced coronary bypass surgery — many patients now stented instead
- 🟢 Transformed interventional cardiology
🤔 How this is different from oral Rapacan:
- 🌀 Local delivery only — sirolimus coats stent surface
- 🚫 Minimal systemic exposure — no systemic side effects
- 🌊 Slow release over months
- 🤔 Different clinical considerations — dual antiplatelet therapy rather than immunosuppression monitoring
- 🏥 Interventional cardiologist rather than transplant specialist
📊 Modern drug-eluting stents have evolved from the original sirolimus-coated Cypher to include:
- 🏆 Everolimus-eluting — Xience, Promus (most widely used today)
- 🏆 Zotarolimus-eluting — Resolute, Endeavor
- 🏆 Biodegradable polymer stents — delivery technology improved
- 🏆 Biolimus and other analogs
🎯 The drug-eluting stent story illustrates how a single compound (sirolimus) found therapeutic application through completely different delivery routes. The oral Rapacan tablets for transplant and LAM, and the sirolimus coating on coronary stents, both work through mTOR inhibition of unwanted cell proliferation — just in very different clinical contexts.
📋 Important considerations for stent recipients:
- 💊 Dual antiplatelet therapy — aspirin + clopidogrel/prasugrel/ticagrelor
- 📅 Duration — typically 6-12 months, varies by stent type
- ⚠️ Stent thrombosis risk if dual antiplatelet stopped prematurely
- ✂️ Surgery planning around stent timing
- 🏥 Cardiology follow-up long-term
🤔 Note for patients taking oral Rapacan separately:
- 🤔 Having a sirolimus-eluting stent does not change oral Rapacan dosing
- 🤔 Systemic exposure from stent is negligible compared to oral therapy
- 🤝 Communicate between cardiology and prescribing specialist
The drug-eluting stent story is one of modern medicine's success stories, with sirolimus playing a foundational role. For readers of this Rapacan guide, the stent application mainly serves as context for the broader significance of mTOR inhibitor therapy — a compound discovered in Easter Island soil ultimately touching the lives of millions of patients through diverse clinical applications.
⚖️ Sirolimus vs Tacrolimus Transplant Immunosuppression Choice
Sirolimus vs tacrolimus is a fundamental comparison in transplant immunosuppression. Both are powerful immunosuppressants, both are routinely used, but they work through different mechanisms, have different side effect profiles, and fit different clinical niches.
Tacrolimus (a calcineurin inhibitor) dominates modern kidney transplant protocols. Sirolimus (an mTOR inhibitor) is used in specific situations where its distinct properties provide advantages.
⚖️ Tacrolimus wins for routine new transplants. Sirolimus wins for CNI nephrotoxicity, skin cancer prevention, and specific scenarios where its mechanism matters.
| Factor | Sirolimus (Rapacan) | Tacrolimus |
|---|---|---|
| Mechanism | mTOR inhibitor | Calcineurin inhibitor |
| Nephrotoxicity | Minimal | Significant long-term |
| Rejection prevention | Adequate | Superior in trials |
| Diabetes risk | Lower | Higher |
| Hyperlipidemia | Marked | Mild |
| Hypertension | Can occur | Significant |
| Wound healing | Impaired | Normal |
| Skin cancer risk | Lower | Higher |
| Mouth ulcers | Common | Rare |
| Pneumonitis | Specific risk | Not typical |
| Proteinuria | Can develop | Rare directly |
🎯 Tacrolimus advantages for most new transplants:
- 🟢 Better acute rejection prevention in trials
- 🏆 Modern tacrolimus doses are lower than historical — less toxicity
- 🤝 Combines well with mycophenolate and prednisolone
- 🩹 Better wound healing early post-operative
- 📊 Extensive outcome data over 30 years
🎯 When sirolimus is preferred over tacrolimus:
- 🫀 CNI nephrotoxicity — declining kidney function
- 🏆 Post-transplant skin cancer — multiple SCCs on CNI
- 🏆 Post-transplant lymphoproliferative disease (PTLD)
- 🦠 Recurrent CMV
- 🩸 CNI-induced diabetes — sometimes converts
- 🤚 CNI tremor or neurotoxicity intolerable
🎯 When tacrolimus is preferred over sirolimus:
- 🩹 Early post-transplant (wound healing)
- 👶 Pregnancy planning
- 📈 Severe hyperlipidemia not controllable
- 🫀 Baseline proteinuria
- 🇬 Lung transplant recipient — pneumonitis risk
- 🏫 Rejection history — higher immunologic risk
🎯 Prof. Dirk Kuypers and the European transplant community have published extensively on CNI vs mTOR inhibitor strategies. The modern approach is individualized: tacrolimus for most new transplants, with selective conversion to sirolimus based on specific clinical triggers.
🔄 Combined use of both drugs:
- 📊 Low-dose tacrolimus + sirolimus — CNI minimization strategy
- 🧪 Interaction — sirolimus levels affected by concurrent cyclosporine or tacrolimus
- 🎯 Specific protocols use both to reduce individual drug burden
- 🏥 Specialist supervision essential for combined regimens
The sirolimus vs tacrolimus comparison illustrates the sophisticated individualized nature of modern transplant care. Neither drug is universally better; each has clinical niches where it excels. Transplant teams tailor regimens to individual patient factors, graft characteristics, and emerging complications over time.
⚖️ Sirolimus vs Everolimus mTOR Inhibitor Comparison
Sirolimus and everolimus are the two main mTOR inhibitors in clinical use. Everolimus is a derivative of sirolimus with different pharmacokinetics but the same core mechanism. The clinical choice between them involves half-life, specific approved indications, and prescriber familiarity.
⚖️ Sirolimus and everolimus share the same mechanism (mTOR inhibition) but differ in half-life, dosing schedule, and specific regulatory approvals. In many clinical scenarios they are interchangeable; in others one is clearly preferred.
| Factor | Sirolimus (Rapacan, Rapamune) | Everolimus (Zortress, Afinitor, Votubia) |
|---|---|---|
| Half-life | ~62 hours | ~30 hours |
| Dosing frequency | Once daily | Twice daily |
| Steady state time | 5-7 days | 3-4 days |
| Kidney transplant approval | FDA 1999 | FDA 2010 (Zortress) |
| Liver transplant approval | Not FDA approved | FDA 2013 |
| LAM approval | FDA 2015 | Not FDA approved (off-label) |
| TSC approvals | Not FDA approved (off-label) | SEGA, AML, epilepsy approved |
| Cancer indications | Limited | Multiple (RCC, breast, NET) |
🎯 Side effect profile is similar for both:
- 📈 Hyperlipidemia — both drugs
- 🩹 Impaired wound healing — both drugs
- 👄 Mouth ulcers — both drugs
- 🫁 Pneumonitis — both drugs
- 🫀 Proteinuria — both drugs
- 📊 Myelosuppression — both drugs
🎯 When sirolimus is typically preferred:
- 🫁 LAM — approved indication; MILES trial evidence
- 👶 Pediatric vascular anomalies — more experience base
- 🕚 Once-daily dosing preferred — adherence advantage
- 💰 Cost — generic sirolimus (like Rapacan) widely available
🎯 When everolimus is typically preferred:
- 🧠 TSC manifestations — multiple FDA approvals
- 🏫 Specific transplant indications — liver, heart
- 🏫 Oncology — multiple cancer indications
- 🛑 Faster washout needed — shorter half-life
🎯 Converting between the two drugs is done when FDA approval status, pharmacokinetic requirements, or specific clinical factors change. Approximate dose conversion: everolimus 0.75-1 mg twice daily is roughly equivalent to sirolimus 1-2 mg once daily, but blood level monitoring guides the actual conversion.
🤔 Shared cautions for both drugs:
- 🍅 Avoid grapefruit — same CYP3A4 interaction
- 💊 Azole antifungals — raise levels of both
- 💊 Rifampin, phenytoin — lower levels of both
- 🧪 Trough level monitoring — essential for both
- 🏥 Pneumonitis vigilance — required for both
- 🩹 Wound healing concerns — same for both
📊 Research applications:
- 🕚 Longevity research — both studied in aging models
- 🧬 Rare disease applications — expanding for both
- 🏆 Combination with other targeted therapies — cancer research
The sirolimus vs everolimus choice usually comes down to specific indication, FDA approval status for that use, and prescriber familiarity. For patients who need an mTOR inhibitor, the clinical effect is similar regardless of which specific drug is chosen. Blood level monitoring guides either therapy.
⏰ Rapacan Response Timeline and Steady State
Rapacan response develops at different rates depending on the indication and clinical measurement. The long half-life (~62 hours) means pharmacokinetic steady state takes about 5-7 days after any dose change. Clinical effects on the target condition develop over weeks to months.
⏰ Rapacan response has two components: pharmacokinetic steady state (days) and clinical response (weeks to months). Both matter for prescribing decisions.
⏰ Pharmacokinetic timeline:
- 🕚 Peak level after single dose — 1-3 hours
- 🕚 Half-life — approximately 62 hours (very long)
- 🕚 Steady state blood level — 5-7 days of consistent daily dosing
- 🕚 Blood level after dose change — new steady state in 5-7 days
- 🕚 Washout after discontinuation — weeks for complete elimination
| Indication | Clinical response timeline |
|---|---|
| Kidney transplant maintenance | Immediate immunosuppression once at target level |
| Lymphangioleiomyomatosis | FEV1 stabilization over months; angiomyolipoma shrinkage over 6-12 months |
| Tuberous sclerosis SEGA | Tumor shrinkage over 3-12 months |
| Vascular anomalies | Symptom improvement in weeks; size reduction over months |
| Side effect development | Hyperlipidemia within weeks; others develop over months |
⚠️ The long half-life has practical implications:
- 🕚 Loading dose often used to reach target faster
- 🕚 Dose adjustments take 5-7 days to reflect in blood levels
- 🕚 First level check at 5-7 days after any change
- 🕚 Missed single dose less impactful than for shorter half-life drugs
- 🕚 Washout for pregnancy or surgery takes weeks
⏰ Monitoring timeline during Rapacan initiation:
- 📅 Day 0 — baseline labs, loading dose considered
- 📅 Day 5-7 — first trough level, dose adjustment if needed
- 📅 Week 2 — recheck level if dose adjusted
- 📅 Weeks 2-4 — weekly to biweekly monitoring
- 📅 Month 1-3 — biweekly to monthly
- 📅 Month 3+ — monthly to quarterly as stable
- 📅 Long-term stable — every 3-6 months
🎯 What to expect in the first weeks:
- 🕚 Blood level rising to target
- 😢 Some side effects may develop — mouth ulcers, GI upset
- 📈 Lipid rises start
- 📉 CBC changes may begin
- 🏥 Frequent appointments — monitoring intensive
- 🤝 Clinical response not yet visible
🎯 In LAM specifically, clinical benefit from sirolimus takes months to become clearly visible. The MILES trial measured response at 12 months. Patients who continue therapy consistently through this period typically experience stabilization of lung function that would otherwise decline. Expectations should be set at the start.
🤔 Long-term expectations:
- 🕚 Treatment is typically indefinite for most indications
- 🔄 Benefits lost on discontinuation — disease often progresses
- 🏥 Lifelong monitoring required
- 🗓️ Annual specialist review at minimum
- 🔄 Dose adjustments over time based on levels and response
🤔 When to consider dose modification:
- 📊 Blood level out of target range
- 🩹 Side effects emerging or worsening
- 🔄 Disease progression despite therapy
- 💊 Interacting medication added or stopped
- 🫀 Kidney function changes
Understanding the sirolimus response timeline helps patients set realistic expectations and maintain adherence during the extended period before clinical benefits become visible. The combination of patient patience, prescriber monitoring, and sustained therapy produces the best long-term outcomes across all indications where Rapacan is used.
🩸 Blood Level Monitoring During Rapacan Therapy
Blood level monitoring is the central safety and efficacy discipline in Rapacan therapy. Unlike most oral medications given at fixed doses, sirolimus has a narrow therapeutic index — the range between effective and toxic levels is small, and individual pharmacokinetics vary substantially.
Routine trough level measurement guides dose adjustments to keep patients in the therapeutic range for their specific indication.
🩸 Trough level monitoring is non-negotiable for Rapacan therapy. Levels guide dosing. Dose adjustments wait for level results. Patients without level monitoring are not getting safe sirolimus therapy.
🧪 How sirolimus levels are measured:
- 🕐 Trough level — drawn immediately before next dose
- 🕚 Timing matters — 24 hours after last dose for once-daily dosing
- 🧪 LC-MS/MS assay — gold standard laboratory method
- 🏥 Specialized labs — not all hospital labs offer; may need send-out
- 📊 Reported in ng/mL
| Indication | Target trough range |
|---|---|
| Kidney transplant + cyclosporine | 4-12 ng/mL |
| Kidney transplant CNI-free | 12-20 ng/mL |
| Lymphangioleiomyomatosis | 5-15 ng/mL |
| Tuberous sclerosis complex | 5-15 ng/mL |
| Vascular anomalies | 5-15 ng/mL |
⚠️ Factors that change sirolimus levels:
- 💊 Dose change — obvious direct effect
- 🍅 Grapefruit juice — raises levels significantly
- 💊 Azole antifungals — ketoconazole, voriconazole raise levels
- 💊 Macrolide antibiotics — raise levels
- 💊 Rifampin, phenytoin — lower levels
- 🏷️ Brand change — different formulations can produce small differences
- 🍽️ Food timing — consistent timing matters
- 🫀 Liver dysfunction — may raise levels
🕚 Monitoring schedule during Rapacan therapy:
- 📅 Days 5-7 — first trough level after starting
- 📅 Week 2 — after dose adjustment
- 📅 Weeks 2-4 — weekly during stabilization
- 📅 Months 1-3 — biweekly to monthly
- 📅 Stable long-term — every 3 months typically
- 🔄 Any new interaction — recheck within 1-2 weeks
- 🏥 Illness — consider recheck if clinical course changes
🧪 Other labs monitored alongside trough levels:
- 🧪 CBC — myelosuppression surveillance
- 🧪 Lipid panel — nearly universal hyperlipidemia
- 🧪 LFTs — monitor hepatic function
- 🫀 Creatinine — kidney function
- 🩸 Urinalysis / spot protein — proteinuria detection
- 🧪 Fasting glucose, HbA1c — diabetes monitoring
🎯 Patients should know: hold your morning dose until after the blood draw when a trough level is being measured. Taking the dose before the draw will give a falsely high reading and lead to incorrect dose reduction.
🤔 What to do if level is out of range:
- 📉 High level — dose reduction; investigate interactions
- 📈 Low level — dose increase; investigate adherence and interactions
- 🤔 Unexpectedly variable — check draw timing, adherence, interactions
- 📱 Communicate with prescriber — before independently adjusting
📋 Patient tips for accurate monitoring:
- 🕚 Consistent dose timing daily
- 🍅 Avoid grapefruit consistently
- 📋 Keep medication log if timing varies
- 🏥 Arrive early for appointments so draw happens before next dose
- 📱 Ask about results at each visit
- 🤝 Communicate with pharmacy about brand consistency
Blood level monitoring is the operational backbone of safe Rapacan therapy. The combination of trough measurements, dose adjustments, and attention to interactions produces consistent therapeutic exposure that balances efficacy with toxicity. Patients who understand their role in accurate monitoring contribute meaningfully to safe long-term therapy.
🩹 Side Effects From Oral Rapacan Therapy
Rapacan has a distinctive side effect profile that reflects mTOR's broad biological roles. Many side effects are predictable, dose-related, and manageable with monitoring and intervention. Others require specific vigilance because of their clinical significance.
🩹 Rapacan side effects by category
- Hyperlipidemia
- Mouth ulcers / stomatitis
- Peripheral edema
- Acne
- Hypertension
- Impaired wound healing
- Proteinuria
- Thrombocytopenia
- Anemia
- Diarrhea
- Pneumonitis / ILD
- Hepatic artery thrombosis (liver transplant)
- Hyperglycemia / diabetes
- Opportunistic infections
- Severe pneumonitis
- Angioedema
- Thrombotic microangiopathy
- Severe infections
- Malignancy risk
🤔 Early side effects (first weeks):
- 😢 Mouth ulcers — often appear in first weeks
- 📈 Lipid rise — detectable within weeks
- 💧 Lower limb edema — may develop early
- 😢 Acne-like skin eruption
- 😢 GI upset
🤔 Later side effects (months to years):
- 📈 Progressive proteinuria
- 🫁 Possible pneumonitis
- 🏆 Non-melanoma skin cancer less than CNIs but still present
- 🦠 Chronic infections — opportunistic
- 🌞 Photosensitivity
- 🤾 Chronic cytopenias may persist
| Side effect | Reversible? | Dose-related? |
|---|---|---|
| Hyperlipidemia | Yes on stopping | Yes |
| Mouth ulcers | Yes | Yes |
| Proteinuria | Variable | Yes |
| Pneumonitis | Usually yes | Not strictly |
| Wound healing impairment | Yes on holding | Yes |
| Myelosuppression | Yes | Yes |
🚨 Stop and seek urgent medical review if:
- 🫁 New shortness of breath or dry cough — possible pneumonitis
- 🌡️ Fever with respiratory symptoms
- 🏥 Severe infection signs
- 🤾 Significant bleeding
- 😮 Facial swelling or difficulty breathing — angioedema
- 💧 Rapidly worsening edema
🎯 Risk minimization strategies:
- 📉 Lowest effective dose consistent with target levels
- 🧪 Routine lab monitoring — CBC, LFTs, lipids, proteinuria
- 💊 Lipid management — often need statins
- ☀️ Sun protection — skin cancer risk persists
- 💉 Vaccinations — before starting
- 🏥 Infection vigilance
- ✂️ Perioperative planning — may need to hold around surgery
The dedicated sections that follow cover specific major side effects (hyperlipidemia, impaired wound healing, mouth ulcers, pneumonitis, proteinuria, myelosuppression, infection, edema) and their management in detail. Understanding each helps patients and prescribers use Rapacan safely over the long term.
📈 Hyperlipidemia Elevated Cholesterol on Rapacan
Hyperlipidemia (elevated blood lipids) is the most common and clinically significant side effect of Rapacan. It affects the majority of patients within weeks of starting therapy. The elevation includes both total cholesterol and triglycerides, with particularly marked triglyceride rises.
Most patients on Rapacan require statin therapy and sometimes additional agents to manage sirolimus-induced hyperlipidemia.
📈 Expect hyperlipidemia on Rapacan. Nearly all patients develop it. Lipid management becomes part of standard sirolimus care. Statins are frequently needed.
🧬 Why Rapacan raises lipids:
- 🧪 mTOR regulates lipid metabolism
- 🌀 Increased hepatic lipogenesis
- 🌀 Impaired lipoprotein lipase activity
- 🌀 Reduced lipid clearance
- 📈 Combined effect raises total cholesterol, LDL, triglycerides
| Lipid parameter | Typical Rapacan effect |
|---|---|
| Total cholesterol | Rises 20-50% |
| LDL | Rises significantly |
| Triglycerides | Rises most dramatically; sometimes doubles |
| HDL | Variable; may rise or fall |
⚠️ Severe hypertriglyceridemia risks:
- 🩸 Pancreatitis — above 1000 mg/dL
- ❤️ Cardiovascular events long-term
- 🏥 Urgent management if triglycerides very high
- 💊 Fibrates often added
- 🏃 Lifestyle intervention intensified
🎯 Management of Rapacan-induced hyperlipidemia:
- 💊 Statin therapy — usually atorvastatin or rosuvastatin
- 💊 Fibrates — for high triglycerides; fenofibrate commonly
- 💊 Omega-3 fatty acids — EPA/DHA adjunct
- 💊 Ezetimibe — add-on when statin alone insufficient
- 🥕 Diet modification — low saturated fat, limited refined carbs
- 🏃 Exercise — raises HDL, lowers triglycerides
- 🚬 Weight management
💊 Statin-sirolimus combination: most statins are compatible with Rapacan. Simvastatin and lovastatin have the strongest interaction concern (potential myopathy) and are usually avoided. Atorvastatin, rosuvastatin, pravastatin are preferred for sirolimus patients.
🛡️ Lipid monitoring schedule:
- 📅 Baseline — before starting Rapacan
- 📅 Month 1 — first check
- 📅 Month 3 — assess effect
- 📅 Every 3-6 months — long-term maintenance
- 🔄 After any dose change — may affect levels
- 🔄 After starting statin — recheck in 4-6 weeks
🎯 Treatment targets:
- 🎯 LDL — follow general cardiovascular risk-based targets
- 🎯 Triglycerides — under 500 mg/dL at minimum; ideally lower
- 🎯 Non-HDL cholesterol — often tracked in transplant recipients
- 🎯 Risk-based intensity — higher-risk patients to lower targets
⚠️ Statin side effects to monitor: muscle aches (myalgia), weakness, elevated liver enzymes, rare rhabdomyolysis. Report any new muscle pain promptly, especially combined with Rapacan which can also affect muscle in rare cases.
🤔 Lifestyle approaches that help:
- 🥕 Mediterranean-style diet — olive oil, fish, vegetables, nuts
- 🚫 Reduce refined carbohydrates and sugars
- 🚫 Reduce saturated fat and trans fats
- 🏃 Regular aerobic exercise — 150+ minutes weekly
- 💪 Resistance training — supports muscle health
- ⚖️ Weight management
- 🚫 Alcohol moderation
Hyperlipidemia is nearly universal on Rapacan but highly manageable with structured intervention. The combination of statin therapy, lifestyle modification, and routine monitoring prevents lipid-related complications while allowing continued mTOR inhibitor benefit. This is one of the clearest examples of a predictable side effect that becomes a routine part of chronic therapy management.
🩹 Impaired Wound Healing on Rapacan Perioperative
Impaired wound healing is a mechanism-based side effect of Rapacan. mTOR inhibition slows the cell proliferation needed for tissue repair, delaying wound closure and increasing complications. This creates specific challenges around surgery and procedures during sirolimus therapy.
Perioperative management of sirolimus is a crucial aspect of safe care that patients and surgical teams must address together.
🩹 Wound healing on Rapacan: critical perioperative consideration
- 🕚 Hold Rapacan before elective surgery when possible
- 🕚 Resume after wound healing established
- 🤝 Surgeon awareness essential — mention Rapacan
- 🔄 Communication between prescribing specialist and surgeon
🧬 How Rapacan impairs wound healing:
- 🚫 Blocks fibroblast proliferation — cells needed for wound closure
- 🌀 Reduces epithelial cell proliferation
- 🛡️ Suppresses angiogenesis — new blood vessel formation
- 📉 Slows collagen synthesis
- 📉 Delays wound contraction
| Procedure type | Rapacan management |
|---|---|
| Elective major surgery | Hold 2-4 weeks before; resume after healing |
| Minor skin procedures | Case-by-case; often continue |
| Dental procedures | Continue for routine; discuss for extractions |
| Emergency surgery | Cannot hold; manage wound closely post-op |
| Transplant surgery | Historically hold until wound healed; now variable protocols |
🚨 Wound complications more frequent on Rapacan:
- 🩸 Wound dehiscence — opening along closure line
- 🩸 Delayed closure
- 🩸 Wound infections — immunosuppression plus delayed healing
- 🩸 Lymphoceles — particularly after transplant
- 🩸 Hernias — abdominal wall
- 🩸 Poor cosmetic outcomes
🎯 Perioperative Rapacan management guidelines:
- 📅 2-4 weeks before elective surgery — hold Rapacan if clinically feasible
- 🔄 Convert to alternative immunosuppression during perioperative period
- ✂️ Surgery with wound closure
- 📅 Resume Rapacan after wound well-healed — typically 2-4 weeks post-op
- 🧪 Check trough level after resuming
🎯 Transplant surgery decisions: some centers now use sirolimus-based regimens in kidney transplant immediately post-operative, finding manageable wound complication rates. Other centers continue to hold sirolimus until weeks post-transplant. The approach varies by institutional experience and specific patient factors.
🤔 Factors that worsen Rapacan wound healing effects:
- 💊 Combined with corticosteroids
- 📈 Higher sirolimus doses
- 🫀 Diabetes mellitus
- 🚬 Smoking
- 🥕 Malnutrition
- 🚬 Alcohol excess
- 👴 Advanced age
🎯 Communication responsibilities:
- 🏥 Patient — mention Rapacan to any surgeon or dentist
- 🏥 Primary prescriber — coordinate with surgical team
- ✂️ Surgeon — aware of mTOR inhibitor presence
- 👨⚕️ Anesthesiologist — medication list review
- 🤝 Multidisciplinary planning for major procedures
⚠️ Minor procedures still need discussion. Dental extractions, skin biopsies, mole removals, podiatric procedures — all may heal more slowly. Discuss with the prescribing specialist and the operator before scheduling. Many minor procedures can proceed on Rapacan with awareness and careful technique.
Wound healing considerations illustrate how Rapacan's mechanism affects normal physiology. The medication cannot distinguish between unwanted cell proliferation (its therapeutic target) and necessary cell proliferation (wound repair). Perioperative management requires coordination between prescribing specialist and surgical team to balance disease control with surgical outcomes.
👄 Mouth Ulcers Stomatitis From Rapacan
Mouth ulcers (aphthous stomatitis) are one of the most common and recognizable Rapacan side effects. They typically appear in the first weeks of therapy, can be painful enough to interfere with eating, and often improve with dose adjustment or local management.
Severity ranges from mild occasional single ulcers to extensive painful aphthous disease that significantly impacts quality of life.
👄 Mouth ulcers on Rapacan are expected for many patients but can be managed. They usually improve with local treatment, dose adjustment, or occasionally dose timing changes.
🧬 Why Rapacan causes mouth ulcers:
- 🧪 mTOR regulates rapidly dividing cells
- 👄 Oral mucosa cells turn over quickly
- 🚫 mTOR inhibition disrupts normal mucosal maintenance
- 📉 Reduced epithelial regeneration
- 🤾 Ulcer formation at points of minor trauma
| Severity | Management |
|---|---|
| Mild occasional ulcers | Local care; often tolerable |
| Recurrent multiple ulcers | Topical corticosteroids; consider dose reduction |
| Severe interfering with eating | Reduce dose; intensive topical therapy |
| Extensive mucositis | Hold Rapacan; refer to oral medicine |
🛡️ Topical treatments for Rapacan mouth ulcers:
- 💊 Topical corticosteroids — triamcinolone paste (Orabase), dexamethasone mouth rinse
- 💊 Lidocaine solution or gel — pain relief before meals
- 💊 Chlorhexidine mouthwash — reduces secondary infection
- 💊 Sodium bicarbonate rinse — gentle pH balance
- 🧴 Avoid alcohol-based mouthwashes — irritating
- 🚫 Avoid acidic, spicy, salty foods during active ulcers
🎯 Local comfort measures:
- 🍽️ Soft diet during flares
- 🥵 Avoid temperature extremes
- 🧈 Cold or room temperature foods — easier to tolerate
- 👶 Infant formulas or soft nutrition if severe
- 🧽 Soft toothbrush
- 🚫 Avoid smoking — delays healing
- 🍩 Yogurt, honey — some patients find soothing
🤔 Dose adjustment considerations:
- 📊 If level toward high end of range — reduce dose
- 📊 If level in therapeutic range — discuss trade-off
- 🔄 Split dosing may help some patients
- 🕚 Timing changes — some benefit from bedtime dosing
- 🤝 Discuss with prescriber — before independent adjustment
⚠️ When mouth ulcers suggest something else: ulcers with coating that look infected, large single lesions that do not heal, ulcers with associated fever or systemic symptoms, lesions that persist beyond 2 weeks. These warrant oral medicine or dental evaluation to rule out other causes.
🤔 Interventions for severe recurrent mucositis:
- 💊 Dexamethasone elixir swish-and-spit
- 💊 Clobetasol topical gel for severe lesions
- 💊 Thalidomide — off-label for refractory cases
- 💊 Colchicine — sometimes used
- 🔄 Rapacan dose reduction or hold
- 🔄 Switch to alternative — if severe and non-responsive
🎯 Prevention strategies:
- 🧽 Good oral hygiene
- 🏥 Dental care — address issues before they become painful
- 🚫 Avoid oral trauma — sharp foods, aggressive brushing
- 🚬 Smoking cessation
- 🥕 Nutritional support — B vitamins, iron, zinc if deficient
- 🏥 Dental cleaning schedule — especially for chronic users
Mouth ulcers are among the most quality-of-life-impacting Rapacan side effects. The combination of topical management, dose adjustment when needed, and preventive oral care allows most patients to continue therapy comfortably. Severe cases require specialist input and sometimes alternative therapy decisions, but these are the minority of users.
🫁 Pneumonitis Interstitial Lung Risk From Rapacan
Pneumonitis (interstitial lung disease) is one of the most serious Rapacan side effects. It is relatively uncommon but potentially severe, requiring prompt recognition and intervention. Sirolimus pneumonitis can present as subacute shortness of breath with cough, often misattributed to infection initially.
Patients and prescribers must be alert for respiratory symptoms during Rapacan therapy and have a low threshold for pulmonary evaluation.
🚨 Rapacan pneumonitis — critical to recognize
- 🫁 New shortness of breath or dry cough — evaluate promptly
- 🌡️ May include low-grade fever
- 🏥 CT chest typically needed
- 🔄 Usually requires holding Rapacan
- 📈 Can be severe and life-threatening if unrecognized
🫁 Clinical presentation:
- 😮 Progressive dyspnea — often over weeks
- 🤧 Dry cough — typically non-productive
- 🌡️ Fatigue
- 🌡️ Low-grade fever may occur
- 😫 Exercise intolerance
- 📉 Oxygen saturation falls on exertion
- 🫁 Bilateral infiltrates on imaging
| Severity | Approach |
|---|---|
| Mild (asymptomatic imaging finding) | Monitor; consider dose reduction |
| Moderate (symptomatic) | Hold Rapacan; corticosteroid consideration |
| Severe (hypoxemia) | Stop Rapacan; high-dose steroids; hospital evaluation |
| Respiratory failure | ICU; definitely stop sirolimus permanently |
⚠️ Diagnostic workup for suspected pneumonitis:
- 🏥 High-resolution CT chest — characteristic patterns
- 🫁 Pulmonary function tests — restrictive pattern typical
- 🧪 Rule out infection — especially PCP, atypical pneumonia
- 🏥 Bronchoscopy with BAL — some cases
- 🏥 Lung biopsy — rarely needed; distinctive pattern on tissue
🎯 Risk factors for sirolimus pneumonitis:
- 📈 Higher sirolimus levels
- 🫀 Pre-existing lung disease
- 🫁 Lung transplant recipients — higher risk
- 🚬 Smoking history
- 🏫 Combined with other pulmonary toxins
- 👴 Older age
🔄 Management approach:
- 🛑 Hold Rapacan — essential first step
- 💊 Oral prednisolone — typically 0.5-1 mg/kg daily
- 🏥 Oxygen support if needed
- 🧪 Infection workup — usually rule out before steroids
- 🔄 Slow steroid taper over weeks to months
- 🔄 Rechallenge decision — individualized
🎯 Rechallenge after pneumonitis: if mild and clear resolution, some patients can resume at lower dose with close monitoring. If severe pneumonitis, permanent avoidance of sirolimus is usually recommended — and often of everolimus too given shared mechanism. Alternative immunosuppression is substituted.
🎯 Baseline pulmonary assessment:
- 🫁 Pre-treatment chest imaging
- 🫁 Baseline pulmonary function tests — for comparison
- 🧑⚕️ Pulmonologist awareness if existing lung disease
- 🏥 Smoking cessation support
- 💉 Pneumococcal and flu vaccination
🤔 Differential diagnosis of lung problems on Rapacan:
- 🦠 Opportunistic infection — PCP, CMV, aspergillus
- 🦠 Routine pneumonia
- 🤥 Heart failure
- 🫁 Pulmonary embolism
- 🏆 Underlying LAM progression if LAM patient
- 🤥 Other drug-induced lung injury
Sirolimus pneumonitis is uncommon but requires high clinical suspicion. The combination of patient awareness of respiratory symptoms, prompt medical evaluation, and specialist pulmonary assessment prevents serious outcomes. Clear communication about new breathing symptoms during therapy is one of the most important safety behaviors for Rapacan users.
🫀 Proteinuria Kidney Effects on Rapacan Therapy
Proteinuria (protein in urine) is a common side effect of long-term Rapacan therapy. It develops over months to years and reflects altered glomerular permeability. Monitoring urine protein is essential for all Rapacan users, particularly those on prolonged therapy.
Mild proteinuria usually requires monitoring only. Significant proteinuria may need intervention including ACE inhibitors, dose reduction, or occasionally discontinuation.
🫀 Proteinuria on Rapacan develops in a substantial fraction of long-term users. Routine screening with urine protein-to-creatinine ratio or spot urine protein catches it early for appropriate management.
🧬 How Rapacan causes proteinuria:
- 🧪 Alters glomerular filtration barrier
- 🌀 Reduces podocyte function — filtration cells in glomerulus
- 📈 Increases glomerular permeability
- 📈 Protein leaks through filter into urine
- ⏳ Develops gradually over months
| Proteinuria level | Clinical significance |
|---|---|
| Under 0.3 g/day | Normal; monitor |
| 0.3-1 g/day | Mild; start ACE inhibitor if appropriate |
| 1-3 g/day | Moderate; consider dose reduction |
| Over 3 g/day (nephrotic) | Significant; often discontinue Rapacan |
⚠️ Monitoring schedule for proteinuria:
- 🧪 Baseline — before starting Rapacan
- 🧪 Month 3 — first follow-up check
- 🧪 Every 3-6 months — ongoing surveillance
- 🧪 Spot urine protein-to-creatinine ratio — convenient test
- 🧪 24-hour urine collection — gold standard quantification
🎯 Management of Rapacan proteinuria:
- 💊 ACE inhibitor or ARB — reduces proteinuria
- 💓 Blood pressure control — essential
- 📉 Rapacan dose reduction if proteinuria significant
- 🔄 Consider conversion to alternative if proteinuria persists
- 🫀 Nephrology input for significant proteinuria
- 🧂 Sodium restriction — supports BP and proteinuria control
🎯 ACE inhibitors (like lisinopril, ramipril) or ARBs (like losartan, valsartan) are mainstays of proteinuria management. They work by reducing glomerular pressure and have been shown to slow progression of proteinuric kidney disease. Starting one of these agents at moderate proteinuria is standard practice.
🎯 Factors that worsen Rapacan proteinuria:
- 💓 Uncontrolled hypertension
- 🫀 Baseline kidney disease
- 🫀 Diabetes
- 📈 Higher Rapacan levels
- 🕚 Longer duration of therapy
- 📈 Pre-existing proteinuria at baseline
🤔 When to consider Rapacan discontinuation for proteinuria:
- 📈 Nephrotic range proteinuria (over 3 g/day)
- 📈 Rapidly progressing proteinuria
- 🫀 Declining kidney function alongside proteinuria
- 🚫 Inadequate response to ACE inhibitor/ARB
- 🤔 Alternative immunosuppression available and acceptable
⚠️ Proteinuria is a specific transplant concern. In kidney transplant recipients, new or worsening proteinuria on sirolimus may indicate rejection, recurrent native kidney disease, or sirolimus toxicity itself. Workup with nephrology input is essential rather than attributing all proteinuria to Rapacan reflexively.
🤝 Patient role in proteinuria management:
- 📋 Attend monitoring appointments
- 🚽 Provide urine samples as requested
- 💓 Monitor and report BP
- 🥕 Low-sodium diet if hypertensive
- 🚬 Avoid smoking
- 🤝 Communicate changes — new leg swelling, foamy urine
Proteinuria is a common and manageable Rapacan side effect in the hands of attentive clinicians. The combination of routine monitoring, timely ACE inhibitor/ARB therapy, blood pressure control, and dose adjustment when needed preserves kidney function in most patients. Specialist nephrology input guides decisions in more challenging cases.
📊 Myelosuppression Low Blood Counts From Rapacan
Myelosuppression (reduced blood cell production) is a predictable Rapacan side effect reflecting mTOR's role in bone marrow proliferation. The medication can cause thrombocytopenia (low platelets), anemia (low red cells), and leukopenia (low white cells) — often in that order of frequency.
Most cases are mild and dose-related, allowing continued therapy with monitoring. Severe cases require dose reduction or discontinuation.
📊 Blood count monitoring is routine on Rapacan — part of the standard immunosuppression lab surveillance. Mild cytopenias are expected and managed through dose adjustment.
🧬 How Rapacan affects blood cell production:
- 🚫 Blocks hematopoietic cell proliferation in bone marrow
- 📉 Affects megakaryocytes — platelet precursors most sensitive
- 📉 Reduces erythropoiesis — anemia development
- 📉 Can lower neutrophils — less consistent
- ⏳ Dose and level dependent
| Blood count finding | Approach |
|---|---|
| Normal | Continue; monitoring per schedule |
| Mild thrombocytopenia (100-150k) | Monitor; usually continue |
| Moderate thrombocytopenia (75-100k) | Consider dose reduction; recheck |
| Severe thrombocytopenia (under 50k) | Hold Rapacan; investigate |
| Significant anemia | Investigate causes; iron, B12, folate |
| Severe neutropenia | Hold; consider growth factor; infection risk |
⚠️ CBC monitoring schedule on Rapacan:
- 📅 Baseline — before starting
- 📅 Weeks 1-4 — weekly
- 📅 Months 1-3 — every 2-4 weeks
- 📅 Months 3-6 — monthly
- 📅 Stable long-term — every 3 months
- 🔄 After any dose change — recheck within 1-2 weeks
🎯 Management of myelosuppression:
- 📉 Dose reduction — first intervention for moderate cases
- 🔄 Hold temporarily for severe or symptomatic cytopenias
- 🧪 Investigate other causes — infection, nutritional deficiency, bone marrow
- 💉 G-CSF (filgrastim) — severe neutropenia
- 💉 Erythropoietin — chronic anemia if indicated
- 💉 Platelet transfusion — severe thrombocytopenia with bleeding
🤔 Other causes to consider alongside Rapacan:
- 🦠 Viral infections — parvovirus, CMV, EBV
- 💊 Other medications — mycophenolate, ganciclovir, trimethoprim
- 🥕 Nutritional deficiencies — iron, B12, folate
- 🫀 Kidney disease — erythropoietin deficiency
- 🏫 Underlying disease — some conditions cause cytopenias independently
🎯 In kidney transplant recipients: cytopenias on Rapacan are often multifactorial. CMV, mycophenolate, trimethoprim prophylaxis, and sirolimus all contribute. Workup looks at all possible causes rather than attributing to Rapacan alone.
🚫 Warning signs patients should report:
- 🤾 Unexplained bruising or bleeding
- 😫 Severe fatigue with pallor
- 🌡️ Fever (ANC may be low)
- 🤾 Petechiae — small red spots on skin
- 🦟 Mouth bleeding
- 🧼 Blood in urine or stool
🚨 Severe myelosuppression concerns:
- 🌡️ Febrile neutropenia — medical emergency; immediate antibiotics
- 🤾 Severe thrombocytopenia with bleeding — may need transfusion
- 😫 Severe anemia — may need transfusion
- 🏥 Hematology consultation for persistent severe cases
🔄 Rechallenge after resolution:
- 📉 Reduce dose on resumption
- 🧪 Close monitoring — weekly CBC initially
- 🎯 Lower target trough level if feasible
- 🔄 Alternative immunosuppression if cytopenias recur
Myelosuppression on Rapacan is predictable and well-managed through routine monitoring. The combination of CBC surveillance, prompt dose adjustment when needed, and investigation of contributing causes allows continued therapy for most patients while preventing serious complications.
🦠 Infection Risk from Rapacan Immunosuppression
Rapacan is an immunosuppressant and thus increases infection risk. Both routine and opportunistic infections are more frequent and potentially more severe. Risk depends on dose, duration, combined immunosuppression, and underlying patient factors.
Infection management is a core discipline during Rapacan therapy, with pre-treatment vaccination, routine vigilance, and prompt evaluation of symptoms as cornerstones.
🦠 Infection risk on Rapacan is real but manageable through pre-treatment vaccination, careful monitoring, and prompt medical evaluation of any infection symptoms.
🎯 Common infection types on Rapacan:
- 🥵 Bacterial — pneumonia, UTI, skin infections more common
- 🥵 Viral reactivation — CMV, herpes zoster, EBV, HSV
- 🥵 Opportunistic — PCP, aspergillus, nocardia at higher doses
- 🥵 Fungal — thrush, candidiasis commonly
- 🥵 Hepatitis B reactivation — in chronic carriers
- 🥵 HPV-related — warts, dysplasia
- 🥵 BK virus — particular transplant concern
| Scenario | Infection risk level |
|---|---|
| Rapacan monotherapy | 🟡 Modest increase |
| Rapacan + CNI (kidney transplant) | 🟠 Significant |
| Rapacan + mycophenolate + steroid | 🔴 Multi-drug combined immunosuppression |
| LAM or TSC on sirolimus alone | 🟡 Modest; mainly surveillance |
🛡️ Prevention strategies before starting Rapacan:
- 💉 Vaccinations — influenza, pneumococcal, HBV, zoster (Shingrix), COVID
- 🧪 Screen for latent TB — TST or IGRA
- 🧪 Hepatitis B screening — prophylaxis if positive
- 🧪 HIV screening if risk factors
- 🚫 Avoid live vaccines during therapy
- 🏥 Early medical attention for infection symptoms
🦼 Prophylactic therapy for specific infections (especially transplant):
- 💊 Pneumocystis prophylaxis — trimethoprim-sulfamethoxazole
- 💊 CMV prophylaxis — valganciclovir in high-risk recipients
- 💊 HSV prophylaxis — acyclovir in some protocols
- 💊 Antifungal prophylaxis — selected high-risk patients
- 💊 HBV prophylaxis — tenofovir or entecavir in carriers
🚨 Clinical signs of infection to escalate on:
- 🌡️ Fever over 38 C — even if source unclear
- 🤧 Productive cough or shortness of breath
- 🤿 Burning urination, flank pain
- 🤩 Severe sore throat
- 😵 Confusion — especially elderly
- 🤕 Severe headache with neck stiffness
- 🤾 Spreading cellulitis or wound infection
- 🤾 Shingles rash
🚨 Herpes zoster is a specific Rapacan concern:
- 🎯 Reactivation risk doubled or more
- 🤾 Can be severe or disseminated
- 💉 Shingrix vaccine protects effectively (and is non-live)
- 🏥 Antiviral treatment if reactivation
- 🛑 Postherpetic neuralgia can be prolonged
🤔 Specific infections requiring attention:
- 🦠 CMV disease — fever, cytopenia, GI, retinitis
- 🦠 BK virus nephropathy — transplant-specific; monitor viremia
- 🦠 EBV-driven PTLD — post-transplant lymphoproliferative disorder
- 🦠 Pneumocystis jirovecii — opportunistic pneumonia
- 🦠 Nocardia — brain abscess, pneumonia
- 🦠 Listeria — from unpasteurized foods, deli meats
🏥 Food safety considerations:
- 🚫 Unpasteurized dairy — listeria risk
- 🚫 Soft cheeses — listeria risk
- 🚫 Raw sprouts — salmonella, E coli
- 🚫 Rare meat — toxoplasma
- 🚫 Unwashed produce
- ✅ Normal food hygiene otherwise
Infection management on Rapacan is a well-worn clinical discipline. The combination of pre-treatment vaccination, prophylactic antimicrobials for specific infections (especially in transplant), food safety awareness, and prompt medical evaluation of symptoms produces safe long-term therapy for most patients.
💧 Edema Lower Limb Swelling on Rapacan
Peripheral edema (lower limb swelling) is a common Rapacan side effect. It typically affects the ankles and lower legs, worsens with prolonged standing or sitting, and improves with elevation. The mechanism involves lymphatic drainage impairment through mTOR-dependent effects.
💧 Lower limb edema on Rapacan affects many patients. It is usually mild to moderate but can be bothersome. Simple measures help most patients continue therapy comfortably.
🧬 Why Rapacan causes edema:
- 🌀 Impaired lymphatic drainage — mTOR regulates lymphatic function
- 🚫 Reduced lymphangiogenesis — new lymphatic vessel formation
- 🌀 Capillary leak — sometimes contributes
- 📈 Dose-related effect for many patients
- 🕐 Can persist or evolve over months
| Edema severity | Management |
|---|---|
| Mild ankle swelling | Elevation, compression stockings |
| Moderate lower leg edema | Compression, lifestyle, possibly diuretic |
| Significant edema with symptoms | Diuretic trial; dose reduction consider |
| Severe lymphedema | Specialist referral; consider discontinuation |
🛡️ Non-pharmacologic management:
- 🧶 Elevation — raise legs when sitting
- 🧦 Compression stockings — graduated 20-30 mmHg typical
- 🏃 Regular movement — walking pumps lymphatics
- 🧂 Reduce dietary sodium — worsens fluid retention
- 🛌 Elevate foot of bed for nighttime drainage
- 👕 Avoid tight clothing on legs
- 🏊 Swimming or water aerobics — natural compression
🎯 Pharmacologic management:
- 💊 Furosemide or torsemide — loop diuretics; monitor K+
- 💊 Spironolactone — aldosterone antagonist; K+-sparing
- 💊 Thiazide diuretic — mild cases
- 🧪 Monitor potassium and renal function on diuretics
- 📉 Dose reduction if severe
⚠️ Rule out other edema causes:
- 💓 Heart failure — check brain natriuretic peptide if symptoms
- 🫀 Kidney disease — proteinuria, declining function
- 🫀 Liver disease — cirrhosis
- 🦠 Deep vein thrombosis — especially if unilateral acute
- 🌀 Lymphatic obstruction — cancer, surgery
- 💊 Other medications — calcium channel blockers, steroids
🚨 When edema warrants urgent evaluation:
- 😮 Sudden swelling with difficulty breathing — pulmonary edema or anaphylaxis
- 😤 Unilateral painful swelling — DVT concern
- 🤾 Skin changes — redness, warmth, drainage
- 📈 Rapid weight gain — several kg in days
- 🫁 Shortness of breath
- 😫 Facial swelling — angioedema concern
🎯 Lymphedema vs other edema:
- 💧 Rapacan edema — usually symmetric, lower limbs, improves with elevation
- 💧 Heart failure — symmetric; may have shortness of breath
- 💧 DVT — unilateral, acute, painful
- 💧 Lymphedema (true) — harder, doesn't pit, often starts dorsal foot
- 💧 Venous insufficiency — chronic, skin changes
🎯 Edema improves on dose reduction for many patients. If quality of life significantly affected and clinical situation allows, lowering sirolimus dose by small increments can substantially reduce swelling while maintaining therapeutic effect. Discuss with the prescribing specialist.
🤝 Daily life adaptations:
- 🚶 Walking breaks during prolonged sitting
- 🏃 Calf exercises while seated
- 🧦 Put on compression stockings before getting out of bed
- 🤷 Avoid crossed legs
- 🛌 Elevate feet during the day
- 🧴 Skin care — moisturize to prevent cracks
Lower limb edema is one of the most consistent Rapacan side effects. The combination of compression, elevation, lifestyle adjustment, and sometimes diuretics or dose reduction allows most patients to manage symptoms while continuing effective therapy. Significant lymphedema requires specialist input and sometimes alternative therapy decisions.
🔗 Rapacan Drug Interactions and CYP3A4 Pathway
Rapacan has numerous clinically significant drug interactions because sirolimus is metabolized through CYP3A4 and transported by P-glycoprotein. Both pathways are affected by many common medications, substantially altering sirolimus blood levels.
Every prescription or OTC medication added or stopped during Rapacan therapy warrants review for potential interaction.
🔗 Rapacan drug interactions are extensive. Patients should mention sirolimus at every medical encounter and before starting any new medication. Pharmacists are a valuable resource for interaction checking.
🔗 Interactions by category
- Ketoconazole, voriconazole, itraconazole
- Erythromycin, clarithromycin
- Protease inhibitors (ritonavir)
- Diltiazem, verapamil (modest)
- Grapefruit juice
- Rifampin, rifabutin
- Phenytoin, phenobarbital
- Carbamazepine
- St. John's wort
- Efavirenz, nevirapine
- Cyclosporine (raises levels; use 4-hour separation)
- ACE inhibitor + sirolimus (angioedema risk)
- Other immunosuppressants
- Nephrotoxic drugs
- Most statins (not simvastatin/lovastatin)
- Most antihypertensives
- SSRI antidepressants
- Levothyroxine
- PPIs
🤔 CYP3A4 inhibitors to avoid or manage carefully:
- 🛑 Azole antifungals — especially ketoconazole, voriconazole
- 🛑 Macrolide antibiotics — erythromycin, clarithromycin
- 🛑 Protease inhibitors — HIV medications
- ⚠️ Non-dihydropyridine CCBs — diltiazem, verapamil (modest)
- 🍅 Grapefruit juice — dedicated section follows
🚨 Specific dangerous combinations:
- 💊 Voriconazole + sirolimus — sirolimus levels rise 10-fold; usually avoid combination
- 💊 Ritonavir + sirolimus — marked level rise
- 💊 Rifampin + sirolimus — levels crash; usually ineffective
- 💊 St. John's wort + sirolimus — levels drop; often not recognized
🤔 Managing necessary interacting medications:
- 📊 Check level before adding — baseline
- 📉 Pre-emptive dose reduction if adding strong inhibitor
- 📈 Pre-emptive dose increase if adding strong inducer
- 🧪 Recheck level in 1-2 weeks after addition
- 🔄 Adjust iteratively based on levels
- 🤝 Specialist consultation for complex scenarios
🎯 Statin considerations:
- ✅ Atorvastatin, rosuvastatin, pravastatin — preferred
- 🚨 Simvastatin, lovastatin — myopathy risk; avoid
- ⚠️ Monitor for myalgia on any statin + Rapacan
- 🧪 CK level if muscle pain develops
🎯 ACE inhibitor and ARB caution with sirolimus: rare but serious cases of angioedema reported with combination. Routine use continues when needed for proteinuria or blood pressure, but patients should be aware of this rare interaction and seek immediate care for any facial swelling or breathing difficulty.
🤔 OTC and supplement considerations:
- 🍅 Grapefruit, Seville oranges, pomelos — avoid
- 🌿 St. John's wort — avoid
- 🍅 Pomegranate juice — variable; discuss
- 🍀 Herbal supplements generally — discuss before use
- 🍀 Echinacea, licorice — variable interactions reported
- 🍀 Chamomile — usually compatible but check
🤝 Patient responsibilities:
- 📋 Keep medication list current and shared with all providers
- 🤝 Tell every provider about Rapacan
- 🤝 Ask pharmacist about potential interactions
- 🚫 Do not start new OTCs or supplements without checking
- 📋 Report dietary changes affecting food intake patterns
Rapacan drug interactions require active management rather than one-time learning. The combination of patient awareness, pharmacist consultation, prescriber coordination, and blood level monitoring during medication changes allows safe long-term therapy despite the extensive interaction profile.
🍊 Grapefruit Juice Dangerous With Rapacan Levels
Grapefruit juice is contraindicated during Rapacan therapy. This common dietary item contains compounds that strongly inhibit CYP3A4 in the gut wall, raising sirolimus levels substantially and unpredictably. The interaction has caused serious toxicity and is one of the most important dietary rules in sirolimus care.
🍅 THE GRAPEFRUIT RULE
Avoid completely during Rapacan therapy:
- 🍅 Grapefruit (whole fruit, segments)
- 🥤 Grapefruit juice — even small amounts
- 🍊 Seville oranges (bitter oranges) — same effect
- 🍊 Pomelos — grapefruit relative
- 🍊 Grapefruit-containing marmalades or products
🧬 Why grapefruit affects Rapacan:
- 🍅 Furanocoumarins in grapefruit inhibit CYP3A4
- 🌀 Gut wall CYP3A4 normally reduces sirolimus absorption
- 🚫 Inhibition means more sirolimus absorbed intact
- 📈 Blood levels rise 2-5 fold or more
- ⏳ Effect lasts 24-72 hours after single grapefruit exposure
| Scenario | Sirolimus level change |
|---|---|
| Single glass of grapefruit juice | Can double levels for 1-3 days |
| Half grapefruit daily | Sustained 2-5x level elevation |
| Grapefruit occasionally over weeks | Unpredictable fluctuations |
| Grapefruit extract supplements | Same effect; equally dangerous |
⚠️ Clinical consequences of grapefruit-raised sirolimus:
- 🩹 Increased side effects — mouth ulcers worsen, more edema
- 📊 Severe myelosuppression
- 🫁 Pneumonitis risk increased
- 🫀 Proteinuria worsens
- 🦠 Infection susceptibility increases
- 📈 Lipid rises further
✅ Fruits that are safe with Rapacan:
- 🍎 Apples, pears
- 🍌 Bananas
- 🍇 Grapes (not grapefruit)
- 🍓 Berries — strawberries, blueberries, raspberries
- 🍒 Cherries, plums, peaches
- 🍉 Melons, watermelons
- 🍊 Regular sweet oranges — not Seville
- 🍋 Lemons, limes
- 🥥 Avocados
- 🥭 Mangoes, kiwi, pineapple
🍅 If grapefruit was consumed by accident: contact the prescribing specialist. A single exposure may raise levels for a few days. Depending on circumstances, next dose may be held or reduced temporarily, and a trough level check may be advised to confirm return to therapeutic range.
🤔 Other foods and supplements that affect sirolimus levels:
- 🍅 Pomegranate juice — mild inhibitor; discuss
- 🍇 Starfruit — some interaction
- 🌿 St. John's wort — CYP3A4 inducer; lowers levels
- 🍀 Echinacea — variable
- 🍀 Licorice (large amounts) — can affect metabolism
- 🍀 Milk thistle — usually compatible but variable
🤝 Patient education on grapefruit avoidance:
- 📋 Learn to read labels — grapefruit in beverages, cocktails
- 🥄 Watch for grapefruit in juice blends
- 🍸 Alcoholic drinks — some cocktails contain grapefruit
- 🥕 Vitamin and supplement labels — grapefruit extract exists
- 🏪 Ask at restaurants about fruit components if unclear
- 🤝 Family and household awareness
🎯 This is a lifelong rule for anyone on Rapacan or similar CYP3A4-metabolized medications. The interaction is predictable and dangerous. The restriction is one of the simplest and most effective safety behaviors for mTOR inhibitor patients.
Grapefruit avoidance illustrates how dietary components can seriously affect medication safety. The restriction is simple to follow once learned, and the alternative fruits available are abundant. Patients who maintain consistent avoidance protect themselves from one of the most predictable toxicity risks of Rapacan therapy.
🤰 Rapacan Pregnancy Breastfeeding Safety Considerations
Rapacan is generally avoided during pregnancy because of concerns about fetal effects, including embryotoxicity in animal studies and limited human data showing fetal growth restriction. The medication is considered a relative contraindication in pregnancy, with specific scenarios requiring individualized decisions.
Breastfeeding during Rapacan use is also generally discouraged due to limited data on infant exposure.
🤰 Pregnancy on Rapacan requires careful planning. For most patients, discontinuing or switching before conception is preferred. For some scenarios (critical transplant maintenance), continuation with careful monitoring may be necessary.
🧬 Why Rapacan is problematic in pregnancy:
- 🧬 Animal studies show embryotoxicity and skeletal abnormalities
- 👶 Limited human data — mostly transplant case series
- 👶 Reported outcomes — low birth weight, prematurity
- 🚫 mTOR critical for fetal development — cell growth and tissue formation
- ⏳ Long half-life — washout takes weeks
| Scenario | Typical approach |
|---|---|
| Planning pregnancy on Rapacan | Switch to alternative before conception |
| LAM patient wanting pregnancy | Difficult decision; disease vs drug risk |
| Kidney transplant on Rapacan planning pregnancy | Convert to azathioprine before conception |
| Accidental pregnancy on Rapacan | Stop immediately; obstetric and specialist review |
| Male partner on Rapacan | Pregnancy outcomes appear acceptable; continue |
🛑 Pre-conception considerations:
- 📅 Washout before conception — at least 12 weeks for complete elimination
- 🔄 Alternative immunosuppression — azathioprine most common conversion
- 🤝 Multidisciplinary planning — obstetrics, transplant, pulmonology etc
- 📈 Disease stability — important before conception
- 👶 Family planning — reliable contraception during Rapacan
🎯 LAM pregnancy challenges:
- 🫁 LAM typically affects women of reproductive age
- 🫁 Pregnancy can worsen LAM — estrogen stimulates abnormal cells
- 👶 Stopping sirolimus during pregnancy may allow disease progression
- 👩 Family planning discussion essential at LAM diagnosis
- 🤝 Specialist LAM-obstetric collaboration required
🎯 Kidney transplant pregnancy:
- 🫀 Pregnancy possible after kidney transplant but requires planning
- 🔄 Switch from sirolimus to azathioprine at least 12 weeks before conception
- 🔄 Switch mycophenolate if present (teratogenic)
- 📈 Tacrolimus continues through pregnancy
- 📈 Low-dose prednisolone continues
- 🤝 Multidisciplinary transplant-obstetric team
🎯 The alternative immunosuppressant comparison for pregnancy:
- ✅ Azathioprine — compatible with pregnancy; standard for transplant
- ✅ Tacrolimus — compatible with pregnancy; continues
- ✅ Low-dose prednisolone — compatible
- 🛑 Mycophenolate — teratogenic; stop
- 🛑 Sirolimus/everolimus — discouraged; stop
🤱 Breastfeeding considerations:
- 🚫 Generally discouraged during Rapacan
- 👶 Infant exposure unknown — limited data
- 👶 Potential infant immunosuppression
- 👴 Case-by-case discussion for mothers on sirolimus
- 👶 Alternative therapy may be preferred during nursing period
👶 If accidental pregnancy on Rapacan:
- 🛑 Stop Rapacan immediately
- 🤝 Contact prescribing specialist and obstetrician urgently
- 🔄 Alternative therapy arranged quickly
- 🏥 Enhanced prenatal monitoring — ultrasound surveillance
- 👶 Pediatric follow-up after delivery
- 🤷 Counseling about outcomes based on gestational timing
Pregnancy planning on Rapacan requires forward thinking well before conception. The combination of mandatory washout period, alternative immunosuppression arrangement, multidisciplinary care coordination, and realistic risk-benefit discussion produces the best outcomes for both mother and future child.
🍷 Alcohol Interaction and Lifestyle on Rapacan
Rapacan and alcohol have no direct pharmacologic interaction, but combined use raises several lifestyle and health considerations. Moderate drinking is generally compatible with therapy, but heavy drinking creates compounded risk for hyperlipidemia, hepatotoxicity, and immune suppression.
🍷 Moderate drinking during Rapacan is generally acceptable for most patients. Heavy drinking is discouraged. Patients with specific scenarios may need stricter limits.
🤔 Why alcohol matters on Rapacan:
- 📈 Alcohol raises triglycerides — compounds sirolimus hyperlipidemia
- 🫀 Both affect liver — occasional LFT monitoring complicated
- 🦠 Heavy drinking impairs immunity — adds to Rapacan immunosuppression
- 📈 Can worsen edema
- 🦓 Interacts with judgment — medication adherence
| Drinking pattern | Rapacan impact |
|---|---|
| Occasional social | 🟢 No specific concern |
| Moderate daily | 🟡 Monitor lipids and LFTs |
| Heavy regular | 🟠 Compounded risks |
| Binge drinking | 🔴 Discouraged; metabolic stress |
⚠️ Specific concerns with alcohol on Rapacan:
- 📈 Alcohol-induced hypertriglyceridemia on top of sirolimus-induced
- 🫀 LFT abnormalities harder to attribute
- 🦠 Infection risk compounded in heavy drinkers
- 📈 Weight gain from calories
- 🛌 Sleep disruption affecting adherence
- 💧 Hydration status
🎯 Alcohol guidelines for Rapacan users:
- 🍸 Men — up to 2 standard drinks daily; not every day
- 🍷 Women — up to 1 standard drink daily; not every day
- 🧴 Alcohol-free days each week ideal
- 🚫 Avoid binge drinking
- 🚫 Avoid grapefruit-containing cocktails (critical)
🛑 Alcohol strictly limited or avoided:
- 🛑 Liver transplant recipients — alcohol usually completely avoided
- 🛑 Significant hypertriglyceridemia — alcohol worsens
- 🛑 Prior pancreatitis
- 🛑 Chronic hepatitis
- 🛑 LFT abnormalities on current monitoring
- 🛑 Alcohol dependence history
🏃 Lifestyle factors that matter on Rapacan:
- 🚬 Smoking cessation — cancer, infection, wound healing all affected
- 🥕 Nutrition — especially cardiovascular and bone health
- 🏃 Regular exercise — supports lipid management and overall health
- 🛌 Adequate sleep — immune function
- ☀️ Sun protection — skin cancer prevention
- 🧴 Dental hygiene — mouth ulcer prevention
- 🏥 Stress management
🎯 For most Rapacan users: moderate drinking is compatible with safe therapy. Heavy drinking creates compounded risks across lipid, hepatic, and immune domains. Open discussion with the prescribing specialist helps calibrate individual limits based on specific clinical factors.
🛡️ Lifestyle counseling priorities on Rapacan:
- 📈 Mediterranean-style diet — supports lipid management
- 🥕 Reduced saturated fat and refined carbs
- 🥕 Reduced sodium — helps edema
- 🚫 Grapefruit absolutely avoided
- ☀️ Daily sun protection
- 🏃 Regular exercise — walking especially helpful
- 🧴 Oral hygiene emphasis
Alcohol considerations on Rapacan focus on compound effects rather than direct drug interaction. Moderate drinking fits most patients' therapy without specific concern. The combination of overall healthy lifestyle, grapefruit avoidance, structured monitoring, and medication adherence produces the best long-term outcomes during what is often multi-year sirolimus therapy.
💉 Vaccinations During Rapacan Live Vaccine Rules
Vaccination management during Rapacan therapy follows the general immunosuppressant principle: inactivated vaccines are safe and recommended; live vaccines are contraindicated. Pre-treatment vaccination before starting therapy is strongly preferred when circumstances allow.
💉 Vaccination approach: complete needed vaccinations before starting Rapacan when feasible. Continue inactivated vaccines (annual flu, COVID, pneumococcal) during therapy. Avoid live vaccines until Rapacan stopped.
💉 Vaccines compatible with Rapacan:
- ✅ Inactivated influenza — annually
- ✅ Pneumococcal — PCV13/15/20 and PPSV23
- ✅ Hepatitis B
- ✅ Hepatitis A
- ✅ COVID-19 — routine updates
- ✅ Tetanus-diphtheria-pertussis
- ✅ HPV vaccine
- ✅ Shingrix (recombinant zoster)
- ✅ Meningococcal
- ✅ Inactivated typhoid Vi
🚫 Live vaccines contraindicated during Rapacan:
- 🚫 MMR (measles, mumps, rubella)
- 🚫 Varicella (chickenpox)
- 🚫 Zostavax (live zoster) — use Shingrix instead
- 🚫 Yellow fever
- 🚫 BCG
- 🚫 Oral polio
- 🚫 Oral typhoid Ty21a — use inactivated Vi instead
- 🚫 Rotavirus (in infants of mothers on Rapacan)
- 🚫 Nasal spray flu (LAIV) — use inactivated injection
| Timing scenario | Approach |
|---|---|
| Planning to start Rapacan | Complete vaccinations 2-4 weeks before starting |
| Live vaccines pre-Rapacan | Give at least 4 weeks before Rapacan start |
| On stable Rapacan | Continue inactivated vaccines routinely |
| Travel to endemic area | Pre-travel consultation; alternatives if live vaccines needed |
| After stopping Rapacan | Wait 1-3 months before live vaccines (longer washout given long half-life) |
💉 Priority vaccines before Rapacan start:
- 💉 Shingrix (if 50+ or at risk) — important before immunosuppression
- 💉 Pneumococcal — prevents severe pneumonia
- 💉 Annual influenza
- 💉 HPV — appropriate age groups
- 💉 Hepatitis B — if not immune
- 💉 MMR — if non-immune, before starting
- 💉 Varicella — if non-immune, before starting
- 💉 COVID-19 — up to date
🤔 Vaccine response on Rapacan:
- 📊 Response may be reduced but usually adequate
- 📊 Pneumococcal and influenza antibody titers lower
- 📊 COVID vaccines may need booster schedules
- 📈 Still worthwhile — partial protection better than none
🌍 Travel considerations:
- 🚫 Yellow fever areas — cannot be vaccinated; consider alternate itinerary
- 🚫 Typhoid-endemic travel — use Vi inactivated, not oral Ty21a
- 💊 Malaria prophylaxis — usual choices compatible
- 🧪 Pre-travel consultation — for extended trips to developing countries
- 🏥 Travel medicine specialist if complex itinerary
Vaccination strategy during Rapacan requires planning and coordination between specialists. Complete the vaccination panel before starting if possible. Maintain routine inactivated vaccines throughout therapy. Avoid live vaccines until medically supervised cessation. This structured approach substantially reduces vaccine-preventable infections during the extended period of mTOR inhibitor therapy.
🕚 Missed Rapacan Doses Impact on Levels
Missed Rapacan doses are usually not critically significant for occasional lapses because of the long half-life (~62 hours). A single missed dose causes only a modest drop in blood level. However, repeated or extended gaps can allow sirolimus levels to fall below therapeutic range with disease consequences.
🕚 Rapacan missed doses are forgiving for occasional lapses because of the long half-life. Chronic adherence problems matter more than individual missed doses.
| Missed pattern | What to do | Impact |
|---|---|---|
| Within 12 hours of usual time | Take when remembered | 🟢 None |
| Close to next dose | Skip, continue schedule | 🟢 None |
| Several over a week | Resume daily schedule | 🟢 Minimal |
| Full week off | Resume; check level | 🟡 Modest drop |
| 2-4 weeks off | Contact prescriber | 🟠 Significant subtherapeutic |
| Months off | Medical review before restart | 🔴 Essentially restarting |
🛑 Never double a dose to make up for a missed one. The long half-life means extra drug stays in the system; doubling can cause acute toxicity.
✈️ Travel considerations:
- 🧳 Pack extra supply — buffer against delays
- 🛄 Carry in original packaging — pharmacy label
- 🌍 Time zone adjustment — minor shifts fine
- 🔐 Store at room temperature, protected from light
- 📋 Immunosuppressant card for international travel
📋 Adherence strategies:
- 🪥 Pair with routine — morning coffee, breakfast, teeth brushing
- ⏰ Phone alarm — daily reminder
- 📱 Habit tracking app
- 🎒 Weekly pill organizer
- 🤝 Family reminder
- 📅 Automated refill — never run out
🤔 If a significant gap occurs: contact prescriber. For transplant recipients, extended gaps risk rejection. For LAM, disease may progress. For TSC, tumors may regrow. The response varies by indication but all warrant medical input.
🎯 Reasons patients miss Rapacan:
- 🕚 Simple forgetting
- 🤒 Side effects — may lead to deliberate skipping
- 💰 Cost or supply issues
- 🏥 Hospitalization — ensure team continues
- 😢 Feeling better — disease may be stable because of medication
- 🤔 Confusion about regimen
🧪 Monitoring after missed doses:
- 🧪 Check level if gap over a week
- 🧪 Baseline labs after extended gap
- 🏥 Clinical assessment of disease status
- 🔄 Dose adjustment if needed on restart
Rapacan adherence is a long-term discipline reflecting the chronic nature of indications treated. Occasional missed doses are forgiven by the long half-life. Chronic lapses undermine therapeutic benefit over time. Simple adherence strategies prevent most problems during the years of therapy that mTOR inhibitor indications typically require.
🔄 Rapacan Discontinuation When and How Safely
Rapacan discontinuation is a complex decision depending on indication, disease stability, and alternative therapy availability. For most indications, discontinuation leads to disease recurrence or progression because sirolimus suppresses rather than cures the underlying problem.
🔄 Stopping Rapacan typically means the underlying condition will return or progress. Discontinuation decisions require specialist supervision and clear transition plans.
🎯 Reasons to consider Rapacan discontinuation:
- 🩹 Serious side effects — pneumonitis, severe myelosuppression, extensive proteinuria
- 🛑 Pregnancy or pregnancy planning
- ✂️ Elective surgery — temporary hold for wound healing
- 🏆 New malignancy — some scenarios
- 🔄 Alternative therapy available — better suited to patient
- 💰 Loss of access — address if possible before stopping
- 😭 Patient preference — after informed discussion
| Indication | Consequences of stopping |
|---|---|
| Kidney transplant | Rejection risk; switch to alternative immunosuppressant |
| LAM | Lung function decline resumes; disease progresses |
| TSC manifestations | Tumors regrow; symptoms return |
| Vascular anomalies | Lesions may recur or worsen |
| Autoimmune indications | Disease flare risk |
⚠️ How to stop Rapacan safely:
- 🤝 Discussion with prescribing specialist
- 🔄 Taper or stop — usually just stop; no mandatory taper
- ⏳ Long washout — levels decline over weeks
- 🧪 Monitor disease status during and after
- 🔄 Alternative therapy arranged if needed
- 🏥 Close follow-up early after discontinuation
🔄 Washout timeline after stopping:
- 🕚 Day 1-7 — level drops as drug is cleared
- 🕚 Week 2 — levels substantially lower
- 🕚 Week 4-6 — essentially cleared
- 🕚 Full washout — approximately 5-7 half-lives (3-4 weeks)
- 👶 Pregnancy washout — wait at least 12 weeks for complete elimination
🔄 Alternative immunosuppressants for conversion:
- 💊 Kidney transplant — back to tacrolimus-based regimen
- 💊 LAM — limited alternatives; disease progression accepted or lung transplant
- 💊 TSC — everolimus can substitute for sirolimus
- 💊 Vascular anomalies — symptomatic management; occasionally alpelisib
🤔 If Rapacan is stopped unexpectedly (adverse event, loss of access, pregnancy): contact the prescribing specialist urgently. Alternative therapy arrangements, monitoring intensification, and disease surveillance plans need rapid implementation.
🔄 Restarting Rapacan after a break:
- ▶️ Can restart at any time if clinically appropriate
- 📈 Loading dose consideration — reaches target faster
- 🧪 Baseline labs — CBC, LFTs, lipids, creatinine
- 🏥 Reassess clinical situation
- 🕚 Previous dose may need adjustment
- 🤝 Specialist supervision
🎯 Rapacan is typically a long-term medication. Many patients continue indefinitely because their condition requires ongoing mTOR inhibition. Attempts at discontinuation after sustained control may be considered in specific scenarios but usually result in disease recurrence.
🤔 Perioperative hold vs permanent discontinuation:
- ✂️ Perioperative hold — typically 2-4 weeks before surgery and until wound healed
- 🔄 Restart after healing — usual dose and monitoring
- 🚫 Permanent discontinuation — after serious adverse event or indication change
- 🤝 Decision rests with prescribing specialist and multidisciplinary team
Rapacan discontinuation decisions reflect the chronic nature of the diseases it treats. Many patients continue indefinitely because disease control depends on ongoing mTOR inhibition. Others successfully transition to alternative therapies or accept disease recurrence as the trade-off for avoiding side effects. The common thread is close specialist supervision throughout any transition.
🧬 Rapacan Research Longevity Off-Label Uses
Beyond its established clinical indications, sirolimus is one of the most actively researched compounds in aging biology, longevity, and off-label medical applications. The mTOR pathway it targets is implicated in cellular aging, and preclinical studies in multiple species have shown lifespan extension with mTOR inhibition.
This has generated substantial interest in sirolimus for anti-aging applications, though these remain investigational and not evidence-based for routine use.
🧬 Longevity research with sirolimus is active and intriguing but not yet evidence-based for routine use. Research applications should remain within supervised studies rather than self-directed use.
🌄 Why sirolimus interests aging researchers:
- 🧬 mTOR hyperactivation is implicated in cellular aging
- 🛁 Caloric restriction extends lifespan partly through mTOR inhibition
- 🐭 Rapamycin extends mouse lifespan in National Institute on Aging studies
- 🧪 Multiple species benefit in preclinical models
- 🚀 Autophagy enhancement — cellular cleanup process
- 🛡️ Possible immune aging benefits at low doses
| Research application | Status |
|---|---|
| General aging biology | Preclinical strong; human research early |
| Immunosenescence | Low-dose studies showing benefit (RTB101 program etc) |
| Alzheimer disease | Early investigation; autophagy pathway |
| Cancer prevention | Rationale exists; evidence mixed |
| Age-related macular degeneration | Investigational |
| Cardiovascular aging | Preclinical signals; clinical studies ongoing |
🚨 Self-directed use for longevity is NOT recommended:
- 🛑 No approved anti-aging indication
- 🛑 Risk-benefit unclear in healthy individuals
- 🛑 Side effects are real even at low doses
- 🛑 Monitoring requirements make unsupervised use unsafe
- 🛑 Grapefruit, drug interactions require awareness
🧪 Established off-label Rapacan uses with evidence:
- 🩸 Castleman disease — selected cases
- 🤾 Autoimmune cytopenias — refractory ITP, AIHA
- 🦠 Autoimmune lymphoproliferative syndrome
- 🏃 Specific muscular dystrophies — research applications
- 👩 Ovarian cancer — selected scenarios
- 🏆 Progeria — investigational
🎯 The PEARL trial (Participatory Evaluation of Aging with Rapamycin for Longevity) and other formal studies are investigating low-intermittent-dose sirolimus for aging effects in healthy adults. Results are preliminary. Participation in research is the appropriate route for interested individuals rather than self-prescription.
🎯 Low-dose intermittent dosing paradigm:
- 📉 Weekly dosing — studied for immunosenescence
- 📉 Lower cumulative exposure than daily immunosuppressive doses
- 🧬 Different biological effects than high-dose immunosuppression
- 🧪 Research only — not established clinical practice
🏆 Related research directions:
- 🚀 Everolimus for immunosenescence — RESTORE study program
- 🚀 Rapamycin + metformin combinations
- 🚀 Senolytics — related aging research
- 🚀 Caloric restriction mimetics
👩⚕️ For patients interested in longevity applications:
- 🤝 Discuss with physician — honest conversation
- 📑 Clinical trial participation — where appropriate
- 🚫 Not self-prescribing — serious drug
- 📊 Follow evidence as it develops
- 🤾 Accept uncertainty — applications remain investigational
The research applications of sirolimus illustrate how a drug discovered for one purpose (antifungal, then immunosuppressant) continues to open new therapeutic frontiers decades later. The combination of mTOR biology insights and clinical trials expanding across diverse diseases means Rapacan's role in medicine continues to evolve. For patients on established indications, this research context underscores the medication's broad biological significance.
🚫 Who Should Not Use Rapacan Contraindications List
Rapacan has specific contraindications and situations where alternative therapy is preferred. Understanding when the medication is NOT appropriate helps match patients to the right treatment and prevents avoidable complications.
Most contraindications are relative rather than absolute. Rapacan is used in high-risk scenarios when the alternative is worse than the medication.
🚫 Contraindications by category
- Known sirolimus allergy
- Severe active pneumonitis
- Severe active infection
- Prior severe sirolimus pneumonitis
- Severe hyperlipidemia uncontrolled
- Significant proteinuria at baseline
- Elective surgery in next 2-4 weeks
- Severe liver dysfunction
- Allopurinol combination without planning
- Pregnancy planning
- Breastfeeding
- Chronic infections
- Significant underlying lung disease
- Baseline cytopenias
- Controlled chronic conditions
- Moderate alcohol
- Routine age (adult)
- Most concurrent medications (with interaction awareness)
🚫 When Rapacan is NOT the right choice:
- 🚫 Known sirolimus allergy or anaphylaxis
- 🚫 Prior severe pneumonitis — usually permanent avoidance
- 🚫 Severe active infection — treat first
- 🚫 Significant active malignancy — oncology input
- 🚫 Severe hepatic dysfunction — metabolism affected
- 🚫 Recent major surgery — wound healing concern
- 🚫 Severe baseline cytopenias
| Red flag situation | Alternative or action |
|---|---|
| 🫁 History of interstitial lung disease | Avoid or use with pulmonary surveillance |
| 🫀 Baseline nephrotic range proteinuria | Usually avoid; worsens |
| 🛑 Active hepatic artery thrombosis | Avoid in liver transplant setting |
| 🤰 Pregnancy | Usually discontinue; alternative therapy |
| 🤔 Severe hyperlipidemia | Address before starting; may need alternative |
🧑⚕️ When to see a specialist before starting Rapacan:
- 🫁 History of lung disease or recent pneumonia
- 🫀 Baseline kidney abnormalities
- 💓 Severe hyperlipidemia or triglycerides
- 🤰 Pregnancy or planning pregnancy
- 🤔 Rare or complex clinical situation
- 🤔 Significant comorbidities
🎯 For most patients with appropriate indications (kidney transplant, LAM, TSC, vascular anomalies) and no absolute contraindications, Rapacan is a safe and effective therapy when prescribed and monitored by experienced specialists. The medication requires blood level monitoring, lipid management, infection vigilance, and interaction awareness — but these are routine aspects of specialist care.
📚 This guide reflects evidence through 2026. Sirolimus practice continues to evolve, particularly in:
- 🧬 Pharmacogenomic insights — individualized dosing
- 🚀 Rare disease applications — expanding indications
- 🚀 Aging research — longevity applications in development
- 🚀 Combination therapies — with biologics, targeted agents
- 🏥 Transplant protocol refinement — optimal mTOR inhibitor placement
🗓️ Long-term users benefit from annual specialist review covering disease activity, side effect assessment, blood level targeting, lipid management, kidney function surveillance, pulmonary vigilance, cancer screening, vaccination updates, and consideration of alternative therapies as new options emerge.
Rapacan represents the clinical fulfillment of a remarkable scientific journey — from Easter Island soil in 1972 to transformative therapies for kidney transplantation, lymphangioleiomyomatosis, tuberous sclerosis, and expanding rare disease applications. The medication requires sophisticated clinical use, blood level monitoring, interaction awareness, and specialist coordination — but delivers substantial benefit for appropriately selected patients across its range of indications. Informed use with structured monitoring produces the best outcomes.
Rapacan — Frequently Asked Questions
-
What is Rapacan (Sirolimus)?
Rapacan is a brand name for Sirolimus, an immunosuppressant drug used to prevent organ rejection in transplant patients and treat certain medical conditions. -
How does Rapacan work?
Rapacan works by weakening the immune system to help your body accept the new organ as if it were your own. -
What conditions is Rapacan used to treat?
Primarily used to prevent organ rejection in kidney transplant patients, it's also used for lymphangioleiomyomatosis and as a coating for coronary stents. -
Is Rapacan a steroid?
No, Rapacan is not a steroid. It's a macrolide compound that inhibits T-lymphocyte activation and proliferation. -
How is Rapacan administered?
It's usually taken orally, in tablet form. -
What are the side effects of Rapacan?
Common side effects include mouth sores, diarrhea, nausea, reduced platelet count, and increased susceptibility to infections. -
Can Rapacan be used during pregnancy?
It's generally not recommended during pregnancy unless necessary. It's important to discuss the risks and benefits with your doctor.
See all Rapacan questions (33)
📚 Drug Description Sources:
The information in this Rapacan guide is compiled from authoritative pharmacologic, transplant medicine, pulmonology, and rare disease sources covering sirolimus therapy since its discovery on Easter Island in 1972 and FDA approval for kidney transplantation in 1999, the clinical placement in calcineurin-free and calcineurin-sparing immunosuppression protocols, the pivotal MILES trial that established sirolimus for lymphangioleiomyomatosis, the EXIST trials in tuberous sclerosis complex, and the specific pharmacokinetic monitoring required for blood level optimization.
🏛️ Regulatory and Government Agencies
- CDSCO India Rapacan Product Information — Central Drugs Standard Control Organisation listing for Biocon sirolimus
- FDA Approved Labeling — Rapamune Oral Solution and Tablets — reference prescribing information
- FDA 1999 Approval for Kidney Transplant Rejection Prophylaxis — original indication
- FDA 2015 Approval for Lymphangioleiomyomatosis — first drug approved for LAM
- EMA and MHRA Sirolimus Scientific References — European regulatory monographs
📚 Professional Societies and Clinical Guidelines
- KDIGO Guidelines on Kidney Transplant Immunosuppression — international standards
- ATS Clinical Practice Guidelines on LAM — American Thoracic Society sirolimus recommendations
- International Tuberous Sclerosis Complex Consensus Group — mTOR inhibitor guidelines
- British Transplantation Society Immunosuppression Guidelines — UK clinical standards
- American Society of Transplantation Position Statements — evolving protocols
🔬 Landmark Clinical Research
- Vezina rapamycin discovery 1972 — original Streptomyces hygroscopicus isolation from Rapa Nui soil
- MILES trial 2011 — established sirolimus for lymphangioleiomyomatosis (McCormack)
- EXIST-1 and EXIST-2 trials — established mTOR inhibitors for TSC manifestations
- CONVERT trial — sirolimus conversion from calcineurin inhibitors in kidney transplant
- Hall and Sabatini mTOR research — foundational cell biology discoveries
📖 Medical References and Textbooks
- Danovitch Handbook of Kidney Transplantation — standard transplant reference
- Murray and Nadel Textbook of Respiratory Medicine — LAM and interstitial lung disease
- Goodman and Gilman Pharmacological Basis of Therapeutics — immunosuppressant pharmacology
- Harrison Principles of Internal Medicine — multi-system immunosuppressant use
- UpToDate - Sirolimus clinical use — continuously updated reference
Note: This information is educational and does not replace consultation with qualified transplant, pulmonary, or specialty medical providers. Rapacan is a Biocon sirolimus formulation and clinical evidence applies equally to generic sirolimus from reputable manufacturers. The medication requires specialist supervision for blood level monitoring, lipid management, pneumonitis vigilance, drug interaction management (particularly CYP3A4 inhibitors), and specific procedures around wound healing and surgery.
🩺 Medical Expert Review:
Content based on the published research and clinical practice of international transplant medicine, cell biology, rare lung disease, and tuberous sclerosis authorities with particular expertise in sirolimus clinical use, mTOR pathway biology, and the clinical placement of mTOR inhibitor therapy across transplant, lymphangioleiomyomatosis, and tuberous sclerosis indications.
Prof. Michael N. Hall, PhD
Professor of Biochemistry, Biozentrum University of Basel; Lasker Basic Medical Research Award 2017 for mTOR discovery — Basel, Switzerland
Prof. Hall discovered the mTOR protein and the pathway it regulates in the 1990s, work recognized by the Lasker Award in 2017. His research established the fundamental cell biology underlying sirolimus action and informs the entire field of mTOR inhibitor clinical use including transplantation, LAM, TSC, and emerging aging research applications.
Prof. Francis X. McCormack, MD
Professor of Internal Medicine, University of Cincinnati; LAM Foundation Scientific Director — Cincinnati, Ohio
Prof. McCormack led the MILES trial (New England Journal of Medicine 2011) that established sirolimus as effective therapy for lymphangioleiomyomatosis, resulting in FDA approval in 2015. This was the first drug approved for LAM. His continuing work on sirolimus optimization and biomarkers shapes current LAM care worldwide.
Prof. Dirk R. Kuypers, MD, PhD
Professor of Nephrology and Transplant Medicine, KU Leuven University Hospitals; former ESOT board member — Leuven, Belgium
Prof. Kuypers is a European authority on kidney transplant immunosuppression and the clinical placement of mTOR inhibitors in modern protocols. His research covers calcineurin-free and calcineurin-sparing strategies using sirolimus, long-term outcomes, and side effect management in transplant recipients.
Prof. Suphamai Bunnapradist, MD, MS
Professor of Medicine, UCLA David Geffen School of Medicine; Director Outpatient Services UCLA Kidney Transplant Program — Los Angeles, California
Prof. Bunnapradist has published extensively on kidney transplant immunosuppression outcomes including sirolimus use in various protocols. His research on real-world transplant data and comparative effectiveness informs US and international practice on mTOR inhibitor selection and management.
Prof. David N. Franz, MD
Professor of Pediatrics and Neurology, Cincinnati Children's Hospital Medical Center; Director Tuberous Sclerosis Clinic — Cincinnati, Ohio
Prof. Franz is a leading authority on tuberous sclerosis complex (TSC) and mTOR inhibitor therapy. He participated in EXIST trials establishing mTOR inhibitor efficacy for TSC manifestations including SEGA brain tumors, renal angiomyolipomas, and refractory epilepsy. His clinic is a reference center for pediatric TSC care.
Disclosure: Expert names and credentials are cited for educational reference. This content is not endorsed by the named experts. Content prepared by the RXshop editorial team based on published literature, regulatory documents, and international guidelines current at the time of writing.
More Immunosuppressants Medications

