Bulimia: What Purging Actually Does to the Body

Bulimia is usually described in terms of behaviour — eating and then compensating. That description is accurate and almost useless, because it explains nothing about why the illness is dangerous, why it is so hard to stop, and why the person doing it is frequently the last to understand what is happening to their body.
This article is about the physical side. Not because the psychological side matters less, but because the physical facts are the ones people are most often wrong about, and being wrong about them keeps the cycle running.
📖 A note on the old classification. Bulimia used to be split into a purging type and a non-purging type, depending on the method of compensation. That division was removed from the diagnostic manual in 2013, because it did not predict severity, treatment response or outcome. Categories such as bulimia associated with obesity or bulimia with variable weight have never been diagnostic categories at all.
What replaced the subtypes is a severity rating based on how often compensation happens. It is a more honest measure, and it makes the point that matters: the method is less important than the frequency, and no method is safe.
🔄 The loop, and why it tightens
The cycle has a shape that repeats regardless of who is in it, and each stage feeds the next in a way that is close to mechanical.
| Stage | What happens | Why it leads to the next |
|---|---|---|
| Restriction | Eating is limited, often severely, and often across most of the day | Physiological hunger builds and self-control is spent. This is a biological state, not a character failure |
| Binge | A large amount eaten rapidly, with a distinct sense of loss of control | Produces shame, physical discomfort and acute fear about weight |
| Compensation | Purging, laxatives, diuretics, fasting or driven exercise | Relieves the fear temporarily, which teaches the brain that the behaviour works |
| Resolve | A commitment to eat strictly from now on | Which is restriction, and the loop closes |
The important part is the third stage. Compensation is enormously reinforcing, not because it does what the person thinks it does, but because it reliably removes an unbearable feeling within a short time. That is exactly the learning pattern that makes a behaviour hard to give up, and it is why willpower is such a poor tool against it.
The second important part is that restriction is the engine, not the binge. Treatment that focuses on stopping the binges without addressing the restriction almost always fails, because the restriction is what generates the next binge.
🫀 The complication that kills people
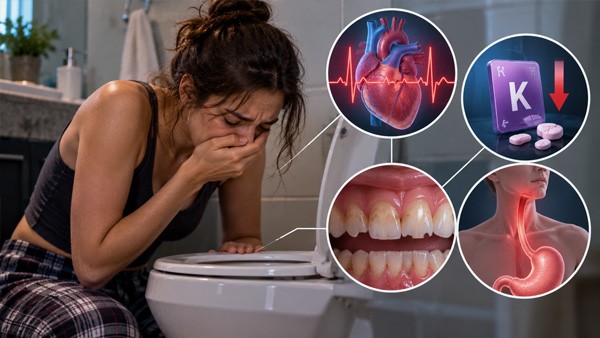
Most people with bulimia are worried about their weight. Almost nobody is worried about their potassium, and potassium is the thing that ends lives.
Vomiting, laxatives and diuretics all remove potassium from the body. Potassium is what allows heart muscle to reset electrically between beats. When it falls far enough, the heart becomes prone to abnormal rhythms, and some of those rhythms are fatal within minutes.
🔴 This is the single most dangerous thing about bulimia, and it gives very little warning. Low potassium produces muscle weakness, cramps, unusual tiredness, palpitations, constipation and numbness or tingling — symptoms so unremarkable that they are attributed to stress or poor sleep. The step from those symptoms to a dangerous rhythm is not gradual.
Chest pain, a racing or irregular heartbeat, fainting, or severe muscle weakness in anyone who is purging is a medical emergency. It needs to be said out loud, at that appointment, that purging is happening — because a potassium level is a simple blood test and nobody orders it without a reason.
Vomiting also strips the body of acid, which pushes the blood chemistry in an alkaline direction and makes the kidneys hold onto acid while dumping more potassium. The result is that the two problems reinforce each other. Laxatives and diuretics produce a related but different disturbance, and diuretics also lower sodium, which at low enough levels causes confusion and seizures.
None of this requires years of illness. It can develop during a single intensive period.
🦷 The damage that does not reverse
Stomach acid dissolves tooth enamel, and enamel does not grow back. This is the one permanent consequence of bulimia in someone who otherwise recovers fully, and it is often the reason the illness is discovered.
The pattern is distinctive enough that dentists recognise it immediately: erosion on the inner surfaces of the upper front teeth, where acid pools, while the outer surfaces look normal. Fillings begin to stand proud of the tooth surface around them, because the filling material does not dissolve and the tooth around it does. Sensitivity to cold and sweetness arrives early. Teeth become shorter, translucent at the edges, and yellower as the darker layer beneath shows through.
Two practical points are worth more than any amount of general advice here.
⚠️ Do not brush immediately after vomiting. The enamel is softened by acid at that moment, and brushing scrubs it away. Rinsing with water, or with water containing a little bicarbonate of soda, and then waiting at least half an hour before brushing does considerably less damage.
Tell the dentist. Erosion of this kind is treated differently from ordinary wear, high-fluoride products can be prescribed to slow it, and restorative work carried out while purging continues will simply fail. Dentists see this regularly and are not there to judge.
Alongside the teeth, the salivary glands in front of the ears frequently swell, giving the face a rounded appearance. This is a benign response to repeated vomiting and it settles after purging stops, though it can take weeks and it often becomes temporarily more noticeable at first — a detail worth knowing, because it is deeply demoralising to someone who has just stopped.
💧 What each method actually achieves
This section exists because the beliefs behind these behaviours are factually wrong, and correcting them is one of the few pieces of information that changes what people do.
| Method | What people believe | What actually happens |
|---|---|---|
| Vomiting | The food is removed | A substantial proportion of calories has already been absorbed. Roughly half of what was eaten remains. Potassium, acid and enamel are lost in exchange |
| Laxatives | Food passes through unabsorbed | Calories are absorbed in the small intestine, and laxatives act on the large intestine, after that has already happened. The weight lost is water. It returns within a day |
| Diuretics | Fluid weight is shed | Water only, replaced as soon as fluid is drunk. Removes potassium and sodium, and stresses the kidneys |
| Fasting | The excess is cancelled out | Restriction is the direct trigger for the next binge. This is the most reliable way to guarantee the cycle repeats |
| Driven exercise | The intake is burned off | The energy figures do not match by a wide margin. Combined with low potassium it adds cardiac risk, and it commonly produces stress fractures |
The laxative row deserves emphasis because the misunderstanding is so complete. Digestion and calorie absorption finish in the small intestine. Laxatives work on the colon, which is downstream of all of it, and whose main job is reclaiming water. So the only thing a laxative removes is water. The number on the scale falls, which appears to confirm the theory, and it returns the following day, which is taken as evidence that a larger dose is needed.
Prolonged use makes the bowel dependent, so that normal function does not resume without them. Stopping then produces days of constipation and bloating, which feels like proof that they were necessary. They were not. That phase passes, and it passes faster with fluid, fibre and time than with another dose.
📈 The trap in the first weeks of stopping
This is the least known and most destructive thing in the whole subject, and it is the reason a great many attempts to stop fail in the first fortnight.
When the body has been losing fluid repeatedly through purging, laxatives or diuretics, it responds by producing hormones that make it hold onto salt and water. Those hormones stay elevated for a while after the losses stop. So when someone stops purging, the retention system is still running at full strength with nothing to counteract it, and the body holds water.
The result is swelling of the hands, feet, ankles and face, and a rapid rise on the scale — sometimes several kilograms within days. To someone who has just made an enormous effort to stop, this looks exactly like the catastrophe they were purging to prevent.
✅ It is water, it is temporary, and it resolves on its own. Typically over one to four weeks, occasionally longer where laxatives were used heavily. It is not fat, and the scale is not telling the truth during that period.
What helps: staying off the scale entirely for those weeks, eating regularly with adequate salt rather than restricting it further, elevating the legs, and knowing in advance that this is coming. What makes it far worse: restricting or purging in response, which restarts the whole hormonal cycle from the beginning.
Anyone planning to stop should be warned about this before they start, and should ideally have medical supervision through it, particularly where purging has been frequent or laxative use heavy.
🩸 Insulin omission
Among people with type 1 diabetes there is a form of compensation that has no equivalent in anyone else: deliberately reducing or skipping insulin so that glucose is lost in the urine rather than stored.
It is effective at causing weight loss, which is why it happens, and it is among the most dangerous behaviours in this entire field. It drives blood sugar high, causes severe dehydration, and can produce a life-threatening metabolic emergency. Repeated over time it accelerates damage to eyes, kidneys and nerves by many years, and it substantially shortens life expectancy.
It is under-recognised because the signs — unexplained high readings, repeated ketoacidosis, weight loss, missed appointments — are usually read as poor self-management rather than as an eating disorder. Anyone with type 1 diabetes whose control has become erratic alongside weight concerns needs assessment for this specifically, and needs care from a team that handles both problems together rather than each separately.
🔍 Why it goes unnoticed for years
The single most persistent myth about bulimia is that a person with an eating disorder is visibly underweight. In bulimia that is usually not the case. Most people with bulimia are within a normal weight range, and some are above it. Nothing about their appearance suggests illness.
The behaviour is also concealed with considerable skill, and the shame surrounding it makes disclosure exceptionally difficult — more so than with restriction, which is sometimes admired before it is recognised as a problem. Bulimia is rarely admired by anybody, including the person doing it.
What is actually visible, if anyone knows to look, is a set of physical signs rather than a body shape.
| Sign | Where it comes from |
|---|---|
| Swelling in front of the ears, along the jaw | Enlarged salivary glands from repeated vomiting |
| Calluses or scarring across the knuckles | Contact with the teeth during vomiting |
| Teeth appearing shorter, more transparent at the edges | Acid erosion of enamel |
| Persistent sore throat, hoarseness, reflux | Acid damage to the throat and oesophagus |
| Tiny red spots around the eyes or on the face | Burst capillaries from the pressure of vomiting |
| Frequent tiredness, cramps, palpitations | Low potassium |
| Disappearing to the bathroom after meals | The behaviour itself |
| Missing or irregular periods | Disruption of the hormonal cycle |
None of these is proof on its own. Several together, in someone preoccupied with weight, is a reason to ask directly and kindly.
🧠 What treatment actually consists of
Bulimia has better outcomes than most people expect, and the evidence for what works is unusually clear.
Psychological therapy is the primary treatment — specifically the forms designed for eating disorders, which work on the restriction that drives the binges rather than on the binges themselves. Guided self-help programmes based on the same principles are effective for a substantial number of people and are far more accessible than specialist therapy in most places, which matters when waiting lists are long.
The core of it is establishing regular eating: consistent meals across the day, without gaps long enough to generate a binge, and without compensating afterwards. This is enormously difficult and it is also the single most effective intervention. Most of the improvement in binge frequency follows from it.
Medication is an adjunct rather than a treatment on its own. It reduces binge and purge frequency, and it works best combined with therapy rather than instead of it.
| Drug | Position |
|---|---|
| Fluoxetine | The only medication licensed specifically for bulimia, and it is used at a higher dose than for depression. It reduces binge and purge frequency independently of whether depression is present |
| Other SSRIs | Used where fluoxetine is unsuitable or unavailable. Evidence is weaker but the class effect appears real, and depression and anxiety alongside bulimia are common and worth treating |
| Topiramate | Reduces binge frequency. Used cautiously, since appetite suppression and weight loss can feed the illness rather than treat it, and it must be avoided in pregnancy |
| Bupropion | Contraindicated. See below |
🚫 Bupropion must not be used by anyone with a current or past eating disorder involving purging. It substantially raises the risk of seizures in this group, and that risk is compounded by the electrolyte disturbance that purging already causes.
This matters more than a footnote, because bupropion is widely known for suppressing appetite and causing weight loss, which makes it exactly the drug someone with bulimia is likely to seek out. Wellbutrin (bupropion) is a useful medicine for depression and for stopping smoking, and it is the wrong medicine here. A prescriber cannot apply this restriction if they have not been told, which is one more reason the behaviour has to be disclosed.
Alongside therapy and medication, the physical side needs monitoring in its own right: potassium and other electrolytes checked where purging is frequent, dental review, and specific attention to bone health where periods have stopped for any length of time. The overview of eating disorders covers how the different conditions in this family relate to one another and how they move between each other over time.
📆 What recovery looks like from inside
The honest version is more useful than the encouraging one, because people who expect a straight line give up when they do not get it.
The first weeks are physically uncomfortable. Fluid retention and swelling, bloating, constipation if laxatives were being used, and a stomach that empties slowly and makes normal meals feel enormous. All of this is temporary and all of it feels like evidence that stopping was a mistake.
Anxiety rises before it falls. Compensation was doing a job — relieving fear — and removing it leaves the fear with nowhere to go. That period is what therapy exists to get someone through, and it does pass.
Lapses are part of the pattern, not the end of it. The difference between a lapse and a relapse is almost entirely what happens next: whether the person returns to regular eating the same day, or responds with restriction, which restarts everything.
The physical repair is mostly complete. Electrolytes normalise, the salivary glands settle, the gut recovers, periods return, and the swelling resolves. The enamel does not, which is the one argument for acting sooner rather than later that has nothing to do with how bad things feel today.
🤝 Saying something to someone else
Two things reliably fail. Commenting on appearance or weight, in any direction, because it confirms that bodies are what is being watched and judged. And policing food or bathroom visits, which turns the illness into a contest and drives it further out of sight.
What works better is unremarkable: naming what has been noticed without accusation, saying it privately and once rather than repeatedly, making clear that the offer of help stands whether or not it is taken today, and being willing to sit through the denial that usually comes first. Denial at the first attempt is close to universal and it is not a refusal — it is frequently the moment someone realises they have been seen, which is what eventually makes asking for help possible.
🩺 When to seek help
- Chest pain, palpitations, an irregular heartbeat or fainting in anyone purging — emergency
- Severe muscle weakness, or weakness in the legs — urgent, and a potassium level is needed
- Confusion or a seizure, particularly where diuretics have been used — emergency
- Vomiting blood, or severe chest or abdominal pain after vomiting — emergency
- Difficulty swallowing, or persistent hoarseness — needs assessment
- Erratic blood sugars in type 1 diabetes alongside weight concerns — assessment for insulin omission
- Any purging happening more than occasionally — specialist referral, not watchful waiting
- Before stopping, where purging has been frequent or laxative use heavy — medical supervision through the first weeks
- Tooth sensitivity or visible wear — dental review, with the cause stated
Treatment support is available in the antidepressants category, including Sertafine (sertraline), and Topamax (topiramate), which is sometimes used to reduce binge frequency under specialist supervision. Medication in bulimia works alongside psychological treatment rather than in place of it, and prescribing decisions here depend on information the prescriber can only have if it is given to them.
❓ Frequently asked questions
Are there really four types of bulimia?
No. The split into purging and non-purging types was removed from the diagnostic manual in 2013 because it did not predict severity or outcome, and categories such as bulimia associated with obesity were never diagnostic categories at all. What is used now is a severity rating based on how often compensation occurs. The practical message is that the method matters less than the frequency, and none of the methods is safe.
Do laxatives stop calories being absorbed?
No, and this is the most consequential misunderstanding in the whole subject. Calories are absorbed in the small intestine. Laxatives act on the large intestine, which is downstream of that, and whose job is reclaiming water. So the only thing removed is water, and it returns within a day. Prolonged use makes the bowel dependent without ever having affected calorie absorption at all.
What is the most dangerous physical risk?
Loss of potassium. Vomiting, laxatives and diuretics all remove it, and potassium is what allows heart muscle to reset electrically between beats. When it falls far enough the heart becomes prone to abnormal rhythms, some of which are fatal within minutes. The warning symptoms are unremarkable — tiredness, cramps, weakness, palpitations — which is exactly why this is the risk that gets missed.
I stopped purging and I have gained weight rapidly. What is happening?
Almost certainly fluid retention. Repeated fluid loss makes the body produce hormones that hold onto salt and water, and those hormones stay elevated after the losses stop. The result is swelling of hands, feet and face and a fast rise on the scale over days. It is water, not fat, and it resolves over one to four weeks. Staying off the scale entirely during that period is genuinely useful advice.
Should I brush my teeth after vomiting?
Not immediately. Acid softens the enamel, and brushing at that moment scrubs the softened layer away, which does more damage than the acid alone. Rinse with water, or with water containing a little bicarbonate of soda, and wait at least half an hour before brushing. Enamel does not grow back, so this is one of the few pieces of harm reduction here that has a permanent effect.
Can you have bulimia at a normal weight?
Yes, and most people with bulimia are within a normal weight range, with some above it. The belief that an eating disorder must be visible is the reason bulimia goes undetected for years and the reason people conclude they are not ill enough to ask for help. Severity is determined by the behaviour and its physical consequences, not by body weight.
Which medication is used for bulimia?
Fluoxetine is the only medication licensed specifically for it, given at a higher dose than is used for depression, and it reduces binge and purge frequency whether or not depression is present. Other SSRIs are used where it is unsuitable. Topiramate reduces binge frequency but is used cautiously, since its appetite-suppressing effect can feed the illness. All of these work best alongside psychological therapy rather than instead of it.
Why is bupropion not allowed?
Because it substantially raises the risk of seizures in anyone with a current or past eating disorder involving purging, and that risk is compounded by the electrolyte disturbance purging already causes. It is a real contraindication rather than a caution. It matters particularly because bupropion is known for suppressing appetite, which makes it precisely the drug someone with bulimia is likely to look for.
What is insulin omission in diabetes?
Deliberately reducing or skipping insulin so that glucose is lost in the urine instead of being stored. It causes weight loss, which is why it happens, and it is among the most dangerous behaviours in this field — it can trigger a life-threatening metabolic emergency and it accelerates damage to eyes, kidneys and nerves by years. It is usually mistaken for poor self-management rather than recognised as an eating disorder.
How do I raise this with someone I am worried about?
Avoid commenting on weight or appearance in any direction, and avoid policing food or bathroom visits — both drive the behaviour further out of sight. Name what you have noticed privately, once, without accusation, and make clear the offer stands whether or not it is taken now. Expect denial at the first attempt. It is close to universal, and it is frequently the moment the person realises they have been seen.
📑 Sources and editorial
- Diagnostic criteria for bulimia nervosa and the 2013 removal of purging and non-purging subtypes
- Clinical literature on hypokalaemia, metabolic alkalosis and cardiac arrhythmia in purging behaviour
- Dental literature on perimylolysis and enamel erosion patterns in self-induced vomiting
- Evidence on the site of calorie absorption and the absence of any effect of stimulant laxatives on it
- Literature on pseudo-Bartter syndrome and rebound oedema following cessation of purging
- Guidance on insulin omission in type 1 diabetes with disordered eating
- Trial evidence for fluoxetine in bulimia nervosa and its licensed indication
- Contraindication of bupropion in current or prior eating disorders on seizure-risk grounds
- Guideline recommendations for eating-disorder-focused psychological therapy and guided self-help
- Related reading: understanding eating disorders, how body fat actually works, psychiatric drug classes
- Related products: antidepressants category
- RXshop Editorial Team — reviewed by Emily Chen, MD, Internal Medicine
Medical Disclaimer: The information in this article is for educational and informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always seek guidance from a qualified healthcare provider with any questions you may have regarding a medical condition, and before starting, stopping or changing any medication.