Buy Armod (Armodafinil 150mg) Online - Original Nuvigil Brand Emcure Generic R-Enantiomer Wakefulness Promoter


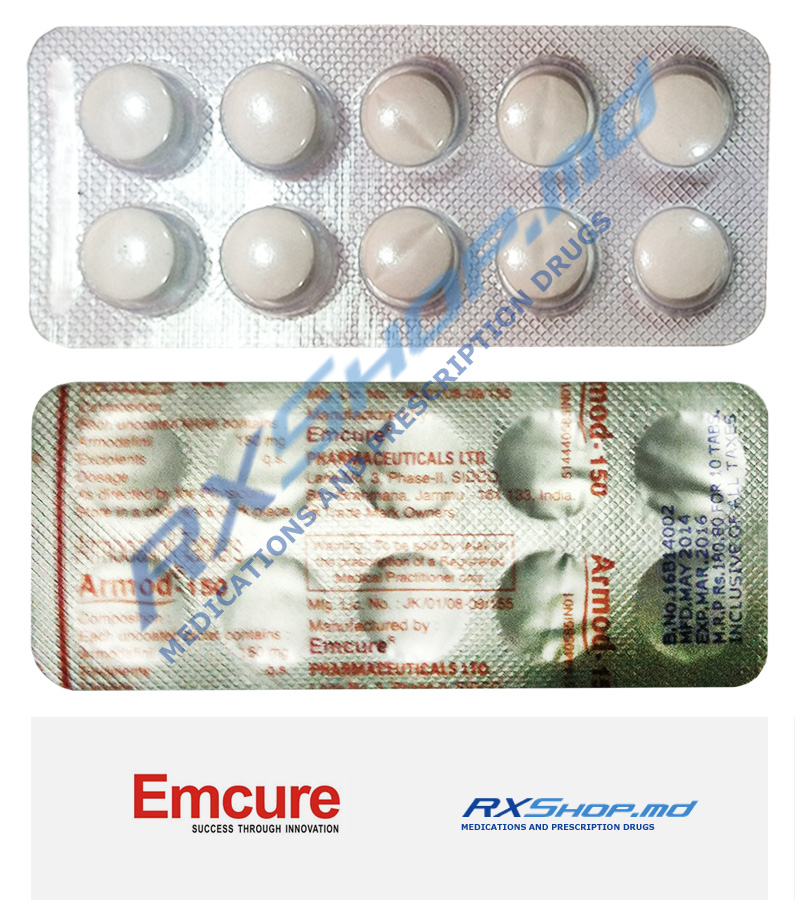
Armod (Armodafinil 150 mg) represents the R-enantiomer wakefulness-promoting therapy - the more potent and longer-acting successor to modafinil for excessive daytime sleepiness management. Originally developed as Nuvigil by Cephalon (later acquired by Teva Pharmaceuticals in 2011) and FDA-approved in 2007 as the first single R-enantiomer wakefulness promoter, armodafinil provides more selective pharmacology than racemic modafinil with longer clinical duration. Armod on rxshop.md is manufactured by Emcure Pharmaceuticals Ltd - Pune-based Indian pharmaceutical company founded 1981 with WHO-GMP certification, US FDA-inspected manufacturing facilities, and global operations in over 70 countries.
NOTE: Armod is currently out of stock. As alternative wakefulness therapy, consider our Modvigil (Modafinil) or Modalert (Modafinil) as racemic modafinil alternatives with equivalent FDA indications and similar mechanism of action.
Armodafinil works as a selective wakefulness-promoting agent through multiple central nervous system pathways. First, armodafinil inhibits dopamine reuptake at the dopamine transporter (DAT) with higher selectivity than amphetamines. Second, armodafinil activates hypothalamic orexin/hypocretin neurons promoting arousal and wakefulness. Third, armodafinil modulates histamine H1 signaling through tuberomammillary nucleus activation. Fourth, armodafinil enhances norepinephrine transmission in wake-promoting brain regions. Fifth, armodafinil reduces GABA-mediated inhibition in cortical wakefulness pathways. Combined effects produce sustained wakefulness without the euphoria or abuse potential of classical stimulants.
Armod primary FDA indications include narcolepsy for reduction of excessive daytime sleepiness, obstructive sleep apnea (OSA) adjunctive therapy to CPAP for residual sleepiness, and shift work sleep disorder (SWSD) for improved wakefulness during scheduled awake periods. Common off-label uses include ADHD in adults, depression augmentation particularly for fatigue and apathy symptoms, chronic fatigue syndrome, jet lag management, and cognitive enhancement in select populations.
Armod at 150 mg strength provides efficacy equivalent to modafinil 200 mg with longer duration of action (armodafinil half-life approximately 15 hours vs modafinil 12 hours) enabling more consistent all-day wakefulness with single morning dosing. Schedule IV controlled substance requiring prescription. Standard dosing: 150 mg once daily in the morning for narcolepsy and OSA; 150 mg one hour before shift start for SWSD.
Free prescription
Discrete packaging
Have questions?
Quality Assurance

- Excessive Daytime Sleepiness: Persistent difficulty staying awake during appropriate wake hours affecting work performance and safety;
- Obstructive Sleep Apnea: Sleep disorder with breathing pauses causing fragmented sleep and residual daytime sleepiness;
- Shift Work Sleep Disorder: Circadian rhythm disorder in night-shift workers causing sleepiness during scheduled awake periods;
- Cataplexy Support: Sudden muscle weakness triggered by strong emotions commonly occurring with narcolepsy diagnosis;
- ADHD in Adults: Off-label use for attention deficit hyperactivity disorder providing focus without amphetamine effects;
- Depression Augmentation: Off-label augmentation therapy for depression with prominent fatigue and apathy symptoms;
- Chronic Fatigue Syndrome: Off-label use for debilitating chronic fatigue with post-exertional malaise disorders;
- Jet Lag Management: Off-label use for circadian disruption from rapid transmeridian travel affecting alertness;
- Cognitive Enhancement: Off-label use for cognitive performance in sleep-deprived states requiring sustained attention;
- Sleep Deprivation Effects: Countering acute sleep deprivation effects in essential occupations requiring sustained alertness;
- Multiple Sclerosis Fatigue: Off-label use for debilitating fatigue in multiple sclerosis affecting quality of life;
- Post Anesthesia Sedation: Off-label use for reversal of persistent post-anesthesia sedation in selected patients;
- Parkinson Disease Fatigue: Off-label use for daytime sleepiness in Parkinson disease affecting daily functioning;
- Idiopathic Hypersomnia: Chronic disorder of excessive daytime sleepiness without clear underlying cause;
- Sleep Attacks Prevention: Prevention of sudden overwhelming sleep episodes disrupting activities and posing safety risks;
- Wakefulness Promotion: Selective wakefulness enhancement without stimulant euphoria or classical amphetamine effects;
- CPAP Adjunctive Therapy: Combined with CPAP for obstructive sleep apnea patients with residual daytime sleepiness;
- Night Shift Alertness: Improved alertness during scheduled night-shift work hours requiring sustained attention;
- Long Duration Wakefulness: Extended wakefulness benefit from longer half-life R-enantiomer compared to racemic modafinil.
- Less Daytime Sleepiness: Substantial reduction in excessive daytime sleepiness across narcolepsy and OSA populations;
- Better Focus: Improved sustained attention and concentration during work and study activities;
- Better Cognitive Performance: Improved cognitive function in sleep-deprived states enabling productive work performance;
- Fewer Sleep Attacks: Reduced frequency of sudden overwhelming sleep episodes in narcolepsy patients over months;
- Longer Duration Effect: Extended duration of action from 15-hour half-life vs modafinil 12-hour half-life;
- Once Daily Convenience: Simple once-daily morning dosing provides all-day wakefulness benefit;
- Better Work Performance: Improved workplace productivity and safety through sustained alertness during work hours;
- Better Driving Safety: Reduced drowsy driving risk in patients with narcolepsy or OSA affecting road safety;
- Better Quality of Life: Substantial quality of life improvements from reduced excessive sleepiness symptoms;
- Better Mood Stability: Improved mood as chronic exhaustion resolves supporting daily functioning improvements;
- Better Social Functioning: Improved social engagement as daytime alertness enables interactions and relationships;
- Less Fatigue: Reduced chronic fatigue in narcolepsy CFS and MS populations affecting daily life;
- Better Motivation: Improved motivation and engagement in activities previously abandoned due to sleepiness;
- Improved Reaction Time: Faster reaction times in sleep-deprived states supporting safety and performance;
- Better Memory Function: Improved working memory and consolidation during sustained wakefulness states;
- Lower Abuse Potential: Substantially lower euphoria and abuse potential than classical amphetamine stimulants;
- Better Shift Work Adaptation: Improved adaptation to night shift schedules for shift work sleep disorder patients;
- Less Depression Fatigue: Off-label reduction in depression-related fatigue and apathy as augmentation therapy;
- Better Overall Alertness: Substantially improved daytime alertness enabling engagement in activities previously affected.
Generic Armod (Armodafinil 150 mg) Medication guide:
💡 Introduction to Modaheal and What Modafinil Does
Modaheal is a 200 mg modafinil tablet made by Healing Pharma, a generic equivalent of the original Provigil (Cephalon, 1998). The active ingredient belongs to a small family of wake-promoting drugs called eugeroics, from the Greek for good arousal. The job of a eugeroic is to make a sleepy brain alert enough to work, drive or finish a conversation, without the physical kick of amphetamines or the crash that follows a cup of strong coffee a few hours later.
Modafinil was approved by the United States FDA in 1998 for narcolepsy, the neurological condition in which the brain cannot keep itself in a stable waking state during the day. The approvals grew: in 2003 the FDA added obstructive sleep apnea (OSA) with residual daytime sleepiness despite good CPAP use, and in 2004 it added shift work sleep disorder for workers whose night-shift schedule leaves them unable to stay alert. In Europe, the regulator later narrowed the use to narcolepsy only after a 2011 risk-benefit review.
💡 What Modaheal actually does during the day
It raises the alertness floor — the point below which drowsiness takes over — by about 2 to 3 hours of extended wakefulness in a tired patient.
It does not add energy you did not have — it reduces the sleep pressure your brain is feeling.
It does not fix a lost night of sleep — the sleep debt is still there and shows up as soon as the drug wears off.
It wears off gently rather than crashing — the long half-life means the effect fades across the evening.
It is a controlled substance — US Schedule IV. Supply, prescription limits and tracking rules apply.
Three features explain why clinicians and patients keep coming back to modafinil over the amphetamine stimulants. First, the cardiovascular profile is quieter: average heart-rate and blood pressure changes are small compared with methylphenidate or amphetamine. Second, the abuse potential appears lower than with Schedule II stimulants, although it is not zero and modafinil carries Schedule IV status for a reason. Third, the effect duration covers a whole working day on a single morning dose, which the shorter-acting stimulants cannot do without redosing.
What Modaheal is not is a cognition enhancer for healthy adults who want to work longer hours, nor a replacement for sleep, nor a safe choice during pregnancy. The guide ahead walks through where the drug has strong evidence (narcolepsy, OSA residual sleepiness, shift work), where the evidence is thinner (MS fatigue, depression augmentation, Parkinson disease sleepiness), and where it is dangerous or off-mark (lifestyle use in sleep-deprived students, replacement for a diagnosed sleep disorder, use during pregnancy or alongside hormonal contraception without a backup method).
⚖️ Why Modafinil Is Called a Eugeroic Not a Stimulant
Patients and reporters often call modafinil a stimulant, but the pharmacology does not fit that label well. Classical stimulants like amphetamine and methylphenidate release large amounts of dopamine from storage pools in nerve terminals and dump norepinephrine at the same time. The effect is a wide, fast rise in alertness and arousal, with a reliable rebound and a reliable crash. Modafinil is something different: a selective, modest change in a few arousal pathways rather than a sledgehammer across the dopamine system.
| ⚖️ Feature | Amphetamine | Modafinil |
|---|---|---|
| Main action | Dopamine release and reuptake block | Mild dopamine reuptake block plus orexin and histamine support |
| Peak effect | 30-60 minutes | 2-4 hours |
| Half-life | 10-13 hours (dextroamphetamine) | 12-15 hours (modafinil); up to 15 hours (R-modafinil) |
| Blood pressure and heart rate | Noticeable rise, dose-dependent | Small rise, usually 2-4 mm Hg and 2-5 bpm |
| Appetite effect | Strong suppression | Mild suppression, often unnoticed |
| Classical euphoria | Yes, high at higher doses | Rare at labelled doses; some mild reward signal in abuse-liability studies |
| US controlled schedule | Schedule II | Schedule IV |
| Crash on wearing off | Common and often sharp | Mild fade across the evening |
Dopamine is the shared thread. Amphetamine floods it; modafinil nudges it. In healthy human studies, modafinil blocks the dopamine transporter by about 50 percent at a 200 mg dose, which is a measurable but modest effect compared with a therapeutic amphetamine dose. The practical result is that modafinil can keep a tired brain alert without reproducing the amphetamine euphoria, appetite loss and cardiovascular lift at the same scale.
A simple way to think about the difference: amphetamine makes a sleepy brain feel awake and driven by pushing dopamine through the whole brain; modafinil makes a sleepy brain feel awake and settled by nudging a few specific arousal circuits. For a narcolepsy patient trying to get through a workday without a drive to work harder than usual, settled is often what is wanted.
⚠️ Not amphetamine does not mean not controlled
The modafinil abuse profile is lower than that of amphetamine but not zero. Reward signals do appear in abuse-liability studies at high doses, and tolerance is possible. Modafinil is a Schedule IV controlled substance in the United States for a reason: dependence can develop in people who use it for lifestyle wakefulness over months, and the drug has street value. The low-crash profile is a selling point, not a safety guarantee.
Comparisons with caffeine come up often. A standard adult dose of modafinil adds roughly as much alertness as 400 to 600 mg of caffeine, which is three to five strong coffees, but without the jitter and the diuresis. Unlike caffeine, modafinil does not create tolerance in the first weeks and does not have the same half-life problem for evening dosing — caffeine clears in 5 to 7 hours in most people, modafinil does not clear fully for 48 hours or so.
For most patients, the right frame is: modafinil is a focused tool for a defined sleep problem, not a general-purpose stimulant for a long day. The next sections unpack the mechanism in plain language and then move to the practical dosing side.
🔬 The Modafinil Mechanism in Four Pathways
The mechanism of modafinil is a story of four pathways working together, not one receptor flipped. The result is a net wake-promoting effect without a strong classical stimulant signature. The pathways below are the main ones in current pharmacology; several more have been proposed but the four here carry the weight of the clinical effect.
Pathway one is the dopamine transporter block. Modafinil binds the dopamine transporter protein and slows the removal of dopamine from the synaptic gap. At a 200 mg dose this reaches about 50 percent transporter occupancy in positron emission tomography studies, which is enough to raise dopamine signalling in reward and attention regions without the amphetamine-level flood. This is the most stimulant-adjacent part of the mechanism and the main reason the drug carries Schedule IV status.
Pathway two is orexin, also called hypocretin. Orexin neurons sit in the lateral hypothalamus and are the master wake-stabilising cells of the brain. In narcolepsy type 1, these neurons are selectively destroyed by an autoimmune process. Modafinil activates orexin cell firing in animal studies, which may be the main reason it works so well in people whose own orexin signal is damaged but not completely gone. This downstream engagement of the arousal system is a key piece of the story Jerome Siegel and colleagues mapped in the 1990s.
Pathway three is histamine. Histamine neurons in the tuberomammillary nucleus keep the cortex alert during waking. Antihistamines block this signal and make you sleepy. Modafinil raises histamine release in several brain regions, adding to the wake-promoting effect through a mechanism that is actually the opposite of a sedating allergy pill. This is why clinicians sometimes describe modafinil as a partial antidote to drowsy antihistamine side effects, although that is not a formal indication.
🧠 Why the mechanism matters for side effects
Because the dopamine push is modest, modafinil produces less euphoria, less appetite suppression and smaller blood pressure change than amphetamine. Because orexin and histamine are involved, the effect is a stable waking state rather than a stimulant high. And because glutamate rises while GABA falls, the brain feels more alert, which is also why insomnia appears if the dose is taken too late in the day.
Pathway four is the glutamate and GABA balance. Modafinil raises glutamate signalling (excitatory) and lowers GABA signalling (inhibitory) in several brain regions. Net result: more cortical excitation. This change is modest and reversible, but it is one reason modafinil can trigger anxiety or irritability in a minority of users — the same shift that keeps you alert can also keep you edgy.
Note what the mechanism is not. Modafinil is not a classical stimulant that releases stored dopamine. It is not a serotonin drug. It does not act on acetylcholine receptors in the brain. It does not block the norepinephrine transporter in any strong way. The limited specificity is a selling point for safety and a limitation for raw potency. The next section translates all of this into real plasma numbers and clock times you can act on.
⏱️ Modaheal Pharmacokinetics and the 15-Hour Half-Life
Modafinil is one of the longer-acting prescription stimulants on the market. A single 200 mg Modaheal tablet taken in the morning will still be measurable in your blood the following evening, and traces will be gone by about 48 hours after the dose. This long half-life is what makes once-daily dosing possible — and also what makes late-day dosing a reliable path to insomnia.
Oral absorption is reliable. The 200 mg Modaheal tablet is well absorbed from the small intestine. Food slows absorption by about an hour but does not reduce the total amount reaching the blood, so Modaheal can be taken with or without food. The peak plasma concentration arrives 2 to 4 hours after the dose, which is when you feel the full effect for the first time on a new prescription.
The half-life — the time for the plasma level to drop by half — is 12 to 15 hours for racemic modafinil. R-modafinil, the longer-lasting enantiomer, has a half-life closer to 15 hours; S-modafinil clears faster at about 4 to 5 hours. Modaheal, as racemic modafinil, carries both and shows an effective 15-hour clinical duration in most adults.
Metabolism happens almost entirely in the liver. The main pathway is a hydrolysis step followed by oxidation. Important for interactions, modafinil is both a moderate inducer of CYP3A4 and a mild inhibitor of CYP2C19. The CYP3A4 induction is the mechanism behind the clinically meaningful hormonal contraceptive interaction covered later in the guide. Modafinil has very little effect on CYP2D6 or CYP1A2.
🧪 Who metabolises modafinil slower than average
Older adults — hepatic clearance drops roughly 20 percent after age 65. A 100 mg starting dose is reasonable in frail elderly patients.
People with liver disease — moderate to severe hepatic impairment doubles exposure; dose halving is standard.
CYP2C19 poor metabolisers — a small share of patients clear modafinil much more slowly; higher plasma levels, more side effects.
Patients on other CYP3A4 inhibitors — ketoconazole, erythromycin and some HIV protease inhibitors raise modafinil levels.
Elimination is through the kidneys as inactive metabolites, mostly modafinil acid. Only about 10 percent of a dose leaves the body as the parent drug. Severe kidney disease does not require a dose change for modafinil itself because the kidneys are mainly clearing already-inactivated metabolites, not the active parent.
The pharmacokinetics explain the clock-based dosing rules. Taking Modaheal at 7 AM gives peak plasma around 9 to 11 AM, strong wake effect through midday and into the afternoon, and a tail that is still active at 10 PM. Taking the dose at noon instead pushes the active tail into 3 AM and reliably ruins the next night. Taking the dose at 4 PM, which some people do when they forget the morning tablet, makes the following night nearly impossible to sleep through.
Steady state is reached in 2 to 4 days on daily dosing. The first day of a new Modaheal prescription usually feels like a lighter version of the effect you will have by day three or four. For patients weighing a dose change, the clinician usually waits one week on a new dose before deciding whether the response is stable.
💊 Modaheal 200 mg and the Standard Adult Dose
The Modaheal 200 mg tablet is the single available strength from Healing Pharma. The adult standard dose is one tablet in the morning, taken with water, with or without food. This dose is the one established in the US registration trials and is the dose recommended by most sleep medicine clinicians for a healthy adult with narcolepsy or OSA residual sleepiness.
The dose logic rests on two numbers. The minimum effective dose for most adults is roughly 100 mg; below that the wake-promoting effect is small. The peak useful dose for most adults is 200 mg; above that the extra alertness per extra milligram starts to level off, and the side-effect rate rises faster than the benefit. Doubling to 400 mg has evidence of extra benefit for only a minority of patients and almost always doubles the headache, insomnia and blood pressure signal.
| 💊 Daily dose | Typical patient | Comments |
|---|---|---|
| 100 mg (half tablet) | Older adults, hepatic impairment, slow metabolisers, side-effect sensitivity | Starting point when caution is warranted |
| 200 mg (one tablet) | Standard adult daily dose | The established FDA target for narcolepsy and OSA residual sleepiness |
| 400 mg (two tablets) | Severe narcolepsy with inadequate response at 200 mg | Split-dose option: 200 mg at 7 AM plus 200 mg at noon |
| Beyond 400 mg | Rare, specialist decision only | Side effects dominate; evidence of extra benefit is thin |
The Modaheal tablet is scored, meaning it has a central line that allows splitting into two 100 mg halves with a pill cutter or a sharp knife. A half tablet is appropriate for a starting dose in an older or sensitive patient, and splitting is a reasonable way to confirm tolerability before committing to the full dose. Full 200 mg once daily is the default once tolerability is confirmed in the first week.
💡 First-week plan on a new Modaheal prescription
Day 1-2: 100 mg at 7-8 AM (half tablet). Record how long the wake effect lasts, any headache or insomnia.
Day 3-7: if tolerated, move to 200 mg at 7-8 AM. Track any blood pressure or heart rate change, mood, and sleep that night.
Week 2: if the wake effect is good and side effects are tolerable, continue 200 mg once daily. If the effect is weak after a full week on 200 mg and no side effects limit, discuss a dose increase with the clinician.
If insomnia appears: move the dose earlier, not lower. The target is a dose taken no later than 10 AM.
If headache dominates: this is the most common first-week side effect; usually fades by day 5. Hydration and a mild analgesic help.
The split-dose option for severe narcolepsy is 200 mg at 7 AM plus a second 200 mg at noon. The second dose must not drift later than noon or sleep that night suffers. Split dosing is used when a single morning 200 mg provides good morning alertness that fades by early afternoon; adding a second 200 mg extends the useful window into evening without a bedtime hit, as long as the second dose stays before 1 PM.
Missed doses are a common question. If the morning dose is forgotten and recognised by 10 AM, take it. If the forgetting is noticed at noon or later, skip the dose for that day and take the normal morning dose the next day. Doubling the dose the next morning to compensate is not useful and raises side effects.
Running out of Modaheal is more disruptive than it sounds. The next day after a missed dose, the sleep debt from your underlying condition shows up at full strength. Set a 7-day refill reminder on your phone and keep a 2-day backup in the bag you travel with. The pharmacy refill for a Schedule IV drug can take longer than you expect, especially around holidays.
🧪 When To Start At 100 mg Instead of 200 mg
Three groups benefit from starting on the half tablet (100 mg) rather than the full 200 mg. The groups overlap in practice, so the right starting dose is the result of looking at the patient as a whole rather than following a single rule. The savings here are not just a matter of smaller side effects; it is also about catching poor tolerance early and switching before day three turns miserable.
🟡 Who may clear modafinil slowly
Older adults over 65 — hepatic clearance is lower; plasma levels run about 20 percent higher at the same dose.
Patients with moderate or severe liver disease — standard practice halves the dose; a 100 mg start is the way to confirm tolerance.
Underweight adults under 55 kg — absolute exposure runs higher per kilogram; side-effect risk rises.
CYP2C19 poor metabolisers — about 2 to 5 percent of white and 15 to 20 percent of East Asian populations clear modafinil much more slowly; higher plasma levels, more insomnia and headache.
Patients on other CYP3A4 inhibitors — ketoconazole, erythromycin, clarithromycin, and some HIV protease inhibitors raise modafinil blood levels further.
Patients with a history of anxiety or sleep-onset insomnia — even in a healthy liver, these patients tend to feel the 200 mg dose more sharply.
Older adults deserve particular attention. Narcolepsy and OSA do not spare people over 65, and the eugeroic class is well suited to the usual geriatric worries because modafinil does not cause classical anticholinergic side effects, does not fall into the Beers Criteria for inappropriate medications, and does not noticeably impair memory or balance. The caution is specifically about plasma exposure: 100 mg will often produce the same wake effect in a 72-year-old that 200 mg produces in a 42-year-old.
The CYP2C19 poor metaboliser phenotype is one of the few genetic facts worth mentioning here. Carriers of two reduced-function CYP2C19 variants metabolise modafinil much more slowly, which raises plasma levels by about 30 to 50 percent for the same tablet. The clinical signal is that these patients feel more side effects at 200 mg than most people. If a patient has had a formal pharmacogenomic test (common when they are also on clopidogrel or voriconazole), the result is useful; otherwise the clinical approach is simply to start low and watch for the pattern.
The practical workflow in a slow metaboliser is a conservative two-step. Week 1: 100 mg at 7 AM. If the wake effect is clearly present and side effects are mild, this may be the maintenance dose. Week 2: if the wake effect is lacking and nothing is intolerable, the second week moves to 200 mg at 7 AM. If side effects appear during the second week, drop back to 100 mg permanently. Many slow metabolisers settle on 100 mg long term, which is a legitimate maintenance dose.
Children are a different question entirely. Modafinil is not approved under age 17 in the United States. The FDA received reports of serious skin reactions including Stevens-Johnson Syndrome in paediatric trials in the late 2000s, which closed off a paediatric indication. Off-label use in children happens occasionally for severe narcolepsy under specialist supervision, but it is not routine, and the risk-benefit discussion is heavier than in adults.
The last practical note: if 100 mg produces a flat response in a slow metaboliser, waiting 7 to 10 days before escalating to 200 mg gives time for steady state. Jumping to the full dose on day three because day one felt flat is the single most common reason people end up with side effects they did not need to have.
🌅 Why Modaheal Must Be Taken Before 10 AM
Modaheal is best taken no later than 10 AM for most adults. The reason is not pharmacology for its own sake. It is the sleep-debt trap: the drug extends your wakefulness window into the evening, but it does not reduce the sleep debt you have already accumulated. If you push the next bedtime later and later while on modafinil, the debt grows, the drug cannot fully cover it the next day, and you end up in a slow slide into chronic fatigue that no eugeroic can rescue.
Think of the dose timing as a wake-promoting window that lasts about 10 to 12 hours past peak. A 7 AM dose keeps you alert until 7 to 9 PM comfortably, with the natural drowsy signal taking over by 10 to 11 PM for sleep. A 9 AM dose keeps you alert until 9 to 11 PM, which can still fit a normal bedtime. A noon dose pushes the active tail to midnight or 2 AM.
The second half of the trap is cumulative. Modafinil does not repay sleep debt the way sleep does. If you push 3 or 4 nights in a row by 2 or 3 hours each, your underlying fatigue climbs even while your daily alertness feels fine. Then on the day you miss a dose, or stop the drug, you fall into a pit the drug was holding you above. This is a slow pattern that often goes unnoticed in people who use modafinil for work rather than for a sleep diagnosis.
⚠️ How the sleep-debt trap builds
Monday: you dose at 7 AM, feel alert until 10 PM, go to bed, sleep 7 hours.
Tuesday: you dose at 7 AM, stay up to midnight for a project, sleep 6 hours.
Wednesday: you dose at 7 AM, feel sharp enough, finish at 1 AM, sleep 5 hours.
Thursday: you dose at 7 AM, feel OK, keep pushing, sleep 5 hours.
Friday: you take a day off from modafinil to catch up, and feel much worse than any day since Monday because the debt is now 12 hours deep.
The fix is to keep bedtime stable even on modafinil, and treat the drug as covering your underlying sleep disorder, not your working hours.
If late dosing has already pushed your sleep into shambles, the correction takes a few days. Move the dose on the following day back to 7 AM. Resist stretching the next evening. Accept 1 or 2 slightly groggy mornings as the price of resetting. By day three the sleep pattern usually stabilises again. A short course of a sedating sleep aid (such as melatonin or doxylamine) in those catch-up nights is reasonable for 2 to 3 nights only, not a long-term pairing with modafinil.
Shift workers deserve different timing rules, covered in section 11. The 10 AM cutoff applies to day workers on a conventional schedule. A night worker doses before the shift begins, which may be 10 PM or 2 AM, and uses sleep-protection tactics during the daytime off period.
A simple rule: Modaheal makes the day longer, it does not make the night optional. The patients who stay well on this drug for years are the ones who respect that trade. The ones who crash hard in month three are the ones who ignored it.
📋 Modafinil Approved Uses and Where Off-Label Begins
Modafinil has three FDA-approved indications in the United States and a long list of off-label uses that range from well-supported to speculative. The approved indications are backed by randomized controlled trials and formal regulatory review. The off-label uses sit on a spectrum from reasonable (MS fatigue, depression augmentation) to thin evidence (ADHD, jet lag) to unsupported (student stimulant, routine shift extension).
| 📋 Indication | Status | Evidence level |
|---|---|---|
| Narcolepsy | FDA approved (1998) | First-line in AASM 2021 guideline |
| OSA with residual sleepiness on CPAP | FDA approved (2003) | Add-on only; not a substitute for CPAP |
| Shift work sleep disorder | FDA approved (2004) | Documented formal diagnosis required |
| Multiple sclerosis fatigue | Off-label, reasonable evidence | Rammohan 2002, several follow-ups |
| Depression augmentation | Off-label, mixed evidence | Several small trials; signal mild |
| Fatigue in cancer patients on treatment | Off-label, mixed evidence | Oncology society guidance split |
| Adult ADHD | Off-label, thin evidence | Not first-line; stimulants and atomoxetine come first |
| Jet lag or occasional sleep deprivation | Off-label, thin evidence | Military use documented; civilian use rarely a good idea |
| Lifestyle use for study or long work hours | Not approved | Health risks and dependence outweigh any benefit |
| Weight loss | Not approved | Appetite suppression is mild and not clinically useful |
The three approved indications are:
Narcolepsy is the primary indication. The condition involves sudden daytime sleep attacks, often with cataplexy (muscle weakness triggered by emotion in type 1), sleep paralysis, hypnagogic hallucinations and disrupted night-time sleep. Modafinil treats the daytime sleepiness, not the cataplexy. The US registration trial covered 283 narcolepsy patients and showed a mean sleep latency improvement of about 2 to 3 minutes on the maintenance of wakefulness test.
Obstructive sleep apnea with residual daytime sleepiness is the second indication. The condition itself is a repeated collapse of the upper airway during sleep, causing hundreds of micro-arousals a night. The main treatment is CPAP (continuous positive airway pressure). About 12 to 15 percent of CPAP-adherent patients still feel sleepy during the day, and modafinil is added for them. The crucial boundary: modafinil is not a replacement for CPAP, which treats the underlying airway closure and prevents the cardiovascular and metabolic consequences of OSA.
Shift work sleep disorder is the third indication. The condition is a formal diagnosis requiring documented chronic insomnia or excessive sleepiness linked to a non-standard work schedule. The 2004 approval was based on 209 patients in the Czeisler NEJM study. The real-world use is tighter than the broader concept of shift fatigue: a formal diagnosis is expected before modafinil is prescribed, not just a label of someone who works nights.
Section 12 and 13 of this guide go deeper on the off-label uses with real evidence (MS, depression, cancer fatigue) and the off-label uses without (student stimulant, routine jet lag, long work shifts without a diagnosis). The current section establishes the frame: modafinil has a narrow approved zone, a modest off-label zone with reasonable evidence, and a wide zone of use that is popular but not justified.
😴 Narcolepsy Treatment With Modaheal and What To Expect
Narcolepsy is a chronic neurological disorder of the wake-sleep boundary. The brain cannot keep itself stably awake during the day, cannot stay stably asleep at night, and intrudes rapid-eye-movement sleep elements (dreaming, muscle paralysis, vivid imagery) into the waking state. It affects about 1 in 2,000 people and typically starts in the teens or twenties. Modaheal does not cure narcolepsy, but it reliably raises daytime alertness to a level where school, work and driving become possible.
Two forms exist. Narcolepsy type 1 is caused by autoimmune destruction of orexin neurons in the lateral hypothalamus. These patients have severe daytime sleepiness, cataplexy (muscle weakness triggered by emotion, especially laughter), sleep paralysis and hypnagogic hallucinations. Narcolepsy type 2 has the sleepiness without cataplexy; the mechanism is less clearly defined but likely overlaps with partial orexin loss.
💬 Expert view
Prof. Michael Thorpy, Albert Einstein College of Medicine, AASM 2021 narcolepsy guideline co-author: Modafinil treats the daytime sleepiness of narcolepsy well. It does not treat cataplexy, hypnagogic hallucinations or sleep paralysis. For narcolepsy type 1, modafinil is a step-one wake-promoting agent, but the patient almost always needs a second drug for cataplexy — sodium oxybate at night, or pitolisant, or an SSRI. Expecting modafinil alone to control type 1 narcolepsy is the single most common prescribing error in the first year after diagnosis.
What a patient should expect from the first 4 weeks on Modaheal for narcolepsy: by day 3-5 the morning sleepiness is noticeably better; by week 2 the Epworth Sleepiness Scale score (a 0-to-24 self-rating of likelihood of falling asleep in common situations) usually drops by 3-5 points; by week 4 the clinical response is stable and the dose decision is made. In the registration trial, the mean MWT (Maintenance of Wakefulness Test) latency improved by about 2 to 3 minutes on 200 mg daily, which is modest in absolute terms but a visible shift in daily function.
| Narcolepsy symptom | Does Modaheal help? | Second-line drugs if needed |
|---|---|---|
| Excessive daytime sleepiness | Yes, main indication | Pitolisant, solriamfetol, sodium oxybate |
| Cataplexy | No, add a cataplexy drug | Sodium oxybate, pitolisant, SSRIs, SNRIs, clomipramine |
| Sleep paralysis | Partial, mainly through reduced REM intrusion | SSRIs, sleep schedule tightening |
| Hypnagogic hallucinations | Partial | SSRIs |
| Disrupted night sleep | Modaheal does not help; may worsen if dosed late | Sodium oxybate at bedtime |
Driving is where narcolepsy treatment pays off most visibly. Untreated narcolepsy raises crash risk roughly 3 to 4 times above the general population. On Modaheal with good control, the risk drops close to baseline but does not reach zero. Patients should not drive long distances alone until the response is stable at week 4, and should pull over for a 20-minute nap at the first sign of nodding off even on a well-adjusted dose.
Scheduled daytime naps are not optional. The current standard is a planned 20-minute nap once or twice a day, even in a well-controlled patient on 200 mg. The nap discharges some sleep pressure and reduces the need for a higher Modaheal dose. The AASM guideline makes this explicit: naps and medication together outperform either alone.
Long-term outcomes are reasonable. With good adherence to Modaheal plus naps plus a cataplexy drug when needed, most adults with narcolepsy function in work, parenting and driving at close to normal daily capacity. The disease is lifelong and the medication is lifelong. Short holidays off the drug are possible when the schedule allows a lot of napping (long holidays at home) but should not be routine without a clinician agreeing.
🌬️ Modaheal for OSA Residual Sleepiness on CPAP
Obstructive sleep apnea is caused by repeated collapse of the upper airway during sleep. The patient stops breathing for 10 to 30 seconds, their oxygen drops, the brain partially wakes to restart the breath, and the cycle repeats hundreds of times across the night. The result is destroyed sleep architecture even when the patient is in bed for 8 hours. Treatment is CPAP — continuous positive airway pressure — which keeps the airway open with a steady air stream through a mask.
Most patients on good CPAP therapy feel dramatically better within weeks. But about 12 to 15 percent continue to feel sleepy during the day despite verified CPAP adherence and resolution of the apneas on the device data. These patients have what is called residual sleepiness, and this is where Modaheal has an FDA-approved role as an add-on, following the Pack 2001 trial of 157 OSA patients.
🚨 Modaheal does not replace CPAP in OSA
Modafinil treats the symptom of sleepiness. CPAP treats the underlying airway closure that causes the cardiovascular, metabolic and cognitive consequences of OSA. Taking Modaheal to feel awake while skipping CPAP leaves stroke, heart failure, hypertension and sudden death risk at the untreated OSA baseline. The 2003 FDA approval is explicit: modafinil is for residual sleepiness in CPAP-adherent patients, not in CPAP-refusers.
What "CPAP-adherent" means in practice: the patient uses the device at least 4 hours per night on at least 70 percent of nights, and the modem data shows the apnea-hypopnea index corrected to under 5 events per hour. Only after this threshold is met is modafinil appropriate. Clinicians generally require two to three months of documented CPAP use before adding modafinil, because many patients who seem to have residual sleepiness are actually missing nights or using the device for only part of the night.
Dosing in OSA is 200 mg once daily in the morning, same as narcolepsy. Response is usually visible within a week: average Epworth Sleepiness Scale improvement is 3 to 4 points on 200 mg. If 200 mg is inadequate after 2 to 3 weeks of stable use, the next step is usually to recheck CPAP adherence and look for other causes of sleepiness before escalating the modafinil dose.
🔎 Causes of residual sleepiness that modafinil will not fix
CPAP non-adherence — by far the most common. Check the device modem data first.
Mask leak — the AHI number can read low while the air pressure in the airway is actually not reaching therapeutic levels.
Insufficient sleep time — a 6-hour night even on perfect CPAP leaves sleep debt behind.
Chronic alcohol use — alcohol damages sleep architecture independent of CPAP.
Hypothyroidism — untreated low thyroid produces fatigue that overlaps with sleep apnea.
Depression — low mood with fatigue is a separate problem; modafinil is sometimes used off-label for this but is not the first-line approach.
European regulators took a different view. In 2011, the EMA restricted modafinil in Europe to narcolepsy only, removing both OSA residual sleepiness and shift work indications. The reason given was a benefit-risk reassessment: for the OSA indication, the regulator judged the benefit modest and the cardiovascular and psychiatric risks poorly characterised. European OSA patients with residual sleepiness are therefore less likely to be on modafinil than their North American counterparts; alternatives such as solriamfetol are more commonly used.
Many OSA patients taking Modaheal start to feel so much better that CPAP adherence slips, and some stop CPAP altogether. This is the single most dangerous pattern on this prescription. Any OSA patient on Modaheal should keep CPAP adherence under monthly review with the device data; if adherence falls below the 70 percent threshold, the modafinil should be reconsidered rather than continuing to mask a worsening underlying problem.
🌙 Shift Work Disorder and Modaheal Dose Timing
Shift work sleep disorder is a formal diagnosis in the International Classification of Sleep Disorders. Not everyone who works nights has it. The diagnosis requires at least three months of insomnia or excessive sleepiness tied to a non-standard work schedule, with the symptoms resolving when the schedule changes. The patient usually keeps a sleep diary and sometimes a formal sleep study documents the pattern.
Modaheal is approved for this diagnosis in the US, based on the Czeisler NEJM 2005 trial of 209 patients who worked at least 5 night shifts a month. The patients on modafinil 200 mg taken an hour before the shift showed reduced extreme sleepiness during the shift and better performance on a driving simulator at the end of the shift. The effect was clinically modest but statistically clear.
Timing is unusual for this indication because the workday starts at night. The dose is taken roughly one hour before the start of the shift, which may be 10 PM for a 11 PM-to-7 AM shift, or 7 PM for an 8 PM start. Peak plasma arrives 2 to 4 hours into the shift, which covers the worst sleepiness period usually around 2 to 4 AM.
💬 Expert view
Prof. David Dinges, University of Pennsylvania, sustained-wakefulness research lead: Modafinil improves alertness during a night shift but does not restore full daytime function. A worker on modafinil during an 11 PM to 7 AM shift still has impaired reaction time and judgment in the first 90 minutes after shift end, especially during the drive home. The drug makes the shift workable; the drive home is still the most dangerous part of the day for a night-shift worker, and no dose of modafinil fixes that. Napping before the shift and avoiding the morning commute drive when alone are the controls that matter.
Sleep protection during the day is the other half of this treatment. A night-shift worker on Modaheal needs to sleep during the daytime hours after the shift, which fights the natural circadian wake drive. Blackout curtains, a cool bedroom (18-19 degrees Celsius), a white-noise machine, no caffeine after midpoint of the shift, and a disciplined bedtime of 8-10 AM are the usual tools. Even with these, most people get only 5 to 6 hours of daytime sleep, which is less than the 7+ hours they would get at night.
Rotating shifts complicate the picture. If the schedule rotates between day and night in the same week, modafinil can be used only on the night-shift days, taken the standard 1 hour before shift start. On day-shift days, the standard morning dosing timing applies. Patients on week-long rotating schedules sometimes find that modafinil only on scheduled night shifts fits their life better than continuous daily use.
Not every tired night worker needs Modaheal. Lifestyle adjustments first — blackout curtains, consistent sleep schedule even on days off, limiting caffeine in the second half of the shift, strategic 20-minute pre-shift naps — resolve most shift-related fatigue in otherwise healthy adults. Modaheal is correct when the formal diagnosis is made and lifestyle adjustments have been tried and are not enough.
Military and emergency responders have their own protocols using modafinil for sustained operations beyond 24 hours. These protocols use modafinil at 200 mg every 15 to 20 hours and are not meant for civilian daily use. The Dinges operational studies that defined these protocols were run under medical supervision in sleep laboratories; copying the dosing pattern for a long work week at home is not safe.
📑 Off-Label Modafinil Uses With Reasonable Evidence
Modafinil has three off-label uses with reasonable published evidence: multiple sclerosis fatigue, depression augmentation when first-line antidepressants have failed, and fatigue in some cancer-treatment settings. None of these are FDA-approved, but clinicians in the relevant specialties use modafinil in these settings based on specific trials and observational data.
Multiple sclerosis fatigue is the strongest off-label indication. Rammohan et al. (J Neurol Neurosurg Psychiatry 2002;72:179-183) ran a 9-week placebo-controlled trial in 72 MS patients. Modafinil 200 mg significantly reduced fatigue scores. Follow-up trials have been mixed but the signal has held across several meta-analyses. The MS fatigue population is large, the condition is debilitating, and no better oral treatment exists; modafinil is often added at MS specialty centres when fatigue dominates the clinical picture.
| Off-label use | Trial evidence | When clinicians consider it |
|---|---|---|
| MS fatigue | Rammohan 2002 plus several follow-ups | After amantadine trial, when fatigue dominates |
| Depression augmentation | DeBattista 2003; small positive signal in treatment-resistant cases | After SSRI/SNRI failure in patients with residual fatigue |
| Cancer-related fatigue | Cochrane 2015 mixed; some positive trials in opioid-related sedation | Palliative care; opioid-related sedation |
| Parkinson disease sleepiness | Several small trials; mixed | When daytime sleepiness persists after dopaminergic dose adjustment |
| Idiopathic hypersomnia | Pre-newer-drug data; now second-line to pitolisant and sodium oxybate | Specialist decision |
Depression augmentation is a narrow use case. DeBattista et al. (J Clin Psychopharmacol 2003;23:60-62) ran a 6-week open-label trial of modafinil added to SSRIs in 35 patients with residual fatigue and sleepiness despite antidepressant treatment. The response rate for the fatigue component was high. Larger randomized data have been mixed, and the signal is specifically for the fatigue and attention component of depression, not for depressed mood itself. Psychiatrists reserve modafinil for cases where fatigue dominates after SSRIs have improved mood.
Cancer-related fatigue is a split issue. A 2015 Cochrane review of modafinil for cancer-related fatigue concluded that the overall evidence does not support routine use, but subgroup analyses show benefit in opioid-related sedation and in patients with severe fatigue scores. In palliative care, where patients want awake hours for family time rather than long-term survival benefit, modafinil 100-200 mg daily is sometimes added to a stable opioid regimen with good patient-reported outcomes.
💡 What to expect in off-label use
Off-label modafinil is not covered by many insurance plans, so the patient may need to pay out of pocket. Response rates are lower than in approved indications: a 60-70 percent response rate for narcolepsy drops to perhaps 40 percent for MS fatigue and lower for depression. The side-effect profile is the same. If 200 mg produces no visible change in 2 to 3 weeks of use for an off-label indication, continuing is unlikely to pay off.
Parkinson disease daytime sleepiness has mixed evidence. The main concern is that Parkinson sleepiness often comes from the dopaminergic medications used to treat the movement disorder (ropinirole, pramipexole, levodopa) rather than from the disease itself. Adjusting the Parkinson regimen comes first. If sleepiness persists after that, modafinil can be considered but rarely changes the picture dramatically.
Idiopathic hypersomnia is a rare but distressing condition of long sleep and sleep inertia with no apnea or orexin loss. Modafinil was long the standard treatment, but newer drugs including low-sodium oxybate (Xywav) have gained approval specifically for idiopathic hypersomnia. Modafinil remains in use but is no longer first-line in centres that have access to the newer agent.
Across all off-label uses, the standard caveats apply. Hormonal contraceptive risk, Stevens-Johnson Syndrome risk, Schedule IV status, dependence potential and the cardiovascular signal are the same off-label as on-label. The drug does not become safer just because the indication is informal.
🚫 Off-Label Modafinil Uses Without Good Evidence
Many off-label modafinil uses have no reasonable evidence behind them, despite popularity. The gap between what people take modafinil for and what the drug has been shown to help is wide. This section covers the most common unsupported uses and the reasons they do not work out.
🚫 Common unsupported modafinil uses
- Study aid for healthy students — cognitive effects in healthy adults are small and not reliable
- Long work days without a sleep diagnosis — builds sleep debt, dependence risk over months
- Jet lag for occasional travellers — melatonin and schedule shifting work better
- Weight loss — appetite effect is too mild to matter
- General fatigue in healthy adults — usually has a non-pharmacologic fix
- Pre-game stimulant for athletes — banned by WADA (World Anti-Doping Agency), tests catch it
- Social anxiety or energy for events — can actually worsen anxiety in sensitive users
The student stimulant story is the most researched. Minzenberg and Carter (Neuropsychopharmacology 2008) systematically reviewed modafinil cognitive effects in healthy volunteers. The findings were mixed. Working memory and reaction time showed small improvements under sleep deprivation; under rested conditions, improvements were inconsistent across tasks. Studies in students specifically have not shown that modafinil produces better exam scores or faster essay writing in rested young adults. The subjective feeling of enhanced focus is real, but it does not translate into measurable better work.
Worse, students using modafinil usually overlap it with sleep restriction. A student taking modafinil to study until 2 AM is building sleep debt that lowers next-day memory consolidation, which is the opposite of what good exam performance needs. Memory formation happens during sleep. Trading sleep for drug-assisted study hours is a worse trade than it feels.
Long work days without a diagnosis are a different trap. A healthy adult who takes modafinil to work 14 hours a day for several weeks slides into dependence: tolerance to the drug does develop with daily use over months, sleep architecture deteriorates, and the person then needs modafinil just to feel baseline normal in the morning. This is the pattern that most often ends in a clinic visit asking for help getting off the drug.
⚠️ Modafinil for jet lag — why it rarely helps
Jet lag is a circadian misalignment problem. The traveler goes to bed with their internal clock set to the old time zone and the environmental cues set to the new one. The fix is circadian realignment: timed exposure to bright light in the morning of the new zone, melatonin at the new-zone bedtime, and schedule discipline for the first 3 days. Modafinil can mask daytime sleepiness during the first 2 days of the trip, but it does not shift the clock. For most civilian travellers, the melatonin and light approach works better and has no controlled-substance paperwork.
Athletic use is firmly off-limits. Modafinil has been banned by the World Anti-Doping Agency since 2004 and is detected by routine testing. Cyclists Rutger Beke and Kelli White and sprinter Dwain Chambers all received competition bans for modafinil. The ban is both for the direct stimulant effect and because modafinil masks fatigue that would otherwise signal overtraining. Athletes under drug-testing protocols should not take modafinil even for a legitimate medical indication without a therapeutic use exemption.
For general fatigue in healthy adults, the first-line approach is almost always non-drug: sleep hygiene, iron and thyroid checks, screen for depression, review alcohol intake. Chronic fatigue in a healthy adult that resists these approaches deserves a clinical workup, not a prescription for a controlled substance.
Social anxiety and energy for events are the subtlest misuses. Modafinil can lift mood briefly, which some patients confuse with reduced anxiety. The glutamate-up GABA-down shift in the brain can actually raise social anxiety in sensitive people. The post-event crash is more pronounced when the drug was taken for an elective purpose than for a diagnosed sleep problem.
🧬 Modafinil vs Armodafinil - The R-Enantiomer Choice
Modafinil is a racemic mixture of two mirror-image molecules: R-modafinil and S-modafinil. The two look identical by chemical formula but orient differently in three-dimensional space, which changes how enzymes clear them. In 2007, the FDA approved armodafinil (Nuvigil), which is pure R-modafinil, as a separate product. The marketing argument was that the R-enantiomer provides a longer, steadier effect. The pharmacology is more interesting than the marketing suggests.
The pharmacokinetic difference is real but modest. Racemic modafinil 200 mg produces a plasma curve with a sharper early peak (from the S-component) and a long tail (from the R-component). Armodafinil 150 mg contains only the long-tail component, so the plasma curve is flatter and the afternoon peak is slightly later. In practice, this means some patients notice less of a mid-afternoon dip on armodafinil compared with racemic modafinil.
The clinical difference is small. Head-to-head trials have found armodafinil 150 mg roughly equivalent to modafinil 200 mg in both narcolepsy and OSA residual sleepiness. The Food and Drug Administration approved armodafinil as a separate product because it is a different molecule, not because it works better. Insurance in the United States often prefers the generic modafinil for cost reasons.
| 🧬 Feature | Modafinil (racemic) | Armodafinil (R only) |
|---|---|---|
| Available strengths | 100, 200 mg | 50, 150, 200, 250 mg |
| Standard adult dose | 200 mg once daily | 150 or 250 mg once daily |
| Plasma peak timing | 2-4 h | 2-6 h (slightly later) |
| Plasma curve shape | Sharper early rise, longer tail | Flatter, more sustained plateau |
| Afternoon dip | Possible around 3-5 PM | Often less pronounced |
| Side effect rate | Standard profile | Similar; subjectively slightly cleaner for some |
| Monthly cost (US) | Lower, generic widely available | Higher; generic armodafinil available but less competitive |
Which should you take? The default is Modaheal (racemic modafinil 200 mg) because cost, availability and track record are better. Switch to armodafinil only if:
- the afternoon dip on modafinil 200 mg is a real problem and increasing the dose or splitting is not working; or
- the patient has had unusual difficulty with the early peak on modafinil, like a brief jittery feeling at 10 AM followed by a flat afternoon; or
- insurance happens to cover armodafinil better than modafinil (unusual but possible).
Switching between modafinil and armodafinil is straightforward. The dose equivalence is approximately modafinil 200 mg = armodafinil 150 mg, and modafinil 400 mg = armodafinil 250 mg. The switch takes effect from day one; no tapering or washout is needed.
A note on supply. Modafinil has been more consistently available worldwide than armodafinil, and when supply shortages hit (as they did in 2026 for some generic suppliers), switching to the available enantiomer is a reasonable short-term solution rather than going without wake-promoting treatment entirely.
⚖️ Modafinil vs Amphetamine Side By Side
Patients and clinicians often weigh modafinil against the amphetamine stimulants — dextroamphetamine (Dexedrine), mixed amphetamine salts (Adderall) and methylphenidate (Ritalin, Concerta). The comparison is important because the amphetamine class is the main alternative for daytime sleepiness, and the choice between them is not purely about effectiveness. It is about risk profile, controlled-substance scheduling and side-effect pattern.
| ⚖️ Dimension | Modaheal (modafinil) | Amphetamines |
|---|---|---|
| Wake-promoting strength | Moderate; raises alertness floor | Strong; adds drive and arousal |
| Narcolepsy evidence | First-line in AASM 2021 guideline | Also first-line; some patients respond better |
| Cardiovascular effect | Small BP and HR rise | Larger rise, more cardiac concern |
| Appetite | Mild suppression | Significant suppression |
| Dependence risk | Lower; Schedule IV | Higher; Schedule II |
| Euphoria at labelled dose | Rare | Common; part of drug attraction |
| Crash on wearing off | Mild fade | Often sharp and uncomfortable |
| Prescription paperwork | Schedule IV; monthly refills possible | Schedule II; new prescription each month |
| Hormonal contraceptive | Reduces effectiveness; backup needed | No interaction |
| Psychiatric history concerns | Mild; rare psychiatric signals | Significant; mania, psychosis risk |
For a patient with narcolepsy and no cardiovascular disease, both modafinil and amphetamines are first-line options. The choice usually goes to modafinil first because the side-effect profile is quieter and the Schedule IV paperwork is lighter. Amphetamines come in if modafinil 200 mg plus naps are not enough.
For a patient with any cardiovascular disease, hypertension not fully controlled, or a history of cardiac arrhythmia, modafinil is strongly preferred. The amphetamine-driven heart rate and blood pressure rise can tip these patients into bad territory, especially during the first weeks of a new prescription.
For a patient with a history of substance use disorder, the Schedule IV status of modafinil is a real but incomplete safety advantage. Some patients with past amphetamine abuse find modafinil "feels like nothing" and tolerate it well; others find the subtle reward signal of modafinil enough to re-trigger old patterns. A clinician familiar with the patient history should make this call, not a self-assessment.
🧭 Which drug for which patient profile
First choice modafinil: cardiovascular disease, hypertension, anxiety-prone, work schedule needing a 10-hour steady effect, insurance covers modafinil generic, no amphetamine history.
First choice amphetamine: severe narcolepsy failing modafinil 200 mg plus naps, ADHD plus narcolepsy comorbidity, patient explicitly needs the energetic feel of a classical stimulant.
Both viable: uncomplicated narcolepsy in a young adult without comorbidities — the choice can rest on patient preference and cost.
Neither suitable: active substance use disorder with current amphetamine or cocaine use; untreated severe hypertension; pregnancy.
Switching between modafinil and amphetamine is not a direct substitution. The dose equivalence is approximate at best. A typical switch from modafinil 200 mg goes to amphetamine salts 10-20 mg in the morning; from methylphenidate 20-40 mg long-acting. The clinician usually overlaps for 1-2 days or does a straight swap, with the patient tracking the response for the first week.
Combining modafinil and amphetamine is not a routine strategy, but it happens occasionally in severe narcolepsy that fails both as monotherapy. The combination is a specialist decision and comes with stacked cardiovascular and psychiatric risk.
🛑 Modaheal and Hormonal Contraception Critical Warning
The single most important drug interaction for Modaheal is with hormonal contraception. Modafinil induces a liver enzyme called CYP3A4, which breaks down most hormonal contraceptive agents. The result is reduced contraceptive effectiveness, with pregnancy rates in women using combined oral contraceptive pills while on modafinil estimated to be two to three times higher than in non-modafinil users on the same pills.
This affects:
- Combined oral contraceptive pills (estrogen + progestin)
- Progestin-only pills ("mini-pill")
- Contraceptive patch
- Vaginal contraceptive ring
- Hormonal implants (etonogestrel implant, Nexplanon)
- Emergency contraceptive pills (levonorgestrel; ulipristal partially affected)
Not affected:
- Copper intrauterine device (IUD) — non-hormonal, works mechanically
- Hormonal IUD (levonorgestrel-releasing, Mirena, Kyleena) — local hormone release, systemic levels low, interaction minimal
- Depot medroxyprogesterone injection — given as deep injection every 3 months, interaction minimal
- Barrier methods (condom, diaphragm, cervical cap)
- Fertility awareness and sterilisation
💬 Expert view
Prof. Yves Dauvilliers, Montpellier University Hospital, National Reference Centre for Narcolepsy, France: A woman of reproductive age starting modafinil must be told at the first visit that her oral pill is now unreliable. The best substitute is a copper or levonorgestrel IUD, placed before modafinil is started where possible. If an IUD is not acceptable, dual methods — pill plus condom — are the minimum. This conversation is as important as the dosing conversation and should happen at the same visit, not later.
The interaction continues for at least one month after stopping modafinil. The enzyme induction takes 1 to 2 weeks to build up and 2 to 4 weeks to resolve after the last dose. So a woman who stops modafinil cannot reliably return to her oral pill on day one; she needs backup contraception for a month after the last tablet.
⛔ Minimum contraception if continuing hormonal methods on modafinil
Dual methods: continue the oral or patch contraceptive, and add a condom at every intercourse. This is the explicit FDA label guidance and the Dauvilliers clinic protocol. A single method of hormonal contraception on modafinil carries an unacceptable pregnancy risk for most patients. The safer long-term solution is to switch to a copper IUD or a hormonal IUD, which keep working regardless of CYP3A4 induction.
Emergency contraception is a specific concern. If a woman on modafinil has unprotected intercourse, standard levonorgestrel emergency pills (Plan B, over-the-counter) are less reliable because of the same CYP3A4 induction. Options in order of effectiveness:
- A copper IUD inserted within 5 days of the unprotected intercourse is the most reliable emergency contraception on modafinil and does not depend on hormone metabolism.
- Ulipristal acetate (ella) is less affected by CYP3A4 induction than levonorgestrel but is partially reduced; still works better than levonorgestrel on modafinil.
- A double dose of levonorgestrel (3 mg instead of standard 1.5 mg) is sometimes recommended on CYP inducers, including by some European guidelines, though the US label does not endorse this approach.
Perimenopausal women deserve attention here. The decline in natural fertility starts in the mid-forties, but it is not reliable until menstruation has fully stopped for 12 months. A woman in her late forties on modafinil cannot assume she is infertile. The same contraception rules apply as for younger women; the interaction with hormonal methods is the same.
Men on modafinil who want to father a child are not affected by the contraceptive interaction directly, but should be aware that their female partners on hormonal pills while they are not may be at elevated unplanned-pregnancy risk if either partner was previously relying on the pill. This is a counselling moment that often gets missed.
🔐 Modafinil Schedule IV What The Classification Means
Modafinil was listed as a Schedule IV controlled substance by the US Drug Enforcement Administration in 1999, one year after FDA approval. Schedule IV is the second-least restrictive category of controlled drugs, below Schedule II (where amphetamines sit) and above Schedule V (where some cough preparations sit). The classification signals low to moderate potential for dependence and recognises a legitimate medical use.
What the schedule means in practice:
| Rule | Modafinil Schedule IV | Amphetamine Schedule II |
|---|---|---|
| Written prescription | Required | Required |
| Refills allowed on one prescription | Up to 5 refills within 6 months | No refills; new prescription each time |
| Telephoned or faxed prescription | Allowed | Not allowed in US |
| Carry across US state lines | Allowed with valid prescription label | Allowed with valid prescription label |
| International travel | Varies by country; may require documentation | Many countries ban import entirely |
| Pharmacy tracking | Logged in state Prescription Drug Monitoring Program | Logged in state PDMP |
The 5-refills-in-6-months rule is the practical convenience of Schedule IV. A Modaheal patient on stable 200 mg daily can get a single written prescription from the clinician, use the five refills over 6 months, and visit the clinic for review at the half-year mark. Compare with amphetamine salts for ADHD, where a new paper prescription is needed every 30 days.
🌍 International travel notes
UK and most of EU: modafinil is a prescription medicine (POM in UK, Rx in EU) but not scheduled as a controlled drug. Carrying a prescription label is sufficient.
UAE, Saudi Arabia, Japan: modafinil is classified as a controlled or restricted substance; travellers may need advance import documentation.
China: modafinil is a Class 1 Psychotropic drug; import for personal use is tightly regulated and often not permitted.
Russia: listed under psychotropic schedules; import is not routine.
Rule of thumb: check the destination embassy or official customs resource at least 2 weeks before any international trip; carry the prescription in the original labelled packaging; do not transfer tablets to a pill organiser for travel through customs.
Military and sports contexts have their own rules. The US Department of Defense allows modafinil for certain sustained operations under medical supervision. The World Anti-Doping Agency bans modafinil in competition for all athletes under its code; a therapeutic use exemption is possible with documentation of a medical indication like narcolepsy, but routine use is detected and sanctioned.
Prescription Drug Monitoring Programs in the United States track Schedule IV drugs the same way they track Schedule II. If a patient tries to fill the same modafinil prescription at two pharmacies in the same month, the system flags it. Patients using multiple prescribers for the same drug (whether intentionally or because of care fragmentation) will have the pattern noticed. The purpose of the system is to catch dependence and diversion patterns early; the practical effect for most patients is zero friction.
Online pharmacies and foreign suppliers of modafinil are common. The quality of the product is generally reliable from reputable sources selling Modaheal, Modalert, Modvigil and similar generics made in India. The legal exposure depends on jurisdiction. In the US, importing modafinil without a prescription is technically illegal; enforcement against individual patients ordering a legitimate medical supply has been inconsistent. The safer path is to use a clinician-prescribed supply from a licensed pharmacy.
🔁 Dependence And Withdrawal Risk With Modafinil
Modafinil has a lower dependence risk than classical stimulants but is not without potential for dependence. The published rate of problem use is low in supervised narcolepsy and OSA populations and higher in off-label lifestyle use. The schedule is Schedule IV for a reason: there is a real signal, especially with chronic daily use beyond a year without a diagnosed sleep disorder.
What dependence looks like with modafinil is different from the classical stimulant pattern. There is no sharp withdrawal syndrome, no amphetamine-style crash, no measurable physical dependence like with opioids or alcohol. The pattern is psychological reliance: the user feels they cannot function at their job or during their day without the daily tablet, even after months of what should be adequate sleep. The subjective sense is that life has shifted so that a baseline of alertness without modafinil now feels like exhaustion.
| Dependence pattern | Risk level with modafinil |
|---|---|
| Physical withdrawal syndrome | Minimal; some fatigue return and mild rebound sleepiness |
| Tolerance to the wake effect | Mild; some patients need dose increase after 12+ months of daily use |
| Psychological reliance | Real; most problematic pattern |
| Euphoria-driven dose escalation | Rare at labelled doses; possible with high-dose misuse |
| Diversion to others | Documented; patients give tablets to students or shift workers |
| Formal addiction diagnosis | Rare; one case series out of Kent, UK |
Stopping modafinil after long daily use produces a mild withdrawal: fatigue returning to baseline, sometimes briefly worse than baseline for 2 to 4 days, and occasional transient low mood. This is not pharmacologic withdrawal in the formal sense; it is the sleep debt or underlying sleepiness surfacing without the drug covering it. The symptoms resolve as the underlying sleep problem comes back under control or as the sleep debt is paid down with longer nights.
Who is at higher risk of developing problematic use?
- Patients using modafinil off-label without a sleep diagnosis — most common risk group
- Patients with past substance use disorder, especially stimulant or cocaine
- Patients with major depression who feel modafinil lifts mood as well as alertness
- Patients taking modafinil for several years continuously without planned drug holidays
- High-pressure work environments where cessation is seen as a competitive disadvantage
✅ Habits that keep use within healthy bounds
Keep the dose at 200 mg or below — dose escalation is the first marker that something has drifted.
Take weekend breaks when the schedule allows — especially useful for shift workers.
Plan a 2-week drug holiday every 6 to 12 months — confirms you still function off the drug.
Watch for mood-related reach for extra doses — using modafinil to lift a bad day is a slide, not a treatment.
Keep clinician reviews on schedule — a 6-month check prevents quiet drift.
Do not share with friends or family — it is a controlled substance and the sharing pattern is a classic diversion risk flag.
Stopping modafinil for good after years of use is reasonable in most cases. The approach: taper over 2 to 4 weeks by dropping to 100 mg for a week, then 100 mg every other day for a week, then stop. The taper is not pharmacologic (there is no acute withdrawal to prevent) but gives the patient a transition week to adjust lifestyle and expectations. Some patients find they can simply stop with no transition and feel only mild fatigue for a few days.
If stopping produces more than a few days of fatigue return, the next question is what the original problem was. A narcolepsy patient who stops modafinil will return to the full daytime sleepiness of their disease, which is severe. A shift worker who stops will return to the fatigue of the shift pattern. These are not withdrawal; they are the disease the drug was treating.
🚨 Modaheal Side Effects You May Notice
Modaheal is reasonably well tolerated in most adults. The side-effect profile has three common complaints that show up in the first week and usually settle within two to three weeks, a short list of less common signals worth watching, and a very short list of rare but serious events that need urgent recognition. This section is the map; the next five sections drill into the most important ones.
| 📊 Frequency | Effect | What to do |
|---|---|---|
| Common (10-30 percent) | Headache | Hydrate, mild analgesic; usually settles by day 5 |
| Common | Nausea | Take with food; usually settles by day 7 |
| Common | Insomnia | Move dose earlier; no later than 10 AM |
| Less common (1-10 percent) | Anxiety, irritability | Reduce dose; discuss if persistent |
| Less common | Dry mouth | Hydrate; rinse mouth |
| Less common | Elevated blood pressure (2-5 mm Hg mean) | Monitor; dose adjust or discontinue if sustained |
| Less common | Dizziness, mild tremor | Usually transient first week |
| Rare but serious | Stevens-Johnson Syndrome, TEN, DRESS | Stop drug immediately; emergency care |
| Rare but serious | Psychiatric: mania, psychosis, suicidal ideation | Stop drug; same-day psychiatric evaluation |
| Rare but serious | Angioedema, anaphylaxis | Stop drug; emergency care |
| Rare but serious | Significant cardiac arrhythmia | Stop drug; cardiology referral |
The common three — headache, nausea, insomnia — are the ones that make patients consider stopping Modaheal in the first week. All three have practical fixes. Insomnia almost always traces to late dosing; nausea almost always traces to empty stomach dosing in a sensitive patient; headache is usually transient and responds to hydration and over-the-counter analgesics. The next section covers each in order.
The rare but serious group is small but mandatory to know. The Stevens-Johnson Syndrome rash warning is on the US label after case reports from 2007 onwards. Any new rash in the first 6 to 8 weeks of Modaheal, especially with mouth sores, fever or peeling skin, is a reason to stop the drug and seek urgent care. The psychiatric emergence signal is low in healthy adults but higher in patients with a history of bipolar disorder or psychosis.
📋 What the next sections cover
Section 20 — Headache: the first-week visitor, with practical cures and when it signals a bigger issue.
Section 21 — Insomnia: the predictable result of late dosing, with the fix that works nearly every time.
Section 22 — Blood pressure: the small but real cardiovascular signal and who should monitor at home.
Section 23 — Stevens-Johnson Syndrome: rare but mandatory to recognise within the first 8 weeks.
Section 24 — Mood and psychiatric signals: anxiety, irritability and the rarer serious psychiatric events.
A side effect that lasts beyond 3 weeks of steady use, or interferes with daily life, is a reason to speak with the clinician. There are almost always practical solutions: dose reduction to 100 mg, splitting the dose, swapping to armodafinil for a flatter curve, or ultimately switching drug classes.
Serious side effects such as any new rash, chest pain, severe depression or thoughts of self-harm, lip or face swelling, or a sudden sharp mood change should be reported the same day and the drug stopped until the clinical team reviews.
🤢 Headache On Modaheal And How To Manage It
Headache is the single most common side effect of Modaheal. It shows up in roughly 1 in 3 adults in the first week of a new prescription, typically within 2 to 4 hours of the morning dose, and usually fades by day 5 to 7 as the body adjusts. The pattern is a mild to moderate frontal or temporal headache, often described as a dull band across the forehead, not a sharp or throbbing migraine-type pain.
The exact mechanism is not fully pinned down. The leading explanation is increased glutamate signalling plus mild cerebral vasoconstriction from the dopamine lift, both of which can produce a tension-type or dull vascular headache. Blood pressure rise contributes marginally. Dehydration during the day stacks the effect because modafinil is a mild diuretic.
💧 Practical steps that help
Drink a glass of water with the tablet — takes care of 30 to 50 percent of first-week headache in most patients.
Keep a water bottle at the desk — aim for 2 to 2.5 L across the day.
Take a small snack 30 minutes after the dose — low blood sugar in the morning can trigger headache that modafinil then amplifies.
Reduce coffee intake temporarily — the combination of 300+ mg of caffeine on top of modafinil raises the headache rate.
Try paracetamol 500-1000 mg or ibuprofen 400 mg as needed. Avoid daily use to prevent medication-overuse headache.
Try a 100 mg dose for a week — half of a Modaheal tablet. If the headache resolves, 100 mg may become the permanent dose.
If headache persists beyond 2 weeks on 200 mg despite hydration and food timing, the next step is usually a dose reduction to 100 mg (half tablet) for a week. Many patients who were headache-prone on 200 mg are fine on 100 mg, and the wake effect at 100 mg is still clinically useful for most sleep indications in a healthy adult.
Patients with a prior history of migraine have a slightly higher rate of Modaheal headache in the first weeks and may experience a short-lived increase in migraine frequency. This usually settles over 4 to 6 weeks. If migraines increase and stay increased, modafinil may not be the right drug for that patient; armodafinil sometimes feels cleaner but is not a guaranteed fix.
⚠️ When a headache is not just a Modaheal headache
- Sudden severe headache described as the worst of your life — emergency department now
- Headache with fever and stiff neck — emergency department now
- Headache with vision change, weakness or speech trouble — emergency department now
- New headache in a patient over 55 who did not have headaches before — same-day clinician
- Headache that worsens with cough, sneeze or straining — same-day clinician
- Headache plus persistent high blood pressure — same-day clinician
Caffeine deserves a specific note. Many Modaheal users maintain their coffee habit, and in moderate amounts (1 to 2 cups a day) this is fine. Heavy coffee drinkers (4+ cups) often find that cutting back to 2 cups during the first week on Modaheal prevents the headache signal almost entirely. The combination of modafinil plus heavy caffeine plus dehydration is the three-way setup for a reliable mid-afternoon headache.
Headache that comes on in the evening after a daytime dose is usually a sign that the dose is too high for your pharmacokinetics. The late-day plasma level is unusually elevated, which raises the headache signal. The fix is dose reduction to 100 mg or splitting the dose into two 100 mg takes, one at 7 AM and another at noon. The 7 AM only dose is simpler for most people.
Finally, if the headache has a pulsating, one-sided character with nausea or sensitivity to light, that is a migraine pattern, not a Modaheal tension headache. A triptan for a severe migraine attack is compatible with Modaheal (no interaction), as is a daily migraine preventative such as topiramate or propranolol if the clinician decides prevention is needed.
😴 Insomnia From Late Day Dosing Of Modaheal
Insomnia on Modaheal is almost always traceable to dose timing. Patients who take the tablet at 7 AM rarely have trouble sleeping that night. Patients who take the tablet at 11 AM, noon or later consistently struggle. The 15-hour half-life means a late-morning dose keeps the plasma level above the alerting threshold through the natural bedtime, and the drug fights the sleep signal that would normally take over at 10 to 11 PM.
The fix for garden-variety Modaheal insomnia is simple: move the dose to 7 AM. If you have been dosing at 9 AM or later and sleep is suffering, the switch to 7 AM dosing almost always resolves the problem within 3 days. Set a phone alarm. Keep the tablet on the bedside table so you can swallow it with water as soon as you wake up, then dress and start the day.
If 7 AM dosing is already in place and sleep still suffers, the next step is dose reduction to 100 mg. This cuts the overnight plasma level in half and resolves insomnia for most of the remaining patients. The wake effect at 100 mg is softer, but for many people it is still enough.
🛏️ Sleep hygiene steps for the first weeks on Modaheal
Fixed bedtime — even on weekends. Variability makes everything harder on a wake-promoting drug.
Dim lights after 9 PM — blue light exposure delays melatonin on top of the modafinil effect.
Cool bedroom (18-19 degrees Celsius) — body temperature drop is a sleep signal.
No caffeine after 2 PM — combined with modafinil, late caffeine is the single biggest sleep killer.
No alcohol in the evening — alcohol fragments sleep architecture even in small amounts.
No screen in bed — raising sleep latency further compounds the modafinil effect.
Melatonin 0.5-3 mg at 9-10 PM — a reasonable short-term aid for 1-2 weeks of adaptation.
Melatonin deserves special mention. A small dose (0.5 to 3 mg) taken 1-2 hours before the target bedtime can help re-anchor the sleep onset signal in a Modaheal user whose natural melatonin rise is being masked by the drug. There is no interaction between modafinil and melatonin. Melatonin is sold over the counter in the US; dosing in Europe may require a prescription for the extended-release version.
Sleep aids beyond melatonin are a different conversation. Short-term use of doxylamine (over-the-counter) or a prescription hypnotic (zolpidem, eszopiclone) for a week while adjusting to modafinil can help, but longer use is a sign that something is not working. The underlying question is why the sleep is not coming on its own, and the answer is usually the dose timing or the dose level, not a missing sleeping pill.
A specific trap: Modaheal plus a bedtime hypnotic to force sleep against the drug action is a pharmacologic tug-of-war that produces unrefreshing sleep and daytime grogginess the next morning. The right fix is almost always to adjust Modaheal timing or dose, not to layer another drug on top.
If you have narcolepsy and inherently fragmented night sleep, Modaheal does not help the night fragmentation. A dedicated night-time drug like sodium oxybate at bedtime is sometimes added by the narcolepsy specialist to improve night sleep consolidation. The combination of Modaheal in the morning plus oxybate at night is a classic narcolepsy regimen and works well in selected patients.
🩸 Modaheal And Blood Pressure Monitoring At Home
Modaheal raises blood pressure and heart rate modestly in most adults. The mean effect is roughly 2 to 5 mm Hg in systolic blood pressure and 2 to 5 beats per minute in heart rate. These numbers are small and usually of no clinical consequence. But three groups of patients need attention: those with pre-existing hypertension, those with structural heart disease, and those who happen to be big responders at the individual level.
The cardiovascular effect comes from the mild dopamine reuptake block and the modest glutamate rise, both of which raise sympathetic nervous system activity. The effect is dose-dependent — it is larger at 400 mg than at 200 mg — and it is slightly larger in the first weeks than later, as the body adapts.
| Patient profile | Blood pressure monitoring plan |
|---|---|
| No hypertension, no heart disease | Baseline reading; recheck once at 4 weeks |
| Controlled hypertension on medication | Home readings 2x per week for first month, then monthly |
| Uncontrolled hypertension | Delay Modaheal until pressure is controlled |
| Known cardiac arrhythmia | Cardiology clearance before starting |
| Structural heart disease or recent MI | Specialist decision; usually avoid |
| Mitral valve prolapse with syncope history | Avoid per FDA label guidance |
Home blood pressure monitoring is the practical tool. A patient starting Modaheal can take 3 readings on 3 days in the week before starting (morning and evening), average them, and use that as their baseline. Then on week 4 of Modaheal, repeat the same pattern. A rise of 5 mm Hg or less in the mean is expected and acceptable. A rise of 10 mm Hg or more is a signal to reduce the dose or reconsider the drug.
Heart rate changes work the same way. A new resting heart rate consistently above 100 beats per minute on Modaheal, in a patient whose baseline was 70, is a reason to recheck with the clinician. Rare arrhythmia reports (SVT, isolated PACs) have appeared in post-marketing data; most settle on stopping the drug but a cardiology evaluation is worth doing.
🚨 Cardiac warning signs that need urgent care
- Chest pain, pressure or tightness — especially with exertion or during the first weeks on Modaheal
- Palpitations lasting more than a few minutes or associated with lightheadedness
- Fainting or near-fainting — stop Modaheal, same-day evaluation
- Shortness of breath at rest not explained by anxiety or exertion
- Sudden sharp blood pressure rise above 180 systolic or 110 diastolic at home
Patients taking antihypertensive medications usually continue them without adjustment while starting Modaheal. The small blood pressure rise is accommodated by the existing medication reserve in most cases. If the pressure drifts up over the first month, the first move is a conversation with the clinician about either adjusting the antihypertensive or reducing Modaheal, not stacking a new blood pressure medication on top.
Patients on beta-blockers (metoprolol, propranolol, bisoprolol) tolerate Modaheal well. The beta-blocker partially blunts the heart rate rise, and the pressure change is usually fully absorbed. This is a reasonable combination in a hypertensive narcolepsy patient.
Patients on MAO inhibitors (phenelzine, tranylcypromine, selegiline) are a specific concern. The theoretical interaction raises both blood pressure and sympathetic signalling. Modafinil is not an absolute contraindication with MAOIs, but combined use requires close monitoring and starts with a 100 mg dose. Most clinicians prefer to avoid the combination when another wake-promoting option is possible.
Finally, patients with sleep apnea who are prescribed Modaheal for residual sleepiness need their blood pressure watched extra carefully because untreated OSA itself raises blood pressure. Confirming CPAP adherence first is as important as monitoring Modaheal effects.
🛑 Stevens-Johnson Syndrome And The Modaheal Rash Warning
Stevens-Johnson Syndrome (SJS), Toxic Epidermal Necrolysis (TEN) and DRESS syndrome are rare but potentially fatal skin and systemic drug reactions. The FDA added a formal warning about these conditions to the modafinil label in 2007 after case reports in both adult and paediatric trials. The rate is very low — well under 1 in 10,000 users — but the consequences are severe enough that any new rash on Modaheal in the first 8 weeks is a reason to stop the drug and seek evaluation.
Any new rash on Modaheal deserves a same-day review. The further right on the gauge, the more urgent.
The pattern of a Modaheal-related serious rash is distinctive. Within 1 to 5 weeks of starting the drug (and nearly always within the first 8 weeks), the patient develops fever, feels unwell and notices a rash that is often painful rather than just itchy. The rash spreads over hours to days. Mucous membranes may be involved — sore mouth with ulcers, red eyes, genital soreness. Blistering appears. Peeling of the skin follows.
🚨 Warning signs that need immediate care
- Any new rash in the first 8 weeks on Modaheal
- Fever with the rash
- Mouth sores, eye redness, or genital soreness with the rash
- Painful skin that feels like a sunburn without having been in the sun
- Blistering or peeling skin
- Facial swelling, lymph node enlargement with the rash (suggests DRESS)
- Yellow eyes or skin, dark urine with the rash (suggests DRESS with liver involvement)
Action: Stop Modaheal immediately and go to the emergency department. Bring the medication package.
SJS and TEN are the same disease on a severity scale. They are an immune-mediated attack on skin and mucous membranes, triggered by a drug the body has decided to react against. Modafinil joins a list of other triggers including allopurinol, lamotrigine, carbamazepine and some antibiotics. The condition has a mortality rate of 10 to 50 percent depending on the extent of skin involvement, so early recognition and withdrawal of the trigger matter. Supportive care is the mainstay once the drug is stopped; some centres add immunosuppressive agents.
DRESS (Drug Reaction with Eosinophilia and Systemic Symptoms) is a separate but overlapping syndrome. It usually appears 2 to 8 weeks after starting the drug with fever, rash, lymph node enlargement, and liver or kidney inflammation. The pattern is slightly later and less skin-dominant than SJS. Treatment is the same first step: stop the drug.
Risk factors for serious skin reaction on modafinil are not fully mapped. Children appear to be at higher risk than adults, which is one reason the drug is not approved under age 17. Patients with HLA genetic variants that mark increased risk of SJS from other drugs may also be at raised risk, but routine HLA testing before Modaheal is not standard.
If a patient has had a previous SJS, TEN or DRESS from any drug, modafinil is not recommended. This is a hard rule, not a shared-decision point. The anatomic damage from a previous episode makes a second episode more dangerous, and multiple triggers often share immunologic mechanisms.
Minor skin reactions — a transient mild itch, a few patches of mild rash without fever or mucous involvement — are not rare, do not necessarily indicate SJS, and usually resolve on stopping the drug. The problem is that the early stage of SJS can look similar to a minor rash. The safe default is to stop Modaheal with any new rash in the first 8 weeks, let the clinician evaluate, and resume only if the rash is confirmed to be minor and unrelated.
Patients should know this before the first tablet. The pharmacist dispensing Modaheal in the US is required to provide a medication guide with the SJS warning. If you received the drug without this handout, ask for it. The recognition and immediate drug withdrawal are the main defences; the rash itself is not something to tough out.
🧠 Modaheal And Mood Anxiety And Psychiatric Signals
Modaheal has a short list of psychiatric effects. The common ones are anxiety and irritability, both at the mild end for most patients. The uncommon but important ones are new or worsening depression, suicidal thoughts, mania in bipolar patients, and rare psychotic symptoms. Any psychiatric change that is significant or lasting is a reason to review the drug, not to push through.
The mild end first. About 5 to 15 percent of patients notice some degree of anxiety, nervousness or irritability in the first weeks. The symptoms are usually in the morning and early afternoon, following the plasma peak, and often fade as the body adjusts over 2 to 3 weeks. Specific experiences patients describe:
- A buzz-like feeling in the chest or head, mostly in the first 2 hours after the dose
- Shortened patience at work or at home, more irritable than usual
- Restlessness, a sense of needing to move or finish tasks fast
- Jaw tension or teeth grinding during focused work
- Social edginess or avoiding small talk because it feels effortful
💡 If anxiety or irritability is noticeable
Reduce dose to 100 mg for 1 to 2 weeks and watch for improvement. Many anxiety-sensitive patients find 100 mg produces the wake effect without the edge.
Cut caffeine — the combination of modafinil plus heavy caffeine amplifies anxiety.
Add structured physical activity — a 20-30 minute walk at midday takes the edge off the plasma peak.
Avoid alcohol as self-medication — the next-day rebound worsens the pattern.
Give it 2-3 weeks — most mild anxiety fades as the body adapts, if the dose is right.
If still intolerable — discuss a switch to armodafinil (flatter curve may feel less edgy) or discontinuation.
Depression is a specific worry. Modafinil has mild antidepressant-like effects in some studies, but new or worsening depression on modafinil has been reported. Any patient who experiences a significant mood drop, lack of interest or pleasure, persistent sadness or thoughts of self-harm after starting Modaheal should treat this as a potential drug effect and raise it with the clinician promptly.
Mania or hypomania is a signal in patients with underlying bipolar disorder. Modafinil can precipitate a manic episode in someone with latent or diagnosed bipolar illness. Signs include unusually elevated mood, decreased sleep need without feeling tired, pressured speech, grandiose thinking, impulsive spending or sexual activity, and racing thoughts. These are a reason to stop the drug immediately and see a clinician the same day.
🚨 Psychiatric warning signs that need urgent care
- Suicidal thoughts or self-harm thoughts — call emergency services, go to the ED, or call a crisis line
- Manic episode: elevated mood, no sleep need, pressured speech, grandiose plans, impulsive behaviour
- Psychotic symptoms: hearing voices, paranoid beliefs, loss of reality contact
- Severe depression: persistent low mood, inability to function, hopelessness
- Sudden personality change noticed by family or close coworkers
Patients with a history of psychosis or schizophrenia may have their symptoms worsened by modafinil through the dopamine lift. Modafinil is not an absolute contraindication in schizophrenia, and some patients tolerate it well for a sleepiness indication, but the decision requires psychiatric agreement and close monitoring during the first 4 to 6 weeks.
Patients with a history of substance use disorder are a different concern. The subtle reward signal of modafinil can re-trigger previous patterns in some patients with past stimulant or cocaine use, even if the person feels in control at the start. The relapse pattern often involves escalating the dose (300 to 400 mg instead of 200 mg), taking a second dose at midday, and gradually losing track of the structure around the drug. If any of this appears, a frank conversation with the clinician and often a drug holiday or discontinuation is the right move.
Finally, modafinil can affect sleep architecture in ways that worsen mood through a different route. Chronic sleep debt causes depression. If modafinil is being used to push through sleep debt rather than to treat a diagnosed sleep disorder, the sleep debt itself can bring mood down over months of use. The right response in this situation is not more modafinil — it is to address the sleep problem directly, usually with lifestyle changes, sleep schedule discipline and sometimes short-term melatonin or a prescription sleep aid for sleep restoration.
🔗 Modafinil Drug Interactions Beyond Contraception
Beyond the hormonal contraceptive interaction already covered, Modaheal has a handful of other drug interactions worth knowing. They fall into three mechanisms: induction of CYP3A4 (reducing levels of other drugs), inhibition of CYP2C19 (raising levels of a few other drugs), and additive effects on blood pressure or dopamine signalling with specific other drug classes.
| 🔗 Severity | Drug or class | Mechanism and effect | What to do |
|---|---|---|---|
| Avoid or watch | MAO inhibitors (phenelzine, tranylcypromine, selegiline) | Added sympathetic activation; hypertensive crisis theoretical | Specialist decision; close BP monitoring if combined |
| Avoid or watch | Hormonal contraceptives | CYP3A4 induction reduces effectiveness | Add barrier method or switch to IUD (see section 16) |
| Caution | Warfarin | Variable INR change from CYP effects | INR check at week 2 and 4 after starting |
| Caution | Cyclosporine, tacrolimus, sirolimus | Levels may drop from CYP3A4 induction | Transplant team consultation before start |
| Caution | Phenytoin, diazepam | Levels may rise from CYP2C19 inhibition | Monitor levels and effect |
| Caution | Tricyclic antidepressants | Levels may rise; cardiac effects stack | Clinician review |
| Interactions worth noting | Ketoconazole, erythromycin, HIV protease inhibitors | May raise modafinil levels | Lower modafinil start dose, 100 mg |
| Interactions worth noting | Rifampin, carbamazepine, St John wort | May lower modafinil levels | May need higher modafinil dose |
| Low concern | SSRIs, SNRIs | No major interaction; combination common in depression augmentation | Use together as prescribed |
| Low concern | Most antihypertensives | No significant interaction | Monitor BP as usual |
The CYP3A4 induction effect of modafinil is the mechanism behind most of the clinically meaningful interactions. Modafinil raises CYP3A4 activity in the liver over 1 to 2 weeks of daily use, which accelerates the breakdown of drugs that pass through this enzyme. Besides hormonal contraceptives, the drugs most affected are: cyclosporine (transplant immunosuppressant), midazolam (benzodiazepine), triazolam (benzodiazepine), and some HIV protease inhibitors. Patients on any of these should have levels checked at week 2 and 4 of Modaheal.
The CYP2C19 inhibition works the other way: a few drugs break down more slowly on modafinil and their levels rise. Phenytoin (anti-epileptic), diazepam, omeprazole and clopidogrel are in this group. Phenytoin levels can rise enough to produce toxic symptoms (sedation, ataxia, blurred vision); a drug level check in the first weeks is sensible. Clopidogrel is converted to its active form by CYP2C19, so the modafinil inhibition could theoretically reduce clopidogrel effectiveness; this is more theoretical than clinically documented at modafinil doses, but worth knowing.
💡 Over-the-counter and food interactions
Grapefruit juice inhibits CYP3A4 and could theoretically raise modafinil levels, but the effect is small because modafinil clearance does not depend heavily on CYP3A4 for its own metabolism. Occasional grapefruit is fine; daily large volumes are not advised. St John wort is a strong CYP3A4 inducer and can lower modafinil levels; patients using the herbal for depression may notice a weaker modafinil effect. Caffeine has no pharmacokinetic interaction, but combined pharmacodynamic effect on alertness is additive.
Warfarin needs its own note. Modafinil has a mixed effect on warfarin metabolism — it can shift INR either way through combined CYP3A4 and CYP2C9 interactions. The practical approach is simple: check INR at week 2 and week 4 after starting Modaheal, and again if any bleeding or clotting symptoms appear. Dose adjustment of warfarin is often needed but is usually small.
Transplant medications are the highest-stakes category. Cyclosporine, tacrolimus and sirolimus are all CYP3A4 substrates with narrow therapeutic ranges. A drop in level can lead to graft rejection; a rise can lead to toxicity. Any patient on these medications who needs Modaheal must have the transplant team involved in the decision and in level monitoring for the first 2 months.
Finally, patients on more than one of the interacting drugs face stacked risk. Someone taking an oral contraceptive, warfarin and modafinil all together has three interactions to track. Simplifying the regimen (switch to an IUD, switch warfarin to a direct oral anticoagulant) often makes the modafinil management more straightforward.
🍷 Alcohol and Modaheal What To Watch For
Alcohol and modafinil are a bad combination. There is no direct enzyme interaction, but the pharmacodynamic clash is predictable: modafinil raises alertness and alcohol lowers it, and the sum of two drugs working against each other is a user who feels less drunk than they are. The practical result is impaired judgment that feels less impaired than it is, which raises accident risk substantially.
Three specific risks:
Masked intoxication. Users who drink while on modafinil often report they can drink more before feeling drunk. Blood alcohol level rises the same way it would without modafinil, but the subjective drunkenness is reduced. The result is more drinks than intended, higher blood alcohol, and worse judgment at the end of the night. This is the most dangerous pattern on this combination.
Sleep damage. Alcohol fragments sleep architecture independently of modafinil. On modafinil, the sleep problem compounds — the drug is still working through the night at some level, the alcohol fragments the sleep that does happen, and the next day the user feels worse than either drug would produce alone.
Mood swings. The up of modafinil and the down of alcohol followed by the up of the morning dose and the down of hangover produces a mood whiplash that patients consistently describe as worse than either drug alone.
🍷 Practical drinking rules on Modaheal
If you drink at all, drink less than you would without modafinil — your sense of drunkenness is unreliable.
Count drinks, do not rely on how you feel — 1-2 drinks maximum on a modafinil day.
Never drive after drinking on modafinil, regardless of how alert you feel.
Space from the dose — dose in the morning, drink in the evening if at all; do not drink before noon when the peak plasma is building.
Do not drink on days you are already short on sleep — the compounding effect is worst then.
Avoid alcohol during the first 2 weeks on a new modafinil prescription — let yourself establish a stable response to the drug first.
Patients with narcolepsy have additional reasons to limit alcohol. Alcohol depresses REM sleep and worsens cataplexy triggers in some patients. The combination of narcolepsy, modafinil and heavy alcohol intake produces unpredictable daytime function the following day. Clinicians specialising in narcolepsy often recommend no more than one drink on treatment days, if any.
Patients using modafinil for OSA with CPAP face another problem. Alcohol worsens upper airway muscle tone, which worsens the apneas even on CPAP. Worse still, alcohol often leads to patients taking off CPAP in the middle of the night because the mask feels harder to tolerate. Modafinil the next day masks the sleepiness that would otherwise warn them that the CPAP night was poor. The downstream pattern is a slow deterioration in disease control that only becomes obvious at the next sleep study.
🚨 High-risk patterns worth avoiding entirely
- Binge drinking the night before a modafinil day — next-day function is worse than the drug can fix
- Drinking during the modafinil active plasma window — subjective impairment misleads
- Alcohol plus caffeine plus modafinil during a long day — multiple drugs working against each other
- Using modafinil to work after a drinking night — builds habit and dependence
- Driving a motor vehicle after any alcohol while on modafinil — even if you feel alert, your legal and real blood alcohol are the same as without the drug
Chronic heavy alcohol use affects liver function, and modafinil is metabolised by the liver. Patients with alcohol-induced liver disease should discuss modafinil with the clinician; dose reduction to 100 mg or avoidance of the drug may be appropriate.
No formal lab monitoring is required for Modaheal in a patient drinking moderately. Liver enzymes should be checked at baseline and at 6 months in patients with any underlying liver condition or heavier drinking history. Modafinil itself does not raise liver enzymes meaningfully in healthy drinkers at labelled doses.
If drinking has become a problem alongside Modaheal use — and the combination can accelerate this — the modafinil clinician is often a good first contact. Brief counselling plus structured support reduces alcohol intake in most patients who recognise the pattern. Depending on the pattern, the Modaheal itself may need pausing until drinking is under control.
☕ Caffeine Nicotine and Other Stimulants With Modaheal
Caffeine, nicotine and other stimulants all touch arousal pathways that overlap with modafinil. Combining them is common and sometimes fine, sometimes problematic. The practical rules are different for each substance.
Caffeine has no pharmacokinetic interaction with modafinil. The combined pharmacodynamic effect on alertness is additive: 200 mg of modafinil plus 400 mg of caffeine from several cups of coffee produces more alertness than either alone, with proportional side effects. Most Modaheal users keep their coffee habit, and in moderate amounts (1 to 2 cups per day) this works out fine.
The problem is heavy coffee drinkers on Modaheal. Four or more cups of coffee plus 200 mg of modafinil stacks three unpleasant effects: headache, anxiety, insomnia. The headache rate rises from the baseline 30 percent of first-week Modaheal users to above 50 percent in heavy coffee drinkers. Anxiety doubles. And late afternoon coffee combined with modafinil wrecks the night sleep.
☕ Caffeine rules on Modaheal
1-2 cups morning only — the simple safe pattern for most users.
No caffeine after 2 PM — late caffeine plus the modafinil tail wrecks sleep.
Cut back during the first week on a new modafinil prescription — let the body adjust to one stimulant at a time.
Energy drinks are a bad idea — too much caffeine too fast, plus other stimulants.
Watch for jitter or chest racing as the signal that the combination is too much — cut coffee first before cutting modafinil.
Nicotine is pharmacodynamically additive with modafinil and raises blood pressure and heart rate further. The main concern is not the pharmacology but the smoking itself: smokers have higher cardiovascular risk, and the small blood pressure rise of modafinil adds to the much larger cardiovascular risk of chronic smoking. Patients who stop smoking during modafinil therapy do fine; nicotine replacement patches, gum and lozenges are compatible, as are varenicline and bupropion for smoking cessation.
Vaping nicotine is not a safer combination. The cardiovascular effect is similar to cigarettes, and the chronic airway irritation is probably worse than once thought. If you are using modafinil for OSA residual sleepiness and vape as well, the vape pattern is worsening the OSA; a quit plan serves the sleep goal.
Classical stimulants (amphetamines, methylphenidate, cocaine) with modafinil are not a routine combination and should not be self-combined. The pharmacology stacks: dopamine release from amphetamine, dopamine reuptake block from modafinil, blood pressure rise from both. Occasional specialist use of amphetamine added to modafinil for severe narcolepsy is a monitored decision, not a lifestyle choice.
🚫 Do not combine with these
- Cocaine — severe cardiovascular risk, dopamine stacking
- Methamphetamine — same stacking plus severe psychiatric risk
- MDMA — serotonergic plus dopaminergic hyperactivation
- High-dose ephedrine or other sympathomimetics — blood pressure crisis risk
- Yohimbine supplements — blood pressure stacking
Cannabis has no direct interaction but the pharmacodynamic clash resembles alcohol. Cannabis dulls alertness and modafinil raises it; combined use produces unpredictable states where judgment is reduced but subjective alertness feels fine. Avoid in situations that need driving or decision-making. If cannabis is medically indicated, use at the end of the day well after the modafinil tail has faded.
Psychostimulant herbal supplements — guarana, ginseng, yerba mate, caffeine pills — add caffeine content that most users do not realise is substantial. A single guarana supplement may contain 300 mg of caffeine. Patients on modafinil should read supplement labels for stimulant content and factor it into their daily caffeine total.
Overall rule: modafinil is a stimulant for your sleep problem, not a license for layered stimulant use. Keep the stimulant total low and spread over the first half of the day. The patients who stay well on modafinil long-term are those who match it with calm habits in the rest of their day.
🌱 Modafinil in Pregnancy Why To Avoid
Modafinil in pregnancy is a difficult area. The drug carries a reproductive-toxicity signal in animal studies and limited but worrying human case series. The current FDA pregnancy category classification (pre-2015 system) was C, meaning animal reproductive studies showed adverse effects and no adequate human studies existed. In 2019, Cephalon updated US labelling after a review of case series data to recommend against use in pregnancy except when the benefit clearly outweighs the risk.
What the human data show:
A French pregnancy registry analysis published in 2020 by Dauvilliers and colleagues reviewed 61 pregnancies exposed to modafinil in the first trimester. The pattern suggested an elevated rate of major congenital malformations, including cardiac defects and hypospadias, at roughly 15 percent compared with 3 percent in the general population. The small sample size limits certainty, but the signal was consistent with the animal toxicology.
Other registries have shown similar signals: Danish and US registry data have reported case clusters of malformations. The regulatory response has been to restrict use rather than to ban the drug entirely in pregnancy, because narcolepsy patients may need treatment and alternatives for severe daytime sleepiness during pregnancy are limited.
🛑 Current guidance for women of reproductive age
Avoid modafinil during pregnancy and in women planning pregnancy. If a woman becomes pregnant on modafinil, stop the drug and contact the clinician promptly. The highest-risk window is the first trimester when organogenesis occurs. If modafinil must be continued because of severe narcolepsy that cannot be managed otherwise, the decision requires joint sleep specialist and maternal-fetal medicine consultation and documentation of informed consent.
The hormonal contraceptive interaction covered in section 16 is directly relevant here. A woman on modafinil who relies on oral contraception alone is at raised pregnancy risk. The combination of this interaction and the pregnancy risk is why most sleep clinicians switch women of reproductive age to a copper or hormonal IUD before starting modafinil, or add a barrier method as the second line.
If a pregnancy is detected on modafinil, three actions take priority:
1. Stop the drug as soon as pregnancy is confirmed.
2. Contact the sleep clinician within a day to plan ongoing management of the underlying narcolepsy or sleep disorder.
3. Enrol in the pregnancy registry (Nuvigil/Provigil pregnancy registry maintained in the US; local equivalents in other countries) so that outcome data accumulate for future patients.
Management of the underlying sleep disorder in pregnancy without modafinil varies by indication. In narcolepsy, strict sleep hygiene, planned naps, and sometimes short-acting methylphenidate are the fallback. Methylphenidate is also not without pregnancy concern but has somewhat more human data. For OSA residual sleepiness, strict CPAP adherence often reduces residual sleepiness to levels where modafinil is not needed. For shift work disorder, schedule change away from night shifts is usually the recommendation during pregnancy.
| Scenario | Approach |
|---|---|
| Planning pregnancy, on modafinil for narcolepsy | Discuss stopping before trying to conceive; plan nap-based management |
| Pregnancy confirmed on modafinil | Stop the drug; same-day clinician contact; join registry |
| Severe narcolepsy with cataplexy, cannot stop modafinil | Joint sleep + MFM consultation; informed consent; lowest effective dose |
| Pregnancy exposure already occurred, now second trimester | Discontinue; MFM referral for detailed anatomy scan at 18-20 weeks |
| Unplanned pregnancy, modafinil + oral pill failure | Same approach; the contraceptive interaction likely contributed |
Men on modafinil who want to father a child are a different conversation. There is no formal signal of modafinil-related male fertility problems in the human literature. Animal data show high-dose effects on testicular tissue in rats, but these doses are far above human exposure. Routine modafinil continuation in men planning to father a child is generally acceptable.
The right time to have this conversation is before starting modafinil, not after an unplanned pregnancy. Any woman of reproductive age starting the drug should hear the pregnancy warning along with the contraceptive interaction warning at the same visit. Both pieces of information belong together, and both are often missed when prescribing time is rushed.
🍼 Modafinil in Breastfeeding and Infant Exposure
Modafinil in breastfeeding has sparse human data and the general recommendation is to avoid when possible. The drug does cross into breast milk in small amounts based on limited published case data, and the long half-life means an infant feeding on-and-off through the day is exposed to a sustained low level rather than a sharp peak.
What is known:
- Modafinil has been detected in breast milk at low concentrations in case reports.
- The relative infant dose is estimated at under 10 percent of the maternal weight-adjusted dose, which is below the usually-cited 10 percent threshold for breastfeeding safety but with limited sample size.
- No formal paediatric case series of modafinil-exposed breastfed infants exists.
- The drug class (eugeroic) has no clearly documented adverse infant effects, but the signal in the first weeks of life would be subtle and easy to miss.
⚠️ Practical approach for a nursing mother
Avoid if possible — delay starting modafinil until weaning when feasible.
Pump and discard for 24 hours after a single dose — not a standard approach but reasonable if a one-off dose was unavoidable.
If chronic use is unavoidable for severe narcolepsy, discuss formula feeding or mixed feeding with the paediatrician.
Lowest effective dose — 100 mg if it covers the mothers clinical need.
Watch the infant for unusual irritability, feeding difficulty or poor sleep patterns.
LactMed and the regional poison control service can be helpful resources for specific case questions.
Why is modafinil different from, say, caffeine (which is widely considered acceptable in moderate amounts for a nursing mother)? The main reasons are the long half-life (modafinil 15 hours vs caffeine 6 hours in adults, longer in young infants), the limited data on infant exposure, and the low infant metabolic clearance for drugs cleared through the liver. A healthy newborn clears modafinil much more slowly than an adult, so even a small milk-transferred dose can accumulate in the infant blood over days.
If a mother is already on modafinil at the time of pregnancy or delivery:
- During pregnancy, see section 28.
- At delivery, the drug is often stopped if feasible. If continuation is needed for severe narcolepsy, the decision is a joint sleep medicine and paediatric consultation.
- Mixed feeding (modafinil during the day, formula after dosing hours, breast at other times) is sometimes attempted but is practically hard to execute and provides uncertain protection.
Narcolepsy specifically poses a safety issue for mothers of newborns. Severe daytime sleepiness while responsible for an infant is dangerous for both. The decision is not simply "stop the drug" but "manage the sleep disorder while nursing", which may involve more help from family, formal naps, formula supplementation, or combination of these.
Pumping and discarding is a limited tool. Modafinil persists in the maternal bloodstream for about 48 hours after a dose. A 24-hour pump-and-dump after a one-off tablet reduces infant exposure but does not eliminate it. On daily dosing, pump-and-dump is not a useful protection.
Alternative wake-promoting agents in nursing mothers are similarly data-limited. Pitolisant and solriamfetol have less human breastfeeding data than modafinil. Methylphenidate has somewhat more data and is sometimes used by sleep specialists in nursing mothers with narcolepsy; the decision is case by case.
The honest summary: there is no fully safe approach to modafinil in breastfeeding. Avoid when possible, minimise exposure when necessary, watch the infant, and keep the paediatrician informed. The right conversation happens with both the sleep specialist and the paediatrician before delivery, not during a late-night feeding crisis.
✈️ Driving Flying and Shift Transitions on Modaheal
Three travel-related situations change how Modaheal fits into a day: driving on narcolepsy or OSA treatment, flying across time zones, and transitioning between day and night shift schedules. Each has specific rules.
Driving on Modaheal. The core truth: Modaheal makes a sleepy brain functional, but it does not make a sleepy brain fully safe behind the wheel. In narcolepsy, driving while on well-adjusted Modaheal is safer than driving untreated, but the risk is not zero. A patient should not drive long distances alone during the first 2-4 weeks of a new prescription, and even on stable treatment should pull over for a 20-minute nap at the first sign of sleepiness.
Jurisdictions differ on how narcolepsy diagnosis affects driving licence. In the UK, DVLA requires notification and the licence is retained if symptoms are controlled. In the US, state-level rules vary; a few states require physician reporting of patients with narcolepsy or epilepsy. The modafinil prescription itself is not a reportable item in most jurisdictions, but the underlying diagnosis often is.
🚨 When to stop driving even on Modaheal
- Any sleep attack while driving — stop immediately, do not resume until clinician review
- New Modaheal prescription first week — limit driving to short, essential trips
- Cataplexy episode within the last 3 months on current treatment — discuss with specialist
- Missing doses for several days — back to untreated baseline risk
- Any alcohol intake — do not drive, same as general rules
- Lack of sleep the previous night — modafinil does not fix the risk
Flying across time zones. This is where Modaheal and jet lag get confused. Modafinil masks daytime sleepiness; it does not shift the circadian clock. Three travel patterns handle differently:
- Short trips (1 to 3 days) in a 3-5 hour time zone shift: many travellers skip circadian adjustment entirely, maintain home-time habits and let the daytime routine remain in local time. Modafinil taken at the usual home time (which may be local 10 AM) covers the key daytime hours of the trip.
- Longer trips (over 4 days) in a significant time zone shift: gradual circadian adjustment is the right approach. Melatonin and morning light at the new-zone bedtime and wake time, respectively. Modafinil can cover the daytime sleepiness during the adjustment week.
- Rotating business travel every week: circadian misalignment becomes chronic. This pattern itself is a problem; modafinil masks the symptom without fixing it. Address the schedule if possible.
Shift transitions. Workers moving between day and night shifts within the same week find Modaheal useful on the night-shift days and sometimes a complication on the recovery days. The practical pattern is:
| Shift pattern | Modafinil approach |
|---|---|
| Day shift (7 AM start) | Dose at 7 AM |
| Night shift (11 PM start) | Dose at 10 PM (one hour before shift) |
| Day off after night shift | Skip dose; prioritise daytime sleep |
| Transition day (day shift to night shift) | Skip Modaheal; nap in the afternoon; dose at 10 PM |
| Rotating 24-hour schedule | Specialist decision; often not sustainable long-term |
High altitude and extreme climates do not change modafinil dosing. Air pressure and temperature do not affect oral absorption or liver metabolism meaningfully. The usual altitude-related sleep issues (altitude insomnia above 3,000 m) do not interact with modafinil; a traveller may add melatonin for altitude-related sleep onset problems at high elevation.
Scuba diving on modafinil is not restricted by the drug itself, but the underlying sleep disorder may be. Narcolepsy with cataplexy is a contraindication to scuba diving under dive medicine guidelines; the risk of a sleep attack or cataplexy episode underwater is unacceptable. Controlled narcolepsy without cataplexy on stable modafinil treatment is a shared-decision call between the diver, the sleep clinician and a dive medicine specialist.
🏥 Pre-Op Dental and Sick Day Planning on Modaheal
Three everyday situations deserve a short plan on modafinil: planned surgery, dental procedures, and sick days with cold, flu or other illness. In each one, the drug is usually continued or paused briefly, but the surrounding plan is what prevents problems.
Elective surgery. Modaheal is generally continued through the day of surgery, including the morning dose, unless the anaesthesia team has a specific reason to hold it. Discuss the drug at the pre-op visit; most anaesthesia teams prefer the dose to be held on the morning of surgery because the mild cardiovascular effect and sympathetic activation can complicate anaesthesia management, and the long half-life means the patient will have substantial active plasma from the previous day anyway. The post-op resumption is day one or two after surgery once oral intake is secure.
🏥 Pre-op planning on Modaheal
Tell anaesthesia at the pre-op visit — the drug, dose and indication.
Follow their guidance on day-of dosing — usually hold the morning dose.
Expect the usual plasma tail — the previous day dose is still present at surgery time.
Watch for post-op sleepiness — the underlying sleep disorder is still there, and skipping modafinil for a day or two leaves the patient tired. This is especially relevant if the surgery requires lying flat and may trigger sleep attacks in narcolepsy.
Resume within 24-48 hours — most surgical teams approve this.
Flag any new psychiatric or cardiac issues — general anaesthesia plus modafinil in the recovery days has rare reports of hyperactive delirium.
Dental procedures. Local anaesthesia for routine dentistry does not interact with modafinil. The epinephrine used with local anaesthetic in dental procedures causes a small, brief heart rate rise — on top of the modafinil baseline, this is usually unnoticed. For long dental procedures under IV sedation, the dentist should know about the drug; sedation targets may need adjustment, and the usual pre-op fast rules apply.
Dental surgery or extraction with pain management is straightforward. Non-opioid analgesics (paracetamol, ibuprofen, naproxen) have no interaction with modafinil. Short courses of opioids (codeine, tramadol) also work alongside modafinil without issue, though the opioid-related sedation may partly cancel the modafinil wake effect for a day or two.
Sick days. Modafinil is usually continued during a cold or mild illness. The drug is not immunosuppressive and does not worsen viral infections. The main practical issue is fever: a febrile patient taking a stimulant should keep the fluid intake up because modafinil mildly dries fluid retention and dehydration worsens fever symptoms.
| Sick day signal | Modaheal approach |
|---|---|
| Mild cold, no fever | Continue regular dose |
| Fever above 38 degrees C | Continue, drink extra water, consider holding if the patient wants to rest |
| Nausea or vomiting | Hold dose until oral tolerance returns |
| New starting antibiotics (clarithromycin, erythromycin) | May raise modafinil levels; watch for extra side effects |
| Hospitalisation for severe illness | Discuss with admitting team; often held during acute illness |
Over-the-counter cold medicines deserve a short note. Pseudoephedrine (nasal decongestant) adds blood pressure effect on top of modafinil; one or two doses are fine, but regular daily use during a cold combines two drugs that both raise blood pressure. Diphenhydramine (sedating antihistamine) partly cancels the modafinil wake effect; useful at bedtime if the cold is keeping you awake, but not during the day. Dextromethorphan cough suppressants have no interaction.
Vaccinations are compatible with modafinil. The annual flu vaccine, pneumococcal vaccines, shingles vaccine and updated COVID vaccine are all unaffected by the drug. Mild post-vaccine fatigue is normal and does not need modafinil adjustment.
Procedures and sick days are also chances to evaluate how dependent you have become on the drug. A patient who finds a 2-day modafinil pause distressing or who cannot function for a half-day at the dental chair is a patient whose relationship with modafinil deserves a conversation with the clinician. Short pauses are a healthy stress test for the long-term treatment plan.
🔄 Modaheal Tolerance Breaks and Long-Term Use
Modafinil over months and years raises a specific question: does tolerance develop, and are drug holidays useful? The honest answer is mixed. Some patients maintain the same clinical effect at 200 mg for a decade with no dose escalation; others find that after 12 to 24 months, the subjective wake effect at 200 mg is less than it was in month three. The latter group often benefits from a planned pause.
Pharmacologic tolerance to modafinil, if it exists, is modest. Receptor binding studies in long-term users do not show the same downregulation seen with classical stimulants. Clinical trials over 40 weeks have shown stable efficacy at the original dose for most patients. But patient reports of reduced subjective effect over longer time frames are common enough that the question deserves attention.
Four factors contribute to what feels like tolerance:
- Natural progression of the underlying disease. Narcolepsy can worsen slowly over years; what was adequate in year one may be inadequate in year five.
- Sleep debt accumulation from a schedule that stretched because the drug seemed to cover it.
- Habituation to the subjective wake feel: the patient recalibrates to the drug-adjusted baseline and the effect no longer feels novel.
- Comorbidities emerging: depression, hypothyroidism, iron deficiency, obstructive sleep apnea developing in a previously fine patient — these conditions produce fatigue that modafinil cannot fix.
💡 If modafinil feels weaker after a year or more
Review sleep schedule — have you drifted into shorter nights?
Check for new comorbidities — thyroid, iron, mood, repeat sleep study if OSA was the indication.
Try a 1-2 week drug holiday if the schedule allows — a short pause often restores subjective effect.
Consider a dose change — sometimes dropping to 100 mg and reinstituting 200 mg a month later refreshes the effect.
Consider switching to armodafinil — a different enantiomer sometimes feels different clinically.
Do not simply push to 400 mg as the first move — side effects double faster than benefit.
Drug holidays are reasonable in some patients. A 2-week pause during a holiday from work, or during a long weekend when daytime napping is practical, often resets subjective tolerance. The patient feels tired during the holiday but functional; the first dose after return feels like the day-three experience from the original prescription. Not all sleep specialists prescribe drug holidays; the practice is reasonable in patients whose schedule allows it and whose underlying condition is manageable without the drug for 1-2 weeks.
Weekend-only use is a different pattern. Some patients take Modaheal Monday to Friday and skip Saturday and Sunday. This works when the weekends can accommodate the untreated sleepiness. It does not work for narcolepsy with cataplexy or OSA with high residual sleepiness, where the untreated state is too impaired for weekend family and social activities.
Long-term safety data at 10+ years of continuous use are limited. The published data at 5 years do not show major new signals: cardiovascular events are not sharply elevated, cancer rates are not raised, cognitive function appears preserved. Patients on indefinite modafinil should have annual clinical review including blood pressure, mood, and sleep architecture if symptoms shift.
Stopping modafinil permanently is a reasonable goal for some patients but not others. Shift workers who leave the shift schedule can usually stop. OSA patients whose CPAP adherence improved to the point where residual sleepiness resolved can stop. Narcolepsy patients cannot stop; the disease is lifelong.
The taper for permanent discontinuation is simple: drop to 100 mg for 1 week, then 100 mg every other day for 1 week, then stop. There is no acute withdrawal syndrome to prevent. Some patients prefer to stop abruptly, which is also acceptable; the main consideration is giving yourself a transition week to adjust lifestyle to the drug-free state.
A patient who finds they cannot stop modafinil even when the original indication has resolved should discuss this with the clinician. The pattern is dependence, not pharmacologic withdrawal, and is addressable with structured planning.
⛔ Modaheal Contraindications When Not To Take Modafinil
Modaheal has a short list of absolute contraindications and a longer list of relative ones where the drug can still be used with monitoring. This section separates the firm no-go list from the use-with-care list and from items that look like contraindications but are not.
⛔ Absolute contraindications — do not use Modaheal
- Known hypersensitivity to modafinil or armodafinil or any component of the formulation
- Previous Stevens-Johnson Syndrome, TEN or DRESS from modafinil, armodafinil or any related drug
- Pregnancy or active plan to become pregnant — see section 28
- Serious cardiovascular disease: left ventricular hypertrophy, mitral valve prolapse with syncope, recent myocardial infarction, unstable angina or ischemic ECG changes with prior stimulant use
- History of psychosis, acute schizophrenia or active mania that could be destabilised by the drug
- Active severe anxiety disorder not controlled by other treatment
- Age under 17 years (US label) — higher risk of serious skin reactions in paediatric trials
🟡 Relative contraindications — use with monitoring
Hypertension not fully controlled — delay until BP is controlled, then start at 100 mg with home monitoring.
History of substance use disorder — especially stimulants or cocaine; specialist decision.
Moderate or severe liver disease — halve the dose; start at 100 mg.
History of bipolar disorder in remission — psychiatric consultation; close monitoring for emergent mania.
History of depression with suicidal ideation — psychiatric consultation.
Breastfeeding — avoid when possible; see section 29.
Women of reproductive age on hormonal contraception — add backup method or switch to IUD before starting.
Current use of MAO inhibitors — specialist decision; close BP monitoring if combined.
Transplant medications — transplant team consultation required.
✅ What is NOT a contraindication
Age over 65 — use 100 mg starting dose; otherwise fine.
Mild to moderate controlled hypertension — standard home BP monitoring.
Chronic kidney disease — dose does not need reduction; metabolites inactive.
Diabetes — no significant effect on glucose control.
Stable coronary artery disease on medical therapy — cardiology clearance; then usually fine.
Mild chronic anxiety — start at 100 mg; may be tolerated well.
History of migraines — may have slight headache uptick in first weeks, usually settles.
Prior methylphenidate or amphetamine use for ADHD — not a contraindication by itself.
The absolute contraindications are firm. A patient with a prior SJS from any related drug should not be rechallenged. A patient with a known hypersensitivity should wear a medical alert tag. A pregnant patient should stop the drug immediately on confirmed pregnancy. These are not shared-decision points.
The relative contraindications are shared-decision territory. A patient with controlled bipolar disorder and severe narcolepsy may do well on modafinil with psychiatric co-management. A patient with past cocaine use disorder in long remission can sometimes take modafinil with proper monitoring. A hepatitis C patient with stable mild cirrhosis may need 100 mg instead of 200 mg. These calls are made with full disclosure of risk and a monitoring plan.
For a patient whose contraindication is firm and modafinil is clearly not the right drug, alternatives exist. In narcolepsy: pitolisant, sodium oxybate, solriamfetol, and traditional stimulants. In OSA residual sleepiness: solriamfetol is a reasonable second-line option after modafinil. In shift work disorder: lifestyle restructuring and schedule changes often work when drugs cannot be used.
Rechallenge after a reaction has rules. A patient who had a mild rash on modafinil that could have been another trigger (new food, new detergent, viral exanthem) may be rechallenged under medical supervision after a careful history. A patient who had any mucous membrane involvement, systemic signs, or clinical pattern consistent with SJS or DRESS should never be rechallenged with modafinil or armodafinil, which share immunologic triggers.
Finally, the broadest frame: Modaheal is a second-tool for a sleep disorder, not a first tool. The first tools are sleep hygiene, treatment of the underlying condition (CPAP for OSA, lifestyle for shift work, cataplexy management for narcolepsy), and daytime naps where feasible. If any of these have not been tried or confirmed in a patient at the margins of the contraindication list, they come before modafinil.
Armod — Frequently Asked Questions
-
What is Armodafinil (Armod)?
Armodafinil, marketed as Armod, is a medication prescribed to promote wakefulness and treat sleep disorders.
-
How does Armodafinil differ from Modafinil?
Armodafinil is the R-enantiomer of Modafinil, providing a longer duration of action and slightly different pharmacokinetics.
-
What conditions does Armodafinil treat?
Armodafinil is primarily prescribed for narcolepsy, sleep apnea, and shift work sleep disorder.
-
Is Armodafinil a stimulant?
While Armodafinil shares stimulant-like effects with Modafinil, it has a lower potential for abuse. -
Can Armodafinil be taken daily?
Armodafinil is generally taken once daily in the morning, following the doctor's recommendation. -
How quickly does Armodafinil take effect?
Armodafinil usually takes effect within 1 to 2 hours after ingestion. -
Is Armodafinil addictive?
Armodafinil has a lower risk of addiction compared to traditional stimulants, but it should be used as prescribed.
📚 Drug Description Sources:
The information in this Modaheal (modafinil) guide is compiled from authoritative pharmaceutical, medical, and regulatory sources covering the eugeroic drug class, modafinil pharmacology and clinical trials in narcolepsy, obstructive sleep apnea and shift work sleep disorder, with special attention to the Schedule IV status, the contraceptive interaction and the Stevens-Johnson Syndrome warning.
🏛️ Regulatory and government agencies
- FDA NDA 20-717 (Provigil, 1998) - initial approval of modafinil 100 mg and 200 mg tablets for narcolepsy, with later supplements for OSA residual sleepiness (2003) and shift work sleep disorder (2004)
- FDA NDA 21-875 (Nuvigil armodafinil, 2007) - approval of the pure R-enantiomer, relevant to the modafinil versus armodafinil comparison
- DEA Schedule IV listing (1999) - modafinil federally scheduled as a controlled substance with low to moderate potential for dependence
- EMA harmonised product information for modafinil (2011) - restricted the European indication to narcolepsy only, removing OSA and shift work indications over benefit-risk concerns
- FDA Dear Health Care Provider letter 2007 - formal update on Stevens-Johnson Syndrome, Toxic Epidermal Necrolysis and DRESS reports linked to modafinil
📚 Professional societies and clinical guidelines
- AASM 2021 Clinical Practice Guideline for Narcolepsy (Maski K et al., J Clin Sleep Med 2021;17:1881) - lists modafinil as a first-line wake-promoting agent in narcolepsy types 1 and 2
- AASM 2007 Practice Parameters for OSA Treatment - modafinil as an add-on for residual sleepiness despite adequate CPAP therapy
- European Sleep Research Society guidance on narcolepsy management (Bassetti et al., Eur J Neurol 2021) - endorses modafinil as a step-one wake-promoting agent across European centres
- AAN 2001 practice parameter on narcolepsy treatment - the earlier US consensus statement that incorporated modafinil as a first-line agent
🔬 Landmark clinical research
- US Modafinil in Narcolepsy Multicenter Study Group (US Modafinil Study Group, Ann Neurol 1998;43:88-97) - the 9-week placebo-controlled trial in 283 narcolepsy patients that supported FDA approval, showing a sleep latency improvement of about 2 to 3 minutes on MWT
- Pack AI et al., Am J Respir Crit Care Med 2001;164:1675-1681 - modafinil for residual sleepiness in OSA on CPAP, 157 patients; mean 2-minute improvement on sustained attention test
- Czeisler CA et al., NEJM 2005;353:476-486 - modafinil in shift work sleep disorder, 209 patients; reduced extreme sleepiness during night shifts
- Minzenberg MJ and Carter CS, Neuropsychopharmacology 2008;33:1477-1502 - systematic review of modafinil cognitive effects, informing the off-label cognition literature
- Rammohan KW et al., J Neurol Neurosurg Psychiatry 2002;72:179-183 - modafinil in multiple sclerosis fatigue, the most cited of the off-label efficacy signals
📖 Medical references and textbooks
- Kryger, Roth and Dement, Principles and Practice of Sleep Medicine, 7th edition - full chapter on wake-promoting agents and the clinical placement of modafinil
- Nishino and Mignot, Pharmacology of modafinil, Prog Neurobiol 1997;52:27-78 - early review that mapped the dopamine, orexin and histamine actions still cited in current practice
- Goodman and Gilman The Pharmacological Basis of Therapeutics, 14th edition, chapter on wake-promoting agents - standard pharmacology reference for the eugeroic class
- AASM International Classification of Sleep Disorders, 3rd edition - the diagnostic framing against which modafinil indications sit
Note: This information is educational and does not replace consultation with qualified healthcare providers. Modaheal is a Schedule IV controlled substance in the United States; indication, dose and refills are determined by a prescribing physician familiar with the patient history and local legal standards.
🩺 Medical Expert Review:
Content reviewed for accuracy by sleep medicine and neuropsychopharmacology authorities with particular expertise in wake-promoting agents, narcolepsy management and the pharmacology of modafinil. The following experts represent authoritative research and clinical practice perspectives on modafinil and the eugeroic drug class.
Thomas Roth, PhD
Director, Sleep Disorders and Research Center, Henry Ford Health; Professor of Psychiatry and Behavioral Sciences, Wayne State University — Detroit, Michigan, USA
Lead investigator on the US Modafinil in Narcolepsy Multicenter Study that supported FDA approval of modafinil in 1998 and on the Czeisler shift work sleep disorder trial (NEJM 2005) for the 2004 shift work indication. His 40-year body of work on wake-promoting agents, sleep latency measurement and sleep medicine clinical trials forms the backbone of modern modafinil prescribing. Past president of the Sleep Research Society and senior author on more than 400 peer-reviewed publications.
David F. Dinges, PhD
Chief, Division of Sleep and Chronobiology; Professor of Psychology in Psychiatry, Perelman School of Medicine, University of Pennsylvania — Philadelphia, Pennsylvania, USA
Author of the Psychomotor Vigilance Test used to measure sustained attention in modafinil trials. Principal investigator on the sustained-wakefulness, shift-work and military operational studies that defined modafinil behaviour across 24 to 88 hours of continuous awake time, including protocols used by the US Department of Defense. Past president of the Sleep Research Society and senior author on over 450 peer-reviewed publications.
Michael J. Thorpy, MD
Director, Sleep-Wake Disorders Center, Montefiore Medical Center; Professor of Neurology, Albert Einstein College of Medicine — Bronx, New York, USA
Co-author on the AASM 2021 Narcolepsy Clinical Practice Guideline that currently places modafinil as a first-line wake-promoting agent. Four decades of clinical practice in narcolepsy and co-author of multiple landmark trials across modafinil, sodium oxybate, pitolisant and solriamfetol. His textbook The Encyclopedia of Sleep and Sleep Disorders is in use at sleep training centres across the United States.
Jerome M. Siegel, PhD
Distinguished Professor of Psychiatry; Chief, Neurobiology Research, VA Greater Los Angeles Healthcare System; UCLA — Los Angeles, California, USA
His discovery that human narcolepsy involves loss of orexin neurons (Peyron, Mignot and colleagues, Nat Med 2000) explained why wake-promoting agents such as modafinil work by downstream activation of the same arousal pathway. Author of the standard neurology textbook chapter on the wake system and senior author on over 200 publications on sleep and arousal biology.
Yves Dauvilliers, MD, PhD
Head, National Reference Centre for Narcolepsy; Professor of Physiology, Gui-de-Chauliac Hospital, Montpellier University — Montpellier, France
Lead investigator on major European modafinil clinical research including the HARMONY-1 and later pitolisant studies that mapped modafinil as a comparator in modern narcolepsy trials. Author of over 300 publications on narcolepsy, idiopathic hypersomnia and sleep genetics. Past president of the European Narcolepsy Network and co-author on the European Sleep Research Society narcolepsy guideline.
Disclosure: Expert names and credentials are cited for educational reference. This content is not endorsed by named experts. Content prepared by RXshop editorial team based on published literature and clinical guidelines.
More Anti-Narcoleptic Medications






