Buy Lodonak (Generic Naltrexone) Online — Affordable Opioid Receptor Antagonist for Alcohol & Opioid Use Disorder


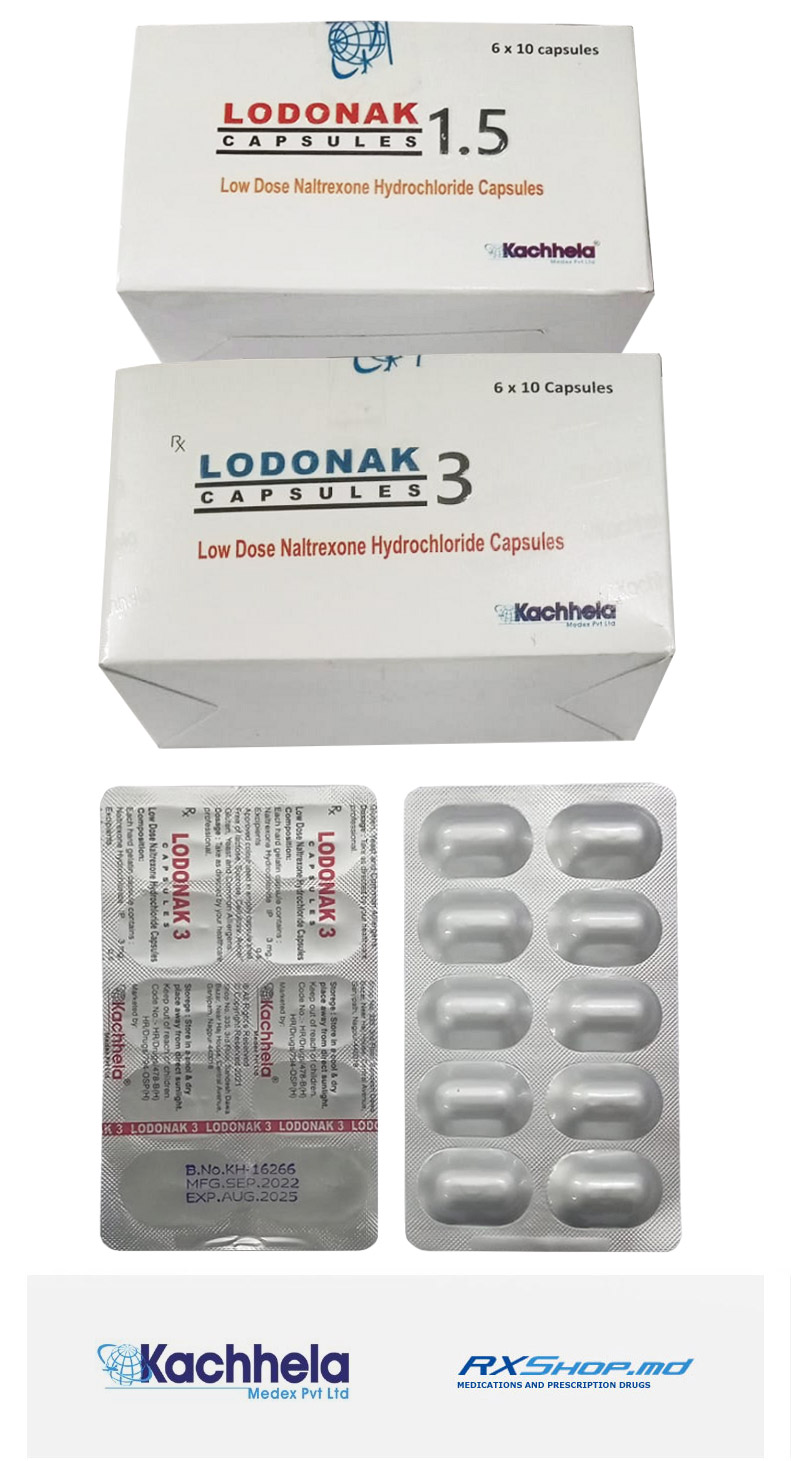
Lodonak is an affordable generic Naltrexone hydrochloride — the same proven opioid receptor antagonist molecule found in branded medications such as Revia (oral) and Vivitrol (extended-release intramuscular injection). Naltrexone represents a fundamentally different approach to alcohol use disorder than deterrent medications like Disulfiram — instead of producing an aversive reaction when alcohol is consumed, Naltrexone blocks the brain's reward response to alcohol, dramatically reducing the pleasurable effects and the craving for further drinking. As a generic Naltrexone, Lodonak delivers identical therapeutic effects to brand-name versions at a fraction of the cost.
Generic Naltrexone works as a competitive antagonist at mu, delta, and kappa opioid receptors in the brain. By blocking these receptors, it prevents endogenous opioids (endorphins) from binding when alcohol is consumed — the mechanism that normally produces the pleasurable, rewarding effects of drinking. The result is a dramatic reduction in alcohol's reward value, which translates clinically into reduced cravings, fewer drinking days, and lower likelihood of heavy drinking episodes.
FDA-approved for alcohol use disorder in 1994 and for opioid use disorder since 1984, Naltrexone has established itself as one of the most clinically important medications in modern addiction medicine. Lodonak is included on the WHO Model List of Essential Medicines, reflecting its global importance in addiction recovery programmes.
Unlike Disulfiram-based deterrent medications, generic Naltrexone does not produce a dangerous reaction if alcohol is consumed during therapy. This makes Lodonak particularly suitable for the "sinclair method" — an approach where patients continue to take Naltrexone before drinking, gradually extinguishing the conditioned association between alcohol and reward over time.
Standard dosing is 50 mg once daily orally, taken with or without food. Some clinicians use higher doses (75-100 mg) for selected patients. Lodonak is most effective in patients who have undergone medically supervised alcohol detoxification and are participating in a comprehensive recovery programme including counselling and support groups.
An important safety consideration is that Naltrexone must not be used in patients currently dependent on opioids, as it precipitates acute opioid withdrawal. A documented opioid-free period of 7-10 days is required before initiation in patients with opioid use history. Periodic liver function monitoring is recommended during long-term therapy.
Free prescription
Discrete packaging
Have questions?
Quality Assurance

- Heavy Drinking Reduction: Documented reduction in heavy drinking episodes and total weekly alcohol consumption;
- Alcohol Craving: Specifically reduces alcohol craving frequency and intensity through opioid reward blockade;
- Sinclair Method: For patients implementing pharmacological extinction approach — taking Naltrexone before drinking to gradually unlearn the conditioned reward;
- Opioid Use Disorder: For abstinence support after medically supervised opioid detoxification — particularly in patients motivated to remain opioid-free;
- Heroin Recovery: Blocks the euphoric effects of heroin if relapse occurs — supports continued opioid abstinence commitment;
- Prescription Opioid Recovery: For oxycodone, hydrocodone, fentanyl, and other prescription opioid use disorder recovery support;
- Post Detox Maintenance: Initiated 7-10 days after the last opioid dose — bridges medically supervised detox to long-term community recovery;
- Combined Substance Recovery: Single medication treats both alcohol and opioid use disorders in patients with concurrent dependencies;
- HIV HCV Coinfection Recovery: For substance recovery in patients with hepatitis or HIV who need non-hepatically-cleared options;
- Cocaine Use Disorder: Off-label use with emerging evidence supporting Naltrexone in cocaine dependence, particularly with concurrent alcohol use;
- Pathological Gambling: Off-label use for compulsive gambling disorder — reduces gambling urges through reward pathway modulation;
- Compulsive Sexual Behaviour: Off-label for hypersexuality and compulsive sexual behaviour disorders involving reward dysregulation;
- Eating Disorder Adjunct: Off-label use for binge eating disorder and bulimia — reduces compulsive food-related reward seeking;
- Fibromyalgia LDN: At 1.5-4.5 mg daily, off-label use for fibromyalgia pain modulation through neuroimmune effects;
- Multiple Sclerosis LDN: Off-label low-dose Naltrexone use for symptomatic management in multiple sclerosis;
- Crohns Disease LDN: Off-label low-dose use for inflammatory bowel disease symptom management;
- Cholestatic Pruritus: For severe itching in cholestatic liver disease where endogenous opioid pathways contribute to symptoms;
- Autism Self Injury: Selective off-label use in autism spectrum patients with severe self-injurious behaviour involving opioid pathway dysregulation.
- Less Heavy Drinking: Documented reduction in heavy drinking days when added to behavioural therapy;
- Reduced Opioid Use: Blocks euphoric effects of subsequent opioid use, discouraging relapse and supporting abstinence;
- Better Recovery Outcomes: Documented improvement in treatment retention, drug-free urine samples, and clinical recovery measures;
- Less Relapse Severity: Even when drinking or opioid use occurs, reward blockade limits relapse intensity and supports rapid re-stabilisation;
- Diminished Pleasure: Reduces rewarding subjective experience of alcohol and opioid use, weakening addiction's behavioural reinforcement;
- Better Mood: Reduced substance reward seeking supports stable mood throughout recovery;
- Better Quality of Life: Sustained recovery leads to measurable improvement in mood, relationships, work productivity, and daily functioning;
- Better Family Life: Successful recovery improves family relationships, child welfare, and economic stability;
- Better Work Life: Sustained recovery improves workplace performance and career advancement;
- Once Daily Dosing: Single 50 mg morning tablet supports adherence in busy recovery patients;
- Reduced Overdose Risk: Successful adherence reduces opioid overdose risk in opioid use disorder patients;
- Opioid Receptor Antagonist: Competitive antagonist at mu, delta, and kappa opioid receptors — broader receptor coverage than selective agents;
- Generic Naltrexone: Affordable generic versions expand global access to anti-craving therapy across financial situations;
- Revia Equivalent: Same Naltrexone molecule as branded Revia at fraction of cost — meets bioequivalence standards;
- Vivitrol Equivalent: Oral alternative to monthly injectable brand Vivitrol with same active molecule;
- Anti Craving Therapy: Reduces cravings rather than producing aversion — fundamentally different from Disulfiram-based deterrents;
- Reward Blockade: Blocks the brain reward response to alcohol and opioids, weakening addiction at its neurochemical foundation;
- Sinclair Method Therapy: Supports pharmacological extinction approach with targeted dosing before drinking;
- Dual Indication Approval: Effective for BOTH alcohol use disorder AND opioid use disorder — particularly valuable in concurrent dependencies;
- No Aversion Reaction: Unlike Disulfiram-based deterrents, no dangerous reaction occurs if alcohol is accidentally consumed — broader safety profile;
- Non Sedating Recovery: No cognitive impairment, drowsiness, or psychomotor effects — supports work, study, driving, and parenting;
- Non Controlled Recovery: Not a controlled substance — no abuse potential, no withdrawal syndrome, no diversion risk;
- Office Based Treatment: Does not require federal opioid treatment programme certification — primary care physicians can prescribe;
- No Withdrawal Risk: Stopping Naltrexone produces no withdrawal syndrome unlike methadone or buprenorphine;
- Combinable Acamprosate: Can be combined with acamprosate for multi-modal anti-craving therapy in selected patients;
- Compatible Counselling: Designed to enhance — not replace — psychological treatments like CBT, motivational interviewing, and 12-step programmes;
- LDN Therapy: At 1.5-4.5 mg off-label, used for fibromyalgia, MS, Crohn's disease, and chronic pain syndromes;
- Behavioural Addiction Spectrum: Off-label evidence supports use in gambling, eating disorders, and compulsive behaviours involving reward dysregulation;
- Liver Function Monitoring: Well-defined LFT monitoring protocols support safe long-term use across patient populations;
- Treatment As Prevention: Successful adherence reduces overdose mortality and substance-related medical complications;
- WHO Essential Medicine: Listed on the WHO Model List of Essential Medicines for addiction therapy;
- 40 Plus Year History: FDA-approved since 1984 (opioid) and 1994 (alcohol) with extensive real-world safety data;
- Stable Storage: No refrigeration required — practical for home, travel, and humanitarian distribution;
- Globally Available: Wide international availability supports continuity of recovery care across travel and relocation.
Generic Lodonak (Naltrexone Hydrochloride 1.5 mg) Medication guide:
💊 What is Lodonak (Naltrexone by Macleods)
Lodonak is a brand name for naltrexone hydrochloride, manufactured by Macleods Pharmaceuticals, one of India's largest pharmaceutical companies. The active ingredient is the same molecule found in branded ReVia, generic naltrexone, and other naltrexone products worldwide. Lodonak is widely used for the treatment of alcohol use disorder (AUD) and opioid use disorder (OUD), working through a fundamentally different mechanism than disulfiram - reducing the rewarding effects of these substances rather than creating an aversive reaction.
Key features of Lodonak
Indian pharmaceutical brand of naltrexone, manufactured in WHO-GMP certified facilities.
Same molecule used in naltrexone globally since 1984; identical mechanism.
Blocks opioid receptors; reduces alcohol and opioid reward; does not produce intoxication.
Used as part of comprehensive treatment with counseling and support.
What makes Lodonak distinctive
🏭 Macleods Pharmaceuticals and Indian generic naltrexone
Understanding Lodonak begins with understanding Macleods Pharmaceuticals - one of India's largest privately-held pharmaceutical companies and a major contributor to global generic medication access. Founded in 1989, Macleods has grown into a globally recognised manufacturer with WHO-GMP and US-FDA approved facilities. Lodonak reflects Macleods' broader commitment to producing essential medications at accessible prices.
Macleods is among India's top 10 pharmaceutical companies by revenue, specialising in anti-tuberculosis, antimalarial, and CNS medications. The company operates manufacturing facilities inspected and approved by major international regulators, exports to 170+ countries, and is recognised globally for high-volume affordable generic production.
Macleods milestones
Established in Mumbai with focus on anti-infective medications.
Expanded portfolio across multiple therapeutic categories including CNS.
Achieved US-FDA, WHO-GMP, UK MHRA, and EU EMA approvals.
Operations in 170+ countries; among India's top pharmaceutical manufacturers.
Why this matters for Lodonak users
🌍 Why Lodonak matters for global AUD and OUD access
Both alcohol use disorder and opioid use disorder are global health crises affecting hundreds of millions of people. Yet medication-based treatment remains unavailable to most who could benefit, due to cost, distribution gaps, or absence of approved options in their region. Lodonak helps close this gap, bringing naltrexone treatment within financial and practical reach across India, developing markets, and for cost-conscious patients worldwide.
WHO estimates approximately 283 million people have AUD globally; another 40+ million have OUD. Only about 2 in 100 with severe AUD receive medication treatment worldwide. In low/middle-income countries the rate falls below 1%. Cost is a major barrier - and where Lodonak is most impactful.
Regional access through Lodonak
Widely prescribed across Indian addiction medicine practice for both AUD and OUD. Used in both public and private treatment settings.
Reaches Africa, Southeast Asia, parts of Latin America, Eastern Europe through Macleods distribution network.
Uninsured patients worldwide may access Lodonak at significant cost savings versus branded alternatives.
Cost perspective (illustrative)
Approximate monthly costs for naltrexone 50 mg daily from different sources.
Indicative only. Actual pricing varies considerably by region, pharmacy, and insurance coverage.
🔀 How naltrexone differs from disulfiram (Antabuse)
Patients researching AUD treatment often compare naltrexone (Lodonak) and disulfiram (Antabuse, Carnotol). These medications have fundamentally different mechanisms, goals, and patient populations. Understanding the difference is essential - they are not interchangeable, and they treat AUD through opposite approaches.
The core mechanism difference
Blocks mu-opioid receptors that release endorphins when alcohol is consumed. Removes the rewarding feeling; alcohol becomes "uninteresting" rather than dangerous.
Blocks ALDH2 enzyme. If alcohol is consumed, acetaldehyde builds up causing severe physical reaction. Patient learns alcohol equals terrible feelings.
Detailed comparison
🔬 How Lodonak works at the molecular level
Lodonak works by blocking mu-opioid receptors in the brain. This single, precise molecular mechanism explains why naltrexone reduces alcohol craving, blocks the effects of opioids, and works for both AUD and OUD. The pharmacology is well-studied and represents one of the cleanest examples of mechanism-based pharmacotherapy in addiction medicine.
The endorphin connection
When alcohol is consumed, the brain releases endorphins. These endogenous opioids bind to mu-opioid receptors and produce the pleasant "buzz" - the reward that drives drinking.
Naltrexone occupies mu-opioid receptors with high affinity. When endorphins are released, they cannot bind. The reward signal is blocked; alcohol becomes less satisfying.
Pharmacokinetic profile
Receptor selectivity
Highest affinity. The main target. Where alcohol and opioid rewards are processed. Strong, sustained blockade by naltrexone.
Moderate affinity. Some blockade contributes to stress and dysphoria modulation. May partly explain mood effects.
Lower affinity. Less clinical relevance at standard dosing. Minor contribution to overall effect.
🍺 Lodonak for alcohol use disorder
The most common use of Lodonak is treatment of alcohol use disorder (AUD). Naltrexone is one of three FDA-approved AUD medications and arguably the most widely prescribed today, particularly in the United States. Its evidence base spans 40+ years of clinical use including landmark trials demonstrating efficacy across diverse populations.
Reduces the rewarding feeling of drinking. Reduces craving for alcohol. Reduces "heavy drinking days" and total alcohol consumed. Supports either abstinence or controlled-drinking goals depending on patient preference. Works alongside counseling and support to enable sustained behavior change.
Clinical effects in AUD
Two treatment approaches with naltrexone
Take 50 mg every day regardless of drinking plans. Maintains continuous receptor blockade. Standard approach for abstinence goal.
Take 50 mg 1-2 hours BEFORE drinking only. Each drinking episode becomes less rewarding; drinking habits gradually extinguish.
Evidence highlights
Naltrexone is most effective when combined with counseling. Patients who use the medication alone, without behavioral support, see smaller benefit. Skills for managing craving, stress, and social drinking situations matter alongside the pharmacological effect.
💉 Lodonak for opioid use disorder
Beyond AUD, Lodonak is also approved for opioid use disorder (OUD). In this role, naltrexone blocks opioid receptors so completely that taking opioids produces no effect - no euphoria, no pain relief, no respiratory depression. This makes it useful for maintaining abstinence after detoxification, but it carries critical safety requirements that differ entirely from naltrexone's AUD use.
Starting Lodonak while still opioid-dependent will trigger precipitated withdrawal - sudden, severe withdrawal symptoms that can be medically dangerous. Patient must be fully opioid-free for 7-14 days before starting Lodonak.
How Lodonak works for OUD
Naltrexone occupies mu-opioid receptors with high affinity, preventing exogenous opioids from binding.
If patient takes opioids while on naltrexone, they cannot produce their usual effects. Removes incentive to use.
Knowing opioids won't work removes the rational appeal of using; supports sustained abstinence.
OUD vs AUD - key differences
When Lodonak fits OUD treatment
- Patients who have completed detoxification (opioid-free 7-14 days)
- Strong external motivation (legal, professional licensing, etc.)
- Stable living situation with supervision available
- Pattern of relapse from short-term opioid exposure
- Cannot or do not want to use buprenorphine or methadone
- Highly motivated and committed to abstinence
When patients stop naltrexone and then relapse to opioid use, their tolerance has dropped significantly during the months on medication. The same dose they used before treatment can cause fatal overdose. This is the single most important safety issue with naltrexone for OUD.
🎯 The Sinclair Method explained
The Sinclair Method is a specific approach to using naltrexone for AUD that emphasises reduced drinking rather than total abstinence as the primary goal. Developed by Finnish researcher Dr. David Sinclair, it uses pharmacological extinction - the gradual unlearning of drinking habits when the reward is consistently blocked. The method has gained substantial support, particularly in Europe.
Take naltrexone 1-2 hours BEFORE drinking. When alcohol is consumed with receptors already blocked, no reward is felt. Over weeks and months, the brain "unlearns" that alcohol equals reward. Drinking gradually becomes less interesting and less frequent.
How to do the Sinclair Method
Recognise you are about to drink. Self-honesty matters - this doesn't work if you take it later.
Take Lodonak 1 to 2 hours before the first drink. With water; with or without food.
Do not try to "drink through it." Notice that drinking is less rewarding than usual.
Take before EVERY drinking session. Over 3-6 months, drinking patterns shift.
Sinclair Method vs daily naltrexone
Does it work?
The Sinclair Method has demonstrated efficacy in multiple studies for reducing heavy drinking and helping some patients transition toward abstinence. Success rates of 60-80% in motivated patients have been reported. The method is officially endorsed for AUD treatment in Finland and recognised across Europe.
👮 Identifying patients who benefit from Lodonak
As with any medication, patient selection significantly affects Lodonak outcomes. Naltrexone works better for certain AUD/OUD profiles than others. Understanding who benefits most - and who is less likely to benefit - helps providers and patients make appropriate treatment choices.
Good fit vs poor fit
- Strong craving as core feature of AUD
- Drinking is rewarding/reinforcing rather than compulsive
- Open to either abstinence or reduction goal
- Willing to take medication daily or before drinking
- Liver function reasonable
- Not currently taking opioid medications
- Engaged in counseling alongside medication
- Previous trial of disulfiram failed or unsuitable
- Requires opioid pain medications for chronic pain
- Active opioid use (without proper washout)
- Severe liver dysfunction
- Pregnancy
- Cannot maintain daily adherence to oral medication
- Hypersensitivity to naltrexone
- Cannot stop opioids for 7-14 days before OUD use
- Drinking driven primarily by withdrawal relief, not reward
Patient profile types where Lodonak particularly helps
Strong reward from drinking, difficulty stopping at one drink, no daily compulsion.
Sinclair Method ideal patient. Wants moderation rather than total abstinence.
Has tried abstinence but craving overwhelms decisions; needs the craving reduction.
Completed opioid detox, highly motivated, has external accountability and stable support.
Physician, pilot, healthcare worker with monitoring requirements; documented adherence.
Cardiac history, hepatic concerns, or just unable to tolerate aversive approach.
Patient values evidence-based pharmacotherapy without aversive component.
Lodonak's affordability versus branded alternatives important factor in feasibility.
📋 Standard Lodonak dosing
Lodonak dosing is straightforward and identical to other naltrexone products. The standard adult dose is 50 mg once daily. Some patients use lower doses (25 mg) initially or for sensitivity reasons. Higher doses (100 mg) are sometimes used in specific situations but offer marginal additional benefit. The medication is taken with or without food at a consistent time each day.
When to use lower or modified doses
Start at 25 mg for first 3-5 days; helps assess tolerability before full dose. Increase to 50 mg if no significant side effects.
May start and maintain at 25 mg; slower titration; more frequent monitoring during early weeks.
Consider 25 mg/day with closer LFT monitoring. Moderate-to-severe liver disease: avoid.
Standard 50 mg dose taken 1-2 hours before drinking only (not daily). See Sinclair Method section.
When to take Lodonak
Practical daily-use rules
◆ With or without food - food does not significantly affect absorption
◆ With water - standard way to swallow tablet
◆ Do not crush or split - tablet not designed for division
◆ If you miss a dose - take when remembered same day; do not double
◆ For OUD - missing doses creates relapse risk; build adherence support
◆ Tell prescriber if doses missed regularly - adjust plan
⏱️ The critical opioid washout requirement
The single most critical safety requirement for starting Lodonak is being completely opioid-free. Starting naltrexone while opioids are still present in the body precipitates immediate, severe withdrawal - a medically dangerous reaction that requires emergency care. Both patients and providers must understand and respect this requirement absolutely.
If naltrexone is taken while opioids occupy mu-receptors, it displaces them with extreme rapidity. This causes severe withdrawal symptoms compressed into minutes rather than hours. The reaction includes profuse vomiting, severe muscle pain, agitation, autonomic instability, and can be life-threatening. Recovery requires emergency medical support.
Required opioid-free periods
Pre-treatment screening
Detailed history of opioid use including prescription, OTC, and illicit. Be specific about timing and last use.
Standard pre-naltrexone test. Must be negative for all opioid metabolites before first dose.
Sometimes used: small naloxone test dose, observe for any withdrawal signs before naltrexone.
Often start with 25 mg as first naltrexone dose - smaller reaction if any opioid still present.
If precipitated withdrawal occurs
- Symptoms within 30-60 minutes of naltrexone - severe nausea/vomiting, abdominal cramping, restlessness, muscle aches, sweating, tachycardia
- Call emergency services - this is a medical emergency
- Supportive care at ER - fluids, antiemetics, sometimes clonidine for autonomic symptoms
- Cannot be reversed by giving opioids - naltrexone blockade is too strong
- Resolves in 12-24 hours typically, though distressing
🕑 Lodonak timeline - when it starts and how long it lasts
Lodonak has a relatively quick onset and short residual effect compared to disulfiram. Naltrexone reaches peak plasma levels within an hour, blocks receptors within 1-2 hours, and most effects resolve within 1-3 days of stopping. Understanding this timeline helps patients plan around medical procedures, surgery, and any need to stop treatment.
The Lodonak timeline at a glance
How Lodonak compares to other AUD medications
Practical scenarios
Take today's dose at normal time. The 24-hour coverage from each dose means short gaps have less impact than with some other medications - but build daily routine.
Discuss with surgeon. Naltrexone blocks opioid pain medications - may need to stop 3-7 days before procedure. See dedicated surgery section.
Effect resolves in 1-3 days. Much shorter washout than disulfiram. For OUD patients - be cautious about reduced opioid tolerance.
Shift by a few hours if necessary. The medication does not need precision timing. Resume normal schedule once settled.
📝 Adherence challenges with daily oral naltrexone
One of the most well-documented limitations of oral naltrexone is adherence. Real-world adherence to daily oral medication for AUD averages only 30-50% over months, and naltrexone specifically faces additional adherence challenges - patients can feel "fine" without it, removing daily reminder of the problem the medication addresses. Understanding adherence challenges helps build strategies to overcome them.
Adherence reality with oral naltrexone
Why oral naltrexone is hard to stay on
Strategies to improve adherence
Take with a fixed daily routine (breakfast, brushing teeth, morning coffee). Habits stick better than discrete decisions.
Weekly pill box provides visual confirmation each day. Especially helpful in early treatment when adherence matters most.
Recurring alarm at consistent time. Most people now check phones immediately - works well for medication.
Brief daily moment with partner/family member during dosing. Removes "did I take it?" uncertainty.
Discuss medication taking each session. Address ambivalence as it surfaces rather than letting it grow.
If adherence consistently struggles, Vivitrol monthly injection removes the daily decision entirely.
If you have been opioid-free during the gap, restart at full dose. If you used opioids while off naltrexone, you must establish the 7-14 day opioid-free period again before resuming.
🆚 Lodonak (oral) vs Vivitrol (monthly injection)
Vivitrol is the brand name for extended-release injectable naltrexone - approved by the FDA in 2006 for OUD and 2010 for AUD. Lodonak is the daily oral form; Vivitrol is the same molecule reformulated as a monthly injection. Choosing between them is a meaningful decision affecting adherence, cost, and clinical strategy.
Side-by-side
- 50 mg once daily, oral
- Onset: 1-2 hours
- Washout: 1-3 days
- Cost: lower per month
- Stop anytime quickly
- Daily adherence required
- Patient controls dosing
- 380 mg IM every 4 weeks
- Onset: days to peak
- Washout: ~1 month
- Cost: significantly higher
- Cannot stop quickly
- One decision per month
- Requires clinic visit
Detailed comparison
Common questions
Yes. Take last oral dose, then within 1-3 days receive the injection. Many patients start oral first to confirm tolerance before committing to the injection.
Yes. Wait approximately 30 days after last injection, then start oral naltrexone. Some patients prefer the lower cost and flexibility of oral once they have established stability.
Comparable when both are adhered to. In real-world settings where adherence is the main challenge, Vivitrol often performs better simply because monthly dosing is more reliable than daily.
Limited availability and very high cost in many markets. Lodonak is far more accessible. This is one major reason oral naltrexone remains the practical option for many patients globally.
👭 Combining Lodonak with counseling and support
Lodonak by itself is not enough. The strongest evidence for naltrexone treatment - including the landmark NIAAA COMBINE Study - consistently shows that medication combined with counseling outperforms medication alone. The pharmacological effect (reduced craving and reduced reward) enables sustained behavior change; counseling builds the skills that enable that change to last.
The 2006 NIAAA COMBINE Study tested combinations of medications and behavioral interventions in over 1,300 AUD patients. The major finding: naltrexone combined with brief medical management was as effective as naltrexone combined with intensive cognitive behavioral therapy - both significantly better than naltrexone alone. The behavioral component matters.
Evidence-based counseling approaches
Mutual support groups
Alcoholics Anonymous; 12-step; worldwide free meetings.
Science-based; CBT framework; secular.
Reduction-focused; aligns with Sinclair Method users.
Narcotics Anonymous - for OUD context use.
How counseling and medication work together
Some effect, but significantly less. Patients who use medication alone have modest improvements compared to placebo; those with combined counseling+medication have meaningfully better outcomes. Counseling teaches the skills medication enables.
Weekly is standard during early treatment (first 3-6 months); spacing out to monthly or as-needed once stable. The pattern that works long-term matters more than the absolute frequency.
Many evidence-based options exist beyond 12-step. SMART Recovery, individual CBT, MET, Moderation Management all work. Lodonak does not require any specific support model.
🚨 Lodonak Side Effects Overview
Lodonak side effects fall into two patterns: short-term effects during the first few days to weeks (typically mild and self-limiting), and longer-term effects that may persist or develop during ongoing use. Most patients tolerate Lodonak well; serious side effects are uncommon but require attention when they occur.
Prevalence of common Lodonak side effects
Approximate frequency from clinical experience with naltrexone.
Side effects by category
- Nausea (early days)
- Headache
- Mild fatigue
- Insomnia or vivid dreams
- Anxiety, irritability
- Joint or muscle pain
- Decreased appetite
- Mood changes
- Hepatotoxicity
- Severe depression
- Suicidal thoughts
- Severe allergic reaction
🟢 Common Lodonak side effects
This section focuses on the day-to-day side effects most Lodonak patients may notice. Most are mild, develop early in treatment, and improve as the body adapts. Understanding each one - what it feels like, why it happens, and what helps - prevents unnecessary worry and supports adherence.
Common day-to-day side effects
Mild to moderate nausea during first 1-2 weeks. Take with food, start at 25 mg, give body time to adapt.
Mild dull headache; usually resolves within 2-3 weeks. Hydration; standard analgesia (acetaminophen) if needed.
Mild tiredness particularly during dose-onset hours. Take at bedtime if disruptive to daytime function.
Some patients have unusual dream activity or sleep disruption. Take in morning if bothering at night.
Light-headedness particularly with position changes. Adequate hydration; stand up gradually.
Mild increased anxiety in some; mu-receptor blockade affects mood circuits. Discuss with provider if pronounced.
Mild reduction; sometimes modest weight loss. Usually not concerning. Monitor if significant.
Abdominal discomfort, soft stools, or constipation. Take with food; mild and usually transient.
When to call vs manage at home
Side effect resolution timeline
Peak side effects; nausea, headache most prominent
Significant improvement for most; body adapting
Most patients stable; minimal residual effects
Generally well tolerated; periodic monitoring
🟡 Less common and rare side effects
Beyond the common side effects, Lodonak can occasionally cause less frequent but more serious reactions. These rare effects make periodic monitoring (especially liver function tests) and patient awareness of warning symptoms important. This section catalogues the less common and rare side effects and their warning signs.
Less common side effects (1-3%)
Mild arthralgia or myalgia. Often transient. NSAIDs help; rule out other causes if persistent.
Some patients report sexual side effects. Less common than with SSRIs but possible. Discuss if affecting quality of life.
Some patients develop depression or low mood. Endorphin blockade may contribute. Monitor closely; may need to stop.
Mild dermatologic reactions occasionally. Severe rash requires immediate evaluation.
Some patients notice. Usually mild; adequate hydration. Not usually clinically significant.
ALT/AST slight increases in some patients. Monitor; usually does not require stopping unless higher.
Rare side effects (<1%)
Marked LFT elevation or clinical hepatitis. Very rare at standard doses; higher risk in pre-existing liver disease.
Major depressive episode emerging during treatment. Requires evaluation and possible discontinuation.
Reported rarely. Most likely in patients with predisposing factors. Immediate evaluation needed.
Widespread rash, angioedema, anaphylaxis. Stop immediately and seek emergency care.
Warning signs - call provider immediately
Rare serious side effects are why Lodonak requires medical supervision, periodic LFT monitoring, and patient awareness of warning signs. Most serious effects can be detected early - while still reversible - if patients know what to watch for and stay engaged with their treatment team.
🚫 Lodonak Contraindications and Warnings
Lodonak is contraindicated in several specific conditions where the risk of taking the medication outweighs the benefit. Absolute contraindications mean the medication must not be used. Relative contraindications mean special caution, additional monitoring, or alternative treatments should be considered. Pre-treatment screening for these is part of safe Lodonak prescribing.
Absolute contraindications
Lodonak must NOT be prescribed if any of the following apply.
Patient still has opioids in system from regular use. Causes precipitated withdrawal - medical emergency.
In acute withdrawal phase - need to complete full 7-14 day washout before starting.
Acute hepatitis or hepatic failure. Lodonak is hepatically metabolised; risk too high.
Patients requiring opioids for chronic pain cannot effectively use Lodonak - blocks pain relief.
Known allergy to naltrexone or related compounds. Risk of serious allergic reaction.
Generally avoided. Insufficient safety data; alternative approaches preferred.
Relative contraindications
Use only with caution; additional monitoring; alternatives often preferred.
Pre-treatment screening checklist
🫀 Liver safety with Lodonak
Like many medications metabolised by the liver, Lodonak can occasionally affect liver function. Hepatotoxicity is the most clinically significant rare adverse effect. While severe liver injury is uncommon at therapeutic doses (estimated 1-2% of patients), the risk is real - and historically there was an FDA black-box warning at one time. This makes pretreatment LFT baseline, periodic monitoring, and patient awareness of warning symptoms essential.
Understanding your LFTs
Standard LFT monitoring schedule
Baseline ALT, AST, bilirubin before first dose
First check; assess any early hepatotoxicity
Quarterly during first year of treatment
Long-term: every 6 months after stable
Warning signs of liver injury
Yellow tinge in skin or whites of eyes. Direct sign of significant liver dysfunction.
Tea or cola-coloured urine suggests bilirubin spillover.
New or worsening nausea beyond early treatment phase.
Notable change from baseline; sense of being unwell.
Discomfort in right upper abdomen where liver sits.
Clay-coloured stools indicate impaired bile excretion.
Risk factors for hepatotoxicity
- ALT or AST > 5x upper normal
- Clinical hepatitis symptoms (jaundice, RUQ pain, dark urine)
- Rising trend across multiple checks
- Bilirubin elevation beyond mild
🤰 Lodonak during pregnancy
Lodonak (naltrexone) is generally avoided during pregnancy. While naltrexone has not been definitively shown to cause birth defects in humans, safety data are limited. The risk-benefit analysis depends heavily on the indication - AUD vs OUD have different considerations during pregnancy. Specialist consultation is appropriate for any pregnant patient considering naltrexone.
FDA pregnancy category for naltrexone: limited safety data. Animal studies have shown some adverse effects at high doses. Human exposure data is limited. Generally avoid during pregnancy when alternatives exist; weigh carefully if severe AUD/OUD where alternatives are inadequate.
Trimester considerations
Period of organogenesis; highest concern for any drug exposure. Lodonak particularly avoided. Pregnancy testing before starting recommended.
Organ systems established but still developing. Lodonak still avoided. Behavioral approaches remain mainstay.
Fetal growth phase. Still avoided. Planning for postpartum AUD/OUD management important - high relapse risk period.
AUD vs OUD pregnancy considerations
Pre-conception planning
- Discuss pregnancy plans with addiction medicine provider
- Transition to alternative AUD/OUD treatment before conception
- 1-3 day Lodonak washout adequate before conception attempts
- Increase counseling and support engagement during transition
- Engage obstetric care early
- Plan postpartum AUD/OUD management - relapse risk peaks
- Family/partner support for prenatal sobriety
🤱 Lodonak during breastfeeding
Lodonak use during breastfeeding is not generally recommended. Naltrexone and its metabolites pass into breastmilk, and infant safety data are limited. For breastfeeding mothers requiring AUD or OUD treatment, alternative approaches that allow continued safe breastfeeding are preferred when possible.
Naltrexone passes into breastmilk in detectable amounts. Long-term safety of infant exposure has not been adequately studied. Most guidelines recommend either avoiding Lodonak while breastfeeding, transitioning to alternatives, or considering weaning if pharmacotherapy is essential.
Common questions about Lodonak & breastfeeding
Generally not recommended. Discuss with provider. Alternative AUD/OUD treatments or weaning are usually preferred.
Standard washout: 3-5 days. Naltrexone clears the system in 1-3 days; metabolites in a few more. Confirm with treating provider.
Contact provider. Often the advice is to "pump and discard" milk for 1-3 days while Lodonak clears. Single accidental exposures are unlikely to cause harm but consultation is appropriate.
Some mothers with severe AUD/OUD may choose to wean to access Lodonak. Personal decision - balance breastfeeding benefits against pharmacotherapy benefits. Discuss with both pediatrician and addiction provider.
Alternatives during breastfeeding
Compatible with breastfeeding. CBT, motivational enhancement, group support all work without medication.
Partner involvement; family therapy; structured social support during postpartum.
For AUD - limited data; sometimes considered when severity warrants pharmacotherapy.
For OUD - more breastfeeding safety data than naltrexone; often preferred during lactation.
If choosing to wean for Lodonak treatment
Sudden cessation uncomfortable; gradual over weeks preferred.
Transition to formula or solid foods per infant's age.
Weaning adds stress; reinforce counseling and family support.
After milk supply fully suppressed; usually 1-2 weeks after last feeding.
👴 Lodonak in older adults
Older adults (typically 65 and over) require special considerations when using Lodonak. Age-related changes in liver and kidney function, increased side effect sensitivity, higher likelihood of cardiovascular comorbidity, and frequent polypharmacy all affect how the medication should be used. With appropriate adjustments, naltrexone can be used safely in this age group, but the threshold for caution is lower than in younger patients.
Why aging matters for Lodonak
Several physiological changes that come with age affect how Lodonak works in the body. Hepatic clearance declines, meaning naltrexone metabolites can accumulate at standard doses. Renal function reduces, slowing elimination. Older adults are also more sensitive to side effects from many medications - what feels mild in a 40-year-old can feel disruptive in someone over 70.
The other major consideration is polypharmacy. The average older adult takes five or more medications, creating more chances for drug interactions with Lodonak. A thorough medication review before starting is even more important than in younger patients.
Start at 25 mg daily for the first weeks. Many older adults remain on 25 mg long-term and do not need to increase. The loading approach is typically skipped entirely - go directly to maintenance dose with gentler titration.
Slower titration and closer monitoring during the first few weeks help catch any tolerability issues early. If 25 mg is well tolerated for 2-4 weeks, increase to 50 mg only if clinical response is inadequate at the lower dose.
Common challenges in older adults
Monitoring should be more frequent than in younger patients. Liver function tests every 1-2 months during the first six months of treatment, then quarterly long-term. Many older adults benefit from family or caregiver involvement in monitoring for new side effects they may not report on their own.
"Start low, go slow" applies fully to Lodonak in older adults. Beginning at 25 mg/day, monitoring closely, and adjusting upward only if needed is much safer than starting at standard dose and adjusting downward after problems develop.
🪷 Lodonak with kidney or liver impairment
Both liver and kidney function affect Lodonak metabolism and elimination. The liver metabolises naltrexone into its active metabolite (6-beta-naltrexol); the kidneys excrete both. Patients with impaired organ function need adjusted dosing, more intensive monitoring, or in severe cases avoidance of Lodonak altogether. This section provides practical guidance for the spectrum of organ impairment encountered in clinical practice.
Liver impairment
Hepatic impairment is the most common organ-function consideration with Lodonak. The clinical approach depends on severity, ranging from standard dosing in mild liver disease to absolute contraindication in decompensated cirrhosis.
For patients with mild liver concerns, more frequent monitoring usually allows safe use. The earlier any worsening of liver function is detected, the more reversible it tends to be. Moderate impairment should prompt specialist consultation before starting Lodonak - sometimes the AUD severity justifies cautious use, sometimes alternatives are clearly preferable.
Kidney impairment
Naltrexone is primarily renally excreted. Kidney function affects how quickly the medication and its metabolites clear from the body. Significant renal impairment can cause accumulation and increased side effects at standard doses.
- eGFR >60 mL/min: Standard 50 mg daily dose; no specific adjustment
- eGFR 30-60 mL/min: Consider 25 mg; more frequent monitoring; watch for accumulation
- eGFR <30 mL/min: Generally avoid; specialist decision if used
Even normal-for-age kidney function in older adults clears medications more slowly than in younger adults. This is one reason older patients often do well on 25 mg long-term rather than progressing to 50 mg.
Decision approach for impaired patients
When organ impairment is present, the question becomes whether the benefit of Lodonak outweighs the increased risk. For severe alcohol or opioid use disorder where untreated substance use is causing ongoing harm, the answer is often yes - but only with appropriate dose reduction and monitoring. For mild AUD where behavioral approaches alone might suffice, the safer path may be to skip naltrexone entirely.
Specialist consultation is the right approach for any uncertain situation. Hepatology, nephrology, or both can help determine whether the impairment is stable enough to permit cautious Lodonak use.
Lower starting dose plus more frequent monitoring lets most patients with mild-to-moderate organ impairment use Lodonak safely. The combination of dose adjustment and vigilance is what makes the difference, not just one or the other.
🧠 Lodonak in patients with co-occurring mental illness
Alcohol and opioid use disorders commonly co-occur with other mental health conditions: depression, anxiety, PTSD, bipolar disorder, and others. Lodonak can be used in patients with mental illness, but the underlying psychiatric condition must be stable and adequately treated first. Active psychosis or untreated severe mental illness are contraindications to starting naltrexone.
The stability principle
Mental health stability before starting Lodonak is the fundamental requirement. The medication requires consistent adherence, judgment about avoiding alcohol exposure or opioid relapse, and engagement with treatment - all of which are impaired during acute psychiatric instability. The general rule is to treat the psychiatric condition first, then add Lodonak once stable.
This does not mean dual diagnosis patients are excluded from naltrexone treatment. Quite the opposite - most AUD and OUD patients have at least one co-occurring mental health condition, and naltrexone is an important treatment option. The key is timing and coordination of care.
Condition-by-condition compatibility
Coordination of psychiatric and addiction care
Both providers - the psychiatric specialist and the addiction medicine provider - need to know what the other is doing. Patients who get their mental health care from one office and their AUD treatment from another can receive conflicting advice or have side effects misattributed. Integrated dual-diagnosis programs do this naturally; otherwise the patient often needs to be the bridge between providers.
Mood monitoring during Lodonak treatment deserves special attention. A minority of patients experience worsened mood on naltrexone, possibly related to endorphin receptor blockade affecting mood circuits. If new or worsening depression appears during treatment, contact the provider promptly. The medication can be stopped if needed.
Stop Lodonak and contact your provider or emergency services immediately. Naltrexone is not a common cause of suicidal ideation, but when it appears in patients with predisposing factors, urgent evaluation is appropriate.
Single-condition counseling (just AUD or just depression) is less effective than integrated approaches addressing both simultaneously. Find a treatment team that handles dual diagnosis, or coordinate explicitly between providers if separate offices.
🆘 The opioid emergency problem
One of the most distinctive considerations with Lodonak is what happens if you need opioid pain relief while on the medication. Because naltrexone blocks mu-opioid receptors, standard opioid analgesics simply do not work. This creates real problems in emergency situations - severe trauma, sudden surgery, kidney stones, severe cancer pain - where opioids would normally be the first-line treatment.
If you experience a medical emergency requiring opioid pain control while on Lodonak, standard doses of morphine, fentanyl, or oxycodone may produce inadequate pain relief. This is not a hypothetical concern - it has real implications for emergency care planning.
Telling emergency staff about Lodonak
Always inform emergency medical staff that you are taking naltrexone. The information directly affects their treatment decisions. Carry a medical alert card or wear a medical alert bracelet noting "naltrexone (Lodonak) - mu-opioid antagonist." Both the medication name and the mechanism note matter for emergency staff who may not be familiar with naltrexone specifically.
If you are unconscious or unable to communicate, the alert bracelet may be the only way emergency staff know to adjust pain management strategy. This is one situation where the inconvenience of wearing identification is genuinely worth it.
How emergency teams handle pain on naltrexone
The clinical approach depends on the urgency. For minor injuries with manageable pain, non-opioid medications often suffice. For severe trauma or major surgery, regional anesthesia and high-dose opioid strategies under close monitoring may be needed. Many anesthesiologists and emergency physicians have encountered naltrexone patients before and have established protocols.
Planning for predictable medical events
For planned procedures, the simplest approach is to stop Lodonak ahead of time. A 3-7 day washout before elective surgery allows opioid analgesics to work normally during recovery. After healing, the medication can be resumed. This is discussed in more detail in the surgery section.
For unpredictable emergencies, planning means having the medical alert visible and having had at least one conversation with your AUD treatment provider about emergency scenarios - so you know what to communicate and what to ask for.
Ask your AUD provider: "What would I do if I had a severe injury or surgery while on Lodonak?" Their answer will give you a plan and a phone number to call. Five minutes of preparation can prevent serious complications in an emergency.
🏥 Surgery and acute pain management on Lodonak
Planned surgery on Lodonak requires careful coordination between the addiction medicine provider, the surgeon, and the anesthesiology team. For most elective procedures, the simplest approach is to stop Lodonak in advance - allowing opioid analgesics to work normally during recovery, then resuming the medication once healing is complete. Emergency surgery is more complex but still manageable with the right communication.
The basic rule for elective surgery
Naltrexone clears the system in 1-3 days after the last dose; 3-7 days provides a safety margin and ensures opioid receptors are fully available for postoperative pain control.
Tell every member of the surgical team: surgeon, anesthesiologist, pre-op nursing, recovery nursing. The information directly affects medication choices throughout the perioperative period. Many hospitals have specific protocols for patients on naltrexone - some will not perform certain elective procedures unless the medication has been held for the appropriate window.
Pre-surgery timeline
The post-operative period deserves particular attention. Patients restarting Lodonak after surgery face the same opioid washout requirement as initial naltrexone treatment - 7 to 14 days off all opioids before the first naltrexone dose. Restarting too early risks precipitated withdrawal.
Emergency surgery
If emergency surgery cannot be delayed for naltrexone washout, the anesthesia and pain teams have several options. Regional anesthesia (epidural, spinal, nerve blocks) avoids the need for systemic opioids entirely. High-dose opioids can sometimes overcome receptor blockade with careful titration and monitoring. Non-opioid analgesics like NSAIDs, acetaminophen, and ketamine can manage moderate pain.
For these patients, intensive monitoring during the perioperative period is essential. When Lodonak eventually clears and receptors become free again, normal opioid doses can suddenly cause much more sedation and respiratory depression than expected. The transition period requires vigilance.
Non-opioid pain strategies
For minor procedures - dental work, dermatology, minor outpatient surgery - non-opioid pain management is often sufficient and Lodonak does not need to be stopped. NSAIDs (ibuprofen, naproxen) work normally on Lodonak. So does acetaminophen, local anesthetics, and most regional blocks. This avoids the disruption of stopping AUD treatment for minor reasons.
When scheduling any procedure - dental, dermatology, minor surgery - mention naltrexone during the consultation, not on the day of the procedure. This gives the team time to plan pain management appropriately and avoids last-minute schedule changes.
🔄 Drug interactions with Lodonak
Lodonak has a relatively clean interaction profile compared to many psychiatric medications. The most clinically significant interactions involve opioids (obviously) and a few specific other drug classes. Pre-treatment medication review is straightforward but important, and ongoing vigilance about new prescriptions matters throughout treatment.
Major interactions to know about
The opioid interactions are the central concern. This includes prescription opioids, over-the-counter cough preparations containing codeine or dextromethorphan in some formulations, illicit opioids, and even some herbal products. If unsure whether a medication contains opioid activity, ask the pharmacist before taking.
Generally safe combinations
Most psychiatric medications can be used safely with Lodonak. SSRIs, SNRIs, mood stabilisers (lithium, lamotrigine), and most antipsychotics have no significant interaction. Most antihypertensives, antidiabetics, and statins also coexist with Lodonak without problems. This makes naltrexone considerably easier to use in dual-diagnosis patients than some other addiction medications.
The category that requires more care is hepatotoxic medications. Acetaminophen at standard doses is fine, but high or chronic doses combined with Lodonak warrant closer LFT monitoring. Similarly for isoniazid (TB treatment), methotrexate, and a few others.
Practical management
Tell every new prescriber that you take naltrexone. Mention it during pharmacy interactions, dental visits, urgent care, emergency departments. Most providers know about the interactions but they can only adjust if they know you are on the medication. A wallet card listing Lodonak as a current medication makes these conversations easy.
- List all prescription medications including OTC, supplements, herbal products
- Specifically ask about any opioid-containing products (cough syrups, pain medications)
- Check for hepatotoxic medications that may compound liver risk
- Identify thioridazine or other interaction-prone psychiatric meds
- Update your pharmacy and electronic medical record so future prescriptions are checked automatically
Use one pharmacy for all your medications when possible. Modern pharmacy systems automatically flag potential interactions if all prescriptions are in one place. Multiple pharmacies fragment the safety check.
🆚 Lodonak vs Antabuse/Carnotol (disulfiram)
The most common medication comparison patients face for AUD is between Lodonak (naltrexone) and disulfiram (Antabuse, Carnotol). These two FDA-approved AUD medications work through completely different mechanisms and suit different patient profiles. Understanding the difference is essential for making the right treatment choice.
The mechanism difference
Naltrexone is an anti-craving medication. It blocks the mu-opioid receptors that normally release endorphins when alcohol is consumed - the chemical pathway that makes drinking rewarding. With Lodonak, alcohol becomes less interesting; the satisfaction is removed. The medication does not prevent drinking; it just removes the reward.
Disulfiram is an aversive medication. It blocks the ALDH2 enzyme, so if alcohol is consumed, acetaldehyde accumulates and produces severe physical symptoms - flushing, vomiting, tachycardia, headache. The medication deters drinking through threat of unpleasant consequence, not through any direct effect on craving or reward.
Side-by-side comparison
Choosing between them
Lodonak fits patients who experience strong cravings or reward from alcohol and want to reduce that. It also fits patients who want flexibility - abstinence is good but moderation may also be acceptable. The Sinclair Method (covered separately) particularly suits patients who can plan their drinking and want a gradual extinction approach.
Disulfiram fits patients who need an external deterrent against impulsive drinking. The classic profile is "I can be sober for stretches but I keep slipping after one drink." For these patients, the threat of severe reaction provides a hard stop that craving reduction cannot. Disulfiram patients must commit fully to abstinence and accept the safety requirements around hidden alcohol sources.
Many patients try one and switch to the other. The mechanisms are so different that response varies significantly. A failure on naltrexone does not predict failure on disulfiram, and vice versa.
Yes - some patients benefit from both medications simultaneously, getting the chemical deterrent of disulfiram plus the reduced craving of naltrexone. Specialist consultation is appropriate. Combined liver function monitoring becomes especially important since both medications have hepatic considerations.
🆚 Lodonak vs Acamprosate for AUD
Acamprosate (Campral and other brands) is the third FDA-approved medication for AUD. It works by modulating glutamate and GABA neurotransmission to reduce the prolonged withdrawal-related discomfort that drives relapse. This is yet another mechanism - completely different from naltrexone's anti-reward approach and disulfiram's aversive approach.
The mechanism difference
Naltrexone (Lodonak) acts at the moment of drinking - removing the reward when alcohol is consumed. It is most useful when craving is driven by anticipation of reward.
Acamprosate acts during recovery - helping the brain heal from the prolonged neurochemical disruption of chronic alcohol use. It is most useful when craving is driven by ongoing discomfort, sleep problems, anxiety, and "everything feels wrong" sensations during early sobriety. The neurochemistry it targets takes weeks to months to normalise.
Side-by-side comparison
Which fits which patient
Lodonak fits patients whose AUD includes strong reward-seeking - "I crave that feeling I get when drinking." It also fits patients who want flexibility about reduction versus abstinence, and patients who prefer once-daily dosing over three-times-daily.
Acamprosate fits patients who have completed detoxification and are in early recovery struggling with post-acute withdrawal symptoms - poor sleep, anxiety, restlessness, "feeling off" - that drive return to drinking. It is also the preferred choice for patients with liver concerns where naltrexone is risky and disulfiram impossible.
Can they be combined?
Yes. Naltrexone and acamprosate have complementary mechanisms - one removes the moment-of-drinking reward, the other reduces the chronic discomfort of recovery. Some clinical guidelines support combining them in specific patient profiles. The COMBINE Study examined this combination among other treatment combinations and found benefit, though not dramatically more than each medication alone.
Both medications are evidence-based and underused. Most AUD patients who could benefit from pharmacotherapy receive no medication at all. The choice between Lodonak and acamprosate is much less important than the choice to start medication-assisted treatment at all.
🆚 Lodonak vs other naltrexone brands
Naltrexone is available under several brand names across the world: ReVia (the original Western brand), Vivitrol (the extended-release injection), Lodonak (Macleods, India), Naltima (Cipla, India), Nodict (Sun Pharma, India), and generic naltrexone in many markets. All contain the same active ingredient at the same standard doses. The choice between brands typically comes down to availability and cost rather than therapeutic difference.
Major naltrexone brands
Bioequivalence: the key point
All branded versions of oral naltrexone must demonstrate bioequivalence to reference naltrexone before being approved. This means they produce the same blood levels in the body. The clinical effect, side effects, drug interactions, and contraindications are identical across brands. The drug class is the same; the active ingredient is the same; the dose is the same.
- Price - sometimes by a factor of 10 or more
- Regional availability and distribution
- Inactive ingredients (excipients) - rarely matters clinically
- Brand reputation and patient preference
- For Vivitrol specifically: formulation (injection vs oral)
What does NOT differ: therapeutic effect, side effect profile, drug interactions, contraindications.
When to choose which brand
For most patients globally, Lodonak or other Indian generics provide the practical pathway - affordable, available through pharmacies and online sources, identical clinical effect to branded ReVia. Patients in markets where Lodonak is readily available rarely have reason to seek out more expensive alternatives.
Patients in the United States with good insurance coverage often receive whatever generic naltrexone the pharmacy stocks, or branded ReVia if specifically prescribed. Vivitrol is the choice when adherence is the primary concern - the monthly injection removes daily dosing decisions entirely.
Switching between oral brands is straightforward: same dose, no washout, simply transition from one product to another at next refill. The body cannot tell the difference between oral naltrexone brands.
The most important factor in choosing a naltrexone brand is which one you can reliably access and afford long-term. A bottle of Lodonak in your hand is more therapeutic than a prescription for ReVia that goes unfilled because of cost. All brands work the same way.
⚠️ Post-treatment opioid sensitivity warning
The single most important safety warning for Lodonak in the context of opioid use disorder is what happens after the medication is stopped. Tolerance to opioids drops dramatically during naltrexone treatment. If patients relapse to opioid use after stopping Lodonak, they face a significantly elevated risk of fatal overdose - because the dose they previously tolerated can now be lethal.
Regular opioid use causes the body to adapt - this is tolerance. Stopping opioids reverses this adaptation over weeks. While on Lodonak, the receptor blockade means the body is functionally "opioid-free" even though no withdrawal occurs. Tolerance drops to baseline or below. When Lodonak is stopped and opioids are used again, the same dose hits a system without tolerance - and respiratory depression at fatal levels can result.
The clinical reality
Overdose deaths after stopping naltrexone treatment have been documented in multiple studies. The risk is highest in the first few weeks after discontinuation, when tolerance is at its lowest and when patients may be psychologically vulnerable to relapse. This pattern is one reason buprenorphine and methadone are often preferred over naltrexone for severe OUD - they do not produce this discontinuation-related overdose vulnerability.
The risk applies to any stopping of Lodonak: planned discontinuation, missed doses leading to gaps, switching to other treatments, or simply forgetting refills. Anyone who has been on naltrexone for OUD must understand this risk before stopping or considering relapse.
Risk reduction strategies
The most effective protection is to not stop Lodonak abruptly. If discontinuation is planned, coordinate it with intensive recovery support: increased counseling frequency, family involvement, restricted access to opioids, and clear contingency plans for if cravings appear. The first month after stopping is the period of highest risk.
If relapse to opioid use occurs after stopping Lodonak, treat it as a medical emergency requiring immediate evaluation. Naloxone (the opioid overdose reversal medication) should be readily available - in the home, with family members, and the patient and family should know how to use it. Naloxone is available without prescription in many regions.
Patients themselves need to understand and remember this risk. The intuitive sense that "I used X amount before, I can use X amount now" is dangerously wrong after months of Lodonak. The same X is far more dangerous than it was before treatment.
Stopping Lodonak does not stop OUD - it just removes the receptor blockade, leaving the patient with no tolerance to opioids. Plan stops carefully and have naloxone available; the risk is real and well documented.
🛑 Stopping Lodonak safely
Most patients on Lodonak will eventually stop the medication - whether due to completed treatment, side effects, life circumstances, or pregnancy planning. The pharmacology of naltrexone makes stopping relatively straightforward compared to disulfiram (1-3 day washout versus 7-14 days). However, the implications of stopping differ dramatically depending on whether treatment is for AUD or OUD, and on what plans exist for ongoing recovery support.
When stopping is appropriate
There is no single right duration of Lodonak treatment. Some patients use it for a few months during early recovery, then transition to behavioral approaches alone. Others remain on it for years. The duration of treatment depends on factors including the severity of the original substance use disorder, how stable the patient is in recovery, presence of co-occurring conditions, and the patient's own preference about continuing pharmacotherapy.
How to stop
Naltrexone does not need to be tapered. There is no withdrawal syndrome from stopping. The receptor blockade simply lifts as the medication clears the system over 1 to 3 days. This is one of the easiest medications to stop pharmacologically.
The challenges of stopping are not pharmacological but behavioral. The medication has been providing some level of protection against drinking or opioid use; once stopped, that protection is gone. The success of stopping depends entirely on whether other recovery supports are in place to fill the gap.
Planning the stop
Before stopping, ensure adequate recovery infrastructure is in place: regular counseling sessions, engaged support network, identified high-risk situations and coping plans, and clear contingencies for if cravings reappear. The first weeks after stopping deserve increased rather than decreased treatment intensity for many patients.
If stopping for OUD treatment specifically, the post-discontinuation opioid sensitivity warning becomes critical. See the dedicated section on this topic. Have naloxone available in the home, and ensure family members know how to use it and recognise overdose.
This is not a failure - it is a treatment data point. Many patients restart Lodonak after a period off. Contact the prescribing provider promptly to discuss whether resuming naltrexone, switching medications, or intensifying behavioral treatment is the right next step.
Stopping Lodonak should be a decision made WITH your provider, not a quiet decision to skip refills. Open communication makes the transition safer and keeps the path back to treatment open if needed.
📅 If you miss a dose of Lodonak
Missing a dose of Lodonak is not an emergency. Naltrexone's pharmacology forgives short gaps - the active metabolite continues to occupy receptors for some time after the last dose. However, repeated missed doses or sustained gaps undermine the treatment, and for OUD specifically, gaps can create relapse risk. Understanding what to do when a dose is missed helps prevent both unnecessary panic and casual non-adherence.
What to do
- If you remember within a few hours of your usual time, take the missed dose
- If you remember close to the next scheduled dose, skip the missed dose and take the next at the usual time
- Never take two doses in the same day to "make up" for a missed one - this increases side effects without therapeutic benefit
The mechanics are straightforward but the underlying issue often is not. Missing one dose occasionally is human. Missing several over a week is a signal worth examining. Why is it happening? Schedule problems? Pill-management issues? Ambivalence about being on medication? Each underlying cause has a different solution.
Why missed doses matter differently for AUD vs OUD
For AUD treatment, missing a dose has a relatively small immediate effect. Naltrexone's protective effect builds over weeks of consistent dosing; one missed day does not undo that. The risk is gradual undermining of the treatment if missed doses become a pattern.
For OUD treatment, the calculation is different. A patient who misses doses and then encounters opportunity for opioid use faces immediate relapse risk - the receptor blockade is weaker than usual. Adherence support for OUD patients is more important than for AUD patients.
Common scenarios
Realised at lunchtime that morning dose was forgotten: Take it now. Resume normal schedule tomorrow. One day with slightly later dosing is not significant.
Realised at bedtime: Take it before bed. May affect sleep slightly but better than skipping. Resume normal morning schedule next day.
Realised next morning that yesterday was missed: Take today's dose at normal time only. Do not take two doses. Continue normally.
Missed multiple days in a row: Resume daily dose at next opportunity. Contact your provider to discuss the gap - especially important for OUD treatment where extended gaps can create relapse vulnerability.
Preventing missed doses
The strategies that work for medication adherence in general work for Lodonak. Pairing the dose with a daily routine (breakfast, brushing teeth, morning coffee) creates an automatic prompt. A weekly pill organiser provides visual confirmation each day. Phone reminders help during early treatment when the habit is still forming. Family or partner involvement creates external accountability.
If you have been on Lodonak for OUD and missed doses are happening regularly, the underlying issue may warrant switching to Vivitrol (the monthly injection). The medication is the same molecule but the dosing schedule is built around the patient who cannot reliably take daily medication.
If you were opioid-free during a missed-dose gap, just resume Lodonak normally. If you used opioids during the gap (even prescribed ones for an unrelated reason), you must re-establish the 7-14 day opioid-free period before resuming naltrexone. Restarting too early risks precipitated withdrawal.
🧊 Storing Lodonak safely
Lodonak is a stable medication that does not require refrigeration or special handling. Standard pharmaceutical storage applies. This section covers practical guidance for storing the medication at home, traveling with it, and handling expiration and disposal.
Storage conditions
Store Lodonak at room temperature - between 15 and 30 degrees Celsius (59 to 86 degrees Fahrenheit). Avoid direct sunlight, which can degrade the medication over time. Avoid humid environments; the bathroom is generally not a good storage location because of shower humidity and temperature fluctuations.
Keep the medication in its original container with the label intact. This protects against light and humidity, preserves the expiration date information, and makes the medication easy to identify in emergencies. Keep out of reach of children and others who should not access the medication.
- Keep in original container with intact label
- Store in a cool, dry location
- Use a weekly pill organiser for daily access
- Tell family members where it is stored
- Check expiration date periodically
- Bathroom storage (humidity)
- Hot windowsills or near radiators
- Unmarked containers (identification problems)
- Using expired tablets
- Sharing with anyone else
Traveling with Lodonak
Carry Lodonak in your original container with the prescription label visible. This avoids customs and security questions about identifying the medication. Bring a copy of your prescription or a brief doctor's letter explaining what the medication is for - particularly useful for international travel.
Always pack Lodonak in your carry-on luggage rather than checked baggage. Checked bags can be lost, delayed, or exposed to temperature extremes in cargo holds. Bring 25-50% more medication than you need for the trip duration to cover unexpected delays.
Most countries allow personal-use prescription medications. The documentation matters mainly for unusual situations: questioned at customs, lost luggage requiring local pharmacy refill, or medical emergency abroad where the treating provider needs to know your medications.
Expiration and disposal
Lodonak tablets typically have a 2-3 year shelf life when stored properly. Check the expiration date on the package before each refill. Do not use expired tablets - potency may decline. Discard expired medication promptly.
For disposal, return unused Lodonak to a pharmacy or medication take-back program. Do not flush down the toilet (environmental concerns). Do not throw in regular trash where children or pets could access. Many pharmacies have medication disposal programs for exactly this purpose.
Proper storage protects both the medication's effectiveness and others around you. A simple system - same cool dry location, original container, daily pill organiser - prevents most problems. Make storage and access part of your daily routine, just like the medication itself.
Lodonak — Frequently Asked Questions
-
What is Lodonak used for?
Lodonak is used to help manage alcohol dependence in people who have stopped drinking and to prevent relapse into opioid use after opioid detoxification. -
How does Lodonak work in treating alcohol dependence?
Lodonak works by blocking the euphoric and sedative effects of alcohol, reducing cravings and helping maintain abstinence. -
Can Lodonak prevent opioid relapse?
Yes, Lodonak blocks the effects of opioids, reducing the desire to use opioids and helping maintain sobriety after detoxification. -
How is Lodonak administered?
Lodonak is typically taken orally once a day. It is available in tablet form. -
Are there any side effects of taking Lodonak?
Common side effects include nausea, headache, dizziness, fatigue, and insomnia. More serious side effects can include liver damage, severe withdrawal symptoms in people still using opioids, and severe reactions at the injection site for injectable forms. -
Is Lodonak effective for everyone?
The effectiveness of Lodonak can vary. It is generally more effective when combined with counseling and support groups. -
How long should someone take Lodonak?
The duration of treatment with Lodonak varies based on individual needs. It is often used long-term for maintaining sobriety.
See all Lodonak questions (32)
📚 Drug Description Sources:
📚 Drug Description Sources
Information on naltrexone (the active ingredient in Lodonak) is drawn from regulatory approvals across India and major Western markets, treatment guidelines from international addiction medicine bodies, and decades of peer-reviewed clinical evidence. Lodonak is manufactured by Macleods Pharmaceuticals, one of India's leading pharmaceutical companies, and is used widely for the treatment of alcohol use disorder and opioid use disorder.
- DCGI (India) - Drug Controller General of India; regulatory authority for Lodonak manufacture
- U.S. FDA - Naltrexone approved 1984 (oral) and 2006 (extended-release injection)
- European Medicines Agency (EMA) - Naltrexone widely approved across EU
- WHO Essential Medicines List - Includes naltrexone for substance use disorders
- UK MHRA, Health Canada, TGA Australia - Major regulators recognising naltrexone
- Macleods manufacturing quality - WHO-GMP certified; US-FDA inspected facilities
- APA Practice Guideline for AUD - American Psychiatric Association
- NIAAA pharmacotherapy guidance - U.S. National Institute on Alcohol Abuse
- SAMHSA Treatment Improvement Protocols - U.S. federal addiction treatment standards
- ASAM National Practice Guideline - American Society of Addiction Medicine
- WHO substance use treatment framework - Global treatment standards
- Indian Psychiatric Society addiction guidelines - Indian clinical practice standards
- NIAAA COMBINE Study (2006) - Landmark trial demonstrating naltrexone efficacy in AUD
- Cochrane systematic reviews - Multiple meta-analyses of naltrexone for AUD and OUD
- Sinclair Method evidence base - Targeted naltrexone for drinking reduction
- VIVITROL development trials - Extended-release injection efficacy data
- UpToDate, DynaMed - Clinical decision support databases
- LactMed lactation safety database - Pregnancy and breastfeeding safety
- FDA FAERS and EMA EudraVigilance - Post-marketing safety surveillance
Macleods Pharmaceuticals bioequivalence studies establish therapeutic equivalence of Lodonak with reference naltrexone products.
🩺 Medical Expert Review:
👨⚕️ Medical Expert Review Panel
The Medication Guide content for Lodonak reflects published research and clinical guidance from internationally recognised authorities in addiction psychiatry and naltrexone pharmacotherapy. All listed authorities have substantial peer-reviewed publication records on naltrexone or AUD/OUD treatment.
Director of NIAAA's Division of Medications Development and one of the world's leading researchers on pharmacotherapy for alcohol use disorder. Decades of work on naltrexone clinical trials, mechanism studies, and treatment optimization. Author of foundational publications on AUD medication development.
Professor and former Chair of Psychiatry at University of Maryland; internationally recognised AUD pharmacotherapy researcher. Editor of major addiction medicine textbooks. Extensive work on naltrexone, topiramate, and ondansetron in AUD treatment.
Chief of the Division of Alcohol, Drugs, and Addiction at McLean Hospital and Professor of Psychiatry at Harvard Medical School. Long career in addiction treatment research including pharmacotherapy and dual-diagnosis care. Author of more than 250 peer-reviewed publications.
Professor of Psychiatry at the University of Washington and Director of the Center of Excellence in Substance Abuse Treatment at VA Puget Sound. Past President of the American Society of Addiction Medicine (ASAM). Extensive research on naltrexone, buprenorphine, and integrated care.
Director of the Center on Drug and Alcohol Research at the University of Kentucky and Professor of Behavioral Science. Major researcher on opioid pharmacology including naltrexone mechanism and clinical trials. Frequent NIDA and FDA advisor.
Note: this panel reflects published evidence and guidance from the listed authorities; it does not imply individual endorsement of this specific medication guide.
More Anti-Alcohol Medications





