Neurotransmitters: How Medicines Actually Act on Them

Neurotransmitters are usually presented as a list to memorise: serotonin for mood, dopamine for reward, GABA for calm. That version is tidy, largely wrong, and explains nothing you can use.
The version worth knowing is different. Almost every medicine acting on the brain works by interfering with one of these chemicals at one specific point in its life cycle, and knowing which point tells you how fast the drug works, why it produces the side effects it does, and why some of them cannot be taken together.
🧪 The observation that should reshape how you think about all of this. An antidepressant blocks serotonin reuptake within hours of the first tablet, so serotonin in the synapse rises the same day. Yet the benefit takes four to six weeks. That gap is not a technicality — it means the raised chemical cannot itself be the therapeutic effect. Something slower is happening downstream, and the same pattern appears across psychiatry. It is the single most useful fact in this article and it is almost never explained to the people taking the tablets.
⚡ Four places a drug can interfere
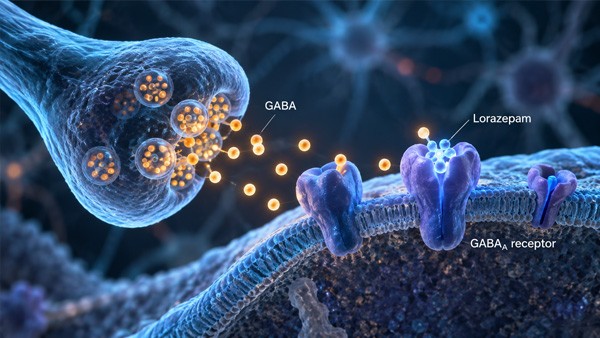
A message passes between two nerve cells across a gap. The sending cell manufactures a chemical, stores it in packets, and releases it into the gap. It crosses, binds to receptors on the receiving cell, and produces an effect. Then it is cleared — either pumped back into the sending cell for reuse, or broken down by an enzyme.
Five steps, and medicines act at four of them.
| Point of action | What the drug does | Examples |
|---|---|---|
| Supply the raw material | Provides more of what the cell needs to manufacture | Levodopa in Parkinson disease |
| Block the reuptake pump | The chemical stays in the gap longer and acts for longer | SSRI and SNRI antidepressants, atomoxetine, modafinil |
| Block the breakdown enzyme | Less is destroyed, so more accumulates | Donepezil in Alzheimer disease, MAOI antidepressants |
| Act at the receptor | Either mimics the chemical or blocks it from binding | Antipsychotics, benzodiazepines, antihistamines, opioids |
That table covers a surprising proportion of everything in a pharmacy. What follows explains what each chemical actually does — and, more usefully, what interfering with it costs.
❌ The chemical imbalance idea
Before the individual chemicals, one framing needs dismantling because it distorts everything built on top of it.
The idea that depression is caused by a shortage of serotonin, anxiety by a shortage of GABA, and so on — that mental illness is a deficiency corrected by topping the chemical back up — is a simplification that was never established. A comprehensive review of the evidence for the serotonin theory of depression specifically found no consistent support for it.
Two things follow, and people frequently draw the wrong one.
The wrong conclusion: that antidepressants therefore do not work. That does not follow at all. They work for a substantial proportion of people, demonstrated in trials, whatever the mechanism turns out to be. A drug being effective and the popular explanation of why being wrong are entirely compatible.
The right conclusion: that these drugs are not correcting a measurable deficiency, that there is no blood test showing your serotonin is low, and that anyone offering one is selling something. They alter a system, the system responds over weeks, and the response is the treatment.
⏳ Why the delay matters
Return to the gap between hours and weeks, because understanding it changes how treatment is experienced.
If raised serotonin were the cure, antidepressants would work by the second day. They do not. What appears to happen over the following weeks is that the receiving cells adapt — adjusting the number and sensitivity of their receptors, altering which genes they express, and, in animal work, growing new connections between cells. The drug starts a process; the process is the treatment.
Three practical consequences.
Stopping at two weeks because nothing has happened is stopping before the thing that works has occurred. This is the commonest reason antidepressant treatment appears to fail, and the same applies to atomoxetine in attention difficulty, which takes four to six weeks for exactly the same kind of reason.
Side effects arrive first. Nausea, headache and restlessness appear within days, because those come from the immediate chemical change. Benefit arrives weeks later. So the first fortnight offers all of the cost and none of the return, which is a difficult thing to sit through and much easier when expected.
Stopping abruptly produces symptoms because the adapted system now has to readapt. That is discontinuation, not addiction, and it is why tapering exists.
😀 Serotonin, and its many other jobs
Serotonin is known for mood and that is a small part of what it does. It regulates sleep, appetite, body temperature, pain perception, sexual function, blood clotting and the movement of the gut — and the overwhelming majority of the body’s serotonin is not in the brain at all but in the intestine, where it drives digestion.
That distribution explains the entire side effect profile of an SSRI without any further information needed.
- Nausea and loose stools in the first weeks
- Serotonin drives gut motility, and the drug raises it there as much as anywhere else. It settles as the gut adapts.
- Sexual difficulty
- Serotonin inhibits sexual response. Raising it does what raising it does. This is common, under-discussed, and worth raising rather than enduring, since options exist.
- Easier bruising and bleeding
- Platelets use serotonin to clump together. Depleting their stores makes them slightly less effective, which matters alongside anti-inflammatory painkillers or anticoagulants.
- Early restlessness or agitation
- Occurs in the first days in some people and should be reported rather than pushed through.
None of these are mysterious reactions. They are the intended mechanism, appearing everywhere the chemical is used.
🔴 Too much serotonin is dangerous, and the combinations that cause it are ordinary. Serotonin syndrome produces agitation, confusion, sweating, shivering, tremor, muscle twitching, a racing pulse and fever, escalating over hours. It arises from combining serotonin-raising drugs: an SSRI with tramadol, with migraine triptans, with the antibiotic linezolid, with St John’s wort bought freely, with certain antinausea drugs, or with another antidepressant. Tramadol is the commonest culprit because it is prescribed as an ordinary painkiller and few people realise it acts on serotonin at all. Any of these symptoms after starting or adding a medicine needs urgent assessment.
🎯 Dopamine, and the trap of moving it either way
Dopamine is the clearest illustration of why a neurotransmitter cannot simply be turned up or down, because it runs along four separate pathways doing four unrelated jobs.
One controls movement. One handles motivation and reward. One supports planning and attention. One suppresses the hormone that produces breast milk.
Any drug given by mouth reaches all four.
| Antipsychotics — blocking dopamine | Parkinson treatment — raising dopamine | |
|---|---|---|
| Intended | Reduces psychosis by damping the reward pathway | Restores movement by supplying the movement pathway |
| On movement | Causes stiffness, tremor and slowness resembling Parkinson disease | The point of treatment |
| On reward | The point of treatment | Can cause compulsive gambling, shopping, eating or sexual behaviour |
| On thinking | Can flatten motivation and emotional range | Can cause hallucinations and delusions |
| On hormones | Raises prolactin, causing breast changes and menstrual disruption | — |
Read the table across and the symmetry is striking: each treatment produces the disease the other treats. Block dopamine for psychosis and you induce parkinsonism. Raise it for Parkinson disease and you can induce psychosis and compulsive behaviour.
The impulse control problem deserves particular emphasis because it is so damaging and so rarely anticipated. People on dopamine treatment for Parkinson disease have gambled away savings and destroyed marriages, and the connection to the medication is frequently missed by everyone including the person themselves. It is a recognised effect, it is reversible on adjusting treatment, and it should be asked about directly rather than waited for.
🔋 Noradrenaline
Noradrenaline handles alertness, focus, the stress response, and the maintenance of blood pressure — the chemistry of being switched on.
Drugs raise it by blocking its reuptake, and the pattern of effects follows directly. Atomoxetine for attention difficulty works this way, as do the SNRI antidepressants. Both improve concentration and both can raise blood pressure and pulse, which is why those are monitored on treatment.
Beta blockers do the opposite at the receptor, which is why they treat blood pressure and also blunt the physical side of anxiety — the pounding heart and the tremor — without touching the worry itself.
And atomoxetine takes four to six weeks, for the same downstream reason antidepressants do. Anyone expecting a stimulant-like response the same afternoon concludes it does not work and stops. That single misunderstanding accounts for a large share of abandoned treatment.
🧘 GABA
GABA is the brain’s main brake. Where glutamate accelerates, GABA slows, and the balance between them determines whether the system is stable or heading toward a seizure.
Benzodiazepines do not create calm. They bind alongside GABA and amplify what it is already doing — which is why they produce reduced anxiety, muscle relaxation, sedation, anticonvulsant effect and memory impairment simultaneously. All five run through the same brake.
Alcohol acts on the same system, which is why the two combined are so dangerous and why benzodiazepines are the correct treatment for alcohol withdrawal.
And amplifying the main inhibitory system continuously causes it to reduce its own sensitivity — tolerance. That adaptation is why the drugs stop working over weeks and why stopping abruptly after prolonged use can cause seizures. The system, having been artificially braked for months, is left with an inadequate brake of its own.
💡 A common misunderstanding worth correcting. Gabapentin and pregabalin have names suggesting they act on GABA. They do not bind GABA receptors at all — they act on a calcium channel that reduces the release of excitatory chemicals. The naming is historical and misleading, and it matters because people assume they behave like benzodiazepines. They do not, though they have dependence potential of their own.
🔥 Glutamate
Glutamate is the accelerator, used by the great majority of excitatory connections in the brain, and it is central to learning and memory.
Too much is destructive. Sustained over-stimulation of its receptors lets excess calcium into cells and damages them, a process implicated in stroke, brain injury and dementia.
Memantine addresses exactly this. It blocks the receptor in an unusual way — loosely enough to be displaced by a genuine signal, tightly enough to block the constant background stimulation doing the damage. It dampens the noise without silencing the message, which is why it is tolerated as well as it is and why it is used in moderate to severe Alzheimer disease rather than mild.
🧠 Acetylcholine, and a contradiction worth spotting
Acetylcholine handles memory and learning in the brain, activates muscle at the nerve ending, and runs the rest-and-digest functions — slowing the heart, stimulating digestion, contracting the bladder, producing saliva and tears.
In Alzheimer disease the cells producing it are lost early, so treatment blocks the enzyme that breaks it down, leaving more available. Donepezil and rivastigmine work this way. Their side effects — nausea, diarrhoea, a slow pulse, vivid dreams, cramps — are simply that same increase acting everywhere else.
Now the contradiction. A large group of common medicines does the opposite: they block acetylcholine. Bladder antispasmodics for urinary urgency. Older sedating antihistamines, including those bought as sleep aids. Tricyclic antidepressants. Several antipsychotics and antinausea drugs.
Their effects on memory and attention accumulate, and long-term use has been associated with increased dementia risk.
So an older person can be prescribed a drug to raise acetylcholine for their memory while simultaneously taking two or three that block it. That happens routinely, and reviewing the second list frequently produces more improvement than adding the first. It is one of the clearest examples of why understanding the chemistry has practical value.
🤧 Histamine, which explains the whole antihistamine aisle
Histamine does two unrelated jobs. In the body it drives allergic reactions. In the brain it is one of the systems keeping you awake.
That single fact explains everything about choosing an antihistamine.
Older antihistamines cross into the brain, so they block the wakefulness system as well as the allergy — producing the drowsiness they are famous for, and impairing concentration and driving for considerably longer than people expect. They also block acetylcholine, adding the problems described above.
Newer ones are built not to cross, so they treat the allergy and leave alertness alone.
Two practical points follow. Using an old sedating antihistamine as a sleep aid is using a side effect as a treatment, and it produces poor quality sleep with a hangover. And a student taking one during examinations is impairing exactly the function being examined — measurably, in studies of examination performance.
😴 Orexin
The most recently understood of these and the most illuminating.
Orexin is produced by a very small population of cells whose job is to hold the boundary between waking and sleeping steady. In narcolepsy type 1 the great majority of those cells are destroyed, almost certainly by the immune system.
Without that stabiliser the boundary becomes unstable in both directions, which explains the entire syndrome from one loss: sleep intrudes into the day as sleep attacks, dream sleep intrudes into wakefulness as cataplexy and hallucinations, and wakefulness intrudes into the night, so nights are fragmented.
Modafinil and armodafinil act partly on this system, which is why they promote wakefulness without the generalised stimulation of an amphetamine.
🗺️ The map
| Chemical | Main jobs | Drugs acting on it |
|---|---|---|
| Serotonin | Mood, sleep, appetite, gut, clotting, sexual function | Antidepressants |
| Dopamine | Movement, reward, planning, prolactin control | Antipsychotics, Parkinson treatments |
| Noradrenaline | Alertness, attention, stress, blood pressure | ADHD treatments, SNRI antidepressants |
| GABA | The main brake — anxiety, sleep, seizures, muscle tone | Anti-anxiety, anticonvulsants |
| Glutamate | The main accelerator — learning and memory | Memantine |
| Acetylcholine | Memory, muscle activation, rest-and-digest | Cholinesterase inhibitors |
| Histamine | Allergy, and wakefulness | Antihistamines |
| Orexin | Holding the wake-sleep boundary steady | Wakefulness agents |
🔗 Why side effects are not accidents
If one idea survives this article, it should be this one.
A tablet cannot deliver a chemical change to one location. It enters the bloodstream and reaches every place that chemical operates. So every job the chemical does anywhere becomes a possible side effect, and the list of side effects is essentially a list of that chemical’s other functions.
Serotonin drives the gut, so an antidepressant causes nausea. Dopamine controls movement, so an antipsychotic causes stiffness. Acetylcholine runs the bladder and the salivary glands, so blocking it causes retention and a dry mouth. Histamine keeps you awake, so an old antihistamine makes you drowsy.
Understood that way, side effects stop being random misfortunes and become predictable consequences — which makes them easier to anticipate, easier to explain, and often easier to tolerate.
It also explains why newer drugs are more selective rather than more powerful. The progress has been in narrowing the target, not in hitting it harder.
📋 What this is actually good for
Judging a medicine on the right timescale. Anything working through receptor adaptation needs weeks. Two weeks is not a trial.
Recognising a side effect as mechanism. Nausea starting an antidepressant is the drug working in the gut, not a reaction to it, and it usually settles.
Spotting drugs that cancel each other. Raising acetylcholine for memory while taking three drugs that block it is the clearest example, and it is common.
Recognising the dangerous combinations. Several serotonin-raising drugs together. Benzodiazepines with opioids or alcohol. Both are predictable from the chemistry.
Treating claims about brain chemistry sceptically. There is no test showing your serotonin is low, and supplements promising to balance neurotransmitters are selling a model that was never established.
Treatment across all of these systems is stocked throughout the catalogue, and the antidepressant category covers the serotonin and noradrenaline drugs that most of this article concerns. The guide to reading a drug monograph explains how to check any of this for a specific medicine.
❓ Frequently asked questions
Why do antidepressants take weeks to work?
Because the raised chemical is not the treatment. Reuptake is blocked within hours of the first tablet, so serotonin in the synapse rises the same day, yet benefit takes four to six weeks. What happens in between is adaptation by the receiving cells — adjusting receptor numbers and sensitivity, altering gene expression, and growing new connections. The drug starts a process, and the process is the treatment.
Is depression caused by a chemical imbalance?
The evidence does not support it, and a comprehensive review of the serotonin theory specifically found no consistent backing. That does not mean antidepressants do not work — they work for a substantial proportion of people, whatever the mechanism turns out to be. It does mean there is no measurable deficiency being corrected and no blood test showing your serotonin is low.
Why does an antidepressant upset my stomach?
Because the overwhelming majority of the body's serotonin is in the intestine rather than the brain, where it drives gut movement. The drug raises it there as much as anywhere else, so nausea and loose stools in the first weeks are the mechanism working rather than a reaction against it. It usually settles as the gut adapts.
What is serotonin syndrome?
Too much serotonin, producing agitation, confusion, sweating, shivering, tremor, muscle twitching, a racing pulse and fever over hours. It arises from combining serotonin-raising drugs — an SSRI with tramadol, migraine triptans, the antibiotic linezolid, St John's wort, certain antinausea drugs or a second antidepressant. Tramadol is the commonest culprit because few people realise an ordinary painkiller acts on serotonin.
Why do antipsychotics cause stiffness and tremor?
Because dopamine runs along four separate pathways doing unrelated jobs, and a tablet reaches all of them. Blocking it damps the reward pathway, which treats psychosis, and simultaneously blocks the movement pathway, producing stiffness, tremor and slowness resembling Parkinson disease. The symmetry is exact: treating Parkinson disease by raising dopamine can in turn produce psychosis.
Can Parkinson medication really cause gambling?
Yes, and it is one of the most damaging effects because it is so rarely anticipated. Raising dopamine acts on the reward and motivation pathway as well as the movement one, and compulsive gambling, shopping, eating or sexual behaviour is a recognised consequence. People have lost savings and marriages without anyone connecting it to the tablets. It is reversible on adjusting treatment and should be asked about directly.
Why do benzodiazepines stop working?
They do not create calm; they amplify the brain's existing brake. Amplifying the main inhibitory system continuously causes it to reduce its own sensitivity, which is tolerance. The same adaptation explains why stopping abruptly after prolonged use can cause seizures — the system, artificially braked for months, is left with an inadequate brake of its own.
Can two of my medicines cancel each other out?
Routinely, and acetylcholine is the clearest example. Alzheimer treatment raises it to help memory, while bladder antispasmodics, older sedating antihistamines, tricyclic antidepressants and several antipsychotics block it. An older person can be taking one drug to raise it and three that block it. Reviewing the second list often produces more improvement than adding the first.
Why do some antihistamines make me sleepy and others do not?
Because histamine does two unrelated jobs — driving allergic reactions in the body and keeping you awake in the brain. Older antihistamines cross into the brain and block both, producing drowsiness and impairing concentration for longer than people expect. Newer ones are built not to cross, so they treat the allergy and leave alertness alone.
Are side effects just bad luck?
Almost never. A tablet cannot deliver a chemical change to one location — it reaches everywhere that chemical operates, so every job it does anywhere becomes a possible side effect. The list of side effects is essentially a list of the chemical's other functions. That is why progress in these drugs has come from narrowing the target rather than hitting it harder.
📑 Sources and editorial
- Umbrella review of the serotonin hypothesis of depression
- Research on delayed onset of antidepressant action, receptor adaptation and neuroplasticity
- Literature on the four dopaminergic pathways and antipsychotic side effect profiles
- Evidence on impulse control disorders with dopamine agonist therapy in Parkinson disease
- Reviews of benzodiazepine tolerance and GABA receptor adaptation
- Pharmacology of gabapentinoids and their action at voltage-gated calcium channels
- Research on NMDA receptor antagonism and excitotoxicity in neurodegeneration
- Studies of cumulative anticholinergic burden, cognition and dementia risk
- Literature on blood-brain barrier penetration of first and second generation antihistamines
- Research on hypocretin and orexin neuron loss in narcolepsy
- Guidance on the recognition and management of serotonin syndrome
- Related reading: how to read a drug monograph, memantine, lorazepam and benzodiazepines
- Related products: antidepressant category
- RXshop Editorial Team — reviewed by Sarah Mitchell, PharmD, Clinical Pharmacist and Chief Editorial
Medical Disclaimer: The information in this article is for educational and informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always seek guidance from a qualified healthcare provider with any questions you may have regarding a medical condition, and before starting, stopping or changing any medication.