Brain Fluid Problems: The Dementia That Can Be Reversed


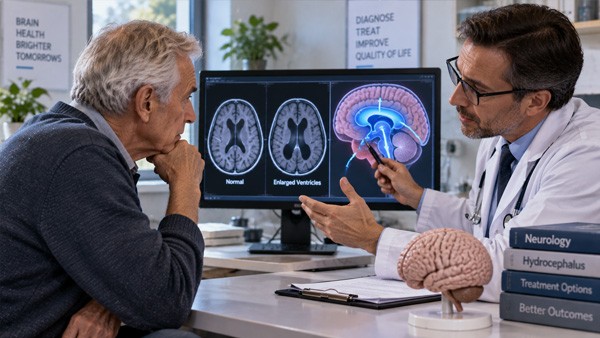
The brain floats. It sits suspended in a clear fluid that fills a set of connected chambers inside it and then surrounds it entirely, and that arrangement is what allows an organ with roughly the consistency of soft jelly to survive being carried around inside a moving skull.
The chambers are the ventricles, and the fluid is cerebrospinal fluid. Most descriptions of this system stop at the anatomy, which is a shame, because what happens when the system fails is where the useful information lives — including one of the very few causes of dementia that can be reversed, and one of the few causes of blindness that is caused by ordinary prescription medication.
💧 Two numbers explain almost everything about how this system fails. There is only about 150 millilitres of cerebrospinal fluid in and around the brain at any moment — roughly a small cup. But around 500 millilitres is produced every day, which means the entire volume is made, circulated and reabsorbed three to four times over in twenty-four hours.
A system turning over that fast has almost no reserve. If drainage or absorption falls even slightly behind production, volume and pressure rise quickly. And the narrowest point in the whole circuit — the channel connecting the third chamber to the fourth — is about the width of a pencil lead, which is why it is the commonest place for the system to block.
The fluid is made in each chamber by a specialised tissue, flows from the two large chambers in the cerebral hemispheres into a central chamber, down that narrow channel to a fourth chamber behind the brainstem, and then out onto the surface of the brain and spinal cord, where it is reabsorbed. Along the way it cushions, it removes waste, and it distributes signalling molecules.
The clearance function has become considerably more interesting in recent years, since it turns out much of it happens during sleep. Which is one of several reasons that sleep quality and brain health are more tightly linked than anyone assumed.
🚶 The dementia that is not dementia
This is the most valuable thing in this article, and it is worth reading even by people with no interest in anatomy at all.
There is a condition in which the ventricles gradually enlarge and the fluid circulation fails, without the pressure ever rising to obviously abnormal levels. It typically appears after the age of sixty. It produces a slow decline that looks like dementia. And unlike almost every other cause of dementia, it can be treated, and treatment can reverse the symptoms.
It is missed constantly, because the assumption when an older person declines is that this is Alzheimer disease, and once that assumption is made nobody looks further.
Three symptoms define it, and the order they arrive in is the single most useful diagnostic clue available to a family.
| Symptom | What it actually looks like |
|---|---|
| Walking, first | Feet that seem stuck to the floor. Short shuffling steps, a wide stance, difficulty starting to walk. Turning requires several small steps rather than one movement. People describe it as walking through treacle, and it is often mistaken for arthritis, old age or Parkinson disease |
| Bladder, second | Urgency progressing to incontinence, appearing far earlier in the decline than it would in Alzheimer disease |
| Thinking, last | Slowness rather than forgetting. Long pauses before answering, loss of initiative, apathy, difficulty planning. The memory itself is relatively preserved early on |
The order is the point. In Alzheimer disease, memory goes first and walking is affected only late. Here it is reversed: the walking changes first, sometimes by a year or more, and the thinking follows.
So the question worth asking about any older person who is declining is not what their memory is like. It is which came first, the walking or the memory. If it was the walking, this deserves ruling out before any dementia diagnosis is accepted.
| This condition | Alzheimer disease | |
|---|---|---|
| First symptom | Walking difficulty | Memory loss |
| Nature of the thinking problem | Slow, apathetic, poor planning. Answers arrive if you wait | Forgetting recent events, repeating questions, losing words |
| Incontinence | Early | Very late |
| Gait | Affected from the start, feet appearing magnetised to the floor | Normal until advanced stages |
| On a scan | Ventricles enlarged out of proportion to any shrinkage of brain tissue | Ventricles enlarged because the surrounding tissue has shrunk, with widened surface grooves |
| Outcome | Potentially reversible | Progressive |
✅ What to ask for, in practical terms. Two things establish the diagnosis. A brain scan showing the ventricles enlarged beyond what any tissue loss would explain. And a test in which a volume of fluid is drained through a needle in the lower back, after which walking is measured before and a few hours after — a clear improvement strongly predicts that treatment will work. Some centres use a drain left in place for a few days instead, which is more reliable.
The treatment is a permanently implanted tube that diverts excess fluid from the brain into the abdomen, where it is absorbed. Walking responds best, bladder control next, and thinking least — and results are considerably better the earlier it is done, which is the argument for asking the question rather than waiting.
It is worth being straight about the limits. Not everyone improves, the operation carries risks, and the condition frequently coexists with genuine Alzheimer disease, which caps how much recovery is possible. But a treatable contribution to a decline is worth finding even when it is not the whole explanation, and the alternative — never looking — guarantees nothing improves.
👁️ Pressure that takes sight before it takes anything else
The opposite problem is raised pressure inside the skull with no tumour, no blockage and no obvious cause. It affects mainly younger adults, predominantly women, and it is dangerous for one specific reason: it damages the optic nerves, and it can do so permanently while the headache is still fairly mild.
The symptoms are distinctive once known, and unrecognisable if not.
| Symptom | What makes it recognisable |
|---|---|
| Headache worse lying flat | Worst on waking and improving after being upright a while — the reverse of most headaches. Worse on coughing, straining or bending |
| A whooshing sound in the ear | Rhythmic, in time with the heartbeat. Highly characteristic, and rarely mentioned by patients unless asked directly |
| Brief greying out of vision | Seconds of dimming or blackout, often on standing or bending, in one eye or both. This is the warning sign that matters most |
| Double vision | Side by side, from pressure affecting a nerve controlling eye movement |
| Swelling of the optic discs | Not felt at all. Seen only when someone looks into the back of the eye, which is why that examination is the whole diagnosis |
The visual loss creeps in from the edges, so central vision stays sharp and the person notices nothing until a large amount of field has already gone. That is why the examination of the back of the eye is not optional in anyone with this pattern of headache.
🔴 A number of ordinary medicines cause this, and two of the main culprits are acne treatments taken by exactly the age group most at risk.
Isotretinoin and related retinoids — Accutane, Isofair and Actoid — can raise pressure inside the skull. So can high-dose vitamin A supplements, which are chemically related.
Tetracycline antibiotics — Vibramycin, Minomycin and Sumycin — carry the same risk, and they are prescribed for acne for months at a time.
The two must not be taken together. Combining a retinoid with a tetracycline is specifically contraindicated because the risk multiplies, and it is a realistic mistake for someone treating stubborn acne who has been given one by a doctor and buys the other separately. Anyone taking either who develops a persistent headache, a whooshing in the ear, or brief episodes of dimmed vision should stop and have the back of the eye examined without delay.
Beyond medication, body weight is the strongest risk factor, and weight reduction is the single most effective treatment — a modest percentage loss produces measurable falls in pressure. Medication that reduces fluid production is used alongside it, and where sight is actively threatened there are surgical options that protect the nerve. The condition is manageable. It is only dangerous when it is not found.
👶 Blockages, shunts, and the signs of failure
Where the circulation is physically obstructed, fluid accumulates behind the blockage and pressure rises. In infants, whose skull bones have not yet fused, this shows first as a head circumference growing faster than it should, a tense bulging soft spot, and a characteristic downward deviation of the eyes. In older children and adults, whose skulls cannot expand, it produces headache, vomiting, drowsiness and blurred vision, and it develops far faster.
The treatment is the same diverting tube described earlier. It works well, and it needs one thing understood by anyone living with one.
⚠️ Shunts block, and blockage is an emergency. The warning signs are headache, vomiting, drowsiness, irritability, personality change and worsening vision — and in a young child, a bulging soft spot, downward-turned eyes, poor feeding or unusual sleepiness.
The pattern that matters is a return of whatever the symptoms were before the shunt was placed. Families usually recognise it faster than anyone else, and they are usually right. This is a reason to go straight to hospital and say the word shunt at the door, not a reason to wait until morning.
🧠 Why the ventricles look bigger in other conditions
Enlarged ventricles turn up on scan reports in Alzheimer disease, in schizophrenia and simply in ageing, and this generates a good deal of confusion that is worth clearing up.
In those conditions the ventricles are not enlarged because too much fluid is being made or because anything is blocked. They are enlarged because the brain tissue around them has shrunk, and fluid has passively filled the space left behind. The pressure is normal. The circulation is working. The chambers are simply occupying room that used to be occupied by something else.
This distinction has consequences. Enlargement of this kind is a consequence of the condition rather than a cause of it, no shunt will help it, and the finding on its own diagnoses nothing — ventricular size varies enormously between healthy people, and it increases in everyone with age. It matters only in combination with the clinical picture, which is precisely why the walking-first pattern described earlier does more diagnostic work than the scan does.
The article on memantine covers what is available once a dementia diagnosis is confirmed, and the article on depressive pseudodementia covers a second condition that imitates dementia and reverses with treatment. Between them and this one, there are three separate reasons not to accept a dementia diagnosis without asking what else it could be.
🩺 Infection in the fluid
Because the fluid runs freely around the whole brain and spinal cord, an infection reaching it spreads through the entire compartment rather than staying local. That is why meningitis moves so fast, and why it is treated on suspicion rather than after confirmation.
The features are worth restating without any softening: fever with severe headache, a stiff neck, intolerance of bright light, drowsiness or confusion, and in some cases a rash that does not fade when a glass is pressed against it. In infants the presentation is vaguer and therefore more dangerous — poor feeding, unusual irritability or floppiness, a high-pitched cry, a bulging soft spot.
This is an emergency with a very short window, and delay is the main determinant of outcome. Nobody has ever regretted going to hospital and being told it was a virus.
📋 What is actually worth asking for
- If walking changed before memory did — ask specifically whether normal pressure hydrocephalus has been considered, before accepting a dementia diagnosis
- If a family member declined and no scan was done — ask why not
- If headaches are worse on waking and lying flat — ask for the back of the eye to be examined
- If there is a whooshing sound in time with the heartbeat — mention it. Most people never think to
- If taking a retinoid or a tetracycline — treat new persistent headache as a reason to stop and be checked, not to take a painkiller
- If taking both together — stop and get advice, because that combination should not be prescribed
- If a shunt is in place — know the failure signs, and go to hospital rather than waiting
- If a scan reports enlarged ventricles — ask whether the pattern suggests blockage or simply tissue loss, since the two mean entirely different things
🚑 When to seek help
- Fever with headache, neck stiffness and light intolerance — emergency
- A rash that does not fade under pressure — emergency
- Headache with vomiting and drowsiness, particularly with a shunt in place — emergency
- Any episode of vision going dim or dark, even briefly — urgent eye assessment
- Sudden double vision — urgent
- A child with a rapidly enlarging head, bulging soft spot or downward-turned eyes — urgent
- Headache that is worst lying flat and on waking, persisting over weeks — needs assessment including the back of the eye
- Progressive difficulty walking in an older adult, with or without memory change — needs assessment rather than being attributed to age
- New headache on a retinoid or tetracycline — stop and seek advice
Where a dementia diagnosis has been properly established, treatment is stocked in the Alzheimer and dementia category, including Aricept (donepezil), Exelon (rivastigmine) and Namenda (memantine). None of them treats the fluid disorder described here, which is precisely why it is worth excluding first.
❓ Frequently asked questions
Which came first matters. Why?
Because it separates a treatable condition from an untreatable one. In normal pressure hydrocephalus the walking goes first, sometimes a year or more before any change in thinking, and bladder problems appear early. In Alzheimer disease memory goes first and walking is unaffected until late. So the single most useful question about an older person who is declining is whether the walking or the memory changed first.
Can a dementia really be reversed?
This one can be improved, and sometimes substantially. Draining the excess fluid through a permanently implanted tube improves walking best, bladder control next and thinking least, with better results the earlier it is done. Not everyone responds, the operation carries risks, and it often coexists with genuine Alzheimer disease which limits recovery. But a treatable contribution is worth finding even when it is not the whole story.
How is it diagnosed?
By a brain scan showing the ventricles enlarged beyond what any shrinkage of tissue would explain, combined with a test of response. In that test a volume of fluid is drained through a needle in the lower back and walking is measured before and a few hours afterwards. A clear improvement strongly predicts that surgery will work. Some centres leave a drain in place for a few days instead, which is more reliable.
Can acne medication really raise the pressure in my head?
Yes, and both main types used for acne can do it. Isotretinoin and related retinoids can raise pressure inside the skull, as can high-dose vitamin A supplements, which are chemically related. Tetracycline antibiotics carry the same risk and are taken for months at a time. Combining a retinoid with a tetracycline is specifically contraindicated, because taking both multiplies the risk.
What kind of headache should worry me?
One that is worst on waking and when lying flat, and improves after being upright — the reverse of most headaches. Worse on coughing, straining or bending. Particularly if accompanied by a whooshing sound in the ear in time with the heartbeat, or by brief episodes of vision dimming. That combination needs the back of the eye examined, because the optic nerves can be damaged while the headache is still mild.
Why is the whooshing in my ear important?
Because it is highly characteristic of raised pressure inside the skull and almost nobody mentions it unless asked directly. It is rhythmic and synchronised with the pulse rather than a constant ringing. If you have it alongside headaches that are worse lying flat, say so at the appointment — it is one of the details that changes what gets examined.
My scan says enlarged ventricles. Do I have hydrocephalus?
Not necessarily, and usually not. Ventricles enlarge passively when brain tissue shrinks, which happens with normal ageing, in Alzheimer disease and in several other conditions — the fluid simply fills the space left behind, and the pressure is entirely normal. Ventricular size also varies enormously between healthy people. The finding means something only alongside the clinical picture, which is why the order of symptoms does more diagnostic work than the scan.
How do I know if a shunt has blocked?
The most reliable sign is the return of whatever the symptoms were before it was placed. Alongside that: headache, vomiting, drowsiness, irritability, personality change and worsening vision, and in a young child a bulging soft spot, downward-turned eyes, poor feeding or unusual sleepiness. Families usually spot it before anyone else and are usually right. Go to hospital and say the word shunt at the door.
Why does the body make so much of this fluid?
There is only about 150 millilitres present at any moment, but roughly 500 millilitres is produced daily, so the whole volume turns over three to four times a day. The constant replacement is what clears waste products from around the brain — a process that appears to happen largely during sleep, which is one of the reasons poor sleep and brain health are so closely connected.
What else imitates dementia?
Several things, which is the argument for never accepting the diagnosis without asking. Depression in older people can produce a convincing imitation that reverses with treatment. So can thyroid disease, B12 deficiency, sleep apnoea, and the cumulative effect of medications with anticholinergic properties. Adding the fluid disorder described here, there are at least four reasons to ask what else it could be before concluding it is Alzheimer disease.
📑 Sources and editorial
- Physiology of cerebrospinal fluid production, circulation and absorption, including turnover volumes
- Literature on glymphatic clearance and its relationship to sleep
- Diagnostic criteria and clinical features of normal pressure hydrocephalus, including the order of symptom onset
- Evidence on tap test and extended lumbar drainage as predictors of shunt response
- Outcome data on shunt surgery by symptom domain and by duration of symptoms before treatment
- Diagnostic criteria and visual outcomes in idiopathic intracranial hypertension
- Evidence on weight reduction as treatment for raised intracranial pressure
- Regulatory and pharmacological literature on retinoid-associated and tetracycline-associated intracranial hypertension, and the contraindication of the combination
- Clinical guidance on shunt malfunction recognition in adults and children
- Literature distinguishing ex vacuo ventricular enlargement from obstructive and communicating hydrocephalus
- Related reading: memantine, depressive pseudodementia, anticholinergic medicines and memory
- Related products: Alzheimer and dementia category
- RXshop Editorial Team — reviewed by James Carter, MD, Neurology
Medical Disclaimer: The information in this article is for educational and informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always seek guidance from a qualified healthcare provider with any questions you may have regarding a medical condition, and before starting, stopping or changing any medication.