Buy Calutide (Bicalutamide) Online — Cipla Selective Non-Steroidal Antiandrogen for Stage D2 Metastatic Prostate Cancer Combined Androgen Blockade


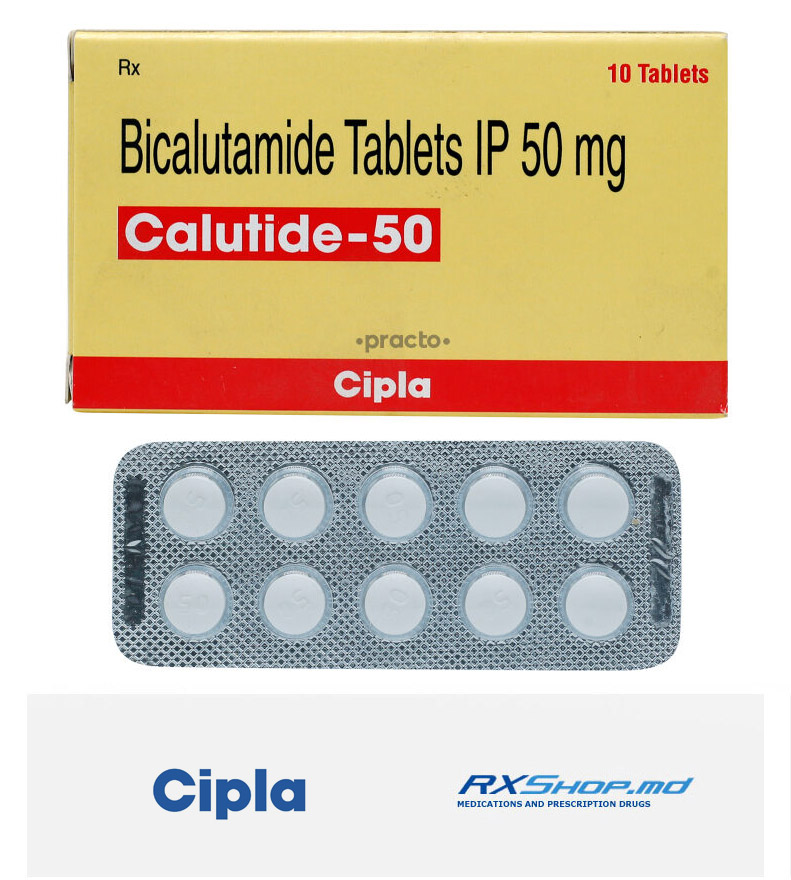
Calutide is the brand-name formulation of Bicalutamide manufactured by Cipla Limited (India) — one of the world's largest generic pharmaceutical manufacturers. Calutide delivers the same active molecule as the original Casodex (AstraZeneca), providing cost-effective access to the gold-standard selective non-steroidal antiandrogen used in metastatic prostate cancer treatment. Bicalutamide FDA-approved since 1995 as Casodex, with Cipla's Calutide offering the same FDA-equivalent active ingredient at significantly reduced cost. Listed on the WHO Model List of Essential Medicines. Calutide is the established standard component of Combined Androgen Blockade (CAB) therapy alongside an LHRH analog (Leuprolide, Goserelin) for stage D2 metastatic prostate cancer.
Pharmacology centers on selective competitive antagonism of the androgen receptor. Bicalutamide binds the androgen receptor in target tissues (prostate, prostate cancer cells, hair follicles, skin) and blocks testosterone and dihydrotestosterone (DHT) from activating the receptor — effectively neutralizing androgen-driven cancer growth signals at the cellular level. Unlike steroidal antiandrogens, Bicalutamide does NOT directly suppress LHRH/FSH production by the hypothalamic-pituitary axis, which is why combined therapy with an LHRH analog provides complete androgen blockade. Long half-life of approximately 6 days supports convenient once-daily dosing with stable plasma levels. Hepatic CYP3A4 metabolism.
Calutide is approved for stage D2 metastatic prostate cancer in combination with an LHRH analog as Combined Androgen Blockade therapy. Off-label uses include non-metastatic prostate cancer (Stage B2-C), flare prevention when initiating LHRH agonist therapy (Bicalutamide started 2 weeks prior blocks the initial testosterone surge), hirsutism in women, female pattern hair loss, transgender hormone therapy (feminizing regimens), and selective use in precocious puberty.
Available as Calutide 50 mg tablets. Standard dosing for Combined Androgen Blockade: 50 mg once daily alongside LHRH analog therapy. Monotherapy for early-stage disease: 150 mg once daily (in markets where this dose is available). Take consistently at the same time daily, with or without food.
Critical safety: ⚠️ Hepatotoxicity — baseline LFTs required, then periodic monitoring; discontinue if significant liver enzyme elevation. Gynecomastia (very common with monotherapy), hot flashes, decreased libido, erectile dysfunction, fatigue, anemia. Hepatic CYP3A4 metabolism — interactions with strong CYP3A4 inducers/inhibitors.
Free prescription
Discrete packaging
Have questions?
Quality Assurance
- Combined Androgen Blockade CAB: Standard CAB therapy component with LHRH analog (Leuprolide, Goserelin);
- Advanced Prostate Cancer: For advanced hormone-sensitive prostate cancer;
- Metastatic Prostate Cancer: For metastatic prostate cancer first-line management;
- Flare Prevention LHRH Initiation: Critical — started 2 weeks before LHRH agonist initiation to block initial testosterone surge ("flare");
- Hormone Sensitive Prostate Cancer: For hormone-sensitive prostate cancer subtypes;
- Stage B2 C Prostate Cancer: Off-label for non-metastatic stage B2-C prostate cancer;
- Locally Advanced Prostate Cancer: For locally advanced prostate cancer adjunct to radiation/surgery;
- Bicalutamide Monotherapy 150mg: 150 mg monotherapy for early-stage prostate cancer (where dose available);
- Hirsutism Women: Off-label for hirsutism in women — antiandrogen approach;
- Female Pattern Hair Loss: Off-label for androgenetic alopecia in women;
- Transgender Hormone Therapy: Off-label for transgender feminizing hormone therapy — androgen blockade;
- Precocious Puberty Selective: Off-label selective use in precocious puberty (familial male-limited);
- PSA Reduction Treatment: Reduces PSA levels in hormone-sensitive prostate cancer;
- Tumor Burden Reduction: Reduces tumor burden in metastatic prostate cancer;
- Bone Pain Palliation: Palliative bone pain reduction in metastatic prostate cancer with bone metastases;
- Prostate Cancer With LHRH Agonist: Combination with LHRH agonists for complete androgen suppression;
- Adjunct Surgical Castration: Adjunct to surgical castration (orchiectomy) for complete androgen blockade;
- Antiandrogen Therapy: Foundational antiandrogen therapy for androgen-dependent disorders;
- Prostate Cancer Maintenance: Long-term maintenance therapy in hormone-responsive prostate cancer.
- Better Prostate Cancer Control: Effective control of hormone-sensitive metastatic prostate cancer;
- Less PSA Progression: Reduces PSA progression in advanced prostate cancer;
- Less Tumor Burden: Reduces tumor burden in metastatic prostate cancer;
- Better Survival Combined Blockade: Combined Androgen Blockade improves survival vs LHRH alone in selected patients;
- Less Disease Progression Metastatic: Slows disease progression in metastatic prostate cancer;
- Less Bone Pain Metastatic: Palliative bone pain reduction in patients with bone metastases;
- Better LHRH Flare Prevention: Critical — prevents testosterone surge "flare" when starting LHRH agonist therapy;
- Less Symptom Worsening LHRH Initiation: Prevents acute symptom worsening during LHRH agonist initiation;
- Better Quality of Life Advanced Disease: Improved quality of life with effective disease control;
- Less Hirsutism Women: Off-label reduction in female hirsutism (excess hair growth);
- Better Female Hair Loss Off Label: Off-label benefit in female pattern hair loss;
- Better Transgender Feminization: Effective androgen blockade in transgender feminizing therapy;
- Better Daily Function: Once-daily dosing supports return to normal daily activities;
- Better Compliance Once Daily: Once-daily dosing improves long-term treatment compliance;
- Better Tolerability vs Steroidal Antiandrogens: Better tolerability profile vs older steroidal antiandrogens;
- Less Cardiovascular Risk vs DES: Lower cardiovascular risk profile vs diethylstilbestrol (DES);
- Brand Calutide Cipla: Cipla Indian generic brand of Bicalutamide — cost-effective alternative;
- Generic Bicalutamide: Affordable generic Bicalutamide versions expand global access to antiandrogen therapy;
- Cipla Generic Manufacturer: Cipla Limited — one of world's largest generic pharmaceutical manufacturers;
- Cost Effective Casodex Alternative: Cost-effective alternative to original Casodex brand — signature Calutide benefit;
- Selective Non Steroidal Antiandrogen: Selective non-steroidal antiandrogen (NSAA) — targeted receptor blockade;
- Androgen Receptor Antagonist: Competitive androgen receptor antagonist — blocks testosterone/DHT activation;
- Combined Androgen Blockade CAB: Standard CAB therapy component with LHRH analog — complete androgen suppression;
- Flare Prevention LHRH Initiation: Critical flare prevention when initiating LHRH agonist therapy;
- Long Half Life 6 Days: Long half-life ~6 days supports stable once-daily dosing with consistent plasma levels;
- Hepatic CYP3A4 Metabolism: Hepatic CYP3A4 metabolism — predictable pharmacokinetic profile;
- No LHRH FSH Suppression: Does NOT directly suppress LHRH/FSH — distinct from steroidal antiandrogens;
- Hormone Sensitive Prostate Standard: Established standard for hormone-sensitive prostate cancer treatment;
- Guideline Recommended NCCN EAU: NCCN, EAU guideline-recommended for advanced prostate cancer;
- WHO Essential Medicine: Listed on the WHO Model List of Essential Medicines for cancer care;
- 30 Plus Year Clinical History: 30+ years of clinical use since 1995 — established antiandrogen with extensive evidence.
Generic Calutide (Bicalutamide 50 mg) Medication guide:
📖 What Calutide Is and How It Works
Calutide is the Cipla brand of bicalutamide, a hormonal drug used to treat prostate cancer in men. AstraZeneca originally launched the drug in 1995 as Casodex. It has been generic since 2009 and Calutide is one of the widely available generic versions.
Prostate cancer in most men depends on testosterone and its more potent cousin dihydrotestosterone (DHT) to grow. Testosterone binds a receptor inside prostate cancer cells - the androgen receptor - and switches on the machinery that makes the cell divide. Cut off that signal and the tumour slows dramatically or stops.
Two main strategies do this. Either you drop testosterone levels themselves (through surgical castration or an LHRH agonist injection) or you leave testosterone alone but block the receptor it needs to bind. Calutide is the receptor-blocking strategy. It sits on the androgen receptor and prevents testosterone and DHT from getting in.
The main reasons Calutide gets prescribed
1. Combined androgen blockade. Given alongside an LHRH agonist injection (leuprolide, goserelin, triptorelin) in advanced or metastatic prostate cancer. The LHRH agonist drops testosterone; Calutide blocks whatever remaining androgen signal exists.
2. To prevent tumour flare. LHRH agonists briefly raise testosterone before they suppress it. Calutide is often started a week before the first LHRH injection to protect against this flare in men with symptomatic bone metastases.
3. Monotherapy at 150 mg in locally advanced disease, when a man wants to preserve libido and sexual function better than castration would allow.
What Calutide is not: a cure for advanced prostate cancer, a rescue drug for acute problems, or something to take without proper urology or oncology guidance. It is one hormonal option among several, prescribed against a specific clinical picture, and taken daily for months to years.
This guide walks through what Calutide does, what to expect in the first weeks, the two side effects most men notice first (gynecomastia and hot flushes), the liver monitoring you will need, and the newer drugs that have started to replace bicalutamide in some settings. Sections 3-5 explain the three main clinical contexts in detail.
💊 Why Doctors Prescribe Calutide for Prostate Cancer
Understanding why Calutide has been chosen for you shapes what to expect. The three main scenarios each have different dose, duration, and side effect balance.
The three main clinical contexts
Advanced or metastatic disease with LHRH agonist: Standard combined androgen blockade. Calutide 50 mg daily plus monthly or three-monthly LHRH injection. Duration usually indefinite until disease progresses.
LHRH agonist tumour flare prevention: Calutide 50 mg daily started 3-7 days before the first LHRH injection and continued for 2-4 weeks after. Prevents the transient testosterone rise from worsening bone pain or spinal cord compression.
Locally advanced monotherapy at 150 mg: Alternative to castration when the man wants to preserve testosterone-driven benefits (libido, energy, muscle mass, mood) at the cost of accepting higher gynecomastia rates. Not licensed everywhere for this indication.
The trade-off in one line
Calutide as monotherapy at 150 mg preserves more masculine function than castration but does not extend life as much in aggressive disease. In combination with an LHRH agonist at 50 mg it adds a modest survival benefit at the cost of side effect stacking. The right choice depends on cancer stage, PSA trajectory, and personal priorities.
Who gets what
- Newly diagnosed metastatic prostate cancer, hormone-sensitive: LHRH agonist + Calutide often started together, though some newer regimens use enzalutamide/apalutamide/darolutamide instead of bicalutamide - see Section 31
- Locally advanced disease, PSA-only recurrence: Calutide monotherapy at 150 mg is one option; LHRH monotherapy or watchful waiting are others
- Symptomatic bone metastases before LHRH start: Calutide flare cover for the first weeks
- Older men with prostate cancer and heart disease: Calutide-based regimens sometimes chosen over full castration to reduce cardiovascular side effect load
- Men who cannot tolerate LHRH agonists due to injection reactions or specific comorbidities
Off-label use of bicalutamide in transgender feminising hormone therapy exists in some clinics but is not a licensed indication and sits outside this cancer-focused guide. That use has different dose, duration, and monitoring rules and should be handled by specialist gender care services.
🔗 Calutide as Part of Combined Androgen Blockade
Combined androgen blockade (CAB) is the classical scenario for Calutide. The idea is straightforward: attack the androgen pathway from two angles at once.
The two arms of blockade
1. LHRH agonist (leuprolide, goserelin, triptorelin): switches off the pituitary signal that tells the testes to make testosterone. Serum testosterone drops to castrate levels (under 50 ng/dL or 1.7 nmol/L) within 3-4 weeks.
2. Calutide 50 mg daily: blocks the androgen receptor so any remaining androgen (adrenal androgens, or intracellular DHT) cannot signal.
Together, this is more complete blockade than either drug alone. Whether the extra 5-10 percent of blockade translates into meaningful survival benefit has been debated for 25 years.
What the meta-analyses show
The Prostate Cancer Trialists' Collaborative Group meta-analysis (Lancet 2000) pooled data from over 8 000 men in 27 trials. Combined androgen blockade with a non-steroidal antiandrogen (like bicalutamide) added about 2-3 percent absolute survival benefit at 5 years versus LHRH alone. Modest but real. This is why CAB is still standard in some countries and centres.
The modern challenge to classical CAB
Since around 2015, several trials have shown that newer androgen receptor inhibitors combined with an LHRH agonist beat classical CAB with bicalutamide:
- ENZAMET (2019) - enzalutamide + LHRH vs bicalutamide + LHRH; better overall survival with enzalutamide
- TITAN (2019) - apalutamide + LHRH; similar survival advantage
- ARCHES (2019) - enzalutamide added to standard ADT; better radiographic PFS
- STAMPEDE abiraterone arm - abiraterone + LHRH; substantial survival benefit
So in high-volume metastatic disease, modern practice often skips bicalutamide altogether and uses enzalutamide, apalutamide, darolutamide, or abiraterone with the LHRH agonist. Bicalutamide remains an option when the newer drugs are unavailable, unaffordable, or not tolerated.
Where Calutide-based CAB still has a role
- Low-volume metastatic disease where trials of newer agents show more modest benefit
- Older or frailer men where the tolerability of bicalutamide beats the newer agents
- Low-resource settings where enzalutamide or apalutamide are unavailable
- Men who cannot tolerate the newer agents due to falls, cognitive change, or cardiovascular limits
- As flare cover only, when the intention is not indefinite CAB
The CAB conversation has evolved. It is not that bicalutamide-based CAB stopped working - it did not. The newer androgen receptor inhibitors just work better on top of an LHRH agonist. Where bicalutamide is chosen today, the choice is deliberate and based on tolerability, availability, or specific clinical context.
🎯 Calutide as Monotherapy for Locally Advanced Disease
Bicalutamide at 150 mg once daily as monotherapy - without an LHRH agonist - is a specific option for locally advanced prostate cancer. The dose is triple the CAB dose. The point is to keep the man's testosterone levels normal while still blocking receptor signalling.
Why monotherapy is different
In classical castration or CAB, testosterone drops to under 50 ng/dL. The man becomes chemically castrated. This produces the full menopause-equivalent picture: hot flushes, loss of libido, erectile dysfunction, muscle mass loss, fatigue, mood changes, bone loss, and (over years) cardiovascular changes.
On bicalutamide 150 mg monotherapy, testosterone stays roughly normal or even rises a bit (feedback from receptor blockade). The man keeps more of his masculine physiology. Libido and sexual function are typically preserved better than with castration. Bone density and muscle mass are less affected. Cardiovascular consequences are milder.
The trade-off - what you accept
To preserve testosterone-driven benefits, you accept:
- High rates of gynecomastia - around 70 percent of men on monotherapy develop breast enlargement, often bilaterally, sometimes with tenderness
- Modestly less anti-cancer effect than combined androgen blockade in aggressive disease
- Occasional hot flushes (but fewer than on castration)
- Small but real liver toxicity risk requiring monitoring
The evidence base
The Early Prostate Cancer Programme (EPC) - three linked trials totalling 8 113 men - directly studied bicalutamide 150 mg in localised and locally advanced disease. Findings:
- Locally advanced disease: bicalutamide reduced disease progression and improved outcomes versus watchful waiting alone
- Localised disease: no clear benefit and possibly worse outcomes; not recommended in localised disease
- Adjuvant after radical prostatectomy: disease progression reduced but with heavy side effect load
On the basis of these findings, bicalutamide 150 mg monotherapy is licensed in Europe and elsewhere for locally advanced disease as an alternative to castration. Not licensed at this dose in the USA. Regulatory differences matter for what your treating team can prescribe.
Not for early localised disease
The EPC data specifically showed that bicalutamide monotherapy in localised, low-risk disease was not helpful and possibly harmful - increased non-cancer mortality without cancer benefit. Regulators withdrew the localised disease indication after these data. Calutide monotherapy is not a treatment for early low-risk prostate cancer - active surveillance, surgery, or radiotherapy fit those settings instead.
Choosing monotherapy at 150 mg over CAB or castration is a personal decision made with a urologist or oncologist. It suits some men very well, especially those where preserving quality of life around sexual function and physical energy matters as much as maximum anti-cancer effect. It suits others less well, particularly where cancer aggression makes maximum blockade the priority.
🔥 Calutide to Prevent LHRH Agonist Tumour Flare
This is the least dramatic-sounding but arguably most protective use of Calutide. LHRH agonists briefly raise testosterone before they suppress it. In some men that transient rise causes real harm. Bicalutamide covers the first weeks.
The physiology of LHRH agonist flare
LHRH agonists like leuprolide and goserelin work paradoxically. Initially they overstimulate the pituitary's LH-releasing receptors, causing a burst of LH and a spike in testosterone. Testosterone can rise to 150 percent of baseline in the first 1-2 weeks before the pituitary desensitises and testosterone falls.
For most men this transient rise is asymptomatic. For men with bone metastases, especially in the spine, this "flare" can produce:
- Worsening bone pain
- Rare but serious spinal cord compression
- Urinary retention if there is significant prostate obstruction
- Occasional cardiovascular events
How Calutide prevents flare
Bicalutamide blocks the androgen receptor within days of starting. When the LHRH-induced testosterone rise arrives, receptors are already occupied by bicalutamide, and the testosterone cannot signal. Flare symptoms are largely prevented.
The standard flare cover regimen
- Start bicalutamide 50 mg daily 3-7 days before the first LHRH injection
- Continue for 2-4 weeks after the first injection
- Stop bicalutamide once testosterone is confirmed at castrate level, unless combined androgen blockade is intended long-term
- If CAB is intended long-term, just continue bicalutamide indefinitely at 50 mg
Who especially needs flare cover
- Any man with symptomatic bone metastases - especially spinal metastases where cord compression could be catastrophic
- Men with significant urinary obstruction from prostate enlargement
- Men with very high PSA or heavy metastatic burden - more tumour means more tissue that can respond to transient testosterone rise
- Men whose disease is causing pain at baseline
The alternative: LHRH antagonists
LHRH antagonists (degarelix, relugolix) do not cause flare in the first place because they block the pituitary receptor directly rather than overstimulating it. Testosterone drops within days without a preceding rise. Men who need immediate testosterone suppression without any risk of flare are often started on degarelix or oral relugolix rather than an LHRH agonist with bicalutamide flare cover. Both approaches are valid.
Flare cover is a short-course use of Calutide. Once the flare window has passed, bicalutamide can usually be stopped. This is different from combined androgen blockade where bicalutamide continues indefinitely. Check with your urologist which pattern applies to you.
🔬 How Bicalutamide Blocks the Androgen Receptor
Understanding bicalutamide's mechanism explains almost every side effect - and every reason it works only in certain contexts.
How androgens normally work
The testes make testosterone under pituitary control. Testosterone circulates in blood, enters cells, and in prostate tissue converts to the more potent DHT. DHT binds the androgen receptor inside the cell. The bound receptor moves into the nucleus and switches on genes that drive prostate cell growth and function.
In healthy prostate this system builds and maintains normal tissue. In prostate cancer the same system fuels malignant growth. Most prostate cancers depend heavily on androgen receptor signalling, at least initially.
What bicalutamide does
Bicalutamide is a competitive, non-steroidal, first-generation antiandrogen. It enters cells, binds the androgen receptor, and prevents testosterone and DHT from binding. The receptor still moves into the nucleus but cannot switch on its target genes properly. Cancer cell proliferation slows or stops.
Testosterone levels themselves are not lowered by bicalutamide alone. In fact, monotherapy at 150 mg often raises serum testosterone slightly because the pituitary senses reduced androgen signalling and increases LH output. This is why the systemic feminising effects of full castration (loss of muscle, bone, cardiovascular changes) are less pronounced on bicalutamide monotherapy.
The pharmacokinetics
- Half-life around 6 days - long enough for reliable once-daily dosing
- Steady state reached in about 4-6 weeks after starting
- Metabolised in the liver primarily by CYP3A4, then glucuronidated
- Excreted in urine and faeces as inactive metabolites
- Two enantiomers (R and S); the R form is the active one
- Absorption not affected by food
Why side effects centre on breast tissue
When androgen signalling is blocked but testosterone stays available, some of that testosterone gets converted to estradiol by the aromatase enzyme in fat and other tissues. Higher estradiol relative to unopposed androgen effect stimulates breast tissue. Result: gynecomastia and breast tenderness in 50-70 percent of men on 150 mg monotherapy, lower rates on 50 mg CAB. Section 15 covers this.
First-generation antiandrogens like bicalutamide have been superseded in some contexts by second-generation antiandrogens - enzalutamide, apalutamide, darolutamide. These bind the androgen receptor more tightly, prevent receptor movement to the nucleus, and do not activate the receptor even in resistance settings. They are more potent but also more expensive and have their own side effect profiles. Section 31 covers the switching landscape.
📊 Where Calutide Sits Among Antiandrogens
Antiandrogens are a small family. Understanding where Calutide sits among them helps explain when it is chosen and when a newer drug fits better.
| Drug | Generation | Notes |
|---|---|---|
| Flutamide | 1st gen non-steroidal | Older, three times daily, more liver toxicity - largely replaced |
| Bicalutamide (Casodex, Calutide) | 1st gen non-steroidal | Once daily, still widely used |
| Nilutamide | 1st gen non-steroidal | Less common; interstitial lung disease risk |
| Cyproterone | Steroidal antiandrogen | Progestin-like; less used for prostate cancer now |
| Enzalutamide (Xtandi) | 2nd gen | Higher affinity, blocks nuclear translocation; approved 2012 |
| Apalutamide (Erleada) | 2nd gen | Similar to enzalutamide, different side effect balance |
| Darolutamide (Nubeqa) | 2nd gen | Less CNS penetration, fewer cognitive effects |
Bicalutamide advantages
- Once-daily oral dosing
- Widely available and cheap as generic (including Calutide)
- Three decades of safety experience
- Generally well tolerated at 50 mg
- 150 mg monotherapy option preserves libido and physical function
- Fewer CNS side effects than enzalutamide
- Fewer falls, less fatigue than newer drugs in older men
Where newer drugs beat bicalutamide
- High-volume metastatic hormone-sensitive disease (ENZAMET, TITAN, ARCHES)
- Non-metastatic castration-resistant disease (PROSPER, SPARTAN, ARAMIS)
- Aggressive disease where maximum receptor blockade is priority over side effect trade-off
- Post-bicalutamide progression - newer drugs can still work when bicalutamide fails
The clinical reality in 2026 is a two-tier landscape. In well-resourced systems with high-volume metastatic disease, enzalutamide, apalutamide, darolutamide, or abiraterone often replace bicalutamide. In many other contexts - low-volume disease, older or frailer men, tolerability priorities, resource limitations - bicalutamide remains a reasonable and widely used option. Calutide continues to sell at scale globally because the newer agents have not replaced it everywhere.
⚖️ The Early Prostate Cancer Trial Programme
The Early Prostate Cancer (EPC) Trial Programme is the biggest single evidence base for bicalutamide monotherapy. Three linked trials, over 8 000 men, and clear findings that shaped how the drug is used at 150 mg.
The trial structure
- Three parallel trials in North America, Scandinavia + rest of Europe, and Australia + Mexico + Israel
- 8 113 men total
- Men with T1-T4, N0/Nx, M0 prostate cancer - localised or locally advanced disease
- Randomised to bicalutamide 150 mg daily or placebo
- Added to standard care - watchful waiting, radical prostatectomy, or radiotherapy
- Long follow-up - primary and secondary publications 2005, 2008, 2010
The main findings by baseline setting
Locally advanced disease (T3-T4 or high-grade):
- Bicalutamide significantly reduced disease progression
- Overall survival benefit in men treated with watchful waiting or radiotherapy
- Established the licensed indication for 150 mg monotherapy in Europe
Localised disease (T1-T2, low-risk):
- No benefit and possibly worse outcomes
- Increased non-cancer mortality
- Led to regulatory withdrawal of localised disease indication
Adjuvant after radical prostatectomy:
- Reduced biochemical progression
- No clear overall survival benefit at long follow-up
- Substantial side effect burden - dropout rates were high
Side effect profile from EPC
- Gynecomastia: 66-75 percent of men on bicalutamide vs 5-8 percent on placebo
- Breast tenderness: 68-73 percent vs 4-8 percent
- Hot flushes: 12-15 percent (much lower than castration)
- Elevated liver enzymes: 3-4 percent
- Discontinuation for side effects: around 20 percent
- Sexual function largely preserved compared with castration
The lasting impact of EPC
The EPC Programme did three important things for clinical practice. It established the licensed 150 mg monotherapy indication in locally advanced disease. It removed the drug from the localised low-risk setting where it did harm. And it quantified the side effect profile at high dose, particularly gynecomastia - which changed practice around prophylactic breast radiotherapy (Section 29). Twenty years on, EPC data still frame how Calutide monotherapy is offered.
📏 Choosing Your Calutide Dose - 50 or 150 mg
Calutide comes in two strengths: 50 mg and 150 mg. The choice between them is driven by clinical context, not personal preference.
The two doses and their uses
| Dose | Main use |
|---|---|
| 50 mg once daily | Combined androgen blockade with LHRH agonist; LHRH flare prevention |
| 150 mg once daily | Monotherapy in locally advanced disease (Europe and elsewhere; not licensed in USA at this dose) |
Why the doses differ
In CAB, testosterone is already suppressed by the LHRH agonist. Only weak adrenal androgens and residual signalling remain. Bicalutamide 50 mg is enough to cover this. Higher doses do not add benefit and just add side effects.
In monotherapy, testosterone stays at normal or slightly elevated levels. 50 mg is not enough to block that. 150 mg gives the receptor occupancy needed to control disease. This is a real dose-response relationship, not a marketing tier.
Practical dosing rules
- Take one tablet once daily
- Same time each day, with or without food
- Do not split or crush tablets
- If you switch between 50 mg and 150 mg indications, this is a treating team decision - do not adjust yourself
- Duration varies from a few weeks (flare cover) to indefinite (CAB or monotherapy)
Doses that are NOT used
- Twice-daily bicalutamide - long half-life makes this unnecessary
- Higher than 150 mg - no additional benefit, more toxicity
- Lower than 50 mg in an adult man for prostate cancer
- Bicalutamide in premenopausal women or children
If your prescription changes from 50 mg to 150 mg or vice versa, ask the treating team why. It usually reflects a shift in clinical strategy - from CAB to monotherapy, or from flare cover to something longer. Understanding the reason helps you understand what to expect from the change.
📅 Your First Two Weeks Starting Calutide Therapy
What actually happens in the first two weeks on Calutide.
Days 1-3. Absorption is complete within a few hours. Bicalutamide starts binding androgen receptors within a day. Effects on PSA and clinical measures are not immediate - the drug needs steady state, and cancer cells need time to respond. You will not usually feel anything from the drug itself in the first few days.
Week 1. Blood levels are still rising toward steady state, which will not be reached for 4-6 weeks due to the long half-life. If you were started on bicalutamide as LHRH flare cover before an injection, this is the critical protective period. If you are on combined androgen blockade, the LHRH agonist is doing most of the visible work at this stage.
Week 2. Some early side effects may appear. Hot flushes are more from the LHRH agonist than from bicalutamide itself, but can be noticed at this point. Breast tenderness may start to appear, especially on monotherapy at 150 mg. Baseline blood tests are usually done around now.
Standard baseline tests before starting
- PSA - the tracking marker for treatment response
- Liver function tests (LFTs) - baseline before hepatotoxicity monitoring
- Serum testosterone - especially if CAB, to confirm castrate levels after LHRH takes effect
- Full blood count and kidney function
- Lipid profile and fasting glucose if starting long-term therapy
- Bone density (DXA) if long-term castration-level testosterone is planned
- ECG in men with cardiac history or QT concerns
Common early experiences
- Little or nothing in the first few days
- Some fatigue in the first weeks - often more from the LHRH agonist
- Occasional early breast sensation (fullness, tenderness) - especially at 150 mg
- Hot flushes appearing within 2-4 weeks (mainly LHRH-driven if on CAB)
- PSA usually falls in the first month if the cancer is hormone-sensitive
Signs to call the treating team in the first two weeks
- Yellowing of eyes or skin - possible liver reaction
- Severe abdominal pain or dark urine
- Rash - especially if extensive or with fever
- Sudden shortness of breath, chest pain
- Sudden worsening of bone pain - possible LHRH flare not adequately covered
- Any new leg weakness or bladder/bowel change - urgent, possible spinal cord compression
- Severe fatigue disproportionate to expected
Most men start Calutide without incident. The drug has one of the smoother onboarding profiles of hormonal cancer treatments. The bigger side effect burden emerges over months rather than days, particularly gynecomastia (Section 15) and metabolic changes.
⏰ When to Take Calutide Each Day
Calutide timing is straightforward. One tablet, once a day. The 6-day half-life means the exact time barely matters - what matters is consistency and adherence over months.
The basic rules
- One tablet once daily
- Same time each day, roughly within a few hours
- With or without food - your choice, be consistent
- Swallow whole with water; do not crush or split
- Morning or evening both work equally well
Anchoring the dose
- With breakfast is common and easy to remember
- Weekly pillbox refilled every Sunday - the single most effective adherence habit
- Phone reminder labelled "Calutide" or "bicalutamide"
- Keep the pack visible - kitchen counter beats bathroom cabinet
- Refill the prescription 2 weeks before you run out
- If travelling, take 30 percent extra supply
Coordinating with LHRH injections
If you are on combined androgen blockade, the LHRH agonist is a monthly or three-monthly injection given at a clinic. Calutide is the daily oral part. The two do not need to be timed together - Calutide is on its own daily rhythm; the injection is on a calendar-based schedule you attend clinic for. Missing a Calutide dose is a small issue (Section 24); missing an LHRH injection matters more and needs a call to the treating team to reschedule.
Long-term adherence is the real challenge
For men on Calutide for years, adherence in year 2 and beyond tends to drift. Side effects fade in urgency, life gets in the way, and it becomes easy to miss doses. The recurrence and progression risk is worse in men who take the drug erratically. If side effects or life pressures are making adherence hard, this is a conversation worth having with the treating team before dose skipping becomes a habit - there are usually better answers than silent dropout.
Section 24 covers what to do about a missed dose. Short version: within 12 hours, take it; more than 12 hours, skip and take the next dose as usual. Never double up.
🍽️ Food, Diet and Weight on Calutide
Diet on Calutide is not fussy. Food does not meaningfully affect absorption. There are no forbidden foods. But two dietary areas matter for men on long-term therapy - weight gain and metabolic changes.
Food and Calutide absorption
- Take with or without food - your choice
- Grapefruit and grapefruit juice - caution: bicalutamide is metabolised by CYP3A4 which grapefruit inhibits; large amounts can raise drug levels
- Moderate occasional grapefruit is generally fine; daily grapefruit juice is not
- Seville oranges - similar mechanism, treat like grapefruit
- St John's Wort - avoid; enzyme induction lowers bicalutamide levels
Weight and body composition changes
Men on Calutide plus LHRH agonist commonly gain 3-5 kg over the first year as the loss of testosterone shifts body composition:
- Muscle mass declines
- Fat mass rises, especially around the waist
- Insulin sensitivity drops - risk of new type 2 diabetes rises
- Cholesterol drifts up
- Metabolic rate falls slightly
On bicalutamide 150 mg monotherapy (without an LHRH agonist), these changes are much smaller because testosterone stays roughly normal.
A sensible eating pattern on Calutide
- Mediterranean-style - vegetables, whole grains, oily fish, olive oil, moderate lean meat
- Adequate protein - 1.0-1.2 g/kg body weight daily supports muscle
- Cut ultra-processed food - the main source of hidden calories, refined carbohydrate, and salt
- Moderate simple carbohydrates - insulin sensitivity is already impaired
- Adequate calcium and vitamin D for bone protection
- Fibre from vegetables, fruit, whole grains
The exercise-diet combination
Diet alone cannot fully counteract the body composition shift from castration-level testosterone. Resistance training combined with adequate protein is the most effective way to preserve muscle mass and metabolic health. Aim for weight machines or bodyweight exercises 2-3 times a week alongside dietary attention. Section 27 covers exercise in more detail.
Supplements to avoid on Calutide include large-dose antioxidant packs marketed for prostate health, saw palmetto in medicinal doses, and any herbal androgen-boosting formulations. Standard multivitamins and reasonable calcium and vitamin D supplementation are fine.
🍷 Alcohol Rules When Taking Calutide Long-Term
Alcohol on Calutide has two considerations. The first is liver-related: Calutide can cause liver enzyme rises, and alcohol adds to the liver load. The second is general - alcohol is a modest independent factor in cancer outcomes and does not help.
The liver angle
Bicalutamide causes elevated liver enzymes in about 3-5 percent of men. Serious drug-induced liver injury is rare but has been reported. Heavy alcohol use amplifies both the risk and the difficulty of interpretation - a raised ALT could be the drug, the drink, or both.
Section 19 covers liver monitoring in detail. On Calutide, LFTs are checked before starting, at 1-3 months, and periodically thereafter.
Sensible position
- Moderate drinking is compatible with Calutide for most men
- Up to 14 units per week spread across the week, per UK CMO guidance
- Alcohol-free days most of the week
- No binge drinking - especially harmful to liver
- Abstain during any active liver enzyme rise
- Cut back during the first months while liver monitoring establishes a stable baseline
Situations to stop or avoid alcohol entirely
- Existing liver disease
- History of alcohol dependence
- Elevated LFTs on routine monitoring
- Concurrent chemotherapy (docetaxel, cabazitaxel)
- Advanced disease with liver metastases
- Multiple hepatotoxic drugs being taken together
Alcohol and hot flushes
Some men on combined androgen blockade find that alcohol triggers or worsens hot flushes and disrupts sleep. This is more marked in men who are chemically castrated (CAB) than on bicalutamide monotherapy where testosterone stays normal. If flushes are troubling on Calutide-based CAB, cutting alcohol back is one of the easier levers.
Alcohol is not banned on Calutide. Moderate drinking is fine for most men with normal liver function and no dependence history. The specific reasons to be careful are liver monitoring and (for men on CAB) hot flushes and sleep. Where the treating team has asked for stricter limits, that guidance overrides general advice.
🚨 Calutide Side Effects - Full Overview
Calutide has a well-characterised side effect profile after three decades of use. Most side effects trace back to the mechanism - androgen receptor blockade. When combined with an LHRH agonist, side effects of CAB reflect both drugs. Below is the whole picture; individual sections that follow go deeper on each major effect.
Common (over 10 percent of men)
- Gynecomastia (breast enlargement) - Section 15; 30 percent on 50 mg, 70 percent on 150 mg
- Breast tenderness - similar rates
- Hot flushes - especially on CAB; Section 16
- Reduced libido on CAB; less on monotherapy; Section 17
- Erectile dysfunction on CAB
- Fatigue - Section 18
Less common (1-10 percent)
- Elevated liver enzymes - Section 19
- Nausea
- Diarrhoea or constipation
- Weight gain - especially on CAB; Section 12
- Mood changes, depression
- Insomnia
- Rash
- Muscle mass loss - on CAB
- Bone density loss - on CAB; Section 20
Uncommon
- Anaemia - especially on CAB
- Fluid retention
- Hair thinning
- Dry skin
- Photosensitivity rash
- QT prolongation - Section 22
- Interstitial lung disease - rare
Rare but serious - stop and seek urgent care
- Drug-induced liver injury - yellowing of eyes/skin, dark urine, right upper abdominal pain
- Severe skin reaction - blistering, peeling, mucosal involvement (Stevens-Johnson syndrome very rare)
- Severe interstitial lung disease - progressive breathlessness, dry cough, fever
- Angina, arrhythmias, or fainting - possible QT-related events
- Anaphylactic reaction - facial swelling, difficulty breathing
- Severe depression with thoughts of self-harm
Comparison note
Calutide has a milder overall side effect profile than the older flutamide (fewer GI issues, less severe liver toxicity) and the newer enzalutamide (less fatigue, less cognitive change, no falls signal). It has more gynecomastia than the newer agents. This is one of the reasons bicalutamide remains widely used - the tolerability profile fits certain men better than the newer options do.
👤 Gynecomastia and Breast Tenderness on Calutide
Breast enlargement is the most distinctive side effect of Calutide, especially at the 150 mg monotherapy dose. It happens in roughly 30 percent of men on CAB at 50 mg and 70 percent of men on monotherapy at 150 mg. For many men it is the biggest quality-of-life issue on this drug.
Why it happens
Bicalutamide blocks androgen receptors but does not lower testosterone. Some of that testosterone is converted by aromatase (in fat and breast tissue) into estradiol. In healthy men, testosterone effects on breast tissue balance out estrogen effects. Block the testosterone effect while leaving estrogen unopposed, and breast tissue grows.
What the enlargement looks like
- Usually starts within 2-3 months of starting the drug
- Bilateral in most cases
- Firm glandular tissue under the nipple, not just fat
- Tenderness often precedes visible enlargement
- Can be mildly painful, especially with clothing friction or physical contact
- Progresses over 6-12 months, then usually stabilises
- Partial reversal on stopping the drug, but not always full
Prevention and treatment options
Prophylactic breast irradiation - a single low-dose radiotherapy fraction (12-15 Gy) to each breast before starting Calutide monotherapy reduces gynecomastia rates by roughly half. Well-established option in many European centres. Section 29 covers this.
Tamoxifen 10-20 mg daily - reduces breast tenderness and slows enlargement. Started at the same time as Calutide or when symptoms appear. Evidence supports both prevention and treatment. Small VTE risk to weigh.
Anastrozole 1 mg daily - aromatase inhibitor; blocks estradiol formation. Less effective than tamoxifen for this specific problem in trials.
Surgical management - subcutaneous mastectomy or liposuction for established gynecomastia that has not resolved on stopping the drug.
When to intervene
For men starting Calutide monotherapy at 150 mg, gynecomastia prevention is worth discussing proactively - either prophylactic breast radiotherapy before starting the drug, or tamoxifen from the beginning. Waiting for established gynecomastia and then trying to reverse it is much less effective. For men on 50 mg CAB, prophylactic measures are used less often because rates are lower, though tamoxifen is a reasonable option if breast tenderness becomes bothersome.
A gynecomastia note that matters
Not every breast change on Calutide is drug-related gynecomastia. A hard, unilateral, non-tender lump - especially in an older man with cancer history - needs proper assessment. Male breast cancer is rare but real, and Calutide alone does not explain unilateral masses. Any unusual breast finding should be examined by the treating team.
Gynecomastia is one of the more distressing side effects because it is visible and affects body image and clothing. It is worth naming this in the initial conversation with your urologist or oncologist, and asking about prevention options, before starting long-term therapy - especially at the 150 mg monotherapy dose.
🥵 Hot Flushes and Night Sweats on Calutide
Hot flushes on Calutide differ dramatically depending on the regimen. In combined androgen blockade with an LHRH agonist, they are common and largely LHRH-driven. On monotherapy at 150 mg without LHRH, they are much less common - testosterone stays normal, so the hypothalamic thermoregulation is less disrupted.
Rates by regimen
- Calutide + LHRH agonist (CAB): hot flushes in 50-70 percent of men, mainly from the LHRH agonist
- Calutide 150 mg monotherapy: hot flushes in 12-15 percent
- Calutide as flare cover only: hot flushes appear when the LHRH agonist takes effect
- Severity typically peaks in the first 6 months then eases somewhat
What they feel like
- A wave of heat, usually starting in the chest or face
- Sweating - sometimes drenching, sometimes just facial
- Sometimes a racing heart
- Duration typically 1-5 minutes per episode
- Night sweats disrupt sleep - often the more troubling form
- Common triggers: hot drinks, spicy food, alcohol, stress
Non-drug strategies
- Cool bedroom - 17-19 C; fan on if a partner disagrees
- Cotton or bamboo bed linen and nightwear
- Layered clothing during the day - easy to shed
- Avoid triggers - alcohol, spicy meals, hot drinks near bedtime
- Regular exercise - reduces frequency and severity in trials
- Weight management - hot flushes worse at higher BMI
- Paced breathing at flush onset - slow deep breaths can shorten episodes
Drug options for troublesome flushes
- Venlafaxine 37.5-75 mg daily - SNRI with the most trial data in men with androgen-deprivation flushes
- Gabapentin 300-900 mg at bedtime - particularly good for night sweats
- Medroxyprogesterone acetate - progestin; effective but comes with its own side effect load
- Cyproterone acetate - steroidal antiandrogen with progestin action; sometimes used specifically for hot flush relief in CAB
- Clonidine - older option, less effective than SNRIs
- Acupuncture - some evidence in trials of men with androgen-deprivation flushes
Do not use for flushes on Calutide
- Testosterone replacement - contraindicated in prostate cancer therapy
- DHEA supplements - can be aromatised to estrogen; may worsen gynecomastia
- Untested herbal "male hormone balance" formulations
Hot flushes usually fade over the first year even without specific treatment. Persistent severe flushes at month 12 deserve active management - not endurance. Sleep is the priority; if night sweats are wrecking sleep, treat that first.
💗 Sexual Function and Libido on Calutide
Sexual function on Calutide depends heavily on the regimen. This is one of the areas where the choice between combined androgen blockade and monotherapy matters most.
On Calutide monotherapy at 150 mg
- Testosterone stays normal or slightly elevated
- Libido preserved in most men
- Erectile function largely preserved - some reduction but nowhere near castration levels
- Ejaculation and orgasm preserved
- This is one of the main reasons monotherapy is chosen over castration when disease allows
On Calutide plus LHRH agonist (CAB)
- Testosterone at castrate level - under 50 ng/dL
- Libido substantially reduced in most men
- Erectile dysfunction common - 70 percent or more
- Reduced ejaculate volume, sometimes anejaculation
- Effects usually appear within the first months and persist through therapy
Managing sexual side effects
- PDE-5 inhibitors (sildenafil, tadalafil, vardenafil) - can help erectile function, especially on monotherapy where libido remains
- Intracavernosal injections (alprostadil) - work even with severe erectile dysfunction on CAB
- Vacuum erection devices - non-drug option
- Penile implants - for definitive erectile dysfunction when other options fail
- Couples counselling and psychosexual therapy - especially for the libido and intimacy dimensions
- Broadening intimacy beyond penetrative sex - realistic conversation for many CAB clients
Bring this up with the treating team
Sexual side effects are among the most under-reported drug complaints in men - a mixture of embarrassment and assuming there is nothing to be done. Both are wrong. Most urology and oncology teams have systematic pathways to help with sexual function during and after prostate cancer therapy. Some centres have dedicated psychosexual clinics linked to the cancer service. Asking is the door that opens options.
Partner impact
Sexual side effects affect relationships as much as the individual. Involving a partner in early conversations about what to expect, and in decision-making about CAB versus monotherapy where both are options, avoids surprises and preserves the relationship better than silent adaptation.
🔋 Fatigue and Reduced Energy on Calutide
Fatigue on Calutide is common and multifactorial. Some of it comes from the drug. More of it - in men on CAB - comes from the low testosterone environment created by the LHRH agonist. Untangling the sources and addressing what can be addressed is worth doing.
Where fatigue comes from
- Low testosterone effects on muscle and energy metabolism (CAB, not monotherapy)
- Muscle mass loss reducing baseline metabolic and functional capacity
- Poor sleep from hot flushes and night sweats
- Anaemia - androgen deprivation drops haemoglobin by around 1 g/dL on average
- Reduced physical activity - deconditioning becomes self-reinforcing
- Cancer-related fatigue - especially in metastatic disease
- Mood effects, depression
- Concurrent chemotherapy if applicable
What actually helps
- Regular aerobic and resistance exercise - by far the strongest intervention for cancer-related and androgen-deprivation fatigue in trials
- Adequate protein and calorie intake - counter muscle loss
- Sleep hygiene and treatment of night sweats
- Address anaemia - iron, B12, folate deficiency correction; erythropoietin in specific settings
- Treat depression if present - SNRIs work for mood and can help fatigue
- Vitamin D optimisation - deficiency worsens fatigue
- Cognitive behavioural therapy for cancer-related fatigue - specific programmes exist
The exercise paradox for fatigued men
Fatigue makes exercise feel harder to start. But exercise consistently reduces fatigue better than rest does. This is counter-intuitive but well-supported. Start with what feels sustainable - 10-15 minutes of walking daily is a foundation. Add strength training twice weekly after a few weeks. Group exercise programmes for men on prostate cancer therapy (dedicated survivorship clinics in some centres) can help both structure and social contact.
When fatigue needs urgent assessment
- New or rapidly worsening breathlessness
- Fatigue with chest pain or palpitations
- Fatigue with pallor and rapid onset
- Fatigue with new severe bone pain - possible progression
- Fatigue with severe abdominal pain or jaundice
Fatigue is one of the side effects that is often left unaddressed because it does not feel like a "real" medical problem. It is. Bringing it to the oncology or urology team, especially when it is affecting daily function, opens genuine treatment options.
🧪 Liver Function Monitoring During Calutide Therapy
Bicalutamide can raise liver enzymes and, rarely, cause serious drug-induced liver injury. This is one of the specific reasons Calutide is monitored more actively than many other cancer drugs. The monitoring itself is boring - three blood tests a year mostly - but the point is to catch trouble early.
What the drug does to the liver
- 3-5 percent of men have elevated liver enzymes on bicalutamide
- Usually asymptomatic - picked up on routine bloods
- Serious drug-induced liver injury is rare (well under 1 percent) but has been reported
- Occurs at any dose (50 or 150 mg)
- Most cases appear in the first 3-6 months of therapy
- Reversible on stopping the drug in almost all cases
Standard monitoring schedule
| When | What is checked |
|---|---|
| Baseline | Full LFTs: ALT, AST, ALP, bilirubin, albumin |
| Month 1 | Repeat LFTs; check ALT particularly |
| Month 3 | Repeat LFTs |
| Every 3-6 months | Continue during first year, then every 6-12 months |
| Any new symptom | Immediate LFT check |
Symptoms that need urgent liver assessment
- Yellowing of eyes or skin (jaundice)
- Dark urine - tea-coloured
- Pale stools - putty-coloured
- Right upper abdominal pain - especially if new
- Persistent nausea or loss of appetite
- Unusual bruising or bleeding
- Itching without rash
Any of these need same-day medical review, LFTs, and consideration of stopping Calutide until liver function is clarified.
Interpreting the numbers
- ALT under 3x upper limit of normal: monitor more frequently but usually continue
- ALT 3-5x upper limit of normal: discuss stopping; investigate other causes
- ALT over 5x upper limit of normal or rising bilirubin: stop Calutide
- Any evidence of clinical hepatitis: stop drug and specialist assessment
After a liver reaction
Most enzyme rises resolve within weeks of stopping bicalutamide. Serious drug-induced liver injury is followed until full recovery. Rechallenge with bicalutamide after a significant hepatic reaction is not usually done - the same drug is likely to produce the same reaction. Enzalutamide or another agent replaces it if hormonal therapy is still needed.
🦴 Calutide Effect on Bone Health and Density
Bone health on Calutide depends entirely on the regimen. On monotherapy at 150 mg with normal testosterone, bone density is largely preserved. On combined androgen blockade with an LHRH agonist, bone loss is significant and needs active protection.
Why CAB damages bone
Testosterone (and estradiol converted from it) supports bone remodelling in men just as estrogen does in women. Dropping testosterone to castrate level accelerates bone resorption. Men on long-term androgen deprivation lose bone density at 2-5 percent per year in the hip and spine, especially in the first years. Fracture risk climbs measurably.
Fracture data
Meta-analyses of men on long-term androgen deprivation show fracture rates approximately double compared with age-matched men not on ADT. Hip fractures particularly matter - one-year mortality after hip fracture in an older man is around 20-25 percent. Bone protection is therefore not cosmetic.
The bone protection plan for men on CAB
Every man starting long-term CAB should have:
- Baseline DXA (bone density) scan
- Vitamin D level checked and corrected if deficient
- Calcium intake reviewed and supplemented to reach 1 000-1 200 mg daily
- Vitamin D3 supplement 800-1 000 IU daily unless replete
- Weight-bearing and resistance exercise regularly
- Repeat DXA every 2 years
- Fall risk assessment especially in older men
When to add a bone-modifying drug
Indications for adding a bisphosphonate or denosumab:
- Baseline T-score below -2.0 on DXA
- T-score falling below -2.0 during therapy
- Any prior fragility fracture
- Rapid bone density loss between DXA scans
- High FRAX risk score
- Bone metastases (different indication and dosing)
Options:
- Denosumab (Prolia 60 mg subcutaneous twice yearly) for bone protection; higher dose (Xgeva) for bone metastases
- Zoledronate 4-5 mg IV once yearly or every 3-4 weeks in metastases setting
- Alendronate or risedronate oral - effective but strict dosing rules
Bicalutamide 150 mg monotherapy - the different story
On monotherapy testosterone stays normal or slightly elevated. Bone density is largely preserved. Some evidence even suggests improved bone density from the higher estradiol resulting from unopposed testosterone conversion. Fracture risk is much closer to baseline than on CAB. Bone monitoring and protective drugs are usually not needed for monotherapy clients unless they have prior osteoporosis. This is one of the significant quality-of-life advantages of monotherapy.
Exercise matters enormously for bone health regardless of regimen. Weight-bearing aerobic exercise plus progressive resistance training preserves bone density and reduces fall risk. Section 27 covers exercise in more depth.
❤️ Cardiovascular Considerations on Long-Term Calutide
Cardiovascular effects of long-term Calutide therapy have been debated for years. The picture is different between the two main regimens and worth understanding.
CAB and cardiovascular risk
Long-term androgen deprivation (LHRH agonist plus bicalutamide) has been linked to modestly increased cardiovascular events in observational cohorts:
- Weight gain and increased body fat
- Insulin resistance and higher rate of new-onset type 2 diabetes
- Modest lipid changes - LDL rise, triglyceride rise
- Small increase in coronary events - most seen in men with pre-existing cardiovascular disease
- Effect appears to accumulate over years of therapy
Monotherapy at 150 mg
Cardiovascular impact is much smaller because testosterone stays normal. The metabolic package that drives cardiovascular risk on CAB (weight gain, insulin resistance, lipid changes) is largely absent. Cardiovascular events on 150 mg monotherapy in the EPC trials were similar to placebo, with one exception - a small signal of non-cancer mortality in low-risk localised disease that led to withdrawal of that indication.
Standard cardiovascular protection for men on long-term Calutide
- Baseline BP, lipids, fasting glucose or HbA1c before starting
- BP at each clinic visit
- Lipids and HbA1c yearly during long-term therapy
- Standard cardiovascular prevention - treat hypertension, statin if indicated, treat diabetes
- Encourage smoking cessation - one of the biggest reversible risks
- Weight management and exercise - counters the metabolic drift
- Cardiovascular risk calculator (QRISK, ASCVD, SCORE2) used to guide statin decisions
Cardiovascular events are a bigger issue than the cancer for many men
For men diagnosed with prostate cancer in their 60s and 70s, cardiovascular disease is often the eventual cause of death - not the cancer. This is especially true for men with lower-risk disease on long-term hormonal therapy. Managing cardiovascular risk factors during the years on Calutide matters as much as taking the drug itself. Do not lose sight of general prevention while focused on the cancer plan.
Cardiovascular symptoms to flag urgently
- Chest pain or discomfort, especially on exertion
- Unusual breathlessness
- Ankle swelling that is new
- Fainting or near-fainting on exertion
- Sustained palpitations
- Sudden severe headache with visual changes
⚡ QT Prolongation Risk with Calutide
QT interval prolongation is a specific electrocardiographic effect where the heart's electrical recovery time is longer than normal. Severely prolonged QT can trigger a dangerous arrhythmia called torsades de pointes. Bicalutamide has been associated with modest QT prolongation, and this is worth understanding for men with cardiac history or on other QT-affecting drugs.
What the data show
- Bicalutamide can prolong QT interval, though modestly
- Clinically important arrhythmias are rare
- Risk climbs when combined with other QT-prolonging drugs
- Older men and men with structural heart disease at higher risk
- Electrolyte disturbances (low potassium, low magnesium) amplify the risk
When to be careful
- Baseline ECG recommended in men with prior cardiac history before starting Calutide long-term
- Baseline electrolytes - correct any low potassium or magnesium before starting
- Congenital long QT syndrome - discuss with a cardiologist before starting
- Prior torsades or unexplained cardiac arrest - Calutide relative contraindication
- Bradycardia or heart block
QT-prolonging drugs to watch for
Common medications that add QT effect on top of Calutide:
- Antiarrhythmics - amiodarone, sotalol, dronedarone
- Some antibiotics - macrolides (azithromycin, clarithromycin), fluoroquinolones (moxifloxacin, ciprofloxacin), some antifungals (ketoconazole, fluconazole)
- Antipsychotics - haloperidol, quetiapine, ziprasidone
- Some antidepressants - citalopram at higher doses, tricyclics
- Ondansetron at higher IV doses
- Methadone
- Hydroxychloroquine, chloroquine
This is not exhaustive. Any new prescription in a Calutide client should be checked for QT effect and interaction potential.
Symptoms of dangerous QT prolongation
- Unexplained fainting - especially with exertion
- Palpitations with dizziness
- Fluttery sensations with near-fainting
- Seizure-like episode - can be arrhythmia-induced syncope
Any of these need urgent ECG and cardiology assessment.
For most men on Calutide, QT prolongation is a theoretical concern rather than a practical problem. The specific attention is warranted when there is pre-existing cardiac disease or when the drug is combined with other QT-affecting medications. The pharmacist's check on new prescriptions catches most trouble.
⚠️ Calutide Drug Interactions You Need to Know
Calutide has moderate drug interaction potential. Bicalutamide is metabolised by CYP3A4 and can affect warfarin. A handful of interactions matter clinically.
Serious - watch closely
- Warfarin and other coumarin anticoagulants - bicalutamide can raise warfarin levels and prolong INR; check INR more frequently after starting or dose change
- Terfenadine, astemizole, cisapride - largely withdrawn but occasionally still encountered; contraindicated with bicalutamide (QT plus metabolism concerns)
- Strong CYP3A4 inhibitors (ketoconazole, itraconazole, ritonavir, clarithromycin) - can raise bicalutamide levels; caution and dose review
- Strong CYP3A4 inducers (rifampicin, phenytoin, carbamazepine, St John's Wort) - lower bicalutamide levels; may reduce efficacy
Moderate - inform prescriber
- Other QT-prolonging drugs - Section 22 details
- Other hepatotoxic drugs - additive liver load
- Grapefruit and Seville orange in large quantities - CYP3A4 inhibition
- Direct oral anticoagulants (apixaban, rivaroxaban, edoxaban, dabigatran) - less well studied but interaction unlikely to be clinically important; watch for bleeding
- Antiretrovirals and antifungals - CYP3A4 pathway shared
Usually safe together
- LHRH agonists (leuprolide, goserelin, triptorelin) - deliberately combined in CAB
- LHRH antagonists (degarelix, relugolix)
- Bone-modifying agents (denosumab, zoledronate)
- Most antihypertensives
- Statins (atorvastatin, rosuvastatin, simvastatin, pravastatin)
- Most SSRIs and SNRIs including venlafaxine and duloxetine for hot flushes
- PDE-5 inhibitors (sildenafil, tadalafil) for erectile dysfunction
- Standard vitamins - D3, calcium, B12
- Paracetamol at usual doses - preferred pain reliever
The everyday reminder
Tell every pharmacist and every doctor that you take Calutide. Over-the-counter "male vitality" or "prostate wellness" supplements are common and some contain saw palmetto, DHEA, tribulus, or other components that may interact or work against the drug's intended effect. Standard multivitamins are fine; anything marketed to men for hormonal effects should be checked with the treating team first.
⏱️ Missing a Calutide Dose - What to Do
Missing an occasional Calutide dose is common and rarely a problem. Bicalutamide has a 6-day half-life, so blood levels change slowly. What matters is the pattern of missed doses over months.
The rule
- Within 12 hours of usual time: take the missed dose now
- More than 12 hours late: skip it, take the next dose at the usual time
- Never double up to catch up
- A single missed dose has no clinical consequence
- Two or three missed days - just restart at usual dose
The long half-life buffer
Because bicalutamide takes about 6 days to halve in your bloodstream, a single missed dose barely changes drug levels. Steady state persists for many days. This is different from short-half-life drugs where a missed dose leaves you effectively untreated for a day.
Restarting after a longer gap
- Missed a week: restart at usual dose
- Missed 2-4 weeks: restart at usual dose but call the treating team at next opportunity
- Stopped for months: call before restarting - the treating team may want a review and updated PSA and blood tests before restart
- If on CAB, remember the LHRH agonist injection schedule is independent - missing the injection matters more than missing bicalutamide
When missed doses become a pattern
Isolated missed doses are fine. A pattern of missed doses over weeks or months does affect outcomes. If you find yourself missing doses regularly, this usually points to one of:
- Side effects that make the drug feel intolerable - discuss with treating team
- Cost issues - generic versions like Calutide are cheap; discuss prescription options
- Ambivalence about continuing therapy - honest conversation is better than silent dropout
- Life stress that makes daily attention difficult - simplify the reminder system
Do not stop the drug quietly because of missed doses. One dose is nothing. Sustained non-adherence is the issue, and the fix is honest conversation with the urologist or oncologist about what is going wrong, not silent stopping.
👵 Calutide in Older Men and Frailty Considerations
Older men make up the majority of Calutide clients - prostate cancer is largely a disease of older age. Some age-related adjustments to therapy are worth understanding.
What changes with age
- Baseline bone density lower - fracture risk climbs faster on CAB
- Muscle mass lower - loss on CAB affects function sooner
- Falls risk higher - fractures more likely to be consequential
- Cardiovascular comorbidity common - metabolic side effects of CAB more likely to matter
- Polypharmacy interactions rise
- Cognitive reserve lower - fatigue and mood effects add to age-related change
- Life expectancy calculation affects whether long-term therapy makes sense
Frailty over age
Age alone is a poor guide to what men can tolerate. A fit, active 78-year-old with newly diagnosed metastatic disease may do very well on CAB. A frail 68-year-old with multiple comorbidities may suffer disproportionately. Geriatric assessment tools (G8, CGA) are used in many centres to guide these decisions rather than birthdate alone.
Practical adjustments for older men
- Same 50 or 150 mg dose - no age-based reduction
- Earlier bone protection - lower threshold to add bisphosphonate or denosumab if on CAB
- Attention to falls - physiotherapy for balance training when energy drops
- Simplify medication regimens where possible
- Regular medication reviews - deprescribe unnecessary drugs to reduce interactions
- Watch for cognitive change - do not attribute all fog to age; consider depression, sleep disturbance, medication side effects
- Consider monotherapy at 150 mg where disease allows - avoids many CAB-related problems in older men
Choosing Calutide over newer agents in older men
Enzalutamide has been associated with increased falls, seizures, and cognitive changes in some older men. Apalutamide has similar concerns. Bicalutamide often tolerates better in this population despite modestly less anti-cancer effect. Where the newer drugs are affordable and available, the choice between bicalutamide-based CAB and a newer agent in an older man often comes down to a tolerability judgment - the treating team weighs individual factors.
Older men deserve the same honest conversation as anyone else about what Calutide offers and what it costs. Age alone does not exclude therapy; frailty and comorbidities weigh in the individual balance.
🤒 Sick Days and Hospital Admissions on Calutide
Calutide is usually continued through routine illness. Some specific situations warrant a pause or adjustment.
Common sick days
- Cold, flu, mild viral illness: continue Calutide if you can keep tablets down
- Stomach bug with vomiting: if you cannot keep tablets down for more than 24 hours, temporary hold is reasonable; the long half-life means brief interruption has minimal effect
- Fever without fluid loss: continue normally
- COVID-19 or similar: continue Calutide; the drug does not affect infection outcome
Hospital admissions
- Tell the admitting team you are on Calutide - it can otherwise be missed on a busy admission
- The drug is usually continued through hospital stays
- If unable to swallow, bicalutamide can be paused for a few days without significant effect
- Any new antibiotic or antifungal starting in hospital - check for QT and CYP3A4 interactions (Section 22, 23)
- Immobilisation from admission - matters if you already have low bone density; discuss
Concurrent chemotherapy
In advanced disease, chemotherapy (docetaxel or cabazitaxel) may be added to hormonal therapy. Bicalutamide is typically continued alongside chemotherapy, though the treating team may adjust based on liver function and other tolerability. This is a specialist decision.
When to hold Calutide temporarily
- Acute drug-induced liver injury (jaundice, dark urine, LFT rises significantly)
- Severe skin reaction
- Severe interstitial lung symptoms (rare but reported)
- Severe QT-related symptoms with cardiac assessment pending
- Severe fluid loss preventing oral intake for over 24-48 hours
- Under treating team guidance around major surgery or critical illness
Restarting after any pause is usually straightforward - resume at usual dose once the reason for pausing has resolved and the treating team is satisfied. Long pauses (over 2-4 weeks) warrant a treating team conversation before restart, especially if the pause was for a serious side effect.
💪 Exercise and Physical Activity on Calutide
Exercise is one of the highest-value non-drug interventions during Calutide therapy - and especially during CAB with an LHRH agonist. It counters bone loss, muscle loss, fatigue, weight gain, metabolic changes, and mood effects.
The evidence in prostate cancer
- Meta-analyses show reduced prostate cancer mortality in men who exercise regularly after diagnosis
- Randomised trials confirm reductions in ADT-related fatigue, improved quality of life
- Exercise preserves muscle mass and bone density on CAB
- Reduces cardiovascular event risk in the long term
- Improves mood, cognitive function, and sleep
- Reduces the muscle-to-fat ratio drift that CAB drives
What to aim for
ACS and ASCO exercise guidelines for cancer survivors recommend:
- 150 minutes per week of moderate aerobic exercise - walking, swimming, cycling
- OR 75 minutes per week vigorous aerobic
- Plus resistance training 2-3 times weekly - critical for muscle mass on CAB
- Flexibility and balance work - especially for older men with fall risk
- Any activity is better than none; scale up gradually
Resistance training specifics
For men on CAB, resistance training matters more than for the general population because of muscle loss risk:
- Compound movements - squats, deadlifts, presses, rows
- Weights heavy enough that the last few reps are hard
- Progressive - increase gradually over weeks and months
- Adequate protein intake (1.0-1.2 g/kg body weight daily)
- Not overtraining - fatigue on CAB means recovery matters more
- Supervised training initially if new to weights
Bone metastases and exercise
Men with bone metastases can and should exercise, but with modification. Physiotherapy-guided programmes reduce fracture risk and preserve function even in advanced disease. High-impact activities and heavy loading of affected bones are usually avoided; walking, cycling, swimming, and modified resistance training remain valuable. Discuss with the treating team - a physiotherapist familiar with cancer bone disease can build a safe programme.
Stop exercise and get review if
- New chest pain or unusual shortness of breath
- Fainting or near-fainting
- Palpitations or irregular rhythm
- Sudden severe bone pain during activity - possible fracture
- New localised weakness (leg dragging, sensory change) - urgent, possible spinal cord compression
💉 Combining Calutide With LHRH Agonists
Combining Calutide with an LHRH agonist is the classical combined androgen blockade scenario. Understanding how the two drugs work together - and where the practical rhythm lives - helps the therapy fit into daily life.
The LHRH agonist options
- Leuprolide (Lupron, Prostap) - monthly or 3-monthly injection; most widely used
- Goserelin (Zoladex) - monthly or 3-monthly subcutaneous implant
- Triptorelin (Decapeptyl) - monthly, 3-monthly, or 6-monthly injection
- Histrelin (Vantas) - yearly implant
How the combination works together
- LHRH agonist drops testosterone to castrate level over 3-4 weeks
- Bicalutamide blocks any residual androgen signalling from adrenal androgens or intracellular DHT
- Bicalutamide also covers the transient testosterone rise (flare) from LHRH agonist start
- Combined effect is close to complete androgen blockade
- Meta-analysis shows modest survival benefit versus LHRH alone
Practical rhythm of CAB
Once established, the therapy has two components on different clocks:
- Daily Calutide tablet - one every day, at the same rough time
- Monthly or three-monthly clinic visit for the LHRH injection - book ahead, do not miss
- Regular blood tests - PSA every 3-6 months, testosterone occasionally to confirm castrate levels, LFTs per Calutide monitoring, calcium and phosphate if on bone-modifying agents
- Bone density (DXA) every 1-2 years
- Yearly cardiovascular review
LHRH antagonist alternative
LHRH antagonists (degarelix injection, relugolix oral tablet) do not cause a flare because they block the pituitary receptor directly. Some men are treated with an LHRH antagonist plus bicalutamide, or with an LHRH antagonist alone. Relugolix is particularly interesting because it is oral - no injection needed - and has shown less cardiovascular event signal in the HERO trial. Where these newer options are available and affordable, some men prefer them.
When to consider stopping bicalutamide within CAB
Sometimes after the initial flare cover and stabilisation, the bicalutamide component of CAB can be stopped while the LHRH agonist continues. This is called "monotherapy with LHRH" and it works nearly as well as full CAB with fewer side effects. The decision depends on disease characteristics and treating team preference. Do not stop bicalutamide without discussion - the decision is not automatic.
☢️ Prophylactic Radiotherapy for Gynecomastia Prevention
Prophylactic breast radiotherapy is a small procedure with big impact for men starting Calutide monotherapy at 150 mg. A single low-dose fraction to each breast, given before or in the first weeks of drug therapy, reduces gynecomastia rates by roughly half.
What it involves
- Single fraction of external beam radiotherapy, typically 12-15 Gy
- Given to each breast in an outpatient session lasting 15-30 minutes
- Done before starting Calutide or within the first 2-4 weeks - earlier is more effective
- Localised to breast tissue with minimal deep dose
- No hospital admission required
The evidence
- Randomised trials show 50-60 percent reduction in gynecomastia rates
- Reduction in breast tenderness slightly less pronounced
- Better outcomes when done before starting bicalutamide
- Less effective when delayed until gynecomastia has developed
Side effects of the radiotherapy
- Mild skin redness at the treatment site
- Transient breast discomfort
- Very small theoretical long-term risk of radiation-induced breast cancer - real but tiny at these doses
- Slight change in skin pigmentation possible
Who should consider this
Men starting bicalutamide 150 mg monotherapy should have this option offered. Some centres offer it routinely; others discuss it only when the man raises breast concerns. Ask about it if you have not been offered - especially if body image or clothing considerations are important to you. Prophylactic tamoxifen 10-20 mg daily is an alternative or additional option (Section 15).
Not indicated for men on CAB at 50 mg
Gynecomastia rates on 50 mg CAB are much lower (30 percent versus 70 percent on monotherapy) and the balance of benefit versus radiotherapy risk is less clearly favourable. Prophylactic tamoxifen is more commonly used in this setting if breast issues emerge.
The radiotherapy is a one-off intervention that pays back over years of therapy. Availability varies by centre and country - some radiotherapy departments do it routinely, others need a referral request. Worth asking about at the initial urology or oncology visit if 150 mg monotherapy is planned.
📆 Duration of Calutide Therapy and Stopping
How long you take Calutide depends entirely on why you started it. Duration ranges from a few weeks (flare cover) to indefinite (long-term CAB in metastatic disease).
Typical durations by indication
| Indication | Typical duration |
|---|---|
| LHRH flare cover | 2-4 weeks |
| Locally advanced monotherapy at 150 mg | Indefinite until progression or intolerable side effects |
| CAB in metastatic disease | Indefinite until progression, then switch |
| Adjuvant after radical prostatectomy | Historically 2-5 years; less commonly used now |
| Combined with radiotherapy | Duration matches the LHRH agonist course (typically 6 months to 3 years) |
When Calutide stops working
Bicalutamide-resistant progression is signalled by:
- Rising PSA on therapy
- New symptomatic disease (bone pain, urinary symptoms)
- New metastases on imaging
- Progressive lymphadenopathy on scans
At this point the disease has become castration-resistant prostate cancer (CRPC) if testosterone is confirmed at castrate levels. Treatment moves to second-line therapies - see Section 31.
The antiandrogen withdrawal response
In roughly 20 percent of men, stopping bicalutamide when PSA is rising produces a paradoxical PSA fall for weeks to months. This "antiandrogen withdrawal response" reflects mutations that make the receptor read bicalutamide as an activator rather than a blocker. Historically this was tried before switching to second-line therapy. Modern practice often skips this and moves directly to enzalutamide, abiraterone, or another next-line drug based on trial evidence.
Stopping mechanics
Calutide does not need tapering. Stopping is a simple cessation. Blood levels drop over 2-3 weeks. Testosterone signalling recovers over the same period. Side effects fade over weeks to a few months - gynecomastia often only partly reverses, especially if it was well established. There is no rebound cancer effect from stopping in the sense that the tumour does not accelerate faster than it was going to anyway.
The decision to stop Calutide - or to continue past 5 years, or to switch - is a clinical decision made with the urologist or oncologist. It weighs PSA trajectory, symptoms, side effect burden, alternatives, and personal priorities. Do not stop on your own without discussion; missed adherence is a different issue from a planned change of therapy.
🔄 Switching From Calutide to Newer Antiandrogens
The prostate cancer treatment landscape has changed substantially since Calutide first launched in 1995. Newer androgen receptor inhibitors and other targeted agents now have specific roles - some in earlier disease, some at progression from bicalutamide-based therapy.
Second-generation androgen receptor inhibitors
| Drug | Main setting | Notes |
|---|---|---|
| Enzalutamide (Xtandi) | mHSPC, nmCRPC, mCRPC | Blocks receptor + prevents nuclear entry |
| Apalutamide (Erleada) | mHSPC, nmCRPC | Similar to enzalutamide; different rash profile |
| Darolutamide (Nubeqa) | nmCRPC, mHSPC + docetaxel | Less brain penetration, fewer cognitive effects |
| Abiraterone (Zytiga) | mHSPC, mCRPC | Blocks androgen synthesis; needs prednisone |
mHSPC = metastatic hormone-sensitive; nmCRPC = non-metastatic castration-resistant; mCRPC = metastatic castration-resistant.
When to switch from Calutide to a newer agent
- Progression on bicalutamide-based CAB - PSA rising on castrate testosterone
- New metastases on imaging
- Symptomatic progression
- High-risk newly diagnosed metastatic disease where newer agents give better first-line outcomes (ENZAMET, TITAN, ARCHES, LATITUDE, STAMPEDE)
- Non-metastatic castration-resistant disease where enzalutamide, apalutamide, and darolutamide have direct trial evidence
Trade-offs of newer agents
Advantages:
- Better anti-cancer effect in most settings
- Less gynecomastia
- Effective when bicalutamide has failed
Trade-offs:
- More expensive - often meaningful for out-of-pocket costs
- Enzalutamide and apalutamide - falls, seizure risk, cognitive change (less with darolutamide)
- Abiraterone - needs concurrent low-dose prednisone; blood pressure, potassium, LFT monitoring
- Different rash profiles (apalutamide has more)
- Availability varies by country and insurance
The switching conversation
Deciding whether to start with bicalutamide-based CAB and switch later, or start with a newer agent upfront, is a common question. In high-volume metastatic hormone-sensitive disease the evidence increasingly favours upfront enzalutamide, apalutamide, or abiraterone over classical CAB. In low-volume or asymptomatic disease, or in older frailer men, bicalutamide-based CAB remains a reasonable option. This is a treating team decision informed by individual factors.
Calutide has not become obsolete. It remains widely used across the world for specific settings and populations. But it now sits within a bigger landscape of options, and the choice of first-line therapy is more nuanced than it was 10 or 15 years ago.
🛑 Calutide Contraindications - When It Must Be Avoided
Situations where Calutide must not be started or must be stopped.
Absolute contraindications
- Known hypersensitivity to bicalutamide or excipients
- Women and children - not indicated
- Pregnancy - teratogenic; not applicable to men but relevant if bicalutamide is being considered off-label
- Severe hepatic impairment at baseline
- Prior drug-induced hepatitis from bicalutamide - no rechallenge
- Concurrent terfenadine, astemizole, or cisapride (rarely encountered but firm interaction)
Relative contraindications - use with care
- Moderate hepatic impairment
- Congenital long QT syndrome or family history of sudden cardiac death
- Concurrent strong QT-prolonging drugs where combination cannot be avoided
- Bradycardia or heart block
- Severe uncontrolled cardiovascular disease
- Localised low-risk prostate cancer at monotherapy dose (harmful per EPC data)
- Warfarin therapy without frequent INR monitoring
Reasons to stop Calutide
- Drug-induced liver injury of any severity
- Severe skin reaction
- Interstitial lung disease
- Symptomatic QT prolongation
- Disease progression despite therapy - switch to next-line agent
- Intolerable side effects despite management
- Completion of planned course (e.g. flare cover)
- Change to newer androgen receptor inhibitor as part of trial evidence-based upgrade
Stopping mechanics
Calutide does not need tapering. The long half-life means the drug clears over 2-3 weeks after the last dose. Testosterone signalling recovers over the same period. Side effects fade over weeks to a few months. There is no rebound cancer risk from stopping - the concern is losing ongoing anti-cancer effect, not any drug withdrawal danger. Where continued androgen blockade is needed, the switch to another agent is planned before stopping bicalutamide rather than stopping first.
Stopping Calutide should be a proper clinical decision, not a silent choice. If side effects are pushing you toward stopping, raise this with the treating team well before you actually stop - the options usually include switching agents, adjusting doses, or adding symptom-relief drugs rather than complete withdrawal.
📦 Storage, Travel, Surgery and Yearly Calutide Review
Final practical topics for long-term Calutide therapy.
Storage
- Room temperature under 25 C, in original packaging
- Not in the bathroom - humidity degrades tablets
- Not in a hot car
- Out of reach of children and pets - bicalutamide in a small child would be dangerous
- Do not use past expiry date
- Return unused tablets to a pharmacy - do not flush or bin
Travel
- Pack Calutide in hand luggage, not checked baggage
- Take 30 percent more than you strictly need for the trip
- Original packaging with pharmacy label for customs
- Bring a letter from the treating team if travelling with a long supply
- Time zone changes - shift the dose gradually over a few days if the change is over 4 hours
- Coordinate LHRH injection schedule with travel - do not miss injections
- Travel insurance - declare prostate cancer and current therapy
Surgery on Calutide
- Tell every surgeon and anaesthetist about Calutide
- Major surgery - Calutide usually continued, though the treating team may pause briefly around big procedures
- Minor surgery and dental work - continue normally
- If you take warfarin, INR management around surgery needs careful coordination given the bicalutamide interaction
- Anaesthetists should know about QT concerns if you have any cardiac history
Yearly review checklist
A yearly Calutide review typically covers:
- PSA trend - the main disease marker
- Symptom review - hot flushes, gynecomastia, sexual function, fatigue, mood
- Adherence check - honest conversation about missed doses
- Full LFTs
- Full blood count
- Kidney function, calcium, phosphate
- Lipids, HbA1c or fasting glucose
- BP and cardiovascular risk assessment
- Bone density (DXA) every 1-2 years if on CAB
- Testosterone if uncertain about castrate status
- Imaging as clinically indicated
- Any new medications and interaction check
- Whether to continue, switch, or extend therapy
- Life issues - work, exercise, mental health, relationships
A closing thought
Calutide is an old, well-understood drug used across many clinical settings in prostate cancer. It is one of several options in a landscape that has expanded with enzalutamide, apalutamide, darolutamide, abiraterone, and other targeted agents. For many men - especially those where cost, tolerability, or specific clinical context matter - bicalutamide remains a solid, familiar, and effective choice. Approaching it as a partnership over years rather than a passive prescription, taking side effects seriously enough to raise them with the treating team, and staying active and engaged with general health, are the elements that make long-term therapy work.
Calutide — Frequently Asked Questions
-
What is Calutide (Bicalutamide)?
Calutide is a non-steroidal anti-androgen medication used primarily in the treatment of prostate cancer. It works by blocking the action of androgens, which can promote the growth of cancer cells in the prostate. -
How does Calutide (Bicalutamide) work?
Calutide binds to androgen receptors, preventing androgens such as testosterone from stimulating prostate cancer cells. This helps to slow down or stop the growth of these cells. -
Who should take Calutide (Bicalutamide)?
Calutide is prescribed for men with advanced prostate cancer, often in combination with other treatments like LHRH analogs. -
How is Calutide (Bicalutamide) administered?
Calutide is taken orally in the form of a tablet, usually once daily. It should be taken at the same time each day. -
Can I take Calutide with food?
Yes, Calutide can be taken with or without food. It should be swallowed whole with a glass of water. -
What should I do if I miss a dose?
If you miss a dose, take it as soon as you remember unless it is almost time for your next dose. Do not double the dose to make up for the missed one. -
What are the common side effects of Calutide?
Common side effects include hot flashes, nausea, breast tenderness, and fatigue. These side effects are generally mild and manageable.
See all Calutide questions (32)
📚 Drug Description Sources:
The information in this Calutide (bicalutamide) guide is compiled from authoritative pharmaceutical, medical, and regulatory sources covering prostate cancer hormonal therapy, non-steroidal antiandrogen pharmacology, and combined androgen blockade. Content spans three decades of bicalutamide clinical experience from its 1995 European approval by Zeneca (now AstraZeneca) as Casodex through modern positioning within urology and medical oncology guidelines. Calutide is Cipla's generic bicalutamide formulation.
🏛️ Regulatory and government agencies
- FDA (US Food and Drug Administration) - bicalutamide US approval 1995 (Zeneca, Casodex) for advanced prostate cancer with LHRH analogue; generic available 2009; current DailyMed prescribing information
- EMA (European Medicines Agency) - bicalutamide European authorisation framework; 50 mg for combined therapy and 150 mg for locally advanced monotherapy
- MHRA (UK Medicines and Healthcare products Regulatory Agency) - Casodex summary of product characteristics
- CDSCO (India) - Calutide approval and manufacturing standards (Cipla)
- Health Canada - Casodex product monograph
- TGA (Australian Therapeutic Goods Administration) - bicalutamide product information
- WHO Model List of Essential Medicines - bicalutamide listed under antineoplastic and immunosuppressive medicines
📚 Professional societies and clinical guidelines
- NCCN Clinical Practice Guidelines in Oncology: Prostate Cancer - bicalutamide positioning in advanced disease and combined androgen blockade
- EAU Guidelines on Prostate Cancer - non-steroidal antiandrogen use in metastatic and locally advanced disease
- ESMO Clinical Practice Guidelines on Prostate Cancer - hormonal therapy pathways
- ASCO Guideline on Hormonal Therapy for Prostate Cancer
- AUA Guidelines on Advanced Prostate Cancer - US urology positioning
- NICE NG131 Prostate Cancer Diagnosis and Management - UK practice recommendations
- APCCC (Advanced Prostate Cancer Consensus Conference) - biennial expert consensus on advanced disease
🔬 Landmark clinical research
- Early Prostate Cancer (EPC) Trialists' Programme (Lancet 2005, 2008, 2010) - 8 113 men across three trials studying bicalutamide 150 mg as adjuvant or immediate hormonal therapy in localised or locally advanced disease
- Prostate Cancer Trialists' Collaborative Group Meta-analysis (Lancet 2000) - combined androgen blockade versus LHRH agonist alone; modest survival benefit at cost of side effects
- Iversen et al. (BJU International 2004, JCO 2006) - bicalutamide 150 mg monotherapy in locally advanced prostate cancer
- Kunath et al. Cochrane Review (2014) - non-steroidal antiandrogens for advanced prostate cancer; comprehensive meta-analysis
- Wirth et al. (European Urology 2007) - bicalutamide as adjuvant after radical prostatectomy
- STAMPEDE Trial - contemporary trials of intensified therapy that inform bicalutamide positioning
- Reference trials on newer antiandrogens (enzalutamide, apalutamide, darolutamide) that define where bicalutamide still fits
📖 Medical references and textbooks
- Campbell-Walsh-Wein Urology - the definitive urology reference; prostate cancer chapters
- DeVita, Hellman and Rosenberg's Cancer Principles and Practice of Oncology - the definitive oncology reference
- Abeloff's Clinical Oncology - prostate cancer chapter
- Goodman and Gilman Pharmacological Basis of Therapeutics - antiandrogen pharmacology
- Harrison's Principles of Internal Medicine - genitourinary cancers chapter
- UpToDate - bicalutamide clinical monographs
- Lexicomp and Micromedex - drug interactions, dosing, and monitoring tables
Note: This information is educational and does not replace consultation with a urologist or oncologist. Individual treatment decisions depend on cancer stage, PSA trajectory, comorbidities, and personal preferences. Always follow the treating team's instructions and report new symptoms promptly.
🩺 Medical Expert Review:
Content based on the published research and clinical practice of prostate cancer authorities with particular expertise in antiandrogen pharmacology, combined androgen blockade, and hormonal therapy trials. The following experts represent authoritative research and clinical practice perspectives on bicalutamide use within contemporary prostate cancer management.
Prof. Peter Iversen, MD, DMSc
Emeritus Professor of Urology, University of Copenhagen; formerly Chief of Urology, Rigshospitalet — Copenhagen, Denmark
Prof. Iversen served as principal investigator on the Early Prostate Cancer Programme, the largest bicalutamide trial series ever conducted, enrolling 8 113 men across three linked trials. He was also principal investigator on the bicalutamide 150 mg monotherapy trial in locally advanced disease. His scholarship on non-steroidal antiandrogen positioning and dose selection has directly informed European clinical practice and EAU guidelines.
Prof. Manfred P. Wirth, MD
Emeritus Professor and former Chairman, Department of Urology, University Hospital Carl Gustav Carus, Technical University Dresden — Dresden, Germany
Prof. Wirth co-led the Early Prostate Cancer trials and served as principal investigator on bicalutamide as adjuvant therapy after radical prostatectomy. He served as past President of the European Association of Urology (EAU). His scholarship on adjuvant hormonal therapy positioning has substantially informed European urology practice.
Prof. William K. Oh, MD
Chief of Hematology and Medical Oncology, Mount Sinai Health System; Professor of Medicine and Urology, Icahn School of Medicine at Mount Sinai — New York, USA
Prof. Oh has published more than 300 peer-reviewed papers on prostate cancer therapy and serves on multiple NCCN Prostate Cancer Guidelines panels. His scholarship on hormonal therapy sequencing and antiandrogen positioning across castration-sensitive and resistant disease has directly informed US clinical practice.
Prof. Bertrand Tombal, MD, PhD
Chairman, Division of Urology, Cliniques Universitaires Saint-Luc; Professor of Urology, Universite Catholique de Louvain — Brussels, Belgium
Prof. Tombal served as Chair of the EAU Prostate Cancer Guidelines Panel and was a founding member of the Advanced Prostate Cancer Consensus Conference (APCCC). He led numerous landmark antiandrogen trials including PROSPER and ARAMIS. His scholarship on where bicalutamide still fits within a treatment landscape now including enzalutamide, apalutamide, and darolutamide substantially shapes European practice.
Prof. Nicholas D. James, MBBS, PhD, FRCP
Professor of Prostate and Bladder Cancer Research, The Institute of Cancer Research & Royal Marsden Hospital — London, UK
Prof. James serves as Chief Investigator on the STAMPEDE trial, the largest randomised prostate cancer trial ever run, enrolling over 10 000 men across multiple arms. His scholarship on hormonal therapy intensification versus older combined androgen blockade has directly informed contemporary NICE and international guidelines on when bicalutamide-based therapy remains appropriate versus when newer agents should be used.
Disclosure: Expert names and credentials are cited for educational reference. This content is not endorsed by named experts. Content prepared by RXshop editorial team based on published literature and clinical guidelines.
More Cancer Medications