Buy Eltroxin (Levothyroxine 50mcg) Online - Foundational Thyroid Hormone Replacement for Hypothyroidism Hashimoto Post Thyroidectomy Treatment

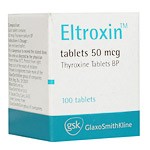
Eltroxin (Levothyroxine 50mcg) represents the foundational thyroid hormone replacement therapy — bioidentical synthetic thyroxine (T4) — providing physiological replacement for hypothyroidism from any cause. Originally developed as Eltroxin by Glaxo (now GlaxoSmithKline) and established as first-line thyroid replacement across UK, India, Canada, Australia, and most global markets, levothyroxine also exists as multiple US brand equivalents including Synthroid (AbbVie — dominant US brand), Levoxyl, Levothroid, Unithroid, and Tirosint. As opposite indication sibling to Carbirose (carbimazole antithyroid) on rxshop.md thyroid category — while Carbirose blocks excessive thyroid hormone production in hyperthyroidism, Eltroxin provides physiological replacement for insufficient thyroid hormone production in hypothyroidism. Available on rxshop.md from two manufacturers: Combitic Global Caplet Pvt India and GSK Pharma India (the Indian subsidiary of GlaxoSmithKline — original Eltroxin brand holder) providing patient choice with equivalent therapeutic outcomes.
Levothyroxine works as bioidentical synthetic thyroxine (T4) — chemically identical to endogenous thyroid hormone produced by the thyroid gland. As a prohormone, levothyroxine is peripherally converted to active triiodothyronine (T3) by 5'-deiodinase enzymes in target tissues throughout the body. This physiological conversion provides sustained thyroid hormone activity supporting normal metabolic rate, cardiovascular function, cognitive processes, body temperature regulation, and growth and development. The long ~7-day half-life allows convenient once-daily dosing while providing steady thyroid hormone levels. Steady state requires 4-6 weeks — meaning clinical assessment of dose adequacy requires patience and TSH monitoring at 6-8 week intervals during titration.
Eltroxin serves comprehensive thyroid replacement needs. Primary uses include primary hypothyroidism (thyroid gland failure — most common); Hashimoto's thyroiditis (autoimmune hypothyroidism); post-thyroidectomy replacement; post-radioactive iodine (RAI) treatment (including after Graves' disease treatment); congenital hypothyroidism (critical for infant brain development); central hypothyroidism; and thyroid cancer TSH suppression at higher doses.
Eltroxin dosed 1.6 mcg/kg/day average (typically 100-150 mcg adults). Elderly/CAD start low 25-50 mcg. Take on empty stomach 30-60 min before breakfast. Avoid coffee, calcium, iron within 4 hours. Monitor TSH q6-8 weeks. Sibling in thyroid category: Carbirose (opposite antithyroid indication).
Free prescription
Discrete packaging
Have questions?
Quality Assurance


- Hashimoto Thyroiditis: Chronic autoimmune destruction of thyroid gland producing progressive hypothyroidism requiring lifelong replacement;
- Post Thyroidectomy Replacement: Complete replacement therapy after surgical thyroid removal for cancer or intractable hyperthyroidism;
- Post Radioactive Iodine Ablation: Replacement after RAI treatment for Graves disease or thyroid cancer when patient becomes hypothyroid;
- Congenital Hypothyroidism: Newborn screening positive infants requiring immediate replacement for critical brain development in first year of life;
- Subclinical Hypothyroidism: Elevated TSH with normal T4 in selected patients with symptoms cardiovascular risk factors or elevated TPO antibodies;
- Central Hypothyroidism: Pituitary (secondary) or hypothalamic (tertiary) hypothyroidism requiring full replacement therapy;
- Myxedema Coma Emergency: Life-threatening severe hypothyroidism requiring emergency high-dose replacement in hospital setting;
- Hypothyroidism in Pregnancy: Critical for fetal neurological development - requirements increase 20-30% during pregnancy monitored monthly;
- Thyroid Cancer TSH Suppression: Higher doses to suppress TSH below 0.1 mIU/L for differentiated thyroid cancer to prevent recurrence;
- Prevention of Recurrent Nodular Goiter: Prevention of goiter recurrence after surgical treatment or in selected iodine-deficient regions;
- Diffuse Euthyroid Goiter: Selected cases of enlarged thyroid with normal function may benefit from TSH suppression therapy;
- Post Graves Disease Treatment Hypothyroidism: Replacement after RAI or thyroidectomy for Graves disease when patient becomes hypothyroid;
- Autoimmune Thyroiditis: Various autoimmune thyroid conditions producing hypothyroidism requiring replacement therapy;
- TSH Suppression Test and Therapy: Diagnostic and therapeutic use to suppress TSH for various clinical scenarios and testing protocols;
- Elderly Hypothyroidism: Age-related thyroid dysfunction requiring careful low-dose initiation with cardiovascular considerations;
- Pediatric Hypothyroidism: Congenital and acquired childhood hypothyroidism requiring pediatric endocrinology supervision and weight-based dosing;
- Iodine Deficiency Hypothyroidism: Hypothyroidism from insufficient dietary iodine intake in select geographic regions;
- Bioidentical Thyroid Hormone Therapy: Bioidentical synthetic T4 hormone matching endogenous thyroxine for physiological replacement;
- Generic Levothyroxine Therapy: Bioequivalent generic alternative to brand Eltroxin and Synthroid at accessible cost for lifelong therapy.
- Improves Symptoms of Hypothyroidism: Comprehensive improvement of fatigue cold intolerance dry skin constipation weight gain and other hypothyroid symptoms;
- Supports Heart Health: Normalizes cardiovascular function reducing hypothyroid-related bradycardia diastolic hypertension and lipid abnormalities;
- Enhances Energy Levels: Restoration of normal thyroid function eliminates profound fatigue characteristic of untreated hypothyroidism improving daily activity capacity;
- Regulates Body Temperature: Restores normal thermoregulation eliminating cold intolerance and low body temperature symptoms of hypothyroidism;
- Promotes Weight Normalization: Restored metabolic rate helps normalize weight though weight loss from levothyroxine alone typically modest;
- Improves Cognitive Functions: Reverses hypothyroid-related brain fog memory problems concentration difficulty and mental slowing;
- Stabilizes Mood: Reverses hypothyroid-related depression low mood and emotional flattening restoring normal affect and psychological wellbeing;
- Supports Pregnancy and Fetal Development: Critical for maternal and fetal thyroid function during pregnancy - inadequate treatment causes fetal neurological damage;
- Minimal Side Effects: Bioidentical hormone with excellent tolerability when appropriately dosed - side effects typically only from over- or under-dosing;
- Better Once Daily Dosing Convenience: Long half-life (~7 days) allows convenient once daily dosing improving compliance for lifelong therapy;
- Better Lifelong Therapy Compatibility: Excellent safety profile enabling lifelong replacement therapy for chronic hypothyroidism without accumulating toxicity;
- Better Bioidentical Hormone: Chemically identical to endogenous thyroxine providing physiological replacement without foreign substance concerns;
- Better Peripheral T3 Conversion: Body regulates peripheral T4-to-T3 conversion providing tissue-specific active hormone as needed;
- Better Post Thyroidectomy Replacement: Essential lifelong replacement after thyroid removal for cancer or intractable hyperthyroidism preserving normal function;
- Better Cancer Recurrence Prevention: TSH suppression therapy at higher doses reduces differentiated thyroid cancer recurrence and improves outcomes;
- Better Congenital Hypothyroidism Outcomes: Immediate replacement in newborn positive screening prevents intellectual disability enabling normal neurological development;
- Better Cardiovascular Protection: Adequate replacement prevents hypothyroid-related cardiovascular complications including atherosclerosis progression;
- Better Two Manufacturer Options: Combitic Global Caplet and GSK Pharma India provide patient choice with equivalent therapeutic outcomes and WHO-GMP quality;
- Better Quality of Life: Effective hypothyroidism management dramatically improves quality of life restoring energy cognition mood and cardiovascular function.
Generic Eltroxin (Levothyroxine 50 mcg) Medication guide:
Eltroxin (Levothyroxine 50mcg) represents the foundational thyroid hormone replacement therapy - bioidentical synthetic thyroxine (T4) - providing physiological replacement for hypothyroidism from any cause. Originally developed as Eltroxin by Glaxo (now GlaxoSmithKline) and established as first-line thyroid replacement across UK, India, Canada, Australia, and most global markets, levothyroxine also exists as multiple US brand equivalents including Synthroid (AbbVie - dominant US brand), Levoxyl, Levothroid, Unithroid, and Tirosint. As opposite indication sibling to Carbirose (carbimazole antithyroid) on rxshop.md thyroid category - while Carbirose blocks excessive thyroid hormone production in hyperthyroidism, Eltroxin provides physiological replacement for insufficient thyroid hormone production in hypothyroidism. Available on rxshop.md from two manufacturers: Combitic Global Caplet Pvt India and GSK Pharma India (the Indian subsidiary of GlaxoSmithKline - original Eltroxin brand holder). This comprehensive medication guide covers every aspect of Eltroxin therapy from hypothyroidism pathophysiology through mechanism as bioidentical T4 prohormone, critical absorption considerations, TSH monitoring framework, dosing across special populations including pregnancy and elderly, comparison with Carbirose opposite indication, cardiovascular considerations, and lifelong therapy management.
💊 Introduction to Eltroxin
Eltroxin is a prescription oral medication containing levothyroxine sodium as its active ingredient in tablet form. Levothyroxine is bioidentical synthetic thyroxine (T4) — chemically identical to the endogenous thyroid hormone naturally produced by the human thyroid gland. Levothyroxine was originally developed by Glaxo Pharmaceuticals (now GlaxoSmithKline) and established as Eltroxin — the standard thyroid hormone replacement therapy across the United Kingdom, India, Canada, Australia, and most global markets. In the United States, levothyroxine is available under multiple brand names including Synthroid (AbbVie — dominant US brand), Levoxyl (Pfizer), Levothroid (Forest), Unithroid (Amneal), and Tirosint (IBSA gel capsule formulation).
The Eltroxin brand available on rxshop.md is manufactured by two trusted manufacturers: Combitic Global Caplet Pvt India (Indian generic manufacturer) and GSK Pharma India — the Indian subsidiary of GlaxoSmithKline maintaining the original Eltroxin brand quality standards and formulation. Both manufacturers produce 50 mcg tablet strength representing a common maintenance dose. Worldwide, levothyroxine is available in multiple strengths from 12.5 mcg (starting dose for elderly) up to 200 mcg (higher replacement doses) enabling precise individualized dosing based on patient weight age comorbidities and TSH response.
Eltroxin occupies a unique clinical position as opposite indication sibling to Carbirose (carbimazole) on rxshop.md within the thyroid category. While Carbirose blocks excessive thyroid hormone production for hyperthyroidism (Graves' disease, toxic goiter), Eltroxin provides physiological replacement for insufficient thyroid hormone production in hypothyroidism (Hashimoto's thyroiditis, post-thyroidectomy, post-RAI ablation, congenital hypothyroidism). This pairing represents the two fundamental pharmacological approaches to thyroid disease management — hormone blocker versus hormone replacement.
🧬 Understanding Hypothyroidism
The Thyroid Gland and Hormone Synthesis
Understanding thyroid gland physiology is essential for appreciating how levothyroxine replacement therapy addresses hypothyroidism. The thyroid gland — located in the anterior neck below the larynx — produces two primary thyroid hormones:
Thyroid hormones and their roles:
- Thyroxine (T4): Prohormone produced in largest quantity, converted peripherally to active T3
- Triiodothyronine (T3): Active hormone binding thyroid hormone receptors in target tissues
- Reverse T3 (rT3): Metabolic pathway during stress or illness - inactive
- Regulation: Hypothalamus-pituitary-thyroid axis (HPA) through TRH-TSH-thyroid hormone feedback
- Iodine dependency: Both T3 and T4 require dietary iodine for synthesis
- Global distribution: Thyroid hormones affect virtually every cell in body
What Is Hypothyroidism
Hypothyroidism is a common endocrine disorder characterized by insufficient thyroid hormone production or action resulting in slowed metabolism and multiple physiological consequences. Key facts:
- Affects approximately 5 percent of adult population globally
- More common in women - approximately 5-8 times higher than men
- Age-related increase - prevalence increases with age
- Primary causes: Hashimoto's thyroiditis (autoimmune), post-thyroidectomy, post-RAI, congenital, iodine deficiency
- Secondary causes: Pituitary tumors, pituitary damage
- Tertiary causes: Hypothalamic disease
- Subclinical hypothyroidism: Elevated TSH with normal T4 - very common
- Untreated consequences: Cardiovascular disease, myxedema coma, developmental problems in infants
Hypothyroidism Symptoms
Common hypothyroid symptoms:
- Constant fatigue: Profound tiredness despite adequate sleep
- Cold intolerance: Feeling cold when others are comfortable
- Weight gain: Unexplained weight increase or difficulty losing weight
- Dry skin and hair: Coarse dry skin, brittle hair
- Hair loss: Diffuse thinning, outer eyebrow loss
- Constipation: Slowed intestinal motility
- Depression and mood changes: Low mood, brain fog
- Cognitive slowing: Memory problems, concentration difficulty
- Muscle weakness and aches: Myopathy
- Menstrual irregularities: Heavy periods, fertility issues
- Bradycardia: Slow heart rate
- Diastolic hypertension
- Elevated cholesterol: Lipid abnormalities
- Goiter: Enlarged thyroid gland in some cases
🧪 Chemistry and Mechanism
Levothyroxine sodium has the chemical formula C15H10I4NNaO4 with molecular weight approximately 798.9 g/mol. Levothyroxine is the sodium salt of the levorotatory isomer of thyroxine — synthetic form chemically identical to endogenous thyroxine (T4) naturally produced by the thyroid gland.
Mechanism as Bioidentical T4 Prohormone
Levothyroxine mechanism at cellular level:
- Absorption: Absorbed primarily in jejunum and ileum with variable bioavailability (60-80 percent)
- Circulation: Bound to thyroxine-binding globulin (TBG) and other proteins (99.97 percent bound)
- Cellular uptake: Free T4 enters target cells through specific transporters
- Peripheral conversion: 5-prime deiodinase enzymes convert T4 to active T3 in tissues
- Nuclear receptor binding: T3 binds thyroid hormone receptors (TR alpha, TR beta) in cell nuclei
- Gene transcription: Receptor complexes modulate transcription of hundreds of thyroid-responsive genes
- Physiological effects: Increased metabolic rate, protein synthesis, gene expression, growth
- Homeostatic feedback: Elevated T4/T3 suppresses hypothalamic TRH and pituitary TSH
Physiological Effects of Adequate T4 Replacement
- Metabolic rate normalization: Restores basal metabolic rate
- Cardiovascular function: Normalizes heart rate, cardiac output, blood pressure
- Body temperature: Restores thermoregulation
- Central nervous system: Restores cognitive function, mood, alertness
- Growth and development: Critical for infant/child development
- Reproductive function: Restores menstrual cycles, fertility
- Gastrointestinal motility: Normalizes intestinal transit
- Bone metabolism: Maintains normal bone remodeling
- Lipid metabolism: Normalizes cholesterol and lipoproteins
Pharmacokinetic Profile
| Parameter | Value | Clinical Significance |
|---|---|---|
| Oral bioavailability | 60-80 percent (variable) | Affected by food and medications |
| Time to peak | 2-4 hours | Peak plasma concentration |
| Half-life | Approximately 7 days | Allows once daily dosing |
| Steady state | 4-6 weeks | TSH monitoring at 6-8 weeks |
| Protein binding | 99.97 percent (mostly TBG) | Very highly protein bound |
| Metabolism | Peripheral deiodination to T3 | Body regulates T3 production |
| Elimination | Biliary excretion, enterohepatic circulation | Slow elimination |
| Food effect | Substantially reduces absorption | MUST take on empty stomach |
| Onset of clinical improvement | 2-4 weeks partial, 6-8 weeks substantial | Gradual response over weeks |
⚖️ Eltroxin vs Carbirose Sibling Comparison
| Property | Eltroxin (Levothyroxine) | Carbirose (Carbimazole) |
|---|---|---|
| Indication | HYPOthyroidism | HYPERthyroidism |
| Function | Hormone REPLACEMENT | Hormone BLOCKER |
| Effect on thyroid hormones | Increases T3/T4 | Decreases T3/T4 |
| Chemistry | Bioidentical synthetic T4 | Thionamide prodrug |
| Mechanism | Physiological replacement | Thyroid peroxidase inhibition |
| Strength | 50 mcg | 5 mg |
| Duration of therapy | Usually lifelong | 12-18 months typical |
| Uses in Graves' disease | AFTER treatment when hypothyroid | Active hyperthyroidism |
| Post-thyroidectomy use | Yes - essential replacement | Not typically after surgery |
| Manufacturer | Combitic Global + GSK Pharma | Prevego |
🎯 Approved Indications
Primary FDA/Global Approved Indications
- Primary hypothyroidism - thyroid gland failure from any cause
- Secondary/tertiary hypothyroidism - pituitary or hypothalamic causes
- Congenital hypothyroidism - newborn screening positive
- Prevention of nodular goiter recurrence after surgical treatment
- Thyroid cancer TSH suppression - after differentiated thyroid cancer treatment
- Multinodular goiter management in selected cases
Broader Clinical Uses
- Hashimoto's thyroiditis - autoimmune chronic thyroiditis (most common cause)
- Post-thyroidectomy replacement - after surgical thyroid removal
- Post-RAI ablation - after radioactive iodine treatment
- Central hypothyroidism - pituitary or hypothalamic disease
- Subclinical hypothyroidism - elevated TSH with normal T4 in selected patients
- Myxedema coma - life-threatening severe hypothyroidism (emergency)
- Hypothyroidism in pregnancy - critical for fetal development
- Post-Graves disease treatment - when patient becomes hypothyroid
- Autoimmune thyroiditis - various forms of thyroid autoimmunity
- Iodine deficiency hypothyroidism - selected geographic regions
- Elderly hypothyroidism - age-related thyroid dysfunction
- Pediatric hypothyroidism - childhood thyroid disorders
Ideal Patient Selection
Eltroxin appropriate for:
- Patients with confirmed hypothyroidism (elevated TSH, low T4)
- Symptomatic hypothyroid patients (fatigue, cold intolerance, weight gain)
- Post-thyroidectomy patients requiring replacement
- Post-RAI ablation patients who become hypothyroid
- Congenital hypothyroidism screening positive infants
- Pregnant women with hypothyroidism (critical for fetus)
- Selected subclinical hypothyroidism patients
- Thyroid cancer patients requiring TSH suppression
- Patients able to comply with morning empty-stomach dosing
- Patients accepting lifelong therapy
- Patients able to attend TSH monitoring
🚫 Contraindications and Precautions
Contraindications
- Untreated thyrotoxicosis - would worsen hyperthyroidism
- Untreated adrenal insufficiency - risk of adrenal crisis - treat cortisol first
- Acute myocardial infarction - initiate cautiously after acute event
- Hypersensitivity to levothyroxine or any excipient
- Not for weight loss - dangerous when used inappropriately in euthyroid patients
Precautions - Cardiovascular Caution
Cardiovascular considerations:
- Elderly patients: Start LOW 25-50 mcg, titrate slowly to prevent cardiac stress
- Coronary artery disease: Excess thyroid can trigger angina, MI, arrhythmia
- Atrial fibrillation: May be precipitated by overtreatment
- Long-standing untreated hypothyroidism: Start low, cardiac adjustment needed
- Osteoporosis: Overtreatment increases bone loss in postmenopausal women
- Diabetes: Thyroid replacement may affect glucose control
Additional precautions:
- Diabetes insipidus: Consider hypothyroidism as differential
- Adrenal insufficiency: Replace glucocorticoids BEFORE thyroid hormone
- Pregnancy: Requirements increase 20-30% - monitor monthly
- Anticoagulation: Thyroid replacement affects warfarin sensitivity
- Diabetes medications: May need adjustment as thyroid normalizes
💉 Dosage and Administration
Standard Adult Dosing
Standard adult dosing:
- Weight-based: Approximately 1.6 mcg/kg/day for full replacement
- Typical adult dose: 100-150 mcg once daily
- Range: 50-200 mcg based on individual requirements
- Once daily dosing: Long half-life supports single daily dose
- Timing: Empty stomach 30-60 minutes before breakfast
Weight-Based Dosing Guide
| Weight | Full Replacement Dose (1.6 mcg/kg) | Typical Starting Range |
|---|---|---|
| 50 kg (110 lb) | 80 mcg daily | 50-100 mcg |
| 60 kg (132 lb) | 96 mcg daily | 75-100 mcg |
| 70 kg (154 lb) | 112 mcg daily | 100-125 mcg |
| 80 kg (176 lb) | 128 mcg daily | 100-150 mcg |
| 90 kg (198 lb) | 144 mcg daily | 125-175 mcg |
Elderly and Cardiovascular Disease Approach
Elderly/CAD titration protocol:
- Starting dose: 25-50 mcg once daily
- Titration: Increase by 12.5-25 mcg every 6-8 weeks
- Target: Achieve euthyroid state slowly to prevent cardiac stress
- Monitor for: Chest pain, palpitations, arrhythmias, worsening heart failure
- Consider cardiac evaluation: Before starting in patients with significant CAD
- Beta-blocker adjustment: May need to reduce as thyroid normalizes
Pregnancy Dosing
Critical pregnancy adjustments:
- Requirements increase 20-30 percent during pregnancy
- Increase dose immediately upon pregnancy confirmation (before pregnancy TSH check)
- Typical increase: Add 2 additional tablets per week initially
- Monitor TSH monthly throughout pregnancy
- Target TSH: First trimester 0.1-2.5, second trimester 0.2-3.0, third trimester 0.3-3.5
- Return to pre-pregnancy dose after delivery
- Critical for fetal brain development particularly first trimester
Cancer TSH Suppression Dosing
- Higher than replacement doses - typically 2.0-2.4 mcg/kg/day
- Target TSH: Below 0.1 mIU/L for high-risk cancer
- Intermediate suppression: 0.1-0.5 mIU/L for intermediate-risk
- Standard replacement: After long-term remission - normal TSH
- Requires close monitoring: Balance suppression vs cardiovascular/bone effects
🍴 Critical Absorption Considerations
Levothyroxine absorption critically affected by food and medications:
Optimal administration:
- Take on EMPTY STOMACH with water only
- 30-60 minutes before breakfast is optimal timing
- Alternative: Bedtime - at least 3 hours after last meal
- Consistency: Same time daily for stable levels
- Water only: No coffee, tea, juice with the dose
- Do not chew or crush - swallow whole with water
Foods and Medications Affecting Absorption
Wait at least 4 hours before/after:
- Coffee and caffeine: Reduces absorption 30-40 percent
- Calcium supplements: Binds levothyroxine reducing absorption
- Iron supplements: Forms complexes reducing absorption
- Magnesium supplements: Interferes with absorption
- Aluminum antacids: Reduces absorption
- Sucralfate: Binds levothyroxine
- Cholestyramine and other bile acid sequestrants: Substantial binding
- Proton pump inhibitors: Reduces absorption
- Milk and dairy: Calcium content reduces absorption
- Soy protein and fiber: May reduce absorption
- Estrogen therapy: Increases TBG, may increase requirements
📊 TSH Monitoring Framework
TSH monitoring schedule:
- Initial dose: Check TSH at 6-8 weeks after starting
- Dose changes: Check TSH at 6-8 weeks after each adjustment
- Once stable: Annual TSH monitoring
- Pregnancy: Monthly TSH monitoring
- Elderly: Every 6 months minimum
- Cancer suppression: Every 3-6 months
- Symptom change: Repeat TSH sooner if symptoms worsen
Target TSH Ranges
| Population/Indication | Target TSH (mIU/L) |
|---|---|
| Standard adult replacement | 0.5-4.0 |
| Elderly patients | 1.0-5.0 (higher acceptable) |
| Pregnancy first trimester | 0.1-2.5 |
| Pregnancy second trimester | 0.2-3.0 |
| Pregnancy third trimester | 0.3-3.5 |
| Thyroid cancer high-risk suppression | Below 0.1 |
| Thyroid cancer intermediate-risk | 0.1-0.5 |
| Pediatric replacement | 0.5-4.0 |
⚠️ Side Effects - Over vs Undertreatment
Signs of Overtreatment (Iatrogenic Hyperthyroidism)
Overtreatment symptoms (dose too high):
- Palpitations, tachycardia
- Weight loss despite normal appetite
- Heat intolerance, excessive sweating
- Anxiety, nervousness, irritability
- Insomnia, sleep disturbance
- Tremor
- Diarrhea, increased bowel movements
- Muscle weakness
- Atrial fibrillation (elderly particularly)
- Bone loss (postmenopausal women)
- Headache
Signs of Undertreatment (Persistent Hypothyroidism)
Undertreatment symptoms (dose too low):
- Persistent fatigue
- Cold intolerance continues
- Weight gain difficulty losing
- Constipation
- Dry skin and hair
- Continued depression, low mood
- Cognitive slowing continues
- Muscle aches
- Menstrual irregularities
- Elevated cholesterol
🔄 Drug Interactions
| Drug/Substance | Interaction |
|---|---|
| Warfarin | Increased anticoagulant effect - monitor INR |
| Diabetes medications (insulin, sulfonylureas) | Thyroid normalization may reduce diabetes medication needs |
| Calcium supplements | Reduces absorption - separate by 4 hours |
| Iron supplements | Reduces absorption - separate by 4 hours |
| Aluminum antacids | Reduces absorption - separate by 4 hours |
| Cholestyramine, colestipol | Substantial binding - separate by 4-6 hours |
| Sucralfate | Reduces absorption - separate |
| PPIs (omeprazole) | Long-term use may reduce absorption |
| Estrogen therapy | Increases TBG - may need dose increase |
| Androgens | Decreases TBG - may need dose decrease |
| Amiodarone | Complex thyroid effects - monitor closely |
| Lithium | Can cause hypothyroidism - may increase requirements |
| Coffee and caffeine | Reduces absorption 30-40% - wait 1 hour after dose |
🛡️ Special Populations
- Pregnancy
- Critical for fetal development. Requirements increase 20-30 percent. Increase dose immediately upon pregnancy confirmation. Monitor TSH monthly. Target TSH varies by trimester (lower in first). Return to pre-pregnancy dose after delivery.
- Lactation
- Compatible with breastfeeding. Minimal excretion in breast milk. Continue normal replacement during nursing. Important for maternal energy and mood during postpartum period.
- Pediatric Patients
- Critical for growth and neurological development. Weight-based dosing higher per kg than adults. Congenital hypothyroidism requires immediate treatment. Pediatric endocrinology supervision essential. Regular growth and TSH monitoring.
- Elderly Patients Over 65
- Start LOW and go SLOW. Begin 25-50 mcg, titrate every 6-8 weeks. Higher TSH targets acceptable (1.0-5.0). Careful cardiovascular monitoring. Consider ECG baseline in cardiac disease.
- Coronary Artery Disease
- High risk of triggering angina, MI, or arrhythmias with overtreatment. Start very low (25 mcg), titrate very slowly. Consider cardiac evaluation before starting. Beta-blocker may be needed during titration.
- Adrenal Insufficiency
- Treat adrenal insufficiency BEFORE thyroid hormone. Levothyroxine before glucocorticoid replacement can precipitate adrenal crisis. Coordinate with endocrinology.
- Post-Thyroidectomy Patients
- Essential lifelong replacement therapy. Full replacement dose based on weight (1.6 mcg/kg/day). Monitor TSH 6-8 weeks after starting, then annually once stable.
- Post-RAI Ablation Patients
- Common cause of hypothyroidism requiring lifelong replacement. Monitor TSH regularly. Requirements may take months to stabilize after RAI treatment.
- Thyroid Cancer Patients
- Higher doses for TSH suppression. Target TSH varies by cancer risk (high-risk below 0.1). Requires balance between suppression benefits and cardiovascular/bone risks. Endocrinology supervision essential.
- Diabetic Patients
- Thyroid normalization may reduce insulin sensitivity and diabetes medication requirements. Monitor blood glucose closely during titration. Diabetes medications may need adjustment.
- Osteoporosis Patients
- Avoid overtreatment - excess thyroid hormone increases bone loss. Target upper end of normal TSH range. Regular DEXA monitoring in high-risk patients.
- Congenital Hypothyroidism Infants
- Critical to start immediately after positive newborn screening. Initial dose 10-15 mcg/kg/day. Absolute necessity for normal brain development. Regular pediatric endocrinology follow-up.
📆 Long-Term Follow-Up
Lifelong therapy considerations:
- Annual TSH monitoring: Once stable dose established
- Symptom assessment: At each visit
- Weight monitoring: Track weight changes potentially requiring dose adjustment
- Cardiovascular monitoring: Particularly in elderly
- Bone density in postmenopausal women: Periodic DEXA if suppression
- Pregnancy planning: Optimize TSH before conception
- New medication assessment: Check for interactions with each new prescription
- Manufacturer consistency: Try to maintain same brand for consistent absorption
- Life changes: Weight changes over 10 percent may require dose adjustment
📦 Storage and Handling
- Store at room temperature between 20°C and 25°C (68°F and 77°F)
- Protect from light, moisture, and heat
- Keep tablets in original packaging
- Keep out of reach of children and pets
- Do not use past expiration date
- Do not share medication with others
- Do not use tablets that appear damaged or discolored
- Maintain consistent supply - avoid missing doses
👨⚕️ When to Contact Your Doctor
- Signs of overtreatment: palpitations, weight loss, heat intolerance
- Signs of undertreatment: persistent fatigue, cold intolerance, weight gain
- Chest pain or worsening angina
- Atrial fibrillation or new arrhythmia
- Confirmed or suspected pregnancy - dose increase needed
- Starting or stopping medications potentially interacting with levothyroxine
- Starting calcium, iron, or PPI therapy
- Significant weight change (over 10 percent)
- Development of new medical conditions
- Time for scheduled TSH monitoring
- Symptoms not improving after 6-8 weeks of therapy
- Signs of allergic reaction (rare)
- Difficulty tolerating the medication
- Missing doses regularly
- Considering brand or manufacturer change
🌟 Key Takeaways
Essential points about Eltroxin (levothyroxine) therapy:
- Eltroxin is Combitic Global + GSK Pharma India generic levothyroxine 50 mcg tablets
- Bioidentical synthetic thyroxine (T4) - identical to endogenous thyroid hormone
- Original Glaxo brand established internationally - US equivalents Synthroid Levoxyl Levothroid Unithroid Tirosint
- Opposite indication sibling to Carbirose - replacement vs blocker for thyroid disease
- Primary indication: hypothyroidism from any cause
- Multiple uses: Hashimoto's, post-thyroidectomy, post-RAI, congenital, cancer TSH suppression
- Long ~7-day half-life allows once daily dosing
- Steady state 4-6 weeks - clinical assessment requires patience
- Adult replacement 1.6 mcg/kg/day average
- Elderly/CAD: start LOW 25-50 mcg, titrate slowly
- Pregnancy: increase 20-30% requirements, monitor monthly
- Take on EMPTY STOMACH 30-60 min before breakfast
- Wait 4 hours before/after coffee calcium iron cholestyramine
- Monitor TSH q6-8 weeks during titration, annually once stable
- Target TSH 0.5-4.0 for standard replacement
- Overtreatment causes iatrogenic hyperthyroidism (palpitations weight loss)
- Undertreatment continues hypothyroid symptoms
- Treat adrenal insufficiency BEFORE starting levothyroxine
- Lifelong therapy typical for most causes
- Excellent safety with appropriate dosing and monitoring
Important Medical Disclaimer: This medication guide provides general information about Eltroxin (levothyroxine 50 mcg tablets Combitic Global + GSK Pharma India) and does not constitute individualized medical advice. Every patient situation is unique and requires evaluation by a qualified healthcare provider before starting continuing or discontinuing thyroid hormone replacement therapy. Levothyroxine therapy requires regular TSH monitoring and dose adjustments - do not modify dose without physician guidance. Take on empty stomach 30-60 minutes before breakfast with water only. Avoid coffee calcium iron cholestyramine and other interfering substances within 4 hours of dosing. Elderly patients and those with coronary artery disease require careful low-dose initiation with slow titration to prevent cardiac stress. During pregnancy requirements increase 20-30 percent - inform your obstetrician immediately if pregnant so dose can be increased and monitoring intensified. TSH monitoring critical: every 6-8 weeks during titration, annually once stable, monthly during pregnancy. Treat adrenal insufficiency BEFORE starting levothyroxine to prevent adrenal crisis. Report signs of overtreatment (palpitations, weight loss, heat intolerance) or undertreatment (persistent fatigue, cold intolerance) to your healthcare provider. Do not use for weight loss in non-hypothyroid patients - dangerous inappropriate use. Levothyroxine typically requires lifelong therapy for most hypothyroid causes - do not discontinue without physician guidance. If you experience concerning symptoms particularly chest pain new arrhythmias or difficulty tolerating the medication contact your healthcare provider promptly. The information provided here should complement but never replace direct professional medical guidance from your endocrinologist or primary care physician.
Eltroxin — Frequently Asked Questions
-
What is Levothyroxine (Eltroxin) used for?
It's used to treat hypothyroidism (underactive thyroid), which means your thyroid does not produce enough thyroid hormones. -
How does Levothyroxine work?
It replaces or provides more thyroid hormone, which is normally produced by the thyroid gland, helping to normalize body energy, metabolism, and growth and development. -
How should I take Levothyroxine?
Take it on an empty stomach, at least 30 to 60 minutes before breakfast. Consistency in timing maximizes absorption. -
Can Levothyroxine affect my weight?
Correcting hypothyroidism with Levothyroxine can help to normalize weight if it had been affected by the condition, primarily through water retention and slowed metabolism. -
What are the side effects of Levothyroxine?
When dosed correctly, side effects are rare but can include symptoms of hyperthyroidism like sweating, sensitivity to heat, nervousness, and insomnia. -
How long does it take for Levothyroxine to work?
Some symptoms improve within a few weeks, but it can take several months for your metabolism to stabilize fully. -
Can I take Levothyroxine with other medications?
Some medications can interfere with its absorption. Discuss all medications you're taking with your healthcare provider.
See all Eltroxin questions (32)
More Thyroid Medications




