Buy Virovir (Generic Famciclovir by Cipla) Online — Affordable Indian Highly Bioavailable Anti-Herpes Antiviral for Shingles, Genital Herpes & Cold Sores


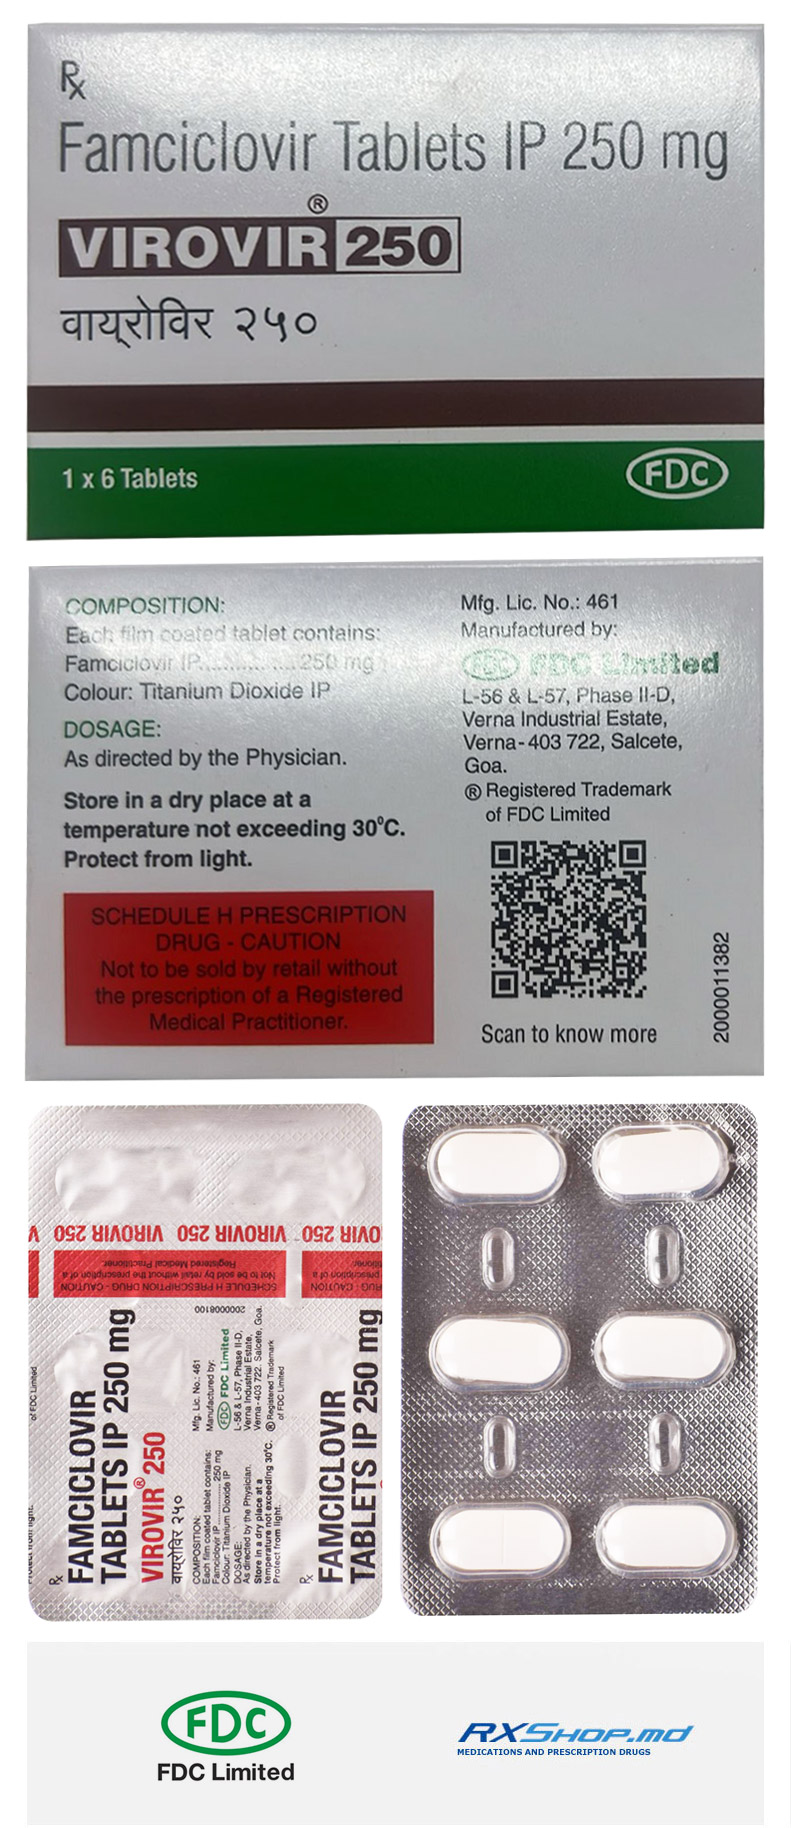
Virovir is an affordable Indian generic of Famciclovir manufactured by Cipla Limited — one of India's largest and most respected pharmaceutical companies. Providing the same therapeutic activity as the original branded Famvir (Novartis) at significantly lower cost, Virovir is a highly bioavailable oral antiviral medication for herpes simplex virus (HSV) and varicella-zoster virus (VZV) infections. Distinguished by superior oral bioavailability and longer intracellular half-life compared to acyclovir, Virovir enables convenient single-day high-dose regimens for cold sores and recurrent genital herpes.
The active ingredient is Famciclovir, an oral prodrug of penciclovir. After oral administration, Famciclovir is rapidly absorbed (~77% oral bioavailability vs 15-30% for acyclovir) and converted to penciclovir, then phosphorylated by viral thymidine kinase (TK) to its active triphosphate. The active triphosphate selectively inhibits viral DNA polymerase. Because phosphorylation requires viral TK, penciclovir is selectively activated in virus-infected cells only — providing excellent selectivity and safety. The active triphosphate has a remarkably long intracellular half-life (10+ hours), supporting less frequent dosing than acyclovir.
Virovir is FDA-approved (as Famvir) for acute herpes zoster (shingles) in immunocompetent adults, recurrent genital herpes treatment (including convenient single-day 1000 mg BID regimen), suppression of recurrent genital herpes, recurrent orolabial herpes (cold sores — single 1500 mg dose), and recurrent mucocutaneous HSV in HIV-positive patients. Off-label uses include herpes simplex keratitis, eczema herpeticum, and HSV in immunocompromised patients.
The medication is available as Virovir 250 mg, 500 mg, and 750 mg tablets. Standard adult dosing varies by indication: herpes zoster 500 mg three times daily for 7 days, recurrent genital herpes 1000 mg BID for 1 day or 125 mg BID for 5 days, genital herpes suppression 250 mg BID, recurrent orolabial herpes 1500 mg as single dose, and HSV in HIV+ 500 mg BID for 7 days.
Critical safety considerations include generally excellent tolerability — most common side effects are mild headache, nausea, diarrhea, and fatigue. Rare adverse effects include thrombotic thrombocytopenic purpura/hemolytic uremic syndrome (TTP/HUS) in immunocompromised patients. Renal dose adjustment required for CrCl below 60 mL/min. Pregnancy Category B. The lactose-containing formulation should be noted in patients with severe lactose intolerance.

Free prescription
Discrete packaging
Have questions?
Quality Assurance

- Acute Shingles Treatment: For acute shingles within 72 hours of rash onset (500 mg three times daily x 7 days);
- Postherpetic Neuralgia Reduction: Reduces incidence of post-herpetic neuralgia following shingles;
- Recurrent Genital Herpes: FDA-approved for recurrent genital herpes (HSV-2) treatment;
- Genital Herpes Single Day: FDA-approved convenient single-day 1000 mg BID regimen for recurrent genital herpes;
- Genital Herpes Suppression: FDA-approved for chronic suppression of recurrent genital herpes (250 mg BID);
- Orolabial Herpes / Cold Sores: FDA-approved for recurrent orolabial herpes/cold sores (HSV-1) — single-dose 1500 mg regimen;
- Cold Sore Single Dose: Single 1500 mg dose for recurrent cold sore episodes — signature convenient regimen;
- HSV HIV Positive Patients: FDA-approved for recurrent mucocutaneous HSV in HIV-positive patients (500 mg BID);
- First Episode Genital Herpes: For first-episode genital herpes (acyclovir/valacyclovir typically preferred);
- Herpes Simplex Keratitis: Off-label for herpes simplex keratitis (with ophthalmology specialist);
- Eczema Herpeticum: Off-label for eczema herpeticum (HSV infection in atopic dermatitis);
- HSV Immunocompromised: Off-label for HSV infection in immunocompromised patients;
- HSV Encephalitis Adjunct: Off-label oral step-down after IV acyclovir for HSV encephalitis;
- Bell Palsy HSV Reactivation: Off-label adjunct for Bell's palsy associated with HSV reactivation;
- HSV Whitlow: Off-label for herpetic whitlow (HSV finger infection);
- HSV Esophagitis: Off-label for HSV esophagitis in immunocompromised patients;
- Recurrent HSV Suppression: For chronic suppression in patients with frequent HSV recurrences;
- Renal Dose Adjusted HSV: Renal dose adjustment for CrCl below 60 mL/min — flexible dosing in renal impairment.
- Less Shingles Pain: Reduction in acute shingles pain duration and severity;
- Less Postherpetic Neuralgia: Reduces incidence and severity of post-herpetic neuralgia following shingles;
- Faster Shingles Rash Resolution: Accelerates herpes zoster rash crusting and resolution;
- Less Genital Herpes Episode Duration: Shortens duration of recurrent genital herpes episodes;
- Less Genital Herpes Symptoms: Reduces severity of genital herpes recurrence symptoms;
- Faster Genital Herpes Healing: Accelerates lesion healing in recurrent genital herpes;
- Less Genital Herpes Frequency: Suppressive therapy significantly reduces recurrence frequency;
- Less Cold Sore Duration: Single 1500 mg dose effectively reduces cold sore episode duration;
- Faster Cold Sore Healing: Accelerates cold sore lesion healing — one-dose convenience;
- Less HSV Viral Shedding: Reduces viral shedding in recurrent HSV-1/HSV-2 infections;
- Less HSV Partner Transmission: Suppressive therapy reduces HSV-2 transmission to sexual partners;
- Less HIV-HSV Severity: Effective treatment of recurrent mucocutaneous HSV in HIV-positive patients;
- Better Daily Function: Return to normal daily activities with faster healing of herpes episodes;
- Better Quality of Life: Substantial quality of life improvement through reduced HSV recurrence frequency and severity;
- Less Psychological Distress HSV: Reduces psychological distress associated with recurrent genital herpes;
- Better Sexual Health: Reduces interference with sexual relationships from HSV recurrences;
- Excellent Tolerability: Generally very well-tolerated with minimal side effects;
- Brand Virovir: Affordable Indian Cipla Limited brand of Famciclovir with international quality manufacturing standards;
- Generic Famciclovir: Affordable generic Famciclovir expanding global access to highly bioavailable anti-herpes therapy;
- Famvir Equivalent: Same Famciclovir molecule as original Novartis brand Famvir with bioequivalent therapeutic profile;
- Cipla Manufacturing: Cipla Limited — one of India's largest and most respected pharmaceutical companies;
- Penciclovir Oral Prodrug: Oral prodrug delivery of penciclovir (only topical Penciclovir/Denavir was available before Famciclovir);
- Nucleoside Analog Antiviral: Foundational nucleoside analog antiviral class;
- 77 Percent Bioavailability: Excellent 77% oral bioavailability vs 15-30% for acyclovir — key tolerability advantage;
- Viral DNA Polymerase Inhibition: Viral DNA polymerase inhibition mechanism — selective for infected cells via TK activation;
- Selective Virus Infected Cells: TK-dependent activation provides selectivity for virus-infected cells — excellent safety profile;
- Long 10 Hour Intracellular Half Life: Long intracellular half-life supports less frequent dosing than acyclovir;
- Single Day Herpes Regimen: FDA-approved single-day regimens for cold sores (1500 mg once) and genital herpes (1000 mg BID x 1 day);
- Shingles First Line: First-line therapy for acute herpes zoster (shingles) in immunocompetent adults;
- Genital Herpes Standard: Standard therapy for recurrent genital herpes treatment and suppression;
- Cold Sore Standard: Standard therapy for recurrent orolabial herpes/cold sores with convenient single-dose option;
- Indian Quality Manufacturing: Indian Cipla Limited manufacturing meeting international quality and bioequivalence standards;
- WHO Essential Medicine: Listed on the WHO Model List of Essential Medicines;
- 30 Plus Year Anti Herpes History: Extensive real-world safety and efficacy data since 1994 across millions of patient courses.
Generic Virovir (Famciclovir 250 mg) Medication guide:
📖 What Is Virovir Cipla Famciclovir Herpes Antiviral
💊 Virovir is the Cipla generic version of famciclovir - an oral antiviral medication for herpes simplex virus (HSV) and varicella-zoster virus (VZV) infections. Originally approved by FDA in June 1994 as Famvir by SmithKline Beecham (subsequently marketed by Novartis in various markets), famciclovir has become an important treatment option for genital herpes, cold sores, and shingles.
🧪 Famciclovir is a diacetyl 6-deoxy ester prodrug of penciclovir - an antiviral nucleoside analog structurally related to acyclovir. The prodrug design achieves excellent oral bioavailability of approximately 77%. After absorption, famciclovir undergoes rapid conversion to penciclovir - the active antiviral form. Penciclovir is then selectively phosphorylated in HSV or VZV infected cells to its active triphosphate form. A distinctive feature is the substantially prolonged intracellular half-life of penciclovir triphosphate (7-20 hours) compared to acyclovir triphosphate (~1 hour) - potentially supporting sustained antiviral activity.
📇 Virovir product snapshot
| Generic name | Famciclovir |
| Chemical class | Diacetyl 6-deoxy ester prodrug of penciclovir; guanosine nucleoside analog |
| Innovator origin | SmithKline Beecham (later marketed by Novartis Pharmaceuticals as Famvir in various markets) |
| Cipla generic sponsor | Cipla Limited (Mumbai, India) - the Virovir product available on RXshop |
| FDA approval | June 1994 (initial herpes zoster approval); subsequent HSV indications through years |
| Formulations | Virovir available as 250 mg (primary), 500 mg, and 750 mg tablets |
| Typical adult dose | Indication-specific ranging from 125 mg twice daily to 1500 mg single dose |
| Bioavailability advantage | Approximately 77% penciclovir bioavailability - excellent oral absorption |
| Distinctive PK feature | Prolonged intracellular half-life of penciclovir triphosphate (7-20 hours) |
| Modern primary indications | Genital herpes (HSV-2), cold sores (HSV-1 single-day), shingles (VZV), HSV suppression, immunocompromised HSV |
| Tolerability signature | Well-tolerated; headache and nausea most common; low overall adverse effect burden |
✅ Modern positioning: famciclovir is an established alternative to acyclovir and valacyclovir in HSV and VZV therapy. Clinical outcomes across HSV and VZV indications are broadly comparable to alternatives. Patient preference, cost considerations, prior experience, and the distinctive PK profile guide choice between famciclovir and alternatives.
🌟 Distinctive PK advantage: the substantially prolonged intracellular half-life of penciclovir triphosphate compared to acyclovir triphosphate means famciclovir provides sustained intracellular antiviral concentrations. This underlies the convenient dosing patterns for famciclovir including once-daily suppression and single-day cold sore treatment. Well-established at Cipla generic pricing for accessible global availability.
📜 History from SmithKline Beecham 1994 to Cipla Generic
📜 The famciclovir development story represents a distinctive chapter in HSV/VZV antiviral history. Developed at SmithKline Beecham (later part of GlaxoSmithKline) as an oral prodrug of penciclovir, famciclovir provided a chemically distinct alternative to the earlier acyclovir. Understanding this development trajectory illuminates famciclovir current clinical role.
📅 Famciclovir historical journey
🧪 1974-1978 - Acyclovir discovery era — Gertrude Elion and colleagues at Burroughs Wellcome develop acyclovir - the first selective antiherpes agent. Establishes the paradigm of viral thymidine kinase-selective antiviral activity. Later shares 1988 Nobel Prize.
🔬 Early 1980s - Penciclovir discovery — Roger Vere Hodge and colleagues at Beecham Research (later SmithKline Beecham) discover penciclovir - a guanosine nucleoside analog with antiviral activity against HSV and VZV. Structurally distinct from acyclovir but similar mechanism.
🔑 Key discovery - prolonged intracellular half-life — Researchers characterize penciclovir triphosphate substantially prolonged intracellular half-life (7-20 hours) compared to acyclovir triphosphate (~1 hour). This distinctive PK property becomes a defining feature.
🗞️ Penciclovir absorption limitation — Penciclovir itself has poor oral bioavailability (~5%) making it unsuitable as oral drug. Available in topical formulation but not oral.
🔬 Late 1980s - Famciclovir prodrug development — SmithKline Beecham chemists develop famciclovir - a diacetyl 6-deoxy ester prodrug of penciclovir. Structure achieves substantially improved oral bioavailability (~77%). After absorption, rapidly converted to penciclovir.
📅 June 1994 - Famvir FDA approval — Famvir approved by FDA for herpes zoster (shingles) treatment. Based on Tyring et al. 1995 pivotal trial showing famciclovir non-inferior to acyclovir. Provides three-times-daily rather than five-times-daily convenient dosing.
💔 1995-1996 - Genital herpes indications — FDA extends Famvir approval to recurrent genital herpes treatment and suppression. Sacks et al. and other clinical trials establish genital HSV efficacy.
🔱 2000 - GlaxoSmithKline formation — SmithKline Beecham merges with Glaxo Wellcome to form GlaxoSmithKline (GSK). Famvir becomes part of the enlarged GSK antiviral portfolio.
👤 2003-2005 - Novartis licensing — Product exchange between GSK and Novartis - Famvir marketing rights transfer to Novartis Pharmaceuticals in various markets. Continued clinical use.
💄 2006 - Single-day cold sore regimen approval — Spruance et al. 2006 pivotal trial supports FDA approval of single-day famciclovir 1500 mg regimen for herpes labialis (cold sores). Convenient one-dose therapy for cold sore prodrome.
💰 2007+ - Generic famciclovir launches — US patent expires; multiple generic manufacturers including Cipla, Teva, Sun Pharma, and others launch generic famciclovir. Prices decline substantially. Global generic access begins.
🇮🇳 Cipla generic Virovir — Cipla generic famciclovir marketed as Virovir. Same therapeutic activity as originator Famvir at substantially lower cost. Widely available including on RXshop.
🌍 Present - Established HSV/VZV alternative — Famciclovir remains one of the three main oral antivirals for HSV and VZV (alongside acyclovir and valacyclovir). Cipla generic Virovir supports affordable access globally.
🌟 Historical significance: famciclovir represents successful medicinal chemistry solving an oral delivery problem - transforming poorly absorbed penciclovir into practical once-to-thrice daily oral therapy. The prodrug design combined with penciclovir distinctive intracellular pharmacology created a differentiated addition to HSV/VZV therapy that continues to serve patients today at accessible generic pricing.
🧪 Chemistry Diacetyl Ester Prodrug of Penciclovir
🧪 Famciclovir is chemically a diacetyl 6-deoxy ester prodrug of penciclovir. The molecule combines the penciclovir parent structure - an acyclic guanosine analog - with esterified acetyl groups and 6-deoxy modification. This structural design was engineered specifically to overcome the poor oral bioavailability of penciclovir.
⚗️ Famciclovir chemical characteristics
| IUPAC name | 2-[2-(2-amino-9H-purin-9-yl)ethyl]-1,3-propanediyl diacetate |
| Molecular formula | C14H19N5O4 |
| Molecular weight | 321.34 g/mol |
| Physical form | White to pale yellow solid |
| Solubility | Freely soluble in acetone, methanol; sparingly soluble in water |
| Chemical class | Diacetyl 6-deoxy ester prodrug of penciclovir; guanosine nucleoside analog |
| Key design feature | Diacetyl esterification and 6-deoxy modification enable oral absorption |
| Active metabolite | Penciclovir (via first-pass metabolism through aldehyde oxidase and esterases) |
| Related compounds | Penciclovir (parent, topical only); acyclovir (structurally related); ganciclovir (related structure) |
🎯 Prodrug design significance
🔬 The bioavailability problem — Penciclovir itself has approximately 5% oral bioavailability - too low for practical oral use. Penciclovir is polar and does not readily cross intestinal epithelium.
🔑 Prodrug engineering solution — Diacetyl esterification plus 6-deoxy modification creates famciclovir with substantially altered physicochemical properties. Increased lipophilicity supports absorption across intestinal epithelium.
🔑 Two-step metabolic activation — After absorption: (1) Ester hydrolysis by intestinal and hepatic esterases removes acetyl groups; (2) Aldehyde oxidase (in liver) oxidizes the 6-deoxy purine to guanine completing conversion to penciclovir.
🔑 Efficient first-pass conversion — Rapid essentially complete conversion to penciclovir during first-pass metabolism. Very little intact famciclovir reaches systemic circulation. Overall penciclovir bioavailability approximately 77%.
🔑 Same antiviral mechanism as penciclovir — Since famciclovir is delivery vehicle for penciclovir, all antiviral activity comes from the penciclovir metabolite. The prodrug component contributes only oral delivery.
🔬 Penciclovir vs acyclovir structural comparison
🧪 Both are acyclic guanosine analogs — Similar overall structure. Both feature an acyclic sugar-like side chain instead of ribose.
🧪 Key structural difference — Penciclovir has a modified side chain with a hydroxymethyl group replacing the terminal hydroxyl. This structural feature underlies the distinctive intracellular pharmacology.
🧪 Consequence - chain termination vs competitive inhibition — Acyclovir causes obligate chain termination after incorporation (missing 3-prime hydroxyl). Penciclovir does NOT cause obligate chain termination - has an equivalent 3-prime hydroxyl and only competes with dGTP for incorporation, reducing viral DNA synthesis efficiency but not stopping it completely.
🧪 Consequence - intracellular persistence — Penciclovir triphosphate has substantially longer intracellular half-life (7-20 hours) than acyclovir triphosphate (~1 hour). Distinctive pharmacology.
🔗 Related compounds and family: famciclovir/penciclovir shares the acyclic guanosine analog family with acyclovir and ganciclovir. Each compound has distinct properties reflecting subtle chemical differences. All targeted at viral thymidine kinase-mediated selective antiviral activity.
📦 Virovir formulations: Cipla Virovir available in 250 mg, 500 mg, and 750 mg tablets. Bioequivalent to innovator Famvir. Different strengths support different indication-specific dosing regimens.
🌟 Cipla generic bioequivalence: Cipla generic famciclovir has demonstrated bioequivalence to innovator Famvir through standard pharmacokinetic studies. Clinical outcomes with Cipla generic famciclovir match innovator product performance in HSV and VZV therapy.
⚙️ Mechanism Bioconversion Chain Termination HSV VZV
⚙️ Famciclovir mechanism operates through a two-stage cascade: prodrug bioconversion to penciclovir, followed by penciclovir selective phosphorylation and viral DNA polymerase inhibition in HSV or VZV infected cells. The mechanism is similar to acyclovir but with distinctive differences that underlie famciclovir clinical characteristics.
🔬 Stage 1 - Prodrug bioconversion
💩 Absorption — Famciclovir absorbed from intestine - substantially better than penciclovir directly due to prodrug engineering. Oral bioavailability approximately 77%.
✂️ Ester hydrolysis — Esterases in intestine and liver rapidly hydrolyze the diacetyl ester groups. This produces 6-deoxy penciclovir intermediate.
🧪 Aldehyde oxidase conversion — Aldehyde oxidase in liver oxidizes the 6-deoxy purine to guanine base completing conversion to penciclovir. Very rapid first-pass conversion - essentially complete before famciclovir reaches systemic circulation.
🔬 Very little intact famciclovir in circulation — Systemic exposure is essentially all penciclovir, not famciclovir. Famciclovir is a highly efficient delivery vehicle.
🔬 Stage 2 - Penciclovir intracellular antiviral action
🧩 Selective viral thymidine kinase phosphorylation — Penciclovir diffuses into all cells but only HSV or VZV thymidine kinase (TK) efficiently phosphorylates penciclovir to penciclovir monophosphate. Uninfected cells lack this activity. Key selectivity step.
🧪 Cellular kinase conversion to triphosphate — Cellular guanylate kinase and nucleoside diphosphate kinase convert penciclovir monophosphate through diphosphate to penciclovir triphosphate - the active antiviral species. Concentration in infected cells becomes much higher than uninfected cells.
🕐 DISTINCTIVE - Prolonged intracellular half-life — Penciclovir triphosphate intracellular half-life is 7-20 hours - substantially longer than acyclovir triphosphate (~1 hour). This is a key differentiating pharmacological feature enabling sustained intracellular antiviral concentrations between doses.
💥 Competition at viral DNA polymerase — Penciclovir triphosphate competes with natural deoxyguanosine triphosphate (dGTP) for incorporation into growing viral DNA strand by HSV or VZV DNA polymerase. Viral polymerase incorporates penciclovir.
🔬 DISTINCTIVE - Non-obligate chain termination — Unlike acyclovir (which causes obligate chain termination due to missing 3-prime hydroxyl), penciclovir has a functional 3-prime hydroxyl equivalent. Penciclovir incorporation does NOT completely stop chain elongation but substantially reduces synthesis efficiency through competitive inhibition of viral DNA polymerase.
🎯 Selectivity and safety implications
🔑 Viral TK requirement provides selectivity — Same viral TK-dependent selectivity as acyclovir/valacyclovir. Uninfected cells accumulate minimal active drug. Excellent tolerability profile results.
🔑 Viral polymerase preference — Penciclovir triphosphate is a much better substrate for viral DNA polymerase than cellular DNA polymerases. Selective viral suppression.
🔑 Cellular sparing — Normal human cell DNA replication minimally affected. Clean therapeutic index.
🔑 No mitochondrial toxicity — Penciclovir does not meaningfully affect mitochondrial DNA polymerase gamma. Contrasts with some other nucleoside analogs.
🔬 HSV vs VZV activity differences
🔑 Strong HSV activity — Penciclovir has strong HSV-1 and HSV-2 activity comparable to acyclovir. Efficiently phosphorylated by HSV TK.
🔑 Moderate VZV activity — Penciclovir has slightly lower VZV activity than HSV activity (approximately 2-3 fold lower). This is similar to acyclovir. Higher doses used for VZV indications.
🕐 Different intracellular half-lives — Penciclovir triphosphate half-life: HSV-1 infected cells ~10 hours; HSV-2 infected cells ~20 hours; VZV infected cells ~7 hours. Longest in HSV-2 cells - contributes to convenient HSV suppression dosing.
❌ What famciclovir does not treat: no meaningful activity against CMV, HHV-6/7/8, EBV, HIV, HBV, HCV, influenza, or other non-HSV/VZV viruses. Focused HSV and VZV therapy - same spectrum as acyclovir and valacyclovir.
🔬 Resistance mechanism preview: HSV/VZV resistance to famciclovir emerges through viral thymidine kinase mutations - substantially cross-resistant with acyclovir/valacyclovir (since same TK phosphorylation step). Rare in immunocompetent patients; more common in severely immunocompromised patients with prolonged treatment. Discussed in section 33.
🔬 Pharmacokinetics Prolonged Intracellular Half-Life
🔬 Famciclovir pharmacokinetics are characterized by excellent oral absorption, rapid conversion to penciclovir, prolonged intracellular half-life of penciclovir triphosphate, and renal elimination. Understanding these PK parameters supports appropriate dosing and dose adjustment framework.
📊 Famciclovir/penciclovir pharmacokinetic parameters
| Oral bioavailability of penciclovir (from famciclovir) | Approximately 77% - excellent |
| Peak plasma penciclovir concentration (Tmax) | Approximately 1 hour after oral famciclovir dose |
| Effect of food | Food delays absorption but does not affect total exposure - can be taken with or without food |
| Famciclovir plasma persistence | Very brief - essentially all converted to penciclovir during first-pass |
| Volume of distribution (penciclovir) | Approximately 1.1 L/kg (widely distributed) |
| Plasma protein binding (penciclovir) | Less than 20% (low binding) |
| Cerebrospinal fluid penetration | Modest - lower than acyclovir |
| Plasma penciclovir half-life | Approximately 2-2.5 hours in healthy adults (similar to acyclovir) |
| Intracellular penciclovir triphosphate half-life | DISTINCTIVE - 7-20 hours depending on infected cell type |
| Half-life in elderly and renal impairment | Substantially prolonged - up to 15 hours in severe renal impairment |
| Primary metabolism | Aldehyde oxidase and esterases convert famciclovir to penciclovir; penciclovir minimally further metabolized |
| CYP450 involvement | Minimal - essentially no cytochrome P450 interactions |
| Primary elimination pathway | Renal excretion of penciclovir as unchanged drug; glomerular filtration + active tubular secretion |
| Renal impairment consideration | Substantial accumulation with reduced renal function - dose adjustment essential |
🕐 The distinctive intracellular pharmacology
🔑 Sustained intracellular concentrations — While plasma penciclovir half-life is short (~2 hours), the intracellular active triphosphate persists 7-20 hours. This means intracellular antiviral concentrations remain sustained between doses.
🔑 Enables convenient dosing intervals — Prolonged intracellular half-life supports twice-daily to three-times-daily dosing patterns. Single-day cold sore treatment (1500 mg single dose) exploits this pharmacology.
🔑 HSV-2 particularly favorable — HSV-2 infected cells show longest intracellular half-life (~20 hours). Supports convenient HSV-2 suppression regimens.
🔑 Contrast with acyclovir — Acyclovir triphosphate persists intracellularly only ~1 hour. This is why oral acyclovir requires 5-times-daily dosing while famciclovir provides similar antiviral effect at less frequent dosing.
🫀 Renal elimination importance: penciclovir is eliminated approximately 60-70% unchanged in urine. Reduced renal function causes substantial accumulation. Dose adjustment for renal function is essential - see section 16.
🌟 Clean interaction profile: minimal CYP450 involvement means famciclovir/penciclovir has minimal drug interactions compared to many other medications. This is one of the drug clinical strengths - similar to acyclovir/valacyclovir in clean interaction profile.
📋 FDA Indications HSV VZV Comprehensive Framework
📋 Famciclovir FDA-approved indications span HSV genital, HSV labialis, HSV suppression, herpes zoster (shingles), and HSV suppression in HIV positive patients. Understanding the complete indication framework supports appropriate clinical use across the broad HSV/VZV therapeutic scope.
📋 FDA-approved indications framework
| Indication | Population | Approval Era |
|---|---|---|
| Herpes zoster (shingles) | Adults | June 1994 (initial FDA approval) |
| Recurrent genital herpes - episodic treatment | Immunocompetent adults | 1995-1996 |
| Recurrent genital herpes - chronic suppression | Immunocompetent adults | 1996 |
| Recurrent herpes labialis (cold sores) | Immunocompetent adults | 2006 (single-day regimen) |
| Recurrent HSV in HIV positive patients | HIV-infected adults | Specific HIV coinfection labeling |
| Off-label - immunocompromised HSV/VZV | Various immunocompromised populations | Clinical practice extension |
🎯 Modern positioning within HSV/VZV framework
💔 Genital herpes management — Famciclovir is one of three main options for genital HSV alongside acyclovir and valacyclovir. Similar efficacy across all three for episodic treatment. Some evidence supports slightly different pharmacokinetic properties for specific scenarios.
👄 Cold sore treatment — Convenient single-day 1500 mg regimen - major appeal for patients preferring one-dose therapy. Comparable efficacy to alternatives.
💀 Shingles treatment — Effective alternative to acyclovir and valacyclovir for herpes zoster. Three-times-daily 500 mg regimen. Comparable clinical outcomes.
👤 HIV coinfection — Specific labeled indication for recurrent HSV in HIV positive patients. Higher dose (500 mg twice daily) than immunocompetent regimen. Important option for HIV/HSV coinfection.
👤 Immunocompromised HSV/VZV — Off-label use in transplant recipients, cancer patients, other immunocompromised - well-established clinical practice supporting HSV/VZV control in these populations.
🌍 Global positioning: famciclovir is widely available generically at accessible prices globally. Cipla Virovir supports global access. Not on WHO Model Essential Medicines List (which includes acyclovir) but widely used regional and national list inclusion.
🎯 Modern practice framework: famciclovir is widely prescribed across many clinical settings - primary care, dermatology, women health, HIV care, immunocompromised care. Cost-effective generic access supports broad utilization.
❌ What famciclovir does not treat: no meaningful activity against CMV, EBV, HIV, HBV, HCV, non-herpesvirus infections. Focused HSV/VZV therapy. CMV requires ganciclovir/valganciclovir; HIV requires antiretroviral therapy.
💔 Recurrent Genital Herpes Treatment and Suppression
💔 Recurrent genital herpes - primarily caused by HSV-2 with increasing HSV-1 involvement in some populations - is one of the most common indications for Virovir prescribing. Famciclovir provides treatment for episodic recurrent outbreaks and daily suppression to prevent recurrences.
💔 Genital HSV management framework
📊 Epidemiology — HSV-2 infects approximately 13% of adults worldwide per WHO estimates. Most infections are asymptomatic or unrecognized. Symptomatic recurrent HSV substantially affects quality of life.
🔑 Episodic recurrent treatment — Famciclovir 1000 mg twice daily for 1 day (2000 mg total) is one convenient option per some newer guidelines. Alternative: famciclovir 125 mg twice daily for 5 days (established regimen). Patient-initiated therapy at prodromal symptoms provides best benefit.
📅 Daily suppressive therapy — For patients with 6+ recurrences per year or preference for daily prevention. Famciclovir 250 mg twice daily is standard suppression regimen. Reduces outbreak frequency by approximately 70-80%. Continuous therapy typically continues for years.
👤 HIV coinfected patients — HIV positive patients with HSV-2 recurrent outbreaks: famciclovir 500 mg twice daily for suppression and 500 mg twice daily for 7 days episodic. Higher dosing than immunocompetent.
🤰 Pregnancy considerations — Limited pregnancy safety data compared to acyclovir. Acyclovir/valacyclovir typically preferred in pregnancy per guidelines. Famciclovir generally reserved for pregnancy when preferred alternatives contraindicated.
🎯 Choosing suppression vs episodic strategy
📅 Suppression preferred for — Frequent recurrences (6+ per year), severe outbreaks, immunocompromise, desire to reduce transmission risk.
🔄 Episodic preferred for — Infrequent outbreaks (less than 6 per year), patient preference for treating only when symptomatic, financial considerations.
🤝 Shared decision-making — Discuss both approaches; patients often try both and settle on preference.
📈 Long-term suppression safe — Clinical trials support years-long safe suppression.
🤝 Counseling essentials: famciclovir controls but does not cure HSV-2 infection. Latent infection persists in sacral ganglia for life. Suppression reduces but does not eliminate transmission risk. Barrier methods provide additional protection. Disclosure to sexual partners supports informed consent.
💓 Emotional and psychological support: HSV-2 diagnosis often causes substantial psychological distress. Compassionate counseling emphasizing HSV commonness (13% global), manageability with therapy, and non-defining nature supports mental health. Support resources when appropriate.
🌍 Global access consideration: Cipla generic Virovir supports affordable HSV management globally. Particularly valuable in resource-limited settings where innovator Famvir pricing was prohibitive.
👄 Herpes Labialis Cold Sores Single-Day Treatment
👄 Herpes labialis (cold sores) - typically caused by HSV-1 - affects approximately 20-40% of HSV-1 seropositive individuals with recurrent outbreaks. Famciclovir provides convenient single-day episodic treatment - a distinctive appeal supporting patient preference.
👄 Herpes labialis framework
💥 Typical presentation — Recurrent cold sores usually appear on or near the lip vermillion border. Prodrome (tingling, burning, itching) 1-2 days before visible lesion. Progression from vesicles to ulcers to crusting to healing over 7-14 days typically. Triggers include sun exposure, stress, fever.
📅 Single-day episodic treatment — FDA-approved regimen is famciclovir 1500 mg orally as a single dose. Total treatment complete in one dose. Based on Spruance et al. 2006 pivotal trial. Distinctive one-dose convenience.
🕑 Timing critical for maximum benefit — Best benefit when started at prodromal symptoms (tingling) before visible lesion. Modest benefit when started early in visible lesion. Limited benefit when started at fully developed lesion.
📊 Clinical benefits — Reduces episode duration by approximately 1 day when started early. Reduces lesion size and severity. Some patients experience aborted episodes (no visible lesion develops) when treatment started at prodrome.
👤 Adult indication — FDA approval is for immunocompetent adults. Pediatric use off-label with weight-based dosing.
🔬 Alternative regimens — Famciclovir 500 mg BID for 7 days historical alternative regimen. Less convenient than single-dose. Comparable efficacy.
🎯 Patient counseling essentials
🕑 Recognize prodrome — Tingling, burning, itching on lip 1-2 days before visible lesion is optimal time to start therapy.
💊 Keep supply available — Patients should have Virovir 1500 mg supply on hand for rapid single-dose initiation.
☀️ Sun protection — UV exposure is common trigger; sunscreen on lips (SPF 30+) helps prevent recurrences.
💧 Stress management — Stress reduction may reduce recurrence frequency.
👤 Avoid kissing during outbreak — Reduces transmission to partners and to other body sites including eyes.
🤝 No sharing of utensils — Do not share cups, lip products during active outbreaks.
🔝 Comparison to alternatives: famciclovir single-day 1500 mg single-dose regimen is most convenient among oral options. Valacyclovir requires 2000 mg twice daily for 1 day (2 doses). Acyclovir requires 5-times-daily dosing. Famciclovir wins on convenience for cold sores.
💀 Complications requiring attention: most cold sores heal without complication. Rare complications include herpes labialis dissemination in immunocompromised patients, HSV keratitis, erythema multiforme, secondary bacterial infection. Progressive presentations warrant specialist evaluation.
👤 Immunocompromised patients: immunocompromised patients (HIV, transplant recipients, chemotherapy) with cold sores may have more prolonged and severe episodes. Extended duration therapy at higher doses may be appropriate. Specialist involvement supports individualized management.
💀 Shingles Herpes Zoster VZV Treatment Framework
💀 Herpes zoster (shingles) - caused by reactivation of latent varicella-zoster virus (VZV) - is famciclovir original FDA-approved indication (June 1994). Famciclovir remains an important option for shingles treatment alongside acyclovir and valacyclovir.
💀 Shingles clinical framework
💥 Typical presentation — Painful vesicular rash in a dermatomal distribution - typically unilateral, respecting the midline. Preceded by 2-4 days of dermatomal pain, tingling, or itching (prodromal phase). Rash progresses over 3-5 days. Healing over 2-4 weeks. Pain often severe.
📊 Epidemiology — Lifetime risk approximately 30% in general population. Incidence increases substantially with age - approximately 50% in adults reaching age 85. Risk factors include advancing age (over 50), immunocompromise.
💊 Standard treatment — Famciclovir 500 mg orally three times daily for 7 days. Convenient TID dosing enabled by prolonged intracellular half-life. Compare to acyclovir 800 mg five-times-daily (less convenient) and valacyclovir 1000 mg TID for 7 days (similar convenience to famciclovir).
🕑 Timing critical — Antiviral benefit is maximal when started within 72 hours of rash onset. Some benefit may extend to 5-7 days in severe presentations or immunocompromise. Later initiation provides less benefit.
📊 Clinical benefits — Reduces rash duration by 2-4 days. Reduces acute pain intensity and duration. Reduces risk of postherpetic neuralgia (PHN) - the most feared complication.
💔 Postherpetic neuralgia (PHN) — Chronic severe neuropathic pain persisting after rash resolution. Affects approximately 10-15% of shingles patients overall - much higher in elderly (up to 30%+ over age 70). Antiviral therapy started within 72 hours reduces PHN risk substantially.
👁️ Herpes zoster ophthalmicus — Involves trigeminal nerve V1 branch affecting eye and forehead. Requires urgent ophthalmology involvement. Antiviral therapy essential and started urgently.
💀 Disseminated zoster — Severe presentation involving multiple dermatomes or systemic involvement. More common in immunocompromised. May require intravenous acyclovir rather than oral famciclovir. Hospital admission typically appropriate.
🎯 Adjunctive therapy considerations
💉 Pain management — Shingles pain can be severe; acetaminophen, NSAIDs, sometimes opioids for acute severe pain.
🧠 Neuropathic pain agents — Gabapentin, pregabalin, or amitriptyline for PHN or severe zoster pain.
💉 Corticosteroids — Considered in some cases (particularly severe pain) though evidence is mixed; not recommended in immunocompromised.
🧴 Wound care — Keep lesions clean and dry; avoid picking or scratching.
💉 Vaccination for prevention — Shingrix vaccine dramatically reduces shingles risk in adults over 50.
🌟 Shingrix vaccination revolutionized prevention: Shingrix (recombinant zoster vaccine) approved 2017 provides over 90% efficacy in preventing shingles in adults 50+. Two-dose series. Prof. Tony Cunningham contributed to Shingrix development. ACIP recommends Shingrix for all adults age 50 and older. Shingrix prevents shingles while antivirals treat established disease.
👤 Immunocompromised patients: patients with HIV, transplant, hematologic malignancy, or on immunosuppressive therapy may have severe, prolonged, or disseminated shingles. Higher doses, longer duration, or intravenous acyclovir may be needed. Specialist consultation typically appropriate.
🤝 Practical framework: for immunocompetent adults with typical dermatomal shingles - Virovir 500 mg TID for 7 days, start within 72 hours if possible. Adjunctive pain management. Consider corticosteroid based on severity. Refer to ophthalmology urgently if V1 involvement. Discuss Shingrix for future prevention.
🛡️ Immunocompromised Patient HSV Management
🛡️ Immunocompromised patients are important target populations for famciclovir given elevated HSV/VZV incidence and often more severe clinical courses. Famciclovir provides an alternative to acyclovir/valacyclovir with distinctive pharmacology potentially beneficial in some scenarios.
👤 Immunocompromised population categories
🧬 HIV/AIDS — HIV positive patients - particularly with low CD4 counts - are at elevated HSV/VZV risk. HSV coinfection common. Famciclovir has specific FDA labeling for HSV suppression in HIV positive patients.
💛 Solid organ transplant — Kidney, liver, heart, lung transplant recipients on immunosuppressive therapy. Elevated HSV/VZV risk and more severe disease if reactivation occurs.
🍄 Hematopoietic stem cell transplant — Bone marrow and stem cell transplant recipients have profound early immunosuppression. HSV reactivation common in first months post-transplant.
🔱 Hematologic malignancy — Leukemia, lymphoma, multiple myeloma - active disease and treatment cause immunosuppression.
🔬 Chemotherapy and biological therapy — Cancer patients on active chemotherapy have variable immunosuppression. Elevated HSV/VZV reactivation risk.
💉 Corticosteroid therapy — Chronic high-dose corticosteroids cause immunosuppression. HSV/VZV reactivation risk elevated.
🎯 Famciclovir considerations in immunocompromised
💊 Higher-dose regimens — Extended duration treatment often needed. HSV suppression in HIV: 500 mg twice daily. Extended treatment (10-14 days) for severe HSV. Shingles may need longer than standard 7 days.
📈 More severe disease presentation — Immunocompromised patients often have more severe HSV/VZV presentations - extensive lesions, prolonged viral shedding, delayed healing, higher risk of dissemination.
💀 Disseminated infection risk — Disseminated shingles or HSV can occur in severely immunocompromised. IV acyclovir often needed rather than oral famciclovir. Hospital admission and specialist consultation.
🔬 Resistance risk elevated — Antiviral resistance more common in severely immunocompromised patients with prolonged treatment. TK-mutant HSV strains can emerge. See section 33 for resistance framework.
💉 Prophylaxis considerations — HSV/VZV prophylaxis in stem cell transplant recipients, some solid organ transplant recipients. Famciclovir alternative to acyclovir/valacyclovir per center protocols and patient factors.
🏥 Transplant considerations
🍄 Stem cell transplant — Standard practice includes HSV prophylaxis starting from conditioning. Famciclovir alternative to acyclovir/valacyclovir. Reduces HSV reactivation during profound immunosuppression.
💛 Solid organ transplant — HSV/VZV prophylaxis common. Famciclovir occasionally used per center protocols.
💉 Interactions with immunosuppressants — Famciclovir has minimal interaction with calcineurin inhibitors, mycophenolate, or mTOR inhibitors. Safe combination.
🌟 Balance of considerations: immunocompromised patients derive substantial benefit from famciclovir therapy for HSV/VZV. Enhanced monitoring and appropriate dose considerations support safe effective use in these populations.
👤 Specialist involvement: infectious disease consultation often appropriate for complex immunocompromised HSV/VZV management. Transplant specialists, HIV specialists, and oncology teams typically involved in coordinated care.
🤝 Practical framework: for immunocompromised HSV/VZV - individualized dose and duration; extended treatment often needed; monitor for response and resistance; awareness of dissemination risk; specialist involvement for severe or refractory cases. Structured approach optimizes outcomes.
🔗 Famciclovir Positioning Among HSV Antivirals
🔗 Understanding famciclovir position among HSV/VZV antivirals illuminates when this option is preferred and when alternatives are better. Famciclovir joins acyclovir and valacyclovir as the three main oral HSV/VZV antivirals used globally.
📊 Comparison to acyclovir
🔑 Efficacy comparable — Similar clinical efficacy across HSV and VZV indications. Non-inferior in pivotal trials.
🔑 Convenience advantage of famciclovir — Famciclovir 3-times-daily vs acyclovir 5-times-daily for shingles. Famciclovir single-day cold sore treatment vs acyclovir 5-times-daily. Substantial adherence advantage.
🔑 Prodrug bioavailability — Famciclovir provides ~77% penciclovir bioavailability vs oral acyclovir ~15-30% bioavailability. Reason for less frequent dosing.
🔑 Cost consideration — Both are generic and affordable. Acyclovir often lowest cost. Famciclovir generic pricing accessible.
🔑 Interaction profiles — Both have clean interaction profiles. Neither meaningfully involves CYP450.
🔑 Renal elimination — Both require renal dose adjustment. Similar consideration.
📊 Comparison to valacyclovir
🔑 Efficacy comparable — Similar clinical efficacy across HSV and VZV indications. Non-inferior comparisons.
🔑 Both prodrugs with good bioavailability — Valacyclovir ~54% acyclovir bioavailability; famciclovir ~77% penciclovir bioavailability. Both substantially improved over parent compounds.
🔑 Distinctive intracellular pharmacology — Penciclovir triphosphate 7-20 hour half-life vs acyclovir triphosphate ~1 hour. This is famciclovir key distinguishing feature.
🔑 Convenience patterns — Valacyclovir supports once-daily HSV suppression (500 mg or 1000 mg). Famciclovir uses twice-daily (250 mg BID) for suppression. Slightly different regimen convenience.
🔑 Cold sore convenience — Famciclovir single-dose 1500 mg may be more convenient than valacyclovir 2000 mg twice daily x1 day. Individual preference matters.
🔑 Pregnancy safety data — Valacyclovir has more extensive pregnancy safety data. Preferred in pregnancy typically. Famciclovir usually reserved for pregnancy when alternatives contraindicated.
🔑 Unique valacyclovir indication — Only valacyclovir has FDA-labeled indication for reducing HSV-2 sexual transmission. Not indicated for famciclovir.
🎯 When famciclovir preferred
✅ Single-dose cold sore treatment — 1500 mg once regimen appeals to patients preferring one-dose therapy.
✅ Patient preference or previous experience — Some patients have prior positive experience with famciclovir or preference for less frequent dosing.
✅ Cost differential — Where famciclovir generic pricing is lower than valacyclovir generic pricing locally.
✅ Distinctive pharmacology advantages — Some clinicians preferentially select famciclovir for specific scenarios based on the prolonged intracellular half-life.
✅ Alternative when others contraindicated — Hypersensitivity to acyclovir/valacyclovir - though cross-reactivity limits option; some patients may tolerate famciclovir differently.
🌟 Clinical decision-making framework: famciclovir, acyclovir, and valacyclovir are therapeutically largely equivalent across HSV/VZV indications. Choice among them often driven by patient preference, cost, prior experience, specific dosing convenience needs, and clinician preference. All three have accessible generic pricing globally.
🤝 Practical framework: discuss options with patient; consider cost, convenience, prior experience, specific dosing needs; famciclovir is an established, well-tolerated alternative to acyclovir/valacyclovir; Cipla Virovir provides affordable generic access; expect comparable clinical outcomes to alternatives.
🌍 Modern Positioning and Cipla Generic Access
🌍 The Virovir product available on RXshop is a Cipla Limited generic famciclovir formulation. This section provides context for the Cipla generic HSV/VZV access framework and how it enables affordable Virovir availability worldwide.
📈 Modern famciclovir positioning
✅ Established HSV/VZV antiviral — Famciclovir remains one of three primary oral antivirals for HSV and VZV worldwide - alongside acyclovir and valacyclovir. Widely used across clinical settings.
💔 Genital herpes established option — Standard alternative for genital HSV management. Multiple regimens available. Prescribed by primary care, dermatology, women health providers.
👄 Cold sore convenience leader — Single-day 1500 mg regimen - most convenient one-dose oral cold sore therapy.
💀 Shingles convenient therapy — Three-times-daily 500 mg for 7 days - convenient dosing pattern.
👤 Immunocompromised alternative — Well-established use in HIV coinfection and other immunocompromised populations.
🌟 Continued relevance despite Shingrix — Shingrix vaccine has dramatically reduced shingles incidence in vaccinated adults, but famciclovir remains essential for treating breakthrough shingles and shingles in unvaccinated populations globally.
🌍 Global generic availability — Cipla and other Indian generic manufacturers make famciclovir affordable globally.
📈 Cipla generic access framework
🇮🇳 Cipla Limited overview — Founded 1935 by Khwaja Abdul Hamied; led by Yusuf Hamied from 1972 through 2013. One of the world largest generic pharmaceutical manufacturers with substantial antiviral portfolio. Historic role in HIV therapy affordability continues into HSV/VZV.
💰 Access-oriented pricing — Cipla generic famciclovir (Virovir) available at accessible prices making episodic and suppression HSV therapy affordable globally.
🏆 Quality frameworks — Cipla manufacturing facilities are approved by US FDA, EMA, WHO Prequalification, and multiple national regulatory authorities. Bioequivalence demonstrated.
🌍 Global distribution — Cipla generic Virovir distributed through national procurement systems, pharmacy chains, and international access programs.
📦 Consistent portfolio quality — Cipla Virovir part of the same manufacturing framework that produces Cipla generic Valtrex (valacyclovir), Hepcvir (sofosbuvir), Ribasure (ribavirin), and other RXshop-available Cipla products. Consistent quality framework across portfolio.
📊 Bioequivalence validation: Cipla generic famciclovir demonstrates bioequivalence to the innovator Famvir product. Peak concentration, area under the curve, and time to peak concentration fall within the standard 80-125% bioequivalence limits. Clinical outcomes with Cipla generic Virovir match innovator product performance.
🌟 Future trajectory: as HSV-2 continues to affect approximately 500 million people globally and shingles remains a major consideration in aging populations, affordable famciclovir access will remain an important option. Cipla generic manufacturing supports this continued availability.
🤝 Practical framework: Virovir provides affordable Cipla generic famciclovir; therapeutic equivalence to innovator; suitable for full range of famciclovir indications (genital HSV, cold sores, shingles, HSV suppression, immunocompromised HSV); accessible pricing supports lifelong suppression therapy where indicated. Structured approach supports patient access to modern HSV/VZV therapy.
📊 Adult Dosing Framework Across Multiple Indications
📊 Virovir adult dosing is indication-specific with substantial dose range - from single-dose 1500 mg (herpes labialis) to 500 mg three times daily for 7 days (shingles). Understanding the complete adult dosing framework across all indications supports optimal individualized therapy.
💊 Adult dosing across FDA-approved indications
| Indication | Dose | Duration |
|---|---|---|
| Herpes zoster (shingles) | 500 mg three times daily | 7 days (start within 72 hours of rash) |
| Recurrent genital herpes - episodic (1-day) | 1000 mg twice daily | 1 day (patient-initiated at prodrome) |
| Recurrent genital herpes - episodic (5-day) | 125 mg twice daily | 5 days (patient-initiated at prodrome) |
| Recurrent genital herpes - suppression | 250 mg twice daily | Continuous (typically years) |
| Recurrent HSV in HIV positive - episodic | 500 mg twice daily | 7 days |
| Recurrent HSV in HIV positive - suppression | 500 mg twice daily | Continuous |
| Herpes labialis (cold sores) | 1500 mg single dose | 1 dose (start at prodrome) |
🎯 Practical dosing considerations
🕑 Timing critical for episodic therapy — Episodic HSV and shingles benefit is maximal when started within 72 hours of symptom onset. Patient education about early recognition and rapid initiation is essential.
📅 Patient-initiated therapy for recurrences — For recurrent genital herpes or cold sores, provide patient with supply of Virovir plus clear instructions to initiate at first prodromal symptom. This patient-initiated approach maximizes rapid initiation benefit.
🍽️ Food effect — Virovir can be taken with or without food. Food may delay absorption but does not affect total exposure. Patients with nausea may prefer taking with food.
💧 Hydration important — Adequate hydration supports renal elimination of penciclovir. Counsel patients on adequate fluid intake during Virovir therapy.
🫀 Renal dose adjustment essential — All Virovir doses require adjustment for reduced renal function. See section 16 for detailed framework. This is the most important practical consideration for safe famciclovir prescribing.
🔴 Do not double up for missed doses — If patient misses dose, take as soon as remembered but skip if close to next dose. Do not double the dose to catch up.
💊 Single-dose cold sore convenience — 1500 mg = 3 tablets of 500 mg strength or 6 tablets of 250 mg strength. Cost-effective one-dose therapy. Patient keeps supply available.
💓 Suppression duration decision framework: chronic suppression duration is individualized based on patient factors. Many patients continue indefinitely. Some clinicians recommend annual reassessment. Others continue indefinitely if patient benefits and tolerates well. No fixed duration limit is required.
🏥 When to admit for IV therapy: severe or complicated HSV or VZV may require intravenous acyclovir rather than oral famciclovir. Scenarios include severe herpes zoster ophthalmicus, disseminated zoster, HSV encephalitis, severe HSV in immunocompromised patients. Famciclovir is oral only - no IV formulation.
🤝 Adherence and counseling: for suppression indications, adherence is essential to maintain effect. Missed doses reduce protective benefit. Twice-daily suppression regimen supports adherence when linked to daily routine. Simple regimen and clear counseling support long-term success.
🧒 Pediatric Considerations for Famciclovir
🧒 Famciclovir pediatric FDA approval is limited compared to acyclovir and valacyclovir. Adolescent use in specific scenarios and off-label pediatric use in specialist care support HSV/VZV management in pediatric populations when needed.
👶 Pediatric use framework
🧑 FDA approval status — Famciclovir is FDA-approved for adults (18+ years). Pediatric labeling is more limited than acyclovir or valacyclovir. Some indications have adolescent (age 18+) labeling only.
🧒 Adolescents (usually 18+) — Adult regimens for HSV genital, cold sores, and shingles when weight and clinical scenario support use. Standard adult doses appropriate.
👶 Off-label pediatric use — Pediatric famciclovir use is off-label but occurs in specialist settings. Doses individualized per weight and clinical scenario. Acyclovir/valacyclovir generally preferred for pediatric HSV/VZV due to more extensive labeling and safety data.
👤 Choose acyclovir/valacyclovir preferentially in pediatrics — For most pediatric HSV/VZV scenarios, acyclovir or valacyclovir preferred given more established pediatric labeling, dosing guidance, and safety data.
👶 Neonatal HSV — Neonatal HSV requires intravenous acyclovir. Famciclovir not appropriate. Followed by oral acyclovir/valacyclovir suppression per current guidelines. Specialist management.
💉 Practical pediatric considerations
💊 Tablet swallowing — Virovir tablets - 250 mg, 500 mg, 750 mg strengths. Younger children may have difficulty swallowing tablets. Compounded oral suspension can be prepared by compounding pharmacy where needed.
🫀 Renal function in children — Pediatric dosing assumes normal age-appropriate renal function. Dose adjustment required for renal impairment. Pediatric nephrology or infectious disease consultation supports these adjustments.
💧 Hydration especially important in children — Children may become dehydrated more readily during illness. Adequate oral hydration supports renal elimination.
💉 Varicella vaccination context — In countries with routine childhood varicella vaccination, most children never develop chickenpox. Where breakthrough occurs, typically mild and antiviral therapy may not be needed.
👤 Specialist involvement recommended — Pediatric famciclovir use warrants specialist input - pediatric infectious disease, dermatology, or ophthalmology depending on scenario.
👤 Adolescent-specific considerations
💔 Adolescent HSV genital — Sexually active adolescents with genital HSV - adult famciclovir dosing applies where FDA-approved (age 18+). For younger adolescents, valacyclovir or acyclovir generally preferred.
👄 Adolescent cold sores — Adult single-day 1500 mg famciclovir where age-appropriate.
💀 Adolescent shingles — Uncommon in adolescents. When occurs, standard adult regimens.
💓 Adolescent counseling — Developmentally appropriate counseling - HSV-2 diagnosis in adolescence can cause substantial psychological impact. Confidentiality where legally permissible in jurisdiction. Non-judgmental communication.
💓 Adolescent adherence — Adherence often challenging in adolescents - address adherence barriers, provide reminders, family support where appropriate.
🌟 Bottom line pediatric: famciclovir has more limited pediatric labeling than acyclovir and valacyclovir. For most pediatric HSV/VZV needs, acyclovir or valacyclovir preferred. Famciclovir role in pediatrics primarily off-label in specialist settings. Adolescent use follows adult framework where age-appropriate.
🤝 Practical framework: for pediatric HSV/VZV - consider acyclovir/valacyclovir first-line; famciclovir off-label in specialist care; adolescent use follows adult framework; specialist involvement for complex pediatric scenarios. Structured approach supports pediatric outcomes.
👴 Older Adult Considerations Renal Function Focus
👴 Older adults represent a major target population for Virovir given shingles incidence rises dramatically with age. Effective and safe famciclovir use in older adults requires attention to age-related renal decline, hydration, and monitoring for elderly-specific adverse effects.
👤 Older adult considerations framework
💀 Shingles is dominant indication in elderly — Shingles incidence rises sharply with age - approximately 50% of adults reaching age 85 will experience shingles. Famciclovir is one of the main oral antivirals prescribed for shingles treatment in elderly patients. Prompt initiation within 72 hours of rash is essential.
🫀 Age-related renal decline — Renal function declines predictably with age - even without diagnosed kidney disease. This substantially prolongs penciclovir elimination and increases plasma concentrations at any given dose. Estimated GFR should be calculated and dose adjusted appropriately.
💔 PHN risk substantially elevated in elderly — Postherpetic neuralgia (PHN) occurs in up to 30%+ of elderly shingles patients over age 70. Prompt Virovir initiation within 72 hours of rash reduces PHN risk substantially. Adjunctive gabapentin or pregabalin often needed for acute pain and PHN prevention.
🧠 CNS effects — Elderly patients - particularly with reduced renal function - are at elevated risk of neuropsychiatric adverse effects. Confusion, hallucinations, agitation can occur with elevated penciclovir levels. Dose adjustment for renal function critical.
💧 Hydration challenges in elderly — Elderly patients often have impaired thirst perception and may be at higher risk of dehydration. Adequate hydration supports renal elimination. Encourage fluid intake and monitor for dehydration signs during Virovir therapy.
🔬 Baseline renal assessment mandatory — Prior to Virovir initiation in elderly patients, obtain baseline serum creatinine and calculate estimated GFR. Dose adjustment per label criteria. Reassess renal function during extended therapy.
💉 Vaccine considerations — Older adults should be counseled about Shingrix vaccination for future shingles prevention. Shingrix is recommended by ACIP for all adults age 50+.
👁️ Herpes zoster ophthalmicus in elderly
🚨 Herpes zoster ophthalmicus (HZO) - shingles involving the trigeminal nerve V1 branch - is more common in elderly. Requires urgent ophthalmology involvement due to risk of vision-threatening complications including keratitis, uveitis, retinitis, acute retinal necrosis. Prompt Virovir initiation plus specialist ophthalmology assessment essential.
👤 Frailty and comorbidity considerations: elderly patients with substantial frailty or multiple comorbidities may benefit from simplified regimens. The famciclovir single-day cold sore regimen (1500 mg once) particularly convenient. Coordination with primary care supports safe management.
💉 Polypharmacy considerations: elderly patients often take multiple medications. Famciclovir has a clean drug interaction profile (minimal CYP450 involvement) but drug interactions through renal transport should be considered - particularly concurrent nephrotoxic medications (NSAIDs, aminoglycosides). Medication review reduces polypharmacy-related risks.
💓 Genital HSV in older adults: older adults with recurrent genital HSV benefit from suppression therapy. Dose reduction may be needed for age-related renal function decline.
🤝 Practical elderly framework: for elderly shingles patient - assess renal function; dose adjust famciclovir per label; ensure adequate hydration; monitor for CNS effects; provide adjunctive pain management; refer urgently to ophthalmology if V1 involvement; discuss future Shingrix vaccination. This structured approach supports safe and effective elderly Virovir use.
🫀 Renal Impairment Dose Adjustment Framework
🫀 Renal impairment dose adjustment is the single most important safety consideration for Virovir prescribing. Penciclovir (active metabolite from famciclovir) is eliminated primarily by kidneys. Reduced renal function causes substantial accumulation, prolonged half-life, and increased risk of CNS and renal adverse effects at standard doses.
📊 FDA-labeled renal dose adjustments
| Indication | CrCl 40-59 mL/min | CrCl 20-39 mL/min | CrCl less than 20 |
|---|---|---|---|
| Shingles (500 mg TID) | 500 mg BID | 500 mg daily | 250 mg daily |
| Recurrent HSV suppression (250 mg BID) | 125 mg BID | 125 mg daily | 125 mg every other day |
| Recurrent genital HSV episodic (1000 mg BID x1) | 500 mg BID x1 day | 500 mg single dose | 250 mg single dose |
| HSV in HIV (500 mg BID) | 500 mg daily | 500 mg every 48h | 250 mg every 48h |
| Herpes labialis single-dose (1500 mg) | 750 mg single dose | 500 mg single dose | 250 mg single dose |
🔬 Why renal function matters critically
📊 Elimination pathway — Penciclovir is eliminated primarily by kidneys through combined glomerular filtration and active tubular secretion. Approximately 60-70% appears unchanged in urine. Essentially no hepatic metabolism.
📈 Accumulation with reduced clearance — Reduced renal function causes substantial accumulation - plasma penciclovir concentrations rise proportionally. Half-life extends from ~2-2.5 hours (normal) to up to 15 hours in severe impairment.
🧠 CNS adverse effects — Elevated penciclovir levels can cause neurotoxicity - confusion, hallucinations, agitation, delirium, myoclonus. This is the primary concern with inadequate renal dose adjustment. Elderly and severely impaired patients most at risk.
🫀 Renal effects — Very high penciclovir plasma concentrations can potentially cause tubular effects. Less prominent than acyclovir crystal nephropathy but still requires attention.
📊 Estimated GFR calculation — Use Cockcroft-Gault or CKD-EPI equation to estimate creatinine clearance. Consider ideal body weight for obese patients. Reassess in patients with changing renal function.
💧 Hemodialysis and CRRT
🫀 Hemodialysis considerations — Penciclovir is substantially removed by hemodialysis (approximately 75% during 4-hour session). For patients on maintenance hemodialysis, dose should be administered after dialysis. Reduced doses per specialty guidance.
🫀 Peritoneal dialysis — Removes penciclovir less efficiently. Individualized dosing.
🫀 CRRT — Continuous renal replacement therapy requires individualized dosing at reduced doses with dialysis machine adjustment. Nephrology or infectious disease consultation supports individualized dosing.
🚨 End-stage renal disease patients: ESRD patients require substantial dose reduction and extended dosing intervals. For suppression, doses may need to extend to every 48-72 hours. Nephrology or infectious disease consultation supports individualized ESRD dosing.
📊 Monitoring in renal impairment: patients with renal impairment on Virovir should have periodic renal function monitoring during therapy - especially in extended suppression scenarios. Baseline serum creatinine, follow-up at 1-2 weeks then periodically. Any deterioration warrants dose reassessment.
🤝 Practical framework: before prescribing Virovir - especially in elderly, chronic kidney disease, diabetes, hypertension patients - always calculate estimated GFR and adjust dose per label. Ensure adequate hydration. Monitor for CNS effects. Reassess renal function during therapy. This structured approach prevents the most common serious adverse effects.
🪶 Hepatic Impairment Considerations for Virovir
🪶 Famciclovir does not require dose adjustment for hepatic impairment in most clinical scenarios. This reflects the renal elimination-dominated pharmacokinetics - minimal hepatic metabolism, no CYP450 involvement, and predominantly renal elimination of penciclovir.
🪶 Hepatic considerations framework
✅ No dose adjustment for mild-moderate hepatic impairment — Famciclovir prodrug conversion via aldehyde oxidase and esterases - not CYP450. These enzymes have significant reserve capacity. Mild to moderate hepatic impairment has minimal effect on penciclovir generation. Standard dosing appropriate.
🗒️ Severe hepatic impairment (Child-Pugh C) — Limited pharmacokinetic data in severe hepatic impairment. Aldehyde oxidase activity may be reduced. Clinical experience suggests standard dosing generally appropriate. Use with clinical monitoring.
🫀 Hepatorenal syndrome — Patients with severe liver disease may develop hepatorenal syndrome. In these patients, estimated GFR calculation is critical and dose adjustment based on functional renal capacity, not liver disease per se.
📈 Rare hepatic adverse effects — Famciclovir has been rarely associated with transient transaminase elevations - usually mild and self-limited. Fulminant hepatic failure exceedingly rare. Discussed in section 30.
👤 Chronic hepatitis B and C context — Famciclovir has no antiviral activity against HBV or HCV. Patients with concurrent viral hepatitis plus HSV or VZV requiring famciclovir: famciclovir does not treat the hepatitis virus. Concurrent hepatitis therapy managed separately.
🎯 Practical considerations for hepatic disease patients
🫀 Assess renal function — Hepatorenal syndrome, ascites diuretic use, and other liver disease factors can affect kidney function. Serum creatinine may underestimate renal impairment in cirrhosis. Consider cystatin C or 24-hour urine collection for accurate GFR estimation.
💧 Hydration status — Cirrhotic patients on diuretics can develop rapid fluid status changes. Careful attention to hydration supports safe Virovir use.
💉 Concurrent medications — Cirrhotic patients often take multiple medications including nephrotoxic agents (NSAIDs, diuretics, aminoglycosides). Comprehensive medication review supports safe Virovir use.
👤 Immune status — Advanced liver disease may impair immune function, potentially affecting HSV or VZV clinical course. Consider clinical course in this context.
✅ Bottom line for hepatic considerations: famciclovir is generally safe in hepatic impairment with no specific hepatic dose adjustment required. Focus attention instead on renal function assessment which may be affected by liver disease-related factors. Cirrhotic patients particularly benefit from careful renal function evaluation using accurate methods.
🤝 Compare to other antivirals: famciclovir hepatic-sparing profile similar to acyclovir/valacyclovir clean hepatic profile. Different from some HIV antiretrovirals with hepatic considerations. Well-suited to patients with liver disease requiring HSV/VZV therapy.
🧬 Drug Interactions Framework for Famciclovir
🧬 Famciclovir has a remarkably clean drug interaction profile - minimal CYP450 involvement means essentially no metabolic drug interactions. The primary interaction concerns relate to renal transport competition and concurrent nephrotoxic medications. This clean interaction profile is one of the drug clinical strengths.
✅ CYP450 non-interaction profile
🧪 Famciclovir metabolism pathway — Aldehyde oxidase and esterases convert famciclovir to penciclovir. Not a CYP450 substrate. Penciclovir itself is minimally metabolized - eliminated predominantly renally as unchanged drug.
✅ No CYP450 inhibition or induction — Famciclovir and penciclovir do not inhibit or induce major CYP450 enzymes. This means Virovir can be safely combined with medications metabolized by CYP450 without dose adjustment.
🔑 Clinical implication — This clean CYP450 profile means Virovir is compatible with essentially all medications from a metabolic perspective. Warfarin, statins, calcium channel blockers, opioids, antidepressants, antiepileptics - all can be safely combined with Virovir without CYP450-mediated interaction concerns.
🔬 Aldehyde oxidase interactions
🔬 Distinctive - aldehyde oxidase mediated — Unlike acyclovir/valacyclovir, famciclovir uses aldehyde oxidase for prodrug conversion. This distinctive metabolism creates specific interaction potential.
💉 Raloxifene — Aldehyde oxidase inhibitor. May reduce famciclovir conversion to penciclovir. Clinical significance limited but consider.
💉 Cimetidine — Mild inhibitor of aldehyde oxidase. May modestly increase penciclovir levels. Generally clinically insignificant.
💉 Some cytotoxic agents — Certain chemotherapy agents (methotrexate) - interaction data limited. Consider in cancer patients on famciclovir.
🫀 Renal transport interactions
🧬 Probenecid — Probenecid inhibits renal tubular secretion of penciclovir increasing plasma levels. Combination generally not contraindicated but monitoring for CNS effects appropriate.
🧬 Cimetidine — May modestly increase penciclovir levels through renal transport effect. Generally clinically insignificant.
🧬 Digoxin — Famciclovir modestly increases digoxin levels (approximately 20% increase). Not typically clinically significant but monitor in patients on narrow digoxin therapeutic index.
⚠️ Nephrotoxicity considerations
💉 Aminoglycosides — Gentamicin, tobramycin, amikacin - concurrent use with high-dose famciclovir may increase nephrotoxicity risk. Adequate hydration important.
💉 NSAIDs — Ibuprofen, naproxen, other NSAIDs - especially in elderly, dehydrated, or those with reduced renal function - concurrent use may increase nephrotoxicity risk. Consider alternative pain management.
💉 Vancomycin — Concurrent use with high-dose IV vancomycin may increase nephrotoxicity risk. Monitor renal function.
💉 Contrast agents — Iodinated radiologic contrast agents can be nephrotoxic. Adequate hydration and delaying non-urgent contrast studies during high-dose Virovir therapy in at-risk patients.
💉 Calcineurin inhibitors — Cyclosporine, tacrolimus - nephrotoxic; commonly used with famciclovir in transplant recipients. Standard combination requires renal function monitoring.
✅ Overall interaction summary: Virovir has one of the cleanest interaction profiles of any commonly prescribed medication. Absence of CYP450 involvement means minimal interaction concerns with the vast majority of concomitant medications. Primary considerations are renal transport interactions and additive nephrotoxicity - both manageable with attention to renal function and hydration.
👤 Practical framework: before prescribing Virovir, brief medication review checking for probenecid, aminoglycosides, high-dose NSAIDs, or other nephrotoxic combinations - especially in elderly or patients with existing renal impairment. In most cases, no special adjustments needed. This clean interaction profile makes Virovir easy to prescribe safely across diverse polypharmacy scenarios.
🌍 Compared to other antivirals: famciclovir clean interaction profile compares favorably to HIV antiretrovirals (many CYP450 interactions) and antifungals (azole CYP450 interactions). Well-suited to polypharmacy scenarios - elderly patients, transplant recipients, cancer patients.
🤰 Pregnancy Considerations for Famciclovir
🤰 Famciclovir pregnancy safety data is more limited than acyclovir or valacyclovir. Available registry and observational data are reassuring but the smaller database means acyclovir or valacyclovir are typically preferred in pregnancy. Famciclovir generally reserved for pregnancy when preferred alternatives are contraindicated.
👶 Pregnancy safety evidence
📊 Famciclovir Pregnancy Registry — Manufacturer-maintained pregnancy registry documented hundreds of pregnancies exposed to famciclovir. No specific pattern of birth defects identified. Smaller database than acyclovir/valacyclovir registries.
📊 Observational studies — Population-based observational studies including from Scandinavian registries have not identified consistent teratogenic signal with famciclovir. Reassuring but limited data.
📊 Animal studies — No consistent teratogenicity in animal reproductive studies. Consistent with lack of clinical signal.
✅ Modern regulatory position — Famciclovir can be used in pregnancy when clinically indicated. FDA replaced letter categories with narrative pregnancy sections. Available safety data limited but reassuring within its scope.
📋 Practical pregnancy framework
✅ Acyclovir/valacyclovir preferred in pregnancy — Standard practice favors acyclovir or valacyclovir for HSV in pregnancy given more extensive safety database. Extensive registry data over 30+ years supports use.
💔 HSV suppression near delivery — Standard obstetric practice uses acyclovir or valacyclovir starting at 36 weeks gestation for pregnant women with recurrent genital HSV. Famciclovir not typically used in this scenario.
💀 Shingles in pregnancy — Shingles in pregnancy is uncommon. Where occurs and antiviral therapy needed, acyclovir or valacyclovir typically preferred. Famciclovir alternative if others contraindicated.
👄 Cold sores in pregnancy — Herpes labialis in pregnancy - self-limited. Antiviral treatment optional. If treatment desired, acyclovir/valacyclovir preferred over famciclovir.
👤 Considered alternative when others contraindicated — Hypersensitivity or intolerance to acyclovir/valacyclovir - famciclovir may be considered. Cross-reactivity possible but sometimes tolerated differently.
👤 Consideration in specific scenarios — Individualized clinical decision - benefit-risk assessment for the specific pregnant patient scenario. Coordinate with obstetric provider.
👤 Coordination and monitoring
👤 Coordination with obstetrics — Famciclovir use in pregnancy should be coordinated with obstetric provider. Timing of initiation, delivery planning, and postpartum considerations require obstetric input.
💉 No specific pregnancy dose adjustment — Standard dosing appropriate. Pregnancy does not require dose modifications beyond standard indication-based dosing.
📊 Renal function — Pregnancy typically increases renal function (higher GFR) so accumulation risk is reduced. Standard doses appropriate.
💓 Report to pregnancy registry — Encourage patient participation in pregnancy registries to expand safety database for future patients.
💓 Neonatal HSV prevention: Neonatal HSV is a devastating disease with high mortality and morbidity. Preventing maternal genital HSV recurrence at delivery is a key clinical goal - typically achieved with acyclovir or valacyclovir suppression, not famciclovir.
🤝 Practical framework: for pregnant patient - prefer acyclovir/valacyclovir first-line if HSV/VZV therapy indicated; famciclovir as alternative when preferred options contraindicated; coordinate with obstetric provider; individualized benefit-risk assessment; encourage pregnancy registry participation. Structured approach supports both mother and infant health.
🍼 Breastfeeding Considerations for Virovir
🍼 Famciclovir breastfeeding safety data is more limited than acyclovir or valacyclovir. Available limited data suggests penciclovir passes into breast milk in modest amounts. Acyclovir/valacyclovir generally preferred during breastfeeding when HSV/VZV therapy indicated.
👶 Breastfeeding safety profile
📊 Penciclovir in breast milk — Limited data - penciclovir passes into breast milk. Milk-to-plasma ratio in animal studies suggests modest transfer. Very limited human data.
👶 Infant exposure — Estimated infant exposure low but exact quantification limited by available data. Penciclovir oral bioavailability is very low (~5%) so infant systemic exposure likely minimal.
❓ Limited clinical experience data — Less extensive clinical experience during breastfeeding than acyclovir/valacyclovir. Adverse effects on breastfed infants not consistently reported but database smaller.
🌍 Professional society considerations — Acyclovir/valacyclovir preferred during breastfeeding where practical given more extensive safety data. Famciclovir alternative when preferred options contraindicated.
💉 Standard dosing appropriate — No specific dose adjustment for breastfeeding. Standard indication-based dosing continues.
💓 Practical breastfeeding considerations
✅ Prefer acyclovir/valacyclovir if possible — For breastfeeding mothers requiring HSV/VZV therapy, acyclovir or valacyclovir typically preferred given more extensive safety database.
👤 Famciclovir if preferred alternatives contraindicated — Hypersensitivity or intolerance to acyclovir/valacyclovir - famciclovir reasonable alternative during breastfeeding.
👄 HSV lesion location matters — Cover any breast, chest, or nipple HSV lesions to prevent direct infant contact. Direct contact with active HSV lesions is the transmission risk - not breast milk itself.
💔 Hand hygiene essential — Mothers with any active HSV lesions - particularly genital or oral - should practice meticulous hand hygiene before handling infant.
👄 No kissing infant during cold sores — Mothers with active herpes labialis should avoid kissing infant on mouth, face, or body until lesions are fully healed. Neonatal HSV infection from maternal cold sore can occur through direct contact.
💀 Maternal shingles considerations — Mothers with shingles may continue breastfeeding. Cover active zoster lesions to prevent infant contact.
✅ Bottom line: for breastfeeding mothers requiring HSV/VZV therapy, acyclovir or valacyclovir typically preferred over famciclovir given more extensive safety database. Famciclovir reasonable alternative when preferred options contraindicated. Standard breastfeeding infection control (covering lesions, hand hygiene) applies regardless of antiviral choice.
🤝 Practical framework: for nursing mother needing HSV/VZV therapy - consider acyclovir/valacyclovir first-line; famciclovir as alternative when preferred contraindicated; continue breastfeeding; cover any HSV lesions especially on breast/chest; meticulous hand hygiene; no need for special feeding schedule adjustment. Straightforward compatibility with attention to preferred agent selection.
📋 Common Adverse Effects Well-Tolerated Profile
📋 Virovir is remarkably well-tolerated - one of its clinical strengths. Adverse effects are typically mild and self-limited. Most patients complete therapy without needing to discontinue or modify treatment. The excellent tolerability profile derives from mechanism-based selectivity that limits effects on uninfected cells.
📊 Common adverse effects overview
| Adverse effect | Frequency | Severity |
|---|---|---|
| Headache | Approximately 20-40% (most common) | Usually mild-moderate; self-limited |
| Nausea | Approximately 3-13% | Usually mild; may improve with food |
| Diarrhea | Approximately 2-9% | Usually mild; supportive care |
| Fatigue | Approximately 3-6% | Mild |
| Vomiting | Approximately 1-5% | Usually mild |
| Abdominal pain | Approximately 3-8% | Usually mild |
| Dizziness | Approximately 1-5% | Mild; typically transient |
| Rash | Less than 3% | Usually mild; rare severe skin reactions (see section 29) |
| Elevated transaminases | Less than 3% | Usually mild and reversible |
🎯 Managing common adverse effects
🤕 Headache — Most common. Usually mild-moderate. Acetaminophen preferred over NSAIDs in patients with renal considerations. Adequate hydration reduces headache frequency. Rest and standard headache measures.
🤢 Nausea — Common. Usually mild. Taking Virovir with food often reduces nausea. Small frequent snacks. Antiemetic rarely needed for episodic Virovir therapy.
💩 Diarrhea — Uncommon. Usually mild and self-limited. Supportive care with oral rehydration. Anti-diarrheal medications (loperamide) if needed. Consider alternative etiology if severe or prolonged.
🤮 Vomiting — Uncommon. May affect ability to keep Virovir down. Antiemetic support and hydration. Reassess ability to tolerate oral therapy.
🥵 Dizziness/lightheadedness — Uncommon and mild. Adequate hydration helps. Rise slowly. Consider whether dose adjustment needed if patient has renal impairment.
😪 Fatigue — Common but often related to underlying HSV/VZV illness. Usually improves as infection resolves.
💥 Abdominal pain — Usually mild. Distinguish from more serious abdominal etiology if severe.
🎯 Well-tolerated profile in perspective
🔑 The mechanism-based selectivity produces remarkable clinical safety:
- 🔑 Most patients complete therapy - discontinuation for adverse effects uncommon
- 🔑 Comparable tolerability to acyclovir and valacyclovir
- 🔑 Mechanism-based selectivity means minimal effect on uninfected cells
- 🔑 Clean drug interaction profile means fewer interaction-related adverse effects
- 🔑 Excellent long-term tolerability supports use for years-long suppression
- 🔑 Serious adverse effects rare - mostly limited to renal/CNS with excessive dosing or inadequate renal adjustment
👤 Individual variation: some patients tolerate Virovir without any noticeable effects; others experience mild headache or nausea. Adverse effect profile often improves after first few doses. Individual variation is substantial.
🤝 Practical counseling: counsel patients that most experience minimal or no adverse effects. Common effects (headache, mild nausea) typically resolve without treatment. Any severe effects, mental status changes, decreased urine output, or unusual symptoms warrant medical attention. Serious adverse effects will be discussed in detail in subsequent sections.
🚨 Virovir Side Effects Navigation Guide
🚨 Understanding the Virovir safety framework benefits from structured navigation of the specific adverse effect categories. This section provides an anchor navigation guide before detailed discussion in subsequent sections (23-33). Focus areas include renal considerations, CNS effects, elderly-specific considerations, immunocompromised considerations, and other specific effect categories.
🗺️ Virovir adverse effect navigation map
🤢 Section 23 - Nausea, headache, common effects — The most common but least severe adverse effects. Predominantly mild and self-limited. Managed with supportive care.
🫀 Section 24 - Renal effects and considerations — Critical safety consideration particularly with high doses or preexisting renal impairment. Prevention through hydration and dose adjustment.
🧠 Section 25 - CNS effects and neuropsychiatric considerations — Rare but concerning adverse effects including confusion, hallucinations, delirium. Most often occur with elevated penciclovir levels from inadequate renal dose adjustment.
👴 Section 26 - Elderly-specific considerations — Elderly patients have elevated risk of both CNS effects and renal effects due to age-related renal decline. Structured framework for elderly-specific management.
🛡️ Section 27 - Immunocompromised patient special considerations — Special safety considerations in severely immunocompromised patients including elevated resistance risk.
🧬 Section 28 - HIV coinfection considerations — HIV-infected patients with HSV are common target population. Higher doses per specific labeling.
🧪 Section 29 - Skin reactions and cutaneous effects — Rare severe skin reactions including Stevens-Johnson syndrome and toxic epidermal necrolysis (very rare). More common mild skin effects.
🪶 Section 30 - Hepatic effects — Uncommon transient transaminase elevations. Rare severe hepatic adverse effects.
🧬 Section 31 - Hematologic effects and considerations — Rare hematologic effects including thrombocytopenia and other cytopenias.
☠️ Section 32 - Overdose considerations — Overdose management approach. Penciclovir is dialyzable - hemodialysis can accelerate elimination in significant overdose.
🔬 Section 33 - HSV resistance framework — Antiviral resistance - rare in immunocompetent patients, more common with prolonged therapy in immunocompromised. Cross-resistance patterns with acyclovir/valacyclovir.
🎯 Overall Virovir safety framework
✅ Excellent overall tolerability — Virovir is one of the best-tolerated antivirals in clinical practice. Most patients experience minimal or mild adverse effects. Long-term suppression tolerated well.
🫀 Renal function is central to safety — The most important safety consideration is appropriate dose adjustment for renal function. Elderly patients, chronic kidney disease patients, and those with acute reduced renal function are at higher risk.
💧 Hydration protects against complications — Adequate hydration is a universal recommendation supporting renal elimination.
👤 Immunocompromised patients need special attention — Immunocompromised patients face somewhat elevated risk of resistance emergence. Additional monitoring appropriate.
💑 Reassuring for most patients — For the vast majority of Virovir users - healthy adults with normal renal function taking standard doses - Virovir is remarkably safe.
🤝 Clinical utility of this navigation: the following sections provide detailed information about each specific adverse effect category. This structured approach supports clinical decision-making about patient selection, monitoring, and management. Understanding the full safety framework enables optimal Virovir use across the diverse patient populations who benefit from HSV/VZV therapy.
🤢 Nausea Headache and Common Effects
🤢 Nausea, headache, and other mild gastrointestinal and general effects are the most frequently reported Virovir adverse effects. These effects are typically mild, self-limited, and manageable with supportive care. Understanding their characteristics and management supports patient counseling and treatment adherence.
🤕 Headache
📊 Frequency — Headache is the most common adverse effect - reported in approximately 20-40% of Virovir users depending on regimen and study. Higher frequency than acyclovir/valacyclovir headache reports. Usually mild to moderate intensity.
🕐 Character — Typically bilateral, mild-moderate, tension-type quality. Distinguish from shingles-related pain (unilateral, dermatomal, more severe) or HSV-related headache.
💊 First-line management — Acetaminophen preferred over NSAIDs given renal considerations with concurrent Virovir. Standard dosing (500-1000 mg every 6 hours as needed) usually adequate.
💧 Hydration considerations — Adequate hydration supports penciclovir renal elimination and often reduces headache frequency.
🚨 Red flag headache features — Severe unusual headache, new focal neurological findings, confusion, or headache with mental status changes warrant evaluation for possible penciclovir CNS effects (see section 25).
🤢 Nausea and gastrointestinal effects
📊 Nausea frequency — Nausea occurs in approximately 3-13% of Virovir users. Usually mild. More common with higher dose regimens (shingles TID or single-dose cold sore 1500 mg) than lower dose (250 mg suppression BID).
🕐 Onset and duration — Nausea typically starts within hours of first dose and may improve after several doses. May persist mildly throughout therapy in some patients.
🍽️ Management approach — Taking Virovir with food or snack reduces nausea for many patients. Small frequent meals, avoiding strong odors, and staying upright after doses help.
💉 Antiemetic use rare — Antiemetic medications (ondansetron, metoclopramide) are rarely needed for Virovir-related nausea. Reserve for severe cases.
🤮 Vomiting — Uncommon (~1-5%). If patient vomits within 30-60 minutes of dose, redose may be reasonable.
💩 Diarrhea — Uncommon (~2-9%). Usually mild and self-limited. Supportive care with oral rehydration. Anti-diarrheal medications (loperamide) if needed. Consider alternative etiology if severe or prolonged.
😪 Other common general effects
😪 Fatigue — Reported in approximately 3-6%. Often difficult to separate from underlying HSV/VZV infection. Usually improves as infection resolves.
🥵 Dizziness — Uncommon (~1-5%). Usually mild. Rise slowly from lying/sitting position. Consider whether dose adjustment needed for renal function.
🫀 Abdominal pain — Reported in approximately 3-8%. Usually mild diffuse or crampy discomfort.
👀 Photophobia and mild visual complaints — Uncommon. Usually resolve with treatment completion.
💜 Menstruation-related effects — Rare reports of dysmenorrhea. Not typically clinically significant.
👤 Individual variation is substantial: patients vary widely in their adverse effect experience. Many patients complete Virovir therapy with no noticeable effects. Others experience mild transient headache or nausea. Serious adverse effects requiring discontinuation are uncommon.
🤝 Practical framework: counsel patients that mild transient headache, nausea, and gastrointestinal effects are the most common Virovir experiences. Recommend taking with food if nauseous. Adequate hydration. Acetaminophen preferred for headache. Contact if severe effects, mental status changes, or unable to keep medication down. Reassure that most patients tolerate Virovir well.
🫀 Renal Effects and Considerations Framework
🫀 Renal effects are an important safety category for Virovir. Penciclovir (active metabolite) is eliminated primarily by kidneys and can accumulate substantially with reduced renal function. Prevention through appropriate dosing and hydration is the mainstay of renal safety.
🔬 Renal effects framework
🫀 Penciclovir accumulation — Reduced renal function causes penciclovir accumulation - plasma concentrations rise proportionally to renal impairment. Enhanced monitoring important.
🧠 CNS toxicity from accumulation — The primary manifestation of penciclovir accumulation is CNS toxicity (see section 25). Elevated levels cause confusion, hallucinations, delirium, tremor.
🗒️ Direct renal toxicity less prominent — Famciclovir does not cause crystal nephropathy in the same manner as acyclovir. Penciclovir is more water-soluble than acyclovir. However, renal effects can still occur at very high concentrations.
🔬 Rare reports of AKI — Acute kidney injury reports - uncommon but possible particularly in high-risk patients (elderly, dehydrated, preexisting CKD, concurrent nephrotoxic medications).
🔴 Risk factors — Elderly, dehydration, high doses, preexisting renal impairment, concurrent nephrotoxic medications, reduced urine output - all increase risk of penciclovir-related complications.
🛡️ Prevention framework
🫀 Appropriate dosing for renal function — Calculate estimated GFR before Virovir initiation and adjust dose per label criteria. This is the single most important preventive measure.
💧 Adequate hydration essential — Encourage generous fluid intake during Virovir therapy - particularly higher-dose regimens. Aim for good urine output.
👴 Elderly special attention — Elderly patients have age-related renal decline. Enhanced attention to hydration and dose adjustment essential.
💉 Avoid concurrent nephrotoxins — Where possible, avoid combining Virovir with other nephrotoxic agents. If combination necessary, monitor renal function closely.
📊 Baseline and monitoring labs — Baseline serum creatinine before extended Virovir therapy or in at-risk patients. Repeat during therapy if clinical concern.
🏥 Management of Virovir-associated renal effects
🔵 Discontinue or dose-adjust Virovir — Recognition of renal effects - discontinue or substantially reduce dose. Consider alternative therapy if HSV/VZV treatment still needed.
💧 Aggressive hydration — IV normal saline hydration to maintain urine output. Careful volume management to avoid overload in elderly or heart failure patients.
🫀 Nephrology consultation — Consider nephrology consultation for significant AKI. Renal ultrasound to exclude other causes.
🩸 Hemodialysis for severe cases — Penciclovir is well-removed by hemodialysis (~75% in 4-hour session). Consider dialysis for severe AKI with clinical need for rapid drug clearance.
📊 Follow-up monitoring — Track serum creatinine trend to document recovery. Most patients recover baseline renal function.
🚨 High-risk populations warranting enhanced attention: elderly patients; chronic kidney disease patients; diabetes; hypertension; concurrent nephrotoxic medications; volume depletion; recent contrast studies; sepsis. Enhanced monitoring and hydration attention in these populations.
🤝 Practical framework: for outpatient Virovir prescribing - check renal function; dose adjust per label; counsel on hydration importance; brief medication review for nephrotoxin combinations; monitor renal function during extended therapy. Simple prevention strategy dramatically reduces renal complication risk. Most patients complete Virovir therapy without any renal issues when this framework is followed.
🧠 CNS Effects and Neuropsychiatric Considerations
🧠 CNS adverse effects are uncommon but concerning Virovir safety considerations. They occur predominantly with elevated penciclovir plasma concentrations from inadequate renal dose adjustment. Presentations range from mild confusion to serious neurotoxicity including delirium and hallucinations.
🧠 Penciclovir neurotoxicity spectrum
🧠 Confusion and cognitive impairment — Most common CNS effect. Ranges from mild concentration difficulties to significant cognitive changes. More common in elderly and renally impaired patients. Usually reversible with drug discontinuation.
👁️ Hallucinations — Visual and sometimes auditory hallucinations - can occur with elevated penciclovir levels. Often frightening for patients. Typically resolve within days of drug discontinuation.
😰 Agitation and delirium — Delirium with disorientation, agitation, restlessness. More common in elderly with underlying cognitive vulnerability.
🤚 Tremor and myoclonus — Involuntary movements. Can be prominent feature in some patients.
🌊 Seizures — Rare but serious - seizures can occur with severe penciclovir neurotoxicity, particularly in patients with underlying seizure risk. Requires urgent management.
😒 Somnolence and lethargy — Reduced level of consciousness. Reversible with drug removal and time.
🔬 Risk factors for CNS toxicity
🫀 Reduced renal function — The primary risk factor. Inadequate dose adjustment for renal impairment causes penciclovir accumulation. Elderly and CKD patients particularly vulnerable.
👴 Advanced age — Elderly patients have age-related renal decline plus altered CNS drug sensitivity. Combination creates elevated risk.
📈 Excessive dosing — Overdose (accidental or intentional) or inadequate dose reduction cause elevated levels. Higher-dose regimens (shingles TID, cold sores 1500 mg single) carry more risk than suppression.
👤 Comorbid conditions — Preexisting cognitive impairment, dementia, cerebrovascular disease, hepatic encephalopathy may lower threshold for CNS effects.
💉 Concurrent CNS-active medications — Concurrent benzodiazepines, opioids, or other sedatives may amplify or complicate CNS effects.
🏥 Management framework
🔵 Immediate discontinuation — Stop Virovir upon recognition of significant CNS effects. Confusion, hallucinations, myoclonus, or delirium require immediate medical evaluation.
🫀 Assess renal function — Check serum creatinine and estimated GFR. Consider whether renal dose adjustment was adequate. Correct dehydration if present.
💧 Hydration and supportive care — IV hydration if inpatient. Support ventilation, prevent falls, delirium precautions.
🩸 Hemodialysis for severe cases — Hemodialysis effectively removes penciclovir and can accelerate recovery in severe neurotoxicity. Nephrology consultation for significant cases.
📊 Rule out alternative causes — Delirium in elderly has many causes - infection, dehydration, other medications, metabolic derangements. Comprehensive evaluation ensures penciclovir is confirmed cause.
🪶 Recovery expectations — Most patients recover fully over days to weeks after drug discontinuation. Slower elimination in renal impairment means delayed recovery. Hemodialysis accelerates recovery.
🌟 Prevention strategy summary: the vast majority of Virovir CNS effects are preventable through appropriate renal dose adjustment. Elderly patients and those with renal impairment should have estimated GFR calculated before prescribing and dose adjusted per label. Adequate hydration supports renal elimination.
🤝 Practical framework: counsel patients and families to watch for changes in mental status, hallucinations, unusual behavior, tremor, or unusual sleepiness. Report any of these promptly. Reassure that CNS effects are uncommon and reversible. Complete recovery is the typical outcome.
👴 Elderly-Specific Considerations Renal Focus
👴 Elderly patients receive Virovir frequently given shingles dominant incidence in older adults. Elderly-specific considerations combine age-related pharmacokinetic changes, elevated risk of both renal and CNS adverse effects, and higher rates of drug interactions and comorbidities.
📊 Elderly-specific safety considerations
🫀 Age-related renal decline — Estimated GFR declines predictably with age. By age 80, average GFR is 60-70% of young adult value. Dose adjustment essential.
🧠 Elevated CNS effects risk — Elderly brains more susceptible to drug-induced neurotoxicity. Combined with reduced renal clearance, elderly patients face substantially elevated risk of confusion, hallucinations, delirium.
💧 Hydration challenges — Elderly patients often have impaired thirst perception, medication-related fluid limitations, and reduced ability to communicate thirst. Dehydration is common.
💉 Polypharmacy considerations — Elderly patients typically take multiple medications. ACE inhibitors, ARBs, NSAIDs, diuretics often used concurrently affect renal function.
💀 PHN risk substantially elevated — Postherpetic neuralgia occurs in up to 30%+ of elderly shingles patients. Prompt Virovir initiation reduces PHN risk.
👁️ HZO more common — Herpes zoster ophthalmicus more common in elderly. Requires urgent ophthalmology involvement.
💉 Practical elderly prescribing framework
📊 Baseline renal assessment — Calculate estimated GFR before Virovir initiation using Cockcroft-Gault or CKD-EPI. Adjust dose per label.
💧 Emphasize hydration — Explicit counseling on adequate fluid intake. Involve family caregivers in hydration support.
💉 Review concurrent medications — Identify nephrotoxic combinations. Discuss NSAID limitation during Virovir therapy.
👤 Family involvement — Involve family or caregiver in medication management, hydration support, monitoring for mental status changes.
📊 Monitor during therapy — For extended therapy, periodic renal function assessment. Watch for changes in cognitive status.
🤕 Adjunctive pain management — Elderly shingles patients often need substantial pain support. Acetaminophen preferred first-line. Gabapentin or pregabalin for neuropathic pain. Cautious opioid use if needed. Avoid NSAIDs due to renal impact.
💉 Consider Shingrix vaccination — After acute shingles resolves, discuss Shingrix vaccination for future prevention. All adults 50+ recommended.
👤 Frailty considerations
👤 Assess overall frailty — Frail elderly patients warrant enhanced attention. Consider gerontology consultation for complex cases.
💉 Simplified regimens — Single-day cold sore regimen (1500 mg once) particularly convenient for frail elderly.
🏥 Care coordination — Elderly patients with shingles often have multiple providers. Care coordination supports optimal outcomes.
🏡 Home care considerations — Home health nursing for frail elderly with severe shingles supports wound care, medication administration, monitoring.
🌟 Reassurance about elderly use: despite elevated risk, the vast majority of elderly patients tolerate Virovir well and benefit from HSV/VZV therapy. Attention to renal function, hydration, and monitoring produces safe effective outcomes. Elderly should not be denied appropriate antiviral therapy.
🤝 Practical framework: for elderly patient - calculate GFR; adjust dose per label; counsel on hydration; involve family in support; review concurrent medications; provide adjunctive pain management; refer to ophthalmology if V1 involvement; discuss Shingrix after acute episode. Structured approach optimizes outcomes.
🛡️ Immunocompromised Patient Special Considerations
🛡️ Immunocompromised patients are common target populations for Virovir. Understanding the specific considerations for this population supports optimal HSV/VZV management including recognizing when famciclovir is appropriate and when alternative approaches may be needed.
🎯 Clinical considerations in immunocompromised patients
📈 More severe disease presentation — Immunocompromised patients often have more severe HSV/VZV presentations - extensive lesions, prolonged viral shedding, delayed healing, higher risk of dissemination.
💀 Disseminated infection risk — Disseminated shingles or HSV can occur in severely immunocompromised patients. IV acyclovir often needed rather than oral famciclovir since famciclovir has no IV formulation. Hospital admission and specialist consultation.
💊 Higher doses and longer duration — Extended treatment duration often needed. HSV suppression in HIV: 500 mg twice daily (higher than immunocompetent). Extended treatment (10-14 days) for severe HSV.
🔬 Resistance risk elevated — Antiviral resistance is more common in severely immunocompromised patients with prolonged treatment. TK-mutant HSV strains can emerge. Substantial cross-resistance with acyclovir/valacyclovir (same TK-dependent activation).
💉 Prophylaxis considerations — HSV/VZV prophylaxis with famciclovir possible in stem cell transplant recipients and other very-high-risk populations. Acyclovir/valacyclovir more commonly used for prophylaxis but famciclovir alternative.
📊 Monitoring considerations — Renal function monitoring given concurrent nephrotoxic medications common in transplant/cancer settings. CBC monitoring for cytopenias.
🏥 Specific transplant considerations
🍄 Stem cell transplant — Standard practice includes HSV prophylaxis starting from conditioning through engraftment. Acyclovir/valacyclovir more commonly used but famciclovir alternative per center protocols.
💛 Solid organ transplant — HSV prophylaxis or CMV prophylaxis common. Individualized by center protocols. Famciclovir occasionally used.
💉 Drug interactions with immunosuppressants — Famciclovir has minimal interaction with calcineurin inhibitors, mycophenolate, or mTOR inhibitors. Concurrent use is safe.
🔬 Resistance considerations in immunocompromised
🔬 When to suspect resistance — Poor clinical response to adequate famciclovir dosing in immunocompromised patient with previously responsive HSV/VZV. Recurrent progressive lesions despite therapy.
📊 Cross-resistance with acyclovir/valacyclovir — Substantial cross-resistance since all three drugs require viral TK for activation. TK-mutant strains typically resistant to all three.
💉 Alternative therapy — Foscarnet IV - first-line for acyclovir-resistant HSV/VZV since foscarnet works independent of viral TK. Cidofovir alternative.
👤 Address underlying immunodeficiency — Improve immune function where possible - antiretroviral optimization in HIV, reduce immunosuppression if possible in transplant. Immune reconstitution supports HSV control.
🌟 Balance of considerations: immunocompromised patients derive substantial benefit from famciclovir therapy for HSV/VZV. Enhanced monitoring and appropriate dose adjustments support safe effective use.
👤 Specialist involvement: infectious disease consultation often appropriate for complex immunocompromised HSV/VZV management.
🤝 Practical framework: for immunocompromised patient - individualized dose and duration; extended treatment often needed; monitor for response and resistance; awareness of dissemination risk (may need IV acyclovir); specialist involvement for severe or refractory cases; consider foscarnet if resistance suspected. Structured approach optimizes outcomes.
🧬 HIV Coinfection Considerations
🧬 HIV positive patients represent an important Virovir prescribing population given elevated HSV coinfection prevalence. Famciclovir has specific FDA-labeled indication for recurrent HSV in HIV positive patients with higher-dose regimen.
📊 HIV/HSV coinfection framework
📊 Prevalence — HSV-2 prevalence substantially elevated in HIV positive populations. Estimates 50-90% of HIV positive individuals also HSV-2 positive - much higher than general population 12-13%.
💔 Clinical presentation in HIV — HIV positive patients with HSV-2 often have more frequent recurrences, more severe outbreaks, prolonged lesion duration, and more asymptomatic shedding.
🔬 HSV amplifies HIV shedding — Active HSV lesions increase HIV viral shedding from genital tract. Amplifies HIV transmission risk. HSV coinfection is significant HIV transmission risk factor.
📈 HSV facilitates HIV acquisition — HSV-2 seropositivity approximately triples HIV acquisition risk in HIV-negative individuals exposed. HSV lesions provide portal of entry.
💊 Famciclovir dosing in HIV coinfection
💔 HSV genital episodic treatment — Famciclovir 500 mg twice daily for 7 days for episodic HSV treatment in HIV positive patients. Duration extended over immunocompetent 5-day or 1-day regimens.
💔 HSV suppression — Famciclovir 500 mg twice daily for HSV suppression in HIV positive patients - higher than immunocompetent dose (250 mg BID). Reflects more frequent recurrences in HIV.
💀 Shingles in HIV — Standard famciclovir 500 mg TID for 7-10 days. Severe or disseminated presentations may need IV acyclovir.
👄 Herpes labialis in HIV — May be more severe or persistent. Standard dosing with extended duration if needed.
🧪 Drug interactions with antiretrovirals
✅ Clean interaction profile with modern ART — Famciclovir has minimal interactions with modern antiretroviral therapy. Compatible with integrase inhibitors, NNRTIs, protease inhibitors, and NRTIs.
🔬 Zidovudine historical — Historical reports of lethargy with high-dose antiviral combinations. Modern zidovudine use limited.
🫀 Tenofovir considerations — Tenofovir DF has some nephrotoxic potential. Combination requires renal function monitoring but is generally safe.
💊 Modern single-tablet regimens — Modern single-tablet HIV regimens compatible with famciclovir. No dose adjustment needed.
🎯 Clinical management considerations
🔬 Test for HSV in HIV positive — HSV-1 and HSV-2 serology testing appropriate for HIV positive patients even without HSV symptoms. Identifies coinfection.
💔 HSV suppression consideration — HSV positive HIV positive patients often benefit from HSV suppression. Individual patient factors inform decision.
👤 Sexual partner considerations — HSV suppression can be part of comprehensive approach in serodiscordant partnerships. Combined with consistent condoms and PrEP for HIV-negative partners.
📈 Resistance monitoring — Antiviral resistance more common in HIV positive patients. If clinical failure, consider resistance testing and alternative therapy (foscarnet).
👤 Specialist involvement: HIV positive patients benefit from HIV specialist involvement in HSV management for complex or refractory cases.
🤝 Practical framework: for HIV positive patient with HSV - test HSV serology; discuss suppression benefits; use higher doses than immunocompetent (500 mg BID for suppression and episodic); coordinate with antiretroviral therapy; monitor renal function; extended treatment for outbreaks; consider resistance testing if refractory. Structured approach optimizes both HSV control and broader HIV care.
🧪 Skin Reactions and Cutaneous Effects
🧪 Skin reactions to Virovir range from common mild rashes to very rare severe cutaneous adverse reactions. The mild reactions typically require only observation; the rare severe reactions require immediate discontinuation and specialist involvement.
📋 Skin reaction spectrum
🔴 Mild rash — Reported in less than 3% of patients. Usually mild erythematous or maculopapular. Non-itching or mildly itchy. Typically self-limited without treatment.
💥 Pruritus (itching) — Occasionally reported. Usually mild and self-limited. Antihistamines can provide symptom relief.
🔴 Urticaria — Uncommon. Hives with itching. May reflect hypersensitivity. Discontinue if severe or accompanying systemic symptoms.
🔴 Angioedema — Rare but concerning. Face, lip, tongue, or throat swelling. Immediate discontinuation and emergency evaluation. Contraindication to future rechallenge.
🔴 Photosensitivity — Rare reports of photosensitivity reactions. Sun protection if photosensitive skin.
🚨 Severe cutaneous adverse reactions (rare)
☠️ Stevens-Johnson syndrome (SJS) — Very rare but life-threatening. Painful erythematous mucocutaneous lesions, blisters, epidermal detachment involving less than 10% BSA. Immediate discontinuation, hospitalization, specialist management.
☠️ Toxic epidermal necrolysis (TEN) — Extremely rare. Similar to SJS but greater than 30% BSA. Burn unit or specialized ICU care.
🔬 DRESS syndrome — Drug reaction with eosinophilia and systemic symptoms. Rare. Presents with rash, fever, eosinophilia, lymphadenopathy, organ involvement.
☠️ Erythema multiforme — Uncommon. Target-like lesions. Discontinue Virovir if suspected.
🚨 Extremely rare frequency — SJS/TEN with Virovir is exceedingly rare. Not on major SJS/TEN causative drug lists. When rare cases occur, rechallenge contraindicated permanently.
🛡️ Recognition and management
🚨 Warning signs to report — Patients should be counseled to report: extensive rash, painful skin lesions, blistering, mucosal involvement (mouth, eyes, genitals), fever with rash, facial swelling, or difficulty breathing. Immediate medical evaluation.
🔵 Immediate discontinuation — Suspicion of severe cutaneous reaction: stop Virovir immediately. Do not continue while evaluating.
🏥 Hospital-based management — SJS, TEN, DRESS require hospitalization and specialist management. Dermatology, ophthalmology (if eye involvement), critical care.
❌ No rechallenge — Patients with significant hypersensitivity reactions should never be rechallenged with famciclovir or penciclovir. Add to allergy list.
🔬 Cross-reactivity considerations — Hypersensitivity to famciclovir may indicate cross-reactivity to acyclovir/valacyclovir (similar guanosine analog structure). Careful clinical consideration if alternative HSV therapy needed.
✅ Reassuring frequency: the vast majority of Virovir users experience no skin reactions. Mild rashes when they occur are self-limited. Severe skin reactions are extremely rare - much less common than with many other medications.
👤 HSV lesions vs drug rash distinction: important to distinguish HSV/VZV disease lesions from drug rash. HSV/VZV lesions are typically dermatomal or genital and vesicular. Drug rash is more diffuse and morbilliform.
🤝 Practical framework: counsel patients about warning signs (extensive rash, blistering, mucosal involvement, fever, facial swelling). Report immediately if these occur. Reassure that severe skin reactions are extremely rare. Mild rashes usually self-limited.
🪶 Hepatic Effects and Monitoring Framework
🪶 Hepatic effects of Virovir are uncommon and typically mild. Transient transaminase elevations are the most frequent hepatic finding, usually asymptomatic and reversible. Serious hepatotoxicity is very rare.
📊 Hepatic effect spectrum
🔴 Transient transaminase elevations — Mild AST and ALT elevations reported in less than 3% of patients. Usually asymptomatic. Detected only on laboratory monitoring. Typically resolve.
🔴 Elevated bilirubin — Occasional mild hyperbilirubinemia. Usually asymptomatic. Rarely clinically significant.
🔴 Elevated alkaline phosphatase — Occasional mild elevations. Usually not clinically significant.
🪶 Symptomatic hepatitis — Rare. Presents with fatigue, abdominal discomfort, jaundice, dark urine. Usually resolves with drug discontinuation.
☠️ Fulminant hepatic failure — Exceedingly rare. Not typically associated with famciclovir. Severe cases warrant transplant hepatology consultation.
📋 Monitoring framework
📊 Routine monitoring not required — For standard short-course Virovir use, routine baseline or follow-up liver testing is not required. Hepatic effects are uncommon and predominantly mild.
📊 Consider baseline in extended use — For chronic suppression therapy over months to years, some clinicians obtain baseline hepatic panel. Periodic monitoring not strictly required but reasonable in patients with baseline liver disease.
📊 Enhanced monitoring in specific scenarios — Baseline and periodic monitoring appropriate for: patients with baseline chronic liver disease; concurrent hepatotoxic medications; severely immunocompromised patients on extended therapy.
🔴 Symptomatic monitoring — Investigate hepatic complaints during Virovir therapy - fatigue, abdominal pain, jaundice, dark urine. Hepatic panel to evaluate.
🎯 Management of hepatic abnormalities
📊 Mild transaminase elevations — Less than 3 times upper limit of normal: usually continue Virovir with monitoring. Often resolve.
📊 Moderate elevations — 3-5 times upper limit of normal: consider continued therapy with enhanced monitoring, or discontinue based on clinical scenario.
🔵 Significant elevations — Greater than 5 times upper limit of normal or symptomatic hepatitis: discontinue Virovir. Comprehensive hepatic evaluation. Consider hepatology consultation.
🪶 Rule out alternative causes — Hepatic abnormalities have many causes. Viral hepatitis (HBV, HCV, HEV), autoimmune hepatitis, drug-induced liver injury from other medications, alcohol, NAFLD progression. Do not attribute to Virovir without evaluation.
🪶 Rechallenge considerations — If Virovir is discontinued for hepatic abnormalities that resolve: rechallenge with careful monitoring possible if HSV/VZV therapy still needed. Alternative antivirals (acyclovir, valacyclovir) available.
💓 Underlying liver disease patients: patients with existing chronic liver disease can generally receive Virovir when HSV/VZV therapy indicated. No specific dose adjustment for hepatic impairment. Focus on renal function assessment and general clinical monitoring.
🤝 Practical framework: for typical Virovir prescribing - hepatic monitoring not routinely required; investigate symptomatic complaints; enhanced monitoring in patients with baseline liver disease; discontinue for significant elevations; evaluate for alternative causes. This structured approach supports safe use across diverse patient populations.
🧬 Hematologic Effects and Considerations
🧬 Hematologic effects of Virovir are uncommon. Rare reports of thrombocytopenia and other cytopenias exist. Understanding this framework supports appropriate monitoring in specific patient scenarios.
📋 Hematologic effect spectrum
🔴 Thrombocytopenia — Rare reports of thrombocytopenia. Usually mild. Rarely clinically significant bleeding.
🔴 Leukopenia and neutropenia — Rare reports. Usually mild. Rarely severe.
🔴 Anemia — Uncommon. Usually mild. Multifactorial in immunocompromised patients.
☠️ TTP/HUS reports — Very rare case reports of thrombotic microangiopathies with acyclovir/valacyclovir/famciclovir class. Historical concern primarily in severely immunocompromised patients on very high doses.
📋 Overall frequency low — Hematologic effects are uncommon in typical famciclovir use. Not a routine monitoring requirement.
📊 Monitoring framework
📊 Routine monitoring not required — For standard short-course Virovir use in immunocompetent patients, routine CBC monitoring is not required. Hematologic effects are uncommon.
📊 Consider baseline in specific scenarios — Baseline CBC appropriate for: severely immunocompromised patients on prolonged therapy; patients with baseline cytopenias; concurrent myelosuppressive medications.
📊 Symptomatic monitoring — Investigate unexpected bleeding, easy bruising, infection frequency, fatigue during Virovir therapy. CBC evaluation appropriate.
🔴 TTP/HUS recognition — Clinical features: thrombocytopenia, microangiopathic hemolytic anemia (schistocytes on smear), acute kidney injury, neurological changes, fever. Prompt hematology consultation if suspected.
🎯 Management framework
📊 Mild abnormalities — Continue Virovir with monitoring. Often resolve. Investigate contributing factors.
🔵 Significant cytopenias — Discontinue Virovir. Comprehensive hematologic evaluation. Consider alternative HSV/VZV therapy.
🔵 TTP/HUS suspected — Emergency evaluation and hematology consultation. Plasma exchange life-saving. Discontinue Virovir.
🔬 Rule out alternative causes — Cytopenias have many causes. Underlying disease, other medications, viral infections, autoimmune conditions. Do not attribute to Virovir without evaluation.
✅ Reassuring frequency: hematologic effects are not a major clinical concern for typical Virovir prescribing. The vast majority of patients experience no hematologic issues.
👤 Enhanced monitoring populations: severely immunocompromised patients on prolonged high-dose therapy warrant enhanced monitoring including periodic CBC. Historical TTP/HUS concerns primarily in this population.
🤝 Practical framework: hematologic monitoring not routinely required in typical Virovir prescribing; enhanced monitoring in severely immunocompromised patients; investigate symptomatic complaints; TTP/HUS rare but requires prompt recognition and specialist management. Structured approach supports safety while avoiding unnecessary monitoring.
☠️ Overdose Considerations and Management
☠️ Virovir overdose - accidental or intentional - is uncommon but can cause significant toxicity. Understanding overdose presentation, mechanism-based effects, and management framework supports appropriate emergency response.
📊 Overdose presentation and mechanism
📈 Toxic effects mechanism — Overdose causes very high penciclovir plasma concentrations that overwhelm renal elimination capacity. The primary toxicities relate to acute kidney injury and CNS effects.
🫀 Renal toxicity — Acute kidney injury from penciclovir accumulation. Rising serum creatinine over hours. Reduced urine output.
🧠 CNS toxicity — Neuropsychiatric effects including confusion, hallucinations, agitation, delirium, tremor, myoclonus, seizures. More severe with higher plasma levels.
🤢 Gastrointestinal — Nausea, vomiting, abdominal pain typically present.
❤️ Cardiovascular — Generally minimal direct cardiovascular effects. Hypotension possible from vomiting-related dehydration.
📊 Threshold for concern — Overdose severity varies by ingested amount, patient baseline renal function, and hydration status. Elderly, renal impaired, or dehydrated patients face lower toxicity threshold.
🏥 Management framework
🔵 Immediate assessment — Emergency evaluation upon overdose recognition. Assess airway, breathing, circulation. Neurological status. Vital signs. Establish IV access.
📊 Baseline laboratory studies — Serum creatinine, BUN, electrolytes, CBC, hepatic panel. Urinalysis. Consider drug levels if available.
💧 IV hydration mainstay — Generous IV normal saline hydration to maintain urine output and support renal elimination. Careful volume management in elderly or heart failure.
🔵 Discontinue Virovir — Obviously stop any further famciclovir administration. Verify no additional home supply accessible.
🩸 Hemodialysis for severe cases — Hemodialysis effectively removes penciclovir - approximately 75% removal in 4-hour session. Indications include severe AKI, severe CNS toxicity, seizures, or very high plasma levels.
🌊 Seizure management — Standard antiepileptic management if seizures occur. Benzodiazepines first-line. Address underlying penciclovir toxicity with hydration and consider dialysis.
🔵 Supportive care — Airway protection if severe CNS depression. Fall precautions. Delirium management.
👤 Intentional overdose — Intentional overdose warrants psychiatric evaluation. Address underlying mental health concerns.
📈 Recovery expectations
🪶 Renal recovery — Most patients recover baseline renal function over days to weeks with appropriate management. Rare cases of persistent impairment.
🧠 CNS recovery — CNS effects reversible with time as penciclovir clears. Full cognitive recovery typical over days. Hemodialysis accelerates recovery.
⚕️ Long-term outcomes — Most patients recover completely from famciclovir overdose with appropriate management. Fatalities from famciclovir overdose alone are exceedingly rare.
💓 Follow-up considerations — Discharge with follow-up - primary care for renal function monitoring, psychiatry if intentional.
👤 Poison control resource: Poison control centers can provide expert consultation on Virovir overdose management. Available 24/7. In the United States: 1-800-222-1222.
🤝 Prevention framework: for outpatient Virovir prescribing - counsel patients on correct dosing; do not double up for missed doses; store safely away from children; discuss access considerations in patients with mental health concerns.
🔬 HSV Resistance and Cross-Resistance Framework
🔬 HSV and VZV resistance to famciclovir is rare in immunocompetent patients but becomes an increasing concern in severely immunocompromised patients with prolonged therapy. Understanding resistance mechanisms, patterns, and management supports appropriate treatment when standard therapy fails.
🧪 Resistance mechanisms
🧬 TK-mutant HSV strains — Thymidine kinase (TK) mutations are the most common resistance mechanism. TK-deficient or TK-altered HSV cannot efficiently phosphorylate penciclovir, preventing conversion to active triphosphate. These strains essentially unresponsive to famciclovir.
🧬 TK mutations types — Include: (1) complete TK deficiency; (2) TK-altered - reduced activity or altered substrate specificity; (3) TK-partial.
🧬 Viral DNA polymerase mutations — Rarely, mutations in viral DNA polymerase can also confer resistance. Less common than TK mutations.
🔬 Emergence mechanism — Resistance emerges from viral quasispecies under drug selection pressure. Prolonged treatment with subtherapeutic drug levels or heavy viral loads (immunocompromised) provides selection environment.
📊 Resistance epidemiology
✅ Immunocompetent patients — Resistance is very rare in immunocompetent patients - less than 1%. Even with years of suppression therapy, immunocompetent patients rarely develop clinically significant resistance.
🔴 Immunocompromised patients — Resistance rates 5-30%+ in severely immunocompromised patients with prolonged treatment. Advanced HIV/AIDS, hematopoietic stem cell transplant populations at highest risk.
🔴 Extended treatment duration — Prolonged continuous therapy in immunocompromised - weeks to months - creates selection environment.
🔴 Subtherapeutic dosing — Inadequate dosing or poor adherence can promote resistance.
🔴 VZV resistance — Similar patterns for VZV - rare in immunocompetent, more common in prolonged treatment of immunocompromised.
🔬 Cross-resistance patterns
🧪 Famciclovir - Acyclovir cross-resistance — Substantial cross-resistance - both drugs require viral TK for activation. TK-mutant HSV resistant to acyclovir/valacyclovir typically also resistant to famciclovir.
🧪 Valacyclovir cross-resistance — Complete cross-resistance since valacyclovir is prodrug of acyclovir.
🧪 Ganciclovir/valganciclovir — Some cross-resistance since these also use viral TK for phosphorylation.
💉 Foscarnet — No cross-resistance - foscarnet works directly on viral DNA polymerase without requiring TK phosphorylation. Alternative for TK-mutant resistant HSV/VZV. IV administration only. Significant nephrotoxicity.
💉 Cidofovir — No cross-resistance in most cases. Cidofovir monophosphate directly active without viral kinase requirement. IV or intralesional use for severe resistant HSV. Significant nephrotoxicity.
🎯 Clinical management of suspected resistance
🔬 When to suspect — Poor clinical response to adequate famciclovir dosing in a patient with previously responsive HSV/VZV, particularly in immunocompromised patient with extended prior therapy.
📊 Diagnostic testing — Viral culture with resistance testing - phenotypic drug susceptibility testing. Available through specialty labs.
💉 Alternative therapy - Foscarnet — Foscarnet IV is first-line alternative for confirmed TK-mutant HSV/VZV. Requires hospitalization and IV access. Significant nephrotoxicity requires careful monitoring.
💉 Alternative therapy - Cidofovir — Cidofovir reserved for foscarnet-refractory or intolerant cases. IV or topical/intralesional. Also nephrotoxic.
👤 Address underlying immunodeficiency — Improve immune function where possible. Immune reconstitution supports HSV control.
✅ Reassurance for typical prescribing: resistance is not a meaningful clinical concern for the vast majority of Virovir prescribing. Standard immunocompetent HSV/VZV treatment maintains high efficacy.
🤝 Practical framework: for standard Virovir prescribing in immunocompetent patients - resistance not a concern; standard dosing and duration; expect good clinical response. For immunocompromised patients with recurrent or refractory HSV/VZV - consider resistance; specialist consultation; resistance testing; foscarnet or cidofovir alternatives. Awareness supports appropriate management when needed.
📈 Monitoring Framework for Virovir Therapy
📈 Virovir monitoring is relatively minimal compared to many other medications reflecting the excellent safety profile in typical patient populations. The monitoring framework focuses on renal function assessment, appropriate dose adjustment, and clinical vigilance for uncommon adverse effects.
📊 Baseline monitoring
🫀 Renal function assessment — Serum creatinine and estimated GFR calculation before Virovir initiation in: (1) elderly patients (age 65+); (2) known chronic kidney disease; (3) diabetes; (4) hypertension with target organ effects; (5) concurrent nephrotoxic medications; (6) any acute illness suggesting impaired renal function.
📊 When routine baseline not required — Healthy young adult for short-course episodic therapy (cold sores single-dose, occasional genital HSV, mild shingles) - baseline monitoring not routinely required unless risk factors present.
🪶 Hepatic panel — Not routinely required. Consider in patients with known chronic liver disease.
🧪 CBC — Not routinely required. Consider baseline in immunocompromised patients or those on high-dose extended therapy.
👤 Clinical assessment — Comprehensive clinical assessment including medication reconciliation, HSV/VZV history, adherence potential.
📅 During therapy monitoring
📊 Short-course therapy — For short-course episodic therapy in immunocompetent patients: no routine monitoring during therapy. Follow-up if adverse effects occur.
📊 Extended suppression therapy — For chronic HSV suppression (indefinite duration): periodic renal function assessment - typically annually. More frequent if renal risk factors.
📊 Immunocompromised patients — Enhanced monitoring including renal function, CBC, hepatic panel at intervals appropriate to clinical scenario.
📊 Clinical response monitoring — Assess clinical response to therapy - lesion healing, symptom resolution. Adequate response confirms appropriate therapy.
📊 Adverse effect monitoring — Ask about adverse effects at follow-up visits. Headache, nausea, dizziness, rash, cognitive symptoms.
🎯 Special population monitoring
👴 Elderly patients — Enhanced attention to renal function, hydration status, cognitive changes. Baseline and periodic renal assessment.
🫀 Chronic kidney disease — Baseline renal assessment, dose adjust per label, more frequent monitoring.
🧬 HIV positive patients — Coordinate with HIV care. Monitor CD4 counts. Evaluate HSV treatment response given elevated recurrence rates.
💛 Transplant patients — Coordinate with transplant team. Monitor renal function.
🤰 Pregnant patients — Prefer acyclovir/valacyclovir; if famciclovir used, coordinate with obstetric provider.
📋 Follow-up framework
📅 Episodic therapy follow-up — Follow-up only if problems occur.
📅 Suppression therapy follow-up — Annual visits at minimum. Reassess outbreak pattern, side effects, need for continued therapy.
📅 Prescription renewals — Annual renewal visits support monitoring.
📅 Escalation triggers — Escalate care for: poor treatment response; severe adverse effects; renal function changes; cognitive changes; complicated HSV/VZV presentations.
✅ Overall monitoring philosophy: Virovir requires minimal formal monitoring in typical prescribing scenarios. This reflects excellent safety profile. Focus attention on appropriate dose adjustment for renal function.
🤝 Practical framework: for typical outpatient Virovir - baseline renal assessment in appropriate patients; dose adjust per label; counsel on hydration and adverse effect awareness; follow-up only if problems occur; annual assessment for chronic suppression. Simple structured approach supports safe effective use.
📦 Storage and Patient Counseling for Virovir
📦 Virovir storage and patient counseling are essential components of safe effective therapy. Simple straightforward storage requirements combined with clear patient counseling support treatment success and safety.
📦 Storage requirements
🌡️ Temperature — Store at 15-30 C (59-86 F) - controlled room temperature. Do not refrigerate. Do not freeze.
💧 Moisture and humidity — Keep container tightly closed. Protect from moisture. Do not store in bathroom cabinet.
☀️ Light protection — Keep in original container which provides light protection. Avoid direct sunlight.
👶 Child safety — Store safely away from children. Child-resistant packaging supports safety.
📅 Expiration date — Do not use past expiration date. Discard properly.
🗑️ Disposal — Pharmacy take-back programs preferred. Consult local guidelines.
📝 Patient counseling essentials
💊 Dosing instructions — Clear written dosing instructions - dose, frequency, duration. Reinforce indication-specific dosing. For episodic therapy, emphasize starting at prodrome for maximum benefit.
💧 Hydration importance — Emphasize adequate fluid intake during therapy. Particularly important for high-dose regimens (single-dose cold sore 1500 mg, shingles TID).
🍽️ Food considerations — Can be taken with or without food. Food may delay absorption but does not affect total exposure. If nauseous, taking with food often helps.
🔵 Missed doses — Take missed dose as soon as remembered. Skip if close to next scheduled dose. Do not double up.
🕑 Timing for suppression — For daily suppression, consistent daily timing supports adherence. Link to daily routine.
📋 Complete the course — Complete full treatment course as prescribed even if symptoms improve early.
🎯 Warning signs to report
🔴 Mental status changes — Report confusion, hallucinations, unusual behavior, severe drowsiness. Particularly important for elderly patients and family caregivers.
🔴 Reduced urine output — Substantial reduction in urine output may indicate developing renal impairment. Report promptly.
🔴 Severe rash or blistering — Extensive rash, painful skin lesions, blistering, mucosal involvement, facial swelling. Discontinue and seek immediate care.
🔴 Persistent vomiting — Unable to keep medication down. May affect therapy success.
🔴 Signs of dehydration — Very dark urine, dizziness, extreme thirst, dry mouth. Increase fluid intake. Contact provider if unable to maintain hydration.
🔴 Poor treatment response — Symptoms worsening or not improving as expected. Contact provider for evaluation.
💓 Living with HSV counseling
🤝 HSV is common and manageable — Reassure patients that HSV is very common - 500 million people globally with HSV-2. Manageable with therapy. Not defining of the person.
👤 Partner disclosure — Discuss disclosing HSV status to sexual partners - allows informed consent.
💊 Transmission risk reduction — Suppression therapy plus consistent condoms plus avoiding sex during outbreaks substantially reduces transmission risk.
💓 Emotional support — HSV diagnosis can cause psychological impact. Support groups, counseling, educational resources available.
🌟 Long-term outlook — Most people with HSV live full normal lives. Outbreaks often become less frequent over years. Suppression therapy can virtually eliminate outbreaks.
🤝 Practical framework: written instructions covering dosing, storage, hydration, warning signs, missed doses, and follow-up expectations. Reassure about excellent safety profile. Address questions and concerns. Simple structured counseling supports treatment success.
🌍 Cipla generic access considerations: Cipla generic Virovir provides affordable access to HSV/VZV therapy. Cost considerations often support treatment adherence and long-term suppression therapy where indicated.
🚫 Virovir Contraindications Absolute and Relative
🚫 Virovir contraindications are limited - reflecting the drug excellent safety profile. Understanding absolute and relative contraindications supports appropriate patient selection and safe prescribing across the diverse populations who benefit from HSV/VZV therapy.
🔴 Absolute contraindications
💀 Hypersensitivity to famciclovir or penciclovir — Prior severe hypersensitivity reaction (anaphylaxis, angioedema, Stevens-Johnson syndrome, toxic epidermal necrolysis, DRESS syndrome) attributed to famciclovir or penciclovir is an absolute contraindication to rechallenge.
💀 Hypersensitivity to inactive ingredients — Severe hypersensitivity to excipients in Virovir tablet formulation. Rare but should be considered.
💀 Cross-reactivity to acyclovir/valacyclovir — Patients with severe reactions to acyclovir/valacyclovir may have cross-reactivity to famciclovir given structural similarity. Careful consideration required. Avoidance often prudent.
🔵 Relative contraindications and cautions
🫀 Severe renal impairment without dose adjustment — Severe renal impairment (CrCl less than 30 mL/min) is not a contraindication but requires substantial dose adjustment. Failure to adjust dose creates unacceptable risk of CNS toxicity.
👴 Elderly with cognitive impairment plus renal impairment — Enhanced caution - not contraindication but requires careful dose adjustment, hydration support, and monitoring.
💧 Severe dehydration — Uncontrolled severe dehydration is a relative contraindication until hydration is restored.
💉 Concurrent nephrotoxic medications — Enhanced caution with concurrent nephrotoxic medications (aminoglycosides, high-dose NSAIDs). Monitor renal function closely.
🤰 Pregnancy - preferred alternatives available — Not contraindicated but acyclovir/valacyclovir preferred given more extensive pregnancy safety data. Famciclovir alternative when preferred contraindicated.
🍼 Breastfeeding - preferred alternatives available — Not contraindicated but acyclovir/valacyclovir preferred given more extensive breastfeeding safety data.
🔑 What is NOT a contraindication
✅ Concurrent HIV/AIDS — HIV positive patients including AIDS receive Virovir routinely with specific FDA-labeled indication.
✅ Concurrent hepatitis B or C — Not contraindication. Famciclovir has no antiviral activity against HBV/HCV but no specific hepatic contraindication.
✅ Mild to moderate renal impairment — Not contraindication. Requires dose adjustment per label.
✅ Advanced age — Not contraindication. Enhanced monitoring for renal function.
✅ Cardiovascular disease — Not contraindication. Famciclovir has no significant direct cardiovascular effects.
✅ Diabetes — Not contraindication. Monitor renal function which may be affected by diabetes.
✅ Hepatitis B or C infection — Not contraindication. Famciclovir does not treat HBV or HCV.
✅ Family history of HSV/VZV complications — Not relevant to individual patient contraindication.
🎯 Practical patient selection framework
📋 Confirm HSV or VZV diagnosis — Ensure diagnosis is HSV or VZV - other viral infections do not respond to famciclovir. Clinical diagnosis often sufficient for typical presentations.
👤 Screen for absolute contraindications — Prior hypersensitivity to famciclovir, penciclovir, acyclovir, or valacyclovir. Ask specifically about prior antiviral reactions.
🫀 Assess renal function — Calculate estimated GFR especially in elderly, CKD, diabetes, hypertension patients. Adjust dose per label.
💉 Review concurrent medications — Brief medication review for probenecid, concurrent nephrotoxins, other considerations. Most combinations safe.
🤰 Consider pregnancy/breastfeeding — Prefer acyclovir/valacyclovir if pregnant or breastfeeding. Famciclovir alternative when preferred contraindicated.
💓 Discuss expectations — Discuss expected treatment course, adherence importance, warning signs to report, and follow-up plan.
📈 Consider comprehensive care needs — Beyond antiviral therapy, consider pain management for shingles, psychological support for HSV, partner counseling for HSV-2, vaccination discussion.
✅ Overall safety framework: Virovir has limited absolute contraindications - primarily hypersensitivity. Relative contraindications are manageable with appropriate dose adjustment, hydration, monitoring, and clinical judgment. This favorable safety profile enables Virovir use across diverse patient populations.
👤 Compare to alternatives: famciclovir favorable contraindication profile compares favorably to foscarnet (significant nephrotoxicity) and cidofovir (nephrotoxicity, ocular effects). Similar to acyclovir/valacyclovir - the three main HSV/VZV antivirals share favorable safety profiles.
🤝 Practical framework: for typical Virovir prescribing scenarios - screen for hypersensitivity history; assess renal function; brief medication review; standard patient counseling; adjust dose as indicated. This structured approach supports safe effective use in the vast majority of patients who benefit from HSV/VZV therapy.
Virovir — Frequently Asked Questions
-
What is Virovir (Famciclovir) used for?
Virovir is used to treat infections caused by herpes viruses, including shingles (herpes zoster), genital herpes (herpes simplex virus type 2), and cold sores (herpes labialis). -
How does Virovir work?
Virovir works by inhibiting the replication of viral DNA, which helps to reduce the severity and duration of herpes outbreaks. -
How should I take Virovir?
Virovir should be taken as prescribed by your healthcare provider, usually with a full glass of water, and can be taken with or without food. -
What should I do if I miss a dose?
If you miss a dose, take it as soon as you remember. If it is almost time for your next dose, skip the missed dose and continue with your regular schedule. Do not double the dose to catch up. -
Can I take Virovir with alcohol?
While moderate alcohol consumption is generally acceptable, it is best to consult your healthcare provider as alcohol can increase the risk of side effects such as dizziness. -
How quickly does Virovir start working?
Virovir typically starts working within 24 to 48 hours. It is most effective when taken at the first sign of an outbreak. -
Are there any common side effects of Virovir?
Common side effects include headache, nausea, diarrhea, and fatigue. These are usually mild and temporary.
See all Virovir questions (32)
📚 Drug Description Sources:
The information in this Virovir (famciclovir) guide is compiled from authoritative pharmaceutical, medical, and regulatory sources covering famciclovir clinical use as a prodrug of penciclovir, herpes simplex virus (HSV) and varicella-zoster virus (VZV) treatment guidelines, the historical SmithKline Beecham development, and the modern Cipla generic access framework supporting global availability of this important HSV/VZV antiviral alternative.
🏛️ Regulatory and government agencies
- FDA (US Food and Drug Administration) - Famvir (famciclovir) approval June 1994 for herpes zoster and subsequent HSV indications; label updates through years
- CDC (Centers for Disease Control and Prevention) - HSV treatment guidance in STI Treatment Guidelines; shingles management guidance
- WHO (World Health Organization) - HSV management guidance; antiviral therapy framework
- EMA (European Medicines Agency) - famciclovir European regulatory framework across HSV and VZV indications
- SmithKline Beecham (originally) - innovator sponsor; famciclovir developed as improved oral bioavailability alternative to earlier antivirals
- Novartis Pharmaceuticals - subsequent marketing of Famvir (branded famciclovir) after GSK/Novartis product exchange
- Cipla Limited - Indian generic manufacturer of Virovir product available on RXshop
- DailyMed (NIH/NLM) - current famciclovir prescribing information
📚 Professional societies and clinical guidelines
- Infectious Diseases Society of America (IDSA) - HSV and VZV clinical guidance
- CDC STI Treatment Guidelines - genital herpes management recommendations including famciclovir option
- American Academy of Dermatology (AAD) - herpes labialis and shingles treatment guidance
- American Academy of Ophthalmology (AAO) - herpes zoster ophthalmicus management
- European Herpes Management Forum - European herpes management guidance
- International Herpes Management Forum (IHMF) - global herpes clinical guidance
- Advisory Committee on Immunization Practices (ACIP) - shingles vaccination context
🔬 Landmark clinical research
- Vere Hodge et al. penciclovir discovery and famciclovir development - SmithKline Beecham foundational chemistry establishing famciclovir as penciclovir prodrug
- Tyring et al. 1995 famciclovir shingles pivotal trial - established famciclovir efficacy for herpes zoster comparable to acyclovir
- Sacks et al. famciclovir recurrent genital herpes trials - Canadian HSV research establishing famciclovir efficacy in HSV-2
- Spruance et al. 2006 single-day famciclovir cold sores trial - established one-day 1500 mg regimen for herpes labialis
- Bodsworth et al. HIV/HSV suppression trials - famciclovir in HSV coinfection management
- Chosidow et al. famciclovir recurrent herpes labialis trials - French research on recurrent cold sores
- Boon et al. penciclovir intracellular pharmacology - characterized the prolonged intracellular half-life advantage
📖 Medical references and platforms
- Mandell Douglas and Bennett Principles and Practice of Infectious Diseases - herpes and varicella-zoster virus infections
- Fields Virology - HSV and VZV molecular biology and antiviral mechanisms
- Goodman and Gilman Pharmacological Basis of Therapeutics - antiviral pharmacology including famciclovir
- Fitzpatrick Dermatology in General Medicine - HSV and VZV cutaneous manifestations
- UpToDate - famciclovir monographs across HSV and VZV indications
- Lexicomp and Micromedex - drug interactions and dosing references
- Sanford Guide to Antimicrobial Therapy - practical antiviral prescribing reference
Note: This information is educational and does not replace consultation with qualified healthcare providers. Famciclovir treatment planning requires clinical assessment given renal dose adjustment needs, specific indication-based dosing, and considerations for immunocompromised patients where additional monitoring applies.
🩺 Medical Expert Review:
Content based on the published research and clinical practice of herpes simplex virus (HSV) and varicella-zoster virus (VZV) authorities with expertise spanning famciclovir clinical trials, HSV/VZV virology, and modern antiviral therapy positioning. The following experts represent authoritative international perspectives on famciclovir role and HSV/VZV clinical management across diverse patient populations.
Prof. Tony Cunningham, AM, MBBS, MD, FRACP, FRCPA
Director, Centre for Virus Research, Westmead Institute for Medical Research; Professor of Medicine, University of Sydney — Sydney, Australia
Prof. Cunningham is an internationally recognized HSV and VZV research authority. His extensive work spans HSV pathogenesis, immunology, vaccine development including landmark contributions to Shingrix (recombinant zoster vaccine) development, and antiviral therapy. He has been principal investigator on numerous international HSV/VZV clinical trials shaping modern practice.
Prof. Judith Breuer, MBBS, MD, FRCP, FRCPath
Professor of Virology, Division of Infection and Immunity, University College London; Consultant Virologist, Great Ormond Street Hospital — London, UK
Prof. Breuer is one of the world leading VZV and HSV virology authorities. Her research contributions span VZV molecular epidemiology, HSV pathogenesis, antiviral resistance mechanisms, and clinical virology. Her work has substantially informed understanding of HSV/VZV epidemiology, resistance patterns, and clinical management shaping current antiviral prescribing practice.
Prof. Kimberly A. Workowski, MD, FACP
Professor of Medicine, Division of Infectious Diseases, Emory University School of Medicine; Lead Author, CDC Sexually Transmitted Infections Treatment Guidelines — Atlanta, USA
Prof. Workowski is a leading US sexually transmitted infection authority whose work has substantially informed national STI clinical guidelines including HSV treatment recommendations. As lead author of CDC STI Treatment Guidelines, she has shaped guidance on famciclovir and other HSV antivirals across US clinical practice.
Prof. Kenneth H. Fife, MD, PhD
Professor of Medicine, Division of Infectious Diseases, Indiana University School of Medicine — Indianapolis, USA
Prof. Fife is a leading HSV clinical trials investigator whose research has substantially contributed to famciclovir clinical development, HSV suppression therapy evaluation, and HSV vaccine research. He has been principal investigator on numerous HSV clinical trials directly informing famciclovir prescribing framework across HSV indications.
Prof. Willem J. G. Melchers, PhD
Professor of Clinical Virology, Department of Medical Microbiology, Radboud University Medical Center — Nijmegen, Netherlands
Prof. Melchers is a leading European clinical virology authority whose research spans HSV molecular diagnostics, antiviral susceptibility testing, and clinical virology. His contributions have informed European approaches to HSV clinical management including antiviral therapy selection and resistance evaluation.
Disclosure: Expert names and credentials are cited for educational reference. This content is not endorsed by named experts. Content prepared by RXshop editorial team based on published literature and clinical guidelines.
More Antiviral Medications




