Buy Dapavel (Dapagliflozin) Online - SGLT2 Inhibitor Generic to Lower Blood Sugar & Protect Heart and Kidneys


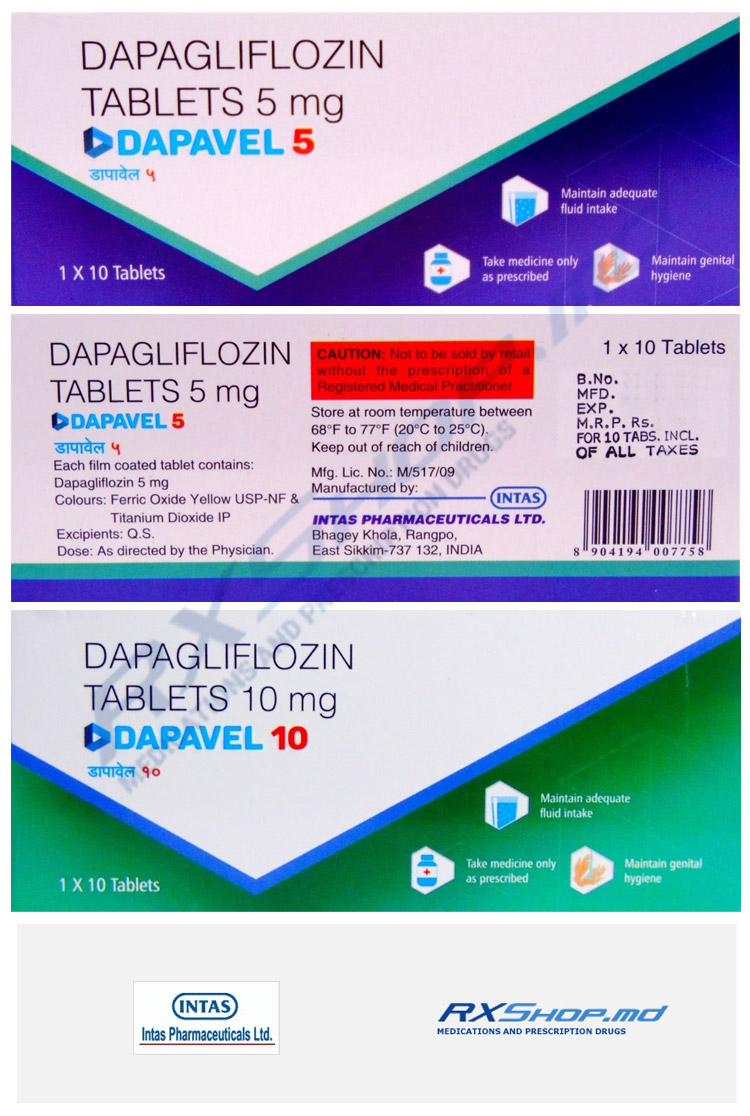
Dapavel (Dapagliflozin) represents an affordable generic version of brand Farxiga, manufactured by Indian pharmaceutical companies under the same chemical and therapeutic standards as original AstraZeneca formulation. As a selective SGLT2 inhibitor, Dapavel works through a unique kidney-based mechanism that excretes excess glucose through urine rather than stimulating insulin or reducing insulin resistance. The 5/10 mg oral tablets deliver consistent blood sugar control with proven cardiovascular and renal protective benefits across diverse patient populations.
Dapagliflozin works by selectively blocking sodium-glucose cotransporter 2 (SGLT2) in the proximal kidney tubules, preventing reabsorption of filtered glucose back into the bloodstream. This blockade causes approximately 60-80 grams of glucose to be excreted in urine daily, directly removing blood sugar without depending on insulin pathways. The result: HbA1c drops 0.5-0.9% from baseline, fasting blood glucose decreases 25-35 mg/dL, body weight reduces 2-3 kg through caloric loss in urine, and blood pressure drops 3-5 mmHg through mild diuretic effect.
Dapavel benefits from landmark cardiovascular and renal evidence. The DECLARE-TIMI 58 trial involving 17,160 patients demonstrated 17% reduction in heart failure hospitalization and significant cardiovascular mortality reduction. The DAPA-HF trial showed 26% reduction in cardiovascular death and heart failure events even in patients without diabetes, expanding dapagliflozin use beyond diabetes alone. The DAPA-CKD trial demonstrated 39% reduction in renal events in chronic kidney disease patients with or without diabetes, establishing dapagliflozin as a foundational therapy for heart failure, chronic kidney disease, diabetic nephropathy, and type 2 diabetes.
Dapavel offers convenient once-daily dosing taken any time of day with or without food, fitting seamlessly into any routine. The medication reaches peak blood concentrations within 2 hours and shows extended therapeutic action with 12.9-hour half-life. Generic dapagliflozin from quality Indian manufacturers provides identical therapeutic effects to original brand Farxiga by AstraZeneca at substantially lower cost. The active ingredient remains chemically identical across both branded and generic versions of this established type 2 diabetes and heart-kidney protection therapy.


Free prescription
Discrete packaging
Have questions?
Quality Assurance

- Type 2 Diabetes: Most common diabetes form where body resists insulin or makes insufficient amounts gradually;
- Type 2 Diabetes Mellitus: Full medical term for adult-onset diabetes characterized by insulin resistance and hyperglycemia;
- High Blood Sugar: Persistently elevated blood glucose levels above 126 mg/dL fasting causing organ damage;
- Blood Sugar: Glucose circulating in blood that cells use for energy through insulin-regulated uptake;
- Hyperglycemia: Medical term for abnormally elevated blood glucose levels above normal threshold values;
- Insulin Resistance: Body cells respond poorly to insulin requiring higher levels to control blood sugar;
- Heart Failure: Condition where heart cannot pump enough blood to meet body needs causing fatigue and edema;
- Heart Failure Reduced Ejection: Heart failure with reduced left ventricular ejection fraction below 40 percent;
- Heart Failure Preserved Ejection: Heart failure with preserved ejection fraction above 50 percent often in elderly;
- Heart Failure Non Diabetic: Heart failure treatment in patients without diabetes per DAPA-HF trial evidence;
- Chronic Kidney Disease: Long-term kidney function decline measured by reduced glomerular filtration rate;
- Diabetic Kidney Disease: Chronic kidney disease specifically caused by diabetes affecting filtration over years;
- Diabetic Nephropathy: Progressive kidney damage from diabetes causing protein loss and declining filtration function;
- Non Diabetic Kidney Disease: Chronic kidney disease in patients without diabetes per DAPA-CKD trial evidence;
- Diabetic Cardiovascular Risk: Elevated heart attack and stroke risk specifically associated with type 2 diabetes;
- Heart Attack Prevention: Reducing risk of coronary artery blockage that permanently damages heart muscle tissue;
- Diabetes Monotherapy: Single-drug treatment when type 2 diabetes can be controlled without combination therapy;
- Metformin Combination: Add-on to metformin when blood sugar remains above target on metformin alone;
- Insulin Combination Therapy: Combined with insulin in advanced diabetes when oral therapy alone is insufficient;
- Diabetic Obesity: Excess body weight common in type 2 diabetes requiring weight management through medication;
- SGLT2 Inhibitor Therapy: SGLT2 drug class treatment offering glycemic cardiovascular and renal benefits in diabetes.
- Lower A1C: HbA1c decreases 0.5-0.9% reflecting better long-term blood sugar control over 3 months;
- Lower Fasting Glucose: Morning blood sugar levels normalize through continuous urinary glucose excretion;
- Lower Post Meal Glucose: Blood sugar spikes after eating flatten through ongoing renal glucose elimination;
- Better Glycemic Control: Overall blood sugar management improves measurably reducing diabetes complication risk;
- Diabetic Weight Loss: Body weight decreases 2-3 kg through caloric loss in urine as excreted glucose;
- Lower Blood Pressure: Systolic blood pressure drops 3-5 mmHg through mild diuretic effect of glucose excretion;
- Less Heart Failure Hospitalization: Heart failure admission risk reduces 26-32% per DECLARE and DAPA-HF trial evidence;
- Less Cardiovascular Death Risk: Fatal cardiac event probability decreases 18% in long-term users with heart failure;
- Less Heart Attack Risk: Cardiovascular event probability drops in diabetic patients with established disease;
- Better Heart Function: Cardiac function improves measurably in heart failure patients regardless of diabetes status;
- Better Kidney Function: Glomerular filtration rate decline slows significantly preserving long-term kidney health;
- Slower Kidney Disease Progression: Chronic kidney disease advancement slows 39% per landmark DAPA-CKD trial;
- Less Diabetic Nephropathy: Diabetic kidney damage progression slows preserving filtration function over years;
- Lower Albuminuria: Protein leakage in urine decreases indicating less kidney filtration barrier damage;
- Less Insulin Need: Insulin injection requirement decreases or delays in patients on combination therapy;
- Less Hyperglycemia: Episodes of dangerously high blood sugar reduce significantly with consistent therapy;
- Less Diabetic Complications: Long-term damage to eyes kidneys and nerves decreases through better glucose control;
- Once Daily Convenience: Single tablet taken any time of day with or without food fits any routine easily;
- Better Quality of Life: Daily wellbeing improves from reduced symptoms stable energy weight loss and reduced hospitalization.
Generic Dapavel (Dapagliflozin 5 mg) Medication guide:
📖 What Dapavel Is and How It Works
Dapavel is the Intas Pharmaceuticals generic version of dapagliflozin, an SGLT2 inhibitor originally approved by the US FDA in January 2014 as Farxiga (AstraZeneca). Dapagliflozin has become one of the most widely prescribed SGLT2 inhibitors globally because of its expansion beyond diabetes into heart failure and chronic kidney disease regardless of diabetes status.
Dapavel at a glance
| Class | SGLT2 inhibitor (gliflozin) |
| Manufacturer | Intas Pharmaceuticals (Dapavel generic) |
| Original brand approval | 2014 as Farxiga by AstraZeneca |
| Available strengths | 5 mg and 10 mg tablets |
| Typical dose | 10 mg once daily |
| Half-life | Approximately 12.9 hours |
| HbA1c reduction | 0.5-0.9 percent |
| FDA-approved indications | Type 2 diabetes, HFrEF, HFpEF, CKD |
The mechanism is elegant. Dapagliflozin blocks the sodium-glucose cotransporter 2 (SGLT2) in the proximal renal tubule. This protein normally reabsorbs about 90 percent of glucose filtered into the kidney tubule. When blocked, glucose spills into the urine. Blood glucose falls. But the benefits extend well beyond glucose - modest diuresis, blood pressure reduction, weight loss, favourable cardiovascular metabolic shifts, and protection against heart failure and kidney disease progression.
What dapagliflozin does
Increases urinary glucose excretion by 70-80 grams daily. Blood glucose falls modestly. Weight decreases 2-3 kg. Blood pressure falls 3-5 mmHg systolic. Heart failure risk reduced substantially. Kidney disease progression slowed. Cardiovascular events reduced. Effects appear in both diabetic and non-diabetic clients.
Beyond diabetes - the expanded story
What distinguishes dapagliflozin (along with empagliflozin) from other diabetes drugs is the substantial evidence base outside diabetes. Four landmark trials shape modern use.
The four defining trials
- DECLARE-TIMI 58 (2019) - 17,160 type 2 diabetes clients; CV safety and 27 percent reduction in HF hospitalisation
- DAPA-HF (2019) - 4,744 HFrEF clients, diabetic AND non-diabetic; primary composite reduced 26 percent
- DAPA-CKD (2020) - 4,304 CKD clients, diabetic AND non-diabetic; primary composite reduced 39 percent
- DELIVER (2022) - 6,263 HFpEF clients; primary composite reduced 18 percent
Safety profile
Dapagliflozin is generally well-tolerated. Common side effects tie to the mechanism - genital mycotic infections, modest urinary tract infection increase, mild volume-related symptoms. Rare but serious concerns include diabetic ketoacidosis in specific settings and very rare Fournier gangrene. Unlike canagliflozin, dapagliflozin does NOT carry amputation or fracture signals - a substantial advantage.
Dapavel as generic
Dapavel contains the identical active dapagliflozin as the original Farxiga. Generic manufacturing by Intas Pharmaceuticals follows international bioequivalence standards. Clinical outcomes match the brand at substantially lower cost.
This guide walks through what dapagliflozin does, the multiple indications where it fits, the once-daily dosing, the cardiovascular and renal outcome evidence, and the safety concerns. Treat this guide as a companion to what your endocrinologist, cardiologist, or nephrologist tells you.
💊 Why Doctors Prescribe Dapavel Today
Dapagliflozin has broadest set of approved indications in the SGLT2 class. Modern practice uses these together across cardiovascular, renal, and diabetes conditions.
FDA-approved indications
Four approved indications
- Type 2 diabetes glycaemic control - approved 2014
- Heart failure with reduced ejection fraction (HFrEF) - approved 2020; diabetic OR non-diabetic
- Chronic kidney disease - approved 2021; diabetic OR non-diabetic
- Heart failure with preserved ejection fraction (HFpEF) - approved 2023
Where dapagliflozin fits particularly well
Modern diabetes, cardiology, and nephrology guidelines have converged. Dapagliflozin is now considered foundational therapy for several patient populations.
Best fit scenarios
- Heart failure (any ejection fraction) - diabetic or non-diabetic
- Chronic kidney disease with albuminuria - diabetic or non-diabetic
- Type 2 diabetes with established ASCVD
- Type 2 diabetes with high CV risk
- Type 2 diabetes with overweight where weight loss desired
- Combined diabetes and kidney or heart disease - benefits stack
- Preference for low-hypoglycaemia agent
Where dapagliflozin does not fit
Not appropriate for type 1 diabetes for glycaemic control. Not effective in end-stage kidney disease or dialysis. Not for diabetic ketoacidosis treatment. Volume depleted clients - correct first. Recurrent severe genital infections - relative contraindication.
Within the SGLT2 class
Position within the class
Dapagliflozin and empagliflozin are typically preferred over canagliflozin (amputation and fracture concerns) or ertugliflozin (less clinical evidence). Between dapagliflozin and empagliflozin, choice depends on specific comorbidities, cost, and availability. Both have similar overall benefit profiles.
The four pillars of HFrEF therapy
Modern guideline-directed HF therapy
For heart failure with reduced ejection fraction: ACE inhibitor/ARB/ARNI. Beta-blocker. Mineralocorticoid receptor antagonist. SGLT2 inhibitor (typically dapagliflozin or empagliflozin). All four should be started early after diagnosis.
Ask your team specifically why dapagliflozin was chosen (indication - diabetes, heart failure, CKD, or combination), what the primary treatment target is, and how it fits with any other medications you take.
🩸 Dapavel for Type 2 Diabetes
Type 2 diabetes glycaemic control was the original FDA-approved indication for dapagliflozin.
What dapagliflozin does to diabetes parameters
| HbA1c reduction (5 mg) | 0.5-0.7% |
| HbA1c reduction (10 mg) | 0.7-0.9% |
| Fasting glucose reduction | 25-35 mg/dL |
| Time to meaningful improvement | 1-2 weeks |
| Time to full glycaemic effect | 6-12 weeks |
| Weight loss (typical) | 2-3 kg over 6 months |
Effect is rapid onset - urinary glucose loss begins within days. Full glycaemic effect within 6-12 weeks. Effect diminishes as kidney function declines because filtered glucose load decreases with lower GFR.
Kidney function and glucose lowering
Effect scales with GFR
Dapagliflozin's glucose lowering depends on filtered glucose load reaching the kidney tubule. eGFR 60+ - full effect. eGFR 45-60 - reduced but substantial. eGFR 30-45 - modest glycaemic effect but CV and renal benefits maintained. eGFR under 25 - not effective for glycaemic control but may continue for renal/CV benefit.
Which clients respond well
Dapagliflozin works particularly well in clients with higher baseline HbA1c. Effect is durable over years. Combination with insulin, metformin, or GLP-1 agonists is straightforward. Weight loss and modest blood pressure reduction are welcome bonuses.
Combination therapy synergy
Common combinations
- Metformin + dapagliflozin - complementary; standard second-line addition
- Metformin + GLP-1 agonist + dapagliflozin - triple therapy with excellent glycaemic effect
- Insulin + dapagliflozin - reduces insulin requirement and adds CV/renal benefits
- Sulfonylurea + dapagliflozin - possible but hypoglycaemia risk
Durability advantage
Unlike sulfonylureas which lose glycaemic effect over years, dapagliflozin maintains effect as long as kidney function allows. Beta cell status is not the limiting factor.
Set realistic expectations - dapagliflozin provides modest glycaemic effect alongside cardiovascular protection, kidney protection, weight loss, and blood pressure reduction.
💓 Dapavel for Heart Failure DAPA-HF DELIVER
Heart failure benefit is one of the most important indications for dapagliflozin. The DAPA-HF and DELIVER trials established dapagliflozin's role across the heart failure ejection fraction spectrum.
DAPA-HF - the game-changing trial
DAPA-HF (McMurray et al. NEJM 2019)
- 4,744 clients with HFrEF (LVEF 40 percent or less)
- 42 percent had diabetes; 58 percent did not
- Standard heart failure therapy at baseline
- Randomised to dapagliflozin 10 mg vs placebo
- Median follow-up 18.2 months
- Primary composite reduced 26 percent
- CV death reduced 18 percent; all-cause mortality reduced 17 percent
- Benefits similar in diabetic and non-diabetic subgroups
The transformative finding
DAPA-HF established SGLT2 inhibitor benefit in heart failure regardless of diabetes status. This expanded dapagliflozin from diabetes drug to heart failure drug. Cardiologists routinely prescribe it now.
DELIVER - preserved ejection fraction
DELIVER (Solomon et al. NEJM 2022)
- 6,263 clients with LVEF over 40 percent
- Diabetic and non-diabetic clients
- Standard heart failure therapy at baseline
- Randomised to dapagliflozin 10 mg vs placebo
- Median follow-up 2.3 years
- Primary composite reduced 18 percent
DELIVER extended SGLT2 benefit to the entire heart failure spectrum. HFpEF had previously lacked proven pharmacological outcome therapy.
Heart failure mechanism
The heart failure benefits work through multiple mechanisms. Modest preload reduction from diuretic effect. Improved myocardial energetics with ketone body utilisation. Reduced myocardial stiffness. Anti-inflammatory effects. Uric acid reduction. Improved erythropoiesis.
Modern heart failure guideline recommendations
The four pillars of HFrEF
Modern guidelines recommend four foundational medication classes: ACE inhibitor/ARB/ARNI. Beta-blocker. Mineralocorticoid receptor antagonist. SGLT2 inhibitor. All four should typically be started early and continued long-term.
Practical use in heart failure
Considerations for HF clients
- Start early after diagnosis
- Effect on symptoms visible within weeks
- Monitor volume status
- May need to reduce loop diuretic dose modestly (10-20 percent)
- Monitor eGFR - initial dip expected
- Continue through mild acute illness where possible
Non-diabetic heart failure use
Dapagliflozin does not require diabetes
Following DAPA-HF and DELIVER, dapagliflozin is FDA-approved for heart failure regardless of diabetes status. Non-diabetic clients gain full heart failure benefits without meaningful hypoglycaemia risk.
Dapagliflozin provides substantial heart failure benefits across the ejection fraction spectrum and regardless of diabetes status.
🪩 Dapavel for Kidney Protection DAPA-CKD
Kidney protection is another landmark benefit of dapagliflozin, established by the DAPA-CKD trial.
DAPA-CKD - the landmark kidney trial
DAPA-CKD (Heerspink et al. NEJM 2020)
- 4,304 CKD clients
- eGFR 25-75 mL/min with albuminuria (UACR 200-5000 mg/g)
- 68 percent had diabetes; 32 percent did not
- On ACE inhibitor or ARB
- Randomised to dapagliflozin 10 mg vs placebo
- Median follow-up 2.4 years - stopped early for efficacy
- Primary composite reduced 39 percent
- Kidney failure reduced 36 percent
- All-cause mortality reduced 31 percent
The transformative kidney finding
DAPA-CKD established SGLT2 inhibitor benefit in kidney disease regardless of diabetes status and even in relatively low eGFR (down to 25 mL/min).
Renal protection mechanism
The renal benefits work through multiple mechanisms. Reduced glomerular hyperfiltration. Blood pressure reduction. Uric acid reduction. Weight loss. Direct anti-inflammatory and anti-fibrotic effects in kidney tissue.
The initial eGFR dip - expected and reversible
Do not stop for the initial dip
Starting dapagliflozin causes an initial 3-5 mL/min eGFR reduction over 2-6 weeks. This is haemodynamic and reversible, not injury. Long-term eGFR slope improves substantially compared with placebo.
Guidelines and kidney disease
The KDIGO 2022 Guideline for Diabetes Management in CKD made SGLT2 inhibitors first-line therapy for diabetic kidney disease. The KDIGO 2024 CKD Evaluation and Management Guideline extended this to CKD regardless of diabetes status.
Who benefits most
Best kidney benefit populations
- CKD with albuminuria (UACR over 200 mg/g)
- CKD with reduced eGFR (25-75 mL/min)
- Diabetic kidney disease progressing despite ACE inhibitor/ARB
- Non-diabetic CKD - IgA nephropathy, FSGS, others
- Combined heart failure and kidney disease
eGFR considerations
| eGFR 60+ mL/min | Standard 10 mg daily |
| eGFR 45-60 mL/min | Continue standard 10 mg daily |
| eGFR 25-45 mL/min | Continue 10 mg for renal/CV benefit |
| eGFR under 25 mL/min | Not for initiation; may continue if established |
Dapagliflozin provides substantial kidney protection in CKD regardless of diabetes status. Modern practice makes SGLT2 inhibitors a cornerstone of CKD care.
🫀 Dapavel for Cardiovascular Prevention DECLARE
Cardiovascular protection is a well-established dapagliflozin benefit. The DECLARE-TIMI 58 trial provided the CV safety data required for approval.
DECLARE-TIMI 58 - the CV outcomes trial
DECLARE-TIMI 58 (Wiviott et al. NEJM 2019)
- 17,160 type 2 diabetes clients - largest SGLT2 CV outcomes trial
- 41 percent had established CV disease; 59 percent had CV risk factors only
- Randomised to dapagliflozin 10 mg vs placebo
- Median follow-up 4.2 years
- MACE - non-inferior to placebo
- Heart failure hospitalisation reduced 27 percent
- Renal outcomes improved
- No amputation signal (unlike canagliflozin CANVAS)
Cardiovascular event reduction mechanism
The cardiovascular benefits appear through multiple mechanisms. Modest blood pressure reduction. Weight loss. Preload reduction. Improved myocardial energetics. Anti-inflammatory effects. Uric acid reduction. Erythropoiesis stimulation.
Who benefits most from CV protection
Best CV benefit populations
- Type 2 diabetes with established atherosclerotic CV disease
- Type 2 diabetes with heart failure
- Type 2 diabetes with multiple CV risk factors
- Type 2 diabetes with chronic kidney disease
- Older diabetic clients with multiple comorbidities
Class effects and specific comparisons
The cardiovascular benefits are a class effect shared to varying degrees by empagliflozin, canagliflozin, dapagliflozin, and ertugliflozin. Among the SGLT2 inhibitors, dapagliflozin has the broadest heart failure evidence and non-diabetic CKD evidence.
Modern guideline positioning
ADA, EASD, KDIGO, ESC, and AHA/ACC guidelines all now recommend SGLT2 inhibitors including dapagliflozin as first-line addition to metformin in type 2 diabetes clients with established or high CV risk, heart failure, or chronic kidney disease.
Beyond MACE - the broader value
The full cardiovascular story
Modern cardiovascular protection thinking includes more than just MACE. Heart failure hospitalisation matters substantially. Kidney disease progression matters for CV outcomes long-term. Dapagliflozin's combined effect across these outcomes represents substantial cardiovascular value.
Dapagliflozin provides comprehensive cardiovascular protection through heart failure prevention, kidney protection, and modest MACE benefit.
🔬 How Dapagliflozin Blocks SGLT2 Mechanism
Understanding how dapagliflozin works mechanistically clarifies both its effectiveness and its specific safety considerations.
The molecular target
Dapagliflozin blocks the sodium-glucose cotransporter 2 (SGLT2) in the proximal renal tubule. Under normal conditions, SGLT2 reabsorbs about 90 percent of glucose filtered into the kidney tubule. Dapagliflozin is highly selective for SGLT2 over SGLT1.
Sequence of effects after taking dapagliflozin
- Dapagliflozin binds SGLT2 in proximal tubule
- Glucose reabsorption blocked
- Urinary glucose excretion increases - typically 70-80 g per day
- Blood glucose falls proportionally
- Osmotic diuresis draws water and sodium
- Modest volume contraction lowers blood pressure
- Glucosuria drives caloric loss - typically 200-320 kcal/day
- Weight decreases modestly over weeks
- Ketone body production shifts modestly
- Tubuloglomerular feedback reduces glomerular hyperfiltration
Key mechanistic feature
Dapagliflozin works independently of insulin. Insulin sensitivity is not required. Beta cell function is not required. The mechanism is entirely renal. This distinguishes SGLT2 inhibitors from every other diabetes drug class and explains their unique benefits in heart failure and kidney disease even in non-diabetic clients.
Pharmacokinetics
| Absorption | Bioavailability 78%; unaffected by food |
| Peak plasma concentration | 1-2 hours |
| Half-life | 12.9 hours |
| Protein binding | 91% |
| Metabolism | UGT1A9 glucuronidation |
| Excretion | Renal 75%, faecal 21% |
Mechanism-driven benefits
- Weight loss - calorie loss in urine (2-3 kg typical)
- Blood pressure reduction - osmotic diuresis (3-5 mmHg systolic)
- Reduced glomerular hyperfiltration - kidney protection
- Uric acid reduction
- Ketone body utilisation
- Erythropoiesis stimulation
- Anti-inflammatory effects
Mechanism-driven side effects
- Genital mycotic infections - glucose in urine feeds yeast
- UTI increase (modest)
- Volume depletion
- Initial eGFR dip
- Diabetic ketoacidosis (rare)
- Fournier gangrene (very rare)
The elegant renal-focused mechanism defines both dapagliflozin's benefits and specific side effects.
⏰ Dapavel Dose Schedule and Titration
Dapavel dosing is straightforward - once daily, morning ideal but flexible, with or without food.
Standard dosing
| Situation | Dose |
|---|---|
| Adult starting (eGFR 25+) | 10 mg once daily |
| Type 2 diabetes glycaemic control (starting) | 5 mg daily; may increase to 10 mg |
| Heart failure or CKD | 10 mg once daily |
| Maximum dose | 10 mg once daily |
| eGFR 45-90 mL/min | Standard 10 mg daily |
| eGFR 25-45 mL/min | 10 mg for HF or CKD benefit |
| eGFR under 25 mL/min | Not for initiation; may continue if established |
| Mild-moderate hepatic impairment | No dose adjustment |
| Severe hepatic impairment | Start 5 mg with caution |
Available strengths
Dapavel comes as 5 mg and 10 mg tablets. The 10 mg dose is standard for heart failure, kidney disease, and most type 2 diabetes clients.
Timing rule
Once daily flexibility
Dapagliflozin can be taken at any consistent time - morning, afternoon, or evening. Take with or without food. Morning is often preferred because it avoids nocturia. Same time daily for adherence habit.
Expected effect timeline
- Day 1 - urinary glucose excretion begins
- Week 1-2 - fasting glucose lower; HF symptoms may improve
- Week 2-6 - initial eGFR dip; BP reduction
- Week 4-6 - HbA1c improvement clear
- Week 6-12 - full glycaemic effect
- Months - weight loss develops
- Long term - CV and renal outcome benefits over years
Titration approach
For heart failure or CKD, start directly at 10 mg. No titration typically needed. For type 2 diabetes glycaemic control, can start at 5 mg and increase to 10 mg after 4-6 weeks. Above 10 mg does not provide additional benefit.
Duration of therapy
Dapagliflozin is typically long-term therapy when tolerated. Effectiveness is durable over years.
Do not stop suddenly
Glycaemic control worsens within days if dapagliflozin discontinued. Heart failure and kidney protective effects also wane. Plan alternative therapy if stopping.
📅 Starting Dapavel - First Weeks
Starting Dapavel requires careful baseline assessment, awareness of the expected initial eGFR dip, and vigilance for the specific side effect profile.
Typical initiation experience
Most clients notice glucose falling within days if diabetic. Urination frequency may increase modestly. Some clients report increased thirst. Weight begins to fall over weeks. HbA1c improvement clear at 4-6 weeks. Heart failure clients may notice symptom improvement within weeks.
Pre-treatment assessment
Baseline checks before starting
- Indication clarification
- Kidney function - eGFR must be at least 25 mL/min
- Urine albumin - baseline for kidney protection tracking
- Volume status
- Blood pressure
- Genital/urinary infection history
- Concurrent medications
- DKA awareness education
- Pregnancy status and contraception
Setting expectations
Practical points for new starters
- Increased urination - especially first weeks
- Increased thirst - drink adequate fluid
- Modest weight loss welcome for most
- Genital hygiene - reduce mycotic infection risk
- Sick day awareness
- Initial eGFR dip is expected - not a sign of harm
- DKA symptom awareness - even with normal glucose
Follow-up schedule for initiation
| Timing | Focus |
|---|---|
| Week 2-4 | Tolerability review; volume status; check for infections |
| Week 4-6 | eGFR recheck; HbA1c early trend |
| Month 3 | HbA1c response; weight; BP; HF symptoms |
| Every 6 months | HbA1c; eGFR; urine albumin; overall assessment |
| Annual | Comprehensive review |
Warning signs during initiation
Contact team promptly if these occur
- Symptoms of dehydration
- Genital burning, itching, discharge
- Urinary tract infection symptoms
- Severe genital or perineal pain with fever
- Symptoms of DKA - nausea, vomiting, abdominal pain
- Substantial weight loss beyond expected
- Severe hypoglycaemia if on other diabetes drugs
The first weeks are learning. Initial eGFR dip should not prompt discontinuation.
📏 Dapavel Dose Adjustments Response
Dapavel dose adjustment is minimal because 10 mg is the standard dose for most indications.
Standard dosing approach
For most clients, dapagliflozin 10 mg once daily is the appropriate dose. No routine titration. No dose adjustments for age, race, sex, weight, or renal function within the acceptable range.
Common adjustments
| Situation | Action |
|---|---|
| HbA1c not at target on 10 mg | Add GLP-1 agonist, metformin, or insulin |
| eGFR falls to 25-45 mL/min | Continue 10 mg for renal/CV benefit |
| eGFR falls below 25 mL/min | Consider stopping; individual assessment |
| Recurrent genital infections | Longer antifungal course; consider switching |
| Volume depletion symptoms | Reduce loop diuretic; ensure adequate hydration |
| Substantial weight loss beyond target | Assess intake |
| Acute illness with dehydration | Hold dapagliflozin; restart when recovered |
| Major surgery planned | Hold 3+ days prior |
| DKA episode | Stop dapagliflozin; alternative therapy |
Managing the initial eGFR dip
Expected pattern
eGFR typically falls 3-5 mL/min in first 2-6 weeks. Then stabilises. Long-term eGFR slope is improved. Do NOT discontinue for this expected dip.
When dapagliflozin is not enough
Add-on strategy for glycaemic control
- Add metformin if not already
- Add GLP-1 agonist for further HbA1c and weight loss
- Add basal insulin for substantial HbA1c gap
- Add DPP-4 inhibitor for modest addition
Non-response investigation
- Check adherence honestly
- Consider kidney function trajectory
- Assess for concurrent hyperglycaemia drivers
- Rule out other conditions
- Consider drug interactions
- Endocrinology consultation for refractory cases
Dose adjustment for dapagliflozin is minimal. Safety concerns drive holding or discontinuation.
💊 How to Take Dapavel Tablets
Practical routines around Dapavel tablets are simple - once daily at a consistent time.
Daily routine
Take once daily at any consistent time. Morning often preferred to avoid nocturia. Can be taken with or without food. Swallow whole with water. Same time daily supports adherence habit.
Anchor to a daily habit
Take with the morning routine. Some clients prefer evening. Choose the time that fits your routine best. Weekly pillbox helpful. Phone alarm labeled "dapagliflozin" reduces forgetting.
Hydration matters
Drink adequate fluid
Dapagliflozin causes osmotic diuresis - the glucose in urine draws water. Drink adequate water - typically 2-2.5 L daily unless restricted (heart failure clients may have fluid restrictions). Watch for dehydration signs particularly in hot weather, illness, or when combined with diuretics.
Home monitoring priorities
What to track at home
- Fasting glucose (if diabetic)
- Weight monthly - modest loss expected
- Blood pressure - modest reduction expected
- Volume status - dizziness on standing suggests dehydration
- Urinary frequency
- Genital symptoms - itching, discharge, discomfort
- Heart failure symptoms if relevant
Key safety rules
Alert your team about
- Symptoms of dehydration or dizziness
- Any genital burning, itching, or discharge
- Urinary tract infection symptoms
- Severe genital or perineal pain with fever
- Nausea, vomiting, abdominal pain - can signal DKA
- Sudden unusual fatigue with normal glucose - DKA signal
- Substantial rash
- Planned surgery
Sick day awareness
Hold during acute illness
If you develop acute illness with vomiting, dehydration, or inability to eat and drink normally, hold dapagliflozin until recovered. This prevents DKA and volume depletion.
Storage
Room temperature under 30 C. Original packaging. Protect from moisture. Not in bathroom or hot car. Out of reach of children. Do not use past expiry. Return unused tablets to pharmacy for disposal.
Once-daily flexible-time dosing is simple.
🍴 Food and Dapavel Absorption
Dapagliflozin absorption is not meaningfully affected by food.
Food and dapagliflozin absorption
Bioavailability approximately 78 percent. Food does not meaningfully reduce absorption. Take with or without food consistently. Take at the same time daily for adherence habit.
Diet for type 2 diabetes and cardiovascular protection
The Mediterranean or DASH eating pattern has best evidence. Emphasise vegetables, whole grains, legumes, fatty fish, nuts, olive oil. Limit refined carbohydrates, added sugars, processed meats.
Diet considerations for SGLT2 clients
- Adequate hydration - 2-2.5 L water daily unless restricted
- Consistent carbohydrate intake
- Avoid very low carbohydrate diets - raise DKA risk
- Fatty fish weekly - cardiovascular support
- Vegetables at each meal
- Portion control
The very low-carb / ketogenic diet warning
DKA risk elevated with very low carb intake
Ketogenic or very low carbohydrate diets (under 50g/day) raise the risk of diabetic ketoacidosis on dapagliflozin even with normal blood glucose. Discuss with your team before starting a low-carb dietary pattern.
Special dietary considerations for heart failure clients
Fluid and sodium considerations
Heart failure clients often have specific fluid restrictions (typically 1.5-2 L daily) and sodium limits (typically under 2 g daily). Dapagliflozin adds modest diuresis. Discuss with heart failure team about optimal fluid intake.
Hydration awareness
Dapagliflozin puts glucose in urine which draws water through osmotic effect. Drink adequate water throughout the day. This becomes particularly important in hot weather, during exercise, when ill, or when taking diuretics.
Weight management
Dapagliflozin causes 2-3 kg weight loss typically over 6 months. Continue attention to diet and exercise.
Diet supports cardiometabolic health. Adequate hydration is essential. Avoid very low carbohydrate patterns due to DKA risk.
🍷 Alcohol Rules During Dapavel Therapy
Alcohol has specific considerations on dapagliflozin therapy.
Why alcohol matters with dapagliflozin
Alcohol causes diuresis on its own. Combined with dapagliflozin's osmotic diuresis, dehydration risk increases. Heavy alcohol use can precipitate hypoglycaemia if combined with insulin or sulfonylureas. Alcohol excess can precipitate euglycaemic DKA. Alcohol worsens heart failure.
Alcohol concerns on dapagliflozin
- Additive dehydration
- DKA risk in binge drinking or heavy use
- Hypoglycaemia if on insulin or sulfonylurea concurrently
- Heart failure worsening with heavy use
- Liver injury with heavy use
- Blood pressure elevation
Guidelines by scenario
| Scenario | Alcohol guidance |
|---|---|
| Type 2 diabetes stable on dapagliflozin | Moderate at most - 1 drink daily women, 2 daily men max |
| Heart failure | Very limited or avoid |
| CKD advanced | Very limited or avoid |
| Any liver disease | Avoid or minimal |
| Ketogenic or low-carb diet | Strict limitation - DKA risk elevated |
| Concurrent insulin or sulfonylurea | Extra hypoglycaemia caution |
| Volume depletion tendency | Avoid alcohol excess |
Standard drink reference
Beer 12 oz / 350 ml at 5 percent alcohol. Wine 5 oz / 150 ml at 12 percent alcohol. Spirits 1.5 oz / 45 ml at 40 percent alcohol.
Sensible approach if you drink
Practical guidance
- Not more than 2 drinks in one occasion
- Hydration - water alongside alcohol
- Eat with alcohol
- Not before driving
- Consider holding dapagliflozin during binge drinking
- Be honest with your team about intake
Avoid alcohol entirely if:
- Any hepatitis or active liver disease
- Heart failure with substantial symptoms
- Diagnosed alcohol use disorder
- Prior DKA on dapagliflozin
- Volume depletion tendency
- Directed by your team
Alcohol on dapagliflozin requires moderation.
🚨 Dapavel Side Effects Complete Overview and Warnings
Dapagliflozin has a distinctive but relatively favourable side effect profile.
Common effects
Common (over 5 percent)
- Genital mycotic infections - female genital candidiasis 5-8%; male balanitis 3-5%
- Urinary tract infections - modest increase
- Increased urination frequency
- Increased thirst
- Back pain
- Nasopharyngitis
Uncommon but notable
- Volume depletion - dizziness, orthostatic hypotension
- Acute kidney injury - typically in volume depletion contexts
- Elevated LDL cholesterol - modest rise
- Rash - hypersensitivity
- Nausea
- Constipation
Rare but serious
Rare serious effects
- Diabetic ketoacidosis - often euglycaemic
- Fournier gangrene - very rare necrotising infection
- Pyelonephritis or urosepsis
- Severe hypersensitivity
What dapagliflozin does NOT cause
Absent signals - key advantages
- No amputation signal - unlike canagliflozin CANVAS
- No bone fracture signal
- Very low hypoglycaemia risk
- No weight gain - causes modest weight loss
- No heart failure exacerbation - actually prevents HF events
When to seek help urgently
Emergency signals
- Symptoms of DKA
- Severe genital or perineal pain with fever
- High fever with UTI symptoms
- Fainting or severe dizziness
- Substantial rash with mucosal involvement
- Facial or throat swelling
Managing common effects
| Effect | Action |
|---|---|
| Genital mycotic infection (mild) | Antifungal; improved hygiene; continue |
| Genital mycotic infection (recurrent) | Longer antifungal course; consider switching |
| UTI (uncomplicated) | Antibiotic; hydration; continue |
| UTI (recurrent or pyelonephritis) | Antibiotic; investigate; consider stopping |
| Volume depletion | Hydration; reduce diuretic |
| Orthostatic dizziness | Adequate hydration; slow position changes |
| Rash mild | Assess; may continue with monitoring |
Side effect profile is generally favourable. Absent amputation and fracture signals make dapagliflozin preferable to canagliflozin.
🧫 Genital and Urinary Tract Infections
Genital and urinary tract infections are the most common dapagliflozin side effects.
Why infections occur
Glucose in urine feeds bacteria and yeast. The genitourinary tract becomes a favourable environment for infection on SGLT2 inhibitors. Women are affected more often than men.
Genital mycotic infections
Genital candidiasis
- Women - vulvovaginal candidiasis; 5-8 percent
- Men - balanitis or balanoposthitis; 3-5 percent
- Symptoms - itching, burning, discharge, redness, discomfort
- Timing - can occur at any time
- Usually mild and responsive to standard antifungal treatment
Treatment approach
Topical antifungal (clotrimazole cream) or single-dose oral fluconazole 150 mg. Recurrent episodes may need longer course. Do not stop dapagliflozin for isolated mild infection.
Urinary tract infections
- Modest increase - 4-6 percent vs 3-5 percent placebo
- Usually mild lower tract cystitis
- Symptoms - dysuria, urgency, frequency
- Standard antibiotic treatment
- Rare escalation to pyelonephritis or urosepsis
Prevention strategies
Reduce infection risk
- Good genital hygiene
- Adequate hydration - flushes urinary tract
- Wipe front to back (women)
- Post-coital urination
- Loose cotton underwear
- Prompt treatment of any infection
Recurrent infection management
If infections recur
- Standard longer antifungal course
- Optimise hygiene and hydration
- Assess for other contributing factors
- Consider pausing dapagliflozin during recurrent episodes
- Switch to alternative SGLT2 (empagliflozin)
- Consider whether SGLT2 class continuation is worthwhile
Genital and urinary infections are the most common dapagliflozin side effects but usually manageable.
💧 Volume Depletion and Blood Pressure
Volume depletion and blood pressure changes are direct consequences of the osmotic diuresis effect.
The diuretic effect
Glucose in urine draws water and sodium through osmotic effect. Blood pressure falls 3-5 mmHg systolic and 1-3 mmHg diastolic typically.
Who is at risk for volume depletion
Higher risk populations
- Older adults
- Clients on loop or thiazide diuretics
- Clients on ACE inhibitors or ARBs
- Baseline systolic BP under 110
- Reduced eGFR
- Recent surgery or illness
- Hot weather or exercise
Heart failure clients - a special case
Balancing volume in heart failure
Heart failure clients are on loop diuretics. Adding dapagliflozin creates additive diuresis. Often the loop diuretic dose can be reduced modestly (10-20 percent). Monitor weight, symptoms, and volume status closely during transition.
Symptoms of volume depletion
Signs to watch for
- Dizziness on standing
- Lightheadedness
- Fatigue
- Reduced urine output
- Dark urine
- Dry mouth
- Muscle cramps
Management approach
- Ensure adequate fluid intake
- Reduce loop or thiazide diuretic dose if volume depleted
- Slow position changes
- Assess concurrent medications
- Hold dapagliflozin during acute illness with dehydration
- Reassess and restart when volume repleted
Blood pressure effects
The BP effect is typically beneficial
The modest blood pressure reduction from dapagliflozin (3-5 mmHg systolic) is often welcome in hypertensive diabetic clients or CKD clients. May allow reduction of other antihypertensive medications.
Acute kidney injury risk
Volume depletion is the primary cause of acute kidney injury on dapagliflozin. Preventable with adequate hydration and diuretic dose management.
Hold dapagliflozin during
- Acute severe illness with vomiting or diarrhoea
- Substantial reduction in oral intake
- Major surgery (hold 3+ days prior)
- Prolonged fasting
- Signs of volume depletion or acute kidney injury
Volume and blood pressure effects are usually beneficial but require attention in specific populations.
🔴 Diabetic Ketoacidosis Risk Dapavel
Diabetic ketoacidosis on SGLT2 inhibitors is uncommon but potentially serious.
Why SGLT2 inhibitors can precipitate DKA
SGLT2 inhibitors shift metabolism modestly toward ketone body production. Insulin levels drop as glucose falls. Glucagon rises. Ketone body production increases. In specific settings (illness, surgery, low carbohydrate intake, alcohol excess), this shift can amplify to true ketoacidosis.
The euglycaemic DKA trap
Classic DKA has very high glucose (over 250 mg/dL). SGLT2-associated DKA can occur with normal or only modestly elevated glucose (euglycaemic DKA) because dapagliflozin removes glucose in urine. Ketone testing rather than glucose testing is essential when DKA is suspected.
Who is at higher risk
Elevated DKA risk situations
- Acute illness - infection, gastroenteritis, surgery
- Prolonged fasting or substantially reduced carbohydrate intake
- Ketogenic or very low-carb diet
- Dehydration
- Insulin dose reduction or omission
- Excess alcohol
- Recent surgery
- Type 1 diabetes (off-label)
Recognising DKA
Symptoms to recognise
- Nausea and vomiting
- Abdominal pain
- Unusual fatigue or weakness
- Fast or deep breathing (Kussmaul respiration)
- Fruity breath odour
- Confusion or drowsiness
- Symptoms may occur with normal blood glucose
Prevention strategies
Reduce DKA risk
- Hold dapagliflozin during acute illness
- Hold dapagliflozin 3+ days before major surgery
- Avoid ketogenic or very low-carb diets
- Do not omit insulin when on dapagliflozin plus insulin
- Limit alcohol
- Ensure adequate carbohydrate intake with meals
- Report early DKA symptoms - do not wait
If DKA is suspected
Emergency response
- Seek emergency medical care
- Check blood ketones if available
- Do not rely on blood glucose alone
- Hospital treatment - fluids, insulin, electrolyte correction
- Stop dapagliflozin
- Do not restart until fully recovered
DKA on dapagliflozin is uncommon but requires awareness.
⚠️ Fournier Gangrene Rare but Serious
Fournier gangrene is a very rare but serious concern with SGLT2 inhibitors. It is a surgical emergency requiring immediate recognition.
What Fournier gangrene is
Fournier gangrene is a necrotising fasciitis of the perineum, genitalia, or perianal area. Deep soft tissue infection with rapid tissue destruction. Very rare but life-threatening - mortality 20-40 percent even with treatment.
SGLT2 inhibitors and Fournier gangrene
The connection
- FDA identified small number of cases (2013-2018)
- FDA warning added 2018
- Absolute risk very small - estimated less than 1 per 10,000 client-years
- Both diabetic and non-diabetic clients affected
- Mechanism unclear
Warning signs
Immediate medical attention required for
- Severe pain in perineum, genitalia, or perianal area
- Tenderness in these areas
- Redness or swelling
- Skin discolouration - purple, black, or blistering
- Fever
- Feeling generally unwell
- Rapid progression of symptoms over hours
Higher risk factors
- Diabetes (particularly poorly controlled)
- Obesity
- Alcohol use
- Smoking
- Recent surgery or trauma to genital/perineal area
- Immunosuppression
- Prior soft tissue infection
If Fournier is suspected
Emergency response
- Emergency department immediately
- Stop dapagliflozin
- Surgical assessment - debridement usually needed urgently
- Broad-spectrum IV antibiotics
- ICU care often required
- Do not restart dapagliflozin
Prevention
Reduce risk
Good perineal and genital hygiene. Prompt treatment of any perineal or genital infection. Address any wounds promptly. Optimise glycaemic control. Report any concerning symptoms quickly.
Perspective on absolute risk
Absolute Fournier risk on dapagliflozin is very small. The benefits for cardiovascular protection, kidney protection, and heart failure prevention greatly exceed this rare risk.
Fournier gangrene is very rare but life-threatening. Awareness of warning signs and prompt medical attention are essential.
🟡 Kidney Function and Initial eGFR Dip
Kidney function considerations shape both starting and ongoing dapagliflozin use.
The initial eGFR dip
Expected and reversible
Starting dapagliflozin causes an initial 3-5 mL/min eGFR reduction over 2-6 weeks. Then stabilises. This is haemodynamic and reversible, not injury. The mechanism is tubuloglomerular feedback - dapagliflozin reduces glomerular hyperfiltration.
Long-term eGFR benefit
Despite the initial dip, long-term eGFR slope is improved compared with placebo. In DAPA-CKD and other trials, dapagliflozin clients had significantly slower eGFR decline over years.
When to worry about eGFR change
Concerning eGFR patterns
- Expected - 3-5 mL/min dip over 2-6 weeks then stable
- Investigate - dip over 10 mL/min
- Investigate - eGFR fails to stabilise after 6-8 weeks
- Investigate - progressive decline after initial stabilisation
- Investigate - eGFR falls with symptoms suggesting AKI
Kidney function and dapagliflozin
| eGFR 90+ mL/min | Standard 10 mg daily; full benefits |
| eGFR 60-90 mL/min | Standard 10 mg daily |
| eGFR 45-60 mL/min | Standard 10 mg daily |
| eGFR 25-45 mL/min | 10 mg for HF/CKD benefit; reduced glycaemic effect |
| eGFR under 25 mL/min | Not for initiation; may continue if established |
| Dialysis | Not applicable |
Acute kidney injury contexts
Hold dapagliflozin during AKI risk periods
- Severe dehydration
- Acute severe illness with reduced intake
- Contrast studies with borderline kidney function
- Major surgery periods
- Concurrent nephrotoxic medication trial
The CKD paradox
Continue for renal benefit even with reduced GFR
Modern practice continues dapagliflozin for renal protection even when glycaemic effect is reduced. DAPA-CKD showed benefit down to eGFR 25 mL/min.
The initial eGFR dip is expected and reversible. Understanding this pattern prevents inappropriate discontinuation.
💉 Dapavel Drug Interactions Complete Overview and Warnings
Dapagliflozin has relatively few drug interactions compared to many diabetes agents.
Dapagliflozin metabolism
Metabolised primarily by UGT1A9. Minor CYP involvement. Metabolites are inactive. Excretion is mostly renal (75 percent) and faecal (21 percent).
UGT enzyme modulators
Interactions of clinical significance
- Rifampicin - UGT inducer; reduces dapagliflozin AUC by 22 percent
- Phenytoin, phenobarbital, carbamazepine - similar effect
- St John's wort - herbal inducer
Diuretic interactions
Pharmacodynamic effects
- Loop diuretics - additive volume depletion; may need loop dose reduction 10-20%
- Thiazide diuretics - additive volume depletion
- Mineralocorticoid receptor antagonists - generally safe combination
Blood pressure medications
Additive BP effect
Dapagliflozin modestly lowers blood pressure. Combined with ACE inhibitors, ARBs, or calcium channel blockers - the effect is additive. Usually welcome in hypertensive diabetic clients.
Diabetes medication combinations
Common combinations
- Metformin - excellent combination
- GLP-1 agonists - excellent combination
- DPP-4 inhibitors - safe
- Sulfonylureas - hypoglycaemia risk
- Insulin - hypoglycaemia risk; monitor DKA risk
- Pioglitazone - safe combination
Common medications - usually safe
Safe combinations
Statins, warfarin, most antibiotics, most antifungals, most SSRIs, most cardiac medications, most respiratory medications. Dapagliflozin has a favourable drug interaction profile.
Dapagliflozin drug interactions are limited. Most common medications are safe.
💊 Insulin Sulfonylurea Diuretics Interactions
Specific attention to insulin, sulfonylurea, and diuretic interactions ensures safe use of dapagliflozin.
Insulin combination
Dapagliflozin plus insulin is a common and effective combination. Dapagliflozin adds CV and renal benefits and enables lower insulin doses.
Concerns with insulin combination
- Hypoglycaemia risk - may need insulin dose reduction of 10-20 percent
- DKA risk elevated - do not reduce insulin dose excessively
- Monitor glucose more frequently at initiation
The DKA insulin balance
Reducing insulin too aggressively when adding dapagliflozin can precipitate DKA. The rule - reduce insulin doses modestly, not aggressively. Continue basal insulin at reduced but not absent doses.
Sulfonylurea combination
- Hypoglycaemia risk from sulfonylurea component
- Consider sulfonylurea dose reduction (approximately 25-50 percent)
- Modern practice often prefers to discontinue sulfonylurea when starting SGLT2 inhibitor
- If both continued, monitor glucose and hypoglycaemia symptoms
Loop diuretic considerations
- Baseline heart failure on loop diuretic - additive volume effect; may need loop reduction 10-20 percent
- Volume depletion with dapagliflozin - reduce or hold loop diuretic first
- Hyperkalaemia on ACE inhibitor + spironolactone - dapagliflozin modestly reduces K+; helpful
- Blood pressure management - dapagliflozin lowers BP
MRA considerations
Mineralocorticoid receptor antagonists are common in heart failure and CKD. Combined with dapagliflozin, the combination is safe and often synergistic. Both reduce cardiovascular events. Monitor potassium and eGFR periodically.
Practical adjustment approach
When starting dapagliflozin on existing therapy
- On insulin - reduce basal insulin 10-20 percent
- On sulfonylurea - consider stopping SU or reducing dose 25-50 percent
- On loop diuretic (HF) - may reduce 10-20 percent
- On ACE inhibitor/ARB - continue standard; monitor BP
- On MRA - continue; monitor K+ and creatinine
Insulin, sulfonylurea, and diuretic combinations require attention but are manageable.
🩸 Rifampicin and Other Enzyme Inducers
Rifampicin and other UGT inducers modestly reduce dapagliflozin effect.
Rifampicin interaction
Modest reduction in dapagliflozin effect
Rifampicin is a potent UGT enzyme inducer. Reduces dapagliflozin AUC by approximately 22 percent. This is smaller than the effect on canagliflozin (51 percent). Glucose control may worsen modestly during rifampicin course.
Managing rifampicin combination
- Short course rifampicin - continue dapagliflozin; monitor glucose
- Long course rifampicin - continue if glucose control acceptable
- Dose increase - not applicable (10 mg is maximum)
- Close glucose monitoring during rifampicin course
- After rifampicin stops - dapagliflozin levels rise back over 2-3 weeks
Anticonvulsant inducers
Phenytoin, phenobarbital, carbamazepine
- Similar UGT and CYP induction effect
- May reduce dapagliflozin effect modestly
- Newer anticonvulsants (levetiracetam, lamotrigine, lacosamide) generally do not induce UGT
- Monitor glucose during induction period
St John's wort
Herbal preparation with UGT and CYP induction effects. Reduces dapagliflozin levels modestly. Ask clients about herbal supplements. Avoid or discontinue during dapagliflozin therapy if possible.
Other notable interactions
Less common but worth knowing
- Lithium - possible reduced lithium levels; monitor lithium
- Warfarin - no meaningful interaction; safe
- NSAIDs - additive risk for kidney injury with volume depletion
- Contrast media - consider holding during contrast studies
- Digoxin - no significant interaction
Contrast studies
Contrast-induced kidney injury
Dapagliflozin does not have a specific contrast interaction like metformin. However, if kidney function is borderline, holding dapagliflozin around contrast study is reasonable. Ensure adequate hydration before and after contrast.
Practical drug interaction summary
Key interactions to know
- Rifampicin - monitor glucose; usually manageable
- Anticonvulsant inducers - similar to rifampicin
- St John's wort - avoid
- Insulin/SU - dose adjustment; monitor hypoglycaemia
- Loop diuretics - additive volume effect
- Warfarin, digoxin, statins - safe combinations
Dapagliflozin has one of the most favourable drug interaction profiles among diabetes medications.
⏱️ What to Do If You Miss Dapavel
Missed doses of dapagliflozin are relatively forgiving in isolation but chronic non-adherence loses glycaemic and cardioprotective effects.
Missed dose rules
- Missed dose noticed within a few hours - take when remembered
- Missed dose noticed late in day - skip and take tomorrow's dose at usual time
- Never double up - do not take two doses together
- Occasional missed dose - modest immediate impact
- Multiple missed doses - contact prescriber
Impact of missing doses
Effect declines within days
Dapagliflozin's effects depend on active drug in the tubule blocking SGLT2. Half-life 12.9 hours - one missed dose has modest impact. Missing multiple doses substantially reduces effects.
Adherence strategies
- Same time daily anchored to consistent habit
- Weekly pillbox visible
- Phone alarm labeled with medication name
- Refill 2 weeks before running out
- 90-day supplies where insurance allows
- Prescription synchronisation with other daily medications
- Travel supply with buffer
Non-adherence signals to your team
Unexpected HbA1c rise. Weight gain. Blood pressure returning to previous level. Heart failure symptom worsening. Pharmacy refill records lag. Cost concerns.
Occasional missed doses are manageable. Chronic adherence over months determines outcomes.
🩺 Dapavel Monitoring HbA1c Kidney BP
Dapagliflozin monitoring covers glycaemic response, kidney function, blood pressure, heart failure status, weight, and specific safety concerns.
Core monitoring schedule
| Assessment | Frequency |
|---|---|
| HbA1c (if diabetic) | Every 3-6 months |
| eGFR / creatinine | Baseline; 4-6 weeks after start; then every 6 months |
| Urine albumin-to-creatinine ratio | Annual (more often in CKD) |
| Weight | Every visit |
| Blood pressure | Every visit |
| Volume status | Every visit |
| Heart failure symptoms (if relevant) | Every visit |
| Genital/UTI symptom review | Every visit |
| Lipids | Annual |
| Potassium (if on ACE/ARB or MRA) | Baseline; then every 6 months |
| Ketone testing (illness) | As needed if concerning symptoms |
The initial eGFR check
Expect the initial dip
Recheck eGFR at 4-6 weeks after starting dapagliflozin. A 3-5 mL/min dip is expected and reversible. Long-term eGFR slope is improved compared with placebo.
Safety-specific surveillance
Priority safety checks
- Volume status
- Genital/UTI symptoms
- DKA symptom awareness
- Fournier gangrene awareness
- Cardiovascular symptoms
- Heart failure symptoms if indication is HF
Indication-specific monitoring
By primary indication
- Type 2 diabetes - HbA1c, weight, BP, kidney function
- Heart failure - NYHA class, symptoms, hospitalisations, BNP/NT-proBNP, echocardiogram periodically
- CKD - eGFR slope, UACR trend, blood pressure, potassium
- Multiple indications - combined monitoring
Annual review agenda
Comprehensive yearly assessment
- Effectiveness across all indications
- Kidney function trajectory
- Cardiovascular status
- Continued need for dapagliflozin
- Side effect burden
- Diabetes complication surveillance if relevant
- Vaccinations up-to-date
- Overall goals aligned with treatment
Monitoring covers glycaemic effectiveness, kidney function trajectory, cardiovascular and heart failure status, and specific safety concerns.
👵 Dapavel in Older Adults
Older adults benefit substantially from dapagliflozin's cardiovascular, heart failure, and renal protective effects.
Age-specific considerations
Considerations in older adults
- Higher CV, HF, and renal risk - benefit potentially larger
- Volume depletion risk higher
- Polypharmacy common
- Fall risk higher
- Genital infection risk elevated
- eGFR often reduced
Standard older adult approach
Practical adjustments
- Careful volume assessment before starting
- Reduce loop or thiazide diuretic dose modestly at start
- Emphasise adequate hydration
- HbA1c targets often less strict (7.5-8.5 percent) if diabetes
- Blood pressure monitoring at initiation
- Fall prevention
- Cognitive assessment for adherence
Benefits amplified
Older adults gain most from SGLT2 benefits
Cardiovascular events, heart failure, and kidney disease progression are all more common in older adults. Absolute benefits from dapagliflozin can be substantial. DAPA-HF and DELIVER included older adults where the benefits were clearly demonstrated.
Advantages of dapagliflozin in older adults
Compared with canagliflozin, dapagliflozin has no amputation signal and no fracture signal - two concerns particularly relevant to frailer older adults. This makes dapagliflozin preferred within the SGLT2 class for older adults.
Higher stopping threshold in older adults
Lower threshold to discontinue or hold
- Recurrent genital or urinary infections
- Substantial volume depletion or orthostatic symptoms
- Cognitive decline affecting adherence
- Any DKA episode
- Acute illness with poor intake
- Substantial functional decline
Older adults often benefit substantially from dapagliflozin.
🤒 Sick Days and Illness on Dapavel
Illness disrupts diabetes and heart failure management. Dapagliflozin has specific sick day rules.
General principles
Continue dapagliflozin during minor illness if eating and drinking normally. Hold dapagliflozin during moderate-severe illness with vomiting, dehydration, or substantially reduced intake.
Situations by scenario
| Situation | Approach |
|---|---|
| Minor viral illness, eating normally | Continue dapagliflozin; extra hydration |
| Vomiting or unable to eat | Hold dapagliflozin; hydration priority |
| Fever with reduced appetite | Hold dapagliflozin; extra hydration |
| Severe infection with hospitalisation | Hold dapagliflozin |
| DKA (any glucose level) | Emergency; stop dapagliflozin |
| Severe dehydration | Hold dapagliflozin; IV fluids |
| Diarrhoea substantial | Hold if dehydration developing |
| Prolonged fasting | Hold dapagliflozin |
| HF exacerbation stable | Continue dapagliflozin; standard HF management |
Practical sick day rules
Home management during illness
- Home glucose monitoring if diabetic - 3-4 times daily
- Home ketone testing if available
- Maintain fluid intake - 3-4 L daily if able
- Small frequent carbohydrate-containing meals if possible
- Do not stop insulin if on insulin
- Contact team if unable to eat/drink or DKA symptoms
DKA awareness during illness
Check ketones during illness even if glucose normal
Illness is a common DKA trigger. If home ketone testing available, check when unwell. If ketones over 1.5 mmol/L, contact team. If over 3.0 mmol/L, emergency assessment.
DKA symptoms warrant urgent care regardless of glucose level.
Hospital admission
Inform hospital team of dapagliflozin use. Usually held during acute illness. Insulin regimen typically substituted if diabetic. For heart failure clients, dapagliflozin is often continued during HF hospitalisation.
Emergency signals during illness
Seek urgent care for
- Persistent vomiting
- Suspected DKA - any glucose level
- Signs of severe dehydration
- Fainting or severe orthostatic symptoms
- Chest pain
- Confusion
- Severe shortness of breath
- Severe genital or perineal pain with fever
Dapagliflozin sick day management centres on holding during moderate-severe illness, hydration, and DKA awareness.
📅 Vaccinations and Immunizations While Taking Dapavel
Dapagliflozin does not affect vaccine efficacy or safety.
Vaccine safety on dapagliflozin
No known interaction with any vaccine. Immune response unimpaired. All routine and travel vaccines proceed as scheduled. Live vaccines safe. mRNA vaccines safe.
Priority vaccines for adults with diabetes or heart failure
Recommended for diabetic and cardiac clients
- Annual influenza vaccine
- Pneumococcal vaccines (PCV20 or PCV15 + PPSV23)
- COVID-19 vaccine and boosters
- Zoster vaccine (Shingrix) - adults 50+
- Tetanus/diphtheria/pertussis - every 10 years
- Hepatitis B - diabetic adults 19-59
- RSV vaccine - adults 60+
Timing considerations
Take dapagliflozin as usual on vaccination day. Vaccines usually well-tolerated. Post-vaccine fever can transiently affect glucose - monitor. If unable to eat due to vaccine-related nausea (rare), consider holding dapagliflozin that day.
Travel vaccines
Discuss travel plans with team. Yellow fever, typhoid, hepatitis A - all safe on dapagliflozin. Malaria prophylaxis - discuss interactions; most agents safe.
Vaccines proceed normally on dapagliflozin.
🤰 Dapavel in Pregnancy Not Recommended
Dapagliflozin is not recommended in pregnancy.
Pregnancy standard
Dapagliflozin is not recommended in pregnancy. Limited human data. Animal studies show renal developmental abnormalities. Standard pregnancy diabetes management is insulin. If pregnancy is planned, transition before conception. If unplanned pregnancy occurs, transition promptly.
Pre-conception planning
Before conception
- Discuss with team when pregnancy considered
- Transition to insulin before conception
- Discuss heart failure or CKD management with specialist
- Optimise glycaemic control
- Folic acid 5 mg daily for 3 months before conception
- Retinal, renal, cardiac assessment
If unplanned pregnancy occurs
- Contact obstetric and diabetes teams promptly
- Do not stop dapagliflozin abruptly without alternative in place
- Transition to appropriate alternatives
- Antenatal care with combined obstetric-medical team
- Detailed anomaly ultrasound
- Retinal and renal assessment
- Fetal surveillance
Contraception considerations
Standard contraception approaches apply. Dapagliflozin does not interact with oral contraceptives meaningfully.
Post-pregnancy
Insulin continues immediately postpartum for diabetic clients. Consider whether to restart dapagliflozin after breastfeeding.
Dapagliflozin is avoided in pregnancy.
🍼 Breastfeeding While Taking Dapavel Dapagliflozin Safely
Dapagliflozin is not recommended during breastfeeding.
Breastfeeding considerations
- Human breast milk data limited
- Animal studies suggest excretion in milk
- Potential concern about neonatal renal development
- Standard practice - avoid dapagliflozin during breastfeeding
Standard breastfeeding management
Compatible options for diabetes
- Insulin - safe
- Metformin - safe; extensive experience
Decision framework
If breastfeeding, use insulin or metformin for diabetes. For heart failure or CKD, specialist input on breastfeeding-compatible therapy. Restart dapagliflozin after weaning if still appropriate.
Postpartum considerations
Breastfeeding itself supports weight loss and improves insulin sensitivity. Insulin requirements often reduced postpartum.
Dapagliflozin is avoided during breastfeeding.
⚕️ Dapavel Around Procedures and Surgery
Dapagliflozin requires specific attention around surgery to reduce DKA risk.
FDA guidance on surgery
FDA sick-day and surgery guidance
Hold dapagliflozin at least 3 days before major elective surgery. Do not restart until eating normally postoperatively, hydrated, and no signs of DKA.
Elective surgery management
Standard approach
- Hold dapagliflozin 3+ days before major surgery
- Insulin regimen for perioperative period as needed
- Anaesthetist and surgeon should know about dapagliflozin
- Restart dapagliflozin when eating normally, hydrated, stable
- Minor procedures may not require holding
Emergency surgery
Alert team to dapagliflozin use. Insulin perioperatively. Monitor for DKA - ketone check even if glucose normal.
Common procedures
| Procedure | Dapagliflozin approach |
|---|---|
| Colonoscopy/endoscopy | Hold day of procedure if fasting |
| CT with contrast | Consider holding if borderline kidney function |
| Dental procedures (routine) | Continue as normal |
| Cataract surgery | Continue; short procedure |
| Joint replacement | Hold 3+ days prior; insulin coverage perioperatively |
| Cardiac surgery | Hold 3+ days prior; specialist coordination |
| Fasting blood tests | Continue morning dose is fine |
Postoperative restart
Before restarting dapagliflozin
- Eating and drinking normally
- Adequate hydration
- Kidney function checked
- No signs of infection or DKA
- Volume status stable
- Wound healing progressing normally
Heart failure clients
Balancing surgical concerns and HF benefit
For heart failure clients, holding dapagliflozin temporarily may allow modest fluid accumulation. The 3-day hold rule still applies for major surgery, but restart promptly after eating normally.
Dapagliflozin management around surgery follows the 3-day pre-hold rule for major surgery to reduce DKA risk.
🔄 Switching Dapagliflozin Alternatives
Modern diabetes therapy has consolidated around SGLT2 inhibitors and GLP-1 agonists.
Reasons to consider switching from dapagliflozin
- Recurrent genital or urinary infections
- Substantial volume depletion or orthostatic issues
- DKA episode
- Fournier gangrene (very rare)
- Cost changes
- Client preference
Modern SGLT2 alternatives
| Agent | Key trials | Comparison |
|---|---|---|
| Empagliflozin (Jardiance) | EMPA-REG, EMPEROR-Reduced/Preserved, EMPA-KIDNEY | Very similar profile; strongest CV mortality data |
| Canagliflozin (Invokana) | CANVAS, CREDENCE | Amputation and fracture signals disadvantage |
| Ertugliflozin (Steglatro) | VERTIS CV | CV safety established; less clinical use |
Switching within the class
Straightforward switch
All SGLT2 inhibitors share mechanism. Simply substitute at next dose. Approximate equivalents: dapagliflozin 10 mg ≈ empagliflozin 10-25 mg ≈ canagliflozin 100-300 mg.
Dapagliflozin vs empagliflozin specifically
Both are excellent choices
- Both have HFrEF and HFpEF approval and evidence
- Both have CKD approval and evidence
- Empagliflozin arguably has strongest CV mortality data
- Dapagliflozin has broadest CKD trial including non-diabetic clients
- Neither has amputation or fracture signals
- Choice often depends on cost, availability, and formulary
Other class alternatives
Non-SGLT2 alternatives
- GLP-1 agonists - substantial weight loss; CV benefit
- Metformin - first-line standard
- DPP-4 inhibitors - weight-neutral
- Basal insulin - effective at all HbA1c levels
Where dapagliflozin fits
Dapagliflozin remains one of the most well-positioned SGLT2 inhibitors for most clients.
Adding to dapagliflozin
Common - add GLP-1 agonist for further HbA1c reduction, weight loss, and additional CV benefit. Add metformin (if not already) as foundational therapy.
Dapagliflozin is typically maintained rather than switched.
🛑 Dapavel Contraindications When to Avoid Dapagliflozin
Dapagliflozin contraindications reflect the specific safety concerns.
Absolute contraindications
Do not use dapagliflozin if:
- Type 1 diabetes - DKA risk substantially elevated
- Diabetic ketoacidosis - requires insulin
- Hypersensitivity to dapagliflozin or other SGLT2 inhibitors
- End-stage kidney disease or dialysis
- eGFR under 25 mL/min - do not initiate
Relative contraindications
Use only after careful risk-benefit assessment
- Prior DKA
- Recurrent genital or urinary infections
- Prior Fournier gangrene - avoid
- Substantial volume depletion tendency
- Baseline hypotension
- Pregnancy or planned pregnancy
- Breastfeeding
- Severe hepatic impairment
Use with caution
Older adults. Baseline reduced eGFR (25-45 mL/min). Chronic loop diuretic therapy. Ketogenic or very low-carb diet. Recurrent UTIs. Recent surgery or acute illness.
Pre-treatment checklist
Before starting Dapavel
- Confirm indication
- Baseline eGFR and creatinine
- Baseline urine albumin-to-creatinine ratio if CKD relevant
- Volume status assessment
- Blood pressure
- Genital/UTI history
- Medication reconciliation
- Pregnancy status and contraception
- DKA and sick-day education
- Fournier gangrene awareness education
Stop dapagliflozin if these develop
- DKA
- Fournier gangrene
- Substantial volume depletion or AKI not manageable
- Severe hypersensitivity reaction
- Recurrent severe genital or urinary infection
- Pregnancy
- eGFR falling below 25 mL/min (individual decision)
Dapagliflozin contraindications are focused. Dapagliflozin has one of the most favourable safety profiles in modern diabetes/HF/CKD therapy.
📦 Storage Travel and Yearly Review
Practical routines around Dapavel support long-term consistent use.
Storage
- Room temperature under 30 C
- Original blister packaging until use
- Protect from moisture
- Not in bathroom or hot car
- Out of reach of children
- Do not use past expiry date
- Return unused tablets to pharmacy for safe disposal
Travel planning
Extra supply - 2-3 weeks beyond trip duration. Original packaging with labels. Prescription copy. Diabetes or heart failure letter from team if useful. Insurance and pharmacy contact information. Time zone changes - keep taking daily.
Travel with dapagliflozin
Specific travel considerations
- Hydration priority
- DKA awareness
- Consider ketone strips for illness during travel
- Genital hygiene - infection prevention
- Fast-acting glucose if on insulin/sulfonylurea concurrently
- Medical alert identification
- Travel insurance covering conditions
Annual review agenda
Yearly assessment topics
- Effectiveness across all indications
- Kidney function trajectory
- Cardiovascular status
- Heart failure status if relevant
- Ongoing need for dapagliflozin
- Side effect burden
- Other complication surveillance if diabetic
- Vaccine status
- Overall goals aligned with treatment
The bigger picture
Dapagliflozin is one tool in comprehensive cardiometabolic and renal care. Diet, exercise, weight management remain foundational. Blood pressure and lipid control matter for cardiovascular outcomes.
Practical routines support consistent long-term Dapavel use. This guide is a companion to what your endocrinologist, cardiologist, or nephrologist advises specifically for you.
Dapavel — Frequently Asked Questions
-
What is Dapagliflozin (Dapavel)?
Dapagliflozin, marketed as Dapavel, is a medication used for the treatment of type 2 diabetes. -
How does Dapagliflozin work?
It works by helping the kidneys to remove glucose from the bloodstream through the urine. -
Who is Dapagliflozin for?
It's prescribed for adults with type 2 diabetes to improve blood sugar control. -
How is Dapagliflozin taken?
Dapagliflozin is taken orally, usually once a day. -
What are the dosing options for Dapagliflozin?
Common dosages include 5 mg and 10 mg tablets. -
Can Dapagliflozin be used with other diabetes medications?
Yes, it can be used alone or with other diabetes medications like metformin. -
What are the common side effects of Dapagliflozin?
Side effects include urinary tract infections, yeast infections, and increased urination.
See all Dapavel questions (33)
📚 Drug Description Sources:
The information in this Dapavel (dapagliflozin) guide is drawn from pharmaceutical, endocrinology, cardiology, and nephrology sources. Content reflects a decade of clinical experience since dapagliflozin's FDA approval in 2014, the pivotal DECLARE-TIMI 58 cardiovascular outcomes trial, the landmark DAPA-HF and DELIVER trials across heart failure ejection fraction spectrum, and DAPA-CKD for chronic kidney disease regardless of diabetes status. Dapavel is manufactured by Intas Pharmaceuticals as an equivalent generic version of the original AstraZeneca Farxiga.
🏛️ Regulatory and government agencies
- FDA (US Food and Drug Administration) - dapagliflozin US approval January 2014 as Farxiga (AstraZeneca); heart failure with reduced ejection fraction approval 2020; chronic kidney disease approval 2021; heart failure with preserved ejection fraction approval 2023
- EMA (European Medicines Agency) - dapagliflozin European authorisation 2012
- MHRA (UK) - dapagliflozin summary of product characteristics
- Health Canada - dapagliflozin product monographs
- TGA (Australia) - dapagliflozin product information
- CDSCO (India) - dapagliflozin available including Intas Pharmaceuticals' Dapavel generic
📚 Professional societies and clinical guidelines
- ADA Standards of Care in Diabetes - SGLT2 inhibitor positioning
- EASD - joint ADA/EASD consensus reports
- ESC Heart Failure Guidelines 2021 - SGLT2 as pillar of HFrEF and HFpEF therapy
- AHA/ACC/HFSA Heart Failure Guidelines 2022 - class I recommendation
- NICE (UK) NG28 Type 2 Diabetes in Adults
- KDIGO Diabetes in CKD Guidelines 2022 - SGLT2 first-line for diabetic kidney disease
- KDIGO CKD Guidelines 2024 - SGLT2 for CKD regardless of diabetes status
🔬 Landmark clinical research
- DECLARE-TIMI 58 - Wiviott et al. NEJM 2019 - 17,160 type 2 diabetes clients; heart failure hospitalisation reduced 27 percent
- DAPA-HF - McMurray et al. NEJM 2019 - 4,744 clients with HFrEF, diabetic and non-diabetic; primary composite reduced 26 percent
- DAPA-CKD - Heerspink et al. NEJM 2020 - 4,304 CKD clients; primary composite reduced 39 percent; stopped early
- DELIVER - Solomon et al. NEJM 2022 - 6,263 HFpEF clients; primary composite reduced 18 percent
- DAPA-MI - Hlatky et al. Nature Medicine 2024
- Meta-analyses of SGLT2 class effects
📖 Medical references and textbooks
- Williams Textbook of Endocrinology
- Joslin's Diabetes Mellitus
- Braunwald's Heart Disease
- Brenner and Rector's The Kidney
- Goodman and Gilman Pharmacological Basis of Therapeutics
- UpToDate - dapagliflozin clinical monographs
- Lexicomp and Micromedex - dapagliflozin drug interactions
- Circulation, JACC, NEJM, JASN, Diabetes Care - specialised journals
Note: This information is educational and does not replace consultation with an endocrinologist, cardiologist, nephrologist, or general practitioner. Dapagliflozin has multiple approved indications spanning type 2 diabetes glycaemic control, heart failure regardless of diabetes status or ejection fraction, and chronic kidney disease regardless of diabetes status. Dapavel is an Intas Pharmaceuticals generic equivalent to the original AstraZeneca Farxiga. Always follow the treating team's specific instructions.
🩺 Medical Expert Review:
Content based on the published research and clinical practice of authorities in cardiovascular clinical trials, nephrology, and heart failure medicine - the disciplines shaping SGLT2 inhibitor use in modern practice. The following experts represent authoritative research and clinical practice perspectives on dapagliflozin and the broader SGLT2 class.
Prof. Christopher B. Granger, MD, FAHA, FACC
Professor of Medicine; Director, Cardiac Care Unit, Duke University Medical Center; Duke Clinical Research Institute — Durham, North Carolina, USA
Prof. Granger has led numerous landmark cardiovascular clinical trials over three decades. Past chair of major diabetes-cardiovascular outcomes committees. His scholarship on acute coronary syndromes, anticoagulation, atrial fibrillation, and cardiovascular clinical trials methodology continues to shape international cardiology practice.
Prof. Peter Rossing, MD, DMSc
Chief Physician and Head of Complications Research, Steno Diabetes Center Copenhagen; Professor of Medicine, University of Copenhagen — Copenhagen, Denmark
Prof. Rossing has led numerous major diabetes and kidney disease clinical trials including SGLT2 inhibitor and endothelin receptor antagonist studies. His scholarship on diabetic kidney disease pathophysiology, biomarkers, and pharmacological progression prevention continues to shape international nephrology and endocrinology practice.
Prof. David Z.I. Cherney, MD, PhD, FRCP(C)
Professor of Medicine, University of Toronto; Nephrologist and Clinician Scientist, Toronto General Hospital, University Health Network — Toronto, Ontario, Canada
Prof. Cherney has published extensively on SGLT2 inhibitor renal mechanisms and clinical effects in diabetic kidney disease. His scholarship on diabetes and kidney disease, cardiovascular-renal interactions, and pharmacological mechanisms continues to shape modern nephrology practice.
Prof. Bertram Pitt, MD
Professor of Medicine Emeritus, University of Michigan School of Medicine — Ann Arbor, Michigan, USA
Prof. Pitt has led numerous landmark heart failure clinical trials over five decades including the RALES, EPHESUS, and EMPHASIS-HF trials that established mineralocorticoid receptor antagonists in heart failure. His scholarship on neurohormonal antagonism in heart failure, aldosterone biology, and cardiorenal-metabolic disease has profoundly shaped cardiology practice worldwide.
Prof. Robert J. Mentz, MD
Professor of Medicine; Chief, Heart Failure Section, Duke University Medical Center; Duke Clinical Research Institute — Durham, North Carolina, USA
Prof. Mentz has led numerous heart failure clinical trials and contributed to SGLT2 inhibitor evidence base. His scholarship on heart failure clinical trials methodology, health services research, and implementation of guideline-directed medical therapy continues to shape modern heart failure practice.
More Diabetes Medications




