Buy Linox (Generic Linezolid) Online — Oxazolidinone Antibiotic for MRSA, VRE & Drug-Resistant Gram-Positive Infections

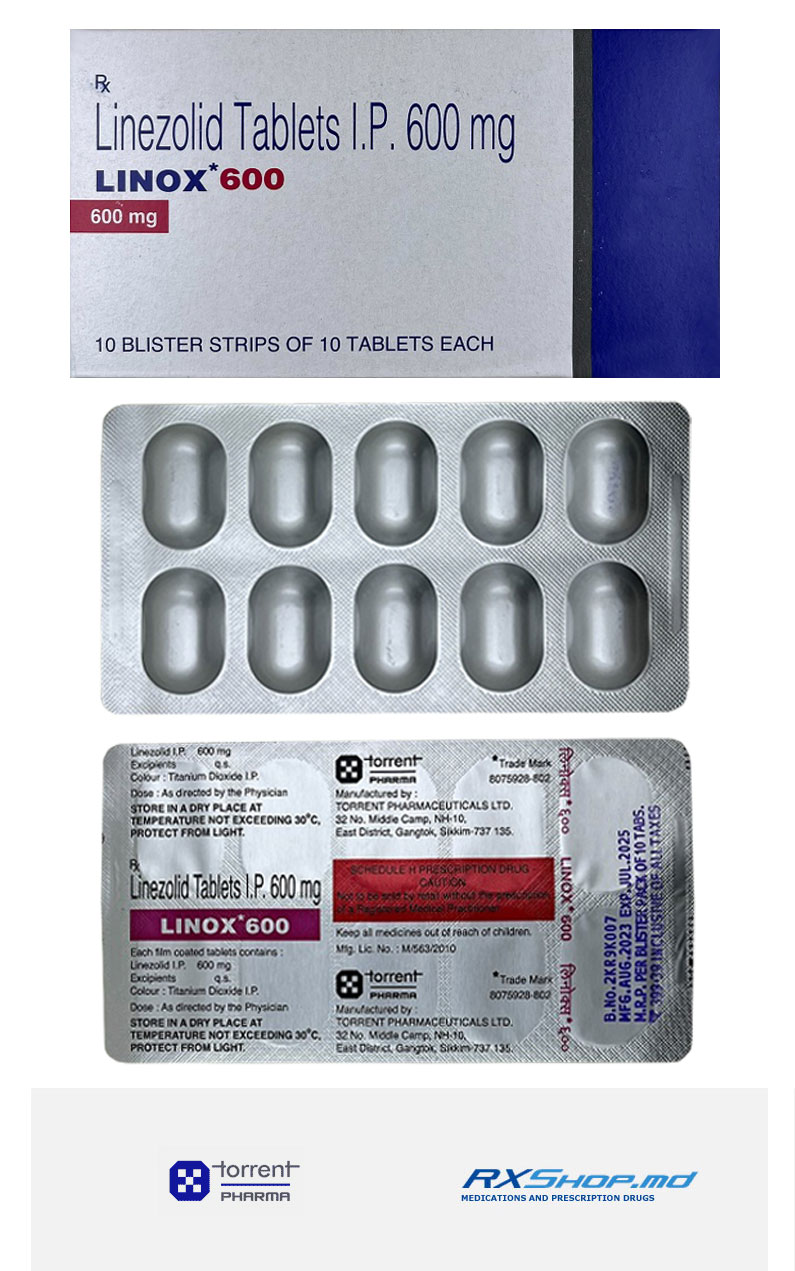
Linox is the Cipla-brand form of linezolid, a first-in-class oxazolidinone antibiotic reserved for infections caused by drug-resistant gram-positive bacteria including methicillin-resistant Staphylococcus aureus (MRSA), vancomycin-resistant Enterococcus (VRE), and penicillin-resistant Streptococcus pneumoniae. Since its FDA approval in April 2000 under the Zyvox brand from Pharmacia and Upjohn, linezolid has become a foundational agent in hospital and outpatient management of serious resistant infections that historically required intravenous vancomycin or daptomycin.
What makes linezolid clinically distinctive is its combination of 100 percent oral bioavailability and reliable tissue penetration into lung, skin, and bone. Because the oral dose and intravenous dose are identical (600 mg twice daily), patients can be transitioned from hospital IV therapy to outpatient oral therapy without adjustment and often without extended hospital stay. This IV-to-oral switch capability for a MRSA-active agent is one of the most valuable stewardship features of the modern antibiotic formulary.
Linezolid works through a unique mechanism: it binds to the 50S bacterial ribosomal subunit at a site not shared with other protein synthesis inhibitors, preventing formation of the 70S initiation complex. This binding location means no cross-resistance with other classes including macrolides, chloramphenicol, aminoglycosides, or tetracyclines. Linezolid is bacteriostatic against most staphylococci and enterococci and bactericidal against streptococci.
Linezolid's ability to cross the blood-brain barrier and reach therapeutic concentrations in bone, lung epithelial lining fluid, and sanctuary tissues supports its use in complicated skin and soft tissue infections, hospital-acquired and ventilator-associated pneumonia, community-acquired pneumonia with resistant pathogens, diabetic foot infection with MRSA, and off-label roles in multi-drug resistant tuberculosis and osteomyelitis. Its reserve status protects it from broad empirical use, keeping resistance rates low.
Free prescription
Discrete packaging
Have questions?
Quality Assurance

- MRSA Nosocomial Pneumonia: For hospital-acquired pneumonia caused by MRSA — oral and IV formulations supporting therapy continuation;
- MRSA Hospital Acquired Pneumonia: For HAP and VAP caused by MRSA in inpatient settings;
- MRSA Community Acquired Pneumonia: For CAP caused by community-acquired MRSA in selected severe cases;
- VRE Bacteremia: FDA-approved for vancomycin-resistant Enterococcus faecium bacteremia — signature unique indication;
- VRE Infection: For vancomycin-resistant Enterococcus faecium infections including bacteremia and complicated UTI;
- Vancomycin Resistant Enterococcus: For VRE infections where vancomycin is not effective — few alternative therapies exist;
- Complicated Skin Infection MRSA: For complicated MRSA skin and soft tissue infections including diabetic foot infections;
- Uncomplicated MRSA Skin: FDA-approved for uncomplicated skin and skin structure infections caused by MRSA;
- Diabetic Foot MRSA: For diabetic foot infections with MRSA — oral therapy supports outpatient management;
- Cellulitis MRSA Severe: For severe MRSA cellulitis where other oral options have failed or are contraindicated;
- Necrotizing Fasciitis MRSA: For necrotizing fasciitis with MRSA component — combined with clindamycin for toxin suppression;
- MDR Tuberculosis: Off-label critical component of multidrug-resistant tuberculosis treatment — lifesaving for MDR-TB patients;
- XDR Tuberculosis: Off-label component of extensively drug-resistant tuberculosis regimens;
- TB Treatment Adjunct: Critical adjunct in WHO MDR-TB and XDR-TB treatment regimens worldwide;
- Penicillin Resistant Pneumococcus: For pneumonia caused by penicillin-resistant Streptococcus pneumoniae;
- Drug Resistant Gram Positive: For Gram-positive infections where multiple antibiotic resistance limits standard therapy options;
- MRSA Endocarditis: Selective use in MRSA endocarditis when vancomycin intolerant or failed — off-label;
- MRSA Osteomyelitis Step Down: For oral step-down therapy in MRSA osteomyelitis following IV vancomycin;
- MRSA Septic Arthritis: For MRSA septic arthritis — oral step-down therapy following IV treatment;
- IV To Oral Switch Therapy: Same dose IV and oral — supports hospital-to-home discharge in resistant infections;
- Outpatient MRSA Therapy: For outpatient oral therapy of MRSA infections requiring extended treatment;
- CNS MRSA Selective: Selective use in MRSA CNS infections — good CSF penetration when vancomycin not feasible;
- Vancomycin Intolerant Patient: For Gram-positive infections in patients intolerant to vancomycin or with renal impairment.
- Less Cough: Resolution of cough in MRSA pneumonia as bacterial infection clears;
- Better Breathing: Improvement in respiratory function as resistant pneumonia resolves;
- Less Chest Pain: Reduction in pleuritic chest pain associated with MRSA pneumonia;
- Better Wound Healing: Resolution of complicated MRSA skin and diabetic foot infections;
- Less Drainage: Resolution of purulent drainage from MRSA wound infections;
- Better Energy: Recovery from severe systemic infection-related fatigue;
- Better Appetite: Restoration of appetite as systemic infection resolves;
- Lifesaving Recovery: Critical for MRSA and VRE infections where few alternatives exist;
- Outpatient Continuation: Oral formulation supports hospital-to-home discharge with continuity of resistant infection therapy;
- Faster Hospital Discharge: 100% oral bioavailability supports earlier hospital discharge in resistant infections;
- Better Daily Function: Return to normal activities as serious resistant infection resolves;
- Brand Linox: Affordable Cipla-manufactured generic Linezolid with international quality manufacturing standards;
- Generic Linezolid: Affordable generic Linezolid expanding global access to critical oxazolidinone therapy;
- Zyvox Equivalent: Same Linezolid molecule as original Pfizer brand Zyvox with bioequivalent therapeutic profile;
- Oxazolidinone Antibiotic: First-in-class oxazolidinone with totally novel mechanism — no cross-resistance with other classes;
- Unique 50S Mechanism: Binds unique site on 50S ribosomal subunit preventing 70S initiation complex formation;
- 70S Initiation Complex Inhibitor: Prevents initiation of bacterial protein synthesis — mechanism unlike any other class;
- MRSA Coverage: Excellent activity against methicillin-resistant Staphylococcus aureus — signature unique indication;
- VRE Coverage: Active against vancomycin-resistant Enterococcus faecium — few alternatives exist;
- Vancomycin Resistant Enterococcus: Critical agent for VRE infections including bacteremia and complicated UTI;
- Mycobacterium Tuberculosis Coverage: Critical agent in MDR-TB and XDR-TB treatment regimens worldwide;
- MDR TB Critical: Critical component of multidrug-resistant tuberculosis regimens — transformative for MDR-TB outcomes;
- 100 Percent Oral Bioavailability: Same dose oral and IV without adjustment — unique property among antibiotics;
- IV Oral Switch Antibiotic: Supports rapid IV-to-oral switch — reduces hospitalisation time and costs;
- MRSA Pneumonia Therapy: FDA-approved for MRSA nosocomial and community-acquired pneumonia;
- Diabetic Foot Antibiotic: For complicated MRSA diabetic foot infections requiring extended oral therapy;
- Complicated Skin Infection Therapy: For severe MRSA complicated skin and soft tissue infections;
- No Cross Resistance Class: Novel mechanism means no cross-resistance with other antibiotic classes — reliable when others fail;
- Outpatient Resistant Infection: Oral formulation supports outpatient management of resistant Gram-positive infections;
- Cipla Generic Quality: International quality manufacturing standards meeting global bioequivalence requirements;
- Affordable MRSA Therapy: Generic version significantly cheaper than branded Zyvox — expands access to MRSA therapy;
- WHO Essential Medicine: Listed on the WHO Model List of Essential Medicines for MDR-TB therapy;
- Myelosuppression Warning: Thrombocytopenia, neutropenia, and anemia common particularly with prolonged courses — weekly CBC monitoring;
- 28 Day Maximum Course: Treatment duration typically limited to 28 days to minimise myelosuppression risk;
- Neuropathy Risk Extended: Peripheral and optic neuropathy may occur with extended use beyond 28 days;
- Serotonin Syndrome Risk: Weak MAO inhibitor — avoid SSRIs, SNRIs, triptans, and other serotonergic drugs;
- Tyramine Avoidance: Avoid tyramine-rich foods (aged cheese, cured meat, wine) due to MAO inhibition;
- Hypoglycemia Risk Diabetic: Particularly in diabetics on insulin or sulfonylureas — monitor blood glucose;
- Lactic Acidosis Risk: Risk of lactic acidosis — monitor with prolonged use;
- Stable Storage: Tablets stable at room temperature — oral suspension stable for 3 weeks after reconstitution;
- Globally Available: Widely supplied in international markets in branded (Zyvox) and generic (Linox, Lizolid) forms.
Generic Linox (Linezolid 600 mg) Medication guide:
📖 What is Linox and where linezolid fits in modern resistant infection care
Linox is the Cipla brand of linezolid, the first commercially available member of the oxazolidinone antibiotic class. Linezolid entered clinical practice in April 2000 under the Zyvox brand from Pharmacia and Upjohn (later Pfizer), and Cipla now produces the generic form widely used internationally.
🔑 Key facts at a glance
- Class: oxazolidinone (first-in-class 2000)
- Mechanism: 50S ribosomal subunit binding, blocks translation initiation
- Oral bioavailability: 100 percent — IV-equivalent oral
- Half-life: 4 to 6 hours (adult)
- Standard dose: 600 mg IV or PO every 12 hours
- Elimination: partly non-renal — no dose adjustment for renal impairment
- Pregnancy category: C
- MAO inhibitor: reversible non-selective — important for drug interactions
Linezolid's clinical role is defined by coverage of drug-resistant gram-positive bacteria: methicillin-resistant Staphylococcus aureus (MRSA), vancomycin-resistant Enterococcus (VRE), penicillin-resistant Streptococcus pneumoniae, and other gram-positive pathogens where beta-lactams are ineffective. Because linezolid binds to a ribosomal site not shared with other protein synthesis inhibitors, it has no cross-resistance with macrolides, tetracyclines, aminoglycosides, or chloramphenicol.
⚠️ Serious adverse effects to know upfront
- Thrombocytopenia — dose-limiting toxicity, time-dependent (see section 20)
- Peripheral neuropathy and optic neuropathy — with prolonged use over 28 days
- Serotonin syndrome — interaction with SSRIs, SNRIs, MAOIs, other serotonergic agents
- Lactic acidosis — rare mitochondrial toxicity
- Hypoglycemia in diabetics on sulfonylureas or insulin
✅ Why linezolid remains a reserve agent
Linezolid's unique mechanism, 100 percent oral bioavailability enabling IV-to-oral switch, and lack of cross-resistance make it invaluable for resistant gram-positive infections. Its reserve status — not used empirically for common infections — protects it from the resistance selection pressure that erodes broader-use agents.
🕑 History: 2000 Pharmacia approval and the first oxazolidinone
Linezolid's development represented a milestone in antibacterial drug discovery: it was the first entirely new antibiotic class approved by the FDA in more than 35 years (since nalidixic acid, the first quinolone, in 1962). Oxazolidinones had shown antibacterial promise in DuPont laboratories in the 1980s but were shelved for hepatotoxicity; the Pharmacia team optimised the scaffold to produce linezolid.
| Year | Milestone |
|---|---|
| 1980s | DuPont identifies oxazolidinone scaffold with gram-positive antibacterial activity |
| 1990s | Pharmacia and Upjohn optimises the scaffold to yield linezolid (PNU-100766) |
| April 2000 | FDA approval NDA 021130 for Zyvox tablets and IV formulation |
| 2001 | First VRE bacteremia case reports establishing linezolid role |
| 2003 | Pfizer acquires Pharmacia and takes over Zyvox marketing |
| 2005 to 2010 | Recognition of serotonin syndrome risk with SSRIs prompts label update |
| 2011 | IDSA MRSA Treatment Guidelines position linezolid as first-line for MRSA pneumonia and complicated SSTI |
| 2012 | ZEPHyR trial published (Wunderink et al) — linezolid clinical success advantage over vancomycin for MRSA pneumonia |
| 2014 | Tedizolid (Sivextro) approved — second oxazolidinone, once daily, better safety profile |
| 2015 onwards | Generic linezolid enters US market; Cipla and other manufacturers produce international brands including Linox |
| 2019 | WHO Consolidated TB Guidelines place linezolid as Group A first-line for MDR-TB regimens |
| 2020 to present | Emerging linezolid resistance monitored (cfr, optrA genes); stewardship measures preserve activity |
🧪 Why a new class mattered
By the late 1990s, MRSA had become the dominant hospital pathogen in many US and European centres, and VRE was emerging as a significant threat. Available treatments — vancomycin, teicoplanin, and older agents — had reliability, tissue penetration, or toxicity issues. Linezolid's oral formulation with 100 percent bioavailability was particularly transformative: for the first time, a MRSA-active oral agent enabled outpatient management of infections that previously required IV vancomycin and hospitalisation.
⚙️ Mechanism: unique 50S ribosomal binding blocks translation initiation
Linezolid inhibits bacterial protein synthesis through a unique mechanism not shared with any other antibiotic class. It binds to the 50S ribosomal subunit at the P-site, preventing formation of the functional 70S initiation complex needed to begin protein synthesis.
🧬 The molecular story
- Linezolid diffuses passively into bacterial cells and reaches the 50S ribosomal subunit
- Binds to the 23S rRNA at domain V of the peptidyl transferase center
- Prevents f-Met-tRNA binding to the ribosomal P-site
- Without initiator tRNA in place, the 70S initiation complex cannot form
- Protein synthesis is halted before the first peptide bond is formed
- Bacteria cannot produce essential proteins — growth stops
🔬 Bacteriostatic vs bactericidal
- Bacteriostatic against staphylococci and enterococci
- Stops growth; immune system clears infection. This is why linezolid combined with rifampin or aminoglycosides is sometimes used for deep-seated staphylococcal infection.
- Bactericidal against streptococci
- Directly kills streptococci — relevant for CAP with resistant pneumococcus.
🔑 Why the unique binding site matters
- Other protein synthesis inhibitors (macrolides, chloramphenicol, aminoglycosides, tetracyclines) bind different ribosomal sites
- No cross-resistance with these other classes
- Bacteria resistant to macrolides remain susceptible to linezolid
- MRSA and VRE (resistant to many classes) remain susceptible to linezolid
- This is why linezolid is a genuine reserve agent for resistant gram-positives
🔴 Resistance mechanisms — monitored but still uncommon
- 23S rRNA mutations (G2576T)
- Point mutations at the linezolid binding site reduce affinity. Selected during prolonged linezolid use, particularly in enterococci. Chromosomal, spread slow.
- cfr gene
- Plasmid-mediated methylase that modifies 23S rRNA. Confers cross-resistance to linezolid, chloramphenicol, streptogramin A, pleuromutilins. Can spread between bacterial species.
- optrA gene
- Plasmid-mediated ABC transporter conferring linezolid and tedizolid resistance. Increasingly reported in enterococci and staphylococci.
- poxtA gene
- Recently identified plasmid-mediated resistance mechanism.
Linezolid resistance remains uncommon globally (under 1 to 2 percent in most surveys) but has been rising in certain enterococcal populations. Stewardship — using linezolid only when indicated and switching to definitive therapy based on culture — preserves activity.
🧬 Linezolid alone in a class: how oxazolidinones differ
The oxazolidinone class remains one of the newest antibiotic classes in clinical use. Only two members are FDA-approved: linezolid and tedizolid. Several others (radezolid, delpazolid) are in various stages of development.
| Agent | FDA approval | Notes |
|---|---|---|
| Linezolid (Zyvox / Linox) | 2000 | Original oxazolidinone; broad indication set; BID dosing |
| Tedizolid (Sivextro) | 2014 | Once daily; less thrombocytopenia; SSTI only; 6-day course |
| Radezolid | Investigational | Extended-spectrum oxazolidinone; some gram-negative activity |
| Delpazolid | Investigational | Being studied for TB use |
🔗 Where linezolid stands out among oxazolidinones
- Broadest FDA indication set — pneumonia (CAP, HAP, VAP), SSTI, VRE bacteremia
- Established WHO TB Group A role for MDR-TB regimens
- Longest safety record and largest clinical experience
- Universal generic availability, lowest cost among oxazolidinones
- IV and oral formulations at equivalent dose
- Extensive PK/PD literature and dose modification guidance
⚖️ Linezolid vs tedizolid at a glance
Tedizolid is a newer oxazolidinone with several improvements over linezolid:
- Once-daily dosing (linezolid is BID)
- Lower thrombocytopenia risk (better safety at 6-day courses)
- Less MAO inhibitor activity, reduced serotonin syndrome risk
- Approved only for complicated SSTI, not pneumonia or bacteremia
- Considerably higher cost (still on-patent)
See section 29 for detailed comparison.
🦠 MRSA, VRE, and resistant gram-positive spectrum
Linezolid's spectrum is focused on drug-resistant gram-positive bacteria. It does not cover gram-negatives, anaerobes below the diaphragm, or atypical intracellular pathogens.
✅ Reliable coverage
- Methicillin-resistant Staphylococcus aureus (MRSA) — hospital and community strains
- MSSA — excellent, though beta-lactams preferred for cost and efficacy
- Coagulase-negative staphylococci including S. epidermidis
- Vancomycin-resistant Enterococcus faecium (VRE-EFm)
- Vancomycin-resistant Enterococcus faecalis (VRE-EF)
- Vancomycin-susceptible Enterococcus faecalis and faecium
- Streptococcus pneumoniae including penicillin-resistant and multi-drug resistant
- Viridans streptococci
- Group A, B, C, G streptococci
- Listeria monocytogenes (bacteriostatic)
- Corynebacterium jeikeium
- Nocardia species — some activity
- Mycobacterium tuberculosis — including MDR and XDR strains
- Non-tuberculous mycobacteria including M. abscessus — some activity
⛔ No coverage
- All gram-negative bacteria — E. coli, Klebsiella, Pseudomonas, Enterobacter, etc.
- Anaerobes below diaphragm including Bacteroides fragilis
- Atypical intracellular pathogens — Mycoplasma, Legionella, Chlamydia at standard doses
- Fungi and parasites
- Bacteria with cfr or optrA gene plasmid-mediated resistance
🧪 Coverage strategy
Linezolid is a focused gram-positive agent. For polymicrobial infections (diabetic foot ulcer, intra-abdominal infection), it is combined with a gram-negative and anaerobe-active agent. For empirical treatment where gram-negatives are possible, linezolid is paired with a beta-lactam or a fluoroquinolone. Empirical linezolid monotherapy is only appropriate when the pathogen is known or highly suspected to be gram-positive resistant.
💉 100 percent oral bioavailability and food independence
Linezolid's pharmacokinetics are among the most favorable of any modern antibiotic: 100 percent oral bioavailability, food-independent absorption, wide tissue distribution, and predictable half-life supporting BID dosing.
| PK parameter | Value |
|---|---|
| Oral bioavailability | 100 percent — complete IV equivalence |
| Food effect | Minimal — can take with or without food |
| Time to peak (Cmax) | 1 to 2 hours |
| Serum peak (600 mg dose) | 15 to 20 mcg/mL |
| Protein binding | 31 percent (low) |
| Volume of distribution | 40 to 50 L (approximates total body water) |
| Serum half-life | 4 to 6 hours |
| Half-life in renal impairment | Modest increase; no dose adjustment |
| Renal excretion | 30 to 35 percent unchanged; 65 to 70 percent metabolised |
| Metabolism | Non-enzymatic oxidation; not CYP substrate |
| PK/PD driver | Time-dependent (T>MIC 40 to 50 percent) and AUC/MIC |
🌐 Tissue distribution highlights
- Lung epithelial lining fluid
- Concentrations 2 to 4 times serum — foundation of MRSA pneumonia efficacy
- Bone
- 40 to 60 percent serum — supports osteomyelitis oral step-down role
- Skin and soft tissue
- Concentrations exceed serum in skin blister fluid — supports SSTI use
- Cerebrospinal fluid
- 30 to 100 percent serum with inflamed meninges — supports gram-positive meningitis alternative
- Prostate
- Good penetration — niche role for MRSA prostatitis
- Intracellular
- Some intracellular activity for TB and Nocardia
🔄 The IV-to-oral switch superpower
Because linezolid oral bioavailability is 100 percent and the oral and IV doses are identical (600 mg every 12 hours), IV-to-oral switch requires no dose adjustment. Once a patient tolerates oral medications and is clinically improving, the switch happens seamlessly. This is transformative for MRSA infections that would otherwise require prolonged IV vancomycin: outpatient antibiotic therapy for MRSA becomes feasible.
🏥 FDA-approved indications
Linezolid's FDA-approved indications reflect its role as a reserve agent for resistant gram-positive infections. Empirical use for common infections is not appropriate.
🎯 FDA-approved indications
- Vancomycin-resistant Enterococcus faecium infections including concurrent bacteremia
- Nosocomial pneumonia caused by Staphylococcus aureus (MSSA and MRSA) or Streptococcus pneumoniae (penicillin susceptible)
- Community-acquired pneumonia caused by S. pneumoniae including multi-drug resistant strains, and concurrent bacteremia
- Complicated skin and skin structure infections including diabetic foot infection without concomitant osteomyelitis, caused by MSSA, MRSA, S. pyogenes, S. agalactiae
- Uncomplicated skin and skin structure infections caused by MSSA and S. pyogenes
| Off-label but supported use | Framework |
|---|---|
| Multi-drug resistant tuberculosis | WHO Group A first-line for MDR-TB regimens |
| MRSA bone and joint infection oral step-down | After IV loading and clinical improvement |
| MRSA bacteremia salvage (persistent) | Combination therapy with daptomycin considered |
| Diabetic foot with osteomyelitis | Considered after IV loading and orthopaedic input |
| Gram-positive meningitis alternative | When vancomycin not usable; combined with beta-lactam |
| Nocardia infection | Combination therapy with sulfonamide |
| M. abscessus and NTM infections | Part of multi-drug regimens |
🧪 Not indicated for
Uncomplicated cystitis, uncomplicated bronchitis, uncomplicated sinusitis, viral infections, empirical treatment of undifferentiated fever, and any indication where a beta-lactam or narrower agent would work. Empirical linezolid use is reserved for the situations where MRSA is likely or documented.
🤕 Complicated SSTI with MRSA suspicion
Complicated skin and skin structure infection (cSSTI) with MRSA suspicion is one of the most established linezolid indications. Linezolid is equivalent to vancomycin in efficacy per multiple RCTs but has the additional advantage of an oral formulation enabling outpatient management.
| cSSTI scenario | Linezolid role |
|---|---|
| Purulent SSTI with MRSA risk (no severe features) | TMP-SMX or doxycycline first-line; linezolid alternative |
| Complicated cellulitis with MRSA suspicion | Linezolid PO or IV first-line alternative to vancomycin |
| Diabetic foot ulcer with MRSA | Linezolid PO or IV plus gram-negative and anaerobe coverage |
| Post-surgical wound infection with MRSA | Linezolid oral step-down after debridement |
| Necrotising fasciitis | Not first-line; use vancomycin + broad-spectrum + clindamycin |
| Uncomplicated MSSA cellulitis | Cephalexin or dicloxacillin first-line; linezolid not appropriate |
✅ Why linezolid fits cSSTI with MRSA
- Excellent skin and soft tissue penetration — concentrations exceed serum in blister fluid
- Oral formulation enables outpatient management or early hospital discharge
- Effective against streptococci (co-pathogens in cellulitis)
- No renal dose adjustment simplifies elderly outpatient use
- Weigelt J et al 2005 trial showed clinical success comparable to vancomycin
- IDSA MRSA 2011 guidelines endorse linezolid as first-line alternative
🔴 What linezolid does NOT do for cSSTI
- Not gram-negative active — add coverage for diabetic foot with polymicrobial infection
- Not anaerobe active for below-diaphragm anaerobes — add metronidazole for deep infections
- Not appropriate for necrotising fasciitis empirical monotherapy (use vanco + broad gram-negative + clindamycin for toxin suppression)
- Not appropriate for pure MSSA infection where beta-lactam preferred
📋 Typical cSSTI dosing
Linezolid 600 mg PO or IV every 12 hours for 10 to 14 days. Shorter courses (7 to 10 days) may be appropriate for uncomplicated MSSA cellulitis. Longer courses for deep tissue infection or associated osteomyelitis (see off-label section 12).
🏥 Nosocomial and ventilator-associated pneumonia with MRSA
Hospital-acquired and ventilator-associated pneumonia (HAP/VAP) with MRSA suspicion is one of linezolid's most established roles. The ATS-IDSA 2016 HAP/VAP guidelines position linezolid alongside vancomycin as empirical MRSA coverage.
🎯 ATS-IDSA framework
Empirical MRSA coverage is added to HAP/VAP regimens when:
- Prior MRSA colonisation or infection
- Prior IV antibiotic use in the last 90 days
- Local MRSA prevalence in HAP/VAP over 20 percent
- Severe presentation requiring mechanical ventilation or vasopressors
- Concomitant risk factors
Either vancomycin or linezolid is appropriate first choice.
🧪 The ZEPHyR trial and its implications
The ZEPHyR trial (Wunderink RG et al, Clin Infect Dis 2012) compared linezolid 600 mg IV every 12 hours with vancomycin dose-adjusted for HAP with proven MRSA. Linezolid showed higher clinical success (57.6% vs 46.6%) with equivalent microbiologic outcomes. Renal effects were fewer in the linezolid arm. This trial supports linezolid as at least equivalent, and possibly superior, to vancomycin for MRSA HAP/VAP.
| Scenario | Linezolid preference over vancomycin |
|---|---|
| Baseline acute kidney injury | Linezolid preferred (no renal effects) |
| Concurrent nephrotoxic agents | Linezolid preferred |
| Vancomycin allergy or intolerance | Linezolid preferred |
| Vancomycin MIC creep (MIC 1.5 to 2) | Linezolid preferred |
| Need for IV-to-oral switch | Linezolid preferred |
| Concurrent SSRI or MAOI | Vancomycin preferred (serotonin risk) |
| Baseline thrombocytopenia | Vancomycin preferred |
| Anticipated prolonged course (over 14 days) | Depends on toxicity balance |
📋 Standard HAP/VAP dosing
Linezolid 600 mg IV every 12 hours as component of empiric regimen; oral switch to 600 mg PO BID once tolerating oral medications and clinically improving. Course typically 7 to 14 days based on clinical response; longer for complicated bacteremic pneumonia or with abscess formation.
🫁 Community-acquired pneumonia with resistant pathogen risk
Linezolid's role in community-acquired pneumonia (CAP) is narrow but defined. It is not first-line for typical CAP but appropriate for CAP with resistant pathogen risk or in specific patient scenarios.
| CAP scenario | Linezolid role |
|---|---|
| Outpatient healthy adult CAP | Not indicated; use amoxicillin or doxycycline |
| Inpatient non-severe CAP | Not first-line; use beta-lactam + macrolide |
| CAP with prior MRSA colonisation | Add linezolid or vancomycin to CAP regimen |
| Post-influenza pneumonia with S. aureus risk | Add linezolid or vancomycin |
| Necrotising pneumonia (PVL-positive) | Linezolid preferred (toxin suppression like clindamycin) |
| CAP in penicillin anaphylaxis with pneumococcal resistance risk | Consider linezolid for resistant pneumococcus coverage |
| CAP with septic shock and MRSA suspicion | Add linezolid to broad-spectrum regimen |
🧪 The necrotising pneumonia niche
Panton-Valentine leukocidin (PVL) producing MRSA can cause rapidly progressive necrotising pneumonia particularly following influenza. Linezolid suppresses toxin production in addition to killing the bacteria — similar to clindamycin's role for group A streptococcal toxic shock. In severe MRSA pneumonia with toxin-mediated features, linezolid may be preferred over vancomycin for this reason.
📋 Standard CAP dosing when linezolid is added
Linezolid 600 mg IV or PO every 12 hours combined with the standard CAP regimen (ceftriaxone + macrolide or respiratory fluoroquinolone). Course typically 7 to 14 days based on clinical response and organism.
🧫 Vancomycin-resistant enterococcus infections
Vancomycin-resistant Enterococcus (VRE) infection is one of the most challenging modern hospital pathogens. Linezolid is one of two main oral options for VRE alongside daptomycin (IV only) and, for E. faecalis, ampicillin.
| VRE scenario | Linezolid role |
|---|---|
| VRE bacteremia | First-line option alongside daptomycin |
| VRE endocarditis | Combination therapy considered; daptomycin high-dose often preferred |
| VRE complicated UTI | Linezolid PO acceptable if concurrent bacteremia |
| VRE colonisation (asymptomatic) | Do not treat |
| VRE intra-abdominal infection | Linezolid PO or IV plus gram-negative and anaerobe coverage |
| VRE catheter-related infection | Linezolid or daptomycin plus catheter removal if feasible |
🔑 Why linezolid matters for VRE
- E. faecium is intrinsically resistant to cephalosporins and often to ampicillin (unlike E. faecalis)
- Vancomycin resistance eliminates the mainstay glycopeptide option
- Aminoglycoside high-level resistance often accompanies vancomycin resistance
- Linezolid remains reliably active against most VRE (under 5 percent resistance)
- Oral formulation enables outpatient follow-through after IV bacteremia clearance
⚖️ Linezolid vs daptomycin for VRE bacteremia
Multiple observational studies have compared linezolid and daptomycin for VRE bacteremia. Neither has a definitive efficacy advantage. Choice is often driven by patient-specific factors: renal function (both fine), platelets (linezolid concern), serotonergic co-medications (linezolid concern), CPK baseline (daptomycin concern), lung penetration (linezolid better if concurrent pneumonia). See section 28 for detailed comparison.
⚠️ Emerging linezolid resistance
Linezolid resistance in VRE has emerged in some healthcare facilities, particularly through plasmid-mediated cfr and optrA genes. Institutions with linezolid-resistant VRE outbreaks require heightened stewardship and molecular surveillance. When resistance is documented, alternative options include daptomycin high-dose combinations or specialist consultation for salvage regimens.
🩺 Off-label uses: drug-resistant tuberculosis and bone infection
Linezolid's activity against Mycobacterium tuberculosis including MDR and XDR strains has established a major off-label role: linezolid is now a WHO Group A first-line drug for MDR-TB regimens.
🧪 WHO Group A classification (2019)
The WHO Consolidated TB Guidelines classify anti-TB drugs by preference:
- Group A (three drugs, first choices): levofloxacin or moxifloxacin, bedaquiline, linezolid
- Group B: clofazimine, cycloserine or terizidone
- Group C: additional drugs when Group A/B insufficient
A modern all-oral MDR-TB regimen typically combines all three Group A drugs plus one or two additional agents for 18 to 20 months.
| TB scenario | Linezolid dosing |
|---|---|
| MDR-TB regimen | 600 mg PO daily (or 300 mg daily after toxicity) |
| Pre-XDR and XDR-TB | 600 mg PO daily as core component |
| BPaL regimen (Nix-TB trial) | Bedaquiline + pretomanid + linezolid 600 mg for 6 months |
| TB in NTM (M. abscessus) | 600 mg PO BID as multi-drug regimen component |
⚠️ Toxicity monitoring in TB use
Prolonged linezolid (months) for TB carries substantial cumulative toxicity risk requiring proactive monitoring:
- Weekly CBC for first 4 weeks, then monthly (thrombocytopenia)
- Baseline and periodic visual acuity, color vision, Amsler grid
- Baseline and periodic neurologic assessment (peripheral neuropathy)
- Lactate check if unexplained metabolic acidosis
- Dose reduction (600 mg to 300 mg) considered if toxicity develops
- Discontinuation and alternative regimen if severe adverse effect
🩺 Other off-label uses
- MRSA bone and joint infection oral step-down
- After 2 to 6 weeks IV loading (vancomycin or daptomycin) with orthopaedic input and source control, transition to oral linezolid or in combination with rifampin. Course 6 to 12 weeks total.
- Persistent MRSA bacteremia salvage
- Linezolid combined with daptomycin or ceftaroline for salvage after vancomycin failure.
- Nocardia infection
- Linezolid as component of multi-drug therapy for pulmonary or disseminated nocardiosis.
- Gram-positive meningitis when vancomycin unusable
- Excellent CSF penetration supports this role. Combination with beta-lactam preferred.
💊 Adult dosing: 600 mg twice daily
Linezolid dosing is refreshingly simple: 600 mg every 12 hours for essentially all indications, with no renal dose adjustment and no weight-based calculation for adults. Oral and IV doses are identical.
| Indication | Adult regimen | Duration |
|---|---|---|
| Complicated SSTI with MRSA | 600 mg IV or PO every 12 h | 10 to 14 days |
| Uncomplicated SSTI (MSSA, strep) | 400 or 600 mg PO every 12 h | 10 to 14 days |
| Nosocomial pneumonia (HAP/VAP) | 600 mg IV every 12 h | 7 to 14 days |
| Community-acquired pneumonia | 600 mg IV or PO every 12 h | 7 to 14 days |
| VRE bacteremia | 600 mg IV every 12 h | 14 to 28 days (source-controlled) |
| MDR-TB regimen | 600 mg PO daily (or 300 mg after toxicity) | 6 to 20 months |
| MRSA osteomyelitis oral step-down | 600 mg PO every 12 h | 6 to 12 weeks total (IV + PO) |
| Nocardia component | 600 mg PO every 12 h | Months (multi-drug regimen) |
🍴 Administration
- Take with or without food — no clinically meaningful food effect
- Swallow tablets whole with a full glass of water
- Oral suspension available for children or patients unable to swallow tablets
- IV infusion over 30 to 120 minutes when IV route used
- Complete the full course even if symptoms resolve early
- Report side effect warning signs immediately (see sections 20 to 26)
⚠️ Duration matters for toxicity
Linezolid toxicity accumulates with time. Courses under 14 days generally have low serious adverse effect rates. Courses over 28 days substantially amplify risk for thrombocytopenia, peripheral neuropathy, and optic neuropathy. TB and osteomyelitis regimens over months require dedicated toxicity monitoring (see section 12 for TB and sections 20 to 21 for neuropathy).
👶 Pediatric dosing
Children over 11 years: 600 mg every 12 hours (adult dose). Children under 11 years: 10 mg/kg every 8 hours. Neonates and infants: 10 mg/kg every 8 to 12 hours based on age. Pediatric use requires PID specialist input.
🔬 Renal and hepatic considerations
Linezolid's elimination profile is unusual and clinically convenient: partly non-renal, partly renal, and not requiring dose adjustment across a wide range of renal function.
✅ No renal dose adjustment for standard use
- Any CrCl: 600 mg every 12 hours — no adjustment
- Approximately 30 to 35 percent renal excretion of unchanged drug
- 65 to 70 percent metabolised by non-enzymatic oxidation
- Not a CYP substrate — hepatic function does not change dosing
- Approximately 30 percent removed by hemodialysis — give post-dialysis on dialysis days if possible
| Situation | Dose adjustment |
|---|---|
| Normal renal function | 600 mg every 12 h (no change) |
| Mild to moderate renal impairment | 600 mg every 12 h (no change) |
| Severe renal impairment (CrCl below 30) | 600 mg every 12 h (no change) but monitor for adverse effects — metabolite accumulates |
| Hemodialysis | 600 mg every 12 h; give after dialysis on dialysis days if timing allows |
| Peritoneal dialysis | 600 mg every 12 h (no change) |
| CRRT | 600 mg every 12 h (no change); consider TDM in ICU |
| Hepatic impairment | 600 mg every 12 h (no change) |
🧪 Why this profile is a stewardship advantage
Vancomycin requires weight-based dose calculation, trough level monitoring, and dose adjustment for changing renal function. Linezolid is fixed-dose across all renal function levels. This simplifies prescribing, reduces pharmacy time, avoids dose-related errors, and eliminates the acute kidney injury risk that complicates vancomycin use. It is one of the strongest arguments for linezolid over vancomycin in patients with unstable renal function.
⚠️ Watch the metabolite in severe renal impairment
While parent drug dosing does not change, two inactive metabolites accumulate in severe renal impairment. Some case reports link this accumulation with heightened adverse effect risk (lactic acidosis, hypoglycemia) in dialysis patients on prolonged courses. Monitor closely; consider therapeutic drug monitoring in specialist settings when prolonged treatment is needed with ESRD.
💥 Drug interactions and MAO inhibitor status
Linezolid is a reversible non-selective MAO inhibitor. This single pharmacologic property drives its most important drug interactions and has no equivalent in any other antibiotic.
🔴 Serotonergic interactions — risk of serotonin syndrome
Concurrent use with serotonergic agents can cause life-threatening serotonin syndrome. AVOID or use with extreme caution:
- SSRIs — fluoxetine, sertraline, paroxetine, citalopram, escitalopram
- SNRIs — venlafaxine, duloxetine, desvenlafaxine
- TCAs — amitriptyline, nortriptyline
- Triptans — sumatriptan, rizatriptan
- Meperidine, tramadol, methadone, fentanyl
- MAOIs — selegiline, phenelzine, tranylcypromine, isocarboxazid
- Buspirone, dextromethorphan
- Lithium
- Ecstasy (MDMA), cocaine if in recreational context
- St. John's wort, 5-HTP supplements
🚨 Adrenergic interactions — hypertensive crisis risk
MAO inhibition means adrenergic agents can cause severe hypertension:
- Pseudoephedrine and phenylephrine (OTC cold medications)
- Dopamine, epinephrine, norepinephrine IV pressors — use lower doses, monitor closely
- Amphetamines and derivatives
- Cocaine
- Tyramine-rich foods in high quantities (aged cheeses, cured meats, red wine) — theoretical risk
| Interaction category | Management |
|---|---|
| Serotonergic (SSRI/SNRI/TCA) | If linezolid essential: hold SSRI/SNRI 2 to 5 weeks before; monitor for serotonin syndrome |
| MAOI — other | Wash out 2 weeks before starting linezolid |
| Sympathomimetics oral | Avoid; use non-pseudoephedrine cold agents |
| IV vasopressors | Use lower doses, titrate carefully, monitor BP |
| Tyramine-rich foods | Modest restriction; avoid extremes; unlike irreversible MAOIs |
| Insulin, sulfonylureas | Monitor blood glucose — hypoglycemia risk (see section 24) |
| Warfarin | Modest interaction; monitor INR |
| Rifampin | May reduce linezolid levels — consider dose adjustment in TB use |
🧪 Practical framework
Before every linezolid prescription, review medication list explicitly for SSRIs, SNRIs, TCAs, MAOIs, tramadol, meperidine, methadone, dextromethorphan, and adrenergic agents. If any of these are present, either substitute an alternative antibiotic (vancomycin, daptomycin) or plan the wash-out period. This is one of the most consequential drug interaction screens in modern antibiotic prescribing.
🧠 Serotonin syndrome and SSRI concerns
Serotonin syndrome is the most consequential MAO inhibitor interaction with linezolid. It is life-threatening but preventable with proper drug interaction screening and management.
🔴 Serotonin syndrome features (Hunter Criteria)
Diagnosis requires exposure to serotonergic agent PLUS one of:
- Spontaneous clonus
- Inducible clonus PLUS agitation or diaphoresis
- Ocular clonus PLUS agitation or diaphoresis
- Tremor and hyperreflexia
- Hypertonia PLUS temperature above 38 C PLUS ocular or inducible clonus
🧠 Clinical triad
- Cognitive/behavioral
- Agitation, anxiety, restlessness, confusion, hallucinations, coma
- Neuromuscular
- Tremor, hyperreflexia, myoclonus, muscle rigidity (lower extremities more affected), clonus
- Autonomic
- Hyperthermia (can exceed 41 C in severe cases), tachycardia, diaphoresis, mydriasis, diarrhea
🩹 Management
- Discontinue linezolid and all serotonergic agents immediately
- Supportive care: IV fluids, cardiac monitoring, cooling for hyperthermia
- Benzodiazepines for agitation, tremor, myoclonus
- Cyproheptadine (serotonin antagonist) 12 mg initially, then 2 mg every 2 hours until symptoms resolve, for severe cases
- Intubation and paralysis for severe hyperthermia (over 41 C) or rhabdomyolysis
- Most cases resolve within 24 to 72 hours with drug discontinuation
- Avoid all serotonergic agents lifetime after severe episode
- Report to FDA MedWatch
📋 Prevention strategy
- Comprehensive medication review at the point of every linezolid prescription
- Wash-out serotonergic agents 2 to 5 weeks before starting (SSRIs), 5 weeks for fluoxetine
- If linezolid necessary and wash-out impossible: use alternative agent (vancomycin, daptomycin)
- Counsel patient about warning signs
- Do not start SSRI within 24 hours of finishing linezolid
- Include OTC dextromethorphan and St John's wort in the review
⚠️ The urgency dilemma
A patient with MRSA bacteremia on chronic SSRI faces a real clinical tension: linezolid works well for the infection but risks serotonin syndrome. In this scenario, alternatives should be strongly preferred (vancomycin IV, daptomycin IV). If linezolid is genuinely necessary despite SSRI use, this decision should involve pharmacy consultation, careful monitoring, and explicit patient consent.
🤰 Pregnancy category C and lactation
Linezolid is FDA Pregnancy Category C with limited human pregnancy data. Use is generally avoided during pregnancy except when clearly necessary for serious infection without alternatives.
⛔ Pregnancy avoidance
- Category C — animal reproductive toxicity at high doses
- Limited controlled human data
- Crosses the placenta
- Alternative agents (vancomycin, daptomycin) preferred for most MRSA pregnancy indications
- Reserved for serious infection when alternatives are unsuitable or ineffective
| Pregnancy scenario | Preferred alternative |
|---|---|
| MRSA SSTI | Vancomycin IV or beta-lactam if MSSA |
| MRSA pneumonia | Vancomycin IV |
| MRSA bacteremia | Vancomycin IV or daptomycin IV |
| VRE bacteremia | Daptomycin IV; linezolid if no alternative |
| MDR-TB in pregnancy | Consult TB and OB/GYN specialists; linezolid may be used with monitoring |
👶 Lactation
Linezolid passes into breast milk. LactMed advises caution. For short courses, monitor infant for GI symptoms. Extended courses (over 14 days) — consider weaning. Alternative agents may be preferred when nursing mother has options.
🔗 Linox versus other linezolid brands and tedizolid
Since the 2015 generic linezolid entry into major markets, multiple manufacturers produce linezolid under various brand names. Linox is Cipla's brand, widely distributed internationally.
| Brand | Manufacturer | Notes |
|---|---|---|
| Linox | Cipla | India-based generic, widely distributed internationally |
| Zyvox / Zyvoxam | Pfizer | Original brand; still marketed alongside generics |
| Zyvoxid | Pfizer | European market brand |
| Linezolid generic | Multiple: Teva, Mylan, Sandoz, Sun, Aurobindo | Post-patent generic products |
| Tedizolid (Sivextro) | Merck (was Cubist) | Next-generation oxazolidinone; SSTI only; on patent |
⚖️ Linezolid vs tedizolid comparison at a glance
- Dosing frequency
- Linezolid BID; tedizolid once daily
- Indication set
- Linezolid broad (SSTI, pneumonia, VRE); tedizolid SSTI only
- Course length
- Linezolid variable; tedizolid 6-day course for SSTI
- Thrombocytopenia risk
- Higher with linezolid over 10 to 14 days; tedizolid safer at 6-day course
- Serotonin syndrome
- Both are MAO inhibitors; linezolid stronger signal
- Cost
- Linezolid low (generic); tedizolid high (on patent)
See section 29 for detailed clinical comparison.
🤔 Common adverse effects
Linezolid's common adverse effects are mostly mild and manageable at standard doses over short courses. Serious effects (see subsequent sections) become more likely with prolonged use.
| Adverse effect | Approximate frequency | Management |
|---|---|---|
| Nausea | 4 to 8 percent | Take with food; antiemetic if severe |
| Diarrhea | 3 to 8 percent | Hydration; watch for CDI signs |
| Headache | 6 to 12 percent | Usually mild; self-limited |
| Taste disturbance (metallic) | 3 to 6 percent | Resolves after course |
| Insomnia | 2 to 4 percent | Take earlier in day; usually mild |
| Dizziness | 2 to 4 percent | Fall precautions |
| Rash | 2 to 4 percent | Evaluate if extensive; consider discontinuation |
| Anemia | 2 to 5 percent (time-dependent) | Weekly CBC in extended courses |
| Elevated LFTs | 1 to 3 percent | Usually mild; monitor if extended |
| Tongue discoloration | Uncommon | Cosmetic; reversible |
⚠️ Symptoms warranting immediate discontinuation and evaluation
- Easy bruising, petechiae, bleeding (thrombocytopenia) — see section 20
- Vision changes, blurred vision, color vision loss (optic neuropathy) — see section 21
- Numbness, tingling, burning in extremities (peripheral neuropathy) — see section 21
- Agitation, confusion, tremor, sweating (serotonin syndrome) — see section 26
- Unexplained fatigue, muscle pain, difficulty breathing (lactic acidosis) — see section 23
- Hypoglycemia symptoms in diabetic patients — see section 24
- Severe or bloody diarrhea (CDI concern)
- Extensive rash, blistering, mouth sores (SJS, TEN)
- Anaphylaxis — wheezing, throat tightness, hypotension
🩸 Thrombocytopenia: the dose-limiting toxicity
Thrombocytopenia is the dose-limiting toxicity of linezolid. It is dose-dependent and time-dependent: risk rises substantially after 10 to 14 days of therapy, and becomes very common with courses over 28 days.
🩸 Frequency and pattern
- Overall rate 2 to 4 percent in typical 10 to 14 day courses
- Rises to 20 to 30 percent in courses over 14 days
- Rises to 50 to 70 percent in courses over 28 days
- Onset typically 10 to 14 days into therapy, sometimes earlier
- Nadir platelet count varies from mild (100 to 150 x10⁹/L) to severe (below 50 x10⁹/L)
- Bleeding complications rare unless very severe
- Generally reversible within 1 to 2 weeks of discontinuation
🔬 Mechanism
Linezolid inhibits mitochondrial protein synthesis in bone marrow precursors (a consequence of mitochondrial ribosome similarity to bacterial ribosome). This impairs platelet production. The mechanism also explains the anemia and rare pancytopenia (see section 25) that can accompany prolonged linezolid use.
🔴 Amplified risk factors
- Course duration over 14 days — primary risk factor
- Renal impairment (metabolite accumulation)
- Baseline thrombocytopenia or low platelet count
- Concurrent immunosuppression
- Concurrent chemotherapy
- Concurrent other myelosuppressive drugs
- Advanced age
- Liver disease
| Monitoring schedule | Recommendation |
|---|---|
| Baseline CBC | Required before starting therapy |
| Standard course (up to 14 days) | Weekly CBC during therapy |
| Extended course (over 14 days) | CBC every 3 to 5 days |
| Very extended (TB, bone infection) | Weekly CBC for first month, then monthly |
| Post-discontinuation | Follow-up CBC at 1 to 2 weeks after stopping |
🩹 Management thresholds
- Platelets 100 to 150 x10⁹/L
- Continue linezolid; recheck weekly; monitor for bleeding
- Platelets 50 to 100 x10⁹/L
- Consider dose reduction, switch to alternative, or discontinue based on infection severity and alternatives
- Platelets below 50 x10⁹/L or active bleeding
- Discontinue linezolid; switch to alternative; monitor for spontaneous bleeding
- Rebound after discontinuation
- Platelet count usually recovers 1 to 2 weeks after stopping
🦵 Peripheral and optic neuropathy with prolonged use
Peripheral neuropathy and optic neuropathy are among the most concerning linezolid adverse effects because they can be irreversible in some patients. Both are strongly time-dependent, becoming meaningful risks with courses over 28 days.
🦵 Peripheral neuropathy
- Presentation
- Symmetric distal numbness, tingling, burning pain in hands and feet. Sensory more prominent than motor. May include gait unsteadiness.
- Onset
- Typically after 4 weeks (28 days) of therapy. Occasional cases earlier.
- Reversibility
- Partial or complete recovery over weeks to months in most; some patients experience persistent symptoms.
- Mechanism
- Mitochondrial toxicity to peripheral nerve axons.
👁️ Optic neuropathy
- Presentation
- Progressive vision loss, decreased visual acuity, altered color vision (red-green), central or centrocecal scotoma, optic disc pallor on fundoscopy.
- Onset
- Typically after 3 to 4 months of therapy in TB use, or 4 to 12 weeks in bone infection use.
- Reversibility
- Partial recovery in most with immediate discontinuation; some patients have persistent vision impairment.
- Mechanism
- Mitochondrial optic neuropathy affecting retinal ganglion cells and optic nerve.
| Monitoring for prolonged linezolid | Frequency |
|---|---|
| Baseline visual acuity and color vision | Before starting extended therapy |
| Baseline neurologic exam | Before starting extended therapy |
| Visual acuity, color vision testing | Monthly during extended therapy |
| Amsler grid self-testing | Weekly by patient |
| Symptom review for neuropathy | Every visit |
| Ophthalmology referral | If any vision symptom develops |
🩹 Management if neuropathy develops
- Discontinue linezolid immediately at first symptom
- Do not wait to see if symptoms progress — delayed discontinuation is associated with worse outcomes
- Switch to alternative antibiotic if continued treatment needed
- Ophthalmology referral for vision symptoms; neurology for peripheral
- Symptomatic management: gabapentin or pregabalin for painful neuropathy
- Nerve conduction studies for baseline and follow-up if needed
- Lifetime linezolid avoidance for confirmed severe neuropathy
- Report to FDA MedWatch
📋 Practical framework for extended courses
When linezolid is being planned for over 28 days (TB, bone infection, VRE endocarditis suppression), the extended-course toxicity risks must be discussed with the patient explicitly. Consider a lower dose (300 mg daily instead of 600 mg BID) after the first month, if the indication permits, to reduce cumulative toxicity. Some MDR-TB centres routinely use dose reduction to preserve linezolid activity while limiting adverse effects.
❗ Severe adverse effects reference
Severe adverse effects with linezolid concentrate around mitochondrial toxicity (bone marrow suppression, peripheral and optic neuropathy, lactic acidosis) and MAO inhibitor effects (serotonin syndrome, hypertension). Awareness allows early recognition and immediate discontinuation.
🔴 Serious adverse effects requiring immediate discontinuation
- Anaphylaxis
- Rapid hives, angioedema, wheezing, hypotension. Epinephrine, emergency care.
- Severe thrombocytopenia
- Platelets below 50 or active bleeding. See section 20.
- Peripheral neuropathy
- Can be irreversible. See section 21.
- Optic neuropathy
- Can cause permanent vision loss. See section 21.
- Serotonin syndrome
- Agitation, hyperthermia, clonus, autonomic instability. See section 26.
- Lactic acidosis
- Unexplained fatigue, muscle pain, tachypnea. Mitochondrial toxicity. See section 23.
- Severe hypoglycemia
- In diabetics on hypoglycemic agents. See section 24.
- Pancytopenia and severe myelosuppression
- Rare but reported. See section 25.
- Hypertensive crisis
- With sympathomimetic use (pseudoephedrine, cocaine, IV vasopressors). MAO inhibitor effect.
- C. difficile colitis
- Severe watery or bloody diarrhea. Lower risk than clindamycin or fluoroquinolones but possible.
- Hepatotoxicity
- Rare. Elevated LFTs typically mild. Immediate discontinuation for severe.
- SJS, TEN, DRESS
- Rare but reported. Skin sloughing, mucous membrane involvement. Emergency care.
📋 Warning symptoms to counsel patients
- Easy bruising, petechiae, unusual bleeding — possible thrombocytopenia
- Vision changes, blurred vision, color loss — urgent ophthalmology
- Numbness, tingling, burning in hands or feet — stop drug
- Agitation, confusion, tremor, sweating — possible serotonin syndrome
- Unexplained fatigue, muscle pain, difficulty breathing — possible lactic acidosis
- Hypoglycemia symptoms in diabetics — monitor blood glucose
- Severe or bloody diarrhea — possible CDI
- Yellowing of skin or eyes, dark urine — hepatic concern
- Severe headache, chest pain, palpitations — possible hypertensive reaction
- Extensive rash, blistering, mouth sores — severe skin reaction
🧪 Adverse effect context
For short courses (up to 10 to 14 days), linezolid's adverse effect profile is manageable and comparable to vancomycin overall. For extended courses (over 28 days), the toxicity burden becomes substantial, particularly thrombocytopenia and peripheral/optic neuropathy. This time-dependency is why linezolid is best used for defined, time-limited indications where an alternative can take over for prolonged suppression.
🔴 Lactic acidosis: mitochondrial toxicity
Lactic acidosis is a rare but serious linezolid adverse effect caused by mitochondrial protein synthesis inhibition. It typically develops with prolonged therapy (weeks to months) but can occasionally develop earlier.
🔴 Presentation
- Unexplained fatigue and weakness
- Muscle pain, particularly leg cramps
- Nausea and vomiting without other explanation
- Tachypnea and hyperventilation (compensatory)
- Confusion, altered mental status in severe cases
- Elevated serum lactate (over 2 mmol/L, often much higher)
- Anion gap metabolic acidosis on ABG
- Rising creatinine as pattern progresses
🔬 Mechanism
Linezolid binds to mitochondrial ribosomes (evolutionarily similar to bacterial ribosomes). This inhibits mitochondrial protein synthesis, impairing oxidative phosphorylation. Cells shift to anaerobic metabolism, producing excess lactate. The same mechanism explains thrombocytopenia, peripheral and optic neuropathy — all mitochondrial toxicity manifestations at different tissue levels.
🚨 Amplified risk factors
- Course duration over 28 days — primary risk factor
- Renal impairment (metabolite accumulation)
- Underlying mitochondrial disease
- Concurrent metformin (both affect lactate handling)
- Liver disease (impaired lactate clearance)
- Sepsis (already elevated baseline lactate)
- Advanced age
🩹 Management
- Discontinue linezolid immediately
- Check serum lactate, ABG, bicarbonate, creatinine
- IV fluid resuscitation for volume depletion
- Consider hemodialysis for severe acidosis or metabolite removal
- Switch to alternative antibiotic based on infection
- ICU management for severe cases
- Lactate typically improves 3 to 7 days after discontinuation
- Lifetime linezolid avoidance for confirmed case
📋 When to suspect during prolonged linezolid
Any patient on prolonged linezolid (TB, bone infection, VRE suppression) presenting with unexplained fatigue, muscle pain, nausea, or tachypnea should have a serum lactate check. Early recognition is essential — delayed diagnosis with continued therapy can progress to severe acidosis requiring dialysis. Include lactate in the routine monitoring panel for TB regimens.
🍬 Hypoglycemia in diabetic patients
The FDA added hypoglycemia to linezolid labeling after post-marketing reports of severe hypoglycemic events including some fatalities in diabetic patients on hypoglycemic agents.
🔴 Hypoglycemia recognition
- Sweating, tremor, palpitations
- Confusion, dizziness, difficulty concentrating
- Hunger, weakness
- Anxiety, agitation
- Loss of consciousness in severe cases
- Seizures in severe cases
- Can develop within days of starting or later in course
🔴 Highest-risk populations
- Diabetic patients on insulin
- Diabetic patients on sulfonylureas (glyburide, glipizide, glimepiride)
- Diabetic patients on meglitinides (repaglinide, nateglinide)
- Elderly diabetic patients with baseline hypoglycemia unawareness
- Patients with concurrent hepatic or renal impairment
- Patients with poor oral intake during infection
📋 Management strategy
- Before starting linezolid in diabetic patients: increase blood glucose monitoring frequency
- Consider preemptive dose reduction of sulfonylureas or insulin
- Counsel patient about hypoglycemia warning signs
- Ensure patient has fast-acting glucose available (juice, tablets)
- Ensure caregiver awareness for elderly patients
- If hypoglycemia develops: reduce hypoglycemic agent dose, adjust based on pattern
- Severe recurrent hypoglycemia: consider switching antibiotic
- Effect usually resolves within days of discontinuation
⚠️ Elderly diabetic patients
Elderly diabetic patients with baseline hypoglycemia unawareness and concurrent renal impairment are at highest risk. In this population, if MRSA infection requires anti-MRSA therapy, vancomycin or daptomycin may be preferred over linezolid to avoid the hypoglycemia burden. If linezolid is necessary, close glucose monitoring and preemptive hypoglycemic dose reduction are essential.
🩸 Rare pancytopenia and myelosuppression
Beyond isolated thrombocytopenia (see section 20), linezolid can cause broader myelosuppression affecting all blood cell lines. Anemia, leukopenia, and rare pancytopenia have all been reported.
| Cell line affected | Approximate frequency | Duration risk |
|---|---|---|
| Platelets (thrombocytopenia) | 2 to 30 percent (dose-dependent) | Rises after 14 days |
| Red cells (anemia) | 2 to 8 percent | Rises after 14 days |
| White cells (leukopenia) | 1 to 3 percent | Rises after 28 days |
| Pancytopenia (all three) | Rare | Rises after 28 days; more common with pre-existing marrow disease |
🔬 Mechanism
Linezolid mitochondrial toxicity in bone marrow precursor cells impairs production across all cell lineages. Sideroblastic anemia has been described, characterised by ringed sideroblasts on bone marrow biopsy. This changes the differential diagnosis for cytopenia during linezolid therapy.
📋 Monitoring schedule for extended courses
- Baseline CBC before starting
- Weekly CBC during first month
- Every 2 weeks for months 2 to 3
- Monthly for extended TB or bone infection use
- Peripheral smear if unexplained cytopenia
- Bone marrow biopsy considered if severe or unclear cytopenia
⚠️ When to discontinue
Discontinue linezolid for: platelets under 50 without clear alternative cause, hemoglobin under 8 g/dL requiring transfusion, absolute neutrophil count under 1000, or pancytopenia. Consider alternative antibiotic. Most cytopenias resolve within 2 to 4 weeks of stopping. Persistent pancytopenia warrants hematology consultation.
🤯 Serotonin syndrome recognition and management
Building on section 16's prevention framework, serotonin syndrome management deserves focused review because it is the most common serious linezolid drug interaction complication when interaction screening is inadequate.
🔴 Severity spectrum
- Mild (many patients)
- Anxiety, tremor, diaphoresis, tachycardia. May resolve with drug discontinuation and supportive care alone.
- Moderate
- Adds hyperreflexia, ocular clonus, agitation, temperature 38 to 40 C. Benzodiazepines and cyproheptadine typically effective.
- Severe (life-threatening)
- Adds hyperthermia over 41 C, sustained clonus, rigidity, DIC, rhabdomyolysis, renal failure. Requires ICU care, paralysis, aggressive cooling.
🩹 Emergency management protocol
- Immediately stop linezolid and all serotonergic agents
- ABC assessment; secure airway if altered mental status
- IV fluid resuscitation with normal saline
- Continuous cardiac monitoring
- Benzodiazepines (lorazepam or midazolam) for agitation, tremor, and myoclonus
- Cyproheptadine 12 mg PO initial then 2 mg every 2 hours until symptoms resolve (5HT2 antagonist)
- Aggressive cooling for hyperthermia: cold IV fluids, ice packs, cooling blankets
- Severe cases: intubation and paralysis to control hyperthermia and rigidity
- Chlorpromazine 25 to 50 mg IV alternative to cyproheptadine for severe cases
- Renal protection and treatment of rhabdomyolysis
- Most patients recover 24 to 72 hours after drug removal
⛔ Avoid these interventions
- Do NOT use antipyretics (acetaminophen, NSAIDs) — hyperthermia is muscle-driven, not hypothalamic
- Do NOT use bromocriptine or dantrolene — these treat neuroleptic malignant syndrome, not serotonin syndrome
- Do NOT use physical restraint alone — increases muscle activity and hyperthermia
- Do NOT restart the offending serotonergic agent
📋 Post-event management
After recovery: document the event, add drug allergy to medical record, patient education about future avoidance, coordinate with mental health if SSRI restart is planned for original psychiatric indication (typically wait 2 weeks after linezolid discontinued), report to FDA MedWatch, consider alternative anti-MRSA agent (vancomycin, daptomycin) for future infections.
⚖️ Linezolid versus vancomycin for MRSA pneumonia
The comparison between linezolid and vancomycin for MRSA pneumonia is one of the most important clinical decisions in modern hospital medicine. The ZEPHyR trial (Wunderink et al 2012) provides the strongest direct evidence.
| Dimension | Linezolid | Vancomycin |
|---|---|---|
| MRSA clinical success (ZEPHyR) | 57.6 percent | 46.6 percent |
| Lung epithelial lining fluid concentration | 2 to 4x serum | Approximately equal to serum |
| Dosing complexity | Fixed 600 mg BID; no monitoring | Weight-based with trough monitoring |
| Renal effects | None | Nephrotoxicity risk 10 to 20 percent |
| Renal dose adjustment | Not needed | Required for renal impairment |
| IV-to-oral switch | Yes (100 percent bioavail) | No (IV only for systemic infection) |
| Thrombocytopenia risk | 2 to 5 percent short course | Rare |
| Serotonin syndrome risk | Yes with SSRIs, SNRIs, MAOIs | None |
| Toxin suppression | Yes (PVL, TSST) | None |
| Cost per course | Moderate to high | Low |
✅ Linezolid preferred when
- Baseline acute kidney injury or renal impairment
- Concurrent nephrotoxic agents
- Vancomycin MIC creep (over 1.5)
- Vancomycin allergy or intolerance
- Vancomycin trough not achievable
- Need for oral step-down (early discharge)
- Necrotising pneumonia (PVL toxin suppression benefit)
🔵 Vancomycin preferred when
- Concurrent SSRI or MAOI
- Baseline thrombocytopenia or myelosuppression
- Anticipated prolonged course over 14 to 21 days
- Cost is a primary consideration
- Concurrent VRE infection (linezolid needed for VRE, use vancomycin for coincident MSSA if applicable)
⚖️ Linezolid versus daptomycin for VRE bacteremia
For VRE bacteremia, the choice is typically between linezolid and daptomycin. Both are effective but differ in route, tissue distribution, and adverse effect profile.
| Dimension | Linezolid | Daptomycin |
|---|---|---|
| Route | IV or PO | IV only |
| Standard VRE dosing | 600 mg every 12 h | 10 to 12 mg/kg daily |
| Bactericidal/bacteriostatic | Bacteriostatic | Bactericidal |
| Lung penetration | Excellent | Poor (surfactant-inactivated) |
| Bone penetration | Moderate | Moderate |
| Renal function needs | No adjustment | Adjustment CrCl below 30 |
| Key toxicity | Thrombocytopenia, neuropathy (extended) | Myopathy, rhabdomyolysis (elevated CPK) |
| Monitoring required | CBC weekly; drug interactions | CPK weekly; statin interactions |
| Concurrent SSRI | Serotonin syndrome risk | No interaction |
| Emerging resistance | cfr, optrA rare | Reduced susceptibility with prolonged use |
| Cost (generic) | Moderate | Moderate to high |
🎯 Selection framework
- Choose linezolid for VRE
- Concurrent VRE pneumonia (lung penetration), need for oral step-down after IV clearance, elevated CPK or myopathy history, hemodialysis patient where daptomycin dosing is complex
- Choose daptomycin for VRE
- Concurrent SSRI or MAOI, baseline thrombocytopenia, anticipated prolonged course over 14 days, endocarditis (bactericidal advantage), persistent bacteremia despite linezolid
- Combination therapy
- Persistent VRE bacteremia may warrant combination of linezolid plus daptomycin, ampicillin (for E. faecalis), or ceftaroline in specialist consultation
⚖️ Linezolid versus tedizolid comparison
Tedizolid (Sivextro) is the second oxazolidinone, approved 2014. It offers several improvements over linezolid but with a much narrower indication set and higher cost.
| Dimension | Linezolid | Tedizolid |
|---|---|---|
| Dosing frequency | 600 mg BID | 200 mg once daily |
| FDA indications | SSTI, pneumonia, VRE bacteremia | Acute bacterial SSTI only |
| Course duration for SSTI | 10 to 14 days | 6 days |
| Thrombocytopenia risk (6-day course) | Low | Very low |
| Thrombocytopenia risk (14-day course) | Moderate | Low (studies mostly 6 days) |
| Serotonin syndrome risk | Substantial (MAO inhibitor) | Lower (weaker MAO inhibition) |
| Peripheral neuropathy risk | With extended use | Low with 6-day course |
| Bioavailability | 100 percent | 91 percent |
| Cost per course | Low (generic) | High (on patent) |
🎯 When each fits
Choose tedizolid for acute bacterial SSTI when a 6-day once-daily oral regimen with better safety profile is preferred and cost is not the primary factor (patient with concurrent SSRI, need for adherence support, wanting shortest course). Choose linezolid for all non-SSTI indications (pneumonia, VRE bacteremia, TB, bone infection) and for SSTI when cost is a primary factor. The oxazolidinone class overall gets one relatively narrow-spectrum option for SSTI and one broader-spectrum for other indications.
🧪 Cross-resistance
Linezolid resistance often confers cross-resistance to tedizolid (both bind similar ribosomal site). If linezolid resistance is documented, tedizolid may not be a rescue. Newer research suggests some cfr-mediated resistance may spare tedizolid but this is not reliable clinically.
⚖️ Linezolid versus vancomycin for MRSA SSTI
For MRSA SSTI (complicated skin and soft tissue infection), linezolid and vancomycin are both first-line options. The comparison is different from pneumonia because both have adequate skin/soft tissue penetration.
| Dimension | Linezolid | Vancomycin |
|---|---|---|
| Clinical success (Weigelt 2005) | Equivalent | Equivalent |
| Route options | IV or PO | IV only for systemic; oral vanco not absorbed |
| Hospital length of stay | Shorter (oral step-down enables early discharge) | Longer if requiring full IV course |
| Renal effects | None | Nephrotoxicity risk |
| Line requirement | Not required (oral) | Central line often needed for OPAT |
| Serotonin syndrome risk | Yes with SSRIs | None |
| Diabetic foot infection role | Good (with GN cover) | Good (with GN cover) |
| Cost per course | Moderate | Low |
🎯 Practical framework
For MRSA SSTI where oral outpatient management is feasible and safe, linezolid's ability to enable early hospital discharge (or complete outpatient management) is a major advantage. This translates to reduced hospital-acquired infection risk, lower healthcare costs, and improved patient satisfaction. For inpatients where IV therapy is planned regardless, vancomycin's lower cost drives many institutional protocols. When SSRI use or thrombocytopenia rule out linezolid, vancomycin remains the fallback.
🔄 When to choose an alternative
Linezolid's reserve status means that an alternative should be actively considered for every prescription. It should not be first-line for common gram-positive infections, and should not be used empirically without MRSA or VRE suspicion.
⛔ Do not use linezolid — alternatives mandatory
- Prior linezolid-induced anaphylaxis
- Prior linezolid-induced serotonin syndrome
- Prior linezolid-induced peripheral or optic neuropathy
- Prior linezolid-induced pancytopenia
- Prior linezolid-induced lactic acidosis
- Concurrent MAOI (phenelzine, tranylcypromine, isocarboxazid, selegiline, methylene blue)
- Uncontrolled hypertension
- Untreated hyperthyroidism
- Untreated pheochromocytoma
- Carcinoid syndrome
🟡 Reconsider linezolid — alternative often better
- Uncomplicated infections where beta-lactams or narrower agents work — use those
- Empirical use without MRSA or VRE suspicion — use appropriate empiric coverage
- Concurrent SSRI, SNRI, TCA, or other serotonergic agents — use vancomycin or daptomycin
- Baseline thrombocytopenia or myelosuppression — prefer vancomycin
- Anticipated course over 28 days — consider daptomycin (bacteremia) or vancomycin
- Diabetic patient on multiple hypoglycemic agents — prefer vancomycin
- MSSA infection where a beta-lactam is appropriate — use cefazolin or nafcillin
- Streptococcal infection where penicillin works — use penicillin
✅ Where linezolid genuinely fits
MRSA complicated SSTI with need for oral step-down or outpatient management, MRSA HAP/VAP (particularly ZEPHyR-supported scenarios), VRE bacteremia and other VRE infections, MDR-TB regimen (WHO Group A), MRSA bone infection oral step-down, necrotising MRSA pneumonia (PVL toxin suppression), Nocardia component therapy, gram-positive meningitis when vancomycin unusable, and specific IDSA-supported indications where alternatives are inadequate.
📦 Storage and stability
Linezolid tablets and oral suspension have straightforward storage requirements.
| Formulation | Storage | Shelf after opening |
|---|---|---|
| 600 mg film-coated tablets | Room temperature 15 to 25 C, dry | Until printed expiry |
| Powder for oral suspension (unopened) | Room temperature | Until printed expiry |
| Reconstituted oral suspension | Room temperature (do not refrigerate) | 21 days |
| IV infusion bag | Room temperature, protect from light | Per package insert |
📦 Storage rules
- Store tablets in original blister or bottle to protect from moisture and light
- Do not refrigerate tablets or reconstituted suspension
- Reconstituted suspension: gentle inversion to mix (do not shake vigorously); discard after 21 days
- Keep out of reach of children
- Discard past printed expiry date
⏰ Missed dose management
Linezolid is BID with 4-6 hour half-life, so missed dose management is straightforward.
⏰ Missed dose rule
- If less than 6 hours late
- Take the missed dose as soon as remembered. Continue next scheduled dose at usual time.
- If more than 6 hours late (approaching next dose)
- Skip the missed dose. Take next scheduled dose. Do not double-dose.
⚠️ Do not double-dose
Taking two doses close together does not improve cure and may amplify serotonergic and adrenergic MAO inhibitor effects (dose-dependent). Continue single dosing.
💡 Adherence supports
- Take BID doses roughly 12 hours apart (morning and evening)
- Anchor to routine meals (breakfast, dinner) or morning/bedtime
- Set phone alarms for BID reminders
- Use pill organiser for extended courses
- Extended courses (TB, bone infection): consider directly observed therapy where feasible
- Report missed doses to prescriber for critical indications (endocarditis, bone infection)
👵 Geriatric considerations
Elderly patients face a distinctive linezolid risk profile: higher rates of thrombocytopenia, hypoglycemia, and drug interactions, but no dose adjustment for age-related renal decline.
✅ Advantages in older adults
- No renal dose adjustment — simpler prescribing than vancomycin
- No vancomycin trough monitoring burden
- Oral formulation supports early discharge
- No nephrotoxicity to compound age-related renal decline
👵 Amplified risks in the elderly
- Thrombocytopenia more likely with baseline renal impairment and prolonged courses
- Hypoglycemia in diabetic elderly on hypoglycemic agents (particularly sulfonylureas)
- Drug interactions more common with polypharmacy (SSRIs are widely used in elderly for depression)
- Falls risk if hypoglycemia or dizziness develops
- Peripheral neuropathy already prevalent in diabetic elderly; linezolid can add or worsen
| Geriatric prescribing check | Action |
|---|---|
| Comprehensive medication review | Screen for SSRIs, SNRIs, TCAs, tramadol, meperidine, sympathomimetics |
| Baseline CBC and platelet | Weekly during therapy |
| Blood glucose monitoring in diabetics | Consider hypoglycemic agent dose reduction |
| Baseline neurologic exam | Assess baseline peripheral neuropathy |
| Fall risk assessment | Precautions if dizziness or hypoglycemia develops |
| Counsel on warning signs | Sedation, bruising, vision changes, muscle pain, hypoglycemia |
💰 Cost, generic availability, and future outlook
Generic linezolid has been available since 2015 in major markets. Prices have fallen substantially, though linezolid remains more expensive than most beta-lactams and older antibiotics.
| Antibiotic (10-day course) | Course cost USD |
|---|---|
| Linezolid (Linox, generic) | 40 to 150 |
| Zyvox brand | 300 to 800 |
| Vancomycin IV (per day) | 5 to 15 |
| Daptomycin IV (per day) | 100 to 200 |
| Tedizolid (Sivextro 6-day) | 1500 to 3000 |
| Ceftaroline IV (per day) | 200 to 400 |
💰 Cost context
Linezolid remains modestly more expensive than vancomycin IV per unit cost, but the total course cost may favor linezolid when factoring in hospital length of stay, IV line costs, nephrotoxicity workup, and vancomycin trough monitoring. Direct drug cost is not the full picture. Cipla's Linox brand is among the more affordable generic forms available internationally.
🔭 Future outlook
- Continued reserve status
- Stewardship pressure keeps linezolid narrow to resistant gram-positive indications. This preserves activity against MRSA and VRE where alternatives are limited.
- Rising resistance surveillance
- cfr and optrA plasmid-mediated linezolid resistance in enterococci and staphylococci is monitored. Institutional outbreaks require targeted response.
- TB niche expansion
- The BPaL regimen (bedaquiline + pretomanid + linezolid) has revolutionised MDR-TB treatment with 6-month all-oral courses. This role will continue.
- New oxazolidinones
- Delpazolid, sutezolid, and radezolid are in development, particularly for TB. Some may offer improved safety profiles.
- Toxicity mitigation strategies
- Dose reduction (600 to 300 mg daily) after initial period is increasingly used for extended courses to reduce cumulative mitochondrial toxicity while preserving efficacy.
⛔ Absolute contraindications and precautions
Final consolidation of all situations where linezolid must not be used, or must be used only with specific safeguards.
⛔ Absolute contraindications — do not prescribe
- Prior anaphylaxis to linezolid
- Lifetime avoidance.
- Prior linezolid-induced serotonin syndrome
- Lifetime avoidance of linezolid, tedizolid, and all serotonergic combinations.
- Prior linezolid-induced peripheral or optic neuropathy
- Lifetime avoidance — risk of irreversible recurrence.
- Prior linezolid-induced pancytopenia
- Lifetime avoidance.
- Prior linezolid-induced lactic acidosis
- Lifetime avoidance.
- Concurrent MAO inhibitor
- Phenelzine, tranylcypromine, isocarboxazid, selegiline, methylene blue. Wash out 2 weeks before starting linezolid.
- Uncontrolled hypertension
- MAO inhibitor effect can precipitate hypertensive crisis.
- Untreated hyperthyroidism
- Adrenergic sensitivity amplified.
- Pheochromocytoma or carcinoid syndrome
- Catecholamine or serotonin excess amplified by MAO inhibition.
🟡 Relative contraindications and cautions
- Concurrent SSRI, SNRI, TCA
- Serotonin syndrome risk. If linezolid essential, wash out 2 to 5 weeks; 5 weeks for fluoxetine.
- Concurrent tramadol, meperidine, methadone, fentanyl
- Serotonergic; avoid or substitute non-serotonergic analgesic.
- Concurrent dextromethorphan
- Serotonergic; avoid or substitute.
- Concurrent sympathomimetics
- Pseudoephedrine, phenylephrine, amphetamines. Substitute alternative.
- Concurrent tyramine-rich foods
- Modest restriction (unlike irreversible MAOIs); avoid extremes.
- Baseline thrombocytopenia (platelets under 100)
- Amplified risk of severe thrombocytopenia; prefer vancomycin if possible.
- Baseline peripheral neuropathy
- Amplified risk; monitor closely if used.
- Diabetic patient on hypoglycemic agents
- Hypoglycemia risk; monitor blood glucose closely; consider hypoglycemic dose reduction.
- Pregnancy Category C
- Avoid except for serious infections without alternatives.
- Anticipated course over 28 days
- Consider dose reduction (300 mg after first month) or alternative agent if feasible.
- Severe renal impairment with prolonged course
- Metabolite accumulation amplifies toxicity risk; monitor closely.
| Warning sign during therapy | Action |
|---|---|
| Anaphylaxis symptoms | Stop drug; epinephrine; emergency care |
| Easy bruising, petechiae, bleeding | Check platelets; stop if under 50 or active bleeding |
| Vision changes, color loss | Stop drug; urgent ophthalmology |
| Numbness, tingling, burning extremities | Stop drug; neurology assessment |
| Agitation, tremor, sweating, hyperthermia | Stop drug; consider serotonin syndrome; benzodiazepine, cyproheptadine |
| Unexplained fatigue, muscle pain, tachypnea | Check lactate; consider lactic acidosis |
| Hypoglycemia symptoms | Check glucose; adjust hypoglycemic agents |
| Severe or bloody diarrhea, fever | Stop drug; CDI stool test; avoid loperamide |
| Severe headache, hypertension, chest pain | Emergency evaluation; consider hypertensive reaction |
| Jaundice, dark urine | Stop drug; LFTs; hepatology if severe |
| Extensive rash, blistering, mouth sores | Stop drug; SJS/TEN evaluation |
📋 Populations requiring extra vigilance
- Patients on concurrent SSRIs, SNRIs, TCAs, tramadol, or other serotonergic agents
- Patients on MAOIs (absolute contraindication)
- Diabetic patients on hypoglycemic agents (insulin, sulfonylureas)
- Patients with baseline thrombocytopenia or myelosuppression
- Patients with baseline peripheral neuropathy
- Patients requiring extended courses over 28 days (TB, bone infection, VRE endocarditis)
- Patients with severe renal impairment on prolonged courses
- Elderly patients with polypharmacy
- Pregnant and lactating women
- Patients with uncontrolled hypertension or hyperthyroidism
Used within these boundaries, linezolid remains one of the most valuable antibiotics in the modern armamentarium: the reliable oral option for MRSA and VRE infections that previously required prolonged IV vancomycin, a foundational component of MDR-TB regimens, and a well-tolerated agent for short-course infections. Its reserve status is essential to preserve activity against the resistant gram-positive pathogens for which no reliable alternative exists.
Linox — Frequently Asked Questions
-
What is Linox (Linezolid) used for?
Linox is prescribed to treat serious bacterial infections caused by Gram-positive organisms, including MRSA and VRE. It is especially valuable when other antibiotics fail, making it a cornerstone for resistant infections. -
How does Linox work in the body?
Linezolid works by preventing bacteria from producing proteins necessary for survival. It binds to ribosomal RNA, blocking protein synthesis at the earliest stage, stopping bacterial growth and preventing further spread. -
Which infections can Linox effectively treat?
It treats pneumonia (both community- and hospital-acquired), complicated and uncomplicated skin infections, bloodstream infections caused by resistant organisms, and vancomycin-resistant enterococcal infections, making it versatile against severe Gram-positive infections. -
Can Linox be used for MRSA infections?
Yes, Linezolid is highly effective against MRSA. Clinical studies show it works well for MRSA pneumonia, bloodstream infections, and skin infections, often when vancomycin is not effective or tolerated. -
Is Linox effective against VRE?
Yes, one of its most important uses is in treating vancomycin-resistant Enterococcus infections. It is often considered a first-line therapy when VRE causes bacteremia or other serious systemic infections. -
Can Linox treat pneumonia?
Linox is approved for both community-acquired and hospital-acquired pneumonia. It is especially useful for cases caused by resistant bacteria, including MRSA, and has strong penetration into lung tissues. -
How is Linox usually taken?
Linox can be given orally or intravenously. Adults typically take 600 mg every 12 hours. Because oral absorption is excellent, oral tablets work just as effectively as IV therapy.
📚 Drug Description Sources:
Evidence supporting Linox (linezolid) draws on FDA regulatory documentation from the 2000 approval, IDSA MRSA guidelines, ATS-IDSA HAP/VAP guidelines, ZEPHyR trial data comparing linezolid with vancomycin for MRSA pneumonia, and multiple safety epidemiology studies characterising thrombocytopenia, neuropathy, and serotonin syndrome risk. Every citation below documents an aspect referenced in this medication guide.
🏛️ Regulatory documentation
- FDA NDA 021130 Zyvox (linezolid) tablets and IV solution, Pharmacia and Upjohn (later Pfizer), April 2000.
- WHO Essential Medicines List Reserve group inclusion for multi-drug resistant tuberculosis.
- Multiple international generic manufacturers approved since patent expiration. Cipla manufactures linezolid under the Linox brand.
- US Package Insert with warnings for myelosuppression, peripheral and optic neuropathy, lactic acidosis, serotonin syndrome, and hypoglycemia.
- FDA Safety Communication updates addressing MAO inhibitor status and serotonin syndrome interaction with SSRIs and SNRIs.
📚 Clinical guidelines
- IDSA MRSA Treatment Guidelines (Liu C et al, Clin Infect Dis 2011) — linezolid alongside vancomycin as first-line for MRSA pneumonia and complicated SSTI.
- ATS-IDSA HAP/VAP Guidelines (Kalil AC et al, Clin Infect Dis 2016) — linezolid or vancomycin for empirical MRSA coverage.
- IDSA VRE Guidelines — linezolid and daptomycin as core options for VRE bacteremia.
- WHO Consolidated TB Guidelines — linezolid as core Group A drug for rifampin-resistant and MDR-TB regimens.
- IDSA Diabetic Foot Infection Guidelines — linezolid for suspected MRSA involvement.
- ATS-IDSA Community-Acquired Pneumonia Guidelines 2019 — linezolid as alternative for CAP with resistant pathogen suspicion.
🧪 Pivotal comparative trials
- Wunderink RG et al 2012 (Clin Infect Dis) — ZEPHyR trial comparing linezolid with vancomycin for nosocomial MRSA pneumonia, showing improved clinical success with linezolid.
- Weigelt J et al 2005 — linezolid versus vancomycin for complicated SSTI showing equivalent efficacy with better oral step-down.
- Stevens DL et al 2002 — foundational SSTI comparison establishing linezolid's role.
- Rubinstein E et al 2001 — original CAP registration trial for linezolid.
- Conte JE et al pharmacokinetic studies establishing lung epithelial lining fluid penetration.
🩺 Safety epidemiology and pharmacology
- Rao N et al. Linezolid-associated thrombocytopenia epidemiology and time-to-onset characterisation.
- Bressler AM et al. Linezolid peripheral neuropathy case series and risk factor analysis.
- Rho JP et al. Linezolid optic neuropathy characterisation and reversibility studies.
- Lawrence KR et al. Linezolid MAO inhibitor activity and serotonin syndrome risk quantification.
- Del Pozo JL et al. Linezolid lactic acidosis mitochondrial toxicity mechanism.
- Cipla product monograph and post-marketing safety experience with Linox brand.
🩺 Medical Expert Review:
Below are five clinicians whose peer-reviewed work directly informs the modern use of linezolid: MRSA infection guidelines, S. aureus bacteremia, vancomycin-resistant enterococci, oxazolidinone research, and ventilator-associated pneumonia management.
Henry F. Chambers, MD
University of California San Francisco School of Medicine, San Francisco General Hospital — San Francisco, California, USA
Dr Chambers is one of the world's leading authorities on Staphylococcus aureus infection and antimicrobial resistance. He was lead author of the IDSA 2011 MRSA Treatment Guidelines and has spent his career defining the appropriate roles for vancomycin, linezolid, daptomycin, and newer anti-MRSA agents across the spectrum of MRSA infection syndromes.
Vance G. Fowler Jr, MD, MHS, FIDSA
Duke University School of Medicine, Duke Clinical Research Institute — Durham, North Carolina, USA
Prof Fowler directs the leading US research program on Staphylococcus aureus bacteremia and endocarditis outcomes. His work informs modern approaches to persistent MRSA bacteremia where linezolid combination therapy, high-dose daptomycin, or salvage regimens are considered. He co-founded the Antibacterial Resistance Leadership Group (ARLG).
Cesar A. Arias, MD, PhD, MSc, FIDSA
Houston Methodist Research Institute, Weill Cornell Medical College — Houston, Texas, USA
Dr Arias is a leading authority on vancomycin-resistant enterococci and gram-positive resistance mechanisms. His work characterises linezolid resistance evolution (23S rRNA mutations, cfr and optrA plasmid-mediated), informing the modern framework for VRE bacteremia treatment where linezolid, daptomycin, and combination approaches are weighed against emerging resistance.
George Sakoulas, MD
Sharp Rees-Stealy Medical Group, University of California San Diego School of Medicine — San Diego, California, USA
Dr Sakoulas has published foundational work on oxazolidinone pharmacology, MRSA vancomycin heteroresistance, and combination antimicrobial therapy. His research informs strategies for linezolid use in complicated bacteremia, prolonged suppression therapy, and combination approaches for daptomycin-resistant or vancomycin-intermediate S. aureus.
Marin H. Kollef, MD, MCCM
Washington University School of Medicine, Barnes-Jewish Hospital — Saint Louis, Missouri, USA
Prof Kollef is one of the leading researchers on ventilator-associated pneumonia and hospital-acquired pneumonia outcomes. His work informs the modern ATS-IDSA HAP/VAP framework where linezolid and vancomycin serve as empirical MRSA coverage, with linezolid preferred in patients with acute kidney injury, vancomycin allergy, or where lung penetration matters most.
More Antibiotics Medications


