Buy Tadaflo (Tadalafil 10/20mg) Online - Cipla Multi Strength Generic Cialis 36 Hour PDE5 for ED and BPH


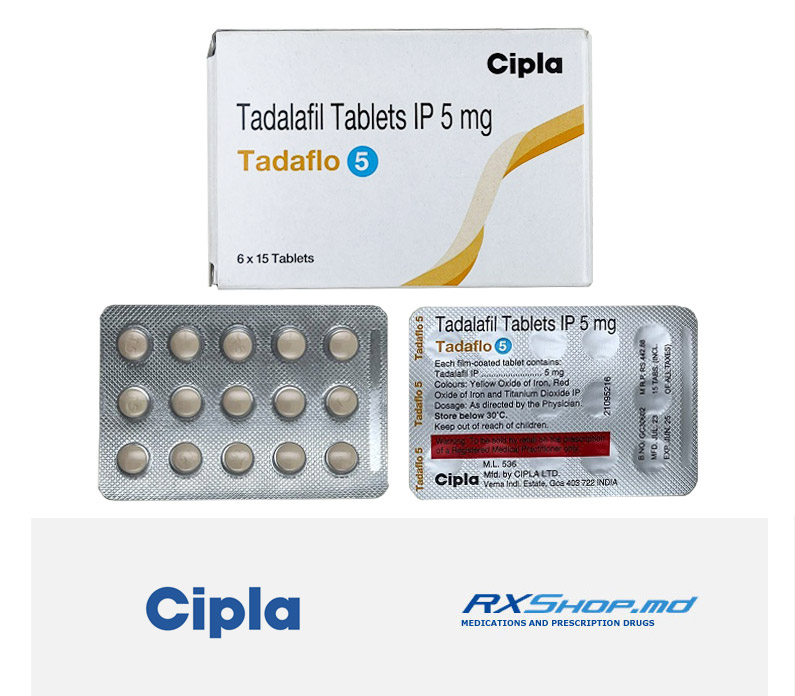
Tadaflo (Tadalafil 10/20mg) represents Cipla Limited's multi-strength tadalafil offering — providing dose flexibility that the standard-strength-only Tadacip line does not offer. Manufactured by Cipla — India's largest and most respected pharmaceutical company with US FDA-approved manufacturing facilities — Tadaflo delivers the signature 36-hour tadalafil window in two strengths: 10 mg for milder ED cases or dose-titration approaches, and 20 mg for standard adult dosing. This flexibility makes Tadaflo particularly attractive to men who want precise dose personalization backed by the same Cipla quality reputation that produces Tadacip and other Cipla generics for global markets including the US, EU, and Australia.
Tadalafil works through selective phosphodiesterase type 5 (PDE5) inhibition — the same mechanism as sildenafil but with dramatically different pharmacokinetics. Tadalafil demonstrates 17.5-hour elimination half-life — 4 times longer than sildenafil's 4 hours. This translates to up to 36 hours of responsiveness after a single dose, providing an unprecedented sexual encounter window that allows spontaneity throughout an entire weekend. Additionally, tadalafil's high PDE5 selectivity versus PDE6 avoids the bluish-vision side effect common with sildenafil. Clinical response: successful intercourse in 75-85% of attempts, onset within 30 minutes, and reliable response with food-independent absorption.
Tadaflo serves three FDA-approved tadalafil indications. The primary is erectile dysfunction of all major etiologies — psychogenic, vasculogenic, diabetic, post-prostatectomy, age-related, and mixed etiology. Additionally approved for benign prostatic hyperplasia (BPH) — daily 5 mg dosing (through 10 mg tablet splitting) improves urinary symptoms through PDE5-mediated smooth muscle relaxation. Third indication is pulmonary arterial hypertension (PAH) at lower TID doses reducing pulmonary vascular resistance. The 10 mg starter strength particularly benefits men wanting titration from lower doses, elderly patients with reduced clearance, or those with drug interaction concerns. 20 mg standard serves majority of adult men with typical ED severity.
Tadaflo requires on-demand dosing 30 minutes before anticipated sexual activity, no more than once per 24 hours. Food-independent absorption. Peak concentrations at 2 hours, 17.5-hour half-life. Cipla India manufactures under WHO-GMP, US FDA, and Indian DCGI quality standards.
Free prescription
Discrete packaging
Have questions?
Quality Assurance
- ED: Medical abbreviation for erectile dysfunction affecting millions of men worldwide;
- Long Duration ED Therapy: Up to 36-hour responsiveness window unique among PDE5 inhibitors for spontaneity;
- Weekend Pill Therapy: Popular nickname reflecting 36-hour window supporting entire weekend sexual encounters;
- Multi Strength Tadalafil Therapy: 10 mg starter and 20 mg standard enable precise dose personalization;
- Mild ED 10mg Starter: 10 mg strength for milder ED cases or dose titration approaches;
- Standard ED 20mg: 20 mg standard adult dose for typical ED severity;
- Impotence: Traditional term for erectile dysfunction affecting sexual function and confidence;
- Male Sexual Dysfunction: Male sexual response impairment responding to PDE5 inhibitor therapy;
- Psychogenic Erectile Dysfunction: Anxiety-driven ED with reliable long-duration response reducing performance pressure;
- Vasculogenic Erectile Dysfunction: ED from arterial insufficiency responding to PDE5-mediated vasodilation;
- Diabetic ED: Diabetes-related erectile dysfunction responding particularly well to long-acting tadalafil;
- Age Related Erectile Decline: Progressive age-related erectile function decline responding to PDE5 inhibition;
- Post Prostate Surgery ED: Erectile dysfunction after radical prostatectomy responding to PDE5 rehabilitation;
- Benign Prostatic Hyperplasia: FDA-approved for BPH symptoms at daily 5 mg dose improving urinary function;
- Combined ED and BPH: Men with both conditions benefit from single daily tadalafil addressing both;
- Pulmonary Arterial Hypertension: Also FDA-approved as Adcirca for PAH exercise capacity improvement;
- Cipla Quality Generic Therapy: Established Indian generic from major manufacturer with US FDA-approved facilities;
- PDE5 Inhibitor Therapy: Drug class targeting phosphodiesterase type 5 for erectile function restoration;
- Generic Cialis Therapy: Bioequivalent generic alternative to brand-name Cialis at substantially lower cost.
- Better 36-Hour Response Window: Longest responsiveness period among PDE5 inhibitors enabling weekend-long sexual freedom;
- Better Multi Strength Options: 10 mg starter and 20 mg standard enable precise dose personalization;
- Better 17.5-Hour Half Life: 4 times longer than sildenafil providing sustained pharmacological effect;
- 30 Minute Onset: Effect begins within 30 minutes of dosing enabling relatively planned sexual activity;
- Better Penile Blood Flow: cGMP-mediated smooth muscle relaxation improves corpus cavernosum blood inflow;
- Better Food Independence: Unlike sildenafil tadalafil absorption is not affected by meals including fatty foods;
- Better Sexual Spontaneity: 36-hour window eliminates strict pre-planning enabling truly spontaneous encounters;
- Better Dose Titration: Start with 10 mg and titrate up to 20 mg based on response and tolerability;
- Better BPH Urinary Symptoms: Daily tadalafil improves urinary flow hesitancy and frequency in BPH patients;
- Better ED BPH Combined Therapy: Single daily dose addresses both conditions eliminating dual-medication complexity;
- Less Visual Side Effects: High PDE5 selectivity versus PDE6 avoids bluish vision seen with sildenafil;
- Better Diabetes ED Response: Diabetic ED patients respond particularly well to long-acting tadalafil;
- Better Post Prostatectomy Response: Nerve-sparing prostatectomy patients benefit from tadalafil penile rehabilitation;
- Better Age Related Response: Progressive age-related erectile decline responds well to long-acting PDE5 inhibition;
- Better Sexual Confidence: 36-hour reliable response restores sexual confidence and eliminates timing anxiety;
- Better Relationship Satisfaction: Restored sexual function improves relationship satisfaction and intimacy quality;
- Better Cipla Manufacturing Quality: Established Indian pharma with US FDA-approved facilities ensures consistent product quality;
- Better Generic Cost: 85-95% lower cost than brand Cialis makes proven long-acting ED therapy accessible;
- Better Quality of Life: Daily wellbeing improves dramatically as ED-related distress resolves and sexual confidence returns.
Generic Tadaflo (Tadalafil 10 mg) Medication guide:
💊 Tadaflo Introduction and Generic Equivalence
Tadaflo delivers generic tadalafil 20 mg — the same molecular entity that launched as brand Cialis in 2003 and became available as generic across major markets from 2017-2018. The clinical identity is unchanged: tadalafil remains the only PDE5 inhibitor with a 36-hour window of effect, food-independent absorption, and dual approval for both erectile dysfunction and benign prostatic hyperplasia symptoms.
💊 Core Facts
Generic tadalafil with 36-hour effect window — spontaneity across the weekend from a single tablet.
Composition
Tadalafil 20 mg generic
Onset
30-60 min; peak at 2 hours
Half-life
17.5 hours terminal
Food Effect
Minimal; meal-independent
The practical philosophy of generic tadalafil is equivalent clinical outcome at substantially reduced cost. Bioequivalence standards require that generic products match the brand version within tight pharmacokinetic parameters — concentration curves must overlap within approximately 80-125% of brand characteristics. For tadalafil generics including Tadaflo, this translates to clinical response that mirrors brand Cialis closely enough that treatment outcomes do not meaningfully differ.
📋 Guide Contents
LONG-ACTING PHARMACOLOGY
Why tadalafil's 17.5-hour half-life produces up to 36 hours of clinical effect, and what this means practically for intimacy timing.
GENERIC EQUIVALENCE
What bioequivalence means for Tadaflo versus brand Cialis, and the practical implications for treatment effectiveness.
DUAL INDICATION
Tadalafil's unique role in treating both ED and benign prostatic hyperplasia symptoms with a single daily low-dose medication.
SAFETY ARCHITECTURE
The absolute nitrate contraindication, cardiovascular assessment framework, and PDE11-related back pain profile specific to tadalafil.
💊 Tadalafil Clinical Identity Preserved
Whether delivered as brand Cialis or as Tadaflo generic, the active molecule and its clinical effect are the same. Twenty years of post-marketing experience with tadalafil applies to Tadaflo. The 36-hour window, food-independent absorption, back pain profile, and nitrate contraindication all transfer directly from brand experience to generic use.
🧬 Tadalafil Pharmacology and PDE5 Mechanism
Tadalafil binds phosphodiesterase type 5 (PDE5) with high affinity and selectivity, inhibiting the enzyme that would otherwise terminate the erection signal. The molecule's structural features produce distinctive pharmacokinetic properties: long half-life, food-independent absorption, and reduced cross-reactivity with retinal PDE6 (less visual side effects than sildenafil).
🧬 From Arousal to Erection
Nitric oxide release in response to arousal
Visual, mental, and tactile stimulation triggers nitric oxide release from parasympathetic nerve endings in penile tissue. NO has brief half-life but potent biological effect.
cGMP second messenger signaling
NO activates soluble guanylate cyclase, which synthesizes cyclic GMP. Rising cGMP triggers calcium channels and myosin light chain kinase changes that relax corporal smooth muscle.
Blood inflow and veno-occlusion
Relaxed smooth muscle allows arterial inflow. Expanding sinusoids compress subtunical venules, trapping blood. This produces rigidity.
Tadalafil extends the signal
PDE5 normally degrades cGMP. Tadalafil competitively inhibits PDE5, allowing cGMP to accumulate and persist. The result is enhanced response to arousal signals that continues as long as tadalafil remains active — up to 36 hours.
🧪 Molecular Characteristics
Beta-carboline chemistry
Tadalafil has methylenedioxyphenyl group and beta-carboline framework. This structure produces slower hepatic clearance than sildenafil's imidazotriazine, giving the long half-life.
PDE5 selectivity profile
Tadalafil has high PDE5 affinity (IC50 approximately 2 nM), with modest cross-reactivity against PDE11. PDE11 is present in testis, prostate, pituitary, and skeletal muscle — the muscle presence contributes to tadalafil's distinctive back pain and myalgia profile.
Low PDE6 cross-reactivity
PDE6 is retinal enzyme that sildenafil weakly inhibits (producing blue vision tint). Tadalafil has much lower PDE6 affinity — vision side effects are therefore uncommon with tadalafil, a potential advantage over sildenafil for men sensitive to visual changes.
🚫 What Tadalafil Does Not Do
- Does not create erection in absence of arousal
- Does not increase sexual desire or libido
- Does not treat premature ejaculation or ejaculation timing
- Does not affect fertility, sperm, or conception
- Does not protect against sexually transmitted infections
- Does not enhance pleasure or orgasm quality beyond baseline
💊 Pharmacology Explains Clinical Behavior
Each distinctive feature of tadalafil — the long window, food independence, back pain tendency, limited visual effect — traces back to specific molecular characteristics. Understanding this helps explain why tadalafil may suit some men better than other PDE5 inhibitors, and why certain side effects appear more frequently.
🔢 ED Epidemiology and Pathophysiology
Erectile dysfunction affects a progressively larger share of men with age. The MMAS and subsequent population surveys consistently document ED prevalence rising from approximately 40% at age 40 to 70% at age 70. For many of these men, PDE5 inhibitor therapy with tadalafil provides adequate improvement to restore satisfactory sexual function.
🔢 Prevalence by Age
- Age 40-49: approximately 40% with some ED
- Age 50-59: approximately 50%
- Age 60-69: approximately 60%
- Age 70+: approximately 70%
- Severe ED: approximately 5% at 40, rising to 15% at 70
A meaningful share of men never seek treatment despite effective options being available.
🎯 Underlying Pathophysiology
Vasculogenic ED
Arterial insufficiency reduces blood inflow. Veno-occlusive dysfunction allows outflow leak. Atherosclerosis, hypertension, diabetes, smoking all contribute. Most common form after age 50.
Neurogenic ED
Pelvic surgery (radical prostatectomy), spinal cord injury, diabetic autonomic neuropathy, multiple sclerosis. Response to tadalafil depends on nerve integrity preserved.
Endocrine ED
Hypogonadism (low testosterone), hyperprolactinemia, hypothyroidism, hyperthyroidism. Address underlying endocrine problem alongside tadalafil.
Psychogenic ED
Performance anxiety, depression, relationship stress. Tadalafil's long window often helps because reduces timing pressure that fuels anxiety cycles.
Mixed etiology
Most men — multiple contributing factors. Combined pharmacologic and psychological approach often most effective.
❤️ ED-Cardiovascular Connection
The penile artery lumen (1-2 mm) is smaller than coronary artery lumen (3-4 mm). Atherosclerosis affects smaller vessels first, which means ED frequently precedes clinically evident cardiovascular disease by 3-5 years. New-onset ED is an opportunity for systematic cardiovascular assessment:
- Blood pressure measurement
- Fasting lipid panel
- Fasting glucose or HbA1c
- Family history of CV disease
- Smoking status and quantification
- Exercise tolerance assessment
💊 Treatment and Prevention Opportunity
For men presenting with ED, Tadaflo addresses the immediate symptom while cardiovascular assessment and lifestyle modification address the underlying disease process. The combined approach treats symptom and prevents progression of the vascular pathology that often links ED to future cardiac events.
🎯 Clinical Scenarios Favoring Tadalafil
Tadaflo is appropriate first-line therapy for erectile dysfunction in most men without specific contraindications. Among the PDE5 inhibitors, tadalafil has particular advantages for specific lifestyle patterns and clinical situations that make it the preferred choice for many men.
🎯 Clinical Scenarios Where Tadaflo Excels
Spontaneity-oriented intimacy pattern
For men whose intimate life does not fit a scheduled single-event pattern, the 36-hour window allows multiple natural moments without recalculating timing against a dose.
Social meals with intimacy to follow
Food-independent absorption means a hearty restaurant meal does not blunt the medication effect. For men whose intimate occasions tend to involve dinner together, tadalafil removes a complication that affects sildenafil.
Coexisting prostate symptoms
For men over 50 with urinary complaints suggesting BPH, daily low-dose tadalafil provides coverage of both ED and prostatic symptoms with one medication — a clinically elegant solution unique to this agent.
Vision sensitivity concerns
Men whose sildenafil experience included bothersome blue-tint vision changes may find tadalafil's reduced PDE6 cross-reactivity more comfortable.
Previous success with brand Cialis
Men who did well on brand Cialis will see essentially the same clinical response from Tadaflo at generic cost. Bioequivalence standards ensure similar efficacy.
🤔 When Other Options Fit Better
Priority on absolute fastest onset
Avanafil (15-30 min) or sildenafil (30-60 min on empty stomach) have slight onset-time advantage for men needing quickest action.
History of back pain with tadalafil
Men whose previous tadalafil experience was marred by significant musculoskeletal pain can switch to sildenafil, which has minimal PDE11 affinity.
Mixed ED + PE requiring both treatments
Men with coexisting premature ejaculation may need combination therapy with dapoxetine rather than tadalafil monotherapy.
Nitrate therapy for cardiovascular disease
Absolute contraindication. Alternative ED approaches needed — vacuum devices, alprostadil injection, or penile implant.
🛑 Absolute Exclusions
- Men on nitrate medications of any form
- Men on riociguat for pulmonary hypertension
- Severe cardiovascular disease (unstable angina, recent MI, class III-IV heart failure)
- History of NAION attributed to prior PDE5 use
- Retinitis pigmentosa
- Severe hepatic impairment
- Known hypersensitivity to tadalafil
- Women (not indicated for any female condition)
- Men under 18
💊 Default First-Line Choice for Many Men
For men whose intimate schedule involves spontaneous occasions, social meals before intimacy, weekend getaways, or coexisting BPH symptoms, Tadaflo is often the first PDE5 inhibitor to try. Men with purely scheduled single-event patterns and cost sensitivity may prefer generic sildenafil as the slightly cheaper alternative.
🕐 Taking Tadaflo and Dose Selection
Using Tadaflo effectively requires attention to timing, dose selection, and understanding of two distinct usage patterns. The 20 mg strength is designed for on-demand use before intimacy; daily low-dose tadalafil (a different product) suits men with frequent intimacy or coexisting BPH.
🕐 On-Demand Protocol with Tadaflo 20 mg
Swallow one tablet whole
With a full glass of water. The film-coated tablet should not be crushed, split, or chewed. Water aids absorption and reduces first-use dizziness.
Allow 1-2 hours for onset
Tadalafil begins having effect within 30-60 minutes but reaches peak concentration at approximately 2 hours. For reliable response, plan intimacy at least an hour after dosing.
Meal timing unrestricted
Can take with or without food. Fatty meals do not interfere significantly. Grapefruit juice should be avoided (CYP3A4 inhibition raises blood levels).
Sexual arousal needed for response
Tadalafil amplifies the body's natural erection response but does not create erection without stimulation. Visual, mental, tactile input all contribute to effective response.
Observe 72-hour minimum between doses
Tadalafil's 17.5-hour half-life means significant levels persist for days. Taking another dose within 72 hours risks accumulation and increased side effects. For more frequent use, daily low-dose tadalafil is the appropriate alternative.
Limit concurrent alcohol
One or two drinks are tolerable. Heavy alcohol impairs erectile function directly and raises orthostatic risk from combined vasodilation.
📅 Alternative: Daily Low-Dose Tadalafil
A separate daily tadalafil formulation (2.5-5 mg) exists for men whose situation fits a continuous-coverage pattern:
- Reaches steady-state over 5-7 days of daily dosing
- Provides spontaneity throughout the week without planning
- Approved separately for BPH symptom treatment
- Appropriate for men with 3+ intimate occasions per week
- Different product than Tadaflo 20 mg; daily use at that strength is not safe
🛠️ Dose Selection
| Clinical Scenario | Approach |
|---|---|
| Standard adult, no complications | Tadaflo 20 mg on demand |
| Age over 65, no complications | Start at 10 mg; adjust to 20 mg if needed |
| Moderate hepatic or renal impairment | 10 mg maximum |
| On moderate CYP3A4 inhibitor | 10 mg; monitor for side effects |
| Side effects at 20 mg but good response | Step down to 10 mg |
💊 Allow Sufficient Trials
Response to tadalafil often improves across the first 4-6 attempts as the man and partner adapt to the medication's timing. Because of the 72-hour interval, these attempts take three to six weeks to accumulate. Judging the medication based on one or two attempts is premature.
🍽️ Food-Independent Absorption Advantage
Tadalafil's absorption is largely independent of meal composition — one of its clinically meaningful advantages. Clinical studies show no significant difference in peak concentration or time-to-peak between fasted and fed states, including high-fat meals. The practical implication is simpler planning around social meals.
🍽️ Meal Pharmacokinetics
EMPTY STOMACH
Standard absorption. Peak at ~2 hours. 36-hour window achieved reliably.
LIGHT MEAL
Essentially unchanged pharmacokinetics. Clinical effect indistinguishable from fasted dosing.
HIGH-FAT MEAL
Minimal effect on peak concentration or time-to-peak. Clinically negligible impact.
GRAPEFRUIT JUICE
Intestinal CYP3A4 inhibition raises tadalafil blood levels unpredictably. Side effect risk increases. Avoid 24-48 hours around dose.
🥪 Practical Meal Guidance
- Dinner date: eat normally. Appetizer, main course, dessert all compatible.
- Business meal: no restrictions on menu choice. Steak, pasta, pizza — all fine.
- Light evening: equally effective; peak timing unchanged.
- Early day dose for evening use: works fine; tadalafil active 36 hours.
- Hydration: full glass of water with dose supports first-use orthostatic safety.
- Grapefruit: avoid grapefruit and juice for 24-48 hours before and after.
🔄 Comparison With Sildenafil
The food-independence is a meaningful difference between tadalafil and sildenafil:
| Meal Scenario | Tadaflo (tadalafil) | Generic Sildenafil |
|---|---|---|
| High-fat dinner | No change in effect timing | Peak delayed 1-2 hours, concentration reduced 30% |
| Light meal | Full effect at usual timing | Mild delay possible |
💊 Meal Freedom Is Practically Important
For men whose intimate moments typically follow restaurant dinners or home-cooked meals with partner, tadalafil's meal independence removes a planning complication. The man can order what he wants from the menu without recalculating medication timing.
🥃 Alcohol Interaction and Moderation Guidance
Alcohol consumption with Tadaflo interacts in two ways: both substances cause vasodilation, raising orthostatic hypotension risk when combined; heavy alcohol directly impairs erectile function through central nervous system depression regardless of PDE5 inhibitor presence.
🥃 Mechanisms of Alcohol Interaction
Additive vasodilation
Both tadalafil (via cGMP) and alcohol (via multiple pathways) dilate blood vessels. Combined effect produces blood pressure drop greater than either alone, particularly on standing.
Direct CNS depression
Alcohol depresses central arousal pathways. Heavy intake reduces libido and physical arousal response that tadalafil is meant to amplify. Medication cannot overcome absent arousal.
Diuretic dehydration
Alcohol inhibits vasopressin, increasing urine output. Dehydrated state amplifies orthostatic hypotension risk.
Extended tadalafil window
Tadalafil active 36 hours. Alcohol caution extends beyond dose evening into following day while medication remains clinically present.
🥃 Alcohol Tolerability Levels
✅ MINIMAL RISK
1-2 drinks over an evening meal. Clinically compatible with tadalafil.
⚠️ MODERATE RISK
3 drinks across the evening. Mild orthostatic risk; mild erection quality effect. Hydrate.
🚫 HIGH RISK
4+ drinks. Significant orthostatic risk; erection quality compromised.
🚫 UNSAFE
Binge drinking (5+ drinks in a few hours). Tadaflo effect undermined; dangerous combination.
💊 Moderation Is Compatible
A glass or two of wine with a meal, or a cocktail at a social gathering, do not meaningfully impair Tadaflo response for most men. Problems arise with heavy drinking or binge patterns, not with normal social alcohol use. Men who are heavy drinkers should address the drinking pattern alongside ED treatment.
🛑 Nitrate Contraindication and Drug Interactions
The nitrate contraindication is the single most important safety rule for Tadaflo. Combined use of tadalafil with nitrate medications can cause life-threatening hypotension. The 48-hour avoidance window is longer than for sildenafil because tadalafil persists in the body for approximately 5 days.
🛑 Absolute Nitrate Contraindication
Men taking any nitrate medication must not use Tadaflo. The interaction can be fatal.
Nitrate medications include:
- Nitroglycerin (sublingual tablets, patches, ointments, aerosol spray)
- Isosorbide dinitrate (immediate and extended release)
- Isosorbide mononitrate
- Amyl nitrite and butyl nitrite ("poppers" recreational use)
- Sodium nitroprusside (hospital use)
If any of these are in use, alternative ED treatment is required.
⏰ 48-Hour Window After Dose
If a man takes Tadaflo and later needs nitrate for cardiac emergency, the longer tadalafil half-life matters:
- At least 48 hours must pass after tadalafil dose before nitrate use
- Longer window than sildenafil (24 hours) because tadalafil persists
- In cardiac emergency, non-nitrate approaches are used in the interim
- Emergency care providers should know about recent PDE5 use
- Carrying medication information for cardiac emergencies is prudent
⚠️ Important Secondary Interactions
Alpha-blockers
Tamsulosin, doxazosin, alfuzosin, silodosin, terazosin, prazosin. Additive orthostatic hypotension. Separate dosing by at least 4 hours. Start Tadaflo at 10 mg if alpha-blocker in use.
Strong CYP3A4 inhibitors
Ketoconazole, itraconazole, ritonavir and other HIV protease inhibitors, clarithromycin, telithromycin, nefazodone. Can raise tadalafil levels substantially. Use 10 mg maximum or avoid.
Moderate CYP3A4 inhibitors
Erythromycin, fluconazole, diltiazem, verapamil. Consider 10 mg dose; monitor response and side effects.
Riociguat
Contraindicated. Soluble guanylate cyclase stimulator for pulmonary hypertension. Dangerous hypotension with any PDE5.
✅ Typically Compatible Medications
- Metformin, insulin, and other diabetes medications
- Statins (atorvastatin, rosuvastatin, simvastatin)
- Non-nitrate blood pressure medications (ACE inhibitors, ARBs, most calcium channel blockers, beta-blockers)
- Standard antibiotics (amoxicillin, azithromycin, cephalosporins — except clarithromycin)
- Acid reducers (omeprazole, pantoprazole, famotidine)
- Thyroid hormone replacement
- Standard analgesics (acetaminophen, ibuprofen, naproxen)
- SSRI antidepressants (sertraline, escitalopram) — no PDE5-specific interaction
- Finasteride (for prostate or hair loss) — often used together with tadalafil
💊 Medication Review Is Mandatory
Every man starting Tadaflo should have a complete medication review with pharmacist or prescriber before first use. The nitrate exclusion is life-saving and nonnegotiable. Alpha-blocker and CYP3A4 inhibitor considerations may require dose adjustment. This review takes 10-15 minutes but prevents serious harm.
❤️ Cardiovascular Assessment Before First Use
Cardiovascular safety assessment precedes Tadaflo use. Tadalafil itself does not increase heart attack rates in long-term studies, but sexual activity requires modest cardiovascular reserve. The 48-hour tadalafil persistence extends cardiovascular considerations beyond the dose evening.
❤️ Princeton Consensus Framework
The Princeton Consensus panels have established risk stratification for ED treatment candidates:
Low cardiovascular risk
Asymptomatic CV disease, controlled hypertension, mild stable angina controlled with occasional nitroglycerin only, past uncomplicated MI more than 6 weeks ago, successful revascularization. PDE5 inhibitor use appropriate with standard precautions.
Intermediate risk
Multiple CV risk factors, moderate stable angina, past MI 2-6 weeks ago, heart failure NYHA Class II, non-cardiac vascular disease. Cardiology evaluation and often exercise testing before PDE5 use.
High risk
Unstable angina, uncontrolled hypertension, recent MI less than 2 weeks ago, heart failure Class III-IV, high-risk arrhythmia, moderate-to-severe valvular disease. Sexual activity itself is risky; PDE5 inhibitors generally contraindicated until cardiac stability.
🏃 Exercise Tolerance as Practical Gauge
Sexual activity requires approximately the metabolic equivalent of climbing 2 flights of stairs or walking briskly. Simple questions tell much:
- Can you climb 2 flights of stairs without stopping?
- Can you walk 1 mile at normal pace without chest pain?
- Do you tolerate moderate activity (housework, gardening) comfortably?
- Do you have exertional symptoms (chest pain, severe breathlessness, dizziness)?
Good exercise tolerance predicts safe sexual activity. Men who cannot meet these benchmarks need cardiac evaluation before any sexual activity, with or without PDE5 inhibitor.
💊 Specific Conditions
| Cardiac Situation | Tadaflo Approach |
|---|---|
| Controlled hypertension, single-agent | Usually appropriate; monitor BP initially |
| Daily nitrate for angina | Contraindicated. 48-hour window. |
| Prior MI more than 6 months ago, stable | Usually appropriate |
| Heart failure NYHA Class II | Cardiology input; start at 10 mg |
| Alpha-blocker plus multiple antihypertensives | Caution; 10 mg start; separate dose timing |
| Pulmonary arterial hypertension | Tadalafil approved separately as Adcirca; coordinate with pulmonologist |
💊 Long Window Extends Cardiac Awareness
The 48-hour tadalafil persistence means cardiovascular considerations extend beyond the dose evening. Men with coronary disease should know the 48-hour nitrate avoidance window. Emergency medical identification mentioning recent PDE5 use is particularly useful for men with cardiovascular risk.
📊 Side Effect Profile and Management
Tadalafil side effects are typically mild and transient but can last longer than with shorter-acting PDE5 inhibitors because of the 36-hour window. Headache, dyspepsia, back pain, and myalgia are the characteristic effects. Vision changes are less common than with sildenafil.
📊 Clinical Trial Side Effect Rates
| Effect | Placebo | Tadalafil 20 mg |
|---|---|---|
| Headache | 4% | 11-15% |
| Dyspepsia | 1% | 7-11% |
| Back pain | 2% | 6-10% |
| Myalgia | 1% | 4-7% |
| Nasal congestion | 1% | 4-7% |
| Flushing | 1% | 3-5% |
| Visual disturbance | 0% | less than 1% |
| Discontinuation due to side effects | 1-2% | 2-3% |
🎯 Managing Common Effects
Headache
Acetaminophen before or at onset. Adequate hydration throughout the day. May persist longer than with sildenafil due to extended tadalafil window.
Dyspepsia
Light meal when dosing if susceptible. Antacid helps acute symptoms. H2 blocker (famotidine) or PPI (omeprazole) if chronic reflux pattern.
Back pain (tadalafil-characteristic)
Appears 12-24 hours after dose and lasts 24-48 hours. From PDE11 affinity in skeletal muscle. Acetaminophen, ibuprofen, hot shower, heating pad help. Men with persistent back pain can switch to sildenafil (minimal PDE11 effect).
Myalgia
Also from PDE11. Similar management as back pain.
Nasal congestion
Vascular dilation in nasal passages. Saline nasal spray. Avoid pseudoephedrine. Resolves as medication clears.
Flushing
Expected systemic vasodilation effect. Cool environment and cool drinks help. Resolves within hours.
🚨 Emergency Care Required
- Erection lasting 4+ hours (priapism)
- Sudden partial or complete vision loss (NAION)
- Sudden decrease or loss of hearing
- Chest pain, severe palpitations, difficulty breathing
- Severe allergic reaction with facial or throat swelling
- Fainting or severe sustained dizziness
- Severe sustained headache not relieved by usual measures
💊 Side Effects Resolve as Medication Clears
Most men experience mild side effects at most, and these resolve within 24-48 hours as tadalafil clears. The back pain and myalgia profile is tadalafil-specific and worth knowing because switching to sildenafil often eliminates it for men who find it bothersome.
🧠 Mental Health and Long Window Benefit
Mental health intersects with ED in bidirectional ways. Depression and anxiety can cause ED directly through altered neurotransmitter signaling; ED itself frequently causes depression, anxiety, and relationship strain. Tadaflo's long window addresses one specific psychological dimension — the timing anxiety that burdens shorter-acting medications.
🧠 Mental Health as ED Contributor
- Depression reduces libido and alters central arousal pathways
- Anxiety activates sympathetic nervous system that opposes erection
- Performance pressure creates self-fulfilling failure cycle
- SSRI antidepressants commonly cause ED — the clinical dilemma
- Relationship conflict often manifests as sexual dysfunction
- Stress and burnout drain the mental resources needed for intimacy
⏰ How Long Window Helps Anxiety
Performance anxiety operates on timing. Men worry about whether erection will happen, whether it will persist, whether they are performing on schedule. Tadalafil's 36-hour window addresses this specifically:
- No scheduled dose-to-intimacy window to meet
- Intimate moments happen when natural arousal arises
- Second-chance opportunity if first attempt feels off
- Reduced partner awareness of specific dosing
- Spontaneity feels more like intimacy, less like scheduled event
- Anxiety cycle broken by removing the timing pressure
🧘 Supportive Mental Health Approaches
- Depression screening: PHQ-9 or similar; treat clinically significant depression
- Anxiety assessment: performance anxiety responsive to psychological support
- Sex therapy: specifically trained therapists address psychogenic ED
- Mindfulness: reduces over-monitoring and performance pressure
- Couples counseling: for relationship dimensions
- Stress management: exercise, hobbies, sleep hygiene
💊 Combined Approach Often Best
Tadaflo plus attention to underlying psychological factors often produces better outcomes than medication alone. The medication provides physiological backup; mental health work addresses the context in which ED developed.
🧓 Age-Based Dose Selection and Considerations
Age influences Tadaflo use through pharmacokinetic changes, accumulated medications, and shifting clinical context. Older men often need dose reduction and benefit from attention to specific aging-related concerns.
🧓 Dose Selection By Age
| Age Range | Typical Approach |
|---|---|
| Under 18 | Not approved; no clinical use case |
| 18-40 | Often psychogenic; address underlying causes; Tadaflo 10-20 mg |
| 40-55 | Tadaflo 20 mg standard; CV workup; lifestyle attention |
| 55-65 | Tadaflo 20 mg; consider daily low-dose if BPH or frequent use |
| 65-75 | Start at 10 mg; adjust up as tolerated |
| 75+ | Daily low-dose tadalafil often preferred over on-demand |
👉 Age-Related Considerations
- Hepatic CYP3A4 activity declines with age — drug clearance slower
- Baroreflex response diminishes — orthostatic hypotension risk higher
- Multiple cardiovascular medications common
- Alpha-blocker therapy for BPH frequent
- Vascular ED predominates — may respond less dramatically than psychogenic
- BPH + ED combination elegantly addressed by daily low-dose tadalafil
- Nitrate therapy for angina is specific exclusion
💊 Daily Low-Dose Often Fits Older Men
For men over 60-65 with ED and emerging BPH symptoms, daily tadalafil 2.5-5 mg often fits better than on-demand Tadaflo 20 mg. The daily approach provides continuous coverage of both conditions and eliminates dose-timing considerations entirely.
🏥 BPH and ED Dual Treatment Opportunity
Benign prostatic hyperplasia (BPH) is common in men over 50 and often coexists with ED. Tadalafil has unique FDA approval for both conditions — daily low-dose tadalafil 5 mg addresses BPH urinary symptoms and ED simultaneously. This dual indication is a distinctive clinical advantage of tadalafil among PDE5 inhibitors.
🏥 Why Tadalafil Helps BPH
PDE5 expression in prostate and bladder
The same PDE5 enzyme that regulates penile smooth muscle also exists in prostate stroma, bladder neck, and bladder detrusor muscle.
Smooth muscle relaxation in prostate
PDE5 blockade allows cGMP to accumulate in prostatic smooth muscle, reducing dynamic obstruction. Static obstruction from gland enlargement is unchanged but the muscular component relaxes.
LUTS symptom improvement
Reduced hesitancy, improved urinary stream, reduced incomplete emptying, less frequency and urgency. IPSS scores improve similar to alpha-blocker therapy.
ED support simultaneous
Same tablet, same mechanism, same timing. Daily use provides continuous coverage. Clinically elegant.
📅 Daily Low-Dose Protocol
Dose: 2.5-5 mg once daily
This is a separate strength from Tadaflo 20 mg. Daily use at 20 mg is not safe. Men needing daily tadalafil use a different product at the lower strength.
Steady state in 5-7 days
Daily tadalafil requires several days to reach continuous therapeutic levels. Full BPH symptom and ED benefit develops over 2-4 weeks.
Same time each day
Consistency matters more than specific hour. Morning or evening — whichever supports daily habit.
Removes timing considerations
No scheduled dose relative to intimacy. Any time of day or night, if arousal arises, response is supported.
🎯 Candidate Profile for Daily Tadalafil
- Both ED and BPH symptoms — natural fit
- Frequent intimacy pattern (more than twice weekly)
- Preference for spontaneity without dose-timing
- Partners finding scheduled doses stressful
- Men with modest reduction of response to on-demand use
- Older men wanting simpler regimen
💊 Unique Dual Benefit
Tadalafil is the only PDE5 inhibitor with FDA approval for both ED and BPH symptoms. For men with both conditions, daily low-dose tadalafil often provides elegant single-medication coverage that other PDE5 inhibitors cannot match.
🏃 Lifestyle Factors Amplifying Response
Lifestyle choices substantially affect both ED risk and tadalafil response quality. Cardiovascular health, body weight, exercise habits, smoking, sleep, and stress management all shape how well the medication works and whether its benefit sustains over time.
🏃 High-Impact Lifestyle Factors
🏋️ AEROBIC EXERCISE
150 minutes weekly moderate-intensity activity. Improves endothelial function; reduces anxiety; associated with better PDE5 response.
⚖️ HEALTHY WEIGHT
Obesity worsens ED via vascular, metabolic, hormonal pathways. 5-10% weight loss consistently improves erectile function.
🚬 NO SMOKING
Nicotine and tobacco smoke damage penile vascular endothelium. Quitting improves ED within months; smoking cessation benefit compounds across years.
😴 QUALITY SLEEP
7-8 hours nightly supports hormonal balance. Sleep apnea increases ED risk through nocturnal hypoxia; CPAP treatment helps.
🍰 MEDITERRANEAN DIET
Vegetables, legumes, fish, olive oil, whole grains. Associated with better erectile function in population studies.
🧘 STRESS CONTROL
Chronic stress maintains sympathetic activation that opposes erection. Mindfulness, exercise, meaningful recreation all help.
🍃 Substance Factors
- Alcohol: moderate (1-2 drinks) tolerable; heavy use impairs response
- Amyl nitrite ("poppers"): absolutely contraindicated — same mechanism as medical nitrates
- Cannabis: variable effects on sexual function; no major PDE5 interaction
- Opioids: chronic use suppresses testosterone, worsens ED
- Grapefruit: CYP3A4 inhibition raises tadalafil levels; avoid 24-48 hours before and after
- Recreational stimulants: additive cardiovascular stress
💊 Lifestyle Compounds Medication Effect
Men who exercise regularly, maintain healthy weight, avoid smoking, manage stress, and sleep adequately consistently show better PDE5 inhibitor response than men with contrary lifestyle. The medication and lifestyle work together — neither replaces the other.
🧪 Hormonal Workup When Clinically Appropriate
Hormonal evaluation deserves consideration when ED presentation includes specific features: low libido, fatigue, loss of morning erections, muscle mass changes, or inadequate response to tadalafil at optimal dose. Not every man with ED needs hormonal workup, but the right clinical pattern makes it valuable.
🧪 When Workup Fits
- ED with reduced sexual desire — libido depends on testosterone
- Fatigue, depressed mood, reduced energy — classic hypogonadism cluster
- Loss of muscle mass or strength changes
- Absence of spontaneous morning erections
- Inadequate tadalafil response at optimal dose
- Features suggesting thyroid dysfunction
- Visual field changes or headaches (prolactinoma consideration)
📋 Appropriate Panel
| Test | Purpose |
|---|---|
| Morning total testosterone | Hypogonadism screen; peak diurnal 7-11 AM |
| Free testosterone and SHBG (if total borderline) | More accurate in obesity, aging, inflammation |
| LH and FSH | Differentiate primary (testicular) vs secondary (pituitary) hypogonadism |
| Prolactin | Pituitary adenoma screen if suggestive symptoms |
| TSH, free T4 | Thyroid function |
| PSA | Baseline if considering testosterone replacement |
🔧 Addressing Identified Issues
- Confirmed hypogonadism: testosterone replacement therapy; may be combined with tadalafil for optimal effect
- Elevated prolactin: dopamine agonist; MRI if adenoma suspected
- Hypothyroidism: levothyroxine replacement
- Diabetes: glycemic control supports overall sexual function
- Follow-up on testosterone: hematocrit, PSA, blood pressure monitoring
💊 Testosterone + Tadalafil Often Needed Together
For men with confirmed hypogonadism who inadequately respond to tadalafil alone, testosterone replacement often restores adequate response. Libido returns with hormone normalization; erectile function improves with PDE5 inhibitor working on a now-responsive hormonal substrate.
🧫 CYP3A4 Metabolism and Prolonged Interactions
CYP3A4 is the exclusive clinical pathway for tadalafil metabolism. Hepatic CYP3A4 clears essentially all tadalafil; minor renal elimination plays no significant role. The long half-life means that drugs modifying CYP3A4 produce prolonged effects on tadalafil levels, often persisting for days.
🧫 Metabolic Pathway
- Tadalafil nearly exclusively hepatically metabolized via CYP3A4
- Formation of catechol metabolite then conjugation
- Elimination predominantly in feces (via bile)
- Approximately 36% urinary elimination (as metabolites)
- Terminal half-life ~17.5 hours in healthy adults
- Clearance can be slower with hepatic impairment or genetic variation
🔒 CYP3A4 Inhibitors
Strong inhibitors
Ketoconazole, itraconazole, posaconazole, voriconazole (antifungals). Ritonavir, saquinavir, nelfinavir, indinavir, atazanavir, darunavir (HIV protease inhibitors). Clarithromycin, telithromycin (antibiotics). Nefazodone. Can elevate tadalafil AUC several-fold. Use 10 mg maximum; often preferable to avoid.
Moderate inhibitors
Erythromycin, fluconazole, diltiazem, verapamil, aprepitant. Grapefruit juice (intestinal CYP3A4). Modest level elevation. Consider 10 mg; monitor side effects.
Mild inhibitors
Standard-dose cimetidine, ciprofloxacin. Clinically negligible. No dose adjustment needed.
🔓 CYP3A4 Inducers
Inducers accelerate clearance, lowering tadalafil levels and potentially reducing effectiveness:
- Rifampin — strong inducer; may render tadalafil ineffective
- Rifabutin — moderate inducer
- Phenytoin, carbamazepine, phenobarbital — antiepileptic inducers
- St John's wort — herbal inducer; often inadvertent use
- Men on these may need alternative ED approach or dose adjustment
💊 Interaction Effects Last Longer
Because tadalafil persists longer than sildenafil, CYP3A4 interactions take longer to resolve. If strong inhibitor was recently used, raised tadalafil levels may last several days. Pharmacy review before first dose catches these interactions.
📋 Clinical Workup and IIEF Assessment
Clinical workup for ED establishes the context for tadalafil therapy. The IIEF-5 questionnaire measures ED severity objectively; history, examination, and selected laboratory testing clarify underlying contributors.
📋 IIEF-5 Score Interpretation
Five-question score ranging 5-25:
- 22-25: no ED
- 17-21: mild ED
- 12-16: mild-to-moderate ED
- 8-11: moderate ED
- 5-7: severe ED
Repeating IIEF-5 after 4-6 Tadaflo attempts gives objective measure of response.
🏥 Clinical Workup Elements
- History: onset pattern, situational vs global, morning erections, libido, relationship context
- Medical history: cardiovascular risk factors, diabetes, pelvic surgery, neurological conditions, mental health
- Medication review: nitrates specifically, alpha-blockers, antidepressants, CYP3A4 modulators
- Physical examination: blood pressure, waist circumference, genital examination, prostate exam as indicated
- Laboratory testing: fasting glucose and lipids; testosterone if hypogonadism features; basic metabolic panel
🔍 Additional Testing When Indicated
- Nocturnal penile tumescence testing (rarely clinically necessary)
- Penile Doppler ultrasound for vascular evaluation before invasive therapy
- Cavernosometry for venous leak evaluation (specialist test)
- Cardiac stress testing for intermediate cardiovascular risk
- IPSS questionnaire for BPH symptoms if daily tadalafil considered
- Hormonal panel for suspected hypogonadism (previous section)
💊 Workup Precedes Treatment
For most men with uncomplicated ED, a focused workup takes 20-30 minutes and identifies the clinical context for Tadaflo use. Nitrate exclusion is the critical step. Cardiovascular risk stratification guides caution. Underlying contributors can often be addressed alongside pharmacotherapy.
📈 Objective Response Monitoring
Objective monitoring of Tadaflo response requires tracking across 4-6 fair attempts. Because of the 72-hour minimum between doses, these attempts span 3-6 weeks. Patience in the evaluation period often rewards men with better response as timing and context are optimized.
📈 Dimensions to Track
💡 ERECTION RIGIDITY
Hardness adequate for penetration and maintained through intercourse. Target: substantial improvement from baseline.
⏰ ONSET AND PEAK
30-60 minute onset; peak at 2 hours. Confirms absorption and timing.
📅 EFFECT PERSISTENCE
Response available up to 36 hours after dose. Documents the window personally.
😊 SATISFACTION
Overall intercourse satisfaction. Partner satisfaction included.
💚 CONFIDENCE
Expectation of successful intercourse. Grows with repeated success.
😔 SIDE EFFECTS
Nature, severity, duration. Headache, back pain, dyspepsia are typical.
🔄 Response Patterns and Next Steps
| Pattern Over 4-6 Attempts | Recommended Response |
|---|---|
| Good response, acceptable side effects | Continue at effective dose |
| Partial response at 20 mg | Already at maximum on-demand; consider daily tadalafil or hormonal workup |
| Side effects acceptable but mildly bothersome | Try 10 mg; may provide adequate response with less burden |
| Back pain limiting use | Switch to sildenafil (minimal PDE11 effect) |
| Frequent intimacy pattern developing | Transition to daily low-dose tadalafil |
| No response at 20 mg | Comprehensive workup; hormonal, vascular, psychological evaluation |
💊 Objective Tracking Supports Good Decisions
Repeating IIEF-5 after several attempts gives objective measure of response. Subjective impression can be unreliable; a 5-point IIEF score improvement is clinically meaningful even when the man might otherwise feel the medication is not helping enough.
🏥 Managing Side Effects Including PDE11 Back Pain
Managing Tadaflo side effects involves practical strategies for the common effects, understanding of tadalafil-specific back pain, and recognition of when to switch to alternative PDE5.
🏥 Managing Specific Effects
Headache
Acetaminophen at onset. Hydration important. Caffeine withdrawal effect sometimes mimics medication headache. Headache may last longer than with sildenafil because of extended tadalafil window.
Dyspepsia
Take with light meal rather than empty stomach if susceptible. Antacid for acute symptoms. H2 blocker or PPI for chronic reflux. Avoid lying flat immediately after dosing.
Back pain and myalgia
Tadalafil-characteristic. Appears 12-24 hours after dose; lasts 24-48 hours. From PDE11 affinity in skeletal muscle. Acetaminophen, ibuprofen, warm shower, stretching all help. Resolves fully as medication clears. Men with persistent bothersome pain can switch to sildenafil (no significant PDE11 effect).
Nasal congestion
Vascular dilation in nasal mucosa. Saline nasal spray can help. Avoid pseudoephedrine decongestants — vasoconstrictor interaction concern. Resolves within hours.
Flushing
Expected systemic vasodilation. Cool environment, cool drinks. Brief and cosmetic. Not harmful.
Visual effects (uncommon)
Rare with tadalafil (unlike sildenafil). Any mild tint or brightness change is usually brief. Sudden vision loss requires immediate medical attention.
🎯 When to Change Approach
- Step down to 10 mg: if side effects noticeable but response adequate
- Switch to sildenafil: for persistent back pain or myalgia (no PDE11)
- Switch to vardenafil: for men needing shorter window; different side effect profile
- Daily low-dose tadalafil: if frequent use pattern developing
- Alternative treatment: injection, vacuum device, or implant for refractory ED
- Discontinue: for severe or unmanageable side effects despite dose and context optimization
🚨 Emergency Care Required
- Erection lasting 4+ hours (priapism)
- Sudden partial or complete vision loss (NAION)
- Sudden hearing loss, possibly with tinnitus or dizziness
- Chest pain or heart attack symptoms
- Severe allergic reaction with facial or throat swelling
- Fainting or severe sustained dizziness
- Severe sustained headache not relieved by usual measures
💊 Most Effects Manageable
Side effect profile is predictable and manageable for most men. The tadalafil-specific back pain profile is distinctive and worth knowing because switching to sildenafil often eliminates it entirely for men who find it bothersome.
🚨 Priapism and NAION Emergency Protocols
Priapism and NAION are the two main medical emergencies associated with any PDE5 inhibitor including tadalafil. Both are rare but genuinely occur. Recognition and rapid response prevent permanent damage.
🚨 Priapism — Prolonged Erection 4+ Hours
Prolonged erection without arousal, or persisting after intercourse ended. Blood is trapped; oxygen depletion begins within hours. Permanent erectile tissue damage results from untreated ischemic priapism beyond 6-8 hours.
Immediate response protocol:
- Walk, climb stairs, or light exercise if comfortable (redirects blood flow)
- Cool shower (not cold — cold can worsen things)
- Urinate — sometimes helps resolution
- If persists 4 hours total: emergency room immediately
- Do not drive if dizzy or lightheaded; have someone drive
- Inform ER staff about recent Tadaflo use
- Do not take another PDE5 inhibitor dose
Timeline matters:
- Under 4 hours: usually resolves without intervention
- 4-6 hours: aspiration and alpha-adrenergic injection often effective
- 6-12 hours: urgent intervention needed; permanent damage risk rising
- 12+ hours: significant permanent ED risk
- 24+ hours: often requires surgical shunt
🚨 NAION — Sudden Vision Loss
Non-arteritic ischemic optic neuropathy — interruption of optic nerve blood supply. Partial or complete vision loss, typically affecting one eye, usually painless.
Risk factors:
- Age over 50
- Small optic disc ("disc at risk")
- Hypertension, diabetes, dyslipidemia
- Smoking
- Sleep apnea
- Prior NAION in other eye (strongest predictor of recurrence)
Response:
- Discontinue Tadaflo immediately and permanently
- Urgent ophthalmology or emergency department care
- Prior NAION contraindicates all PDE5 inhibitors going forward
- Report event to prescriber for record
🛡️ Risk Reduction
- Use lowest effective dose (10 mg often adequate)
- Observe 72-hour minimum between doses
- Do not combine with other PDE5 inhibitors or combinations
- Address cardiovascular risk factors (helps prevent NAION)
- Baseline eye examination for men over 50 with vascular risk
- Treat sleep apnea if present
- Carry emergency medical ID mentioning PDE5 use for cardiac events
💊 Rare But Characterized
Priapism and NAION with tadalafil are rare but well-characterized by 20+ years of post-marketing surveillance. Warning signs and intervention timelines are established. Men should know the signs before first dose so rapid response is possible if events occur.
🌞 Daily Low-Dose Approach vs On-Demand
Daily low-dose tadalafil (2.5 or 5 mg) represents a philosophically different approach to ED treatment. Rather than planning around a dose, continuous PDE5 inhibition keeps the erectile pathway responsive. For men with frequent intimacy or those uncomfortable with scheduled dosing, daily use can transform the experience.
🌞 How Daily Dosing Works
Steady-state plasma level is reached after approximately 5 days. From that point, tadalafil concentration remains relatively constant through the dosing interval. Any sexual stimulation can produce response at any time — no planning around dose timing.
- 2.5 mg or 5 mg once daily at approximately the same time each day
- Can be taken with or without food
- Alcohol considerations similar to on-demand but spread over the day
- Response develops over 5-7 days as steady state established
- Discontinuation: effect wanes over 4-5 days as plasma level clears
🎯 Candidates for Daily Dosing
- Frequent intimacy: couples with regular sexual activity more than 2 times weekly
- Spontaneity preference: men who find scheduled dosing clinical or disruptive
- BPH comorbidity: dual treatment of ED and lower urinary tract symptoms with single medication
- Performance anxiety: continuous availability can reduce anticipation stress
- Partial response to on-demand: continuous low level may provide better consistency
- Diabetic ED: some evidence of better outcomes with daily tadalafil
📊 Daily vs On-Demand Comparison
| Dimension | On-Demand (20 mg) | Daily (5 mg) |
|---|---|---|
| Weekly cost | Lower if infrequent | Higher but predictable |
| Peak levels | Higher spikes | Steady low levels |
| Side effect intensity | Higher with 20 mg peak | Lower, more tolerable |
| Spontaneity | 36-hour window | Continuous |
| BPH relief | Not applicable | Continuous relief |
| Starting approach | Immediate ability to try | 5-7 days to steady state |
💊 Daily Changes the Experience
Daily tadalafil removes planning from intimacy. For some men this restores spontaneity that scheduled dosing eliminated. The cost is continuous medication exposure rather than only on days of actual use. The right choice depends on frequency, preference, and comorbid conditions.
👨⚕️ Chronic Medication Interactions in Depth
ED frequently coexists with other chronic conditions. The medication choices for those conditions directly affect PDE5 inhibitor selection, dosing, and timing. Awareness of these intersections prevents interactions and optimizes care.
👨⚕️ Cardiovascular Medications
Nitrates
Absolute contraindication at any dose, any form, any timing. Includes nitroglycerin, isosorbide dinitrate, isosorbide mononitrate, nitroprusside, amyl nitrite recreational use. Minimum 48 hours since last tadalafil dose for emergency nitrate administration.
Alpha-blockers
Doxazosin, terazosin, prazosin, tamsulosin, alfuzosin, silodosin. Additive hypotensive effect. Start on stable alpha-blocker regimen; introduce tadalafil at 10 mg. Space doses by 4+ hours. Tamsulosin and alfuzosin interact less than non-selective alpha-blockers.
Antihypertensives
ACE inhibitors, ARBs, beta-blockers, calcium channel blockers, diuretics all compatible. Monitor for symptomatic hypotension early in combination. Diltiazem and verapamil are mild CYP3A4 inhibitors; dose adjustment rarely needed but monitor.
Riociguat and other guanylate cyclase stimulators
Absolute contraindication. Used for pulmonary hypertension. Combined vasodilation is dangerous. Riociguat and PDE5 inhibitors are mutually exclusive.
🏥 Other Medication Categories
- Antidepressants: SSRIs commonly cause ED; tadalafil counteracts this effect. No pharmacokinetic interaction
- Diabetes medications: all compatible; metformin may improve ED through modest metabolic benefit
- Statins: compatible and often beneficial through improved endothelial function
- Anticoagulants: warfarin, apixaban, rivaroxaban — all compatible; no bleeding interaction
- Opioids: often cause ED through hormonal effect; tadalafil treats symptom
- Benzodiazepines: compatible; may add to dizziness
- Thyroid medications: compatible; optimize thyroid status first
- Prostate cancer treatments: anti-androgens often cause ED; PDE5 inhibitors offer partial relief
💊 Avoid These Combinations
- Nitrates (absolute — 48-hour window)
- Riociguat (absolute — alternative pulmonary hypertension approach)
- Amyl nitrite ("poppers") recreational use
- Combination with other PDE5 inhibitors (no cumulative benefit, increased risk)
- Yohimbine (unregulated supplement; cardiovascular concern)
- Grapefruit juice in large quantities (modest CYP3A4 effect)
💊 Medication List Review Is Mandatory
Full medication list review including supplements, herbals, and recreational substances is mandatory before first Tadaflo dose. Men should not assume their physician is aware of all substances; a complete self-report is the safest approach.
🔬 Diabetic ED and Multimodal Treatment
Diabetic erectile dysfunction has distinctive features: earlier onset, more severe presentation, often less responsive to PDE5 inhibitors, and benefits from aggressive multifactorial management. Tadalafil can be effective but typically requires 20 mg dose and realistic expectations.
🔬 Mechanisms of Diabetic ED
- Endothelial dysfunction: reduced nitric oxide bioavailability
- Microvascular disease: compromised penile arterial supply
- Autonomic neuropathy: impaired erectile signaling pathways
- Advanced glycation end products: tissue stiffening
- Hormonal effects: diabetic men more likely hypogonadal
- Reduced cavernosal smooth muscle: fewer cells, less contractile capacity
- Oxidative stress: hyperglycemia-driven cellular damage
🎯 Tadalafil Response in Diabetes
- Response rate 60-70% vs 80% in non-diabetic ED
- 20 mg often required rather than 10 mg
- Daily low-dose may offer better consistency
- Response improves with glycemic optimization
- Testosterone replacement when hypogonadal often amplifies PDE5 response
- HbA1c under 7.5% associated with better outcomes
- Diabetes duration over 10 years predicts reduced response
- Daily tadalafil may improve endothelial function over time
📋 Comprehensive Approach for Diabetic Men
Metabolic
HbA1c target under 7.5%. Metformin for weight-related insulin resistance. Blood pressure under 130/80. LDL cholesterol under 100 mg/dL (lower for established vascular disease).
Hormonal
Testosterone screening (morning total T). Weight reduction improves T levels. T replacement when low AND symptomatic. Thyroid screening. Prolactin if suggestive history.
Lifestyle
Weight reduction (5-10% of body weight can restore significant function). Mediterranean dietary pattern. 150 minutes moderate exercise weekly. Smoking cessation. Alcohol moderation (2 drinks maximum).
Pharmacologic
Tadalafil 20 mg on-demand or 5 mg daily. Switch to injection therapy if PDE5 unresponsive. Vacuum erection device as adjunct or alternative. Implant for refractory cases.
💊 Diabetes Needs Multimodal Approach
Diabetic ED is a vascular and metabolic condition expressing itself through sexual function. PDE5 inhibitors address the proximate cause but comprehensive diabetes management addresses the root cause and often improves response over time.
🛏️ Post-Prostatectomy Rehabilitation Protocol
Prostate cancer treatment and its sequelae create a specific category of ED where tadalafil has an important rehabilitation role in addition to symptomatic treatment. Radical prostatectomy and radiation therapy both commonly damage the neurovascular bundles controlling erection.
🛏️ Post-Prostatectomy ED
Even with nerve-sparing technique, 40-60% of men experience significant ED after radical prostatectomy. Nerve recovery takes 12-24 months when it occurs.
Rehabilitation protocol:
- Start daily low-dose tadalafil 2-4 weeks after surgery
- Continue 6-12 months to maintain cavernosal oxygenation
- Augment with on-demand tadalafil 20 mg for attempted intercourse
- Add vacuum erection device for daily use (preserves tissue)
- Consider penile injection if PDE5 insufficient
- Patience: nerve recovery can take 18-24 months
💡 Why Early Rehabilitation Matters
- Without regular blood flow, cavernosal smooth muscle undergoes atrophy
- Fibrotic changes develop within months of disuse
- These changes may become permanent if not addressed early
- Daily low-dose tadalafil maintains baseline tissue oxygenation
- Preserved tissue responds better when nerves recover
- Studies show better long-term outcomes with early rehabilitation
🎯 Post-Radiation ED
Radiation causes gradual vascular damage. Onset of ED typically delayed 6-24 months post-treatment. Progression over several years.
- Tadalafil typically effective in early phases
- Response may decline over years as vascular damage progresses
- Daily low-dose may slow progression
- Advanced cases require injection or implant
- Androgen deprivation (if used) compounds ED through hormonal effect
💊 Androgen Deprivation Therapy Context
Men on ADT for prostate cancer face profound ED from low testosterone itself. PDE5 inhibitors have reduced efficacy without adequate testosterone. Treatment focuses on:
- Realistic expectations during active ADT
- PDE5 inhibitor may partially help
- Vacuum device useful adjunct
- Intracavernosal injection often needed
- Function usually recovers partially after ADT discontinuation
💊 Rehabilitation Begins Early
For cancer survivors, penile rehabilitation starting within weeks of treatment gives the best long-term functional outcomes. Daily low-dose tadalafil is a cornerstone of modern protocols. Discussion with the oncology team ensures no contraindications.
💞 Partner Communication and Relational Context
Partner communication around ED and medication use often determines treatment success more than pharmacology. The relational context shapes meaning, response, and continuity.
💞 Opening Conversations
- Timing: calm private moment, not during or after sexual difficulty
- Framing: joint problem to solve, not personal deficiency to confess
- Information: share what you have learned about causes and treatment
- Reassurance: ED is medical, not reflection of partner desirability
- Collaboration: discuss what works, what to try differently
- Patience: a single conversation rarely resolves relationship patterns
💜 Partner Common Experiences
- Confusion about meaning: "Is he less attracted to me?"
- Guilt about performance pressure
- Grief about intimacy loss and future
- Frustration with avoidance patterns
- Relief when medical cause and treatment identified
- Appreciation for being included in the solution
- Occasional ambivalence about medication-dependent sex
💡 What Helps the Relationship
Shared knowledge
Both partners understanding the medication, timing, and expectations removes mystery and reduces pressure.
Realistic expectations
Tadaflo supports response to arousal; it does not create arousal. Both partners understanding this prevents disappointment.
Broader definition of intimacy
Reducing penetration-focused definition of successful sex relieves pressure. Mutual pleasure takes many forms.
Shared responsibility
Partners becoming aware of nitrate avoidance and emergency signs makes safety a joint responsibility.
Professional help
Sex therapy or couples counseling appropriate when ED has caused significant relational distress. Addressing medical and relational dimensions together improves outcomes.
💊 Tadaflo in Context
A medication is a tool, not a solution to the full experience of ED. Partner understanding and collaborative approach transform pharmacology from clinical intervention into relational support. For most couples, open communication multiplies the medication's benefit.
💰 Generic Access Transformed Pricing Landscape
The economic experience of PDE5 inhibitor therapy varies dramatically across markets. Branded Cialis prices contrast with generic tadalafil access that transformed the therapy for most men. Understanding the pricing landscape helps with reasonable expectations.
💰 Pricing Transformation
Generic tadalafil entered major markets starting 2017-2018 as the compound patent expired. Prices dropped 95%+ in most markets.
Approximate per-dose costs:
- Branded Cialis 20 mg: $20-70 per dose depending on market
- US generic tadalafil 20 mg: $1-5 per dose with insurance
- EU generic tadalafil 20 mg: $2-8 per dose
- Generic tadalafil in international pharmacies: $0.50-2 per dose
- Daily 5 mg tadalafil monthly: $15-60 generic, $150-350 branded
- Prices vary with pharmacy, insurance, and manufacturer
🏷️ Branded vs Generic Equivalence
- Both contain identical tadalafil active ingredient
- Both must meet same bioequivalence standards for approval
- Pharmacokinetic profile essentially identical
- Clinical response equivalent in trials
- Side effect profile equivalent
- Inactive ingredients may differ (binders, colorants)
- Rare allergy to specific inactive ingredient possible
- Switching between generic manufacturers requires no adjustment
🔧 Cost Optimization
- Dose splitting: 20 mg scored tablets split to 10 mg can reduce per-dose cost
- Daily 5 mg: monthly supply more economical than frequent on-demand
- Insurance tiers: generic tadalafil usually lowest tier
- Manufacturer coupons: for branded Cialis if preferred
- Pharmacy comparison: significant price differences across pharmacies
- Mail-order pharmacies: often better pricing for chronic medications
- International options: careful source verification required
⚠️ Source Caution
Verified pharmacy sources are important for authentic medication. Counterfeit tadalafil is a recognized problem with unreliable active ingredient content, impurities, and sometimes adulteration with other substances. Signs of problematic sources include no prescription requirement, prices substantially below generic market, unknown manufacturer, packaging inconsistencies, or unusual tablet appearance.
💊 Access Has Transformed
Generic entry has made effective ED treatment affordable for virtually any man who needs it. The clinical equivalence between branded and generic is well-established. Economic barriers to appropriate care have essentially disappeared where generic access exists.
🛬 Travel Planning and International Considerations
Travel with Tadaflo involves practical considerations around time zones, climate, security, and continuity. The long half-life of tadalafil creates some flexibility but also specific considerations for travelers.
🛬 Air Travel Specifics
- Carry medication in original pharmacy packaging in carry-on bag
- Prescription label visible and legible
- Keep documentation of prescription in case questions arise
- Check destination country regulations — most permit personal use quantities
- Some destinations consider PDE5 inhibitors prescription-only; others OTC
- Avoid combining first dose with jet lag disorientation
- Time zone changes do not require dose adjustment for on-demand use
- Daily dose: adjust toward destination time gradually over several days
🌡️ Climate and Storage
- Store between 15-30°C (59-86°F)
- Avoid car dashboards, direct sunlight
- Protect from humidity (hot bathroom cabinet suboptimal)
- Original packaging provides best protection
- Climate-controlled luggage preferred over checked bags in hot destinations
- Tropical destinations: consider insulated medication case
- Freezing temperatures also affect tablet integrity
🌍 Country-Specific Considerations
United States and most of Europe
Prescription required but personal travel supply well-accepted. Original pharmacy packaging adequate documentation.
United Kingdom
Some tadalafil formulations OTC since 2018. Personal travel supply uncomplicated.
Middle East
UAE, Saudi Arabia, Qatar: carry prescription documentation. Personal use quantities generally accepted but caution with large supplies.
Southeast Asia
Thailand, Vietnam, Indonesia: often available OTC. Original packaging preferred for identification.
Latin America
Mexico, Costa Rica, Brazil: generally available with varying prescription requirements. Personal use well-tolerated at customs.
💡 Trip Planning Checklist
- Supply for trip plus 1 week buffer for delays
- Pharmacy packaging with prescription label
- Written prescription or physician letter if traveling to restrictive destination
- Medication divided between carry-on and checked bag (minimize loss risk)
- Note of generic name (tadalafil) in case replacement needed abroad
- Awareness that alcohol tolerance may change with travel fatigue
- Partner awareness of medication and timing if sudden travel need
💊 Travel Compatible With Treatment
The 36-hour window and long half-life make Tadaflo particularly travel-friendly. Jet lag affects timing less than it would with short-acting PDE5 inhibitors. Reasonable precautions prevent nearly all travel-related issues.
🏃♂️ Lifestyle Foundations for Erectile Health
Lifestyle optimization often produces larger improvements in erectile function than any single medication. For many men, pharmacotherapy becomes the icing on vascular, metabolic, and psychological foundations rather than the primary intervention.
🏃♂️ Physical Activity
- 150 minutes moderate aerobic activity weekly (walking, cycling, swimming)
- Strength training 2 sessions weekly
- Studies show equivalent effects to low-dose PDE5 therapy over 6-12 months
- Mechanism: endothelial function, nitric oxide synthesis, body composition
- Pelvic floor exercises specifically beneficial for erectile mechanics
- Avoid prolonged bicycle seat compression (perineum pressure)
- Combines synergistically with tadalafil
🥗 Nutrition
- Mediterranean dietary pattern associated with reduced ED risk
- Vegetables, legumes, fish, olive oil, nuts, moderate wine
- Limit red meat, refined grains, sugar-sweetened beverages
- Weight reduction: 5-10% body weight loss can restore significant function
- Flavonoid-rich foods (berries, citrus, dark chocolate) linked to better outcomes
- Adequate zinc and vitamin D status support testosterone
- Avoid chronic caloric restriction (lowers testosterone)
🚬 Smoking and Substances
- Smoking cessation produces measurable improvement in 3-6 months
- Vascular endothelial function recovers partially after cessation
- Marijuana regular use associated with impaired function (dose-dependent)
- Cocaine, methamphetamine both cause acute and chronic erectile problems
- MDMA/ecstasy causes significant ED acutely
- Opioid use causes hormonal and direct erectile dysfunction
- Chronic heavy alcohol use causes multiple layers of damage
🛌 Sleep and Recovery
- 7-9 hours quality sleep nightly supports testosterone and erectile function
- Sleep apnea screening and treatment can transform ED
- CPAP therapy improves erectile function in moderate-severe sleep apnea
- Shift work disrupts hormonal rhythms affecting function
- Caffeine late in day can impair sleep quality
- Stress management (meditation, therapy) improves outcomes
- Morning testosterone peak depends on quality overnight sleep
🧠 Mental Health Integration
- Depression treatment often improves ED (if not SSRI-related)
- Anxiety reduction through CBT, mindfulness, or medication
- Performance anxiety specifically responds to cognitive techniques
- Couples therapy addresses relational contributors
- Sex therapy for specific sexual function challenges
- Stress reduction techniques: meditation, breathing, yoga
- Processing of significant life stressors
💊 Foundation Matters More Than Medication
For most men, the foundation of lifestyle factors determines ultimate function. Tadaflo amplifies response in a man with reasonable vascular health; it cannot fully compensate for severe vascular compromise. Investment in lifestyle pays returns in function, response to medication, and overall health.
❌ Common Misconceptions and Realistic Expectations
Common misconceptions about tadalafil shape men's expectations and often create unnecessary concern or false confidence. Clearing up these specific misunderstandings supports better outcomes.
❌ Misconception vs Reality
Myth: tadalafil creates arousal or desire
Reality: tadalafil enhances erectile response to sexual stimulation. Without arousal and stimulation, no erection occurs. Libido medications are entirely separate category.
Myth: higher dose always better
Reality: 20 mg is maximum; higher doses increase side effects without additional benefit. Many men do well on 10 mg.
Myth: tadalafil causes dependence
Reality: no physiological dependence. Discontinuation produces no withdrawal. Psychological dependence can develop as confidence tied to medication use, but this is separate from pharmacological dependence.
Myth: tadalafil damages the heart
Reality: tadalafil is cardiovascularly safe in men with controlled cardiac disease. 20+ years of surveillance show no excess cardiac events. The exercise required for sexual activity is the main consideration, addressed through Princeton Consensus framework.
Myth: tadalafil lowers natural testosterone
Reality: tadalafil does not affect hormonal production. Testosterone, LH, and FSH levels are unchanged.
Myth: 36 hours of continuous erection
Reality: the 36-hour window describes response availability. Erection only occurs with sexual stimulation and ends normally. The window is responsiveness, not persistent erection.
Myth: cannot drink alcohol at all
Reality: moderate alcohol (1-2 drinks) is compatible. Heavy alcohol impairs both erectile function and medication effect.
Myth: generic less effective than branded
Reality: generics meet bioequivalence standards. Clinical response is equivalent. Price difference reflects patent expiration, not quality difference.
📋 Realistic Expectations
- 80% of men achieve significant improvement
- 20% have inadequate response or intolerable side effects
- Response may improve across first several attempts as context optimizes
- Not every attempt will succeed even in good responders
- Pre-existing severe vascular disease limits response
- Occasional variation does not indicate failure
- Patience across 4-6 fair attempts gives true assessment
💊 Accurate Information Supports Success
Realistic expectations improve both outcomes and satisfaction. Men who understand what tadalafil does and does not do navigate the therapy well. Those with inflated or deflated expectations often struggle with the actual experience.
🔄 Second-Line and Specialist Treatment Options
When tadalafil response is inadequate at maximum dose, second-line and specialist approaches offer significant benefit. Many men progress through a hierarchy of treatments, often ending with substantial restoration of function.
🔄 Switching Within the Class
- Sildenafil: shorter window, no PDE11 back pain, lower cost per dose
- Vardenafil: distinct side effect profile, caution with QT prolongation
- Avanafil: fastest onset, selective PDE5, less visual effects
- Approximately 20% of non-responders to one PDE5 respond to another
- No cross-dependence; switch requires only awareness of timing differences
- Trial of alternative PDE5 before escalating to injection therapy
💉 Intracavernosal Injection Therapy
Alprostadil (PGE1), either alone or in combinations (bimix, trimix). Direct injection into cavernosal body produces reliable erection in nearly all men.
- Response rate over 90% independent of underlying cause
- Onset 10-20 minutes
- Duration 30-90 minutes
- Starts with urologist-supervised titration
- Fine needle; most men tolerate well after initial anxiety
- Priapism risk higher than oral PDE5 but manageable
- Peyronies disease risk from repeated injection
- Effective in diabetic ED, post-prostatectomy, severe vascular disease
💨 Vacuum Erection Device
- Negative pressure cylinder draws blood into penis
- Constriction ring at base maintains erection
- Mechanical, no systemic medication
- Useful adjunct for post-prostatectomy rehabilitation
- Can combine with PDE5 inhibitors
- Learning curve 2-4 weeks
- Less spontaneous than oral medication
- No systemic side effects
🏥 Intraurethral Alprostadil (MUSE)
- Alprostadil suppository inserted into urethra
- Less invasive than injection
- Lower response rate than injection (approximately 40-60%)
- Burning sensation common side effect
- Option for men unable or unwilling to inject
- Pre-ejaculate transmission concern with pregnant partner
⚕️ Penile Prosthesis
Surgical implant of inflatable or malleable device within cavernosal bodies. Definitive treatment for refractory ED.
- Inflatable 3-piece: most natural result, highest cost
- Semi-rigid malleable: simpler, lower cost
- Satisfaction rates over 90% in appropriate candidates
- Infection risk 1-3%; higher in diabetics
- Mechanical failure 10-15% within 10 years
- Partner satisfaction equivalent or higher than other treatments
- Appropriate when all less invasive options have failed
🧬 Emerging Approaches
- Low-intensity shockwave therapy (LiSWT): investigational for vascular ED
- Platelet-rich plasma (PRP) injection: insufficient evidence
- Stem cell therapy: experimental
- Testosterone replacement when hypogonadal
- Combination therapy (PDE5 + injection) for severe cases
- Topical nitric oxide donors in development
💊 Treatment Hierarchy Exists
Tadalafil failure is not treatment failure — it is the beginning of specialist evaluation. Urologist consultation offers a hierarchy of effective treatments. The majority of men achieve satisfactory function with appropriate approach.
📖 Scientific Development and Historical Context
The scientific journey of PDE5 inhibitors is a remarkable story of serendipitous discovery leading to transformative therapy. Understanding the history clarifies the current place of tadalafil in treatment.
📖 Discovery and Development
- 1980s: Pfizer developing cardiovascular PDE5 inhibitor (angina)
- Early 1990s: cardiovascular benefit disappointing; patients noting erectile side effect
- 1998: Sildenafil (Viagra) approved as first oral ED treatment
- Late 1990s: Pfizer competitors seek improved compounds
- 2003: Tadalafil (Cialis) and vardenafil (Levitra) approved
- 2008: Daily low-dose tadalafil (2.5-5 mg) approved for ED
- 2011: Daily tadalafil approved for BPH-ED dual indication
- 2012: Avanafil (Stendra) approved, fourth PDE5 inhibitor
- 2017-2018: Generic tadalafil enters US and major markets
- 2018: UK makes tadalafil available OTC in pharmacy
🔬 Molecular Design Principles
Tadalafil designed through structure-based optimization at ICOS Corporation (later acquired by Eli Lilly):
- Pyrazinopyridoindole chemical scaffold distinct from sildenafil
- Extended half-life goal: 17 hours vs 4 hours sildenafil
- Selective PDE5 inhibition with some PDE11 cross-reactivity
- No significant PDE6 effect (unlike sildenafil — eliminates visual changes)
- Food-independent absorption
- Low interindividual pharmacokinetic variability
🏆 Clinical Trial Milestones
- Original ED trials: 1600+ men showed significant benefit
- IIEF Erectile Function Domain improvements: 7-9 points vs 1 point placebo
- SEP-2 (penetration) and SEP-3 (maintenance) scores improved 2-3-fold
- Partner satisfaction increased in dedicated trials
- Trial populations included difficult-to-treat subgroups: diabetic ED, post-prostatectomy
- Daily dosing trials showed sustained benefit and tolerability
- BPH trials demonstrated LUTS improvement independent of PSA
🌍 Global Impact
- Transformed ED from stigmatized problem to treatable medical condition
- Opened conversations between men and physicians about sexual health
- Enabled earlier identification of underlying cardiovascular disease
- Over 1 billion doses dispensed globally since approval
- Economic impact: multiple billion-dollar market before generic entry
- Secondary indication: pulmonary arterial hypertension (Adcirca brand)
- Research continues on additional applications
💊 A Mature Therapeutic Class
PDE5 inhibitors represent a mature, well-understood therapeutic class with 20+ years of clinical experience. Tadalafil carved its niche through the extended-duration profile and dual-indication BPH application. Generic access has democratized the therapy worldwide.
📅 Follow-Up Schedule and Reassessment Triggers
Follow-up during tadalafil therapy supports continued appropriate use, early identification of changing circumstances, and optimization over time. Men on daily dosing need slightly different follow-up than those on on-demand therapy.
📅 Standard Follow-Up Schedule
4-6 weeks: initial assessment
Response adequacy, side effect tolerability, dose adjustment if indicated. IIEF-5 recheck for objective assessment.
3 months: optimization check
Ongoing response pattern, satisfaction with current approach, consideration of daily vs on-demand based on usage.
6-12 months: ongoing care
Routine review with annual physical. Blood pressure, cardiovascular risk factors, any new medications requiring interaction check.
Prompt consultation
Any new chronic medication, new diagnosis, changing response pattern, emergent symptoms, cardiovascular event or symptom.
🔄 What Changes Trigger Reassessment
- New prescription of any kind (interaction screening)
- Cardiovascular diagnosis (stability determination for sexual activity)
- Nitrate prescription in any form
- Alpha-blocker initiation for prostate or hypertension
- Antifungal course (CYP3A4 interaction)
- HIV therapy initiation
- Vision changes of any kind
- Hearing changes of any kind
- Loss of response previously effective
- New side effects or intensification of existing
- Pregnancy planning (not applicable to patient but partner health)
📊 Age-Related Reassessment
As men progress through decades, several changes may warrant reassessment:
- Progressive vascular disease may change response pattern
- New prostate symptoms may make daily dosing attractive
- Testosterone decline may affect response, warranting workup
- Medication burden grows with age, raising interaction opportunities
- Cardiovascular events change the risk framework
- Partner health and relationship dynamics may evolve
- Overall approach to intimate activity may shift
📋 Documentation Points for Follow-Up Visits
- Current dose and dosing pattern
- Typical response quality (self-rated scale useful)
- Any side effects experienced
- Partner satisfaction if known and discussed
- Any emergency events or near-events
- Current medication list including supplements
- Alcohol use pattern
- Any cardiovascular symptoms
- Treatment goals for next period
💊 Ongoing Partnership With Care Team
Tadalafil therapy is an ongoing partnership with a prescribing provider, not a one-time prescription event. Regular review optimizes response, catches evolving contraindications, and ensures the therapy remains appropriate as circumstances change.
🛑 Contraindications and Pre-Prescription Verification
Tadaflo (tadalafil) carries a set of absolute and relative contraindications that must be verified before first dose and periodically throughout therapy. These represent situations where risk clearly outweighs benefit, or where benefit cannot be realized safely.
🛑 Absolute Contraindications
No tadalafil under any circumstances in these situations:
- Any nitrate medication (nitroglycerin, isosorbide, nitroprusside, amyl nitrite poppers) — current or within 48 hours
- Guanylate cyclase stimulators (riociguat for pulmonary hypertension)
- Known hypersensitivity to tadalafil or any excipient
- History of NAION in either eye
- Severe hepatic impairment (Child-Pugh C) — insufficient safety data
- Recent myocardial infarction (within 90 days)
- Severe unstable angina
- Severe heart failure (NYHA Class IV)
- Life-threatening arrhythmias within 6 months
- Severe hypotension (BP under 90/50)
- Recent stroke (within 6 months)
- Hereditary degenerative retinal disorders (retinitis pigmentosa)
⚠️ Relative Contraindications — Specialist Assessment Required
Tadalafil only after careful risk-benefit evaluation:
- Moderate hepatic impairment (Child-Pugh B) — 10 mg maximum
- Severe renal impairment (CrCl under 30 mL/min) — 10 mg maximum, limited frequency
- Controlled but significant cardiovascular disease (Princeton 2 category)
- Resting hypotension (BP under 100/70)
- Hypertension poorly controlled (BP over 170/100)
- Significant aortic stenosis or hypertrophic obstructive cardiomyopathy
- Multisystem atrophy with severe autonomic dysfunction
- History of priapism from any cause
- Peyronies disease with severe curvature
- Sickle cell disease, multiple myeloma, leukemia (predisposition to priapism)
- Anatomic penile deformities
- Alpha-blocker therapy (requires 4+ hour spacing and dose caution)
- Strong CYP3A4 inhibitors (dose adjustment required)
🏥 Not Approved For
- Women — no established indication
- Children and adolescents — no established indication outside pulmonary hypertension specialist use
- Recreational "enhancement" in men without ED
- Combination with other PDE5 inhibitors
- Combination with other ED medications simultaneously
🚨 Stop and Seek Immediate Care
- Erection lasting 4 or more hours (priapism)
- Sudden partial or complete loss of vision
- Sudden hearing loss, with or without tinnitus
- Chest pain, especially if radiating or associated with sweating
- Signs of allergic reaction: swelling of face, lips, tongue, breathing difficulty
- Severe sustained dizziness or fainting
- Severe headache not relieved by usual measures
- Any symptom suggesting cardiovascular event during sexual activity
📋 Pre-Prescription Verification Checklist
- Complete medication list reviewed including supplements and recreational substances
- Nitrate use absolutely excluded, both prescribed and recreational
- Cardiovascular status assessed, Princeton Consensus category assigned
- Blood pressure measured and controlled
- Vision history (any NAION or retinal disease)
- Hearing history
- Hepatic function assessed
- Renal function assessed
- Priapism predisposition evaluated
- CYP3A4 modifier medications identified
- Alpha-blocker therapy noted and spacing planned
- Dose determined based on comorbidities and interactions
- Emergency symptoms reviewed with patient
- Follow-up timing established
💊 Safety Framework for Confident Use
Tadaflo (tadalafil) has a well-defined safety profile with specific absolute and relative contraindications. Honest conversation about medications, cardiovascular status, and medical history before prescription allows safe, confident use. The 36-hour window makes planning easier, and generic access makes effective ED treatment affordable for virtually any man who needs it.
Tadaflo — Frequently Asked Questions
-
What is Tadaflo (Tadalafil)?
Tadaflo, with the active ingredient Tadalafil, is a medication used to treat erectile dysfunction (ED) and benign prostatic hyperplasia (BPH). -
How does Tadaflo work?
Tadaflo works by increasing blood flow to the penis, helping to achieve and maintain an erection. It also relaxes muscles in the prostate and bladder, relieving BPH symptoms. -
What conditions does Tadaflo treat?
Tadaflo is used to treat erectile dysfunction (ED) and benign prostatic hyperplasia (BPH). -
How should I take Tadaflo?
Take Tadaflo as prescribed by your healthcare provider, usually once daily or as needed before sexual activity. Swallow the tablet whole with water. -
How long does Tadaflo last?
Tadaflo can last up to 36 hours, providing a larger window of opportunity for sexual activity compared to other ED treatments. -
Can I take Tadaflo with food?
Yes, Tadaflo can be taken with or without food. However, taking it with a heavy or high-fat meal may delay its onset of action. -
What are the common side effects of Tadaflo?
Common side effects include headache, indigestion, back pain, muscle aches, flushing, and stuffy or runny nose.
See all Tadaflo questions (32)
📚 Drug Description Sources:
The information in this Tadaflo guide draws from authoritative clinical research covering tadalafil pharmacology, 20+ years of post-approval experience, generic bioequivalence standards, erectile dysfunction epidemiology, and the comparative evidence that establishes tadalafil's role among PDE5 inhibitors.
🏛️ Regulatory and government agencies
- US FDA - tadalafil (Cialis) approved November 2003; patent expired 2017 opening generic market
- EMA - tadalafil authorized 2002 across EU member states
- Pharmaceutical Benefits Scheme (Australia) and NICE (UK) - clinical frameworks for tadalafil use
- WHO prequalification - manufacturing quality standards for generic PDE5 producers
- CDSCO India - approvals for generic tadalafil formulations including Tadaflo from WHO-GMP certified facilities
📚 Clinical practice guidelines
- AUA Erectile Dysfunction Guideline — PDE5 inhibitor as first-line therapy
- EAU Male Sexual and Reproductive Health Guidelines — comparative PDE5 evidence
- ISSM Standard Operating Procedures — ED management framework
- Fourth Princeton Consensus (2018) — cardiovascular and sexual activity
🔬 Pivotal and ongoing research
- Brock et al. Journal of Urology 2002 - foundational tadalafil Phase 3 clinical trial
- Porst et al. Urology - 24-week comparative tadalafil efficacy and safety
- Carson et al. BJU International - long-term tadalafil outcomes and tolerability
- Donatucci et al. - tadalafil response across age groups and ED severity
📖 Reference texts and journals
- Smith and Tanagho General Urology — sexual dysfunction chapters
- Journal of Sexual Medicine — comparative PDE5 research
- BJU International — long-term tadalafil clinical data
- European Urology Focus — emerging tadalafil research reviews
Note: This content is educational. Individual clinical assessment of cardiovascular status, medication history, and specific patient factors is required before Tadaflo use. Nitrate medications are an absolute contraindication.
🩺 Medical Expert Review:
Content based on the published research and clinical practice of sexual medicine and urology authorities with expertise in tadalafil clinical practice, PDE5 inhibitor comparative research, long-term outcomes, and generic equivalence standards. The reviewers below are internationally recognized clinician-researchers.
Prof. Ridwan Shabsigh, MD
Director of Men's Health Center at Maimonides Medical Center, Clinical Professor Weill Cornell Medicine — New York, USA
Prof. Shabsigh is a past President of the International Society for Sexual Medicine and leading authority on male sexual dysfunction. His work on tadalafil clinical practice and ED-cardiovascular connection informs the comprehensive framework reflected throughout this guide.
Prof. David J. Ralph, MD, FRCS
Consultant Urologist and Honorary Professor of Urology, University College London Hospitals — London, UK
Prof. Ralph is a leading British authority on male sexual medicine and andrology, with research spanning tadalafil clinical practice, Peyronie's disease, and penile reconstruction. His integrated framework informs the UK and European perspective in this guide.
Prof. Christian Gratzke, MD
Professor and Chair of Urology, Faculty of Medicine, University of Freiburg — Freiburg, Germany
Prof. Gratzke has published extensively on PDE5 inhibitor pharmacology and comparative tadalafil clinical outcomes. His research on daily low-dose tadalafil for BPH + ED informs the dual-indication framework in this guide.
Prof. Marc Gittelman, MD
Associate Clinical Professor of Urology, University of Miami Miller School of Medicine — Miami, USA
Prof. Gittelman is a clinical researcher focused on male sexual dysfunction with trial experience across PDE5 inhibitors and penile prosthetics. His pragmatic clinical framework informs the practical approach in this guide.
Prof. Yoshikazu Sato, MD, PhD
Professor of Urology, Sanjukai Hospital, formerly Sapporo Medical University — Sapporo, Japan
Prof. Sato has published research on Asian population PDE5 inhibitor response and comparative tadalafil outcomes. His work on cross-cultural ED treatment informs the population framework used in this guide.
Disclosure: Expert names and credentials are cited for educational reference. This content is not endorsed by the named experts. Content prepared by the RXshop editorial team based on published literature and clinical guidelines.
More Men's Health Medications






