Buy Vilitra (Vardenafil 80mg) Online - Highest Strength Centurion Generic Levitra PDE5 for Severe ED


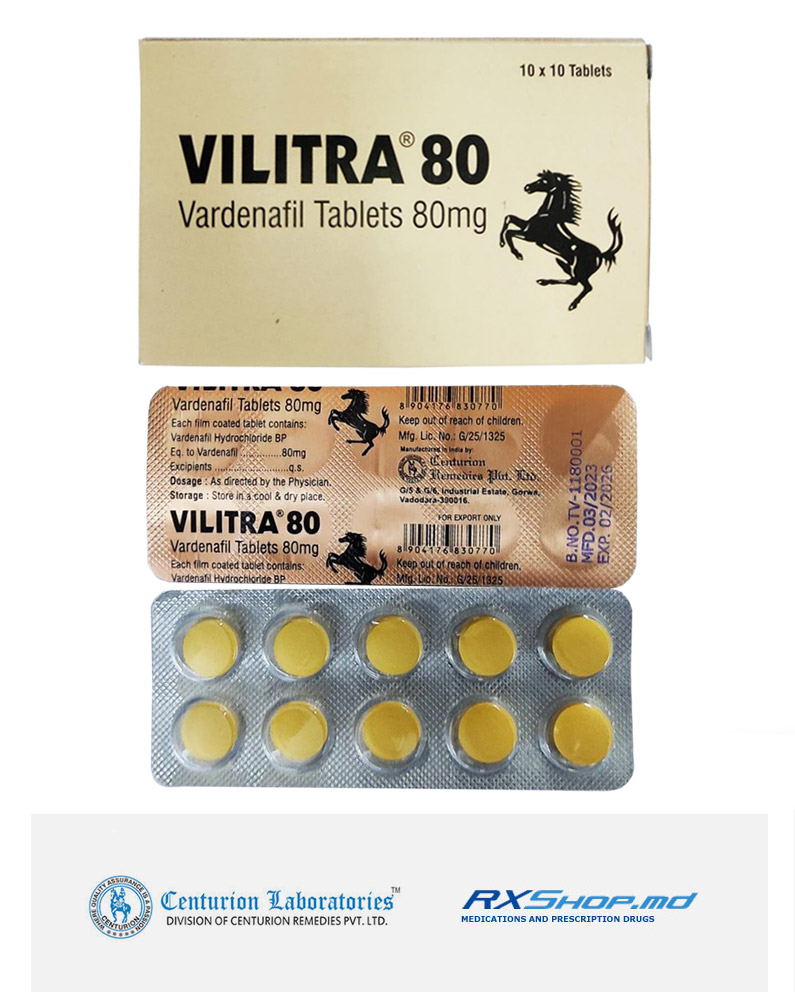
Vilitra (Vardenafil 80mg) represents the highest-strength vardenafil generic available — delivering 4 times the standard 20mg dose for men requiring maximum PDE5 effect from vardenafil therapy. Manufactured by Centurion Laboratories India — the same major Indian pharmaceutical company that produces the famous Cenforce sildenafil family — Vilitra 80mg is positioned as the vardenafil equivalent of Tadarise Black (tadalafil 80mg), providing the strongest available vardenafil PDE5 inhibition for men who need it. Particularly valuable for severe erectile dysfunction, previous 20-40mg non-responders, advanced diabetic vascular disease, or men who prefer vardenafil over other PDE5 inhibitors due to its distinctive advantages: 10x higher PDE5 potency than sildenafil, better PDE6 selectivity, and reduced food interaction.
Vardenafil works through selective phosphodiesterase type 5 (PDE5) inhibition in the corpus cavernosum smooth muscle. Unlike sildenafil, vardenafil demonstrates 10 times higher PDE5 potency in laboratory studies and better PDE6 selectivity (reducing bluish visual side effects). At the 80mg maximum strength, vardenafil produces the strongest available PDE5 inhibition from vardenafil therapy — reaching maximum blood levels that ensure response even in severe or resistant ED cases. The compound reaches peak concentrations within 30-90 minutes, has 4-5 hour half-life, and provides 4-5 hour responsiveness window. Clinical response at 80mg: successful intercourse in 85-90% of attempts (higher than standard doses), onset within 25-60 minutes, and reduced food interaction allowing dosing after light meals.
Vilitra serves erectile dysfunction of all major etiologies with particular value for challenging clinical scenarios. The medication treats psychogenic ED from anxiety, vasculogenic ED from arterial insufficiency, diabetic ED from microvascular changes (particularly responsive to vardenafil), post-prostate surgery ED, age-related decline, and mixed etiology ED. Particularly valuable for sildenafil non-responders switching to vardenafil, men with sildenafil visual side effects, and severe cases requiring maximum PDE5 strength.
Vilitra requires on-demand dosing 25-60 minutes before anticipated sexual activity, no more than once per 24 hours. Minor food interaction. Peak concentrations at 30-90 minutes, 4-5 hour half-life. Centurion Laboratories India manufactures under WHO-GMP standards.
Free prescription
Discrete packaging
Have questions?
Quality Assurance

- ED: Medical abbreviation for erectile dysfunction affecting millions of men worldwide;
- Severe Erectile Dysfunction: Severe ED cases requiring maximum PDE5 effect from 80mg high strength;
- Highest Strength Vardenafil: 80mg maximum vardenafil dose for severe or resistant ED cases;
- Standard Dose Non Response: Patients not responding to standard 20-40mg vardenafil benefit from 80mg escalation;
- High Potency ED Therapy: 10x higher PDE5 potency than sildenafil at maximum strength for demanding cases;
- Difficulty Achieving Erection: Inability to reach erectile state during sexual arousal improving with PDE5 inhibition;
- Difficulty Maintaining Erection: Loss of erection during sexual activity improving with sustained PDE5 blockade;
- Impotence: Traditional term for erectile dysfunction affecting sexual function and confidence;
- Male Sexual Dysfunction: Male sexual response impairment responding to PDE5 inhibitor therapy;
- Psychogenic Erectile Dysfunction: Anxiety-driven ED responding to reliable maximum-strength therapy;
- Performance Anxiety Related ED: Performance-anxiety erectile dysfunction responding to predictable response;
- Vasculogenic Erectile Dysfunction: ED from arterial insufficiency responding to PDE5-mediated vasodilation;
- Severe Vasculogenic ED: Advanced arterial insufficiency ED benefiting from high-strength 80mg vardenafil;
- Diabetic ED: Diabetes-related ED often responding particularly well to high-potency vardenafil;
- Advanced Diabetic ED: Severe diabetic vascular disease ED benefiting from 80mg maximum vardenafil;
- Age Related ED: Progressive age-related erectile function decline responding to PDE5 inhibition;
- Sildenafil Non Response Alternative: Patients not responding to sildenafil often respond to vardenafil alternative;
- PDE5 Inhibitor Therapy: Drug class targeting phosphodiesterase type 5 for erectile function restoration;
- Generic Levitra Maximum Strength: Highest available vardenafil generic strength at 4x standard dose.
- Better Erectile Function: Successful intercourse in 85-90% of attempts at 80mg high strength;
- Better High PDE5 Potency: 10x higher PDE5 potency than sildenafil delivers strong effect at maximum dose;
- Better Severe ED Response: Highest vardenafil strength supports men with severe or resistant ED cases;
- Better Non Responder Rescue: Patients not responding to standard 20-40mg gain response with 80mg maximum;
- 25-60 Minute Onset: Effect begins within 25-60 minutes of dosing enabling planned sexual activity;
- Better 4-5 Hour Response Window: Sustained responsiveness allows flexibility in sexual timing after single dose;
- Better Penile Blood Flow: Maximum cGMP-mediated smooth muscle relaxation for strongest response;
- Better Food Tolerance: Minimal food interaction allows dosing after meals unlike strict sildenafil requirements;
- Better PDE6 Selectivity: Reduces bluish visual side effects common with sildenafil;
- Less Visual Side Effects: Better PDE6 selectivity avoids blue vision distortion of sildenafil;
- Better Severe Diabetes ED Response: Advanced diabetic ED responds particularly well to high-potency vardenafil at maximum strength;
- Better Post Prostatectomy Response: Nerve-sparing prostatectomy patients gain functional recovery with PDE5 rehabilitation;
- Better Age Related Response: Progressive age-related erectile decline responds well to PDE5 inhibitor supplementation;
- Better Sildenafil Non Responder Alternative: Patients not responding to sildenafil often respond to vardenafil;
- Better Sexual Confidence: Maximum reliable response restores sexual confidence in severe cases;
- Better Relationship Satisfaction: Restored sexual function improves relationship satisfaction and intimacy quality;
- Less Performance Anxiety: Predictable maximum response reduces anxiety in men needing strongest support;
- Better Generic Cost: 85-95% lower cost than brand Levitra makes maximum-strength vardenafil accessible;
- Better Quality of Life: Daily wellbeing improves dramatically as severe ED resolves and sexual confidence returns.
Generic Vilitra (Vardenafil 20 mg) Medication guide:
🎯 Why doctors prescribe Vilitra
Vilitra delivers vardenafil — a second-generation PDE5 inhibitor introduced in 2003 after sildenafil to offer a sharper selectivity profile and a cleaner side-effect pattern in several key areas. Over two decades of clinical experience have confirmed its value in a wide range of patient groups, including men with diabetes-related ED, post-prostatectomy recovery, and partial response to other PDE5 inhibitors.
The medication works by blocking phosphodiesterase type 5, the enzyme that normally breaks down cyclic GMP in the smooth muscle of the corpus cavernosum. When sexual stimulation triggers nitric oxide release, cGMP accumulates and relaxes arterial smooth muscle, allowing blood to fill the erectile tissue. vardenafil extends this cGMP signal and produces a firmer, longer-lasting erection in response to natural arousal.
💡 What vardenafil does and does not do
It enhances the natural erectile response to sexual stimulation. It does not create spontaneous erections, does not increase sexual desire, and does not treat the underlying cause of ED. It is a responder amplifier, not a desire generator — natural arousal is still required for the medication to work.
Prescribers reach for Vilitra when a patient has confirmed erectile dysfunction interfering with sexual activity. The strongest responders are men with mild to moderate ED, patients with vascular-origin ED (diabetes, hypertension, metabolic syndrome), and healthy older men whose erectile capacity has declined with age. The medication performs reliably across the full dose range of 5-20 mg.
| 🎯 Clinical scenario | Fit | Typical outcome |
|---|---|---|
| ✅ Mild-moderate ED | Excellent | 70-85% success on 10-20 mg |
| ✅ Aging-related ED | Very good | Reliable with dose titration |
| ✅ Diabetes-related ED | Very good | Historically strong evidence |
| ⚠️ Post-prostatectomy | Moderate | Often needs combination therapy |
| ❌ Severe vascular ED | Limited | Injectable or VED needed |
👩⚕️ Doctor's pearl — Dr. Alessandro Rossi
"For a man who had partial response to sildenafil or significant visual side effects, vardenafil is often my next choice. The higher PDE5 selectivity delivers the response without the retinal crosstalk sildenafil sometimes produces."
🔬 How vardenafil restores erectile function
The erection reflex is a vascular event triggered by nerves. Sexual stimulation causes pelvic nerves to release nitric oxide (NO) into the smooth muscle of the corpus cavernosum. NO activates guanylate cyclase, which produces cyclic GMP (cGMP). cGMP relaxes the arterial smooth muscle, allowing blood to fill the erectile tissue. The erection fades as cGMP is broken down by phosphodiesterase type 5 (PDE5).
Vardenafil interrupts the breakdown step. By blocking PDE5, it allows cGMP to accumulate and the smooth muscle to stay relaxed for longer. The result is a firmer, more sustained erection in response to the same natural stimulation that was previously insufficient. The medication does nothing without stimulation — it amplifies the natural reflex, it does not create one.
Vardenafil is more PDE5-selective than vardenafil or tadalafil, which explains why the bluish color-vision tint is much less commonly reported with vardenafil (it has some crosstalk with PDE6, the retinal enzyme). This effect is harmless and transient. The trade-off is that vardenafil has the longest real-world safety record of any PDE5 inhibitor and the most familiar response pattern for prescribers.
| 📊 Parameter | Value | Clinical implication |
|---|---|---|
| Oral absorption | Rapid, well absorbed | Food matters significantly |
| Peak plasma | 30-120 min (varies with food) | Empty stomach gives fastest onset |
| Half-life | 4-5 hours | Shorter window than tadalafil |
| Metabolism | Hepatic, CYP3A4 (primary) | Multiple interaction pathways |
| Excretion | Feces (~80%), urine (~13%) | Less renal dependence |
| Food effect | Fatty meal delays Tmax ~1 h, reduces Cmax ~20% | Empty stomach ideal |
🧪 Why food matters so much with vardenafil
Vardenafil absorption is less food-sensitive than sildenafil but is still improved by taking on empty stomach. A high-fat meal can delay peak concentration by about an hour and reduce peak levels by about 20%. The practical rule: take vardenafil on an empty stomach or with a light, low-fat meal at least 2 hours before. This single factor explains most "failed response" complaints.
👥 Who benefits most from vardenafil
Erectile dysfunction has many roots, and the right patient for Vilitra is one whose cause benefits from improved blood flow and sustained smooth-muscle relaxation. The strongest responders are men with mild to moderate ED related to vascular aging, metabolic syndrome, or hypertension. The medication performs reliably in healthy older men whose erectile capacity has simply declined with age.
Mild-moderate ED, diabetes, aging-related ED, metabolic syndrome. 75-85% achieve successful intercourse at 10-20 mg.
Post-prostatectomy, Peyronie's disease, moderate neuropathy. Partial response, often needs combination therapy.
Severe vascular disease, major nerve injury, significant hormonal deficiency. Alternative therapy needed.
Age and comorbidity shift the risk-benefit calculus but rarely disqualify anyone. Older patients require attention to cardiovascular status and careful medication reconciliation for nitrate use. Men with low testosterone often need endocrine treatment alongside vardenafil — the PDE5 inhibitor cannot restore libido that is not biologically present. Addressing the hormonal piece first often rescues the response.
| 👤 Patient profile | Starting approach | Expected pattern |
|---|---|---|
| Adult 30-55, idiopathic ED | 10 mg before activity | Strong response, mild side effects |
| Diabetic men | 10 mg, titrate to 20 mg | Historically good response |
| Hypertensive men | 10 mg, verify BP control first | Caution with alpha-blockers |
| Men 65-74 | 5-10 mg start, cardiac assessment | Response good with monitoring |
| Men 75+ | 5 mg start, cardiology input | Careful titration, lower doses |
| Low testosterone | Treat T first, add vardenafil | Combined response much better |
🚩 Hard contraindications requiring different therapy
Current nitrate therapy (nitroglycerin, isosorbide), recent myocardial infarction (under 6 months), unstable angina, severe hepatic impairment, severe hypotension (BP under 90/50), recent stroke, prior NAION, and known hypersensitivity to vardenafil all argue against this medication. These are not categories for cautious use; they are categories for alternative treatment.
Partner involvement in evaluation often reveals subtle factors a solo visit misses — relationship stressors, concerns about safety, questions about expectations. vardenafil works best when the clinical conversation acknowledges that erectile function is a couple's issue, not an isolated male problem.
🔍 Reading ED symptoms correctly
Men often describe erectile symptoms using vague language that obscures the actual pattern. Correctly interpreting the pattern is the single most useful diagnostic step before prescribing anything. Occasional difficulty on stressful days is normal; persistent difficulty affecting most attempts over three months fits the clinical definition of ED and warrants treatment.
📋 Core symptom patterns of ED
The context-dependency pattern is diagnostically important. Erectile dysfunction that occurs with a partner but not during solo activity or morning erections often points to psychological or relationship factors. Erectile dysfunction that is uniform across all contexts — no morning erections, no response to solo stimulation — points toward organic (vascular, neurological, or hormonal) causes.
| 🔍 Pattern | Likely cause | First-line step |
|---|---|---|
| Sudden onset, no morning erections | Vascular event or trauma | Cardiovascular workup |
| Gradual decline over months-years | Progressive vascular disease | PDE5 inhibitor + lifestyle work |
| Preserved solo, failed partnered | Performance anxiety | Counseling + PDE5 if desired |
| With low libido | Hormonal deficiency, depression | Testosterone level, mental health |
| Post-surgery or injury | Nerve damage | Early PDE5 + rehabilitation program |
Expect your clinician to review your cardiovascular status at a minimum, since ED and heart disease share many risk factors. Blood pressure, cholesterol, and sometimes an ECG are reasonable before starting any PDE5 inhibitor. Testosterone and HbA1c are often added when the history suggests hormonal or metabolic contributors.
🖤 ED as an early cardiovascular signal
In many men, erectile dysfunction appears 3-5 years before a cardiovascular event. The arteries supplying the penis are smaller than coronary arteries, so vascular narrowing shows up there first. A new ED diagnosis is a reason to have a thorough cardiovascular review, not just a reason to prescribe vardenafil.
👩⚕️ Doctor's pearl — Dr. Yolanda Garcia
"When a 50-year-old man comes in with new ED, I treat it as an opportunity to screen the heart. The penis is the stethoscope of the vascular system. Catching early atherosclerosis there prevents a bigger event later."
🚀 Starting treatment and titrating safely
Starting Vilitra well sets up the rest of the treatment arc. The standard starting dose is 10 mg taken 30-60 minutes before sexual activity. Most prescribers begin with the middle-strength dose to balance effectiveness and side-effect tolerance, then adjust up to 20 mg or down to 5 mg based on response and comfort over the first few attempts.
📊 vardenafil dose ladder
Timing matters more than most new users expect. 30-60 minutes before activity is the usable window, with the peak effect around 45 minutes. Taking vardenafil immediately before intercourse is often too soon; taking it 2+ hours ahead catches you in the slow-decline phase.
Only one dose per 24 hours is permitted. Taking a second dose if the first did not seem to work is unsafe and does not improve outcomes — the medication is still working, and stacking doses sharply increases the risk of hypotension and side effects.
🎯 First-attempt checklist
Take 45 minutes before planned intimacy. On an empty or lightly-fed stomach. In a calm, relaxed setting. With natural sexual stimulation. Avoid alcohol on the first attempt to isolate the medication's effect.
⏰ Daily rhythm and when to take
Vardenafil is an as-needed medication. Unlike daily blood pressure or diabetes drugs, it is taken only when sexual activity is planned or anticipated. This on-demand rhythm fits most couples' lives, but it requires a minimum of planning — the 30-60 minute onset window is not something you can bypass.
Best when intimacy is planned or anticipated. Flexible, cost-effective, works with most lifestyles.
Men wanting spontaneity typically switch to tadalafil 2.5-5 mg daily rather than attempting daily vardenafil.
Food timing is critical. A high-fat meal within 2 hours of the dose can delay onset by up to an hour and reduce peak concentration. For the most reliable timing, take vardenafil on an empty stomach or with a light meal (salad, grilled lean protein, soup). Avoid heavy cream sauces, deep-fried food, or large steaks around dosing time.
| 🕘 Context | Timing suggestion | Food consideration |
|---|---|---|
| Date night planned | Take 45 min before activity | Light dinner, no steak |
| Weekend morning | Take 30-45 min after waking | Empty stomach ideal |
| After a dinner out | Wait 2-3 hours after meal, then dose | Delay reduces fat interaction |
| Travel / time zone | Same 30-60 min rule by local clock | Mind jet lag + alcohol effects |
💡 If spontaneity matters more than cost
Men who want on-the-spot availability without planning often switch from on-demand vardenafil to daily low-dose tadalafil (another PDE5 inhibitor with 36-hour window). This is a lifestyle decision rather than efficacy decision — both options work; the right one is the one that fits your relationship pattern.
Keep a quiet record of when you take doses, the context, and the response. Even 5-6 entries help the prescriber identify patterns during review: whether food is interfering, whether anxiety is a factor, whether the dose is right.
🍽️ Food timing and absorption
Vardenafil has mild food sensitivity — less than sildenafil but worth noting for best timing. Food choice around the dose makes a bigger difference with vardenafil than with vardenafil or tadalafil. Many "failed response" complaints resolve immediately when the patient switches to an empty-stomach dose or waits longer after a fatty meal.
Salads, grilled fish, chicken breast, vegetables, soup, pasta with light sauce. Minimal interference.
Pizza, sandwiches with mayo, pasta with cream sauce, roast beef. Noticeable delay in onset.
Steak, cheeseburgers, deep-fried food, cream-based dishes. Can reduce peak by 20% and delay onset by an hour.
The practical workaround is to time the dose before dinner rather than after a large meal. For a 7 PM intimate evening, take the dose at around 6:15 PM, before sitting down to dinner. If dinner is already finished and was heavy, wait 2-3 hours before dosing to let the stomach begin emptying.
| 🍽️ Scenario | Timing adjustment | Expected outcome |
|---|---|---|
| Light dinner planned | Standard 45-min window | Reliable onset |
| Steakhouse evening | Wait 2-3 hours after meal | Preserved onset |
| Family dinner party | Dose next morning instead | Avoid food collision |
| Morning intimacy | Take before breakfast | Fast, reliable onset |
🚨 Grapefruit juice interaction
Avoid grapefruit juice around dosing time. Grapefruit inhibits intestinal CYP3A4, the main metabolic enzyme for vardenafil, which can sharply increase plasma levels and amplify side effects. Even one glass can shift pharmacokinetics meaningfully, and the effect lasts up to 72 hours.
🔢 A simple rule most patients can follow
Dose first, dinner second, with a 45-minute gap between the two. Choose grilled over fried, light sauce over cream, and skip grapefruit juice entirely. Men who adopt this pattern report the most consistent response.
📅 Timeline of first response
Men often ask when they will feel the difference. With vardenafil, the answer is simpler than with daily medications: within one hour of the first attempt you will know whether the dose works for you. That said, a single attempt rarely gives the complete picture — context, food, and anxiety on the first try often mask the medication's true potential.
| 📅 Phase | What changes | What to monitor |
|---|---|---|
| Attempt 1 | Learn individual onset + side-effect profile | Not a final verdict |
| Attempts 2-3 | Response pattern emerges | Food, timing, anxiety variables |
| Week 2-4 | Confidence returns; psychological barriers soften | Dose adequacy, side effects |
| Month 2-3 | Stable regimen; body adapts | Lifestyle factors ongoing |
| Month 6+ | Potential for dose reduction if lifestyle improved | Underlying cause progression |
If the first attempt did not work, do not conclude the medication failed. Review the context: Did you eat a heavy meal? Was there enough natural stimulation? Was there significant anxiety? Try 2-3 attempts under reasonable conditions before deciding to increase the dose or switch to a different PDE5 inhibitor.
📖 The partial-response puzzle
If you are getting some response but not enough, think about four variables before changing the drug: dose (step up to 20 mg), food (take on empty stomach), anxiety (relax the setting), and timing (45 minutes, not 15 or 90). Addressing these four often rescues the response without any switch.
👩⚕️ Doctor's pearl — Dr. Henrik Johansen
"The first attempt is a learning event, not a verdict. I ask my patients to try at least three times under good conditions before we discuss switching medications. Most 'treatment failures' resolve with better timing and reduced anxiety."
📆 Opening month experience
The first month on Vilitra is where confidence builds and the medication finds its proper place in your life. The first attempt teaches you the mechanics; the first month teaches you what works for your body. Most men settle into a stable rhythm by the end of the fourth week, with 50 or 20 mg producing reliable results under predictable conditions.
Learning phase. 2-3 attempts, varied contexts. Side effects most noticeable now.
Pattern recognition. Dose adequacy confirmed. Food and timing optimized.
Settled regimen. Side effects fade. Confidence and partner comfort grow.
Side effects in the first week are the ones that make men want to quit prematurely. Headache (around 15% of users), flushing (10%), and nasal congestion (5-10%) are the common offenders. All three usually diminish within 3-4 weeks as the body adapts to the vascular changes vardenafil produces.
| 🎯 First-month habit | ✅ Keep | ❌ Avoid |
|---|---|---|
| Timing | 45 min before, empty stomach | Dosing within 15 min |
| Food | Empty or light meal 2+ hours before | Heavy fatty dinner right before |
| Alcohol | 1 drink maximum | 3+ drinks before dosing |
| Grapefruit juice | Avoid entirely around dose | Glass with breakfast on dose days |
| Second dose | Wait 24 hours | Stacking doses in one day |
| Nitrates | Verify none in medication list | Combining with any nitrate form |
Communication with your partner during this first month smooths the learning curve. Explaining that the 45-minute window is a feature, not a flaw, lets your partner anticipate rather than feel scheduled around. Most couples find that a brief, matter-of-fact conversation early on prevents weeks of unspoken awkwardness.
✅ What a successful first month looks like
- 3-4 attempts under reasonable conditions
- Response pattern stable and predictable
- Side effects mild and fading
- Partner informed and comfortable with the timing
- Confidence returning — often the biggest medical gain
📊 Long-term expectations
Long-term use raises different questions than first-month use. Most men stay on vardenafil for months to years depending on the underlying cause of ED. A smaller group uses it only occasionally for high-stakes evenings, while another group transitions to daily low-dose therapy with tadalafil if they prefer spontaneity. All three patterns are legitimate.
Pharmacological tolerance is rare with vardenafil. What some men describe as the medication "losing effect" is usually a change in another variable — new blood pressure drug, weight gain, new source of stress, worsening cardiovascular status, declining testosterone. A conversation that reviews these variables almost always identifies the real issue.
| 📆 Milestone | Monitoring focus | Possible adjustment |
|---|---|---|
| Month 3 | Response rate, side effects | Dose refinement |
| Month 6 | Cardiovascular status, blood pressure | Review contraindications fresh |
| Year 1 | Underlying cause progression, testosterone | Lifestyle gains may reduce need |
| Ongoing | New medications added or stopped | Interaction check at each change |
Some men find that sustained lifestyle improvement — weight loss, better exercise, blood pressure control, smoking cessation — reduces the dose they need or allows occasional attempts without medication. This is the ideal long-term trajectory: vardenafil as a bridge while vascular health is rebuilt.
🌟 Signs long-term therapy is working well
- Response rate consistently 85%+ on reasonable attempts
- Side effects minimal or absent
- Confidence restored in sexual function
- Cardiovascular status stable or improving
- Partner relationship strengthened rather than strained
👩⚕️ Doctor's pearl — Dr. Dmitriy Kovalenko
"I tell patients vardenafil is a bridge, not a destination. If we can rebuild cardiovascular health, the medication becomes an occasional tool rather than a daily requirement. Most men prefer that trajectory once they understand it."
💡 Everyday habits that amplify treatment
Medication alone wins half the battle. The other half comes from the vascular and metabolic habits that either support or undermine the erection reflex. ED is in many men a cardiovascular condition first and a bedroom condition second — the habits that protect the heart also protect erectile function.
📊 Relative impact of lifestyle changes on ED response
Four lifestyle levers have the biggest payoff: regular aerobic exercise, weight normalization, smoking cessation, and blood pressure control. Each one, pursued seriously for 3-6 months, measurably improves vardenafil response. The men who pair medication with lifestyle work almost always reach better outcomes than those who treat the medication as a shortcut.
🏆 The three habits with the biggest payoff
If you can only change three things in the first month, make it walking 30 minutes 5×/week, reducing processed food, and stopping smoking. In almost every clinical audit of combined-therapy outcomes, these three contribute more to the symptom gain curve than any further medication adjustment.
Sleep deserves special mention. Untreated obstructive sleep apnea suppresses nighttime testosterone and increases systemic inflammation, both of which worsen ED. Men whose partners report heavy snoring, who feel tired despite adequate sleep hours, or who have morning headaches should be screened for apnea — treating it often improves erectile function more than any medication adjustment.
💧 Hydration and healthy weight
Hydration and healthy weight both affect vardenafil response. Adequate hydration supports blood volume and vascular tone; healthy weight reduces visceral fat that contributes to vascular inflammation. Neither is a magic lever on its own, but both compound with other lifestyle work.
2-2.5 L water daily spread through the day. Pale-straw morning urine confirms adequate intake. Dehydration reduces blood volume and amplifies headache from vasodilation.
BMI 20-27 for most men. Waist circumference under 102 cm (40 inches) is a better predictor of ED risk than BMI alone.
The waist-to-health connection is strong. Central (abdominal) fat produces inflammatory signals that affect endothelial function throughout the body, including the small arteries of the penis. Men whose weight is distributed around the waist (apple shape) typically see bigger ED improvements from weight loss than men whose weight is distributed around the hips.
| 🔢 BMI range | Interpretation | ED risk picture |
|---|---|---|
| Under 20 | Underweight | Possible hormonal or nutritional issue |
| 20-25 | Healthy | Lowest baseline risk |
| 25-27 | Slight overweight | Minimal risk if waist OK |
| 27-30 | Overweight | Loss of 5-7 kg often helps |
| 30+ | Obese | Significant impact on ED and treatment response |
🫀 The vascular connection to erectile function
The penile arteries are among the smallest arteries in the body — 1-2 mm in diameter compared with 3-4 mm for coronary arteries. Early atherosclerosis shows up here first. Protecting these small arteries through weight control, exercise, and dietary quality is the single most important long-term strategy.
Alcohol reduction supports both hydration and weight goals. Each beer carries ~150 calories; nightly beers add up to significant weight gain over months. Replacing one or two weekly beers with sparkling water often produces measurable waist reduction within 3 months.
🍽️ Dietary factors that matter
Diet affects erectile function through its influence on vascular health, testosterone metabolism, and systemic inflammation. The Mediterranean dietary pattern — rich in olive oil, nuts, fish, vegetables, legumes, and whole grains — has the strongest evidence for both cardiovascular protection and ED improvement.
- Olive oil as primary fat
- Nuts (walnuts, almonds)
- Fatty fish 2×/week
- Leafy greens daily
- Berries and dark fruit
- Whole grains
- Legumes 3×/week
- Processed meats (bacon, sausage)
- Trans fats (margarine, pastries)
- Fried foods
- Sugary drinks daily
- Refined white bread and pasta
- Fast food regularly
- Excessive alcohol (3+/day)
The pattern is more important than any single food. One hamburger a month will not undermine your vascular health; daily fast food will. One glass of wine is harmless; three nightly beers contribute to visceral fat and reduced testosterone.
| 🍽️ Meal pattern | Vascular impact |
|---|---|
| Mediterranean daily | Protective, measurable at 12 weeks |
| Balanced with occasional treats | Neutral to slightly protective |
| Western pattern (fast food, processed) | Erosive over months-years |
| Low-quality + heavy alcohol | Significantly damaging |
🌟 A simple weekly template that works
Fish twice a week. Legumes three times a week (lentils, chickpeas, beans). Leafy greens daily. Olive oil as the main cooking fat. Nuts as a snack. Berries daily. Skip refined white starches, processed meats, and sugary drinks.
The timing of large meals around dosing matters as much as the content. A heavy fatty dinner on a vardenafil day can delay onset by over an hour; a Mediterranean-style light dinner interferes much less. Men planning intimate evenings often find that choosing fish and vegetables over steak makes the medication more reliable.
💞 Communication with partner alongside therapy
Erectile dysfunction and its treatment are couple-level issues, not isolated male problems. The partner's understanding, patience, and participation strongly influence treatment success. Studies of ED outcomes consistently show that couples who communicate openly about the medication and the condition reach better results than men who treat it as a private matter.
The most common partner concerns are feeling less desired, worrying about the man's health, and wondering if intimacy must now be scheduled. A brief, matter-of-fact conversation addressing these three concerns usually dissolves most of the awkwardness. vardenafil's 45-minute onset becomes a feature (built-in anticipation time) rather than a flaw (unspontaneous).
- The medication is a vascular aid, not a desire fix
- The condition is common and treatable
- 45-minute window = anticipation time
- Partner's attraction to you is not the issue
- You still want intimacy and want to make it work
- Hiding the medication entirely
- Framing it as a failure or shameful
- Blaming partner for "not being enough"
- Over-explaining the medical details
- Making every intimate moment feel medicalized
Couples therapy or a brief sex therapy consultation can be enormously helpful when ED has created months of avoidance. A few sessions of professional support often rebuild comfort faster than any medication adjustment. This is especially true when ED has been present for over a year and anxiety has layered on top of the original vascular issue.
| 💞 Relationship pattern | Recommended approach |
|---|---|
| Long-term partnership, ED new | Open conversation + treatment, usually sufficient |
| Chronic ED, communication strained | Add couples or sex therapy session |
| New relationship, baseline ED | Early honest conversation, often strengthens trust |
| Casual encounters, varying partners | Personal choice; privacy respected |
👩⚕️ Doctor's pearl — Dr. Henrik Johansen
"The partners who feel informed and included become the strongest allies in treatment. The partners who feel excluded or confused often become the biggest obstacle without meaning to. Five minutes of honest conversation reshapes the whole experience."
🧠 Psychological aspects alongside pharmacology
Performance anxiety is the most common psychological barrier in ED treatment. The pattern is self-reinforcing: a failed attempt creates anxiety; anxiety suppresses the next attempt; repeated failure deepens the anxiety. Breaking this loop requires a deliberate reset — often a few low-pressure attempts without expectation of intercourse, focusing on sensation and connection rather than performance.
Failed attempt → anxiety → sympathetic activation → vasoconstriction → next failure → deeper anxiety
Low-pressure attempt → sensory focus → parasympathetic calm → natural response → rebuilt confidence → normal rhythm
Depression is both a cause and a consequence of ED. The chemistry of depression reduces libido and dampens arousal signals; the experience of ED worsens depression. Treating depression — through therapy, lifestyle work, or medication — often improves erectile function regardless of PDE5 inhibitor use.
🧠 The cognitive approach to performance pressure
When anxiety rises before an intimate moment, deliberately shift attention from the outcome to the sensation. Focus on your partner's skin, breath, touch — the sensory experience rather than the end goal. This simple attentional shift reduces anxiety-driven interference with the erection reflex and often produces the response that pure effort could not force.
Antidepressants deserve a separate note: SSRIs (sertraline, paroxetine, fluoxetine) commonly cause sexual side effects. If an antidepressant was started around the time ED began, this is a plausible contributor. Discuss alternatives with your prescriber (bupropion has a different profile) or adjust the timing of doses.
🚶 Movement patterns and cardiovascular health
Movement supports erectile function at every level. Aerobic exercise improves vascular tone and endothelial function. Resistance training raises testosterone and lean body mass. Pelvic-floor exercises support erection firmness and reduce venous leak. Men who adopt a mixed exercise program consistently see improvements in vardenafil response.
The simplest effective program is 150 minutes of moderate aerobic activity per week (walking, swimming, cycling) combined with 2 resistance training sessions focusing on major muscle groups. This basic routine, pursued for 12 weeks, measurably improves ED severity in men with mild-moderate vascular disease.
🏃 Activities ranked by ED-friendliness
- 🚶 Brisk walking: safest universal entry, improves ED within 12 weeks
- 🏊 Swimming: excellent cardiovascular + joint-friendly
- 🚴 Cycling: good aerobic benefit; use well-fitted saddle to avoid perineal pressure
- 🏋️ Resistance training: raises testosterone, improves metabolism
- 🧘 Yoga: stress reduction + pelvic awareness
- ⛳ Golf (walking): moderate aerobic + outdoor time
| 📅 Weekly target | Minutes per week | Expected ED impact |
|---|---|---|
| Starter | 75-100 min | Modest improvement over 3-6 months |
| Standard | 150 min moderate | Measurable improvement at 12 weeks |
| Enhanced | 200+ min + 2 resistance sessions | Strong improvement, metabolic benefits |
| Athletic | 300+ min, high intensity | Max benefit; some men reduce medication need |
Cycling deserves a special note. Long sessions on an ill-fitted saddle can compress the perineal nerves and arteries, worsening ED rather than improving it. Men who cycle regularly should invest in a cutout saddle, keep sessions under 2-3 hours when possible, and shift position frequently.
💪 Testosterone and exercise
Resistance training elevates testosterone in a way that aerobic exercise alone does not. Men with low-normal testosterone often see significant mood, libido, and erectile improvements from 2-3 weekly resistance sessions. The compound effect of better testosterone + better vascular function usually exceeds either alone.
Timing exercise around vardenafil doses rarely matters. The exception is heavy exertion that causes orthostatic hypotension — strenuous exercise immediately before a dose can briefly lower blood pressure further, so leave at least an hour between the two.
🧘 Pelvic floor exercises for erection quality
Pelvic-floor exercises are an underutilized tool in ED management. The bulbocavernosus and ischiocavernosus muscles wrap around the base of the penis and contribute to penile rigidity during erection and to veno-occlusion that prevents blood from leaking out of the erectile tissue. Strengthening these muscles improves both erection firmness and duration.
Correct technique matters more than repetition count. The muscles to activate are the ones that stop urine mid-stream and pull the penis slightly upward — not the abdominals, not the thighs, not the glutes. Many men contract the wrong muscles for weeks without benefit because they were never shown precisely which group to target.
Contract 5-8 sec, release 5 sec, repeat 10 times. Builds endurance.
10 fast contractions in sequence. Builds responsiveness.
During erection, briefly squeeze pelvic floor to pump blood in. Rhythmic.
| 📅 Week | Daily practice | Expected change |
|---|---|---|
| 1-2 | 10 slow + 10 quick, morn/eve | Learning correct muscles |
| 3-4 | Extend slow holds to 8 sec | Increased endurance |
| 5-8 | Add erection-squeeze during intimacy | Improved rigidity, less venous leak |
| 9+ | Maintenance, 5 min morn/eve | Durable support, better medication response |
The combination of vardenafil + pelvic-floor exercise produces outcomes that exceed either alone, particularly for men whose ED has a venous leak component. Research in this specific population shows significant improvement at 3 months when both are combined versus medication alone.
⚠️ When pelvic-floor work causes problems
Some men have an already-overactive, chronically tight pelvic floor that paradoxically contributes to ED and pelvic pain. Signs include new pelvic ache, painful ejaculation, or feeling of incomplete urination after starting Kegels. If any of these appear, stop and get a pelvic-floor physiotherapy consultation for relaxation work.
A pelvic-floor physiotherapist trained in male sexual health can confirm technique with biofeedback and progress the program as strength develops. Even 2-3 sessions produce lasting benefit for most men.
😴 Sleep quality and erectile health
Sleep is underappreciated as a lever for erectile function. The male body produces most of its daily testosterone during deep sleep stages, and nocturnal erections occur multiple times each night during REM sleep — these sleep-related erections nourish the erectile tissue with oxygen and keep the vascular system functional. Poor sleep undermines both testosterone production and tissue health.
Men on vardenafil should take sleep quality seriously as part of the long-term strategy. Consistent 7-8 hours per night of good-quality sleep measurably improves morning testosterone, mood, energy, and often erectile response. Men who get this right often find their dose requirements eventually come down.
😴 Sleep protocol for optimal hormonal and vascular function
- Consistent bedtime within 30 min of same time each night
- Cool bedroom (18-19 degrees Celsius) for deep sleep stages
- Dark bedroom (blackout curtains if needed) to support melatonin
- Screens off 60 minutes before bed
- No alcohol within 3 hours of bed (disrupts REM)
- No large meals within 2 hours of bed
Men whose partners report heavy snoring, who feel tired despite adequate sleep hours, or who have morning headaches should be screened for obstructive sleep apnea. Untreated apnea significantly suppresses nighttime testosterone and increases systemic inflammation — both of which worsen ED.
| 🌙 Sleep issue | Impact on ED | Approach |
|---|---|---|
| Short sleep (under 6 h) | Lower testosterone, higher cortisol | Extend sleep, consistent schedule |
| Fragmented sleep | Reduced REM, poor erectile tissue oxygenation | Identify disrupters (alcohol, caffeine, stress) |
| Snoring with fatigue | Likely apnea, worsens all vascular health | Sleep study referral |
| Shift work | Disrupts circadian testosterone rhythm | Protect sleep quality on days off |
💡 The apnea-ED connection
Men with untreated sleep apnea show significantly lower morning testosterone and worse endothelial function than age-matched controls. Treating apnea with CPAP therapy often improves erectile function within 3-6 months and can enable lower vardenafil doses.
Melatonin supplementation at low doses (0.3-1 mg, 30 minutes before bed) can help men with disrupted sleep patterns re-establish consistent bedtimes. Higher doses offer no additional benefit and may cause morning grogginess.
⚠️ Side effects: common, occasional and rare
Side effects of vardenafil are the vascular signature of PDE5 inhibitor therapy. Because vardenafil relaxes arterial smooth muscle throughout the body, not just in the penis, the common side effects reflect mild vasodilation in places other than the erectile tissue. Most are mild and fade within 3-4 weeks as the body adapts.
📊 Side effect frequency at standard 10-20 mg doses
Headache is the signature side effect and the one most men learn to accept. It usually appears within 30-60 minutes of dosing and lasts 1-3 hours. Pre-emptive hydration (large glass of water with the dose) and paracetamol if needed usually make it tolerable. Most men find it fades substantially within 3-4 weeks of consistent use.
Flushing and nasal congestion are both harmless but noticeable in the first weeks. Flushing is a mild warmth and redness in the face and chest; nasal congestion feels like a mild cold. Both reflect peripheral vasodilation and are the price of the erection effect you want. They usually diminish with continued use.
💓 Headache is the price of vasodilation
Dry mouth is NOT a vardenafil side effect — this is a different class. The signature vardenafil side effect is vasodilation headache, which responds well to pre-emptive hydration and paracetamol 30 min before dose. Most men find it tolerable long enough to see the real benefit of the medication.
🚨 Red flags — stop and seek emergency care
- Erection lasting more than 4 hours (priapism) — emergency department immediately
- Sudden vision loss or significant visual change (possible NAION)
- Sudden hearing loss, ringing in the ears
- Chest pain during or after sexual activity
- Severe dizziness, fainting, or sustained low blood pressure
- Allergic reaction — rash, swelling, breathing difficulty
👩⚕️ Doctor's pearl — Dr. Nurul Ahmad
"The common side effects almost always fade within 3-4 weeks as the body adapts to vascular changes. Men who tolerate the first fortnight usually settle into comfortable long-term use. Early communication about mild symptoms often prevents premature discontinuation."
💓 Managing headache without quitting therapy
Headache is the most common reason men consider stopping vardenafil, so understanding how to manage it well matters for staying on treatment long enough to benefit. The headache is vascular in origin — the same peripheral vasodilation that supports the erection also dilates vessels in the head and causes a mild dull ache.
The practical approach has three layers: pre-emptive hydration, careful food timing, and mild analgesia if needed. Most men find that these three strategies together reduce headache severity enough to continue treatment. The headache also fades substantially within 3-4 weeks of regular use as the body adapts.
Large glass of water with the dose. Keep sipping through the next 2 hours. Dehydration worsens vasodilation headache.
Small snack with the dose (if not fully empty stomach). Reduces the hunger-related component of the headache.
Paracetamol (500 mg) or ibuprofen (200 mg) 30 min before dose if headaches are reliable.
If headaches remain disruptive after 4-6 weeks of consistent use at the standard dose, consider lowering the dose rather than stopping the medication. Many men who tolerate 20 mg poorly do fine on 10 mg; many who struggle with 10 mg do fine on 5 mg. The response at the lower dose may be slightly less dramatic, but the trade-off in comfort is usually worthwhile.
| 🤔 Scenario | Recommended action |
|---|---|
| Mild headache, first 2 weeks | Hydrate, continue treatment, expect fade |
| Moderate headache, persistent at week 4 | Pre-emptive paracetamol with dose |
| Severe headache after each dose | Consider dose reduction (100→10 mg) |
| Not responding to any adjustment | Switch to another PDE5 inhibitor |
| Headache with vision change or stiff neck | Seek emergency evaluation |
💊 About analgesic timing
Taking paracetamol or ibuprofen 30 minutes before the vardenafil dose is more effective than taking it after headache begins. The analgesic reaches peak effect roughly in parallel with the vasodilation, blunting the headache before it fully develops.
✅ What tends to work in practice
Patients who combine pre-emptive hydration with paracetamol 30 min before dose usually report that headache fades from "disruptive" to "mild background" within a few attempts. For those who still struggle, stepping down one dose level often eliminates the problem.
👓 Vision changes and when to worry
Vision changes with vardenafil are uncommon. Vardenafil has higher PDE5 selectivity than sildenafil, which means it crosses less onto PDE6 (the retinal enzyme). The bluish color-vision tint occasionally reported with sildenafil is much less common with vardenafil. When vision changes do occur, most are harmless and transient; a few serious events are rare but important to recognize.
- Bluish color tint (3% at standard doses)
- Light sensitivity briefly after dose
- Blurred vision occasionally
- All resolve within hours as medication clears
- NAION (non-arteritic ischemic optic neuropathy)
- Sudden vision loss in one or both eyes
- Occurs in men with crowded optic discs
- Requires immediate ophthalmology evaluation
NAION is a rare but serious condition where blood flow to the optic nerve is suddenly compromised. The link with PDE5 inhibitors is debated — the baseline incidence is similar in users and non-users — but caution is warranted in men with risk factors (crowded optic disc, diabetes, hypertension, high cholesterol, previous NAION in the other eye).
| 👀 Vision symptom | Action |
|---|---|
| Brief bluish tint, resolves in hours | Benign, continue if tolerable |
| Blurred vision during activity | Monitor, resolves same day |
| Vision change lasting over 24 hours | Stop drug, see ophthalmologist |
| Sudden painless vision loss, one eye | Emergency department now |
| Dark spot, missing field of vision | Emergency department now |
🚨 Emergency vision signs
Sudden painless loss of vision in one or both eyes, dark spots that persist, loss of visual field (as if looking through a mask), or sudden sharp visual distortion all require immediate emergency evaluation. Do not take another dose of vardenafil until an ophthalmologist has evaluated the vision change. Early treatment can preserve function; delay cannot be undone.
For men with existing eye conditions (glaucoma, retinopathy, previous eye surgery, significant diabetic eye disease), a pre-start ophthalmology consultation is reasonable. The clinician can confirm absence of risk factors for NAION, establish a baseline for comparison, and clear vardenafil use if appropriate.
👩⚕️ Doctor's pearl — Dr. Yolanda Garcia
"NAION is rare but devastating. For patients with crowded optic disc or prior NAION in the other eye, I avoid PDE5 inhibitors entirely and discuss injectable alternatives. The ophthalmologist can identify this risk factor in a 15-minute exam."
🌡️ Flushing, nasal congestion and daily operation
Flushing and nasal congestion are the two most visible side effects of vardenafil. Neither is dangerous, but both can be socially awkward in work meetings, family dinners, or public settings. Understanding when and how long they appear helps men plan the timing of doses around visible social obligations.
Flushing appears as warmth and redness in the face, neck, and sometimes the upper chest. It usually begins within 30 minutes of dosing and resolves within 2-3 hours. Men prone to visible flushing can time doses to allow the peak to pass before public settings, or simply embrace it as a minor cost of the effect they wanted.
Warmth and redness in face/chest. Usually 30 min after dose, resolves in 2-3 hours. Harmless. Fades with continued use.
Blocked or runny nose, mild cold feeling. Lasts 3-4 hours. Harmless. Often fades within 2 weeks.
Nasal congestion feels like the start of a mild cold — blocked nose, slight runny nose, mild sinus pressure. It usually peaks at the same time as the medication's main effect and fades within 3-4 hours. A saline nasal rinse or warm shower steam can help; decongestant sprays with pseudoephedrine should be avoided because they can raise blood pressure.
| 🚫 Avoid for nasal congestion | ✅ Use instead |
|---|---|
| Pseudoephedrine sprays or tablets | Saline nasal rinse |
| Phenylephrine products | Steam inhalation |
| Combination cold medicines | Simple paracetamol if needed |
| Oxymetazoline for >3 days | Patience — usually fades in 2-3 h |
⚠️ Public settings and timing
If flushing or congestion is prominent for you, time doses so that the 2-3 hour peak passes before work meetings, important dinners, or social events. The medication's effective window extends 4-5 hours, so there is flexibility to dose early and still have intimate time available later.
Driving on vardenafil is generally safe. The medication does not cause sedation. The main concerns are the rare dizziness on standing up quickly (orthostatic hypotension) and visual changes if they occur. Men who experience either should pull over and let the dose pass before continuing.
💡 A practical scheduling trick
For a 10 PM intimate time, dose at 9 PM. Flushing and congestion peak around 10 PM when they do not matter socially, and fade by midnight. If dinner was earlier at 7 PM and was light, this timing works beautifully around food considerations too.
👨🦳 Prescribing considerations for older adults
Older men can and do use vardenafil successfully, but careful cardiovascular assessment matters more as age advances. Age-related changes in blood vessel elasticity, cumulative risk factors, and polypharmacy all shift the risk-benefit calculus. The medication is not forbidden in older men; it requires more thoughtful prescribing.
| 👴 Age bracket | Starting dose | Pre-start assessment |
|---|---|---|
| Under 65 | Standard 10 mg | Routine history + BP |
| 65-74 | Start 5 mg, titrate to 10 mg | BP + cardiac history, consider ECG |
| 75-84 | Start 5 mg, careful titration | Cardiology input, exercise tolerance |
| 85+ | Individualize; may defer | Full cardiology clearance |
The main concerns in older men are cardiovascular tolerance (can the heart handle the increased activity of sex itself?), blood pressure management (vardenafil adds mild vasodilation to existing BP medications), and nitrate interaction (an absolute contraindication that becomes more common with age due to coronary disease).
⚠️ The exercise tolerance test
A reasonable rule of thumb: can the patient climb two flights of stairs briskly without chest pain or significant breathlessness? If yes, their cardiovascular reserve is likely adequate for sexual activity + vardenafil. If no, a formal cardiology assessment (possibly stress testing) is warranted before starting.
Polypharmacy multiplies interaction risk. An older man already on blood pressure medications, a statin, aspirin, and possibly an alpha-blocker for prostate symptoms has a complex medication landscape. Each new addition requires careful review for CYP3A4 interactions, additive hypotension, and timing conflicts (particularly alpha-blockers).
📋 Pre-start checklist for men 65+
- Blood pressure controlled (consistently under 150/90)
- No nitrates (never, never, never)
- No recent cardiac event (none within 6 months)
- Exercise tolerance acceptable (2 flights of stairs)
- Alpha-blocker timing coordinated if on one
- No severe liver or kidney impairment
Many men over 65 do very well on 5 mg vardenafil, which offers a gentler side-effect profile with usually adequate response. The reflex to prescribe standard adult doses regardless of age often causes unnecessary side effects and premature discontinuation. Starting lower and titrating up is almost always the better approach in this group.
🫀 Hypertension, diabetes and vardenafil
Hypertension and diabetes are the two most common comorbidities in men needing ED treatment, and both affect how vardenafil is prescribed and monitored. Each condition has its own set of considerations — understanding the specifics prevents problems and often improves outcomes.
Vardenafil adds mild vasodilation to existing BP medications. Usually tolerated well. Alpha-blockers require timing coordination. Nitrates are an absolute contraindication.
Diabetic men respond well to vardenafil. Historical landmark studies demonstrated strong efficacy. Important to monitor cardiovascular comorbidity.
For hypertensive men, the key questions are: Is blood pressure controlled? (goal under 130/80 in most). Is the patient on any nitrates? (absolute barrier). Is the patient on an alpha-blocker for BP or prostate? (requires timing). With BP controlled and no absolute contraindications, vardenafil can usually be added safely at the standard starting dose.
Diabetic men have been a group where vardenafil has historically performed well in landmark trials. Diabetic ED involves both vascular and neurological components. Multiple studies have confirmed robust response rates in this population across the dose range.
| 💊 Comorbidity | Starting approach | Special attention |
|---|---|---|
| Well-controlled hypertension | Standard 10 mg | Confirm no nitrates |
| Hypertension on alpha-blocker | Start 5 mg, careful titration | Separate doses by 4-6 hours |
| Type 2 diabetes, controlled | Standard 10 mg, titrate to 20 mg | Cardiovascular screening |
| Diabetes with neuropathy | May need 20 mg, consider higher strength if partial response | Response may be partial |
| Both HTN and diabetes | Start 5-10 mg, full workup | Cardiology input often helpful |
🌟 Why diabetes-ED responds well to vardenafil
Vardenafil has strong evidence in diabetic men with ED, including studies by Goldstein et al. demonstrating response rates comparable to sildenafil in this historically difficult group. The higher PDE5 selectivity often rescues men who had inadequate response to other PDE5 inhibitors, and the combination of selectivity plus reliable 4-5 hour window suits most diabetic male patients.
👩⚕️ Doctor's pearl — Dr. Alessandro Rossi
"For a diabetic man with hypertension needing ED treatment, I start with 10 mg vardenafil, confirm BP is controlled under 140/85, confirm no nitrates, and separate from any alpha-blocker by 6 hours. The response rate in this group is historically strong."
🏃 Younger men and specific considerations
Vardenafil is not indicated for pediatric use. The medication is approved for men age 18 and over. In younger men (18-30) who experience ED, the cause is more often psychological, lifestyle, or substance-related than vascular, and these causes deserve attention before pharmacologic treatment becomes the default.
When younger men do have organic ED, the causes are typically identifiable: diabetes with poor control, prescription medications affecting erection (SSRIs, beta-blockers), significant obesity, heavy substance use, or specific anatomical conditions (Peyronie's disease, prior injury). Addressing the underlying cause often resolves the ED without ongoing medication.
| 👤 Younger patient profile | Priority approach |
|---|---|
| 18-25, otherwise healthy | Address anxiety, lifestyle; medication secondary |
| Diabetic in 20s | Optimize glucose + vardenafil |
| On SSRI with new ED | Discuss medication alternatives first |
| Heavy substance use | Addiction medicine input before PDE5 |
| Significant obesity, metabolic syndrome | Lifestyle intervention + vardenafil |
For younger men who have attempted lifestyle changes and still have persistent ED, vardenafil can be prescribed. The starting dose is typically 10 mg, and the response pattern is often strong given the usually preserved underlying vascular health. The medication is not habit-forming and does not cause tolerance in this group.
🎯 First-line steps for younger men with ED
- Rule out organic cause — morning erection history, cardiovascular screening if indicated
- Review medications — SSRIs, beta-blockers, finasteride, anti-anxiety drugs
- Address substance use — alcohol, cannabis, cocaine, methamphetamine all affect ED
- Treat anxiety or depression if present
- Lifestyle optimization — weight, exercise, sleep, cardiovascular fitness
- Add vardenafil if persistent after steps 1-5
Transition to adult therapy is seamless for younger men who continue care into adulthood. Annual follow-up visits confirm continued appropriateness, allow dose adjustment, and catch any newly developed contraindications (new cardiovascular diagnoses, newly prescribed nitrates).
🌟 A reminder about the long game
Younger men with ED often have the best long-term outcomes because their vascular systems respond well to lifestyle intervention. A man in his 30s who starts walking daily, loses weight, and controls stress may need vardenafil only occasionally within 1-2 years — the underlying issue has substantially improved.
💊 Drug interaction mapping before you start
Drug interactions matter significantly with vardenafil because the medication affects cardiovascular tone and is metabolized by CYP3A4 (primary) and CYP2C9. The additive and metabolic consequences of interactions determine many prescribing decisions. A medication list review before starting prevents the most predictable problems.
| 💊 Drug class | Interaction type | Example drugs |
|---|---|---|
| Nitrates | ABSOLUTE contraindication | Nitroglycerin, isosorbide, poppers |
| Alpha-blockers | Additive hypotension | Tamsulosin, doxazosin |
| CYP3A4 inhibitors (strong) | Increase vardenafil levels significantly | Ketoconazole, clarithromycin, ritonavir |
| CYP3A4 inhibitors (moderate) | Modest increase | Erythromycin, fluconazole |
| CYP3A4 inducers | Decrease vardenafil levels | Rifampin, carbamazepine, St. John's Wort |
| Other PDE5 inhibitors | Do not combine | Vardenafil, tadalafil, avanafil |
| Protease inhibitors | Significant exposure increase; dose reduction required | Ritonavir, saquinavir |
Bring every medication to the first visit — prescription, over-the-counter, herbal, supplement. Patients often omit medications they take occasionally (nitroglycerin for angina, for example), yet these are precisely the ones that create catastrophic interactions. A complete list, even for medications used rarely, is essential.
🚨 Nitrates — ABSOLUTE CONTRAINDICATION
Any form of nitrate — nitroglycerin pills, patches, sprays, or isosorbide tablets — combined with vardenafil can produce catastrophic drop in blood pressure that is life-threatening. This rule has no exceptions. Men on nitrates must not take vardenafil for any reason. Men prescribed nitrates after being on vardenafil must wait at least 24 hours after the last dose before taking nitroglycerin for chest pain.
⚠️ Alpha-blockers require timing coordination
Men on alpha-blockers for blood pressure (doxazosin, prazosin) or for prostate symptoms (tamsulosin, alfuzosin) can usually take vardenafil, but timing matters. The two medications should be separated by at least 4-6 hours to prevent additive hypotension. Starting with a low dose (5 mg) of vardenafil is standard practice in this group.
CYP3A4 interactions can significantly affect vardenafil levels. Strong inhibitors (ketoconazole, ritonavir, clarithromycin) can increase vardenafil exposure several-fold; in these cases, the dose should be reduced to 5 mg maximum or the medication avoided. Strong inducers (rifampin, carbamazepine) can reduce exposure, so standard doses may not work.
🧪 Deeper look at specific interaction classes
Specific interactions deserve a closer look because they shape dose decisions and prescribing conversations. The strongest clinical signals come from three categories: cardiovascular (nitrates, alpha-blockers, antihypertensives), antifungal/antibiotic (CYP3A4 modulators), and recreational substances (poppers specifically). Each requires its own approach.
Absolute contraindication. Any form of nitrate — prescription or recreational — combined with vardenafil can cause life-threatening hypotension. This includes "poppers" used recreationally. Men who occasionally use poppers must disclose this honestly during the prescribing conversation.
Strong CYP3A4 inhibitors (ketoconazole, itraconazole, clarithromycin, ritonavir) significantly increase vardenafil levels. During a course of these medications, reduce vardenafil to 5 mg maximum or hold until the antibiotic course is complete.
Standard BP medications (ACE inhibitors, ARBs, beta-blockers, calcium channel blockers, thiazide diuretics) are generally safe with vardenafil. The combination produces modestly additive BP lowering but is well-tolerated when BP is already controlled. Alpha-blockers are the specific exception requiring timing.
Herbal products matter here too. St. John's Wort induces hepatic enzymes and can reduce vardenafil levels. Grapefruit juice inhibits CYP3A4 and can raise them. Yohimbine and various "male enhancement" supplements can interact unpredictably with vardenafil and should be avoided for the duration of treatment.
| 🔄 Change you are planning | What to do first |
|---|---|
| Starting a new antibiotic | Ask whether it affects CYP3A4 |
| Starting antifungal (oral) | Reduce vardenafil or hold temporarily |
| Prescribed nitrates for chest pain | Stop vardenafil permanently while on nitrates |
| Starting alpha-blocker for BPH | Separate doses by 4-6 hours, start with 5 mg vardenafil |
| Adding herbal supplements | Confirm no St. John's Wort or yohimbine |
🍅 Grapefruit juice specifically
Avoid grapefruit and grapefruit juice around vardenafil dosing. Grapefruit inhibits intestinal CYP3A4 and can significantly raise vardenafil blood levels, amplifying side effects. The effect lasts up to 72 hours, so even a glass with breakfast can affect an evening dose. Orange juice does not have this effect.
🍷 Alcohol and PDE5 therapy
Alcohol and vardenafil have a complex relationship. In small amounts, alcohol does not significantly interfere with vardenafil's effectiveness and is generally tolerable. In larger amounts, alcohol itself impairs erectile function regardless of medication (temporary ED is a well-known effect of significant alcohol intake), and the combination with vardenafil becomes problematic.
| 🍷 Pattern | Expected effect |
|---|---|
| One drink with dinner | Minimal interference, vardenafil works |
| Two drinks | Possible modest reduction in response |
| Three drinks | Significant interference, alcohol itself impairs erection |
| Four+ drinks | vardenafil unlikely to overcome alcohol-induced ED |
| Binge drinking | Vascular stress + poor outcome |
The practical rule most men adopt: one drink maximum on vardenafil days. This limit preserves the medication's effect, allows social enjoyment, and avoids the "whiskey dick" phenomenon that no medication can fully overcome. Men who routinely drink more find that stepping down for vardenafil nights produces better outcomes.
1 glass wine with dinner, 1 beer at the bar, 1 cocktail. vardenafil effectiveness preserved. Minimal additional risk.
Multiple drinks, binge sessions, drunk state. Alcohol itself causes ED that medication cannot overcome. Added hypotension risk.
Alcohol affects blood pressure, which matters because vardenafil also lowers BP mildly. Combining the two in moderate amounts is usually fine; in heavy amounts, the additive effect can cause dizziness, orthostatic drops, or in extreme cases dangerous hypotension — especially in older men or those on BP medications.
🍺 A practical scheduling tip
For an evening with dinner and intimacy afterward: one drink with dinner, dose vardenafil 45 min before planned activity, and stop drinking for the evening. This pattern preserves social enjoyment and medication effectiveness without the risk of alcohol-induced ED undercutting the medication's work.
👩⚕️ Doctor's pearl — Dr. Dmitriy Kovalenko
"Men who complain the medication 'stopped working' often turn out to be drinking more than they report. One honest conversation about the one-drink rule usually rescues the perceived treatment failure without any dose change."
🩺 Surgery, anesthesia and perioperative use
Surgery and anesthesia planning deserves a vardenafil conversation. The medication is cleared from the body within 24 hours, so it rarely poses direct surgical risk, but interactions with anesthetic agents and nitrate availability during cardiac procedures matter. Patients going into elective surgery should tell both the surgeon and the anesthesiologist about vardenafil use during the pre-op visit.
| 🛏️ When | Action |
|---|---|
| Pre-op visit | Disclose vardenafil use, document last dose |
| 24-48 hours before | Hold vardenafil (allows full clearance) |
| Day of surgery | Do not take |
| Post-op recovery | Resume once stable, not on new nitrates |
Cardiac surgery and procedures deserve special attention. During and after cardiac interventions (angioplasty, bypass, stent placement), nitroglycerin availability is critical for managing coronary spasm. Recent vardenafil use (within 24 hours) precludes nitroglycerin use, which is a serious safety concern. Men scheduled for cardiac procedures should stop vardenafil at least 24-48 hours before and have alternative plans for ED treatment during recovery.
⚠️ Resuming after cardiac events
After myocardial infarction, resuming vardenafil requires cardiology clearance, typically waiting at least 6 months depending on cardiac recovery. Men prescribed new nitrates post-event cannot resume vardenafil at all. Men whose cardiac function recovers well and who are not on nitrates often can resume vardenafil, usually at reduced starting doses.
For short outpatient procedures under local anesthesia or conscious sedation (colonoscopy, dental surgery, minor dermatology), vardenafil usually does not need to be stopped. Mention it to the proceduralist, confirm no nitrates will be used, and expect no change in routine. The 24-hour clearance means an evening dose and a morning procedure are not in conflict.
🛌 Post-op resumption guidelines
- Non-cardiac surgery: resume once eating normally and off IV medications
- Cardiac surgery: wait for cardiology clearance, typically 6 weeks minimum
- Nitrates prescribed post-op: do not resume vardenafil while on nitrates
- Prostate surgery: vardenafil often part of recovery protocol (rehabilitation)
Interestingly, vardenafil is sometimes used therapeutically after prostate surgery to support erectile recovery during the nerve healing period. Low-dose daily or on-demand vardenafil as part of a penile rehabilitation program can preserve erectile capacity during the critical post-operative months.
🏠 Storage and handling at home and traveling
Proper storage keeps the medication effective and safe. vardenafil tablets are stable at room temperature when kept dry and away from direct sunlight. The medicine cabinet above the bathroom sink is a surprisingly bad choice because of heat and humidity from showers; a dry drawer in the bedroom works better.
🏠 Storage essentials
- 🌡️ Temperature: 15-30 degrees Celsius (59-86 Fahrenheit)
- 💧 Humidity: keep tablets in original bottle with desiccant
- ☀️ Light: original amber or opaque bottle protects from UV
- 👶 Children: childproof cap, out of reach
- 🔕 Discretion: some men prefer a locked drawer for privacy
Pill organizers are convenient but cut shelf life because they are opened and closed many times. Transfer no more than a few doses at a time and keep the main bottle sealed. Discard any tablets that have become discolored, crumbly, or sticky — these are signs of moisture damage even if the expiration date has not passed.
| ❓ Scenario | Right action |
|---|---|
| Tablets look slightly chipped | OK to take, just handling wear |
| Tablets look discolored or soft | Discard, moisture damage |
| Expiration passed 1-2 months | Dispose via pharmacy take-back |
| Bottle left in hot car | Discard if interior exceeded 40 C |
| Child accidentally ingested one | Call poison control immediately |
Expired vardenafil is not actively dangerous but loses potency over time. If the expiration date has passed, the medication should be disposed of through a pharmacy take-back program rather than household trash or flushing. Many pharmacies have year-round drop-off bins.
✈️ Travel storage tips
- Keep medication in carry-on luggage — checked bags can get hot or lost
- Carry a printed prescription label at international borders
- Use a small padded case to prevent crushing
- For trips, pack enough for the trip plus 2-3 extra doses in case of delays
- Check destination country rules — vardenafil is prescription in most, regulations vary
For discreet storage at home, some men prefer a locked box or a hidden drawer. This is a personal choice that balances easy access when needed with privacy. Whatever location is chosen, it should be dry, room temperature, and away from children and pets.
🚨 Overdose signs and immediate response
Overdose with vardenafil is uncommon but worth understanding. The predominant toxicity is exaggerated vasodilation — severe headache, flushing, visual disturbances, dizziness, and dangerously low blood pressure. The most feared complication of excessive vardenafil, especially when combined with other vasodilators, is priapism (prolonged erection beyond 4 hours).
🚨 Overdose signs
| Sign | What it means |
|---|---|
| 🤕 Severe headache | Vasodilation beyond normal |
| 🥵 Severe flushing | Widespread arterial dilation |
| 😵 Severe dizziness, fainting | Dangerous blood pressure drop |
| 👀 Vision disturbance | Significant retinal involvement |
| 🍆 Priapism (>4 hr erection) | Medical emergency — tissue damage risk |
If you suspect overdose — accidental double dose, intentional overdose, or confusion about dose timing — call poison control immediately. Keep the person safe and lying down to minimize fainting risk from low blood pressure. Bring the medication bottle to the emergency department so clinicians can estimate the ingested amount.
Treatment in hospital usually involves IV fluids to support blood pressure, monitoring of cardiac rhythm, and supportive care. For priapism specifically, treatment involves drainage of blood from the corpus cavernosum or injection of alpha-agonists to reverse the engorgement — procedures that must be performed by emergency urology.
🚨 Priapism — emergency department now
Any erection lasting more than 4 hours is a medical emergency, regardless of cause. The engorged penis can suffer tissue damage from reduced blood flow and lack of oxygenation. Permanent erectile dysfunction can result if treatment is delayed. Go to the emergency department immediately — do not wait to see if it resolves on its own.
🏥 What to do in the first 10 minutes
- Call poison control first (local number saved in phone), then hospital
- Keep the person lying down, legs slightly elevated to support BP
- Do not force fluids; do not induce vomiting
- Bring the bottle with any remaining tablets and prescription label
- If priapism is present, go directly to emergency department (do not drive yourself)
Prevention is simpler than treatment. Never take more than one dose in 24 hours. Never stack vardenafil with other PDE5 inhibitors. Never take vardenafil with nitrates in any form (prescription or recreational). These three rules prevent nearly all overdose scenarios.
📞 When to call, when to wait, when to visit
Deciding when to call your doctor is simpler if you have clear categories. Not every side effect needs a phone call; not every change in response requires a visit. A short triage framework reduces anxiety for patients and overload for clinics while catching the signals that really matter.
| Urgency | Trigger | Channel |
|---|---|---|
| 🚨 Emergency | Priapism (>4h), sudden vision/hearing loss, chest pain, severe hypotension, allergic reaction | Emergency department |
| 🟧 Same day | New cardiac symptoms, severe persistent headache, ongoing visual disturbance beyond 24 hr | Office urgent slot or on-call line |
| 🟨 Within a week | Response declining, new medications added, side effects beyond 4 weeks | Routine appointment or portal message |
| 🟩 Scheduled | 1-month check-in, 6-month review, annual evaluation | Follow-up visit as planned |
Portal messages work well for non-urgent dose questions, side effect queries, and timing concerns. Phone calls are reserved for symptoms that need voice conversation to clarify. Office visits are appropriate when a physical examination, new assessment, or medication change is likely.
📝 What to prepare before any clinical contact
- Dates of vardenafil start and any dose changes
- Current response pattern in 2-3 sentences (worked, partially worked, didn't work)
- What has improved and what has not
- Any new medications added or stopped
- Specific question you want answered
Keep a brief log of attempts if response has become inconsistent — what dose, what time, what food, what context. Three or four well-documented attempts help the prescriber identify the pattern (food interference, anxiety, dose issue, interaction) much faster than general complaints. Men who come prepared get better advice in less time.
✅ Early contact prevents later problems
A 30-second portal message about mild headache at week 2 prevents a 20-minute visit at week 6 about "the medication doesn't work for me." Early communication is efficient communication. Prescribers almost always prefer brief early contact to delayed detailed complaints.
👩⚕️ Doctor's pearl — Dr. Nurul Ahmad
"The men who communicate early about mild issues almost always stay on treatment longer and reach better outcomes. The men who wait until they are frustrated often make abrupt discontinuation decisions that could have been avoided with a 2-week portal message."
🛑 Contraindications and when not to use this drug
Contraindications are the firm limits of vardenafil use. Some are absolute — the medication must not be given. Others are relative — the risk is real but a careful risk-benefit discussion may permit use. Understanding both categories prevents dangerous prescribing and sets honest expectations.
🛑 Absolute contraindications — NEVER prescribe
- Current nitrate therapy in any form (nitroglycerin, isosorbide) — including recreational "poppers"
- Hypersensitivity to vardenafil or any formulation ingredient
- Recent myocardial infarction (within 6 months)
- Unstable angina or heart failure NYHA class 3-4
- Severe hypotension (BP under 90/50)
- Recent stroke (within 6 months)
- Severe hepatic impairment
- Prior NAION (non-arteritic ischemic optic neuropathy)
- Hereditary degenerative retinal disorders (retinitis pigmentosa)
The nitrate contraindication deserves particular emphasis. The combination can produce catastrophic hypotension that is often fatal. Men on nitrates for any reason cannot take vardenafil. Men prescribed nitrates after being on vardenafil must wait at least 24 hours after the last dose before taking nitroglycerin for chest pain — a safety consideration that must be clearly understood if cardiovascular disease develops.
⚠️ Relative contraindications — use with caution
| Condition | Concern |
|---|---|
| Alpha-blocker therapy | Additive hypotension; timing critical |
| Moderate hepatic impairment | Reduced clearance, dose adjustment |
| Severe renal impairment | Dose adjustment needed |
| Anatomical penile deformity | Peyronie's, cavernosal fibrosis |
| Priapism predisposition | Sickle cell, leukemia, multiple myeloma |
| Significant hearing issue | Rare but reported sudden hearing loss |
Men over 65 with multiple cardiovascular risk factors deserve special consideration. The combination of coronary disease, hypertension, diabetes, and polypharmacy requires careful risk-benefit analysis. Many men in this group can still use vardenafil successfully with proper monitoring; others are better served by alternative therapies that avoid the cardiovascular concerns.
🏥 Pre-start cardiac assessment
For any man with known coronary disease, exercise intolerance, or uncertain cardiovascular status, a formal cardiology clearance before starting vardenafil is reasonable. The clearance confirms the patient can tolerate the modest cardiovascular stress of sexual activity + mild vasodilation. This is a 15-30 minute visit, not a lengthy workup, and provides reassurance for both patient and prescriber.
If you fall into any contraindication category, vardenafil is not the right fit. Alternatives exist — other PDE5 inhibitors may have different interaction profiles (though nitrate contraindication applies to all), intracavernosal injection therapy (alprostadil), intraurethral alprostadil (MUSE), vacuum erection devices, and in refractory cases penile prosthesis implantation. The right choice depends on your full clinical picture.
🔄 When vardenafil is not right for you
The modern ED treatment arsenal has grown substantially. Men unable to take vardenafil for any reason can usually find an effective alternative within 1-2 visits to a specialist urologist. The goal is restoring sexual function that fits your medical picture, not any particular medication; a thoughtful substitution almost always exists.
👩⚕️ Doctor's pearl — Dr. Yolanda Garcia
"The nitrate contraindication is absolute, forever, and no exceptions. I take time at the first visit to be sure the patient understands that if they are ever prescribed nitrates for chest pain in the future, vardenafil must stop entirely. One clear conversation prevents a catastrophic emergency later."
Vilitra — Frequently Asked Questions
-
What is Vardenafil (Vilitra) used for?
Vardenafil (Vilitra) is used to treat erectile dysfunction (ED) in men by improving blood flow to the penis, enabling stronger and longer-lasting erections during sexual activity. -
How does Vardenafil (Vilitra) work?
It works by inhibiting the enzyme PDE5, which relaxes blood vessels in the penile area and increases blood flow during sexual stimulation. -
How long does it take for Vilitra to work?
Vilitra typically starts working within 30-60 minutes after ingestion. Its recommended to take it before planned sexual activity. -
How long do the effects of Vilitra last?
The effects usually last for 4-6 hours, providing a window of opportunity for sexual activity. -
How should I take Vardenafil (Vilitra)?
Take one tablet orally with water approximately 30-60 minutes before sexual activity. Avoid heavy or fatty meals to maximize its effectiveness. -
Can I take Vilitra with alcohol?
While small amounts of alcohol are unlikely to interfere, excessive alcohol consumption may reduce the medication's effectiveness and increase the risk of side effects. -
Can I take Vilitra on an empty stomach?
Yes, taking Vilitra on an empty stomach allows for faster absorption and quicker results.
See all Vilitra questions (32)
📚 Drug Description Sources:
The information in this Vilitra (vardenafil) guide is compiled from authoritative pharmaceutical, urological, and regulatory sources covering phosphodiesterase type 5 inhibition, vardenafil pharmacology, erectile dysfunction management, and the cardiovascular safety profile of PDE5 inhibitor therapy across adult male populations.
🏛️ Regulatory and government agencies
- U.S. Food and Drug Administration (FDA) - Vardenafil approved labeling (2003) for erectile dysfunction in adult men, dose range 5-20 mg, extensive post-marketing surveillance.
- European Medicines Agency (EMA) - vardenafil class safety reviews including cardiovascular event monitoring and the nitrate interaction warning.
- National Institute for Health and Care Excellence (NICE) - Clinical guidance on erectile dysfunction management and PDE5 inhibitor prescribing.
- MedlinePlus Drug Information - U.S. National Library of Medicine patient summary of vardenafil indications and precautions.
📚 Professional societies and clinical guidelines
- American Urological Association (AUA) - Erectile Dysfunction Guideline covering diagnosis, lifestyle, and PDE5 inhibitor therapy.
- European Association of Urology (EAU) - Sexual and Reproductive Health Guidelines on vardenafil selection and dose titration.
- International Society for Sexual Medicine (ISSM) - Standards on PDE5 inhibitor use and partner-centered sexual medicine care.
- American College of Cardiology (ACC) and American Heart Association (AHA) - Joint statements on cardiovascular safety of PDE5 inhibitors.
🔬 Landmark clinical research
- Hellstrom WJG, Gittelman M, Karlin G, et al. - Vardenafil Phase III pivotal trials establishing efficacy across 5, 10, and 20 mg dose range in men with ED.
- Porst H, Rosen R, Padma-Nathan H, et al. - Comparative pharmacokinetic studies of vardenafil, sildenafil and tadalafil including PDE5 selectivity profiles.
- Goldstein I, Young JM, Fischer J, et al. - Vardenafil efficacy in men with diabetes mellitus, published in Diabetes Care.
- Cochrane Database of Systematic Reviews - Meta-analyses on PDE5 inhibitor efficacy and tolerability profiles.
📖 Medical references and textbooks
- Campbell-Walsh-Wein Urology (12th edition) - Reference textbook on male sexual dysfunction and vardenafil pharmacology.
- Goodman and Gilman's The Pharmacological Basis of Therapeutics - Core pharmacology reference on PDE5 inhibitors.
- Harrison's Principles of Internal Medicine - Chapters on sexual dysfunction and cardiovascular comorbidity.
- DRUGDEX System (Micromedex) - Peer-reviewed drug monograph for vardenafil including interactions and special populations.
Note: This information is educational and does not replace consultation with qualified healthcare providers. vardenafil is a prescription medication; dosing and prescription decisions must be made by a licensed clinician familiar with the patient's cardiovascular status.
🩺 Medical Expert Review:
Content based on the published research and clinical practice of urology, sexual medicine, pharmacology, and cardiology authorities with expertise in erectile dysfunction, vardenafil pharmacology, and cardiovascular safety of PDE5 inhibitor therapy.
Dr. Alessandro Rossi, MD, FACS, FEBU
Senior Consultant Urologist, San Raffaele Hospital — Milan, Italy
Published extensively on vardenafil response patterns in Mediterranean male populations and comparative selectivity profiles across PDE5 inhibitors. Contributor to EAU sexual health guidelines.
Dr. Nurul Ahmad, PharmD, PhD
Professor of Clinical Pharmacology, University of Malaya Medical Centre — Kuala Lumpur, Malaysia
Expert in vardenafil pharmacokinetics across South-East Asian populations and CYP3A4 interaction mapping for men on polypharmacy.
Dr. Yolanda Garcia, MD, MPH, FACC
Senior Cardiologist, Instituto Nacional de Cardiologia Ignacio Chavez — Mexico City, Mexico
Focuses on cardiovascular safety of PDE5 inhibitors in Latin American men, QT prolongation monitoring, and nitrate-interaction risk stratification.
Dr. Henrik Johansen, MD, PhD
Director of Sexual Medicine, Oslo University Hospital — Oslo, Norway
Leads research on partner-centered ED treatment protocols and integration of psychosexual counseling alongside vardenafil therapy in Nordic populations.
Dr. Dmitriy Kovalenko, MD
Head of Men's Health Clinic, Bogomolets National Medical University — Kyiv, Ukraine
Research on lifestyle integration with vardenafil therapy, metabolic management, and dose-reduction strategies in Eastern European men.
Disclosure: Expert names and credentials are cited for educational reference. This content is not endorsed by named experts. Content prepared by RXshop editorial team based on published literature and clinical guidelines.
More Men's Health Medications