Buy Sildalist (Sildenafil 100mg Tadalafil 20/40mg) Online - Unique Dual PDE5 Combo for Severe ED


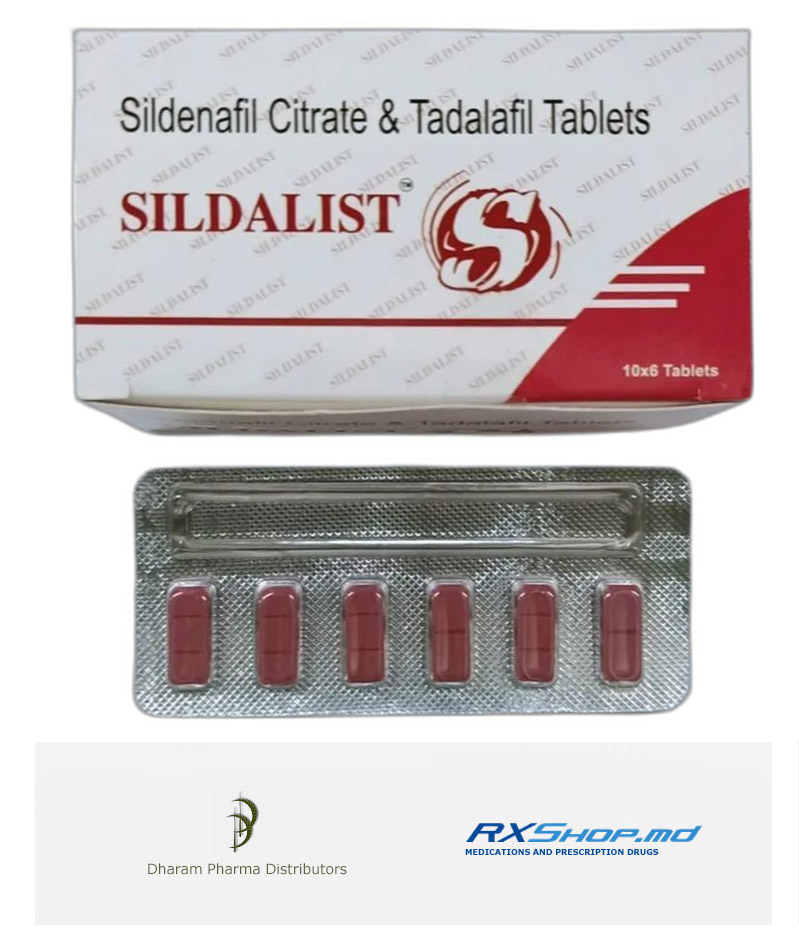
Sildalist (Sildenafil Citrate 100mg + Tadalafil 20/40mg) represents a uniquely powerful dual PDE5 inhibitor combination — the rare fixed-dose product combining TWO different PDE5 inhibitor molecules in a single tablet. Unlike typical ED+PE combos (like Cenforce-D or Super Tadarise which pair PDE5 with dapoxetine SSRI), Sildalist takes a different approach: sildenafil provides FAST 30-60 minute onset for immediate response, while tadalafil provides LONG 36-hour duration extending the window well beyond either drug alone. Manufactured by Dharam Pharma Distributors India, this advanced dual-PDE5 formulation is particularly valued by men who want "best of both worlds" — quick action AND weekend-long responsiveness from a single dose.
Sildenafil and tadalafil both work through selective phosphodiesterase type 5 (PDE5) inhibition allowing cGMP accumulation and corpus cavernosum smooth muscle relaxation for erection, but they have distinctive pharmacokinetic profiles. Sildenafil peaks in blood within 1 hour and has 4-hour half-life providing 4-5 hour effect window. Tadalafil peaks slower at 2 hours but has 17.5-hour half-life providing up to 36-hour responsiveness window. In combination, sildenafil delivers the fast initial onset for the first few hours while tadalafil maintains steady effect throughout an extended weekend. Clinical response: successful intercourse in 80-90% of attempts (higher than either drug alone), onset within 20-30 minutes, and extended 18-36 hour responsiveness window.
Sildalist specifically serves men with severe ED or those wanting maximum PDE5 effect across an extended window. The medication particularly benefits previous single-PDE5 non-responders; patients with severe vascular disease needing dual mechanism; men wanting fast onset AND long duration from single dose; and those valuing maximum sexual flexibility across an entire weekend. Treats psychogenic ED, vasculogenic ED, diabetic ED, post-prostatectomy ED, and age-related decline.
Sildalist requires on-demand dosing 20-30 minutes before anticipated sexual activity, no more than once per 24 hours. Take with water, minor food interaction from sildenafil component. Peak concentrations for sildenafil at 1 hour, tadalafil at 2 hours. Combined effect: fast onset with 18-36 hour extended window. Dharam Pharma India manufactures under WHO-GMP standards.
Free prescription
Discrete packaging
Have questions?
Quality Assurance

- ED: Medical abbreviation for erectile dysfunction affecting millions of men worldwide;
- Dual PDE5 Combo Therapy: Unique combination of sildenafil and tadalafil combining fast onset with long duration;
- Fast Onset Long Duration ED: 20-30 minute onset with 18-36 hour window unique combination benefit;
- Weekend Combo Pill: Single dose enables entire weekend sexual freedom with fast initial response;
- Severe Erectile Dysfunction: Severe ED cases benefiting from dual PDE5 mechanism and 100/40 mg high strength;
- Impotence: Traditional term for erectile dysfunction affecting sexual function and confidence;
- Single PDE5 Non Response: Patients not responding to single-agent PDE5 benefit from dual mechanism;
- Poor Penile Blood Flow: Insufficient arterial blood inflow to corpus cavernosum improving with dual PDE5 inhibition;
- Weak Inconsistent Erections: Unreliable erection quality improving through dual PDE5 mechanism reliability;
- Psychogenic Erectile Dysfunction: Anxiety-driven ED with dual mechanism supporting reduced performance anxiety;
- Vasculogenic Erectile Dysfunction: ED from arterial insufficiency responding to potent dual PDE5-mediated vasodilation;
- Diabetic ED: Diabetes-related erectile dysfunction responding to dual PDE5 combination approach;
- Age Related Erectile Decline: Progressive age-related erectile function decline responding to dual PDE5 inhibition;
- Post Prostate Surgery ED: Erectile dysfunction after radical prostatectomy responding to dual PDE5 rehabilitation;
- Performance Anxiety: Anxiety-related ED responding to predictable rapid-onset extended-window erection;
- Enhanced Sexual Endurance: Longer-lasting sexual capability across extended tadalafil window;
- Spontaneous Intimacy Support: Extended window supports unplanned sexual encounters throughout weekend;
- Multiple Encounter Support: 18-36 hour window supports multiple sexual encounters from single dose;
- Dual PDE5 Inhibitor Therapy: Innovative combination approach for maximum PDE5 effect and extended coverage.
- Faster 20-30 Minute Onset: Sildenafil component provides fast initial response before tadalafil peaks;
- Better 18-36 Hour Extended Window: Tadalafil component extends responsiveness far beyond either drug alone;
- Better Best of Both Worlds ED: Fast sildenafil onset AND long tadalafil duration from single tablet;
- Better Erectile Function: Successful intercourse in 80-90% of attempts through dual PDE5 mechanism;
- Better Firm Erections: Stronger firmer erections through combined sildenafil and tadalafil PDE5 inhibition;
- Better Penile Blood Flow: Enhanced cGMP-mediated smooth muscle relaxation from dual PDE5 blockade;
- Better Sexual Stamina: Extended window enables sustained sexual performance across multiple encounters;
- Better Sexual Flexibility: 18-36 hour window supports both planned and spontaneous encounters;
- Better Sexual Spontaneity: Fast onset with extended window eliminates strict pre-planning of activity;
- Better Multiple Encounter Coverage: Single dose covers multiple sexual encounters throughout extended tadalafil window;
- Better Single PDE5 Non Responder Rescue: Patients not responding to single agent benefit from dual mechanism;
- Better Severe ED Response: Dual PDE5 mechanism handles severe ED where single-agent therapy proves inadequate;
- Better Diabetes ED Response: Dual PDE5 approach helpful in diabetic ED with advanced vascular disease;
- Better Post Prostatectomy Response: Combined mechanism improves nerve-sparing prostatectomy patient rehabilitation;
- Better Sexual Confidence: Reliable dual response restores sexual confidence and reduces performance anxiety;
- Better Relationship Satisfaction: Extended window and reliable response improve relationship intimacy quality;
- Less Performance Anxiety: Predictable dual response reduces anxiety about sexual performance timing;
- Better Generic Cost: Dual generic substantially cheaper than combining brand Viagra plus Cialis separately;
- Better Quality of Life: Daily wellbeing improves dramatically as severe ED resolves and sexual confidence returns.
Generic Sildalist (Sildenafil Citrate with Tadalafil 100 mg / 20 mg) Medication guide:
💊 Sildalist Introduction and Dual PDE5 Overview
Sildalist is a fixed-dose combination tablet containing sildenafil 100 mg plus tadalafil 20 mg, two PDE5 inhibitors with complementary pharmacokinetic profiles. The combination delivers the fast onset of sildenafil together with the extended duration of tadalafil, creating a single-tablet approach for men wanting both features. The combination formulation is produced as generic by Indian manufacturers; it is not FDA-approved as a fixed-dose product.
💊 Core Facts
Dual PDE5 inhibitor — fast onset of sildenafil plus 36-hour window of tadalafil in one tablet.
Composition
Sildenafil 100 mg + Tadalafil 20 mg
Fast Onset
30-60 minutes (sildenafil)
Extended Window
Up to 36 hours (tadalafil)
Approval Status
Generic from India; not FDA fixed-dose
The clinical rationale for a dual PDE5 combination is the different kinetic profiles of the two active ingredients. Sildenafil reaches peak concentration quickly (approximately 1 hour) but is largely cleared by 4-6 hours. Tadalafil reaches peak more slowly (approximately 2 hours) but maintains clinical effect for up to 36 hours. In the combination, sildenafil provides the fast initial response while tadalafil extends the window well into the next day.
📋 What This Guide Covers
DUAL PDE5 MECHANISM
How sildenafil and tadalafil act on the same enzyme but with distinct kinetic profiles, and why combination offers both fast and extended effect.
CARDIOVASCULAR SAFETY
Nitrate contraindication is absolute — both agents in Sildalist carry this risk. Alpha-blocker precautions, cardiac fitness, and Princeton Consensus framework.
DOSING AND TIMING
Single-dose planning, 72-hour minimum interval between uses, food effects, and the realistic expectations for combination therapy.
COMPARATIVE CHOICE
When combination fits better than single-agent sildenafil, tadalafil, or vardenafil. Troubleshooting inadequate response. Not every man needs or benefits from dual therapy.
💊 Combination Rationale
Sildalist is designed for men who want both the fast predictable onset of sildenafil and the long window of tadalafil in a single tablet. The combination is not inherently more effective than optimized single-agent therapy, but offers kinetic flexibility that neither agent alone provides. Many men with established ED find single-agent sildenafil or tadalafil fully adequate; combination is an option for specific preferences or suboptimal single-agent response.
🧬 How Sildenafil and Tadalafil Work Together
Sildenafil and tadalafil work on the same enzyme (phosphodiesterase type 5) through the same mechanism, but their chemistry differs enough to produce distinct absorption, peak timing, and clearance patterns. Understanding both agents clarifies what the combination actually delivers.
🧬 Shared PDE5 Mechanism
Sexual arousal triggers nitric oxide release
Arousal signals from brain cause penile nerve endings to release nitric oxide. This triggers smooth muscle relaxation in the corpora cavernosa through cyclic GMP signaling.
Cyclic GMP relaxes penile smooth muscle
Relaxation allows blood to flow in and fill the corpora cavernosa. The resulting pressure compresses venous outflow, trapping blood for erection.
PDE5 normally breaks down cGMP
Phosphodiesterase type 5 (PDE5) is the enzyme that degrades cGMP, ending the signal. In ED, this process can happen too quickly or the signal starts too weak to maintain erection.
Both drugs inhibit PDE5
Sildenafil and tadalafil both block PDE5, allowing cGMP to accumulate. More cGMP means stronger and longer-lasting smooth muscle relaxation. The combination doubles up on PDE5 blockade through two different molecules.
⏱️ Where the Two Agents Differ
| Property | Sildenafil 100 mg | Tadalafil 20 mg |
|---|---|---|
| Time to peak concentration | ~1 hour | ~2 hours |
| Half-life | ~4 hours | ~17.5 hours |
| Clinical window | 4-6 hours | Up to 36 hours |
| Food effect | Fatty meal delays onset | Minimal effect from food |
| Approved year (brand) | FDA 1998 (Viagra) | FDA 2003 (Cialis) |
🎯 Combination Clinical Profile
Fast initial effect from sildenafil
Within 30-60 minutes of taking the combination, sildenafil levels are therapeutic. Men can plan intimacy within this short window.
Extended window from tadalafil
After sildenafil clears (around 6 hours), tadalafil remains active. The combined effect lasts into the next day, allowing spontaneity.
Both agents require sexual arousal
Neither drug produces erection by itself. The dual PDE5 blockade only works when the nitric oxide pathway is activated by sexual stimulation.
Combined side effects
Headache, flushing, nasal congestion, muscle aches — typical PDE5 effects possible from either agent, overlapping in combination use.
💊 Not Simply Additive Potency
The combination is not twice as potent as either single agent. PDE5 inhibition is already essentially complete at standard single-agent doses. The real combination benefit is the complementary kinetics — fast onset plus extended window — rather than increased peak effect. Men with suboptimal response to maximum single-agent dose may not necessarily respond better to combination therapy.
🔢 Understanding ED Categories and Cardiovascular Link
Erectile dysfunction is the most common male sexual complaint after age 40, affecting approximately 40% of men by age 40 and 70% by age 70. Understanding what ED actually is, its medical significance, and when combination PDE5 therapy fits helps set realistic expectations.
🔢 ED by the Numbers
Massachusetts Male Aging Study and subsequent large population surveys show steadily rising prevalence with age:
- Age 40-49: approximately 40% with some degree of ED
- Age 50-59: approximately 50%
- Age 60-69: approximately 60%
- Age 70+: approximately 70%
- Severe/complete ED: approximately 5% at 40, rising to 15% at 70
Treatment is appropriate for men with bothersome ED affecting intimate relationships — not every age-related change in function requires medication.
🎯 ED Categories
Vascular ED
The most common form. Arterial insufficiency reduces blood inflow; venous leak allows outflow during erection. Associated with cardiovascular risk factors (hypertension, diabetes, smoking, obesity).
Neurogenic ED
Nerve pathway damage. Diabetes, pelvic surgery (prostate, bladder, bowel), spinal cord injury, multiple sclerosis. May respond to PDE5 inhibitors depending on nerve integrity.
Hormonal ED
Low testosterone, elevated prolactin, thyroid disorders. Addressing hormonal imbalance often improves ED. Testosterone replacement does not reliably restore erection without PDE5 inhibitor support.
Psychogenic ED
Performance anxiety, depression, relationship issues. Often responds to PDE5 inhibitors because the medication breaks the anxiety-failure cycle.
Mixed ED
Most men have multiple contributors — some vascular, some neural, some psychological, some medication-related. Combined approach often most effective.
❤️ ED as Cardiovascular Warning
ED frequently precedes cardiovascular disease symptoms by 3-5 years. The penile arteries are smaller than coronary arteries, so endothelial dysfunction and atherosclerosis affect them first. New-onset ED in a man under 60 warrants cardiovascular risk assessment:
- Blood pressure measurement
- Fasting lipid panel
- Fasting glucose or HbA1c
- Family history of heart disease
- Smoking status
- Exercise tolerance assessment
ED is an opportunity for cardiovascular prevention as much as a condition to treat symptomatically.
💊 Combination Therapy Role
Combination Sildalist is typically a second-line choice after a trial of single-agent sildenafil or tadalafil. For men with uncomplicated ED and good response to single agent, combination offers no clear advantage. For men wanting the kinetic flexibility of fast onset plus long window, or for men with partial single-agent response, combination may be useful.
🎯 Who Benefits From Combination PDE5 Therapy
Sildalist combination is most appropriate for specific clinical scenarios rather than first-line treatment of all ED. Understanding when combination fits better than single-agent therapy prevents unnecessary complexity and side effects while matching treatment to the actual clinical need.
🎯 Who May Benefit From Combination
Men wanting both fast onset and long window
Spontaneous evening intimacy plus possible morning encounter. Fast initial effect from sildenafil, extended window from tadalafil in one dose.
Partial response to single-agent maximum dose
Men who get some response to sildenafil 100 mg or tadalafil 20 mg alone but not reliable adequate erection. The combination may help, though sometimes other factors (hormonal, vascular, psychological) are the limiting issue.
Confidence-building after multiple failures
For men with performance anxiety related to prior ED episodes, the combination provides fast reassurance plus the knowledge that effect lasts hours later. Can break the anxiety-failure cycle.
Weekend or special-occasion use
For planned weekends away or special events where intimacy may occur over 24-36 hours, the single-tablet combination simplifies planning versus repeat dosing of single agent.
🤔 When Single Agent Fits Better
Mild-to-moderate ED, good single-agent response
If single-agent sildenafil 50-100 mg or tadalafil 10-20 mg works reliably, there is no benefit from combination. Simpler is better.
Daily or near-daily intimacy pattern
Tadalafil 5 mg daily may fit better. Steady-state continuous coverage without the need for timing around dosing.
Cardiovascular caution
For men with significant cardiovascular disease, single-agent at lowest effective dose is safer than combination. Dual PDE5 effect may raise orthostatic risk, particularly with alpha-blockers.
Clear psychological or hormonal cause
Address the primary issue (depression treatment, testosterone replacement, relationship counseling) rather than escalating PDE5 therapy.
🛑 Not Appropriate For
- Men on nitrate medications (absolute contraindication for both PDE5 agents)
- Men with severe cardiovascular disease where sexual activity itself is risky
- Men with history of severe orthostatic hypotension
- Men on multiple alpha-blockers with uncontrolled hypotension
- Men with severe hepatic or renal impairment
- Men who have had vision loss attributed to prior PDE5 use (NAION)
- Men with retinitis pigmentosa
- Men who have not had ED evaluation (self-treating without medical input)
💊 Match the Approach to the Need
For most men with uncomplicated ED, a trial of single-agent sildenafil or tadalafil at optimal dose is the appropriate first step. Combination Sildalist has a role for specific scenarios — wanting both kinetic profiles, partial single-agent response, confidence-building after failures — but is not the default first choice. Prescriber guidance tailors the approach to individual circumstances.
🕐 How to Take Sildalist for Best Results
Taking Sildalist correctly maximizes effectiveness and manages the dual-agent considerations. Because the tablet contains both sildenafil and tadalafil, the protocol combines elements of both single-agent regimens.
🕐 Standard Sildalist Protocol
One tablet 30-60 minutes before planned intimacy
The sildenafil component is active within 30-60 minutes. Taking too close to intimacy means insufficient onset time; taking too far ahead means missing the sildenafil peak (though tadalafil continues).
Swallow whole with water
Do not split, crush, or chew. Full glass of water helps absorption and reduces first-dose dizziness risk.
Light meal preferred, avoid heavy fatty meal
A heavy fatty meal delays sildenafil absorption by 1-2 hours and may reduce peak. Tadalafil absorption is less affected. Light meal or empty stomach allows both agents to work predictably.
Sexual stimulation required
Neither sildenafil nor tadalafil causes erection without sexual arousal. Both agents work with the nitric oxide pathway; without arousal, there is nothing for the PDE5 blockade to amplify.
Minimum 72 hours between doses
Tadalafil has a half-life of ~17.5 hours. Taking another dose before clearance means dangerous accumulation. Wait at least 72 hours (3 days) between Sildalist doses to allow tadalafil to clear.
Limit alcohol
Both agents interact with alcohol to increase dizziness and orthostatic risk. One drink maximum with the medication; preferably none.
⚠️ First-Dose Precautions
For first use of Sildalist combination:
- Take at home in a safe environment
- Do not combine with alcohol on first dose
- Have water available throughout the evening
- Rise slowly from seated or lying positions for several hours
- Avoid driving for 6-8 hours after dosing
- Have partner or household member aware
- If severe side effects, lie down and hydrate; seek care if persistent
💊 Realistic Expectation Setting
About 60-70% of men with ED see adequate response on first attempt with properly timed PDE5 therapy. Response may improve with the second or third try as both the man and partner adapt to the medication timing and reduce performance anxiety. Give Sildalist 3-4 fair attempts at the correct timing and sexual context before concluding it does not work.
🍽️ Food Effects Differ Between the Two Agents
Food affects the two agents in Sildalist differently. Sildenafil absorption is significantly delayed by fatty meals; tadalafil is relatively unaffected. Understanding this difference allows planning meals and dose timing for optimal combined effect.
🍽️ Food Effects on Each Component
SILDENAFIL + FATTY MEAL
Peak delayed by 1-2 hours. Peak concentration reduced by ~30%. May impact fast onset of combination.
TADALAFIL + FATTY MEAL
Minimal effect on absorption. One of tadalafil's advantages — food-independent.
LIGHT MEAL / EMPTY STOMACH
Both agents absorb normally. Sildenafil peaks at ~1 hour; tadalafil at ~2 hours. Preferred for predictable combination effect.
GRAPEFRUIT JUICE
Inhibits CYP3A4 metabolism of both agents. Raises blood levels unpredictably. Side effect risk increases. Avoid.
🥪 Practical Meal Guidelines
| Dinner Context | Recommended Approach |
|---|---|
| Light meal planned | Take Sildalist 30-60 min before intimacy; eat normally |
| Steak, pasta, pizza, buttery entree | Take Sildalist 2 hours before intimacy to allow sildenafil to overcome delay |
| No dinner planned (empty stomach) | Take 30-60 min before; peak effect fastest. Have water available. |
| Morning dose for evening use | Tadalafil component covers evening; sildenafil largely cleared. Still effective due to tadalafil. |
| Grapefruit habit | Avoid grapefruit for 24-48 hours before and after dose |
💊 Dinner Date Reality
Classic dinner-date scenario — wine, pasta or steak, long meal — works against the fast-onset sildenafil component. Men should either plan for later intimacy (give sildenafil extra time to absorb despite the meal), rely on the tadalafil component for the extended effect, or dose Sildalist earlier before the meal. Combination tadalafil's long window makes dinner-date timing more forgiving than sildenafil alone.
🥃 Alcohol Interaction with Dual PDE5 Combination
Alcohol with Sildalist combination raises orthostatic hypotension and dizziness risk from both PDE5 components. Each agent alone has modest alcohol interaction; combination amplifies this effect. Moderate alcohol is possible with care; heavy drinking is not safe with the medication.
🥃 Why Combination Needs More Caution
Both PDE5 inhibitors cause vasodilation
Sildenafil and tadalafil both cause systemic blood vessel dilation beyond the penile effect. This produces modest blood pressure drop. Combined use may amplify this.
Alcohol adds vasodilation
Alcohol itself dilates blood vessels and lowers blood pressure. Combined with PDE5 inhibitors, the orthostatic drop can be significant.
Alcohol worsens ED performance
Heavy alcohol intake impairs sexual function directly — reduces arousal response and erection quality. The medication cannot fully overcome significant alcohol effect.
Dehydration risk
Alcohol is diuretic. Dehydration increases orthostatic hypotension risk from the medication. Hydration during and after drinking is especially important.
🥃 Practical Alcohol Guidance
✅ LOW RISK
No alcohol with dose. Compatible with Sildalist. Safest option for first use.
⚠️ MODEST RISK
1 glass of wine with dinner. Tolerable but raises dizziness risk. Hydrate well.
🚫 HIGH RISK
2-3+ drinks with dose. Severe dizziness, syncope risk. Also reduces erection quality.
🚫 AVOID COMPLETELY
Binge drinking, heavy drinking. Not safe. Defer medication to another occasion.
💊 A Dinner Date Approach
For a typical dinner date with 1-2 drinks, Sildalist is reasonable but limit yourself to a single glass of wine and ensure adequate hydration. The combination can tolerate this, but adding a second cocktail or liqueur significantly raises orthostatic risk. For heavier drinking occasions, defer the medication.
🛑 Nitrate Contraindication and Critical Drug Interactions
Nitrate medication combined with any PDE5 inhibitor can cause life-threatening blood pressure drop. This is the single most important safety consideration with Sildalist — and because the product contains both sildenafil and tadalafil, the risk is doubled relative to single-agent use.
🛑 Absolute Contraindication: Nitrates
Men on nitrates must NOT take Sildalist. Combined use can cause fatal hypotension.
Nitrate medications include:
- Nitroglycerin (sublingual, patch, ointment, spray)
- Isosorbide dinitrate
- Isosorbide mononitrate
- Any form of nitrate for angina or heart failure
- Amyl nitrite ("poppers") — recreational use
- Sodium nitroprusside
If you take any of these, Sildalist is dangerous. Discuss alternative ED treatment with prescriber.
⏰ Nitrate Timing Window After Sildalist
If a man takes Sildalist and then has chest pain requiring emergency nitrate treatment:
- Sildenafil component: wait at least 24 hours before nitrate use
- Tadalafil component: wait at least 48 hours before nitrate use
- Combination Sildalist: both components must be clear — wait 48 hours minimum
- In emergency situations, this means nitrates may be withheld while using alternative blood pressure or chest pain management
- Tell any emergency care provider that you have taken Sildalist — this changes acute cardiac management
⚠️ Other Significant Interactions
Alpha-blockers (tamsulosin, doxazosin, prazosin)
Significant orthostatic hypotension risk. Combination may be tolerable with careful dose timing (alpha-blocker and PDE5 at least 4 hours apart) but requires caution. For men on alpha-blockers, start with single-agent sildenafil 25 mg or tadalafil 2.5-5 mg to assess tolerance before combination.
Strong CYP3A4 inhibitors (ketoconazole, itraconazole, ritonavir, clarithromycin, telithromycin)
Both sildenafil and tadalafil are CYP3A4-metabolized. Strong inhibitors raise blood levels significantly. Combination not recommended with these drugs. If necessary, use single-agent at reduced dose.
Moderate CYP3A4 inhibitors (erythromycin, fluconazole, diltiazem, verapamil)
Modest blood level increase. Use with care. Consider single-agent at lower dose rather than combination.
Antihypertensive medications
Multiple blood pressure drugs can lead to additive hypotension. Discuss with prescriber. Usually manageable with careful dosing in stable hypertension.
Riociguat (soluble guanylate cyclase stimulator)
Contraindicated with any PDE5 inhibitor. Both act on cGMP pathway with dangerous combined effect. Men on riociguat for pulmonary hypertension cannot use PDE5 inhibitors.
✅ Common Medications Usually Safe
- Metformin, insulin, other diabetes medications
- Statins (atorvastatin, rosuvastatin, simvastatin)
- Blood pressure medications without nitrates (ACE inhibitors, ARBs, calcium channel blockers, beta-blockers)
- Standard antibiotics (amoxicillin, azithromycin — except clarithromycin)
- Acid reducers (omeprazole, pantoprazole, famotidine)
- Thyroid medications (levothyroxine)
- Standard pain relievers (acetaminophen, ibuprofen, naproxen in moderation)
- Anti-depressants (SSRIs, SNRIs) — no PDE5-specific interaction
💊 Medication Reconciliation Essential
Before first use of Sildalist, a complete medication review with the prescriber or pharmacist is essential. Nitrates must be identified definitively; alpha-blocker dose timing planned; CYP3A4 inhibitors adjusted or alternatives considered. This review takes 10-15 minutes but prevents potentially life-threatening interactions.
❤️ Cardiovascular Safety and Princeton Consensus Framework
Cardiovascular safety is the central consideration with Sildalist combination. Because both PDE5 agents affect vascular tone, men with heart disease need particular evaluation. The Princeton Consensus framework for ED and cardiovascular risk helps classify who can safely use PDE5 therapy.
❤️ Princeton Consensus Risk Stratification
LOW RISK — PDE5 inhibitors generally safe
Asymptomatic cardiovascular disease, controlled hypertension, mild stable angina, past uncomplicated MI more than 6-8 weeks ago, mild valvular disease, successful revascularization. These men can usually use PDE5 inhibitors with routine precautions.
INTERMEDIATE RISK — cardiology evaluation first
Three or more cardiovascular risk factors, moderate stable angina, past MI 2-6 weeks ago, heart failure Class II, non-cardiac vascular disease. Need cardiac assessment before PDE5 use. Combination therapy may still be inappropriate even if cleared for single-agent.
HIGH RISK — usually contraindicated
Unstable or refractory angina, uncontrolled hypertension, heart failure Class III-IV, recent MI (less than 2 weeks), high-risk arrhythmia, hypertrophic obstructive cardiomyopathy with symptoms, moderate-to-severe valvular disease. Sexual activity itself is risky; PDE5 inhibitors add to this.
🏃 Exercise Tolerance as Proxy
Sexual activity energy expenditure is comparable to climbing 2 flights of stairs or walking briskly for several minutes. A simple test:
- Can you walk 1 mile at normal pace without chest pain or significant breathlessness?
- Can you climb 2 flights of stairs without stopping?
- Do you tolerate moderate activity (gardening, housework) comfortably?
If yes to these questions and no concerning cardiovascular symptoms, PDE5 inhibitor use is usually appropriate. If no, cardiology evaluation is needed before intimacy regardless of medication.
💊 Specific Cardiovascular Conditions
| Condition | Sildalist Appropriateness |
|---|---|
| Controlled hypertension on single ACE/ARB | Usually appropriate; monitor BP first few doses |
| Stable angina on daily nitrate | Contraindicated. Alternative ED treatment needed. |
| Past MI, stable, more than 6 months ago | Usually appropriate if good exercise tolerance |
| Heart failure Class II | Cardiology input; consider single-agent at low dose first |
| Multiple antihypertensives + alpha-blocker | Caution; consider single-agent at reduced dose rather than combination |
| Significant arrhythmia | Cardiology clearance; depends on specific rhythm issue |
💊 Combination Deserves More Caution
Because Sildalist contains two PDE5 inhibitors with overlapping vasodilatory effects, cardiovascular caution is appropriately higher than for either single agent. Men who tolerate single-agent sildenafil 100 mg or tadalafil 20 mg may still need lower-dose combination or should remain on single agent. For cardiovascular borderline cases, single agent at lowest effective dose is safer than dual therapy.
📊 Common Side Effects From Both Agents
Side effects from Sildalist combination reflect the overlapping profiles of both PDE5 agents. Headache, flushing, nasal congestion, and dyspepsia can come from either sildenafil or tadalafil. Back and muscle pain is more specific to tadalafil. Vision changes are more specific to sildenafil.
📊 Common Side Effect Profile
| Side Effect | Primary Source | Expected Rate |
|---|---|---|
| Headache | Both agents | 12-16% |
| Flushing | Both agents | 10-15% |
| Nasal congestion | Both agents | 4-8% |
| Dyspepsia / heartburn | Both agents | 5-10% |
| Back pain | Tadalafil specific | 4-6% |
| Muscle aches | Tadalafil specific | 3-5% |
| Vision tint (blue haze) | Sildenafil specific | 1-3% |
| Dizziness | Both agents | 2-5% |
| Discontinuation due to side effects | Combined | 3-7% |
🎯 Side Effect Management
Headache
Most common. Acetaminophen or ibuprofen can help. Hydration is important. Usually resolves as the medication clears. If severe or persistent, try single-agent instead.
Flushing
Facial redness and warmth. Expected vascular effect. Not harmful. Usually brief and cosmetic. Cold water, cool environment can help if bothersome.
Nasal congestion
Vascular dilation in nasal passages. Avoid decongestants with pseudoephedrine. Saline nasal spray can help. Resolves as medication clears.
Dyspepsia / heartburn
Take with light meal rather than empty stomach. Antacid may help. Acid reducers (omeprazole, famotidine) are compatible with Sildalist.
Back and muscle pain (tadalafil-specific)
Usually appears 12-24 hours after dose and lasts 24-48 hours. Acetaminophen or ibuprofen can help. If severe or persistent, consider single-agent sildenafil without tadalafil.
Vision changes (sildenafil-specific)
Mild blue tint, brightness, blurring. Usually brief. Any sudden vision loss is a medical emergency — may indicate NAION (non-arteritic ischemic optic neuropathy) and requires immediate care.
🚨 Seek Emergency Care For
- Erection lasting more than 4 hours (priapism) — penile emergency
- Sudden partial or complete vision loss
- Sudden decrease or loss of hearing with ringing or dizziness
- Chest pain, severe palpitations, difficulty breathing
- Severe allergic reaction: facial swelling, throat tightness
- Fainting or severe sustained dizziness
- Severe sustained headache not relieved by usual measures
💊 Side Effects Often Diminish With Experience
The first 2-3 Sildalist doses often cause the most noticeable side effects. Many men acclimate with subsequent uses — headache becomes less, flushing less noticeable, muscle aches milder. For persistent or severe side effects, switching to single-agent therapy is reasonable. The combination is not inherently necessary for most men.
🧠 Mental Health and ED Interaction
Mental health affects both the development of ED and the response to PDE5 therapy. Depression, anxiety, performance pressure, and relationship stress all influence erectile function. Addressing these dimensions alongside medication produces better outcomes than medication alone.
🧠 Mental Health and ED Interaction
Depression as cause and consequence
Depression reduces libido, impairs erection quality through altered neurotransmitter signaling, and reduces interest in intimacy. ED often then worsens depression through self-esteem effects. Treating depression often improves both conditions.
Anxiety and performance pressure
Sympathetic nervous system activation (fight-or-flight) opposes the parasympathetic signaling needed for erection. Performance anxiety becomes self-fulfilling. PDE5 inhibitors break this cycle by providing physiological backup.
Antidepressant medication effects
Many SSRIs (paroxetine, sertraline, fluoxetine) can cause ED and ejaculation changes. The dilemma: untreated depression affects ED; treated depression may cause medication-related ED. PDE5 inhibitors can help bridge this.
Relationship stress
Conflict, communication breakdown, or disconnection often manifest as sexual dysfunction. Couples counseling can address relationship issues; PDE5 inhibitors address the physiological dimension.
🧘 Addressing Mental Health Dimensions
Depression screening
PHQ-9 or similar brief screen. Men with significant depression benefit from treatment (medication, therapy, or both) regardless of ED. Often ED improves with depression treatment.
Sex therapy or couples counseling
Particularly useful for men with psychogenic ED, longstanding relationship patterns, or communication challenges. Sex therapists specialize in sexual dysfunction with evidence-based techniques.
Mindfulness and attention training
Reduces performance anxiety and over-monitoring during intimacy. Growing evidence base for sexual function improvement through mindfulness-based approaches.
Stress management
Chronic stress maintains sympathetic activation that impairs erectile function. Exercise, hobbies, adequate sleep, and relaxation practices all reduce stress physiology.
💊 Combined Approach Works Best
For most men with ED, a combined approach of PDE5 inhibitor plus psychological or lifestyle support produces better and more durable outcomes than medication alone. The medication provides the physiological boost; mental health work addresses the context in which ED developed. Sildalist alone may be adequate for men with purely vascular or neurogenic ED, but mental health factors often matter more than acknowledged.
🧓 Age Considerations and Combination Appropriateness
Age-related considerations with Sildalist combination include medication tolerance, cardiovascular status, and realistic expectations. Older men may have slower absorption, more medications creating interactions, and more cardiovascular comorbidities. Dose adjustments and single-agent consideration often fit better.
🧓 Sildalist Across Age Ranges
| Age Range | Combination Appropriateness | Considerations |
|---|---|---|
| Under 18 | Not indicated | No clinical use case |
| 18-40 | Rarely needed | ED usually psychogenic; address root cause first |
| 40-55 | Reasonable for specific scenarios | After single-agent trial; address CV risk factors |
| 55-70 | Needs individual assessment | More medications, CV workup, dose consideration |
| 70-80 | Single-agent usually preferred | Sildenafil 25-50 mg or tadalafil 5-10 mg instead |
| 80+ | Combination usually not appropriate | Low-dose single agent with cardiology input |
👉 Why Older Men Need More Caution
Reduced hepatic clearance
Older men often have slower CYP3A4 metabolism, prolonging blood levels of both agents. Starting with lower-dose single agent is prudent.
More cardiovascular medications
Multiple antihypertensives, nitrates (contraindicated), alpha-blockers for BPH. Each raises interaction risk with PDE5 inhibitors.
Orthostatic hypotension risk higher
Baroreflex response diminishes with age. Fall risk from dizziness significantly higher. Fractures can be serious.
Different ED picture
Older men more often have significant vascular ED and may need higher PDE5 doses, but also more comorbidities that limit safe dosing. Nuanced balance required.
💊 Older Men Often Fit Single-Agent Better
For men over 65-70, starting with single-agent sildenafil 25-50 mg or tadalafil 5 mg daily is typically safer than combination. If response is inadequate at optimal single-agent dose, careful cardiology evaluation and discussion with urology may support cautious combination use. First-time combination use in older age without this stepped approach is risky.
🤝 Foreplay and Sexual Stimulation Role
Foreplay and sexual stimulation remain essential for PDE5 inhibitor effect. Many men mistakenly expect automatic erection from the medication. In practice, both sildenafil and tadalafil require sexual arousal to trigger the nitric oxide pathway that the drugs amplify.
🤝 Why Sexual Stimulation Matters
PDE5 inhibitors amplify, not initiate
The medication enhances the body's natural erection response but does not create the response from nothing. Without sexual arousal signaling, there is no cGMP to protect from degradation.
Mental and physical arousal both needed
Visual, verbal, mental, and tactile stimulation all contribute to arousal. The combination of all these inputs produces the strongest response. Mechanical stimulation without mental arousal often fails.
Partner engagement important
A partner who is engaged, attracted, and interactive provides stronger arousal input than one who is distracted or passive. Mutual investment improves outcomes substantially.
Age-related arousal changes
Older men typically need more direct tactile stimulation to achieve full arousal. The medication supports response once arousal occurs, but foreplay time usually increases with age. This is normal, not treatment failure.
💭 Practical Approaches
Allow adequate foreplay time
Rushing to intercourse without foreplay often reduces arousal and medication effectiveness. 15-30 minutes of focused intimacy allows the medication to work with the natural response.
Reduce distractions
Phone off, children settled, work stress set aside. Attention on the partner and the moment supports arousal.
Sensate focus exercises
Structured touching exercises that remove performance pressure. Masters and Johnson developed this technique for ED. Guided by sex therapist or self-directed from reputable resources.
Open partner communication
What feels good, what works, what the partner enjoys. Direct conversation improves arousal more than guessing. Many couples benefit from this communication regardless of ED.
💊 Medication Plus Context
PDE5 inhibitors work within the context of sexual stimulation, arousal, and partner engagement. The medication is a pharmacologic support, not a replacement for the physiological and relational elements of intimacy. Many apparent "medication failures" are actually situations where insufficient arousal input prevented the drug from working on its intended target.
🏃 Lifestyle Factors Supporting Vascular Response
Lifestyle factors affect both ED risk and PDE5 inhibitor effectiveness. Cardiovascular health, metabolic status, exercise, sleep, and substance use all influence erectile function. Addressing these factors supports Sildalist response and improves durable outcomes.
🏃 Lifestyle Factors Affecting ED
🏋️ EXERCISE
Regular aerobic activity 150+ min weekly improves vascular endothelial function. Associated with better erectile function in population studies. Compounds with PDE5 benefit.
⚖️ WEIGHT MANAGEMENT
Obesity worsens ED through metabolic, vascular, and testosterone pathways. Even 5-10% weight loss improves erectile function in men with obesity.
🚬 SMOKING
Direct vascular damage. Quitting improves erectile function within months. Men who continue to smoke have reduced PDE5 inhibitor response compared to non-smokers.
😴 SLEEP
Sleep apnea increases ED risk through nocturnal hypoxia and vascular effects. Treatment with CPAP improves erectile function in affected men.
🍰 DIET
Mediterranean-style diet associated with better erectile function. Vegetables, fish, olive oil, whole grains support vascular health.
🧘 STRESS
Chronic stress worsens ED through sympathetic activation. Stress management (mindfulness, exercise, hobbies) supports erectile function.
🍃 Substance Considerations
Alcohol
Heavy use directly impairs erection. Combined with Sildalist raises orthostatic risk. Moderate use OK but limit.
Cannabis
Mixed evidence — some men report arousal enhancement, others report ED. No major interaction with PDE5 inhibitors but can affect baseline sexual function. Men who use regularly should mention to prescriber.
Amyl nitrite ("poppers")
Absolutely contraindicated with any PDE5 inhibitor including Sildalist. Same mechanism as nitrates for angina. Life-threatening hypotension possible.
Opioids
Long-term opioid use suppresses testosterone and can cause ED. Prescription opioid use should be mentioned when evaluating ED. PDE5 inhibitors can still work but underlying cause worth addressing.
💊 Lifestyle Amplifies Medication Benefit
Men who exercise regularly, maintain healthy weight, do not smoke, and manage cardiovascular risk factors consistently respond better to PDE5 inhibitors than men with poor cardiovascular health. The medication works best when the underlying vascular biology is supported. Lifestyle improvements rarely show immediate dramatic ED resolution but build the foundation for durable response.
🧪 Hormonal Workup When Indicated
Hormonal evaluation is appropriate for men with ED and specific features suggesting endocrine contribution. Not every man with ED needs hormonal workup, but men with low libido, fatigue, decreased morning erections, or inadequate response to PDE5 should have testosterone and related tests.
🧪 When Hormonal Workup Makes Sense
Low libido with ED
If sexual desire is reduced along with erection problems, testosterone deficiency is more likely. Pure vascular ED usually preserves libido.
Fatigue, mood changes, muscle loss
Classic hypogonadism symptom cluster. Low energy, depression, reduced muscle mass, increased body fat. Testosterone testing appropriate.
Decreased morning erections
Natural morning erections are testosterone-dependent. Absence over months suggests either low testosterone or significant vascular ED. Testosterone test clarifies.
Inadequate PDE5 response
Men not responding well to maximum PDE5 doses often have untreated hypogonadism. Testosterone replacement combined with PDE5 inhibitor restores response in some men.
📋 Appropriate Hormonal Workup
| Test | Purpose |
|---|---|
| Morning total testosterone | Hypogonadism screen; drawn 7-11 AM |
| Free testosterone (if total borderline) | More accurate in obesity, aging; SHBG adjustment |
| LH, FSH (if testosterone low) | Distinguish primary vs secondary hypogonadism |
| Prolactin (if symptoms suggest) | Pituitary adenoma screen with specific indicators |
| TSH | Thyroid dysfunction can affect sexual function |
| PSA (age 40+ with risk factors) | Baseline before any potential testosterone treatment |
🔧 Addressing Hormonal Issues
If testing identifies hormonal contributors:
- Low testosterone: Testosterone replacement therapy (injections, gel, pellets). Improves libido more reliably than erection. Often combined with PDE5 inhibitor
- Elevated prolactin: Dopamine agonist medication; MRI pituitary if adenoma suspected
- Thyroid dysfunction: Hormone replacement for hypothyroid; antithyroid for hyperthyroid
- Testosterone treatment plus PDE5: Many men need both — testosterone restores libido, PDE5 restores erection
- Monitoring on testosterone: Hematocrit, PSA, blood pressure annually at minimum
💊 Hormonal Workup Fits Specific Scenarios
Most men with ED and intact libido do not need extensive hormonal workup. But men with the specific pattern of low libido + reduced energy + poor PDE5 response deserve testing. Addressing underlying hypogonadism often resolves the inadequate PDE5 response without needing combination therapy escalation.
🧫 CYP3A4 Metabolism and Drug Interactions
CYP3A4 is the primary metabolism pathway for both sildenafil and tadalafil. Drugs that modify this enzyme significantly change blood levels of both agents in Sildalist combination. Understanding the interactions prevents dangerous accumulation or inadequate response.
🧫 CYP3A4 and PDE5 Clearance
Both agents are CYP3A4-dependent
Sildenafil and tadalafil are both metabolized primarily by CYP3A4 in the liver. CYP3A4 modulators affect both agents in the combination.
Inhibitors raise blood levels
CYP3A4 inhibitors reduce clearance, raising peak and total exposure. Side effect risk and interaction potency increase. May require dose reduction or alternative treatment.
Inducers lower blood levels
CYP3A4 inducers accelerate clearance, reducing peak and total exposure. May lead to inadequate response. Alternative treatments or higher doses may be needed.
🔒 CYP3A4 Inhibitors
Strong inhibitors — avoid combination
Ketoconazole, itraconazole, posaconazole, voriconazole (antifungals). Ritonavir, saquinavir, nelfinavir, atazanavir, darunavir (HIV protease inhibitors). Clarithromycin, telithromycin (antibiotics). Nefazodone. Can double or triple PDE5 blood levels.
Moderate inhibitors — use with caution
Erythromycin, fluconazole, diltiazem, verapamil, aprepitant, cimetidine (large doses). Grapefruit and grapefruit juice. Consider single-agent at lower dose rather than combination.
Mild inhibitors — usually safe
Low-dose cimetidine (not routinely used), ciprofloxacin. Minor effect, usually not clinically significant.
🔓 CYP3A4 Inducers — Reduce Effectiveness
Rifampin (antituberculosis)
Strong inducer. Significantly reduces PDE5 blood levels. May render Sildalist ineffective. Alternative ED treatment during rifampin course.
Antiepileptic medications
Carbamazepine, phenytoin, phenobarbital. CYP3A4 inducers that reduce PDE5 effectiveness. Men on these medications may need higher PDE5 doses or alternative treatments.
St John's wort
Herbal CYP3A4 inducer. Reduces PDE5 effectiveness. Men should mention herbal supplement use to prescriber.
💊 Pharmacy Review Essential
Before first use, a pharmacist review of all current medications catches CYP3A4 interactions that general prescribing may miss. Antifungals, HIV medications, and some antibiotics commonly interact. Even seemingly minor over-the-counter supplements like St John's wort can affect PDE5 metabolism. A brief 10-minute pharmacy consultation prevents problems.
📋 ED Workup and IIEF Measurement
ED diagnosis and workup establishes the clinical context for PDE5 therapy. A systematic approach distinguishes vascular, neurogenic, hormonal, and psychogenic contributors. This matters because the right treatment approach depends on the actual cause.
📋 IIEF Questionnaire
The International Index of Erectile Function (IIEF) is the standard measurement instrument developed by Prof. Raymond Rosen and colleagues. The 5-question shortened version (IIEF-5 or SHIM) screens for ED severity:
- Confidence in ability to get and keep erection
- Firmness of erection for sexual activity
- Maintenance of erection after penetration
- Ability to maintain erection to completion of intercourse
- Satisfaction with sexual intercourse
Each item scored 1-5. Total score interpretation:
- 22-25: No ED
- 17-21: Mild ED
- 12-16: Mild-to-moderate ED
- 8-11: Moderate ED
- 5-7: Severe ED
🏥 Clinical Workup Elements
History
Onset (gradual vs sudden), context (situational vs global), presence of morning erections, libido status, relationship factors, prior PDE5 trial response. Guides workup priority.
Medical history
Cardiovascular risk factors, diabetes, hypertension, prior surgeries (prostate, pelvic), neurological conditions, mental health, substance use.
Medication review
Antihypertensives (some cause ED), antidepressants (SSRIs commonly), antihistamines, cold medications. Critical for PDE5 interaction assessment.
Physical examination
Blood pressure, heart rate, waist circumference, visual assessment of genitalia, prostate exam if indicated, peripheral vascular assessment.
Laboratory testing
Fasting glucose, HbA1c, lipid panel, testosterone (if hypogonadism suspected), basic metabolic panel. PSA based on age and risk factors.
🔍 Specialized Testing When Indicated
- Nocturnal penile tumescence testing: distinguishes psychogenic from organic ED (rarely needed in clinical practice)
- Penile Doppler ultrasound: evaluates arterial inflow and venous outflow; useful before penile injection or surgical intervention
- Cavernosography / cavernosometry: specialized tests for venous leak evaluation
- Prostate MRI: if PSA abnormal or specific prostate concern
- Cardiac stress testing: for men with cardiovascular risk requiring intermediate risk assessment
💊 Diagnosis Guides Treatment Choice
Men with mostly psychogenic ED may respond well to single-agent sildenafil used to break the anxiety cycle. Men with significant vascular ED and partial single-agent response may benefit from combination. Men with hormonal ED need testosterone replacement in addition to or instead of PDE5. The workup clarifies which approach fits.
📈 Monitoring Treatment Response Over Attempts
Monitoring Sildalist response requires tracking IIEF or satisfaction over multiple attempts. Single-attempt judgments are unreliable — medication timing, meal content, arousal, and anxiety all affect individual experiences. Structured assessment over 4-6 attempts tells the real story.
📈 What to Track
💡 ERECTION QUALITY
Firmness, maintenance through intercourse. 1-5 scale. Target: improvement by at least 2 points.
⏰ ONSET TIMING
How long after dose until effect noted. Should be 30-60 min with sildenafil component.
📅 DURATION
How long effect lasts after dose. Should extend well into next day due to tadalafil component.
😊 SATISFACTION
Overall intercourse satisfaction including partner. 1-5 scale. Target: improvement.
💡 CONFIDENCE
Expectation of successful intercourse. Grows with repeated success. Target: visible improvement over attempts.
😔 SIDE EFFECTS
Which effects, severity, duration. Typically decreasing trend with repeated use.
🔄 Response Patterns and Next Steps
| Pattern After 4-6 Attempts | Recommended Next Step |
|---|---|
| Good response, tolerable side effects | Continue; consider stepping down to single-agent |
| Good response but side effects limiting | Switch to single-agent sildenafil or tadalafil at optimal dose |
| Partial response at timing well-managed | Hormonal workup; consider testosterone deficiency |
| No response despite good conditions | Comprehensive ED workup; consider alternative treatments (injections, pumps, surgery) |
| Severe side effects | Discontinue; non-oral alternatives (alprostadil injection or urethral) |
💊 Multiple Attempts Needed for Fair Assessment
The initial response to any PDE5 inhibitor often improves with the second to fourth attempts as both the man and partner adapt. Give Sildalist 4-6 fair attempts at correct timing, appropriate meal, adequate arousal, and modest alcohol before concluding it does not work. Many apparent failures become successes with proper setup.
🏥 Managing Side Effects Including Emergency Signs
Managing Sildalist side effects involves practical strategies for the common PDE5 effects, awareness of serious warning signs, and knowing when to switch approach. Most side effects are manageable; a few are medical emergencies requiring immediate action.
🏥 Side Effect Response Strategies
Headache (most common)
Acetaminophen 500-1000 mg before or at onset. Hydration is essential. For persistent headache, step down to single-agent (sildenafil 50 mg or tadalafil 10 mg) to reduce overall dose.
Flushing
Expected vascular effect. Not harmful but cosmetically bothersome. Cool environment, cold drink can help. Resolves within hours. If severe, consider single-agent at lower dose.
Nasal congestion
Saline nasal spray. Avoid decongestants with pseudoephedrine (vasoconstrictor interaction). Usually resolves within hours. Rarely persistent beyond 24 hours.
Dyspepsia / heartburn
Take with light meal. Antacid (calcium carbonate) can help acute symptoms. Men with chronic reflux may benefit from omeprazole or famotidine around medication use.
Back and muscle pain
Specifically from tadalafil component. Appears 12-24 hours after dose. Acetaminophen or ibuprofen. Hot shower or heating pad. If significant, switch to single-agent sildenafil without tadalafil.
Vision changes
Mild blue haze, brightness, or blurring from sildenafil component. Usually brief and benign. Any sudden vision loss is NAION emergency — immediate care.
Dizziness or lightheadedness
Rise slowly from seated/supine positions. Hydration. Avoid combining with alcohol or multiple antihypertensives. If severe or recurrent, consider discontinuation.
🚨 Emergency Signs Requiring Immediate Care
Priapism — erection lasting 4+ hours
Prolonged erection without arousal, or persisting far beyond intercourse. Painful or non-painful. Permanent tissue damage if not treated within 6-8 hours. Emergency room immediately.
Sudden vision loss (NAION)
Non-arteritic ischemic optic neuropathy. Rare but serious. Partial or complete vision loss, often one eye, usually painless. Discontinue medication and seek care immediately.
Sudden hearing loss
Sometimes with ringing (tinnitus) or dizziness. Rare but documented. Discontinue and seek care within 24 hours for best recovery chance.
Chest pain or heart attack symptoms
Chest pressure, pain radiating to arm or jaw, severe shortness of breath. Call emergency services. Tell providers about Sildalist use — this changes nitrate use decisions.
Severe allergic reaction
Facial or throat swelling, difficulty breathing, severe rash. Emergency care immediately.
💊 Most Side Effects Resolve Within Hours
The vast majority of Sildalist side effects are mild, resolve within hours, and do not recur with experience. The rare serious events (priapism, NAION, cardiovascular events) are the medical emergencies. Knowing the warning signs allows quick response if these occur. For non-emergent side effects, management strategies and dose adjustments usually resolve the issue.
🚨 Priapism Warning Signs and Emergency Response
Priapism is a penile medical emergency — prolonged erection without sexual arousal, or persisting far beyond intercourse. Though rare with PDE5 inhibitors, the risk is slightly elevated with combination therapy. Rapid recognition and emergency treatment prevent permanent tissue damage.
🚨 What Priapism Is
Prolonged erection without arousal
Erection lasting more than 4 hours regardless of sexual activity. Can be painful or painless. Must be addressed urgently.
Ischemic (low-flow) priapism most common
Blood is trapped in corpora cavernosa, oxygen depletion begins. If untreated beyond 6-8 hours, permanent tissue damage and ED can result.
PDE5 priapism rare but documented
Occurs in less than 0.1% of PDE5 inhibitor users. Risk slightly higher with combination therapy and in men with sickle cell disease, leukemia, or multiple myeloma.
🛑 Immediate Response Protocol
If erection persists 2+ hours after intercourse or begins without sexual activity:
- Walk, climb stairs, or jog if not uncomfortable (may redirect blood flow)
- Take a cool shower (not cold — cold can increase bleeding risk)
- Urinate
- If erection persists 4 hours total: go to emergency room immediately
- Do not drive if dizzy — have someone drive you
- Tell the ER you took Sildalist (sildenafil + tadalafil)
- Do not take another PDE5 inhibitor dose
Timeline for intervention matters:
- Under 4 hours: usually resolves without intervention
- 4-6 hours: aspiration + alpha-adrenergic injection usually effective
- 6-12 hours: becoming urgent; higher permanent damage risk
- 12+ hours: significant risk of permanent ED and tissue necrosis
- 24+ hours: often requires surgical shunt
🛡️ Risk Factors
Sickle cell disease or trait
Highest risk group. PDE5 inhibitor use requires specialist counseling about priapism risk.
Blood cancers (leukemia, multiple myeloma)
Hematologic malignancies can predispose to priapism. Discuss PDE5 use with oncologist.
Prior priapism episode
Any prior priapism, from any cause, raises recurrence risk. PDE5 use should be cautious with specific prescriber discussion.
Combination therapy (dual PDE5)
Theoretical risk slightly higher than single-agent. Though overall still rare, this is one reason single-agent is preferred for most men.
Penile injection therapy
Alprostadil penile injections carry much higher priapism risk than oral PDE5 inhibitors. Men who use both should be especially cautious.
💊 Rare But Important
Priapism with PDE5 inhibitors is rare but genuinely occurs. Men should know the warning signs, timeline for emergency intervention, and the 4-hour threshold. Awareness allows rapid response that preserves penile tissue and future erectile function. The small risk is one reason to use the lowest effective dose and consider single-agent therapy over combination when possible.
⚖️ Comparing PDE5 Inhibitors and Combination Approach
Four oral PDE5 inhibitors are available: sildenafil, tadalafil, vardenafil, and avanafil. Each has distinct pharmacokinetics and clinical profile. Understanding how combination compares to single-agent therapy helps men and prescribers select the right approach.
⚖️ PDE5 Inhibitor Comparison
| Agent | Onset | Duration | Notable Features |
|---|---|---|---|
| Sildenafil 50-100 mg | 30-60 min | 4-6 hrs | Food-sensitive; most studied |
| Tadalafil 10-20 mg (on-demand) | 1-2 hrs | 24-36 hrs | Long window; food-independent |
| Tadalafil 2.5-5 mg daily | Continuous | 24/7 | Steady-state coverage; spontaneity |
| Vardenafil 10-20 mg | 25-60 min | 4-5 hrs | Similar to sildenafil; QT caution |
| Avanafil 100-200 mg | 15-30 min | 6 hrs | Fastest onset; newer; limited data |
| Sildalist combination | 30-60 min | Up to 36 hrs | Fast onset + extended window |
🎯 Matching Agent to Preference
Fast onset priority: sildenafil, avanafil, or Sildalist
For men wanting medication that works within 30-60 minutes. Avanafil fastest but less experience. Sildenafil most studied. Sildalist combines fast and long.
Long window priority: tadalafil or Sildalist
For men wanting 24-36 hour spontaneity. Weekend getaways, uncertain intimacy timing. Tadalafil alone usually sufficient; Sildalist adds fast initial onset.
Daily use priority: tadalafil daily
Low-dose tadalafil 2.5-5 mg daily provides steady-state coverage. Spontaneity without planning. May also help BPH symptoms. Best for frequent intimacy.
Food-flexible priority: tadalafil, avanafil, or Sildalist
For men whose intimacy often follows dinner. Tadalafil and avanafil work regardless of meal. Sildalist works but sildenafil component is affected by fatty meal.
💊 Combination vs Optimized Single Agent
For most men, a trial of single-agent at optimal dose is the appropriate first approach. Only after exhausting single-agent options should combination therapy be considered. Many men who think they need combination actually need better timing, higher single-agent dose, or treatment of underlying hormonal or cardiovascular issues. Combination is a specific tool for specific scenarios, not a universal upgrade.
💰 Cost Considerations and Economical Alternatives
Sildalist combination is typically more expensive than single-agent generic but still much less than brand Viagra or Cialis. Understanding cost options allows men to choose cost-effective PDE5 therapy without unnecessary expense.
💰 Cost Context
Brand Viagra and Cialis expensive
Pfizer brand Viagra and Lilly brand Cialis typically cost significantly more per pill than generic equivalents. US retail prices particularly high.
Generic sildenafil and tadalafil much cheaper
Both agents are off-patent. Generic versions cost a fraction of brand price. For many men, generic single-agent is the most cost-effective choice.
Sildalist combination intermediate cost
Combines two agents in one tablet. Not FDA approved as fixed-dose; produced by Indian generic manufacturers. Costs more than single-agent generic but less than brand combinations.
Insurance coverage variable
Many US insurance plans do not cover ED medications. Those that do often have significant copays. International markets have variable coverage. Many men pay out of pocket.
📊 Cost-Reduction Strategies
Try generic single-agent first
Generic sildenafil 50-100 mg or tadalafil 10-20 mg typically works well and is substantially cheaper than combination.
Occasional vs daily use decision
For infrequent intimacy, on-demand single-agent is most economical. For frequent intimacy, tadalafil 5 mg daily may be more cost-effective than multiple on-demand doses.
Pharmacy price comparison
PDE5 inhibitor prices vary dramatically between pharmacies. Online price comparison tools reveal substantial differences in local pricing.
Multi-pack ordering
Larger quantities often reduce per-pill cost. PDE5 inhibitors have 3+ year shelf life, making bulk purchase practical.
Discount programs and coupons
Pharmacy discount programs (GoodRx, SingleCare, Amazon Pharmacy) can reduce out-of-pocket costs significantly for PDE5 inhibitors.
💊 Cost-Effective Approach
For most men, generic single-agent sildenafil or tadalafil at optimal dose is the most cost-effective PDE5 approach. Combination Sildalist adds cost without clear advantage for most men. Reserve combination for specific preferences or situations where single-agent clearly does not suffice.
✈️ Travel Planning and Vacation Use
Travel with Sildalist requires attention to legal status, time zone adjustment, and planning around the extended tadalafil window. The combination is prescription-only in most countries and may face customs scrutiny. Thoughtful planning prevents problems.
✈️ Legal Status Worldwide
- Sildenafil and tadalafil separately: approved in nearly all countries; prescription required
- Sildalist combination: not approved as fixed-dose in US, EU, Canada, Australia; approved and widely available in India
- Personal import: men traveling with Sildalist from India should carry prescription documentation; small personal quantities usually not challenged
- Specific country regulations vary: some Middle Eastern and Asian countries have strict medication import rules; check destination before travel
🧳 Travel Packing
Prescription documentation
Original pharmacy label or prescription letter. Keep tablets in original bottle. International travel especially important.
Reasonable quantity
Trip supply plus 50% extra. Carrying large quantities (hundreds of pills) can raise customs questions.
Carry in hand luggage
Essential medications belong in hand luggage. Checked bags can delay or be lost.
Standard storage
Room temperature stable. Avoid extreme heat (closed car in sun). Protect from humidity.
🌍 Travel-Specific Considerations
Jet lag and dose timing
Sildalist is on-demand medication — take 30-60 minutes before planned intimacy in local time. No complex adjustment needed. The 36-hour tadalafil window means timing is forgiving.
Alcohol-heavy travel destinations
Beach vacations, wine country, cruise ships. Combination tolerates less alcohol than either single agent. Limit to 1 drink around dosing time.
New environment orthostatic risk
Unfamiliar hotel room, dehydration from travel. Rise slowly, hydrate thoroughly. First dose at destination best when well rested.
High-altitude travel
Mountain destinations above 2500m may affect sexual function through hypoxia. PDE5 inhibitors still work. Hydration especially important.
Long flights
Dehydration from air travel. Hydrate well before dose. Avoid combining Sildalist with excess alcohol on the flight.
💊 Avoid First-Time Use on Vacation
If this is your first time trying Sildalist, do not take the first dose in an unfamiliar destination. Try the medication at home first to know how you respond. Then on vacation, the combination is a known quantity rather than an unknown with potential side effects far from home.
💬 Partner Communication About ED and Treatment
Partner communication about ED and PDE5 therapy significantly affects both relationship quality and treatment success. Many men hesitate to discuss ED with partners, which worsens anxiety and reduces outcomes. Open conversation usually improves both the relationship and the medication effectiveness.
💬 What Partners Benefit From Knowing
ED is physiological, not about attraction
Partners often wonder if ED reflects reduced attraction. The straightforward answer: ED is a vascular, nerve, or hormonal issue independent of attraction. Direct conversation usually reassures.
What the medication does
PDE5 inhibitor supports erection response but requires sexual arousal to work. Partner engagement and participation matter.
Timing considerations
30-60 minute window after dose for best onset. Avoid heavy fatty meal. 36-hour effect from tadalafil component allows spontaneity.
Possible side effects to notice
Flushing, headache usually harmless. Significant dizziness, chest pain, prolonged erection, vision changes are emergencies.
🤝 Having the Conversation
Choose non-sexual moment
Not during intimacy or immediately before. A calm, relaxed context — evening together, after dinner, during a walk.
Lead with how you feel
"I have been having some issues with erections and it bothers me. I want our intimacy to be as good as possible. I am going to try a medication called Sildalist."
Explain simply
ED is a common medical issue, often with vascular causes. Medication supports the natural response. Takes about 30-60 minutes to work, lasts about 24-36 hours.
Invite partner input
"How do you feel about this? Is there anything that would make intimacy better for you?" Partners usually welcome being part of the discussion.
🌟 What Changes with Combination Therapy
- Longer window of effect — up to 36 hours allows spontaneity across a weekend or special event
- Fewer timing worries — the extended tadalafil component reduces pressure to perform within a short window
- Side effects possible both agents — partner awareness of warning signs is helpful
- Minimum 72 hours between doses — this is a longer-interval medication than daily use
- Expectations should remain realistic — combination is support, not transformation
💊 Partners Usually Welcome Openness
Men often fear partner reaction more than reality warrants. In practice, partners typically respond with support and practical interest rather than criticism or disappointment. Secrecy about ED and medication creates anxiety and sometimes misinterpretation; openness reduces anxiety and allows both partners to participate in making intimacy work well.
🔧 Troubleshooting Inadequate Response
Troubleshooting Sildalist response involves systematic review of dose, timing, expectations, and underlying contributors. Many apparent failures turn out to be issues of context rather than medication inadequacy. Working through troubleshooting steps before switching treatments is almost always worth doing.
🔧 Common Problems and Solutions
Problem: inadequate response first attempt
Solution: this is common. Give 4-6 attempts at proper timing, light meal, modest alcohol, good arousal context. Many apparent failures become successes with better conditions.
Problem: timing seems off
Solution: take 30-60 minutes before planned intimacy. If heavy meal planned, take 2 hours before. Avoid taking immediately before (not enough time) or far ahead (sildenafil clearing).
Problem: good at first, less effective later
Solution: assess whether something changed — new medication, more alcohol, increased stress, weight gain, hormonal change. Check testosterone if libido reduced.
Problem: side effects limiting use
Solution: step down to single-agent. Sildenafil alone or tadalafil alone at lower dose. Reduces overall vascular effect while keeping ED treatment.
Problem: expectations not met
Solution: PDE5 inhibitors support response; they do not restore the function of a 20-year-old. Realistic expectations — firm functional erections, satisfactory intercourse — usually achievable. Perfection often not.
Problem: inadequate at any PDE5 dose
Solution: comprehensive ED workup. Hormonal, vascular, nerve testing. Consider penile injections (alprostadil), vacuum erection device, or penile implant surgery for refractory ED.
🎯 Alternative Approaches When PDE5 Insufficient
Alprostadil penile injection
Direct smooth muscle relaxation. Works regardless of nitric oxide pathway. 80-85% response rate. Higher priapism risk; self-injection technique required.
Alprostadil urethral suppository
Non-injection option. Lower response rate than injection but no needle. Transurethral delivery.
Vacuum erection device
Mechanical device creates vacuum, draws blood into penis. Constriction ring maintains erection. Non-medication option; some couples find device acceptable.
Penile implant surgery
For men with severe refractory ED. Inflatable or malleable prostheses. High patient and partner satisfaction. Permanent and definitive but surgical.
💊 Troubleshooting Pays Off
Many men abandon PDE5 therapy after 1-2 disappointing attempts. Systematic troubleshooting — proper timing, meal awareness, alcohol limit, good arousal, adequate attempts — often identifies the limiting factor. Fixing that factor allows the medication to work. Only after this review has been done is it reasonable to conclude Sildalist does not fit and move to alternatives.
📅 Long-Term Outcomes and Safety Evidence
Long-term outcomes with PDE5 inhibitors are well established through decades of use. Sildenafil has been in use since 1998 and tadalafil since 2003 — both agents in Sildalist have extensive safety and effectiveness data. Combination use shares this safety profile.
📅 Long-Term Data Summary
25+ years sildenafil experience
Massive post-marketing experience since 1998. No major new safety signals have emerged over this long follow-up. Side effect profile remains stable.
20+ years tadalafil experience
Approved 2003. Long-term safety confirmed. Daily low-dose use (2.5-5 mg) also studied extensively. Favorable safety profile.
No tolerance development
Unlike some medications, PDE5 inhibitors do not develop tolerance with continued use. Men can use same dose for years without needing escalation.
No cardiovascular risk increase
Despite initial concerns, long-term follow-up shows no increase in heart attack or stroke risk with PDE5 inhibitor use. In fact, some studies suggest cardiovascular benefit through improved endothelial function.
🎯 What Long-Term Use Looks Like
- Years of continued effectiveness: same dose typically works as well year 5 as year 1
- Decreasing side effect sensitivity: men often experience fewer side effects with continued use
- Confidence restoration: regular use breaks performance anxiety patterns, often improving spontaneous function
- Relationship benefit: sustained intimacy supports partnership quality
- Possible cardiovascular protection: some evidence of endothelial function improvement from regular PDE5 use
- Potential discontinuation: some men with purely psychogenic ED may not need medication long-term
🔄 Reassessment Over Time
Annual medical review
Cardiovascular status, medication list reconciliation, side effects assessment, continued response verification.
Dose optimization
Consider whether combination still needed or whether single-agent at optimal dose would be sufficient. Many men on combination can step down.
Life circumstances changes
New partner, change in frequency, new medications, new health conditions — each warrant reassessment of treatment approach.
Cardiovascular risk evolution
Aging may bring new cardiac issues. New angina or heart failure diagnosis may contraindicate nitrates, requiring PDE5 reassessment.
💊 Well-Studied Long-Term Safety
PDE5 inhibitors are among the most studied medications in all of urology. The combination of extensive clinical trials and 20+ years of post-marketing experience provides strong reassurance about long-term safety. Men on Sildalist can expect sustained benefit without emerging unexpected safety issues.
❌ Common Myths About PDE5 Inhibitors
Myths and misconceptions about PDE5 inhibitors often lead men to use them incorrectly, decline treatment, or hold false expectations. Separating fact from fiction supports better decisions and outcomes.
❌ Myths vs Reality
Myth: PDE5 inhibitors cause erection automatically
Reality: Both sildenafil and tadalafil require sexual arousal to produce erection. The medication amplifies the natural response; it does not create response from nothing.
Myth: combination is twice as effective as single-agent
Reality: PDE5 inhibition at maximum single-agent dose is already essentially complete. Combination offers kinetic flexibility (fast + long), not doubled potency. For most men, optimized single-agent works as well.
Myth: once ED starts, you need the pill forever
Reality: Some ED is reversible (lifestyle, cardiovascular treatment, mental health, hormonal). PDE5 inhibitors do not cause dependence. Many men who address underlying contributors can reduce or stop medication.
Myth: PDE5 inhibitors cause heart attack
Reality: Long-term follow-up shows no increase in heart attack risk. The deaths associated with PDE5 inhibitors are usually from either sexual activity itself (physical exertion) or nitrate interactions. Medication alone does not raise cardiac event risk.
Myth: taking more pills works better
Reality: Maximum single tablet dose. Taking two doses raises side effects without improving effect. Tadalafil especially requires 72-hour interval between doses.
Myth: natural supplements work as well
Reality: Rigorous studies of yohimbine, L-arginine, horny goat weed, and similar supplements show minimal to no benefit for ED. Herbal supplements marketed for ED often contain undisclosed PDE5 inhibitors or other active ingredients with no quality control.
Myth: ED means you are not attracted to partner
Reality: ED is predominantly physiological (vascular, nerve, hormonal) rather than attraction-related. Partners who understand this are relieved. Treatment supports the physiology; attraction itself is a separate dimension.
✅ Established Realities
PDE5 inhibitors are effective
60-80% of men respond to appropriate PDE5 therapy with proper timing and context.
ED often indicates cardiovascular risk
ED precedes cardiac symptoms by 3-5 years. Treatment opportunity for cardiovascular prevention.
Lifestyle improvements amplify medication benefit
Exercise, weight loss, smoking cessation, diabetes control all improve response.
Nitrate interaction is real and dangerous
The single most important safety consideration. Absolute contraindication must be respected.
💊 Information Supports Good Decisions
Men who approach ED treatment with accurate information make better decisions about whether to use PDE5 inhibitors, which agent fits best, and how to maximize effectiveness. Myths lead to inappropriate use or unnecessary avoidance. Clear information supports realistic expectations and good outcomes.
🛑 Stopping Sildalist and Clean Discontinuation
Stopping Sildalist is simple because PDE5 inhibitors are on-demand medications. There is no withdrawal, no tapering, no rebound effect. Men can stop any time without physiological consequences. The clinical decision to stop usually relates to changed circumstances rather than medication issues.
🛑 How to Stop Sildalist
Simply stop using it
No tapering needed. Discontinuation is straightforward. The sildenafil component clears within 24 hours; tadalafil clears over about 5 days.
No withdrawal syndrome
PDE5 inhibitors are not addictive. No physiologic dependence. Discontinuation produces no symptoms.
ED returns to baseline
The medication supports erection during the active window. Discontinuation means return to pre-treatment ED pattern. For sustained improvement, continued use is necessary.
Plan alternative if BPH symptoms
For men who were on tadalafil daily for both BPH and ED, discontinuation of PDE5 may affect urinary symptoms. Plan transition carefully.
🎯 When Stopping Makes Sense
New nitrate medication
If prescribed nitrates for cardiac condition, PDE5 inhibitors become contraindicated. Discontinue permanently and discuss alternative ED management.
Significant adverse event
NAION, hearing loss, priapism, severe allergic reaction. Permanent discontinuation. Alternative ED approaches needed.
No need (ED resolved)
Some men whose ED was situational, psychogenic, or related to reversible factors (weight loss, cardiovascular treatment, depression resolution) may no longer need medication.
Switch to different approach
Moving to single-agent at optimal dose, penile injection, vacuum device, or implant. Discontinue combination for alternative.
End of life planning
In palliative care context, ED medications may be discontinued as treatment goals shift.
💊 Clean Stop Pattern
PDE5 inhibitor discontinuation is among the simplest medication stops in all of medicine. No withdrawal, no complex management, no monitoring needed after stop. Men can start, stop, and restart as circumstances change. This flexibility is one practical advantage of on-demand ED treatment.
👨⚕️ Men Health Coexisting Conditions and Prevention
Men's overall health in the ED age range (typically 40+) involves cardiovascular health, metabolic status, hormonal balance, mental health, and preventive care. Addressing the whole picture supports better ED outcomes and catches other important issues.
👨⚕️ Common Coexisting Conditions
Hypertension
Very common and worsens ED through vascular effects. Control supports response to PDE5. Some BP medications contribute to ED (beta-blockers, thiazide diuretics); others neutral or helpful.
Diabetes
Significantly increases ED risk through vascular and nerve effects. Glycemic control improves response to PDE5 inhibitors. HbA1c monitoring important.
Dyslipidemia
High cholesterol contributes to vascular ED. Statin therapy may actually improve ED through endothelial function. Lipid management supports PDE5 response.
Benign prostatic hyperplasia
BPH and ED often coexist in older men. Daily low-dose tadalafil can address both. Alpha-blocker for BPH may interact with Sildalist combination.
Hypogonadism
Low testosterone affects libido and may reduce PDE5 response. Testosterone replacement combined with PDE5 inhibitor often works better than either alone.
Depression and anxiety
Common and often undertreated. Both contribute to ED. Treatment of mental health often improves ED. Some antidepressants cause ED — discussion with prescriber for best choice.
🩺 Preventive Care Priorities
- Annual physical examination with weight, BP, metabolic panel
- Cardiovascular risk assessment — lipids, BP, family history, smoking
- Diabetes screening if risk factors or over age 45
- Testosterone testing if symptoms suggest hypogonadism
- Prostate screening (PSA + DRE) per age-specific guidelines
- Colonoscopy starting age 45-50
- Mental health check-in annually
- Lifestyle counseling — diet, exercise, alcohol, smoking
- Immunizations — flu annually, shingles after 50, COVID boosters, Tdap
💊 ED as Opportunity for Prevention
ED is often an early marker of cardiovascular disease. Men presenting for ED care have an opportunity for comprehensive health assessment that may prevent future heart attack or stroke. Treating only the sexual symptom while missing the underlying vascular issue is a missed opportunity. The whole-health approach supports better long-term outcomes beyond just the immediate sexual function.
📅 Long-Term PDE5 Safety and Reassessment
Long-term use of PDE5 inhibitors over years is supported by extensive safety data. Men can use Sildalist or single-agent sildenafil or tadalafil for decades without accumulated adverse effects. The main considerations are periodic reassessment and attention to changing cardiovascular status.
📅 Decades of PDE5 Experience
Sildenafil 25+ years
Approved 1998. Hundreds of millions of patient-years of exposure. Safety profile stable with continued use.
Tadalafil 20+ years
Approved 2003. Extensive on-demand and daily-dose data. Long-term safety confirmed.
No new safety signals
Despite extensive post-marketing surveillance, no major new safety concerns have emerged with long-term use.
No tolerance or dependence
Response remains stable with continued use. No escalation of dose needed over years. No withdrawal on discontinuation.
🔄 Periodic Reassessment
Annual medical review
Cardiovascular status, blood pressure, medication list reconciliation, continued treatment benefit. New nitrate contraindication must be identified.
Dose optimization
Combination therapy may not be needed indefinitely. Consider whether optimized single-agent would suffice. Many men can step down over years.
Life circumstances review
New partner, change in frequency, new health conditions — each warrant reassessment.
Alternative consideration
If PDE5 response has diminished or side effects increased, alternatives (injections, implants, lifestyle) may fit better than continued combination.
🏥 Lifetime Treatment Perspective
Men starting PDE5 therapy in their 50s may use it for 20-30 years. Reasonable expectations:
- Continued effectiveness at same dose over years
- Stable side effect profile — what you experience in year 1 is likely year 10
- Nitrate contraindication unchanged — must respect for life
- Dose adjustments possible with aging or new medical conditions
- Combination not always necessary — many men transition to single-agent
- Alternative therapies remain available if PDE5 becomes inadequate
💊 Reassuring Long-Term Safety
PDE5 inhibitors are among the most studied and safest medications in all of urology. Long-term use is well established. Men on Sildalist can continue with reasonable confidence that no unexpected safety issues will emerge from continued use. The main attention points are cardiovascular status changes and new medication interactions over time.
🌟 ED Treatment Through Life Phases
ED treatment considerations shift through the aging process. Early ED in a man under 40 is clinically different from established ED in a 65-year-old or vascular-dominant ED in a 75-year-old. Sildalist combination role varies accordingly.
🌟 Early ED (Under 40)
Uncommon and warrants specific workup. Common considerations:
- Often psychogenic or situational
- Lifestyle contributors common (stress, substance use, relationship)
- Hormonal workup especially valuable in this age group
- Cardiovascular risk assessment valuable — may be early marker
- Short-term PDE5 use often enough to break anxiety cycle
- Combination therapy rarely needed; single-agent usually sufficient
🏆 Middle Age ED (40-55)
Common ED emergence phase. Key patterns:
- Vascular contributors becoming more significant
- Cardiovascular workup should be done
- Hormonal workup if symptoms suggest
- Lifestyle improvements can meaningfully affect ED
- Single-agent PDE5 inhibitor at optimal dose usually sufficient
- Combination may fit for specific preferences (fast + long)
- Mental health dimension often important
👴 Mature Age ED (55-70)
Established ED, more complex clinical picture:
- Vascular ED dominant in most cases
- Multiple comorbidities often present
- Multiple medications common — interactions critical
- Nitrate use for cardiac disease possible — must be identified
- Alpha-blocker for BPH common — combination requires caution
- Testosterone deficiency common — combined treatment often fits
- Combination therapy may be useful for suboptimal single-agent response
🌅 Older Age ED (70+)
Important considerations in this phase:
- Combination therapy often not appropriate
- Single-agent at lower dose preferred (sildenafil 25-50 mg or tadalafil 5-10 mg)
- Cardiology evaluation often needed before PDE5 use
- Orthostatic hypotension risk substantially higher
- Multiple medications — comprehensive interaction review
- Realistic expectations: adequate function, not peak performance
- Alternative options may fit better (penile injection, vacuum device, implant)
- Quality of intimate relationships still important and achievable
💊 Treatment Evolves With Age
ED treatment is a long-term clinical conversation rather than a one-time decision. The 50-year-old starting PDE5, the 65-year-old on combination therapy, and the 75-year-old on lower-dose single agent all have different configurations matching their life phase. Periodic reassessment ensures the treatment remains appropriate for current circumstances.
✅ Pre-Start Checklist Before First Combination Dose
Before starting Sildalist combination, a pre-use checklist ensures that important considerations are addressed. Combination therapy deserves more thorough preparation than single-agent trial because of the dual-agent interactions and cardiovascular load.
✅ Pre-Start Checklist
✅ CONFIRMED ED DIAGNOSIS
Clinical ED with impact on intimate relationship. IIEF or SHIM score if available. Not just occasional difficulty without pattern.
✅ NITRATE USE EXCLUDED
No nitroglycerin (sublingual, patch, spray), isosorbide dinitrate or mononitrate, amyl nitrite ("poppers"). Confirmed with prescriber or pharmacy review.
✅ CARDIOVASCULAR CLEARANCE
Princeton Consensus low or intermediate risk. Exercise tolerance adequate (2 flights of stairs, 1 mile walk). No recent MI, uncontrolled hypertension, significant arrhythmia.
✅ MEDICATION REVIEW
All medications reviewed. Alpha-blockers for BPH or hypertension (if any) noted. Strong CYP3A4 inhibitors avoided. Riociguat not in use.
✅ SINGLE-AGENT TRIED FIRST (IF APPLICABLE)
For most men, single-agent sildenafil or tadalafil tried before combination. Combination for specific scenarios (preference, suboptimal single-agent response).
✅ EXPECTATIONS SET REALISTICALLY
Understanding that PDE5 inhibitors require sexual arousal. 60-70% success rate on first attempts, often improving with experience. Not every attempt will succeed.
✅ FIRST DOSE PLANNING
At home environment. Light meal or empty stomach. Minimal alcohol. Full glass of water with dose. Rise slowly for first few hours. Partner aware.
✅ EMERGENCY SIGNS KNOWN
Priapism (4+ hour erection), sudden vision loss, sudden hearing loss, chest pain, severe allergic reaction — all require immediate medical attention. 72-hour minimum between doses.
✅ FOLLOW-UP PLAN
Review after 4-6 attempts to assess response, side effects, and whether to continue. Communication plan with prescriber if problems.
💊 Preparation Supports Success
Men who complete this checklist have significantly better outcomes than men who start combination therapy without preparation. The nitrate exclusion is life-saving; the cardiovascular clearance prevents dangerous events; the realistic expectations prevent premature discontinuation. The checklist takes 15-20 minutes with the prescriber but prevents problems and supports success.
🛑 Sildalist Contraindications and Emergency Signs
Sildalist contraindications combine the critical nitrate interaction, cardiovascular limitations, specific drug combinations, and patient population restrictions. Because the product contains two PDE5 agents, the contraindications are especially important to respect.
🛑 Absolute Contraindications
Nitrate medication use
Any form of nitrate — nitroglycerin, isosorbide dinitrate or mononitrate, amyl nitrite. Fatal hypotension risk. Absolute contraindication for both PDE5 agents in Sildalist.
Riociguat (soluble guanylate cyclase stimulator)
For pulmonary hypertension. Dangerous hypotension with any PDE5 inhibitor. Alternative ED treatment needed for men on riociguat.
Hypersensitivity to sildenafil or tadalafil
Known allergy to either component or any inactive ingredient.
Severe cardiovascular disease
Recent MI (within 2 weeks), unstable angina, uncontrolled hypertension, heart failure Class III-IV, hypertrophic obstructive cardiomyopathy with symptoms, significant arrhythmia. Sexual activity itself is risky; PDE5 inhibitors add to this.
History of NAION
Prior non-arteritic ischemic optic neuropathy from any PDE5 inhibitor use. Recurrent NAION risk with continued use. Alternative ED treatment required.
Retinitis pigmentosa
Inherited retinal disorder with altered PDE6 expression. Theoretical risk of vision worsening with PDE5 inhibitors. Avoid or use with ophthalmology input.
Not for women, children, or adolescents
Not indicated or approved for use under 18 or in women.
⚠️ Significant Cautions
Alpha-blockers (tamsulosin, doxazosin)
Significant orthostatic hypotension risk. Separate dosing by 4+ hours. Start with single-agent at low dose before combination.
Strong CYP3A4 inhibitors
Ketoconazole, itraconazole, ritonavir, clarithromycin. Avoid combination; use single-agent at reduced dose if essential.
Severe hepatic impairment
Child-Pugh class C. Significantly reduced clearance. Use alternative treatment.
Severe renal impairment
GFR less than 30. Specialist review needed; dose adjustment required.
Priapism risk conditions
Sickle cell disease, leukemia, multiple myeloma, prior priapism. Specialist counseling before PDE5 use.
Age over 75
Limited combination data; orthostatic risk higher. Prefer single-agent at low dose.
🚨 When to Seek Emergency Care
- Erection lasting more than 4 hours (priapism)
- Sudden partial or complete vision loss (NAION)
- Sudden hearing loss with ringing or dizziness
- Chest pain, severe palpitations, shortness of breath
- Severe allergic reaction: facial/throat swelling, difficulty breathing
- Fainting or severe sustained dizziness
- Severe sustained headache not relieved by usual measures
- Any symptoms suggesting hypotension (confusion, cold sweat, rapid pulse)
💊 Prescriber Review Essential
The contraindications list is comprehensive, but individual circumstances always require prescriber review. The dual-agent nature of Sildalist combination deserves especially thorough review of medications, cardiovascular status, and other PDE5-related risk factors. A thorough initial consultation prevents problems that general information cannot anticipate.
Sildalist — Frequently Asked Questions
-
What is Sildalist (Sildenafil Citrate with Tadalafil)?
Sildalist is a combination medication used to treat erectile dysfunction (ED) in men. It contains two active ingredients: Sildenafil Citrate and Tadalafil. -
How does Sildalist work?
Sildalist works by increasing blood flow to the penis through the combined effects of Sildenafil Citrate and Tadalafil, helping to achieve and maintain an erection during sexual stimulation. -
What conditions does Sildalist treat?
Sildalist is used to treat erectile dysfunction (ED). -
How should I take Sildalist?
Take Sildalist as directed by your healthcare provider, usually about 30 to 60 minutes before sexual activity. Swallow the tablet whole with water. -
How long does Sildalist last?
The effects of Sildalist can last up to 36 hours, providing a longer window of opportunity for sexual activity. -
Can I take Sildalist with food?
Yes, Sildalist can be taken with or without food. However, a high-fat meal may delay its onset of action. -
What are the common side effects of Sildalist?
Common side effects include headache, flushing, indigestion, nasal congestion, and dizziness.
See all Sildalist questions (32)
📚 Drug Description Sources:
The information in this Sildalist guide is compiled from authoritative pharmaceutical, urology, and regulatory sources covering erectile dysfunction (ED), PDE5 inhibitor pharmacology, dual-agent combination therapy, cardiovascular safety considerations, and clinical trials establishing the role of sildenafil and tadalafil for ED management.
🏛️ Regulatory and government agencies
- US Food and Drug Administration (FDA) - sildenafil approval 1998 as Viagra; tadalafil approval 2003 as Cialis; combination product is not FDA approved as fixed-dose
- European Medicines Agency (EMA) and MHRA UK - sildenafil and tadalafil approvals with ongoing safety monitoring
- Health Canada and TGA Australia - clinical safety framework for both PDE5 inhibitors
- Central Drugs Standard Control Organization (CDSCO India) - approvals for generic sildenafil, tadalafil, and combination formulations from WHO-GMP certified manufacturers
📚 Professional societies and clinical guidelines
- International Society for Sexual Medicine (ISSM) - standard operating procedures for ED management
- American Urological Association (AUA) - Erectile Dysfunction Guideline with PDE5 inhibitor as first-line therapy
- European Association of Urology (EAU) - Guidelines on Male Sexual and Reproductive Health
- Princeton Consensus Conference - cardiovascular considerations for ED treatment
🔬 Landmark clinical research
- Goldstein et al. NEJM 1998 - foundational sildenafil Phase 3 trial establishing PDE5 inhibitor efficacy for ED
- Padma-Nathan et al. International Journal of Impotence Research 2003 - tadalafil Phase 3 trials and 36-hour window of effect
- Porst et al. Journal of Sexual Medicine - comparative PDE5 inhibitor pharmacokinetics and clinical outcomes
- Hellstrom et al. - PDE5 inhibitor long-term outcomes and comparative clinical research
📖 Medical references and textbooks
- Campbell-Walsh-Wein Urology - ED pharmacotherapy chapter
- Journal of Sexual Medicine - PDE5 inhibitor comparative studies and combination approaches
- International Journal of Impotence Research - ED treatment outcomes across populations
- European Urology - ED management and PDE5 inhibitor clinical reviews
Note: This information is educational and does not replace consultation with qualified healthcare providers. Sildalist combination use requires individual clinical assessment of cardiovascular status, concurrent medications (especially nitrates and alpha-blockers), and specific patient factors not covered by general reference material.
🩺 Medical Expert Review:
Content based on the published research and clinical practice of sexual medicine and urology authorities with particular expertise in erectile dysfunction, PDE5 inhibitor pharmacology, combination therapy approaches, and comparative clinical trials. The reviewers below are internationally recognized for their contributions to ED care.
Prof. Raymond C. Rosen, PhD
Senior Scientist Emeritus, New England Research Institutes — Watertown, USA
Prof. Rosen developed the International Index of Erectile Function (IIEF), the standard measurement instrument used in nearly every PDE5 inhibitor clinical trial. His research shaped the modern approach to ED outcomes assessment reflected throughout this guide.
Prof. Hartmut Porst, MD
Director, European Institute for Sexual Health — Hamburg, Germany
Prof. Porst has published extensively on comparative PDE5 inhibitor pharmacokinetics and clinical outcomes. His work on the pharmacology that distinguishes sildenafil from tadalafil informs the dual-agent combination rationale in this guide.
Prof. Edgardo F. Becher, MD, PhD
Professor of Urology, University of Buenos Aires — Buenos Aires, Argentina
Prof. Becher is a past President of the International Society for Sexual Medicine and leading Latin American authority on ED pharmacotherapy. His research on PDE5 inhibitor outcomes across diverse populations informs the broad clinical framework used here.
Prof. Wayne J. G. Hellstrom, MD
Professor and Chief of Andrology, Tulane University School of Medicine — New Orleans, USA
Prof. Hellstrom has published hundreds of peer-reviewed articles on male sexual dysfunction including comparative PDE5 inhibitor research. His integrated approach to ED and overall male sexual health informs the practical treatment framework in this guide.
Prof. Mohit Khera, MD, MBA, MPH
Professor of Urology and F. Brantley Scott Chair in Urology, Baylor College of Medicine — Houston, USA
Prof. Khera is a leading authority on erectile dysfunction with research spanning PDE5 inhibitors, testosterone, and penile rehabilitation. His work on the hormonal and vascular dimensions of ED informs the comprehensive management framework in this guide.
Disclosure: Expert names and credentials are cited for educational reference. This content is not endorsed by the named experts. Content prepared by the RXshop editorial team based on published literature and clinical guidelines.
More Men's Health Medications