Buy P-Nolol (Propranolol) Online — Cost-Effective Generic Non-Selective Beta-Blocker for Hypertension, Angina, Migraine Prophylaxis & Essential Tremor


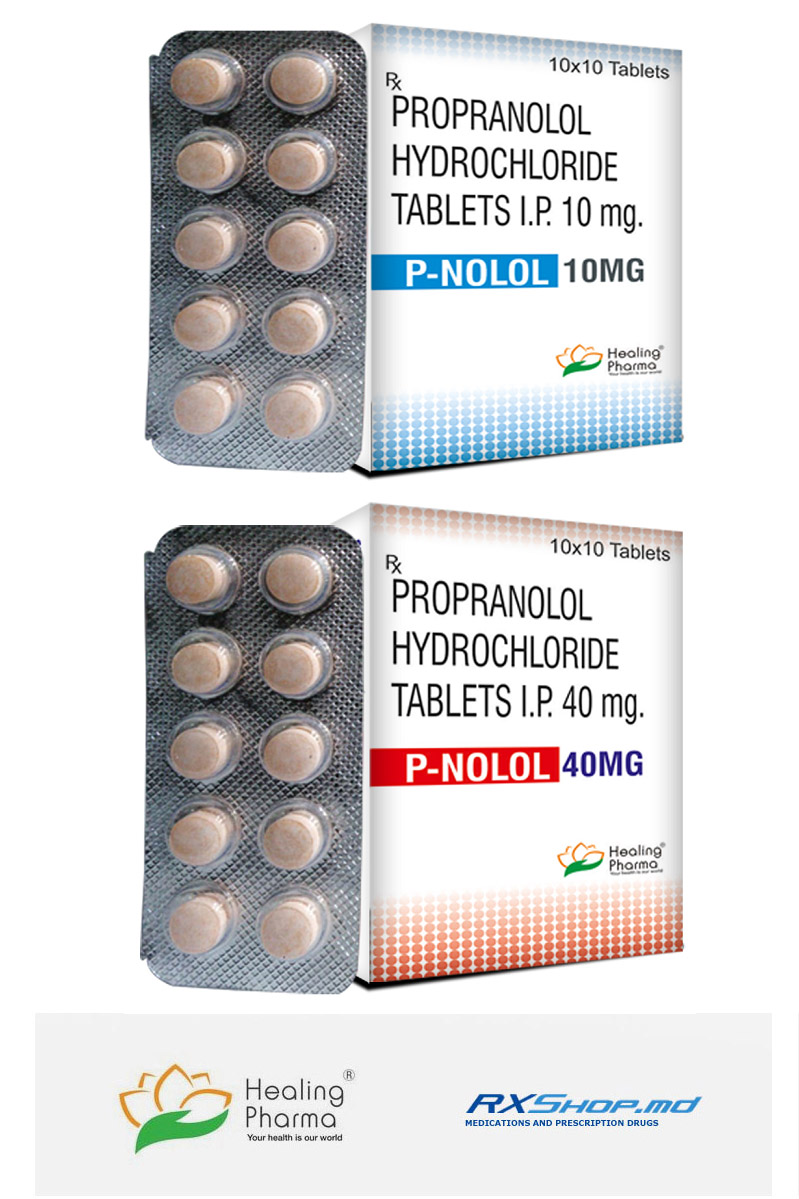
P-Nolol is a cost-effective generic formulation of Propranolol Hydrochloride — the FIRST beta-adrenergic blocker ever developed and a foundational cardiovascular medication. P-Nolol delivers Propranolol in immediate-release (IR) tablets, providing the same flexible dosing as the original brand Inderal at significantly reduced cost. Original Propranolol research by Sir James Black (Nobel Prize in Medicine 1988) established the entire beta-blocker drug class. Propranolol FDA-approved since 1967, listed on the WHO Model List of Essential Medicines. P-Nolol is bioequivalent to Inderal IR — same Propranolol active ingredient, same indications, same safety profile, at affordable generic pricing. Particularly valuable for developing markets and cost-conscious patients requiring flexible IR Propranolol dosing.
The active ingredient is Propranolol Hydrochloride, a non-selective beta-adrenergic receptor antagonist blocking both beta-1 cardiac receptors (reducing heart rate, contractility, cardiac output, renin release) AND beta-2 receptors (bronchi, peripheral vasculature). Propranolol is highly lipid-soluble — readily crosses the blood-brain barrier, supporting numerous CNS-mediated off-label uses (migraine prophylaxis, essential tremor, performance anxiety, PTSD). P-Nolol IR has rapid onset (30-60 minutes) and short half-life (3-6 hours), supporting flexible BID-QID dosing and PRN use. Membrane stabilizing activity contributes to antiarrhythmic effects.
P-Nolol is used for the full Propranolol indication spectrum: FDA-approved for hypertension, angina pectoris, atrial fibrillation rate control, migraine prophylaxis, essential tremor, hypertrophic subaortic stenosis, pheochromocytoma (preoperative), and post-MI mortality reduction. Established off-label uses: performance anxiety / stage fright (10-40 mg PRN), portal hypertension (variceal bleeding prophylaxis), thyroid storm, akathisia, anxiety with somatic symptoms.
Available as P-Nolol 10, 20, and 40 mg tablets. Standard adult dosing: HTN 40 mg BID start, titrate to 120-240 mg/day (TID-QID); angina 80-320 mg/day; migraine prophylaxis 80-240 mg/day; performance anxiety 10-40 mg PRN.
Critical safety: boxed warning regarding abrupt withdrawal — angina exacerbation, MI risk; taper over 1-2 weeks. Contraindicated in asthma/severe COPD (β2 blockade). Caution in decompensated HF, severe bradycardia, advanced AV block. Side effects: bradycardia, hypotension, fatigue, depression (lipophilic), sexual dysfunction, cold extremities, vivid dreams. Masks hypoglycemia symptoms in diabetics.
Free prescription
Discrete packaging
Have questions?
Quality Assurance

- Angina Pectoris: FDA-approved for chronic stable angina pectoris;
- Post MI Mortality Reduction: FDA-approved for post-myocardial infarction mortality reduction;
- Atrial Fibrillation Rate Control: FDA-approved for atrial fibrillation rate control;
- Migraine Prophylaxis: FDA-approved for migraine prophylaxis — foundational migraine prevention agent;
- Essential Tremor: FDA-approved for essential tremor — first-line therapy;
- Hypertrophic Subaortic Stenosis: FDA-approved for hypertrophic subaortic stenosis (HOCM);
- Pheochromocytoma Preop: FDA-approved for pheochromocytoma preoperatively;
- Performance Anxiety Stage Fright: Off-label SIGNATURE use for performance anxiety / stage fright;
- Public Speaking Anxiety: Off-label for public speaking anxiety;
- Musician Performance Anxiety: Off-label for musician performance anxiety;
- Portal Hypertension Variceal: Off-label STANDARD for portal hypertension and variceal bleeding prophylaxis;
- Variceal Bleeding Prevention: Off-label for esophageal variceal bleeding prophylaxis;
- Thyroid Storm Treatment: Off-label for thyroid storm — IR rapid onset preferred;
- Akathisia Antipsychotic: Off-label for antipsychotic-induced akathisia;
- Anxiety Somatic Symptoms: Off-label for anxiety with somatic symptoms (palpitations, tremor);
- Hyperthyroid Symptomatic: For symptomatic control in hyperthyroidism;
- Long QT Syndrome: Off-label for long QT syndrome management;
- Lithium Tremor: Off-label for lithium-induced tremor reduction;
- Cost Sensitive Patients HTN: For cost-conscious HTN patients seeking affordable Propranolol;
- Developing Markets Access: Established access for developing markets through generic manufacturing.
- Less Angina Symptoms: Significant reduction in angina pectoris symptoms;
- Better Post MI Survival: Reduces mortality after myocardial infarction;
- Less AF Heart Rate: Effective rate control in atrial fibrillation;
- Less Migraine Frequency: Significant reduction in migraine attack frequency;
- Less Migraine Severity: Reduces severity of migraine episodes;
- Less Essential Tremor: First-line reduction of essential tremor;
- Better Tremor Daily Function: Restores writing, eating, drinking function in essential tremor;
- Less Performance Anxiety: Effectively blocks physical symptoms of performance anxiety;
- Better Public Speaking Confidence: Improves confidence by suppressing somatic anxiety symptoms;
- Less Stage Fright: Standard pre-performance medication for musicians, actors, public speakers;
- Rapid PRN Onset: IR rapid onset (30-60 min) ideal for situational PRN use;
- Less Variceal Bleeding Risk: Reduces variceal bleeding risk in cirrhotic portal hypertension;
- Less Portal Pressure: Reduces portal venous pressure in cirrhosis;
- Less Thyroid Storm Symptoms: Controls adrenergic symptoms of thyroid storm and hyperthyroidism;
- Less Akathisia: Reduces antipsychotic-induced akathisia;
- Less Anxiety Somatic Symptoms: Reduces palpitations, tremor, sweating of anxiety disorders;
- Better Daily Function: Return to normal daily activities with effective BP/migraine/tremor control;
- Better Quality of Life: Substantial improvement in quality of life across multiple indications;
- Better Affordability vs Inderal: Cost-effective vs original Inderal brand — signature P-Nolol benefit;
- Better Developing Markets Access: Generic manufacturing enables developing markets affordable access;
- Brand P Nolol: Cost-effective generic Propranolol brand — affordable alternative to Inderal;
- Generic Propranolol: Affordable generic Propranolol expands global access to foundational beta-blocker;
- Cost Effective Propranolol Generic: Cost-effective Propranolol access — signature generic advantage;
- Affordable Indian Generic: Affordable Indian generic positioning — value alternative;
- Bioequivalent To Inderal: Bioequivalent to original Inderal brand — same Propranolol active;
- IR Immediate Release Tablets: Immediate-release tablets — flexible BID-QID dosing, PRN-friendly;
- Non Selective Beta Blocker: Non-selective β1+β2 adrenergic antagonist — foundational mechanism;
- Sir James Black Nobel 1988: Founded on Sir James Black Nobel Prize-winning Propranolol research at ICI;
- Lipid Soluble CNS Penetration: Lipid-soluble — CNS penetration enables migraine/tremor/anxiety uses;
- Multiple FDA Indications: Multiple FDA-approved indications across cardiovascular and neurological;
- Membrane Stabilizing Activity: Membrane stabilizing activity contributes to antiarrhythmic effects;
- Class II Antiarrhythmic: Class II antiarrhythmic agent;
- Rapid Onset PRN Use: IR rapid onset ideal for situational/PRN performance anxiety use;
- WHO Essential Medicine: Listed on the WHO Model List of Essential Medicines;
- Propranolol Class Since 1967: Propranolol molecule FDA-approved since 1967 — foundational beta-blocker.
Generic P-Nolol (Propranolol 10 mg) Medication guide:
🎯 What P-Nolol Is and Who Should Take It
P-Nolol is one of the brand names for propranolol, a beta-adrenergic receptor blocker - the drug that opened the whole beta-blocker era of cardiovascular medicine when Sir James Black developed it in 1962. Propranolol was awarded the Nobel Prize in Physiology or Medicine in 1988 (via Black) for its impact on hypertension, angina, and cardiac arrhythmias. Today it is not the beta-blocker most doctors reach for first in hypertension, but it remains widely used for a specific and unusually broad set of conditions.
P-Nolol is not a rescue pill for a spike of BP. It is a long-term medicine, taken every day for years, that reduces heart rate, softens the force of heart contraction, and blunts the sympathetic nervous system's effect on the heart, blood vessels and other tissues. This mechanism turns out to be useful for many things - which is why the drug has more indications than almost any other cardiovascular medicine.
Who is P-Nolol typically prescribed for
- Adults with chronic stable angina - to reduce chest pain frequency and improve exercise tolerance
- Adults after a heart attack - for secondary prevention of a second event
- Adults with certain heart rhythm problems - atrial fibrillation rate control, supraventricular tachycardia
- Adults with frequent migraine attacks - as a preventive rather than an acute treatment
- Adults with essential tremor where hand tremor interferes with everyday tasks
- Adults with performance anxiety or stage fright in specific situations (public speaking, musical performance, exams)
- Adults with cirrhosis and gastro-oesophageal varices - to prevent bleeding
- Adults with overactive thyroid - for symptomatic control of racing heart and tremor while underlying treatment takes effect
- Occasionally in essential hypertension where other classes cannot be used - not first-line
P-Nolol is not the pill for someone with severe asthma or reversible airway disease - because it blocks beta-2 receptors in the airways and can trigger bronchospasm. It is also not safe in severe bradycardia, second- or third-degree heart block, or cardiogenic shock. It requires care in diabetes because it can mask the warning signs of low blood sugar (Section 23). And - critically - it must never be stopped abruptly, because sudden withdrawal after long-term use can trigger rebound angina, arrhythmias, or even a heart attack (Section 24).
This guide will walk you through what P-Nolol does, how to take it (regular vs long-acting), what to eat and drink alongside, which side effects to expect, and how to fit it into the rest of your life - shift work, exercise, travel, illness, surgery. By the end you should know P-Nolol the way you know a tool you have used for years.
🔬 How P-Nolol Works - Blocking Beta Receptors
To understand P-Nolol you need to know about the sympathetic nervous system - the "fight or flight" branch of your involuntary nerves. This branch releases adrenaline and noradrenaline that speed the heart, tighten blood vessels, dilate airways, mobilise glucose, and prepare the body for action. Propranolol blocks the receptors these hormones act on.
Step 1 - Beta receptors have subtypes
Two main subtypes of beta receptor matter clinically. Beta-1 receptors sit mostly on the heart and kidney; when adrenaline binds them, the heart speeds up, contracts more forcefully, and the kidneys release renin. Beta-2 receptors sit mostly on airways, blood vessels, muscle, and liver; when adrenaline binds them, airways dilate, some blood vessels dilate, muscle uses glucose, and the liver releases glucose. Newer beta-blockers (bisoprolol, metoprolol) block mainly beta-1. Propranolol is non-selective - it blocks both.
Step 2 - Blocking beta-1 in the heart
When P-Nolol blocks beta-1 receptors on the heart, three things happen:
- Heart rate slows - typically by 10-20 beats per minute at effective doses
- Force of heart contraction reduces - the heart works less hard
- Cardiac output drops - reducing BP and the oxygen demand of the heart muscle
This is why propranolol reduces angina attacks, controls fast heart rhythms, and prevents post-heart-attack complications.
Step 3 - Blocking beta-2 elsewhere
The non-selective nature of propranolol also blocks beta-2 receptors in other tissues. This is where useful effects (migraine prevention, tremor reduction, thyrotoxicosis control) come from, but also where the important side effects arise:
- Airways - bronchospasm risk in asthma (Section 22)
- Blood vessels in extremities - cold hands, Raynaud reactions (Section 19)
- Muscle - reduced sympathetic amplification of tremor
- Liver - blunted glucose response to hypoglycaemia (Section 23)
- Brain - because propranolol is lipid-soluble, it crosses the blood-brain barrier and affects sympathetic-driven anxiety, tremor amplification, and vivid dreams
The timeline you actually feel
| Timeframe | What happens |
|---|---|
| Hours 1-3 | Heart rate slows measurably; BP starts to drop |
| Days 1-7 | Full heart rate reduction; body adapts to lower cardiac output |
| Weeks 2-4 | Angina attacks reduce; tremor improves; migraine frequency starts to fall |
| Months 2-3 | Full effect on migraine prevention visible |
The half-life of regular propranolol is short - only 3 to 6 hours - which is why regular tablets are taken 2 or 3 times a day. The long-acting (LA) formulation extends the half-life to 8-14 hours and allows once-daily dosing. Section 9 covers timing choices.
📋 What Doctors Prescribe P-Nolol For
Propranolol has one of the longest indication lists of any cardiovascular drug. Understanding which use applies to you helps you know why the drug was chosen and what benefit to expect. Sections 5, 6 and 7 go into detail for each major use; this section is the overview.
1. Cardiovascular uses (Section 5)
- Chronic stable angina - reduces attack frequency
- Post-heart-attack secondary prevention - reduces mortality (BHAT trial 1982)
- Atrial fibrillation rate control - slows the ventricular response
- Supraventricular tachycardia - can terminate or prevent episodes
- Hypertension - older use, not first-line since ASCOT and ALLHAT
2. Neurological uses (Sections 6 and 7)
- Migraine prevention - reduces attack frequency by 30-50 percent on average
- Essential tremor - improves hand steadiness for writing, eating, drinking
- Performance anxiety - single dose before an event to blunt physical symptoms
3. Other well-established uses
- Portal hypertension in cirrhosis - non-selective beta blockade reduces bleeding from gastro-oesophageal varices
- Thyrotoxicosis symptomatic control - relieves racing pulse, tremor, and anxiety while definitive treatment is arranged
- Infantile haemangioma - propranolol has become first-line treatment for problematic infant vascular growths
- Hypertrophic cardiomyopathy - reduces gradient and symptoms in obstructive forms
Why propranolol is no longer first-line for hypertension
The ASCOT-BPLA trial (2005) and ALLHAT (2002) showed that atenolol-based regimens produced fewer cardiovascular benefits than amlodipine or ACE inhibitor regimens for pure BP treatment. This finding, though from atenolol, is generalised to non-vasodilating beta-blockers including propranolol. Modern hypertension guidelines list ACE inhibitors, ARBs, calcium channel blockers, and diuretics ahead of beta-blockers. Propranolol earns its place for the specific indications above - not as a routine BP pill.
Doctors weigh P-Nolol against three main alternatives: cardio-selective beta-blockers (bisoprolol, metoprolol, atenolol) for pure cardiac work; other migraine preventives (topiramate, amitriptyline, CGRP antibodies) for migraine; and other classes for BP. P-Nolol wins when its non-selectivity is actually wanted (migraine, tremor, anxiety, thyrotoxicosis, portal hypertension) or when a client is already tolerating it well and switching would risk destabilising a working regimen.
💊 Propranolol Explained - The First Beta-Blocker
Propranolol was the first clinically successful beta-blocker. Sir James Black at Imperial Chemical Industries (ICI) synthesised it in the late 1950s and it reached clinical practice in 1962. Black won the Nobel Prize in Physiology or Medicine in 1988 for this and related work. Modern medicine still uses many descendants of propranolol, but the original remains in daily prescribing use six decades later.
Propranolol among the beta-blocker family
| Drug | Selectivity | Half-life | Notes |
|---|---|---|---|
| Propranolol (P-Nolol) | Non-selective (b1+b2) | 3-6 h (regular) | Highly lipid-soluble; CNS entry |
| Metoprolol | Beta-1 selective | 3-7 h | Safer in mild airway disease |
| Bisoprolol | Beta-1 selective | 10-12 h | Heart failure evidence base (CIBIS) |
| Atenolol | Beta-1 selective | 6-9 h | Older; falling out of use |
| Carvedilol | Non-selective + alpha block | 6-10 h | Heart failure workhorse |
| Nadolol | Non-selective | 14-24 h | Very long acting; not lipid-soluble |
Two distinctive features of propranolol
1. Non-selectivity
This is the reason for both the wide range of indications (migraine, tremor, thyrotoxicosis) and the safety concerns (asthma, glucose masking). Section 22 covers the asthma warning.
2. Lipid solubility and CNS entry
Propranolol crosses the blood-brain barrier easily. This is why it works for performance anxiety and can reduce the central amplification of tremor. It is also why sleep disturbances and vivid dreams (Section 20) are more common than with water-soluble beta-blockers like atenolol.
Regular vs long-acting (LA)
Propranolol comes as regular tablets (10, 20, 40, 80 mg) needing 2-3 doses per day, and as long-acting or slow-release capsules (60, 80, 120, 160 mg) needing only one dose per day. LA is more convenient but slightly more expensive. Both are equivalent in effect at matching daily total doses.
The specific formulation and strength you were prescribed matters. LA is usually preferred for long-term hypertension, angina and migraine prevention because adherence is easier. Regular short-acting tablets are useful when a client is being titrated up and doses may change quickly, and for single-dose situational use in performance anxiety.
🫀 P-Nolol for Angina, Heart Attack Recovery and Arrhythmias
P-Nolol has three main cardiovascular uses, each with a different clinical logic. Understanding which applies to you helps you interpret why the drug was chosen and what benefit to expect.
1. Chronic stable angina
Angina is chest pain (or pressure, heaviness, or squeezing feeling) caused by narrowed coronary arteries not delivering enough blood to the heart muscle during exertion. P-Nolol reduces attack frequency by:
- Slowing heart rate - the heart uses less oxygen at any given workload
- Reducing contractility - less force means less oxygen demand
- Lowering BP - the heart pumps against less afterload
The result: clients can exercise further before chest pain appears, and attacks at rest become less frequent. Effective doses are typically 80-320 mg total daily (in divided doses for regular tablets, or once daily as LA).
2. Secondary prevention after a heart attack
The BHAT trial (Beta-Blocker Heart Attack Trial, 1982) showed propranolol reduced mortality by 26 percent in survivors of acute MI, over about 2 years of follow-up. This was one of the pivotal trials that established beta-blockers as standard post-MI care.
Modern practice usually uses cardio-selective beta-blockers (metoprolol, bisoprolol) for this indication because they are gentler on airways. But propranolol still qualifies, especially if a client has other reasons for choosing non-selective beta blockade (migraine, tremor, essential hypertension).
3. Rate control in atrial fibrillation and supraventricular tachycardia
In atrial fibrillation, the top chambers of the heart quiver instead of contracting normally, and the ventricles can beat very fast in response. Propranolol slows the electrical signal at the AV node, reducing the ventricular rate to a manageable range.
In supraventricular tachycardia (SVT), propranolol can help prevent recurrent episodes and (less commonly) terminate an ongoing one.
P-Nolol + short-acting nitrate for angina
Clients with angina on P-Nolol usually also carry a short-acting nitrate (sublingual glyceryl trinitrate spray or tablet) for immediate relief of an attack. P-Nolol prevents; nitrate rescues. If chest pain lasts longer than 10-15 minutes despite rest and nitrate, that is an emergency (possible heart attack) - call emergency services.
Cardiovascular use is where the "never stop abruptly" rule matters most
In cardiovascular indications, sudden stopping of P-Nolol can precipitate angina, arrhythmia, or (rarely) a heart attack from rebound sympathetic activity. Section 24 covers the withdrawal rules in detail. This is not overstated - it is one of the most consistent lessons of beta-blocker practice.
🧠 P-Nolol for Migraine Prevention
Migraine is one of the most common neurological conditions, and propranolol is one of the longest-established preventive drugs for it. In clients who experience frequent migraine attacks (usually 4 or more per month), a daily preventive drug can reduce attack frequency, severity and duration - independent of any acute treatment used during individual attacks.
The evidence base
Multiple randomised trials since the 1970s have shown propranolol reduces migraine attack frequency by 30-50 percent on average, with about half of clients experiencing at least a 50 percent reduction in attacks. The American Academy of Neurology guidelines list propranolol as Level A evidence (established effective) for migraine prevention.
The mechanism is not fully understood but appears to involve reducing central noradrenergic activity and modulating cortical spreading depression - the wave of brain activity thought to underlie migraine.
Typical dosing for migraine prevention
- Start low: 20 mg twice daily or 40 mg once daily (LA)
- Titrate slowly over 4-6 weeks based on tolerance
- Typical maintenance: 80-160 mg total daily; occasionally up to 240 mg
- Full effect takes 2-3 months - do not judge effectiveness earlier
- Continue for at least 6-12 months after attacks are well controlled before considering withdrawal
Keep a migraine diary
The single most useful habit for anyone on preventive migraine treatment is a simple headache diary - one line per day noting whether a headache occurred, its severity, duration, and any rescue treatment used. Over 2-3 months of P-Nolol titration, the pattern of reduction (or lack of it) becomes clear. Bring the diary to every follow-up.
What P-Nolol does not do for migraine
- Does not stop an ongoing migraine attack - use standard acute treatment (triptans, ibuprofen, paracetamol, or your prescribed combination)
- Does not cure migraine - it reduces frequency and severity; some clients still have breakthrough attacks
- Does not treat other headache types - tension, cluster, medication-overuse - propranolol is specifically for migraine
- Does not replace lifestyle triggers - sleep hygiene, hydration, regular meals, and avoiding known triggers still matter
When migraine improves - what next?
After 6-12 months of good control on P-Nolol, some clients consider tapering off. This is a shared decision with your doctor. If you decide to stop, do it slowly (reduce dose over 4-6 weeks) rather than abruptly, both because of the beta-blocker withdrawal risk (Section 24) and because migraine can rebound during rapid drug cessation.
Modern neurology also offers newer options for migraine prevention (topiramate, amitriptyline, CGRP monoclonal antibodies). P-Nolol remains a reasonable first choice for many clients because it is cheap, well-tested, and one drug that can also help if migraine coexists with essential tremor, performance anxiety, or hypertension.
⚡ P-Nolol for Essential Tremor and Performance Anxiety
Two off-license but well-supported uses of propranolol are essential tremor and performance anxiety. In both, the drug blunts the physical manifestations of sympathetic activation without affecting cognition or mental clarity.
Essential tremor
Essential tremor is an involuntary shaking movement that most commonly affects the hands, particularly during action - writing, holding a cup, using tools. It is different from Parkinson tremor (which is more prominent at rest). Many clients live with mild essential tremor as an inconvenience; others find their handwriting, work, or eating substantially affected.
Propranolol reduces the visible tremor by muting sympathetic amplification. The muscle-driving signals still fire, but the noradrenaline-driven boost that makes the tremor bigger is dampened.
Typical dosing for essential tremor
- Start: 20 mg twice daily
- Titrate in 20-40 mg increments every 1-2 weeks based on effect and tolerance
- Typical effective dose: 80-320 mg total daily
- Full effect within 2-4 weeks at the maintenance dose
- Some clients use it "on demand" - a single dose before a task that requires steady hands (writing, dining, photography)
Performance anxiety and stage fright
Musicians, public speakers, exam candidates, surgeons, and dancers describe the same physical phenomenon before a performance: hands shake, heart races, voice quivers, mouth goes dry, mind blanks. The cause is not fear itself but the sympathetic surge that fear triggers. Propranolol blocks the beta-receptor targets of that surge.
The result: hands stay steady, pulse stays smooth, voice stays firm, and the client can focus on the actual performance rather than fight physical symptoms. Cognition and quality of thinking are not affected.
Typical use for performance anxiety
- Single dose: 10-40 mg taken 30-60 minutes before the event
- Try the dose at home first - never on the day of a major event without knowing how you respond
- Situational, not daily - performance anxiety is not treated with chronic beta-blockade
- Combines well with brief cognitive strategies but is not a replacement for treatment of an underlying anxiety disorder
What propranolol does not do for anxiety
- Not for generalised anxiety disorder - SSRIs or SNRIs work better for chronic anxiety
- Not for panic attacks without specialist input - the mechanism is different
- Not a substitute for cognitive-behavioural therapy when the underlying issue is fear-based
- Not a mood elevator - it addresses physical symptoms, not underlying mood
These two uses - tremor and performance anxiety - are situations where P-Nolol's central nervous system access and its non-selective blockade become useful features rather than side effects. If you were prescribed the drug for one of these, the counselling is different from cardiovascular use (Section 5) but the safety rules on asthma, diabetes, and withdrawal still apply.
📅 The First Few Weeks on P-Nolol
Starting P-Nolol depends a lot on why you are taking it and what dose you are starting on. But some patterns are universal to beta-blocker initiation.
Days 1-3
Heart rate slows measurably. If you were used to a resting pulse of 75, it may drop to 60-65 within days. This is expected and usually well tolerated.
Some fatigue may appear in the first week as the body adjusts to the reduced cardiac output. Usually settles.
Week 1-2
Adaptation to lower heart rate. Exercise capacity may feel reduced at first because your heart cannot speed up as freely. This usually adapts over 2-4 weeks.
Cold hands and feet may become noticeable, especially in cool weather. Section 19 covers this.
Sleep changes may appear - vivid dreams, occasional nightmares. Section 20.
Week 3-8
Full effect on the specific indication becomes visible. Angina attacks reduce, tremor improves, or migraine frequency starts to fall. For migraine, full effect can take 2-3 months.
Dose adjustments happen now based on effect on symptoms and tolerance of side effects.
Signs that are NOT normal and need a call to your doctor
- Resting pulse below 50
- Severe fatigue that does not improve after 2-3 weeks
- Wheezing, tight chest, breathlessness - possible bronchospasm; go to emergency (Section 22)
- Fainting or near-fainting
- New chest pain that is different from your usual angina
- Very cold, blue, painful hands or feet - possible severe Raynaud
- Confusion or unusual drowsiness
- New severe depression symptoms - rare but recognised
Most people notice slowing of the heart rate and mild fatigue in the first week, then adapt over 2-4 weeks and settle into a stable pattern. If those first weeks pass without incident, the long-term outlook is usually smooth. The critical rule you must never forget - even after months of tolerating the drug well - is Section 24: never stop it abruptly.
⏰ When to Take P-Nolol - Regular vs Long-Acting
The right timing for P-Nolol depends on which formulation you have (regular or long-acting) and what you are taking it for.
Regular (short-acting) tablets
- Half-life: 3-6 hours
- Typical schedule: 2-3 times daily, spread through waking hours
- Common pattern: morning, midday, evening
- Take with food or without - both are fine
- Try to keep intervals reasonably even so blood levels stay smooth
Long-acting (LA / SR / XL) capsules
- Half-life: 8-14 hours
- Typical schedule: once daily
- Common pattern: morning or evening - your choice, as long as it is consistent
- Swallow whole - do not open or crush capsules; the slow-release design depends on the intact shell
- Take with food or without - both are fine, but pick one and stick with it
Performance anxiety - a special case
For situational performance anxiety, take a single dose of regular short-acting propranolol (not long-acting) 30-60 minutes before the event. LA is designed for smooth daily dosing, not for peak-and-hold single-dose use.
Practical anchors
- Morning dose - with breakfast, before coffee
- Midday dose - with lunch or an afternoon habit
- Evening dose - with dinner, before 8 pm to avoid sleep disruption
- Phone alarms labelled for each dose can help if you are on 2-3 daily doses
- Weekly pillbox with multiple compartments per day
Evening dose and sleep
Propranolol crosses into the brain and can cause vivid dreams or wakefulness (Section 20). If evening doses are disturbing your sleep, try moving them earlier - to dinnertime rather than bedtime - or ask your doctor about switching to a cardio-selective beta-blocker that has less CNS effect.
The most common practical mistake with regular P-Nolol is drifting from three-times-daily to two-times-daily on busy days. This creates a gap where blood levels dip too low and heart rate creeps back up. If the three-times schedule is genuinely unworkable, ask your doctor about switching to LA (once daily) or to a longer-acting beta-blocker like nadolol.
🍽️ Food and P-Nolol
Food does not meaningfully change how P-Nolol is absorbed. Take it with meals or without - what matters is consistency. Your body handles the drug the same way each time if the routine is stable.
Food rules for P-Nolol
- With or without food is fine - stick with whichever you choose
- Swallow whole with water - regular tablets can be crushed if needed, but never LA capsules
- Grapefruit is generally fine - propranolol interaction with grapefruit is modest and not clinically important
- No specific food avoidance needed
Salt still matters if you take P-Nolol for BP
P-Nolol is not a diuretic and does not remove salt directly - but high dietary salt still undermines BP control on any pill. Cut salt to about 5-6 g per day (about a teaspoon total) for the best BP effect.
Watch weight and appetite
Beta-blockers can slightly reduce metabolic rate and make weight loss harder over years. If you are trying to lose weight, this is a factor to know about. It does not stop weight loss, but the same effort produces less result than it might on a different BP class.
Migraine trigger foods
If you take P-Nolol for migraine prevention, remember that some foods can still trigger attacks despite the preventive drug: chocolate, aged cheeses, red wine, cured meats, MSG-containing foods, and (for some clients) skipped meals. Keep a headache diary to identify your personal triggers.
Diabetic diet on P-Nolol
If you are diabetic (Section 23), regular meal timing becomes more important because propranolol masks the early warning symptoms of low blood sugar. Skipped meals combined with insulin or sulfonylurea doses are a recipe for hypoglycaemic events you may not sense in time.
Beyond salt (for BP), migraine trigger foods (for migraine), and regular meals (for diabetics), no specific food needs avoiding on P-Nolol. It sits comfortably alongside almost any normal diet.
🍷 Alcohol and P-Nolol
Alcohol and P-Nolol are compatible in moderate amounts. Both can lower BP and both can make you feel more sedated than either alone. The combination is not banned, but the amount and pattern matter.
Three things happen when you drink on P-Nolol
- BP drops more than expected. Alcohol vasodilates; P-Nolol reduces cardiac output. Together the drop can produce dizziness, faintness, or a fall - especially after standing.
- Sedation and fatigue add up. Propranolol can already cause tiredness in the first weeks; alcohol amplifies this. Driving after alcohol on P-Nolol is unwise.
- Chronic heavy drinking undermines the underlying condition. Alcohol raises BP over time, triggers migraine attacks, provokes atrial fibrillation, and worsens angina.
A sensible framework
- Up to 1 standard drink per day for women, 2 for men is compatible with P-Nolol
- Drink water between alcoholic drinks
- Never drink on an empty stomach on P-Nolol
- Skip alcohol for 48 hours after any dose increase
- Do not drive after any alcohol on P-Nolol
Special cases where alcohol on P-Nolol is a bad idea
- Cirrhosis-related P-Nolol use for portal hypertension - alcohol worsens the underlying liver disease
- Migraine prevention - alcohol (especially red wine) is a common trigger
- Atrial fibrillation - alcohol is a known "holiday heart" trigger for AF episodes
- Recent starting or dose increase
- Age 75 or older with any fall history
- Also on a diuretic or ACE inhibitor - additive BP drop
Binge drinking - 5+ drinks in an evening for men, 4+ for women - is particularly risky on P-Nolol. Not only does BP crash, but withdrawal-mediated rebound tachycardia the next morning may produce palpitations or (in coronary disease clients) chest pain. If you know a night is going to be heavy, discuss with your doctor whether a temporary dose adjustment makes sense - but never skip a dose without a plan.
☕ Coffee, Caffeine and Energy Drinks
Caffeine causes a brief small rise in BP - typically 3 to 8 mmHg for 1 to 3 hours after a strong cup - but the effect fades in habitual drinkers. It does not directly interact with P-Nolol at a metabolic level. But there are specific caveats for beta-blocker users.
Coffee on P-Nolol - the practical rules
- Up to 3-4 cups of coffee per day is compatible with well-controlled BP or heart rate
- Do not measure BP or pulse within 30-60 minutes of coffee - readings will be artificially raised
- Habitual heavy drinkers develop tolerance - the BP bump is smaller than in occasional drinkers
Caffeine for migraine users
Caffeine can be both a migraine trigger and (paradoxically) a migraine reliever. Consistent daily intake is fine; sudden changes in caffeine (a missed morning coffee, a very large intake before an exam) commonly trigger migraine attacks in susceptible clients. Keep your caffeine habit stable.
Energy drinks - a different story
Energy drinks combine large caffeine loads (often 200-400 mg per can) with sugar, taurine, guarana, and sometimes borderline ephedrine-type extracts. They produce a larger and longer BP spike, sometimes palpitations or arrhythmias.
On P-Nolol, energy drinks are best kept to an occasional small can - not a daily habit, and not before exercise. For AF or arrhythmia clients, energy drinks are best avoided entirely.
Pre-workout supplements - be very careful
Many pre-workout supplements combine 200-400 mg of caffeine with stimulants that raise BP acutely and can trigger arrhythmias. On P-Nolol these can produce sudden BP swings that defeat the drug, and in arrhythmia clients they can precipitate an episode. If you use one, choose a caffeine-only or caffeine-plus-creatine kind, start with half a scoop, and check home BP and pulse during the session.
Decaf, tea, chocolate
Decaf coffee (2-15 mg caffeine per cup), tea (40-70 mg per cup) and chocolate contain small amounts that do not need avoidance on P-Nolol. Normal daily habits are fine.
If you notice palpitations, tremor, or unusual dizziness after coffee on P-Nolol, cut back. Otherwise, your usual habit is compatible with the drug and there is no need to give up your morning cup because you started BP treatment.
🩺 Home BP and Pulse Monitoring
Home monitoring on P-Nolol should include not just blood pressure but also pulse. Because propranolol slows the heart, tracking the resting pulse is one of the best ways to know whether the drug is at the right dose and whether the dose is working.
What to buy and how to measure
- Upper arm cuff BP monitor - modern models show pulse alongside BP
- Validated model (BHS, ESH or dabl accreditation)
- Correct cuff size for your arm
- Automatic (oscillometric)
Measurement technique
- Sit quietly for 5 minutes before the first reading
- Back supported, feet flat on the floor
- Cuff on bare upper arm at heart level
- Do not talk or use your phone during measurement
- Take 2 readings 1-2 minutes apart; average them
- Ideally morning and evening; before P-Nolol and before coffee
- Record BP AND pulse each time
Target ranges on P-Nolol
| Measurement | Target on P-Nolol |
|---|---|
| Resting pulse | 55-70 beats per minute for most clients |
| BP (adults under 65) | Under 135/85 home average |
| BP (adults 65-79) | Under 140/85 |
| BP (adults 80+) | Under 145/85; fall risk matters more |
When the numbers are telling you something
- Pulse below 50 at rest - too much beta blockade; call your doctor
- Pulse above 80 despite the drug - dose may be too low, or dose timing is off
- BP consistently above target after 4-6 weeks - dose review
- BP below 100 systolic with dizziness - dose may be too high
- Sudden BP or pulse swings - possible arrhythmia, new drug interaction, or major life change
Bring your recorded readings to every doctor visit. The pattern of resting pulse across weeks is often the most useful information for beta-blocker titration.
⚖️ P-Nolol Doses and How They Are Adjusted
P-Nolol dosing depends on the indication. Angina, migraine, tremor and thyrotoxicosis each have their own typical dose ranges. This section covers the general principles; sections 5, 6 and 7 give indication-specific doses.
Available strengths
| Formulation | Strengths |
|---|---|
| Regular tablets | 10 mg, 20 mg, 40 mg, 80 mg |
| Long-acting capsules | 60 mg, 80 mg, 120 mg, 160 mg |
Typical dose ranges by indication
- Hypertension: 80-240 mg total daily (rarely used today)
- Angina: 80-320 mg total daily
- Post-heart-attack: 180-240 mg total daily
- Atrial fibrillation rate control: 40-320 mg total daily
- Migraine prevention: 80-160 mg total daily (occasionally up to 240 mg)
- Essential tremor: 80-320 mg total daily
- Performance anxiety: single dose 10-40 mg before event
- Portal hypertension: titrated to reduce resting pulse by 25% or to 55 bpm
- Thyrotoxicosis symptomatic: 40-320 mg total daily until definitive treatment takes effect
Titration principles
- Start low (usually 20-40 mg twice daily, or 60-80 mg LA once daily)
- Rise slowly every 1-2 weeks
- Target dose based on effect - resting pulse, BP, symptom control
- Do not push above 320 mg daily without specialist input
- Once at maintenance, stay there for months before considering changes
When dose is adjusted downward
- Resting pulse below 50 at rest
- Persistent symptomatic low BP
- Severe fatigue or exercise intolerance that has not adapted by month 2
- New wheeze or breathlessness - do not just reduce dose, review with doctor
- New or worsening depression
- Progression of heart block on ECG
Do not adjust dose yourself
Sudden dose changes on P-Nolol - especially sudden reductions or stopping - can trigger rebound tachycardia and cardiovascular events (Section 24). If you think the dose is wrong, that is a conversation with your doctor - not a solo experiment.
🔗 Combining P-Nolol With Other Drugs
P-Nolol is sometimes used alone but is more often combined with other drugs, depending on the indication.
Common combinations for angina
- P-Nolol + long-acting nitrate (isosorbide mononitrate) - two mechanisms for chest pain prevention
- P-Nolol + dihydropyridine calcium blocker (amlodipine) - safe combination; complementary
- P-Nolol + short-acting nitrate (rescue) - carry sublingual nitroglycerin for acute attacks
- P-Nolol + aspirin + statin - foundation of secondary prevention
Common combinations for hypertension (when used)
- P-Nolol + ACE inhibitor or ARB
- P-Nolol + calcium channel blocker (amlodipine)
- P-Nolol + thiazide diuretic - older combination, less used today
Common combinations for arrhythmia
- P-Nolol + digoxin - rate control in atrial fibrillation, especially in older clients
- P-Nolol + anticoagulant (warfarin, apixaban, rivaroxaban, dabigatran) - AF stroke prevention
- P-Nolol + amiodarone - rhythm control in AF or ventricular arrhythmias; specialist-guided
Combinations to AVOID
- P-Nolol + verapamil OR diltiazem - additive negative effects on heart rate and contractility; can cause severe bradycardia or heart block. Only under specialist supervision.
- P-Nolol + another beta-blocker - redundant, harmful
- P-Nolol + clonidine sudden withdrawal - can precipitate severe hypertension
- P-Nolol + high-dose sotalol or amiodarone - additive risk of arrhythmia through electrolyte and QT effects
The combination and dose you are on has been thought about by your doctor. Any addition of a new drug (prescription, over-the-counter, or supplement) should be mentioned to your pharmacist as "I take P-Nolol" so interactions are checked in seconds.
⚠️ Drug Interactions You Need to Know About
P-Nolol has a substantial list of drug interactions because it is metabolised by liver enzymes (mainly CYP2D6 and CYP1A2) and because it directly affects heart rate and BP - both of which are affected by many other drugs.
Interactions that matter most
| Drug/class | Why it matters |
|---|---|
| Verapamil, diltiazem | Additive bradycardia, heart block risk |
| Digoxin | Additive slowing of AV node; useful in AF but needs monitoring |
| Clonidine | Clonidine withdrawal on top of beta-blocker can cause hypertensive crisis |
| Amiodarone | Additive bradycardia and QT effects |
| Insulin, sulfonylureas | P-Nolol masks warning signs of low blood sugar (Section 23) |
| Warfarin | Small INR increase possible; keep monitoring regular |
| Rifampicin (TB drug) | Speeds propranolol metabolism; effective dose falls |
| Cimetidine, fluoxetine, paroxetine (CYP2D6 inhibitors) | Raise propranolol blood levels; watch bradycardia |
| Ergotamine (migraine acute treatment) | Can cause peripheral vasoconstriction; avoid combination |
Drugs to consider carefully
- NSAIDs (ibuprofen, naproxen) - can blunt the BP effect
- Nasal decongestants with pseudoephedrine - can raise BP
- Beta-agonist inhalers (salbutamol, formoterol) - propranolol partially blocks their effect on airways
- Anti-arrhythmics (sotalol, flecainide) - specialist territory
- General anaesthetics - see Section 24 for surgery context
Over-the-counter drugs and supplements to watch
- Ibuprofen, naproxen, diclofenac gels - even topical NSAIDs count
- Cold and flu combination products - many contain pseudoephedrine or phenylephrine
- Herbal appetite suppressants containing ephedrine, ma huang, or "fat burners"
- St John's wort - accelerates propranolol metabolism
The simplest rule: any new prescription, over-the-counter drug or supplement should be flagged with "I take P-Nolol" to your pharmacist. Beta-blockers have more interactions than ARBs or CCBs, so a quick check at the counter prevents most surprises.
🚨 Side Effects of P-Nolol
This section is a reference bookmark. It groups P-Nolol side effects by how likely they are and how much attention they deserve, and links to deeper sections for the ones that need their own space.
✅ Common but usually mild and often temporary
- Fatigue and reduced exercise tolerance (Section 18)
- Cold hands and feet (Section 19)
- Vivid dreams or unusual sleep (Section 20)
- Mild dizziness on standing (first 1-2 weeks)
- Mild slowing of pulse (part of the mechanism, not really a side effect)
Watch for and monitor
- Wheeze or breathlessness - possible bronchospasm (Section 22)
- Symptoms of low blood sugar being masked if diabetic (Section 23)
- Sexual dysfunction (Section 21)
- Depression or mood changes
- Reduced Raynaud tolerance in cold conditions (Section 19)
- Worsening of psoriasis in some clients
🚨 Rare but STOP P-Nolol and seek urgent care if:
- Severe wheeze or asthma attack - possible bronchospasm
- Fainting or near-fainting
- Severe bradycardia (pulse below 40)
- New severe chest pain
- New severe breathlessness at rest
- Severe skin rash with blistering
- Confusion or unusual drowsiness
- Severe depression with self-harm thoughts
The one non-negotiable rule
Section 24 is the one that every P-Nolol client must know cold: never stop the drug abruptly. If side effects are severe enough to stop, do it gradually over 1-2 weeks under medical guidance - not overnight.
Most people on P-Nolol tolerate the drug well, especially after the first 2-4 weeks of adaptation. The value of knowing the side-effect list is not to worry - it is to spot the rare event early enough to act.
🔋 Fatigue and Reduced Exercise Tolerance
Fatigue is the single most common reason clients ask about stopping a beta-blocker. Understanding why it happens and what to do about it helps you separate a manageable adjustment from a genuine problem that needs a switch.
Why P-Nolol causes fatigue
The drug slows the heart, reduces cardiac output, and blunts the sympathetic response. In practical terms, when you climb stairs, run for a bus, or exert yourself, your heart cannot speed up and pump harder in the same way it did before. You feel tired sooner, and your usual activities may feel more effortful for a few weeks.
The adaptation curve
- Weeks 1-4: most pronounced fatigue, especially with exercise
- Weeks 4-8: the body compensates through increased oxygen extraction and other adaptations
- Month 3 and beyond: most clients feel largely normal at rest and light activity; high-intensity exercise may still feel slightly reduced
- Chronic fatigue that never adapts is one of the reasons for a switch to a cardio-selective beta-blocker or a different class
What helps
- Regular gentle activity - the body adapts faster if you keep moving
- Adequate sleep - propranolol can affect sleep quality (Section 20), which compounds fatigue
- Adequate hydration
- Check for coexisting issues - anaemia, low thyroid, sleep apnoea, depression - all can add to the fatigue attributed to the beta-blocker
- Move the evening dose earlier if fatigue is worst in the evening
- Consider switching to a cardio-selective beta-blocker (metoprolol, bisoprolol) if fatigue does not settle by month 3
When fatigue is not typical P-Nolol adaptation
- Getting worse over months rather than better
- With breathlessness at rest - possible new heart failure
- With low mood, weight change, or hair changes - possible thyroid issue
- With ankle swelling and breathlessness on exertion - possible new heart problem
- With sleep disturbance that could be sleep apnoea
Persistent unusual fatigue is worth investigating rather than attributing entirely to the drug.
For most clients, fatigue on P-Nolol adapts within 2-3 months. If it does not, a switch is a reasonable option to discuss - not a solo decision to stop the drug.
🧤 Cold Hands, Cold Feet and Raynaud Reactions
Cold hands and feet, especially in cool weather, are one of the more distinctive side effects of non-selective beta-blockers like propranolol. This happens because beta-2 receptors in peripheral blood vessels contribute to vasodilation; blocking them shifts the balance toward vasoconstriction.
What clients typically notice
- Cold fingers and toes even in mild cold weather
- Slower return of colour after hands are exposed to cold water
- Reduced tolerance for outdoor winter activities where hands or feet are exposed
- Worsening of pre-existing Raynaud phenomenon
- Cold nose and ears in some clients
Raynaud phenomenon - a specific concern
Raynaud phenomenon (cold-triggered spasm of finger and toe arteries turning digits white, then blue, then red) can be worsened by non-selective beta-blockers. If you have known Raynaud, propranolol is usually not the first-choice beta-blocker - a cardio-selective one (bisoprolol, metoprolol) fits better. Discuss with your doctor if attacks worsen after starting P-Nolol.
What helps
- Warm layered gloves and thick socks in cold weather
- Hand warmers for outdoor activities
- Avoid handling frozen items with bare hands
- Keep whole body warm - if the core is warm, the periphery follows
- Regular movement of fingers and toes to maintain circulation
- Do not smoke - nicotine dramatically worsens peripheral vasoconstriction
- Consider switch to cardio-selective beta-blocker if problem is troublesome
When cold hands or feet need urgent attention
- Persistent numbness or loss of feeling that does not warm up
- Colour change to black or dusky purple that does not resolve
- Painful ulcers on fingertips or toes
- Severe Raynaud attacks lasting hours
These need urgent medical assessment - possible peripheral vascular disease or severe vasospasm requiring different management.
For most clients, cold hands and feet on P-Nolol are a manageable inconvenience with warm clothing and sensible habits. If Raynaud develops or worsens dramatically, a switch to a different beta-blocker or class is a reasonable option to discuss.
💤 Sleep Disturbances and Vivid Dreams
Propranolol crosses into the brain more readily than most other beta-blockers because it is highly lipid-soluble. This CNS access is useful for performance anxiety and tremor control, but it comes with the flip side - some clients experience unusual sleep, vivid dreams, or nightmares.
What clients typically report
- Vivid dreams - more emotional or memorable than usual
- Nightmares - sometimes with themes of falling, being chased, or death
- Difficulty falling asleep
- Awakenings during the night
- Feeling less rested in the morning despite adequate sleep hours
Why P-Nolol affects sleep more than some beta-blockers
Propranolol is lipid-soluble - it enters the brain freely. Once in the brain, it interacts with sleep-regulating pathways, including those governing REM sleep (the phase when most vivid dreaming happens). Water-soluble beta-blockers like atenolol or nadolol enter the brain much less and cause fewer sleep disturbances.
What helps
- Take the last dose of the day earlier - dinner rather than bedtime
- Split total daily dose more evenly so the peak blood level is not at bedtime
- Good sleep hygiene - regular bedtime, cool bedroom, no screens before bed
- Avoid heavy meals or alcohol before bed
- If dreams are severely disturbing, discuss switching to a water-soluble beta-blocker (atenolol, nadolol) - fewer CNS effects
When sleep issues need review
- Persistent disabling nightmares beyond month 2
- Insomnia that affects daytime function
- New depression symptoms alongside sleep disturbance
- Sleep-walking or acting out dreams (possible REM behaviour issues)
- Snoring with witnessed pauses in breathing - possible sleep apnoea
For most clients, vivid dreams on P-Nolol are a mild curiosity that fades over weeks. When they persist and become disruptive, a switch to a cardio-selective or water-soluble beta-blocker often solves the problem while keeping the cardiovascular benefit.
💗 Sexual Function on P-Nolol
Sexual function on beta-blockers has a mixed reputation. Propranolol has been associated with erectile difficulty in some men and (less commonly) with reduced libido or arousal in both sexes. The effect is dose-related, may improve after weeks-to-months of adaptation, and is not universal.
Why beta-blockers can affect sexual function
Beta-blockade reduces the sympathetic arousal that partly drives erectile function and libido. Blood flow to genital tissue may be slightly reduced. And for men with baseline cardiovascular disease that predisposes to erectile difficulty, the addition of a beta-blocker can tip a borderline situation.
In men
- Erectile difficulty - reported in about 5-15 percent of men on beta-blockers
- Reduced libido in a smaller fraction
- Delayed or altered orgasm occasionally
- Effect is dose-related - lower doses cause fewer issues
In women
- Less commonly reported, but reduced libido and altered arousal do occur
- Effect is usually mild and often adapts
- Other causes should be considered - hormonal changes, other medications, mood
What to do if you notice a change
- Raise it with your doctor - this is common enough to be a normal topic
- Rule out other causes - new diabetes, low testosterone, sleep apnoea, depression, stress
- Consider dose reduction if BP or symptoms allow
- PDE5 inhibitors (sildenafil, tadalafil) work well for erectile difficulty and are compatible with P-Nolol - but not with nitrates
- Consider switching to a different beta-blocker - some (nebivolol) are reported to have less sexual effect
- Do NOT self-treat by stopping P-Nolol - abrupt withdrawal is dangerous (Section 24)
Sexual function is a legitimate quality-of-life issue
Do not accept a change silently. Options exist and most men and women can be helped back to their baseline with the right conversation.
🫁 Asthma and Airway Warning
This is one of the two most important safety sections in this guide. Propranolol is a non-selective beta-blocker - it blocks both beta-1 (heart) and beta-2 (airways) receptors. In someone with asthma or reversible airway disease, blocking beta-2 receptors can trigger bronchospasm (a sudden narrowing of the airways) - which can be severe and life-threatening.
🚩 P-NOLOL IS CONTRAINDICATED IN ASTHMA
Do NOT take P-Nolol if you have:
- Asthma of any severity
- Reversible chronic obstructive airway disease
- History of childhood asthma that has "grown out" - can return
- Frequent chest infections with wheeze
- Known severe reactions to previous beta-blockers
Why non-selectivity matters
Airway smooth muscle carries beta-2 receptors. Adrenaline binding to these receptors causes airway dilation. Blocking them with propranolol shifts the airway toward constriction. In someone with normal airways, this rarely matters. In someone with asthma - where airways are already twitchy - it can precipitate a severe attack.
Cardio-selective beta-blockers (bisoprolol, metoprolol, atenolol, nebivolol) block mainly beta-1 and are safer in mild airway disease - but even they are used with caution and specialist input in asthma.
Warning signs of bronchospasm
- Wheeze on breathing out
- Chest tightness
- Difficulty breathing at rest
- Prolonged breathing out
- Speech in short phrases only
- Blueness of lips (severe cases)
If any of these appear, use your rescue inhaler if you have one (though beta-blockers partially block its effect) and call emergency services immediately.
COPD and P-Nolol
Chronic obstructive pulmonary disease (COPD) is a spectrum. Non-reversible COPD without significant bronchial reactivity can sometimes tolerate cardio-selective beta-blockers under specialist supervision. Non-selective P-Nolol is generally avoided in COPD unless the alternatives are unavailable and the specific indication is compelling.
If asthma appears after starting P-Nolol
Sometimes airway problems develop or become clear only after the drug is started. Any new wheeze, cough with wheeze, or exercise-induced breathlessness while on P-Nolol should trigger a call to your doctor. The drug can usually be switched to a cardio-selective beta-blocker or a different class - but the switch itself must be gradual to avoid rebound (Section 24).
The asthma warning is one of the most important prescribing rules in cardiovascular medicine. If you have any airway history and are being offered P-Nolol, this must be discussed carefully. If asthma was missed at prescribing and airway symptoms appear, do not just tolerate them.
🍬 Diabetes on P-Nolol - Masking Low Blood Sugar
This is the second critical safety section. In diabetic clients - especially those on insulin or sulfonylureas - P-Nolol can mask the early warning symptoms of low blood sugar (hypoglycaemia). Understanding this changes how a diabetic client should use the drug, monitor glucose, and respond to symptoms.
How normal hypoglycaemia warning works
When blood sugar drops, the body releases adrenaline. Adrenaline speeds the heart (palpitations), causes shaking (tremor), triggers sweating, and makes the person feel anxious and hungry. These sympathetic symptoms typically appear at glucose levels around 3.5-4.0 mmol/L (63-72 mg/dL) and prompt the person to eat sugar quickly.
🚨 How P-Nolol changes this
Propranolol blocks the sympathetic warning symptoms. The palpitations, tremor, and anxiety that would normally alert you to low blood sugar are muted. Sweating usually remains (it is sympathetic but not beta-mediated), but the classical "racing heart" alarm is gone.
The result: you may not notice hypoglycaemia until the sugar drops much lower - to the point where confusion, drowsiness, or loss of consciousness are the first symptoms.
Which diabetic clients are most affected
- Type 1 diabetes on insulin - highest risk
- Type 2 diabetes on insulin - high risk
- Type 2 diabetes on sulfonylureas (gliclazide, glimepiride, glipizide) - moderate risk
- Type 2 diabetes on metformin alone or on DPP-4/GLP-1/SGLT2 drugs - low risk (these do not typically cause hypoglycaemia)
Practical safeguards for diabetic clients on P-Nolol
- Check blood glucose more often - especially before exercise, before driving, and before bed
- Consider continuous glucose monitoring (CGM) if available - it warns of drops in real time
- Do not skip meals
- Have fast-acting glucose (tablets, gel, sugary drink) always within reach
- Watch for "atypical" hypoglycaemia symptoms - fatigue, difficulty concentrating, mood change, headache
- Talk to your diabetes team - insulin or sulfonylurea doses may need adjusting
- Consider a cardio-selective beta-blocker as an alternative if P-Nolol is not essential
When P-Nolol is not first choice in diabetes
Modern practice generally prefers cardio-selective beta-blockers (bisoprolol, metoprolol) in diabetic clients when a beta-blocker is needed. They still can mask hypoglycaemia to some degree, but less so than propranolol. If you are diabetic and were prescribed P-Nolol specifically (for migraine, tremor, or a non-cardiac indication), the discussion is about whether the specific benefit outweighs the hypoglycaemia risk in your situation.
⛔ Never Stop P-Nolol Abruptly - Rebound and Surgery
This is the third critical safety section and the one that is most universally applicable. Never stop P-Nolol abruptly after long-term use. Sudden discontinuation of any beta-blocker can trigger rebound sympathetic activation - accelerating heart rate, raising BP, worsening angina, and in the worst cases precipitating a heart attack or serious arrhythmia. This is a real, well-documented phenomenon.
🚩 THE WITHDRAWAL RULE
If P-Nolol needs to be stopped (side effects, switching to another drug, planned surgery, pregnancy), it must be tapered gradually - typically over 1-2 weeks:
- Halve the dose for the first week
- Halve again for the second week
- Stop entirely at week 3
- Monitor pulse and BP throughout the taper
- In coronary artery disease clients, the taper is even slower (4-6 weeks) and done under medical supervision
Why the rebound happens
Long-term beta blockade causes the body to upregulate beta receptors (making more of them, or making the existing ones more sensitive) to try to maintain normal function. When the block is suddenly removed, the extra receptors are all activated at once - producing an exaggerated sympathetic response. Heart rate can rise dramatically, BP can spike, and in vulnerable coronary arteries the sudden increased demand can precipitate angina or infarction.
Surgery and P-Nolol - the practical rules
General rule: continue P-Nolol through the perioperative period. Take the morning dose on the day of surgery unless the anaesthetist specifically instructs otherwise.
Why: stopping beta-blockers before surgery increases the risk of perioperative cardiac events. Continuing them is one of the well-established rules of perioperative cardiac care.
Cannot swallow tablets postoperatively? The anaesthetic team can give intravenous beta-blocker equivalents to bridge the gap. Just make sure they know you are on P-Nolol.
Situations where the withdrawal rule is at highest stakes
- Coronary artery disease with angina history - highest risk of rebound MI
- Post-heart-attack long-term use
- Chronic atrial fibrillation on rate control - can precipitate uncontrolled fast rhythm
- Thyrotoxicosis symptomatic use - underlying condition still active
- Cirrhosis with varices - stopping increases bleeding risk from portal hypertension
If you must stop for genuine safety reasons
Bronchospasm from asthma or severe adverse reaction requires immediate stopping - but even then, the client should be watched carefully in the days after, and a cardiologist consulted about how to manage the rebound risk. Ideally the stopping happens in a monitored setting.
The withdrawal rule is one of the most important lessons of beta-blocker practice. Every P-Nolol client should know it, and every doctor prescribing the drug should reinforce it. Never stop this drug without a plan.
⏱️ What to Do If You Forget or Miss a Dose
Missing a dose of P-Nolol is not as forgiving as missing a dose of a long-half-life BP pill like amlodipine or telmisartan. Because propranolol has a short half-life (3-6 hours for regular, 8-14 hours for LA), blood levels drop off relatively quickly, and heart rate can start to rebound within hours.
Rules for missed doses
| Situation | What to do |
|---|---|
| Realised within 4 hours of usual time (regular) | Take the dose now. Continue usual schedule. |
| Realised close to the next scheduled dose | Skip the missed one. Take the next at its usual time. Do NOT double up. |
| Missed all doses for 1 full day | Resume normal schedule the next day. Home BP and pulse may be raised; expect this. |
| Missed all doses for 2-3 days or more | Rebound is possible. Call your doctor. Restart at the maintenance dose but be alert for angina, palpitations, or high BP over the next few days. |
Do not double up
Taking two P-Nolol doses close together can produce excessive bradycardia and hypotension. It is one of the most common causes of preventable complications on this drug.
Practical tricks to not forget
- Weekly pillbox with 2-3 compartments per day
- Phone alarms at each dose time, labelled with which dose it is
- Anchor each dose to a habit - meals, teeth brushing, going to bed
- Keep the bottle visible, not hidden in a drawer
- Refill before you run out
- Extra supply for travel - never rely on pharmacy access in unfamiliar countries
Running out entirely - the highest risk scenario
Running out of P-Nolol completely for several days is the most dangerous form of "missed dose". It effectively becomes abrupt withdrawal (Section 24). This is one of the few situations where an emergency prescription is genuinely justified rather than waiting for a routine appointment. Do not let this happen.
🌙 P-Nolol for Night Shift Workers
Night shift and rotating shift workers on P-Nolol face two challenges: the multi-daily dosing (for regular tablets) has to work around irregular days, and disrupted sleep can worsen the CNS side effects of propranolol (vivid dreams, insomnia).
Reframe the schedule around your personal day
Whether your day starts at 7 am or 4 pm, the principle is the same:
- Morning dose - shortly after you wake
- Midday dose (if on regular tablets) - mid-way through your active hours
- Evening dose (if on regular tablets) - with your main meal, not close to your main sleep
- Once-daily LA - whenever you will remember consistently
The two-schedule problem
If you rotate between night shifts and days off, options:
- Keep the same clock time year-round - simplest but may create gaps
- Shift with your rotation - move doses earlier or later over 2-3 days when your schedule changes
- Ask your doctor about switching to once-daily LA - much easier on shift work
- Or consider switching to a longer-acting beta-blocker (bisoprolol, nadolol) once-daily
Extra shift-work considerations on P-Nolol
- Sleep quality matters - poor sleep worsens P-Nolol's effect on dreams and fatigue
- Watch caffeine and energy drinks (Section 12)
- Bring water to shifts - dehydration adds to fatigue
- Take home BP and pulse at consistent points in your rotation
- Watch salt intake on canteen and vending machine food
- Tell your GP about your schedule
The bigger picture
Long-term night-shift work is associated with higher cardiovascular disease risk independent of any specific pill. P-Nolol addresses the heart rate and BP piece but does not fix the underlying shift-work risk. Where feasible, discuss shift patterns and sleep hygiene with your occupational health service.
🚗 P-Nolol for Drivers and Machine Operators
Driving and machine operation on P-Nolol deserve some caution because fatigue, dizziness, and (in first weeks) reduced exercise tolerance are real. Once you are settled on the dose, most clients drive normally without any issue.
When dizziness or fatigue is most likely on P-Nolol
- First 1-2 weeks after starting
- First week after any dose increase
- 1-3 hours after each dose during the first week
- After alcohol (Section 11)
- Hot weather with low fluid intake
- Standing up quickly from a car seat after a long drive
Practical driving rules on P-Nolol
- Do not drive in the first 24-48 hours after starting or after a dose increase
- Do not drive if you feel dizzy, unusually tired, or unwell
- Avoid alcohol before driving
- Stand up slowly from a car seat after long journeys
- Keep water within reach in the vehicle
- Take breaks every 90-120 minutes on long journeys
- If diabetic, check blood sugar before driving - P-Nolol masks hypoglycaemia warnings (Section 23)
Commercial drivers and safety-critical roles
Pilots, commercial drivers and other safety-critical workers should check specific rules of their regulator or employer. P-Nolol is generally acceptable once stable, but declaration may be required. The multi-daily dosing schedule may not suit some occupational routines; consider whether once-daily LA fits your job better.
Machinery operators
The same principles apply for operating dangerous machinery. Do not operate in the first 3-5 days after starting P-Nolol or a dose increase. If you feel unusual fatigue or dizziness, stop, sit, drink water. Once your body has adapted (usually within 2 weeks), machinery work is usually fine.
💪 P-Nolol, Exercise and Sports
Exercise on beta-blockers deserves specific attention because the drug limits how much the heart can speed up during exertion. This changes what "hard exercise" feels like and how you should judge intensity.
Why exercise feels different on P-Nolol
Beta blockade limits the heart's ability to speed up in response to exertion. Your maximum heart rate is capped 20-30 beats per minute below what it would be off the drug. This has three consequences:
- Peak exercise capacity is reduced - you cannot run as fast or lift as heavy as you might otherwise
- Heart rate is not a good measure of exercise intensity - the usual "220 minus age" formulas overestimate what you can achieve
- Rate of perceived exertion (how hard it feels) is a better guide than a fitness watch heart rate
✅ Exercise that fits well with P-Nolol
- Walking, jogging (moderate pace), cycling, swimming
- Yoga, pilates, tai chi
- Moderate weight training with rest between sets
- Recreational team sports at moderate intensity
- Aim for at least 150 minutes of moderate activity per week
Where to be careful on P-Nolol
- Competitive high-intensity sports - performance is genuinely reduced
- Endurance in hot weather - dehydration adds to BP drop
- Very heavy strength training - spikes BP acutely
- Hot yoga, saunas after workout - can cause faint
- Pre-workout stimulant supplements (Section 12)
Angina and exercise - a specific note
If you take P-Nolol for angina, exercise is not off the menu - in fact controlled aerobic exercise is part of good cardiac care. But the drug's role is precisely to raise your angina threshold so you can exercise further before pain appears. Always carry your short-acting nitrate spray. If you get sudden new chest pain at lower exertion than usual, stop, rest, and if it does not settle in 10-15 minutes with nitrate, call emergency services.
Do not stop P-Nolol before exercise
Some clients think they can perform better on race day by skipping the drug. This is dangerous - abrupt beta-blocker withdrawal in the setting of exertion is a documented cause of exercise-induced cardiac events. If you compete and want to discuss exercise performance, that is a conversation with your doctor about medication choice, not about self-directed skipping.
🫘 P-Nolol for Chronic Kidney Disease
Propranolol is mostly cleared by the liver, not the kidneys, so kidney impairment usually does not require dose adjustment. This is one of the advantages of the drug in CKD.
What kidney filter score means for P-Nolol
| eGFR (kidney filter score) | Approach |
|---|---|
| 60 or higher | Standard dose and titration |
| 30-59 (mild-moderate CKD) | Standard dose; no adjustment needed |
| 15-29 (severe CKD) | Standard dose usually still fine; nephrology input for combinations |
| Under 15 / dialysis | Standard dose; not filtered by dialysis meaningfully (highly protein-bound) |
Practical points in CKD
- Beta-blockers are commonly used in CKD for BP and cardiac protection
- Fluid balance can shift more in dialysis clients - watch BP around dialysis sessions
- Diabetic CKD clients - hypoglycaemia masking (Section 23) matters even more, since diabetic autonomic neuropathy already blunts warning signs
- Combined with ACE inhibitor or ARB - watch potassium (though propranolol itself does not raise potassium meaningfully)
In someone with CKD, propranolol's liver metabolism is a practical advantage over drugs that need dose reduction in kidney impairment. What matters is the pulse and BP response, not the eGFR.
🌱 P-Nolol and Pregnancy - Serious Warning
Propranolol has been used in pregnancy for decades - for pre-existing hypertension, migraine, thyrotoxicosis, and certain arrhythmias. It has more human pregnancy experience than most other cardiovascular drugs. That said, it is not without concerns, and pregnancy management should be led by an obstetric team.
If you become pregnant on P-Nolol
Do not stop the drug abruptly. Call your doctor and obstetric team within 24-48 hours to discuss whether to continue at current dose, modify, or switch. Sudden withdrawal in pregnancy has its own risks for both you and the pregnancy.
Known concerns during pregnancy
- Fetal growth restriction - beta-blockers have been associated with smaller babies, especially with atenolol; less consistent for propranolol
- Fetal bradycardia - baby's heart rate may be slower on maternal beta-blocker
- Neonatal hypoglycaemia - baby may have low blood sugar after birth if exposed near delivery
- Neonatal bradycardia or hypotension - transient, in the first days after birth
When P-Nolol is commonly continued in pregnancy
- Chronic hypertension where alternatives have not been tolerated
- Severe migraine in an otherwise disabled client
- Thyrotoxicosis symptomatic control until definitive treatment
- Hypertrophic cardiomyopathy or arrhythmia where the drug is essential
- Portal hypertension in cirrhosis - continued in pregnancy to prevent bleeding
Pregnancy-safe alternatives
- Labetalol - often preferred beta-blocker in pregnancy
- Methyldopa - long safety record for BP in pregnancy
- Slow-release nifedipine - for BP
Delivery planning
Your obstetric team should know you are on P-Nolol. The baby may need brief monitoring for bradycardia or low blood sugar in the first hours after birth. This is usually straightforward and does not require nursery admission in most cases.
Contraception on P-Nolol
P-Nolol does not affect hormonal contraception. If you are of childbearing age and not planning pregnancy, use effective contraception - but plan the switch to a safer drug (if needed) in advance of trying to conceive.
🍼 P-Nolol While Breastfeeding
Propranolol passes into breast milk in small amounts. The American Academy of Pediatrics and other bodies list it as compatible with breastfeeding, and no consistent reports of harm to the breastfed baby have appeared.
Current guidance for breastfeeding on P-Nolol
- Compatible with breastfeeding in most guidelines
- Baby monitoring: feeding, wet nappies, weight gain, alertness; report any concerns to your GP or paediatrician
- If the baby is premature or has other health issues, discuss with paediatric team - more monitoring may be needed
- Peak infant exposure is 2-3 hours after your dose - some mothers try to feed the baby just before their next dose to minimise transfer
Practical tips for new mothers
- Take home BP and pulse - the first months after birth are a time of change
- Ask about safe painkillers: paracetamol is generally fine while breastfeeding
- Report severe headache, vision change, or persistent very high BP promptly
- Stay well hydrated
Returning to full-dose P-Nolol after weaning
Once you have stopped breastfeeding, you can generally continue P-Nolol at the maintenance dose that worked for you before. The pregnancy and postpartum period is a time when doses are sometimes adjusted; your doctor will help settle the long-term dose.
📚 P-Nolol for Children and Teenagers
P-Nolol has a substantial history of paediatric use, particularly for infantile haemangiomas (where propranolol has become first-line since 2008) and for certain paediatric cardiac and thyroid conditions. But for hypertension in children, propranolol is rarely first-line.
Paediatric uses of propranolol
- Infantile haemangiomas (proliferative vascular growths) - now first-line at low doses; specialist paediatric care
- Certain paediatric arrhythmias - specialist-guided
- Hyperthyroidism in older children - symptomatic control
- Migraine prevention in adolescents - occasionally used; specialist-guided
- Essential tremor in adolescents - rare use
Paediatric hypertension
In children with hypertension, the underlying cause almost always needs specialist investigation first (kidney disease, hormonal problem, coarctation). ACE inhibitors and calcium channel blockers are usually preferred first-line. Propranolol's asthma and diabetes concerns make it a poor first choice.
Safe storage away from children
A single adult P-Nolol tablet can cause serious bradycardia and hypotension in a child who accidentally swallows one. Store P-Nolol out of reach and out of sight, ideally in a lockable drawer. If a child swallows any amount, call poison control immediately.
🕰️ P-Nolol for Older Clients (65 and Above)
P-Nolol is commonly used in adults over 65, particularly for angina, atrial fibrillation, and migraine prevention. But older clients need some specific considerations - propranolol's CNS effects and fatigue are often more pronounced with age, and bradycardia can compound existing conduction slowing.
Why some caution is needed in older adults
- Baseline heart rate is often already slower - beta-blockade may push it too low
- Sinus node function declines with age - risk of significant bradycardia rises
- CNS side effects (sleep, mood, confusion) are more common with age
- Fatigue takes longer to adapt to
- Polypharmacy interactions are more likely
- Diabetic autonomic neuropathy in older diabetics compounds the hypoglycaemia masking
Practical adjustments
- Start low (20 mg twice daily or 40 mg LA once daily) and rise slowly
- Check standing BP as well as sitting - orthostatic drops matter more in the elderly
- Consider a cardio-selective beta-blocker (bisoprolol, metoprolol) if fatigue or CNS effects are troublesome
- Watch for depression - beta-blockers are occasionally implicated
- Baseline ECG is useful to identify pre-existing conduction slowing
Where P-Nolol still fits well in older adults
- Atrial fibrillation rate control - proven effect
- Chronic stable angina - especially if a nitrate-plus-CCB regimen is insufficient
- Essential tremor - can genuinely improve quality of life
- Migraine prevention - cheap, effective
- Thyrotoxicosis in older clients (where atrial fibrillation and racing heart are common)
Age is not a reason to withhold P-Nolol. The care is in choosing the right dose (start low, go slow), monitoring the right things at the right intervals, and never being afraid to reduce or switch when tolerance is poor.
🧪 P-Nolol If You Have Liver Problems
Propranolol undergoes extensive first-pass metabolism in the liver - typically 60-70 percent of an oral dose is metabolised before it even reaches the systemic circulation. In liver disease, this first-pass effect can be reduced, leading to much higher blood levels than expected. Liver impairment matters more for propranolol than for many other cardiovascular drugs.
P-Nolol in different degrees of liver impairment
- Fatty liver (NAFLD) without cirrhosis: standard doses usually fine
- Mild liver problems: standard starting dose with closer monitoring
- Moderate liver problems: start at lowest dose (10-20 mg twice daily); rise slowly
- Cirrhosis: use with specialist input; blood levels can be dramatically raised
- Alcohol avoidance with any liver disease on P-Nolol
Portal hypertension - a paradox
Propranolol is specifically used in cirrhosis to prevent bleeding from gastro-oesophageal varices - the swollen veins in the food pipe that can rupture in advanced liver disease. Non-selective beta blockade reduces pressure in these veins by lowering cardiac output and constricting the vessels that supply the portal circulation. In this specific indication, the drug is essential despite the underlying liver disease. Cirrhotic clients on propranolol for varices have their heart rate reduced by about 25 percent as the target.
Rare liver reactions to propranolol itself
Very rarely, propranolol has been reported to cause acute liver injury or cholestatic jaundice. Yellowing of skin or eyes, dark urine, or pale stools while on P-Nolol warrant an urgent doctor visit and blood tests.
In someone with liver disease, the goal of P-Nolol therapy needs specialist input. The drug can be essential (varices), useful (some cardiac conditions), or problematic (if it accumulates and causes excess bradycardia). This is one of the situations where "call your doctor" rather than self-adjust is genuinely important.
🛑 Contraindications - When P-Nolol Must Be Avoided
This section is a reference list of situations where P-Nolol must NOT be used, or must be used with special caution. Show this list to any doctor, surgeon, or dentist about to prescribe you a new drug.
🛑 Absolute contraindications - do NOT take P-Nolol
- Asthma or reversible airway disease (Section 22)
- Second- or third-degree heart block (without a pacemaker)
- Sick sinus syndrome without pacemaker
- Severe bradycardia at baseline (pulse below 50)
- Cardiogenic shock
- Decompensated heart failure (though beta-blockers are used in stable HF)
- Severe symptomatic low BP
- Pheochromocytoma without prior alpha blockade - can cause hypertensive crisis
- Known severe allergy to propranolol
Relative contraindications - use with caution and specialist input
- Diabetes on insulin or sulfonylurea (Section 23)
- Severe peripheral arterial disease or Raynaud phenomenon
- Severe liver disease (Section 34)
- Depression history
- Psoriasis (can worsen)
- Myasthenia gravis
- Older frail clients with high fall risk
- Pregnancy (Section 30) - not absolute, needs obstetric input
Drugs to combine with caution
| Drug/Class | Reason |
|---|---|
| Verapamil, diltiazem | Severe bradycardia, heart block |
| Another beta-blocker | Redundant, harmful |
| Clonidine (especially withdrawal) | Hypertensive crisis risk |
| Amiodarone | Additive bradycardia |
| Insulin, sulfonylureas (in diabetes) | Masks hypoglycaemia warnings |
Situations to notify your doctor before continuing P-Nolol
- Planned surgery (Section 24)
- New wheeze or breathlessness (Section 22)
- Starting a new drug (especially verapamil, diltiazem, clonidine, amiodarone, insulin)
- Planning pregnancy or suspected pregnancy (Section 30)
- New heart failure symptoms (breathlessness, ankle swelling)
- Any fall or fainting episode
- New depression symptoms
🔄 Switching, Stopping, Storage and Your Yearly Review
P-Nolol is usually a long-term treatment. Some indications (post-heart-attack, migraine prevention, angina) may be lifelong; others (thyrotoxicosis, performance anxiety, situational tremor) may be time-limited. What all uses share is the withdrawal rule (Section 24): never stop abruptly.
Your yearly P-Nolol review should cover
- Home BP and pulse averages over the last months
- Standing BP measurement
- Symptoms of the underlying condition - angina attack frequency, migraine days per month, tremor severity, arrhythmia episodes
- Side effects - fatigue, cold extremities, sleep, sexual function, mood
- Any new airway symptoms
- Any new diabetes diagnosis or changes in glucose control
- New drugs added since last review, interaction check
- Lifestyle changes - alcohol, exercise, weight
- Adherence honestly - are you actually taking it every day?
- Refill plan for the next 12 months
Switching to a different regimen
Reasons your doctor might consider a switch include:
- New airway disease - switch to cardio-selective beta-blocker or different class
- Persistent troublesome fatigue - switch to cardio-selective
- Severe cold extremities or Raynaud - switch to cardio-selective
- Persistent disabling nightmares - switch to water-soluble beta-blocker (atenolol, nadolol)
- Sexual dysfunction - discuss options
- Pregnancy planning - review with obstetric input
- Migraine well-controlled for 6-12 months - can consider tapering off
🚨 Do NOT stop P-Nolol abruptly on your own
Section 24 covers this in detail. If you decide with your doctor to stop the drug:
- Taper the dose gradually over 1-2 weeks (longer in coronary disease)
- Monitor pulse and BP during and after the taper
- Have your rescue nitrate available if you take P-Nolol for angina
- Report any chest pain, palpitations, or high BP to your doctor promptly
Storage of P-Nolol at home
- Room temperature (about 15-30°C)
- Original packaging - protects from light and moisture
- Dry place - NOT the bathroom cabinet
- Do not refrigerate unless the label says otherwise
- Away from children and pets, lockable if possible
- Check expiry date before starting each new pack
- Return expired or leftover P-Nolol to a pharmacy for safe disposal
The bigger picture
P-Nolol - propranolol - is one of the most versatile drugs in cardiovascular medicine. Six decades since its first clinical use, it still holds specific roles in angina, arrhythmia, migraine, tremor, performance anxiety, thyrotoxicosis and portal hypertension. Its non-selectivity is both its strength (broad indications) and its limitation (asthma warning, hypoglycaemia masking).
Your job is simple: take it every day, know the emergency signs (severe wheeze, fainting, severe bradycardia), know the never-stop-abruptly rule, keep the yearly review appointment, tell every doctor and dentist that you take P-Nolol, and stay in touch with your doctor about anything unusual. Whatever the indication that brought you to the drug, used correctly it earns its place - just as it has for six decades.
P-Nolol — Frequently Asked Questions
-
What is P-Nolol (Propranolol)?
P-Nolol, also known by its generic name Propranolol, is a beta-blocker used to treat various cardiovascular conditions, including high blood pressure, angina, and arrhythmias. -
How does P-Nolol work?
P-Nolol works by blocking beta receptors in the heart and blood vessels, reducing heart rate, lowering blood pressure, and decreasing the heart's workload. -
What conditions does P-Nolol treat?
P-Nolol is used to treat hypertension, angina, arrhythmias, heart attack recovery, migraine prevention, essential tremor, anxiety, hypertrophic subaortic stenosis, and portal hypertension. -
How should I take P-Nolol?
Take P-Nolol as prescribed by your healthcare provider. It is typically taken orally, with or without food. Follow your doctor's dosage instructions carefully. -
What are the common side effects of P-Nolol?
Common side effects include fatigue, dizziness, nausea, vomiting, diarrhea, and cold hands and feet. These side effects are usually mild and temporary. -
Can I drink alcohol while taking P-Nolol?
It is advisable to limit alcohol consumption while taking P-Nolol, as it can increase the risk of side effects such as dizziness and low blood pressure. -
Can pregnant or breastfeeding women take P-Nolol?
Pregnant or breastfeeding women should consult their doctor before taking P-Nolol to understand the potential risks and benefits.
See all P-Nolol questions (32)
📚 Drug Description Sources:
The information in this P-Nolol (propranolol) guide is compiled from authoritative pharmaceutical, medical, and regulatory sources covering cardiovascular medicine, neurology, gastroenterology, and dermatology - reflecting propranolol's uniquely broad clinical portfolio. Content spans six decades of clinical experience from the drug's 1964 UK introduction as the first beta-blocker through modern applications in migraine prevention, portal hypertension, essential tremor, and infantile hemangioma.
🏛️ Regulatory and government agencies
- FDA (US Food and Drug Administration) - propranolol (Inderal) approval 1967 as the first beta-blocker in the US; subsequent approvals for angina, post-myocardial infarction mortality reduction, migraine prophylaxis, essential tremor, hypertrophic subaortic stenosis, and Hemangeol pediatric propranolol approval 2014 for infantile hemangioma
- WHO (World Health Organization) - propranolol on WHO Model List of Essential Medicines for hypertension, angina, and thyrotoxicosis
- EMA (European Medicines Agency) - propranolol European regulatory framework; Hemangiol approval for infantile hemangioma
- MHRA (UK Medicines and Healthcare products Regulatory Agency) - propranolol summary of product characteristics; historic UK origin at ICI
- Health Canada - propranolol product monograph with Canadian labelling
- TGA (Australian Therapeutic Goods Administration) - propranolol product information
- DailyMed (NIH/NLM) - current propranolol US prescribing information
📚 Professional societies and clinical guidelines
- American Academy of Neurology (AAN) and American Headache Society - Level A evidence for propranolol in migraine prevention; foundational neurology guideline
- European Federation of Neurological Societies - beta-blockers first-line for migraine prophylaxis
- American Association for the Study of Liver Diseases (AASLD) - propranolol for primary and secondary prevention of variceal bleeding in cirrhosis
- Baveno Consensus Conferences (Baveno VI, VII) - non-selective beta-blockers as cornerstone of portal hypertension management
- American Academy of Dermatology / American Academy of Pediatrics - propranolol first-line for infantile hemangioma
- ESC 2023 Acute Coronary Syndrome Guideline - beta-blocker use post-myocardial infarction
- American Thyroid Association - propranolol for thyroid storm and symptomatic hyperthyroidism
🔬 Landmark clinical research
- Black 1964 (Lancet) - original propranolol clinical description by Sir James Black at ICI; foundational paper that launched the beta-blocker era; Nobel Prize 1988
- BHAT Trial (Beta-Blocker Heart Attack Trial, JAMA 1982) - 3 837 post-MI clients; propranolol reduced 1-year mortality by 26 percent; foundational post-MI evidence
- Weber and Reinmuth 1972 (Neurology) - propranolol for migraine prevention; established neurological indication
- Winkler 1988 (New Engl J Med) - propranolol for essential tremor; foundational movement disorder trial
- Pascal 1987 (New Engl J Med) - propranolol for variceal bleeding prevention in cirrhosis
- Leaute-Labreze 2008 (New Engl J Med) - serendipitous discovery of propranolol for infantile hemangioma; transformed pediatric dermatology
- Leaute-Labreze 2015 (New Engl J Med) - definitive propranolol infantile hemangioma trial; 456 infants enrolled
- Neuhauser 2005 (Neurology) - propranolol in performance anxiety and social phobia
📖 Medical references and textbooks
- Goodman and Gilman Pharmacological Basis of Therapeutics - beta-adrenergic blocking agents chapter
- Braunwald's Heart Disease A Textbook of Cardiovascular Medicine - definitive cardiology reference on non-selective beta-blockers
- Bradley and Daroff Neurology in Clinical Practice - migraine and essential tremor management
- Sherlock's Diseases of the Liver - portal hypertension and beta-blocker therapy
- Katzung Basic and Clinical Pharmacology - beta-adrenergic antagonist pharmacology
- Nelson Textbook of Pediatrics - infantile hemangioma management
- UpToDate - propranolol clinical monographs across all indications
- Lexicomp and Micromedex - drug interactions, dosing tables, and adverse reaction data
Note: This information is educational and does not replace consultation with qualified healthcare providers. Individual medical circumstances vary substantially. Always follow prescriber instructions and report concerns promptly.
🩺 Medical Expert Review:
Content based on the published research and clinical practice of authorities across cardiovascular medicine, neurology, hepatology, and pediatric dermatology - reflecting propranolol's unusually diverse clinical portfolio. The following experts represent authoritative research and clinical practice perspectives on propranolol use spanning its cardiovascular origins through modern applications in migraine, portal hypertension, movement disorders, and infantile hemangioma.
Sir James Whyte Black, OM, FRS, FRSE, FRCP
Founding Professor of Pharmacology, King's College Hospital Medical School; formerly of ICI Pharmaceuticals — London, United Kingdom
Sir James Black is the foundational figure of beta-blocker pharmacology, having developed propranolol at ICI in 1964 as the world's first clinically successful beta-adrenergic antagonist. His work fundamentally reshaped cardiovascular medicine and earned him the 1988 Nobel Prize in Physiology or Medicine. He was appointed to the Order of Merit (OM) and knighted for services to medicine. Historical legacy widely cited as one of the most influential contributions to twentieth-century pharmacology.
Prof. Peter J. Goadsby, MD, PhD, DSc, FRS
Professor of Neurology, NIHR-Wellcome Trust King's Clinical Research Facility, King's College London; Visiting Professor, University of California Los Angeles — London, United Kingdom
Prof. Goadsby is arguably the world's foremost migraine researcher, having contributed foundational discoveries of CGRP pathway biology that led to the development of modern migraine-specific drugs. He was awarded the Brain Prize 2021 - considered the "Nobel Prize of neuroscience" - for this work. His scholarship on preventive migraine therapy including propranolol positioning has substantially informed American Academy of Neurology and international headache society guidelines.
Prof. Jaime Bosch, MD, PhD, FRCP
Emeritus Professor of Medicine, Hepatic Hemodynamic Laboratory, Hospital Clinic Barcelona, University of Barcelona — Barcelona, Spain
Prof. Bosch is an internationally recognised authority on portal hypertension and has chaired multiple Baveno consensus conferences that define global standards for variceal bleeding prevention and treatment. His research on non-selective beta-blocker use in cirrhosis including propranolol and carvedilol has directly shaped AASLD and EASL guidelines. He has authored over 500 peer-reviewed publications on hepatology and portal circulation.
Prof. Christine Leaute-Labreze, MD, PhD
Professor of Pediatric Dermatology, Department of Dermatology, Pellegrin Children's Hospital, University of Bordeaux — Bordeaux, France
Prof. Leaute-Labreze made the 2008 serendipitous discovery that propranolol dramatically shrinks infantile hemangiomas, published in New Engl J Med and considered one of the most important pediatric therapeutic breakthroughs of the century. She led the definitive 2015 New Engl J Med randomised trial in 456 infants that established propranolol as first-line therapy for problematic infantile hemangiomas, replacing decades of surgical and systemic corticosteroid approaches.
Prof. Stephen D. Silberstein, MD, FACP, FAHS, FAAN
Professor of Neurology, Director, Jefferson Headache Center, Thomas Jefferson University — Philadelphia, USA
Prof. Silberstein is a past President of the American Headache Society and chaired the AAN Guideline Development Subcommittee that established Level A evidence for propranolol in episodic migraine prevention. His scholarship on preventive migraine therapy, medication overuse headache, and cluster headache has substantially informed international neurology guidelines. He has authored over 500 peer-reviewed publications on headache medicine.
Disclosure: Expert names and credentials are cited for educational reference. This content is not endorsed by named experts. Content prepared by RXshop editorial team based on published literature and clinical guidelines.
More Blood Pressure Medications