Erectile Dysfunction as an Early Warning: What It Says About Your Arteries and Which Tests to Ask For

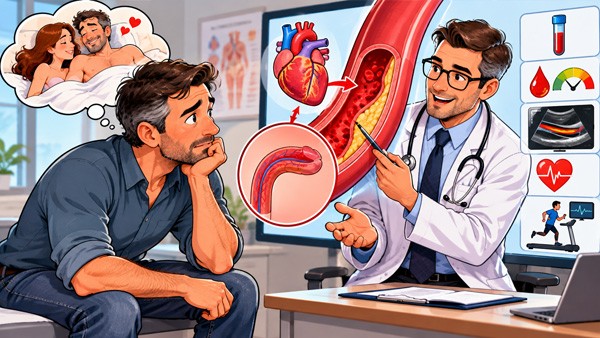

An erection is a hydraulic event in small arteries. Which makes it, inconveniently and usefully, one of the most sensitive early tests of vascular health a man has — and it reports a problem years before anything else does.
❤️ Erectile dysfunction precedes a cardiovascular event by an average of around three years, with studies putting the interval between two and five. In men under 50 with no obvious explanation, it is treated in good cardiology practice as a sentinel event — a reason to assess the whole cardiovascular system rather than simply to write a prescription.
That is the single most valuable thing this symptom offers. Not an embarrassment, but a warning delivered while there is still time to act on it.
How to treat it is covered in our guide to erectile dysfunction: doses and safety. This page is about what it is telling you and what to get checked.
🩸 Why these arteries fail first
The reason is simply size. The arteries supplying erectile tissue are roughly 1 to 2 mm across. The coronary arteries are 3 to 4 mm. The same amount of plaque and the same loss of vessel flexibility narrows the small ones to a critical degree long before the larger ones produce chest pain.
And the mechanism involved is the earliest thing to go wrong in vascular disease, before any plaque at all: the vessel lining loses its ability to release nitric oxide and relax on demand. An erection depends entirely on that relaxation. So the symptom appears at the stage of endothelial dysfunction, which is years ahead of a blockage.
There is also a dose-response relationship worth knowing: more severe erectile dysfunction is associated with higher cardiovascular event rates than mild. It is not a binary warning but a graded one.
🔍 The pattern is the clue: three different stories
This is the part that lets you interpret your own situation before any test.
| Pattern | What it usually means | What to do |
|---|---|---|
| Gradual decline over months to years, present in every situation, worse with exertion, morning erections fading | Vascular or metabolic. This is the pattern that carries the warning | Full cardiovascular and diabetes assessment —> the list below |
| Sudden onset, situational — fine alone or with one partner, fails with another, morning erections intact | Psychological or relational. Anxiety produces adrenaline, and adrenaline closes exactly the vessels that need to open | Reduce the performance pressure; a short course of medication often breaks the loop |
| Abrupt onset after a specific event — a new medicine, pelvic or prostate surgery, an injury, radiotherapy | Drug effect or nerve injury | Medication review, or urology if post-surgical |
🌅 The free test you already have: morning erections.
Present — the blood supply and the nerves are working. That points strongly towards a situational or anxiety-driven cause, and it is reassuring about the arteries.
Absent for weeks or months — points towards a physical cause and is the single most useful piece of history you can bring to an appointment. Mention it unprompted, because it changes what gets investigated.
Healthy men have several erections during sleep, in REM periods, and the morning one is simply the last of them observed on waking. Their disappearance is a measurable change, not a matter of mood or age.
🧪 The tests worth asking for by name
If the pattern is the gradual one, this is the list. It is short, cheap and routinely not done, because the consultation stops at the prescription.
| Test | What you are looking for |
|---|---|
| Blood pressure | Target below 130/80 for most adults. Hypertension both causes this and is predicted by it — see our guide to blood pressure |
| HbA1c or fasting glucose | HbA1c 6.5 percent or fasting glucose 7.0 mmol/L (126 mg/dL) diagnoses diabetes; the prediabetes range starts well below that. See the diabetes section below |
| Lipid profile | LDL target depends on overall risk — below 100 mg/dL at moderate risk, lower with diabetes or established disease. Covered in our guide to cholesterol |
| Morning testosterone | Fasting, before 10 or 11 am, on two separate days. Below about 300 ng/dL or 10.4 nmol/L with symptoms is deficiency — see our guide to low testosterone |
| Thyroid function | Both over and underactive contribute |
| Full blood count and kidney function | Anaemia and chronic kidney disease both cause it |
| Waist circumference and weight | Central obesity is the strongest single modifiable driver, through vessels, hormones and inflammation together |
And one question rather than a test: do you snore, stop breathing at night, or feel sleepy during the day?
🍬 Diabetes: erectile dysfunction is often the first symptom
This connection is strong enough to deserve its own section. Erectile dysfunction is around three times more common in men with diabetes, affects a majority of them over time, and appears ten to fifteen years earlier than in men without it.
The reason it matters here is the direction: in a meaningful number of men, erectile dysfunction is how undiagnosed type 2 diabetes announces itself. Nerve and small-vessel damage begins during the years of prediabetes, before thirst and weight loss appear.
Which means a single blood test at this point can find a condition years before it would otherwise be diagnosed. It also explains why diabetes-related erectile dysfunction responds less well to tablets — there is a nerve component as well as a vascular one, and the earlier it is caught the better that responds. What to do once control starts slipping is in our guide to type 2 diabetes.
😴 The overnight cause nobody checks
Obstructive sleep apnea roughly doubles the likelihood of erectile dysfunction, and it does so through two routes at once: repeated oxygen drops damage the vessel lining, and fragmented sleep suppresses testosterone, most of which is produced during sleep.
It is worth pursuing because treating it improves both. The combination to act on is snoring, witnessed breathing pauses, waking unrefreshed, morning headache and night-time urination — set out in our guide to obstructive sleep apnea, along with the eight-question screening tool.
💊 Before anything else: the medicine cabinet
Where the onset was abrupt and traceable to starting a drug, this is the whole answer, and it includes products we sell ourselves.
- 🩸 Thiazide diuretics and beta blockers — the two blood pressure classes most associated with it. ACE inhibitors, ARBs and calcium channel blockers much less so, and a switch is usually possible
- 🧠 SSRI antidepressants — very common and dose-related. Bupropion and mirtazapine have much less of this effect
- 💊 Finasteride and dutasteride, used for prostate enlargement and hair loss. A minority experience reduced erections and libido, sometimes persisting for a period after stopping
- 💧 Spironolactone, which has anti-androgen activity
- 💊 Opioid painkillers, which suppress testosterone strongly with long-term use
- 🧪 Antipsychotics, many of which raise prolactin
- 🚬 Cannabis, heavy alcohol, and anabolic steroids — the last of these can shut down testosterone production for a long period after stopping
None of these should be stopped on your own. All of them are worth naming at the appointment, because the alternative to a switch is often a second prescription to counteract the first.
🔎 What is not vascular
Three situations where the warning framing does not apply, and where the treatment is entirely different.
- 📐 Peyronie disease — a curve or bend developing in the erection, a firm lump felt along the shaft, shortening, and pain with erection in the active phase. This is scar tissue, not blood flow, and it needs urology. Tablets do not address it
- 🔪 After prostate or pelvic surgery, or pelvic radiotherapy — nerve injury rather than arterial disease. Tablets work less well and other options work better, which is why specialist input matters here
- 🧠 Neurological conditions — multiple sclerosis, spinal cord injury, advanced diabetic neuropathy
Also distinct, and worth separating: low desire is not erectile dysfunction. Not wanting to and not being able to have different causes and different workups, and the hormonal side of the first is covered in our guide to low libido.
🏃 What actually reverses it
This is the payoff of the whole warning framing: the things that improve erections are the things that reduce cardiovascular risk, and they work on the same timescale.
| Change | What is known |
|---|---|
| Aerobic exercise | In trials, around 160 minutes a week over six months produced measurable improvement in erectile function scores. Dose-related, and it works through the vessel lining directly |
| Weight loss | A reduction of around 10 percent improves erectile function, testosterone and insulin sensitivity together |
| Stopping smoking | Improvement within months. The effect of smoking on small arteries is direct and partly reversible |
| Mediterranean-style eating | Consistently associated with better erectile function, and it is the same pattern that lowers cardiovascular risk |
| Treating sleep apnea | Improves both erections and testosterone |
| Reducing alcohol | Acute effect on performance and chronic effect on hormones |
| Controlling blood pressure and glucose | The whole point of the investigation above |
One mechanical note that catches cyclists: prolonged riding on a narrow saddle compresses the nerves and vessels in the perineum and causes this in a minority. A wider saddle or a cut-out design resolves it.
💊 Where the tablet fits in a warning
Medication is not the opposite of investigation, and withholding it while tests are arranged helps nobody. Tadacip (Tadalafil) is a long-acting PDE5 inhibitor that amplifies the natural signal rather than creating arousal — it does nothing without sexual stimulation.
- 🔹 10 mg on demand, range 5 to 20 mg, taken 30 minutes to 2 hours beforehand, effective for up to 36 hours, and food makes no meaningful difference
- 🔹 Or 5 mg once daily, continuously, which removes the planning entirely and also treats an enlarged prostate at the same dose
- ⚠️ Never with nitrates in any form, including the recreational nitrite inhalants, and never with riociguat. Alpha blockers need a stable dose and the lowest starting dose
- 🏥 Cardiac clearance first where there is unstable angina, a recent heart attack or stroke, uncontrolled blood pressure or significant heart failure
- 🚨 An erection lasting over four hours, sudden vision loss or sudden hearing loss means stopping and seeking urgent care
Alternatives and full dosing for all four agents are in our main erectile dysfunction guide, and the range is in the mens health category.
The honest framing: the tablet restores function, and it does not treat the artery. A man who takes it and never has his blood pressure, glucose and lipids checked has silenced an alarm and left the fire.
🗣️ Why this goes unreported for years
Worth naming, because the delay is the problem rather than the condition. Men wait an average of several years before raising this, and the reasons are consistent: embarrassment, the assumption that it is simply age, fear of what it means, and the belief that nothing can be done.
Three things that make the conversation easier:
- 📝 Lead with the pattern, not the feeling — when it started, whether it is every time, whether morning erections are present. That is clinical information and it moves the appointment forward in a sentence
- ❤️ Frame it as a vascular question if that is easier: asking for a cardiovascular check because of this symptom is a legitimate and well-recognised request
- 👥 Tell your partner what is happening. Unexplained avoidance is read as loss of interest almost every time, and that reading causes more damage than the symptom
📞 When to seek help
Urgently:
- Chest pain, breathlessness on exertion, or reduced exercise tolerance alongside this — assess the heart before treating anything else
- An erection lasting more than four hours
- Sudden vision loss or sudden hearing loss on a PDE5 inhibitor
Promptly:
- New persistent erectile dysfunction, particularly under 50 — ask for the test list above, not only a prescription
- Loss of morning erections over weeks to months
- Gradual decline over years with any of: raised blood pressure, smoking history, central weight gain, family history of early heart disease
- Thirst, passing more urine, unexplained tiredness or weight change — check the glucose
- Snoring with breathing pauses or daytime sleepiness
- Onset after starting a new medicine — raise it rather than accepting it
- Reduced desire and fatigue as well — ask for morning testosterone on two days
- Curvature, a lump along the shaft, or pain with erection — a different condition needing urology
- Taking nitrates in any form — these tablets are not an option, and that needs saying before anything is bought
- Low mood or relationship strain, which are common and treatable in their own right
❓ Frequently asked questions
Is erectile dysfunction really a sign of heart disease?
It can be an early one. It precedes a cardiovascular event by around three years on average, because the penile arteries are 1 to 2 mm across against 3 to 4 mm for the coronaries, so the same disease narrows them first.
What does it mean if I still get morning erections?
That the blood supply and nerves are working, which points towards a situational or anxiety-driven cause and is reassuring about the arteries. Their absence for weeks or months points towards a physical cause and should be mentioned unprompted.
Which tests should I ask for?
Blood pressure, HbA1c or fasting glucose, a lipid profile, morning testosterone on two separate days, thyroid function, full blood count and kidney function, plus waist measurement and a question about snoring.
Can erectile dysfunction be the first sign of diabetes?
Yes, and in a meaningful number of men it is. It is about three times more common with diabetes and appears ten to fifteen years earlier, because nerve and small-vessel damage begins during the prediabetes years.
Does sudden onset mean something different from gradual?
Yes. Sudden and situational, with morning erections intact, usually means anxiety or a relational cause. Gradual decline over years in every situation points at the arteries and metabolism. Abrupt onset after a new medicine usually means the medicine.
Can exercise actually improve erections?
Yes. Around 160 minutes a week of aerobic exercise over six months produced measurable improvement in trials, working through the vessel lining. Weight loss of about 10 percent and stopping smoking both help as well.
Could my blood pressure tablet be causing it?
Thiazide diuretics and beta blockers are the classes most associated with it, while ACE inhibitors, ARBs and calcium channel blockers are much less so and a switch is usually possible. Never stop a blood pressure tablet on your own.
Does taking a tablet mean I can skip the tests?
No. The tablet restores function and does nothing to the artery. Treating the symptom while never checking blood pressure, glucose and lipids silences an alarm and leaves the underlying problem running.
What if there is a curve or a lump rather than softness?
That suggests Peyronie disease — scar tissue causing a bend, a palpable firm area and sometimes pain with erection. It is not a blood flow problem, tablets do not address it, and it needs a urology assessment.
Can sleep apnea cause erectile dysfunction?
It roughly doubles the likelihood, through repeated oxygen drops damaging the vessel lining and fragmented sleep suppressing testosterone. Treating the apnea improves both, so snoring and daytime sleepiness are worth pursuing.
📑 Sources and editorial
- Urological association guidance on the evaluation of erectile dysfunction, including recommended laboratory assessment
- Princeton consensus recommendations on erectile dysfunction as a marker of cardiovascular risk and on risk stratification before treatment
- Cohort studies of erectile dysfunction preceding cardiovascular events, including the interval between symptom onset and event, and the relationship between symptom severity and event rate
- Research on endothelial dysfunction and nitric oxide signalling as the shared mechanism of erectile dysfunction and early atherosclerosis, and on comparative penile and coronary artery calibre
- Epidemiological studies of erectile dysfunction prevalence in diabetes, including earlier onset and the proportion presenting before diabetes diagnosis
- Studies of obstructive sleep apnea and erectile dysfunction, including the effect of treatment on erectile function and testosterone
- Randomised and observational evidence on aerobic exercise, weight loss, smoking cessation and dietary pattern on erectile function scores
- Reviews of drug-induced erectile dysfunction by class, including antihypertensives, SSRIs, 5-alpha reductase inhibitors and opioids
- Guidance on Peyronie disease and on erectile dysfunction following radical prostatectomy and pelvic radiotherapy
- Prescribing information for tadalafil, including on-demand and once-daily regimens, duration of action, nitrate contraindication and priapism
- Related reading: erectile dysfunction doses and safety, low libido and testosterone, blood pressure, cholesterol, obstructive sleep apnea
- Related products: Tadacip (Tadalafil), Cialis (Tadalafil), Sildenafil Citrate, mens health category
- RXshop Editorial Team — reviewed by Michael Reeves, MD, FACS — Urologist & Men’s Health Specialist
Medical Disclaimer: The information in this article is for educational and informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always seek guidance from a qualified healthcare provider with any questions you may have regarding a medical condition, and before starting, stopping or changing any medication.