Buy Hepcinat (Generic Sofosbuvir) Online — Affordable Indian Pan-Genotypic HCV DAA for Hepatitis C Functional Cure (Sovaldi Equivalent)


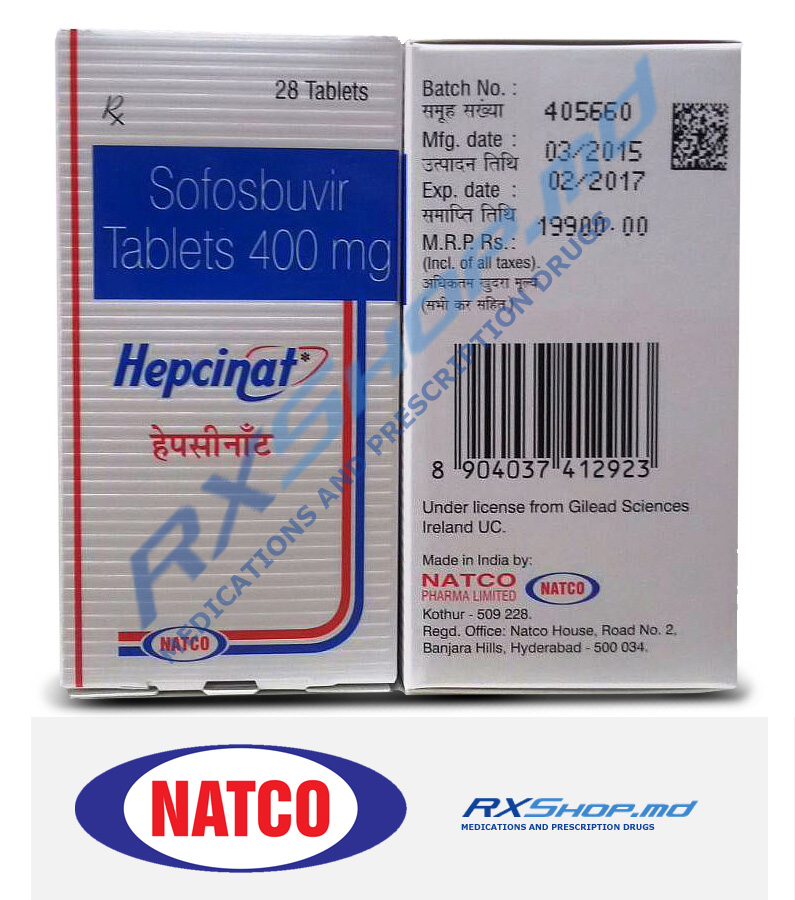
Hepcinat is an affordable Indian generic version of Sofosbuvir manufactured by Natco Pharma — the revolutionary direct-acting antiviral (DAA) that transformed hepatitis C treatment from difficult interferon-based therapy into a simple oral cure. Providing the same therapeutic activity as branded Sovaldi (Gilead Sciences, FDA-approved 2013) at dramatically lower cost, Hepcinat has made HCV cure accessible to millions in developing countries. Sovaldi was the first oral, all-pill, interferon-free hepatitis C therapy and Sofosbuvir remains the backbone of most modern HCV DAA combinations.
The active ingredient is Sofosbuvir, a nucleotide analog inhibitor of HCV NS5B polymerase. Upon intracellular phosphorylation, Sofosbuvir's active metabolite (GS-461203) is incorporated into nascent viral RNA strands, causing immediate chain termination. Sofosbuvir has very high genetic barrier to resistance and demonstrates pan-genotypic activity — effective against all HCV genotypes (1, 2, 3, 4, 5, 6) when combined appropriately. Selectivity for HCV NS5B polymerase explains Sofosbuvir's remarkable safety profile.
Hepcinat is FDA-approved (as Sovaldi) for chronic hepatitis C virus infection in combination with other antivirals — never as monotherapy. Standard combinations include Sofosbuvir + Ledipasvir (Harvoni for genotypes 1, 4, 5, 6), Sofosbuvir + Velpatasvir (Epclusa, pan-genotypic 1-6), Sofosbuvir + Velpatasvir + Voxilaprevir (Vosevi for DAA-failure retreatment), and Sofosbuvir + Daclatasvir (widely used internationally).
The medication is available as Hepcinat 400 mg tablets. Standard adult dosing is 400 mg once daily, typically for 12 weeks (some regimens 8 or 24 weeks based on genotype, prior treatment, and liver disease stage). Always combined with another DAA — never monotherapy.
Critical safety considerations include the FDA boxed warning for hepatitis B virus reactivation in HCV/HBV co-infected patients (HCV suppression can trigger HBV reactivation — screen for HBV before starting), serious bradycardia when combined with amiodarone (especially with Daclatasvir), reduced efficacy with strong CYP/P-gp inducers, renal impairment considerations, and generally mild side effects (headache, fatigue, nausea, insomnia, pruritus). Hepcinat is dramatically better tolerated than older interferon-based HCV regimens.
Free prescription
Discrete packaging
Have questions?
Quality Assurance

- HCV Genotype 1: For HCV genotype 1 infection (most common globally) — combined with Ledipasvir or Velpatasvir;
- HCV Genotype 2: For HCV genotype 2 infection — combined with Velpatasvir or Ribavirin;
- HCV Genotype 3: For HCV genotype 3 infection — combined with Velpatasvir or Daclatasvir;
- HCV Genotype 4: For HCV genotype 4 infection — combined with Ledipasvir or Velpatasvir;
- HCV Genotype 5: For HCV genotype 5 infection — combined with Ledipasvir or Velpatasvir;
- HCV Genotype 6: For HCV genotype 6 infection — combined with Ledipasvir or Velpatasvir;
- HCV Pan Genotypic Combination: Pan-genotypic combinations (Sofosbuvir + Velpatasvir = Epclusa) for all HCV genotypes;
- HCV Treatment Naive: First-line therapy for treatment-naive HCV patients;
- HCV Treatment Experienced: For treatment-experienced patients with prior interferon-based therapy failure;
- HCV Compensated Cirrhosis: For HCV patients with compensated cirrhosis;
- HCV Decompensated Cirrhosis: For HCV patients with decompensated cirrhosis (specific regimens with ribavirin);
- HCV Pre Transplant: For HCV patients on liver transplant waiting list;
- HCV Post Transplant: For HCV recurrence after liver transplant;
- HCV HIV Coinfection: For HCV in HIV co-infected patients (with attention to drug interactions);
- HCV CKD Patients: For HCV in chronic kidney disease patients (with dose adjustment);
- HCV IDU Population: For HCV in people who inject drugs (IDU) populations — key public health use;
- HCV Resource Limited Settings: Affordable generic Sofosbuvir enables HCV elimination programs in resource-limited countries;
- HCV Adolescent Therapy: For HCV treatment in adolescents 12 years and older;
- HCV Reinfection Retreatment: For HCV reinfection after prior successful treatment;
- DAA Failure Retreatment: For prior DAA-failure retreatment (typically as Vosevi triple combination).
- HCV Functional Cure: Sustained virologic response (SVR12) achieved in 95%+ of patients — functionally curative;
- Better SVR Rates All Genotypes: 95%+ SVR rates across all HCV genotypes when combined appropriately;
- Less HCV Liver Damage: Reduction in HCV-related liver inflammation and fibrosis progression;
- Less Hepatitis Symptoms: Resolution of HCV-related fatigue, jaundice, and constitutional symptoms;
- HCV Cure Reverses Cirrhosis Progression: SVR halts cirrhosis progression and may allow partial reversal in some patients;
- Less Hepatocellular Carcinoma Risk: Significant reduction in HCV-related hepatocellular carcinoma risk after SVR;
- Less Liver-Related Mortality: Substantial reduction in liver-related mortality after HCV cure;
- Less Liver Transplant Need: Reduction in HCV-related liver transplant need with effective cure;
- Better Post-Transplant HCV Control: Effective in HCV recurrence after liver transplantation;
- Better HCV/HIV Coinfection Outcomes: Effective HCV cure in HIV co-infected patients;
- Better CKD Patient Outcomes: Effective HCV cure in chronic kidney disease patients;
- Less IDU HCV Transmission: HCV cure reduces transmission in injection drug user populations — public health benefit;
- Better Daily Function: Return to normal daily activities after HCV cure achievement;
- Better Long-Term Quality of Life: Substantial improvement in quality of life after HCV SVR;
- Less Psychological Burden: Resolution of psychological burden of chronic HCV infection;
- Excellent Tolerability: Dramatically better tolerated than older interferon-based HCV regimens;
- Once-Daily Convenience: Single 400 mg tablet once daily simplifies HCV therapy;
- Short Treatment Duration: 12-week (some 8-week) treatment courses replace older 24-48 week regimens;
- Interferon-Free Therapy: First all-oral, interferon-free HCV regimen — revolutionary treatment paradigm;
- Brand Hepcinat: Affordable Indian Natco Pharma brand — key to global HCV elimination efforts in developing countries;
- Generic Sofosbuvir: Affordable generic Sofosbuvir expanding global access to revolutionary HCV cure therapy;
- Sovaldi Equivalent: Same Sofosbuvir molecule as original Gilead Sciences brand Sovaldi with bioequivalent therapeutic profile;
- MyHep Equivalent: Same Sofosbuvir molecule as Mylan brand MyHep;
- Direct Acting Antiviral DAA: Foundational direct-acting antiviral class member — transformed HCV care;
- Nucleotide NS5B Polymerase Inhibitor: Nucleotide analog NS5B polymerase inhibitor with selectivity for HCV-specific enzyme;
- Chain Termination Mechanism: Active metabolite GS-461203 causes viral RNA chain termination upon incorporation;
- Pan Genotypic Activity: Pan-genotypic activity across all HCV genotypes 1-6 with appropriate combinations;
- High Genetic Barrier Resistance: Very high genetic barrier to resistance development — durable response;
- Harvoni Component: Core component of Harvoni (Sofosbuvir + Ledipasvir) for HCV genotypes 1, 4, 5, 6;
- Epclusa Component: Core component of Epclusa (Sofosbuvir + Velpatasvir) — pan-genotypic HCV therapy;
- Vosevi DAA Failure Component: Core component of Vosevi (Sofosbuvir + Velpatasvir + Voxilaprevir) for DAA-failure retreatment;
- HCV Elimination Programs: Foundational to WHO HCV elimination programs in developing countries;
- Indian Quality Manufacturing: Indian Natco Pharma manufacturing meeting international quality and bioequivalence standards;
- HCV Functional Cure: SVR12 achievement effectively cures hepatitis C in responsive patients;
- WHO Essential Medicine: Listed on the WHO Model List of Essential Medicines for HCV care.
Generic Hepcinat (Sovaldi 400 mg) Medication guide:
📖 What Is Hepcinat (Sofosbuvir) HCV Nucleotide Inhibitor
Hepcinat is the widely used Natco Pharma generic formulation of Sovaldi, manufactured under a voluntary licensing agreement with Gilead Sciences that permits Natco to supply the active pharmaceutical ingredient sofosbuvir 400 mg to 91 low- and middle-income countries. Sovaldi was originally launched by Gilead in December 2013 and transformed the treatment of chronic hepatitis C almost overnight. Hepcinat delivers the identical active ingredient at accessible price points across the licensed markets.
Sofosbuvir is a nucleotide analog inhibitor of the hepatitis C virus NS5B RNA-dependent RNA polymerase. It works by blocking the enzyme responsible for HCV genome replication. Its emergence represented the first pan-genotypic direct-acting antiviral with a high genetic barrier to resistance, and it has become the backbone of essentially every modern hepatitis C combination regimen approved worldwide.
📇 Hepcinat product snapshot
| Generic name | Sofosbuvir |
| Reference brand | Sovaldi (Gilead Sciences) |
| Manufacturer of Hepcinat | Natco Pharma (India) under voluntary licensing agreement |
| Drug class | Nucleotide analog NS5B polymerase inhibitor |
| Chemical family | Uridine analog phosphoramidate prodrug (ProTide technology) |
| FDA approval (Sovaldi) | December 6, 2013 |
| Strength | 400 mg film-coated tablets |
| Standard dose | 400 mg once daily with or without food |
| Typical duration | 12 weeks (8 weeks or 24 weeks in specific scenarios) |
| Genotype coverage | Pan-genotypic (HCV genotypes 1 through 6) |
| Cure signature | Sustained virologic response above 95% with appropriate combination regimens |
Sofosbuvir is never used as monotherapy. Its clinical role is always as one component of a combination direct-acting antiviral regimen alongside a second (or sometimes third) DAA that targets a different HCV protein. Common combinations include sofosbuvir plus ledipasvir (marketed as Harvoni), sofosbuvir plus velpatasvir (Epclusa), sofosbuvir plus daclatasvir (widely used globally), and salvage-therapy combinations for retreatment. Modern hepatitis C treatment guidelines from AASLD-IDSA, EASL, WHO, and APASL uniformly build regimens around sofosbuvir as the backbone.
📜 History - Transformation of Hepatitis C Treatment
Sofosbuvir emerged from medicinal chemistry work at Pharmasset, a small biotechnology company founded by Raymond Schinazi. Michael J. Sofia and colleagues at Pharmasset applied ProTide phosphoramidate prodrug chemistry (invented by Chris McGuigan) to a uridine analog and generated the clinical candidate initially designated PSI-7977. Gilead Sciences acquired Pharmasset for approximately 11 billion USD in early 2012, and the compound was renamed sofosbuvir. In December 2013, FDA approved Sovaldi and rewrote the treatment landscape for hepatitis C.
📅 Historical milestones
- 1989: HCV identified
- Michael Houghton, Qui-Lim Choo, George Kuo, and Daniel Bradley clone the hepatitis C virus and identify it as the cause of non-A non-B hepatitis
- 1990s-2000s: Interferon era
- Interferon alpha alone and later peginterferon plus ribavirin become standard of care; cure rates of 40-50% for genotype 1 with heavy side effect burden and poor tolerability
- 2010: Sofosbuvir clinical candidate identified
- Michael Sofia and Pharmasset scientists publish PSI-7977 as clinical candidate with pan-genotypic activity and high resistance barrier
- 2011: Boceprevir and telaprevir approved
- First-generation direct-acting antivirals (NS3 protease inhibitors) added to peginterferon + ribavirin improve cure rates to 60-70% for genotype 1, but retain interferon and add substantial toxicity
- January 2012: Gilead acquires Pharmasset
- Approximately 11 billion USD acquisition brings sofosbuvir into Gilead pipeline
- December 2013: Sovaldi FDA approval
- Sofosbuvir approved for HCV genotypes 1-4, marking the beginning of the interferon-free era for hepatitis C
- October 2014: Harvoni FDA approval
- Sofosbuvir + ledipasvir single tablet approved for genotype 1; simplifies treatment to one pill daily for 8-12 weeks with cure rates over 95%
- 2014-2015: Natco licensing and Hepcinat launch
- Gilead executes voluntary licensing agreement with Natco Pharma and other Indian generics manufacturers, permitting supply to 91 low- and middle-income countries; Hepcinat launches at fraction of Sovaldi price
- June 2016: Epclusa FDA approval
- Sofosbuvir + velpatasvir approved for all six HCV genotypes; first true pan-genotypic combination in a single tablet
- July 2017: Vosevi FDA approval
- Sofosbuvir + velpatasvir + voxilaprevir approved as salvage therapy for treatment-experienced patients including those who failed prior direct-acting antiviral regimens
- 2016-present: WHO HCV elimination framework
- WHO adopts the goal of eliminating hepatitis C as a public health threat by 2030; sofosbuvir central to global scale-up strategy in low- and middle-income countries
Perhaps no antiviral in medical history has changed a disease as dramatically as sofosbuvir changed hepatitis C. In roughly five years, treatment moved from 48-week interferon regimens with major side effects and modest cure rates to 8-12 week all-oral regimens with cure rates above 95% and gentle side effect profiles. Michael Sofia received the 2016 Lasker-DeBakey Clinical Medical Research Award for the sofosbuvir discovery, and the drug is widely regarded as one of the most impactful medicines developed in the 21st century so far.
🧪 Chemistry - Uridine Analog Phosphoramidate Prodrug
Sofosbuvir is a phosphoramidate prodrug of a modified uridine nucleoside. The structural design solves a long-standing problem in nucleoside antiviral chemistry: nucleoside analogs must be phosphorylated intracellularly to reach the active triphosphate form, and this first phosphorylation step (from nucleoside to monophosphate) is often the rate-limiting bottleneck. Sofosbuvir bypasses this bottleneck by delivering the drug essentially pre-phosphorylated, disguised as a phosphoramidate that hepatocyte enzymes will unmask.
⚗️ Structural and physicochemical data
| Chemical class | Uridine nucleoside analog phosphoramidate prodrug |
| Molecular formula | C22H29FN3O9P |
| Molecular weight | 529.45 g/mol |
| Physical form | White to off-white crystalline solid |
| Aqueous solubility | Sparingly soluble in water; freely soluble in ethanol |
| Structural innovation | 2-prime C-methyl and 2-prime fluoro substitutions on ribose; L-alanine ester phosphoramidate ProTide masking group |
| Active intracellular form | GS-461203 (sofosbuvir triphosphate) |
| Inactive terminal metabolite | GS-331007 (accounts for over 90% of urinary excretion; itself pharmacologically inactive) |
The ProTide phosphoramidate technology is central to sofosbuvir behavior. As administered, sofosbuvir is a lipophilic prodrug that passively diffuses across cell membranes into hepatocytes. Once inside, hepatic enzymes (cathepsin A, carboxylesterase 1, HINT1) remove the ProTide masking groups sequentially, unveiling the sofosbuvir monophosphate. Cellular kinases then add the second and third phosphates to generate the active triphosphate. This delivery strategy achieves high intracellular concentrations of the active drug specifically in hepatocytes, which is precisely where HCV replicates.
The 2-prime substitutions on the ribose (C-methyl and fluoro) make the resulting triphosphate a poor substrate for human cellular RNA polymerases while remaining an excellent substrate for the HCV NS5B viral polymerase. This structural design achieves the selectivity that underlies both the excellent tolerability and the potent antiviral activity of sofosbuvir. Together, the phosphoramidate delivery, hepatocyte-targeted activation, and viral polymerase specificity make sofosbuvir a signature example of rational antiviral drug design.
⚙️ Mechanism - NS5B Polymerase Nucleotide Inhibition
Sofosbuvir works by inhibiting the HCV NS5B RNA-dependent RNA polymerase, the viral enzyme that copies the HCV RNA genome during replication. Blocking this enzyme halts HCV replication, viral load falls rapidly, and if therapy continues long enough (typically 8-12 weeks in combination with another DAA), the virus is cleared from the body permanently in the great majority of patients.
🔬 Mechanism unfolds through sequential steps
Step 1 — Hepatocyte delivery
Sofosbuvir is a lipophilic phosphoramidate prodrug that crosses cell membranes efficiently by passive diffusion. Hepatocytes take up the drug avidly. This hepatic tropism concentrates drug where HCV replicates.
Step 2 — ProTide unmasking
Inside hepatocytes, cathepsin A and carboxylesterase 1 cleave the ester bond of the phosphoramidate. HINT1 removes the amino acid moiety, revealing the sofosbuvir monophosphate. This bypasses the rate-limiting nucleoside kinase step.
Step 3 — Cellular phosphorylation to triphosphate
Cellular UMP-CMP kinase adds the second phosphate. Nucleoside diphosphate kinase adds the third phosphate. The resulting sofosbuvir triphosphate (GS-461203) is the active antiviral species.
Step 4 — Competition with UTP at NS5B
Sofosbuvir triphosphate competes with the natural nucleotide uridine triphosphate (UTP) for incorporation into the growing HCV RNA strand by the NS5B polymerase. The viral polymerase incorporates it in place of UTP.
Step 5 — Chain termination
Once incorporated, the 2-prime C-methyl group blocks the next phosphodiester bond because it cannot align properly with the incoming nucleotide. RNA synthesis stalls. This is obligate chain termination.
Step 6 — Viral replication collapses
HCV cannot complete new genome copies. Viral load falls rapidly, often 3-4 log10 within the first weeks of therapy. When combined with a second DAA targeting a different HCV protein (NS5A or NS3/4A protease), viral eradication ensues.
Three features make this mechanism especially attractive. First, the NS5B active site is highly conserved across HCV genotypes, which explains why sofosbuvir works against all six genotypes (pan-genotypic activity). Second, the 2-prime C-methyl substitution creates such a strict steric requirement that most single-point mutations that would confer resistance also cripple the polymerase, resulting in a high genetic barrier to resistance. Third, the hepatocyte-targeted ProTide delivery concentrates drug in the liver while minimizing systemic exposure, contributing to the excellent tolerability.
🔬 Pharmacokinetics and Renal Clearance Framework
Sofosbuvir pharmacokinetics are dominated by rapid absorption, extensive hepatocyte uptake and prodrug activation, renal elimination as the inactive metabolite GS-331007, and minimal cytochrome P450 involvement. This pharmacokinetic profile makes drug interactions unusually manageable and gives sofosbuvir a predictable dosing framework across most populations.
📊 Key pharmacokinetic parameters
| Parameter | Value |
|---|---|
| Oral bioavailability | Estimated over 80% |
| Peak plasma concentration (Tmax) | 0.5-2 hours (sofosbuvir); 2-4 hours (GS-331007 metabolite) |
| Effect of food | High-fat meal delays absorption; overall AUC not significantly altered |
| Plasma protein binding | 61-65% sofosbuvir; under 1% GS-331007 |
| Plasma half-life | 0.4 hours (parent sofosbuvir); 27 hours (GS-331007 inactive metabolite) |
| Metabolism route | Intrahepatic prodrug activation; minimal CYP450 involvement |
| P-glycoprotein substrate | Yes - susceptible to strong P-gp inducers |
| BCRP substrate | Yes |
| Elimination route | Approximately 80% renal (mostly as GS-331007); 14% fecal; 2.5% unchanged sofosbuvir |
| Renal impairment implication | GS-331007 accumulates with reduced renal function; use with caution when creatinine clearance is under 30 mL/min |
The prodrug-active metabolite kinetics deserve emphasis. The parent sofosbuvir has a short plasma half-life (approximately 30 minutes) because it is rapidly taken up by hepatocytes and processed to the active triphosphate. The circulating GS-331007 metabolite (an inactive terminal metabolite formed after intrahepatic activation) has a much longer plasma half-life of about 27 hours. Sustained hepatic drug pressure comes from the intracellular triphosphate concentration, not from the plasma sofosbuvir level.
Minimal CYP450 metabolism makes drug interactions unusually manageable. Sofosbuvir is not a substrate, inducer, or inhibitor of major cytochrome P450 enzymes. The main interaction concerns are with P-glycoprotein and BCRP inducers (strong inducers can reduce sofosbuvir exposure and compromise efficacy), and with amiodarone (a serious pharmacodynamic interaction with severe bradycardia). Most common comorbid medications can be co-administered without concern.
📋 FDA Indications and Genotype Coverage
Sofosbuvir is FDA-approved for the treatment of chronic hepatitis C virus infection across all six major HCV genotypes when used in appropriate combination regimens. The specific FDA-approved labeling has expanded over time as combination products have been developed, but the core indication remains hepatitis C in adults and pediatric patients aged 3 years and older.
📋 FDA-approved indication framework
| Primary indication | Treatment of chronic hepatitis C virus (HCV) infection as a component of a combination antiviral treatment regimen |
| Genotype coverage | Genotypes 1, 2, 3, 4, 5, and 6 (pan-genotypic activity) |
| Adult age | 18 years and older; standard 400 mg once daily |
| Pediatric age | 3 years and older; weight-based dosing (see pediatric section) |
| Cirrhosis status | Approved with and without cirrhosis; duration may be extended to 24 weeks with cirrhosis in specific regimens |
| Treatment-experienced patients | Approved; specific salvage regimens (Vosevi with voxilaprevir) exist for prior direct-acting antiviral failures |
| HCV/HIV coinfection | Approved with same regimens and durations as HCV monoinfection |
| Post-liver transplant | Approved for HCV treatment following liver transplantation with careful drug interaction consideration for immunosuppressants |
The pan-genotypic advantage is significant. Before sofosbuvir, hepatitis C treatment required identifying the specific genotype and matching to genotype-specific regimens - genotype 1 was hardest to treat, genotype 3 was particularly challenging with older drugs, and treatment success varied widely. Sofosbuvir-based regimens work across all genotypes with high cure rates, simplifying pre-treatment workup and expanding treatment access in low-resource settings where genotype testing may be unavailable.
WHO Essential Medicines List includes sofosbuvir, reflecting its global importance in the effort to eliminate hepatitis C. WHO treatment guidelines recommend pan-genotypic regimens as the preferred approach in most settings, with sofosbuvir + daclatasvir and sofosbuvir + velpatasvir being widely used globally. National treatment programs in dozens of countries have incorporated sofosbuvir into standardized HCV elimination initiatives.
What sofosbuvir does not treat: it has no meaningful activity against HIV, HBV, influenza, or non-HCV pathogens. Its antiviral spectrum is essentially specific to hepatitis C. Patients with other viral infections require different therapy. HBV screening is critical before starting sofosbuvir-based therapy because of the risk of HBV reactivation (see section on HBV boxed warning).
🔗 Combination Regimens Built on Sofosbuvir Backbone
Sofosbuvir is the backbone around which essentially every modern HCV combination regimen is built. The strategy of pairing sofosbuvir with a second direct-acting antiviral targeting a different HCV protein (typically an NS5A inhibitor, sometimes an NS3/4A protease inhibitor) exploits two mechanistically independent attack points. This combination approach delivers cure rates above 95% and prevents resistance emergence that would otherwise threaten sofosbuvir monotherapy.
💊 Sofosbuvir-containing combination products
| Product | Composition | Genotype coverage |
|---|---|---|
| Sovaldi / Hepcinat | Sofosbuvir 400 mg alone | Backbone for various combinations |
| Harvoni / Hepcinat LP | Sofosbuvir + ledipasvir (NS5A inhibitor) | Genotypes 1, 4, 5, 6 |
| Epclusa / Velpanat / Velasof | Sofosbuvir + velpatasvir (NS5A inhibitor) | Pan-genotypic (all six) |
| Vosevi / Velsovir | Sofosbuvir + velpatasvir + voxilaprevir (NS3/4A) | Pan-genotypic salvage for DAA failures |
| Hepcinat-Plus / Darvoni | Sofosbuvir + daclatasvir (NS5A inhibitor) | Pan-genotypic (all six) |
| Sofosbuvir + ribavirin | Sofosbuvir with weight-based ribavirin | Historically used for genotypes 2 and 3; largely superseded by NS5A combinations |
The two-DAA principle is critical to understand. HCV replicates with high fidelity but produces enormous numbers of daily virions. Even at low rates, mutation generates virus variants at every position of the genome. A single-drug regimen selects for pre-existing or newly generated resistant variants, and treatment fails. Two drugs targeting different HCV proteins require the virus to acquire simultaneous resistance to both, which is exponentially less likely and rarely occurs in practice.
Common combination partners and their targets: NS5A inhibitors (ledipasvir, velpatasvir, daclatasvir, elbasvir, pibrentasvir) block the NS5A phosphoprotein that scaffolds the viral replication complex. NS3/4A protease inhibitors (grazoprevir, glecaprevir, voxilaprevir, paritaprevir) block the viral protease essential for polyprotein processing. Sofosbuvir plus one of these partners provides two mechanistically independent attacks that together cure hepatitis C in over 95% of patients.
Guideline positioning: AASLD-IDSA HCV Guidance, EASL guidelines, WHO guidelines, and APASL consensus statements all build their HCV treatment recommendations around sofosbuvir-based combination regimens. The specific combination and duration depend on genotype, treatment history, cirrhosis status, coinfection, and comorbidities. Modern practice increasingly favors pan-genotypic regimens (Epclusa/Velpanat, Hepcinat-Plus with daclatasvir, or glecaprevir/pibrentasvir which does not contain sofosbuvir) to simplify pre-treatment workup and standardize therapy.
🌟 Sofosbuvir + Ledipasvir (Harvoni) Genotype 1 Landmark
The first single-tablet sofosbuvir combination was Harvoni (sofosbuvir 400 mg + ledipasvir 90 mg), FDA-approved in October 2014 for HCV genotype 1. Harvoni revolutionized genotype 1 treatment - the most common HCV genotype in the United States and Europe - by delivering an all-oral, once-daily, single-tablet regimen with cure rates over 95% in 8-12 weeks. The Hepcinat LP (Natco generic of Harvoni) provides the same combination for licensed markets.
🌟 ION trial series highlights (sofosbuvir + ledipasvir pivotal evidence)
| Trial | Population | Outcome (SVR12) |
|---|---|---|
| ION-1 | Treatment-naive genotype 1 | 99% at 12 weeks; 97% at 12 weeks + ribavirin (n=865) |
| ION-2 | Treatment-experienced genotype 1 including cirrhotics | 94% at 12 weeks; 99% at 24 weeks (n=440) |
| ION-3 | Treatment-naive non-cirrhotic genotype 1 | 94-95% at 8 weeks (n=647) - established shorter treatment duration |
| SIRIUS | Cirrhotic patients with prior protease inhibitor failure | 96% at 12 weeks + ribavirin; 97% at 24 weeks (n=155) |
| ELECTRON-2 | Various treatment scenarios including genotype 3 | Contributed to genotype 3 and cirrhosis evidence |
Duration selection framework: for treatment-naive non-cirrhotic genotype 1 patients with baseline HCV RNA under 6 million IU/mL, ION-3 established that 8 weeks of Harvoni suffices for cure. Standard duration for other groups is 12 weeks. Cirrhotic treatment-experienced patients may benefit from 12 weeks plus ribavirin or 24 weeks without ribavirin. Modern AASLD-IDSA guidance provides detailed algorithms based on treatment history, cirrhosis status, and prior treatment specifics.
Genotype coverage extension: Harvoni also has FDA-approved indications for genotypes 4, 5, and 6 based on smaller trials (SYNERGY, EASE-3, and others). Cure rates in these genotypes are similarly high (over 95% in most subgroups). For genotype 3, the pan-genotypic Epclusa combination (sofosbuvir + velpatasvir) provides better activity than Harvoni and is preferred.
The clinical impact of Harvoni was enormous. Millions of HCV genotype 1 patients worldwide have been cured with the sofosbuvir + ledipasvir combination. The Hepcinat LP generic launched by Natco under Gilead voluntary licensing has extended access to low- and middle-income countries where Sovaldi/Harvoni original branded prices would be prohibitive. Together, sofosbuvir-based generics have made HCV cure achievable in national elimination programs across the developing world.
🩺 Sofosbuvir + Velpatasvir (Epclusa) Pan-Genotypic Regimen
Epclusa (sofosbuvir 400 mg + velpatasvir 100 mg) received FDA approval in June 2016 as the first true pan-genotypic single-tablet DAA regimen. By combining sofosbuvir with the second-generation NS5A inhibitor velpatasvir, Epclusa delivers cure rates above 95% across all six HCV genotypes with a uniform 12-week treatment duration in most patients. The Natco generic versions (Velpanat, Velasof) and other licensed generics have extended global access.
🩺 ASTRAL trial series (sofosbuvir + velpatasvir pivotal evidence)
| Trial | Population | Outcome (SVR12) |
|---|---|---|
| ASTRAL-1 | Genotypes 1, 2, 4, 5, 6 (n=740) | 99% at 12 weeks |
| ASTRAL-2 | Genotype 2 (n=266) | 99% at 12 weeks (vs 94% sofosbuvir + ribavirin) |
| ASTRAL-3 | Genotype 3 including cirrhotics (n=552) | 95% at 12 weeks (vs 80% sofosbuvir + ribavirin) |
| ASTRAL-4 | Decompensated cirrhosis (Child-Pugh B, n=267) | 83-94% depending on regimen (12 or 24 weeks with/without ribavirin) |
| ASTRAL-5 | HIV/HCV coinfection (n=106) | 95% at 12 weeks |
Pan-genotypic simplicity is Epclusa signature advantage. Before pan-genotypic regimens, treating HCV required identifying the specific genotype (1a, 1b, 2, 3, 4, 5, or 6), selecting an appropriate regimen, and adjusting duration accordingly. This complexity limited access, particularly in resource-limited settings where genotype testing may be unavailable or unaffordable. Epclusa allows treatment initiation without knowing the genotype, and works across the board.
Genotype 3 activity deserves emphasis. Genotype 3 was historically the most challenging HCV genotype - resistant to earlier DAA combinations and associated with faster fibrosis progression and higher hepatocellular carcinoma risk. Velpatasvir has particularly strong activity against genotype 3, and Epclusa achieves cure rates above 95% in non-cirrhotic patients and around 91-93% in cirrhotic patients with genotype 3. This represents a substantial advance over sofosbuvir + ledipasvir (Harvoni), which has lower genotype 3 activity.
Cirrhosis considerations: Epclusa is approved for use in compensated cirrhosis (Child-Pugh A) with 12 weeks of treatment. In decompensated cirrhosis (Child-Pugh B or C), Epclusa may be used with ribavirin for 12 weeks based on ASTRAL-4. This is a distinctive advantage because ledipasvir and other older DAAs are contraindicated in decompensated cirrhosis. Epclusa in this population can achieve viral cure and may reverse hepatic dysfunction to allow patients to be delisted from transplant waitlists.
🌍 Sofosbuvir + Daclatasvir Global Standard Combination
Sofosbuvir + daclatasvir is one of the most widely used HCV combination regimens globally, particularly in low- and middle-income countries. Daclatasvir is an NS5A inhibitor originally developed by Bristol-Myers Squibb. The combination is approved by many national regulators (though not FDA in the United States) and forms the backbone of many national HCV elimination programs. Natco Pharma produces the fixed-dose combination as Hepcinat-Plus (60 mg daclatasvir + 400 mg sofosbuvir), and combined marketed as Darvoni and other names.
🌍 ALLY trial series and global scale-up evidence
| Study | Population | Outcome (SVR12) |
|---|---|---|
| ALLY-1 | Advanced cirrhosis or post-liver transplant | 83% (cirrhotic); 94% (post-transplant) |
| ALLY-2 | HCV/HIV coinfection genotypes 1-4 (n=203) | 96-97% at 12 weeks |
| ALLY-3 | Genotype 3 (n=152) | 89-96% depending on cirrhosis status |
| French ATU cohort | Real-world experience | Confirmed high cure rates across genotypes and cirrhosis levels |
| MSF (Doctors Without Borders) programs | Field programs in low-resource settings | Demonstrated feasibility of decentralized HCV treatment with generic sofosbuvir + daclatasvir |
Global public health significance: sofosbuvir + daclatasvir was among the first widely accessible interferon-free pan-genotypic regimens in the developing world. WHO Prequalification of both molecules and the availability of Indian generic combination products made large-scale treatment feasible in countries where the branded Gilead products were unaffordable. Egypt, Pakistan, Georgia, Rwanda, and many other nations have anchored their national HCV elimination programs on sofosbuvir + daclatasvir combinations.
Egyptian mass treatment program deserves special mention. Egypt had the highest HCV prevalence in the world (approximately 10-15% of adults) due to historical iatrogenic transmission from schistosomiasis parenteral therapy. Following price negotiations and use of generic sofosbuvir + daclatasvir, Egypt executed one of the largest disease elimination programs in history, treating millions of patients between 2014 and 2020 and driving HCV prevalence toward WHO elimination targets. The Egyptian model became a reference for other national programs.
Advantages of the sofosbuvir + daclatasvir combination: pan-genotypic activity (approved for genotypes 1-4 in EU, with real-world data supporting 5 and 6), robust cure rates including in advanced cirrhosis, HCV/HIV coinfection efficacy demonstrated in ALLY-2, availability as separate components or fixed-dose combinations at accessible generic prices, and simpler drug-drug interaction profile than protease inhibitor-containing regimens. The combination remains a workhorse of global HCV therapy despite the more recent emergence of Epclusa and Vosevi.
🧬 HCV/HIV Coinfection Considerations
HCV/HIV coinfection is a common clinical scenario that requires careful attention. Approximately 2-15% of people with HIV also have HCV depending on population and geography, with higher rates among people who inject drugs and men who have sex with men. Coinfection accelerates hepatic fibrosis and increases the risk of complications compared to HCV monoinfection. Fortunately, sofosbuvir-based DAA regimens work as well in coinfected patients as in HCV monoinfected patients, and cure of HCV improves overall clinical outcomes.
🧬 HCV/HIV coinfection management principles
Principle 1 — Cure rates equivalent to monoinfection
PHOTON-1, PHOTON-2, ALLY-2, ASTRAL-5, and other trials have demonstrated that sofosbuvir-based DAA regimens achieve HCV cure rates in HCV/HIV coinfected patients essentially identical to monoinfected patients (over 95% in most groups). Coinfection is no longer a barrier to successful HCV treatment.
Principle 2 — Coordinate antiretroviral therapy
Sofosbuvir can be given during ongoing antiretroviral therapy. Most modern antiretrovirals have manageable interactions with sofosbuvir-based regimens. Specific regimen selection may need review to avoid problematic interactions (see drug interactions section).
Principle 3 — HCV cure benefits HIV outcomes
Curing HCV in coinfected patients reduces hepatic fibrosis progression, decreases risk of hepatocellular carcinoma, and improves overall survival. HIV control also benefits indirectly as clinicians can select simpler antiretroviral regimens without concern for hepatic disease progression from ongoing HCV replication.
Principle 4 — HBV screening essential
All patients starting sofosbuvir-based therapy require HBV screening (HBsAg, anti-HBc). This is particularly important in HCV/HIV coinfected patients who may have triple infection. The HBV reactivation boxed warning (see section 24) applies to all sofosbuvir-treated patients regardless of HIV status.
Principle 5 — Screen for reinfection risk
People who inject drugs and men who have sex with men who cure HCV remain at risk for reinfection through ongoing exposures. Harm reduction (sterile injection equipment, opioid substitution therapy), safer sex counseling, and post-cure HCV RNA testing at intervals support the strategy of cure-and-prevent-reinfection.
Preferred coinfection regimens per IAS-USA, DHHS, and EACS guidelines include: sofosbuvir + velpatasvir (Epclusa/Velpanat) for pan-genotypic coverage; sofosbuvir + ledipasvir (Harvoni/Hepcinat LP) for genotype 1; sofosbuvir + daclatasvir (Hepcinat-Plus/Darvoni) for pan-genotypic coverage globally; and glecaprevir/pibrentasvir (Mavyret) as a non-sofosbuvir pan-genotypic alternative. Regimen selection considers antiretroviral compatibility, prior treatment history, and cirrhosis status.
Public health importance: HCV elimination in HIV populations is a specific WHO focus because coinfection is common among key populations (people who inject drugs, men who have sex with men, incarcerated populations) that are also at higher HCV risk. Integration of HCV screening and treatment into HIV clinics has been shown to be effective. In some settings, treating HCV in HIV-coinfected patients was a specific early-priority strategy in national HCV elimination programs.
🪶 Cirrhosis Management with Sofosbuvir-Based Regimens
Treatment of hepatitis C in cirrhotic patients requires careful attention to cirrhosis stage, regimen selection, and post-cure surveillance. Sofosbuvir-based regimens work well in cirrhosis, and cure of HCV can slow, halt, or occasionally partially reverse hepatic fibrosis. However, cirrhotic patients need distinct consideration for regimen intensity, treatment duration, and long-term monitoring.
🪶 Cirrhosis stage framework
| Stage | Definition | Treatment considerations |
|---|---|---|
| No cirrhosis (F0-F3) | Fibrosis without cirrhosis | Standard sofosbuvir-based regimen 8-12 weeks with high cure rates |
| Compensated cirrhosis (F4, Child-Pugh A) | Cirrhosis with preserved hepatic function | 12 weeks standard; ribavirin may be added in some regimens; cure rates 90-95% |
| Decompensated cirrhosis (Child-Pugh B) | Cirrhosis with ascites, encephalopathy, or coagulopathy | Epclusa + ribavirin 12 weeks; avoid protease inhibitors; hepatology involvement essential |
| Advanced decompensated (Child-Pugh C) | Severe hepatic dysfunction | Epclusa + ribavirin 12 weeks or Epclusa alone 24 weeks; transplant consideration; specialist team |
| Post-liver transplant | HCV recurrence in transplanted liver | Sofosbuvir-based regimen with attention to immunosuppressant interactions |
Protease inhibitor caution in decompensated cirrhosis: HCV NS3/4A protease inhibitors (voxilaprevir, glecaprevir, grazoprevir, paritaprevir) accumulate substantially in advanced cirrhosis and can worsen hepatic decompensation. Vosevi, Mavyret, Zepatier, and Viekira Pak are therefore contraindicated in Child-Pugh B or C cirrhosis. Sofosbuvir + velpatasvir (Epclusa) does not contain a protease inhibitor and is the preferred regimen in decompensated cirrhosis, based on ASTRAL-4 evidence.
Post-cure surveillance: cirrhotic patients who achieve SVR (cure) still require lifelong hepatocellular carcinoma surveillance. Twice-yearly abdominal ultrasound (with or without alpha-fetoprotein) is standard. Although HCV cure substantially reduces HCC risk, it does not eliminate it, particularly in patients with established cirrhosis before treatment. Ongoing hepatology follow-up is essential.
Hepatic function recovery after cure can be substantial. Patients with compensated cirrhosis and preserved function often maintain stable liver disease after cure. Patients with decompensated cirrhosis may show marked functional improvement, sometimes to the point of being removed from the transplant waitlist (the phenomenon of delisting). Fibrosis regression on non-invasive testing (FibroScan) has been documented in real-world cohorts over 2-5 years post-cure. This underscores the importance of treating even patients with advanced disease.
📊 Adult Dosing and Treatment Duration Framework
Adult dosing of sofosbuvir is uniform at 400 mg once daily across essentially all combination regimens. Treatment duration varies by combination product, HCV genotype, treatment history, and cirrhosis status. The straightforward once-daily dosing supports excellent adherence, and the moderate treatment durations (typically 8-24 weeks) make cure achievable even in populations with variable healthcare access.
📊 Standard adult dosing framework
| Parameter | Detail |
|---|---|
| Sofosbuvir dose | 400 mg once daily (single tablet) |
| Administration | With or without food (food does not meaningfully affect exposure) |
| Timing | Same time each day to support adherence; no specific time-of-day requirement |
| Missed dose within 18 hours | Take as soon as remembered; resume regular schedule |
| Missed dose beyond 18 hours | Skip missed dose; resume regular schedule; never double up |
| Adherence critical | Missed doses reduce cure probability; complete the full course |
📅 Treatment duration by regimen and scenario
| Regimen | Population | Duration |
|---|---|---|
| Sofosbuvir + ledipasvir | Treatment-naive GT1, no cirrhosis, HCV RNA under 6 million IU/mL | 8 weeks |
| Sofosbuvir + ledipasvir | Treatment-naive or experienced GT1, most scenarios | 12 weeks |
| Sofosbuvir + ledipasvir | Cirrhotic treatment-experienced GT1 | 24 weeks or 12 weeks with ribavirin |
| Sofosbuvir + velpatasvir | All genotypes, most scenarios | 12 weeks |
| Sofosbuvir + velpatasvir + ribavirin | Decompensated cirrhosis (Child-Pugh B) | 12 weeks |
| Sofosbuvir + velpatasvir + voxilaprevir (Vosevi) | Salvage for prior DAA failure | 12 weeks |
| Sofosbuvir + daclatasvir | All genotypes, non-cirrhotic | 12 weeks |
| Sofosbuvir + daclatasvir + ribavirin | Cirrhotic, treatment-experienced, or difficult scenarios | 12-24 weeks |
Adherence importance cannot be overstated. HCV treatment is a finite course with a specific goal (sustained virologic response). Missing doses can reduce cure probability and increase risk of resistance emergence. Patients should be counseled to link daily dosing to a routine (meal, morning coffee, teeth brushing), keep a supply reminder system, and communicate proactively about any adherence challenges. Twelve weeks of perfect adherence is achievable for most patients with proper support.
🧒 Pediatric Sofosbuvir Considerations
Pediatric sofosbuvir use has expanded steadily since initial FDA approval, with weight-based dosing established for children as young as 3 years of age. Pediatric HCV treatment has become a standard component of family-based HCV elimination efforts, particularly in the WHO framework for global HCV elimination. Pediatric cure rates match adult rates when appropriate weight-based dosing is used.
🧒 Pediatric weight-based dosing (sofosbuvir + ledipasvir)
| Age and weight | Sofosbuvir + ledipasvir dose |
|---|---|
| 3 years and older, under 17 kg | 150 mg sofosbuvir + 33.75 mg ledipasvir (oral granules) |
| 3 years and older, 17-35 kg | 200 mg sofosbuvir + 45 mg ledipasvir (oral granules or low-dose tablet) |
| 35 kg or more | Adult dose 400 mg sofosbuvir + 90 mg ledipasvir |
| Duration | 12 weeks standard; 8 weeks possible in select treatment-naive non-cirrhotic children |
🧒 Sofosbuvir + velpatasvir pediatric dosing
| Age and weight | Sofosbuvir + velpatasvir dose |
|---|---|
| 3 years and older, under 17 kg | 150 mg sofosbuvir + 37.5 mg velpatasvir (oral granules) |
| 3 years and older, 17-30 kg | 200 mg sofosbuvir + 50 mg velpatasvir |
| 30 kg or more | Adult dose 400 mg sofosbuvir + 100 mg velpatasvir |
Pediatric HCV epidemiology: most pediatric HCV in the developed world results from vertical transmission from HCV-positive mothers. Vertical transmission rate is approximately 5-6% in the absence of HIV coinfection and higher in HIV-coinfected mothers. In lower-income settings, iatrogenic exposures and household exposures also contribute. Pediatric treatment now offers definitive cure at a young age, preventing decades of chronic HCV complications.
Cure benefits in children: treating HCV early in life prevents cumulative fibrosis, eliminates lifetime hepatocellular carcinoma risk associated with chronic HCV, removes stigma associated with chronic infection, allows normal participation in family and school activities, and prevents future transmission. Cost-effectiveness analyses in high-income settings show pediatric HCV treatment is highly cost-effective across long time horizons.
Formulation considerations: oral granules for younger children (packet sprinkled on soft food such as applesauce or yogurt) enable accurate dosing without requiring tablet swallowing. Older children who can swallow tablets use the adult formulation. Palatability and family engagement in daily administration support the excellent adherence that produces adult-equivalent cure rates in pediatric populations.
👴 Elderly Considerations for HCV Treatment
Elderly patients are a substantial and growing HCV treatment population. Historically undertreated with interferon due to poor tolerability, older adults now benefit from the excellent safety profile of sofosbuvir-based regimens. Cure rates in patients over 65 are essentially identical to younger adults, and treatment substantially reduces the future disease burden regardless of the age at which cure is achieved.
👴 Considerations specific to elderly HCV patients
Cure rates equivalent to younger adults
Real-world studies of sofosbuvir-based regimens in patients over 65, over 75, and even over 80 consistently show cure rates matching younger populations. Age itself is not a treatment barrier for direct-acting antiviral therapy.
Cirrhosis prevalence higher
Because many elderly patients have had HCV for decades before diagnosis or treatment access, cirrhosis prevalence in this group is often 30-50%. Cirrhotic regimen selection and post-cure hepatocellular carcinoma surveillance apply to this group in particular.
Polypharmacy review important
Elderly patients often take multiple medications for cardiovascular, metabolic, and other chronic conditions. Structured medication reconciliation before starting sofosbuvir identifies potential P-gp inducer conflicts (amiodarone, phenytoin, carbamazepine, St. John Wort) and other interaction concerns.
Renal function assessment
Age-related decline in glomerular filtration rate is expected. Serum creatinine may underestimate the drop because lean muscle mass is often reduced. Estimating creatinine clearance is prudent before starting, with attention to the special consideration for severe renal impairment discussed in section 16.
Amiodarone screening critical
Elderly cardiac patients on amiodarone must be identified before starting sofosbuvir due to the severe bradycardia interaction (see section 23). This can require regimen substitution or coordination with cardiology to change amiodarone therapy.
Life expectancy benefit
Even in the ninth decade of life, curing HCV improves survival and reduces morbidity from decompensation and hepatocellular carcinoma. Age alone should not deter treatment consideration.
No specific age-based dose adjustment is required for sofosbuvir. Adjustments are based on renal function and comorbidities, not chronologic age. This reflects the drug straightforward metabolism and elimination, which do not change substantially with normal aging.
🫀 Renal Impairment - Special Warning for Severe Impairment
Because sofosbuvir major metabolite (GS-331007) accumulates substantially in reduced renal function, patients with severe renal impairment or end-stage renal disease historically required careful consideration. Original prescribing information recommended avoidance in patients with estimated glomerular filtration rate under 30 mL/min. Subsequent evidence and label updates have relaxed this recommendation, but renal impairment remains a special consideration requiring specialist attention.
🫀 Renal impairment framework
| Creatinine clearance | Recommendation |
|---|---|
| Above 60 mL/min | Standard 400 mg once daily; no adjustment |
| 30-59 mL/min | Standard 400 mg once daily; monitor renal function during treatment |
| Under 30 mL/min not on dialysis | Updated 2019 FDA label: full-dose sofosbuvir may be used; consider alternative non-sofosbuvir regimens if available (Mavyret is preferred by many clinicians for severe renal impairment) |
| End-stage renal disease on hemodialysis | Full-dose sofosbuvir combinations demonstrated safe in real-world cohorts; use with specialist involvement; timing relative to dialysis less critical |
| Non-sofosbuvir alternative | Glecaprevir/pibrentasvir (Mavyret) is renally-safer alternative with no dose adjustment needed for any renal function |
The 2019 label update reflected accumulated evidence that sofosbuvir-based regimens are safe and effective in severe renal impairment despite GS-331007 accumulation. The concern was that the inactive metabolite itself is not toxic and its accumulation does not increase adverse effects meaningfully. Real-world experience in dialysis populations, particularly with sofosbuvir + ledipasvir and sofosbuvir + velpatasvir, has confirmed acceptable safety and high cure rates.
Practical approach in severe renal impairment: consult with hepatology and nephrology. If Mavyret is available and accessible, it is generally preferred for creatinine clearance under 30 mL/min. If Mavyret is not available or contraindicated, full-dose sofosbuvir-based regimens can be used with careful monitoring. Fixed-dose combinations do not typically require dose adjustment for the sofosbuvir component even in advanced renal disease.
Post-transplant renal considerations: patients with HCV recurrence in renal transplant recipients can be treated with sofosbuvir-based regimens with attention to immunosuppressant interactions. Coordination between transplant nephrology and hepatology is standard. Excellent cure rates have been achieved in this population without adverse effects on graft function.
🪶 Hepatic Impairment Considerations
Sofosbuvir undergoes intrahepatic prodrug activation rather than systemic hepatic metabolism through CYP450 enzymes. This means that hepatic impairment has different implications for sofosbuvir than for many other drugs. Modest hepatic dysfunction does not require dose adjustment, but decompensated cirrhosis and other advanced hepatic conditions influence regimen selection more than sofosbuvir dose specifically.
🪶 Hepatic impairment framework for sofosbuvir
Mild to moderate impairment (Child-Pugh A or B)
No dose adjustment for sofosbuvir. Standard 400 mg once daily. Regimen selection depends on specific companion drug and cirrhosis stage. Ribavirin may be added in some scenarios.
Severe impairment (Child-Pugh C)
Sofosbuvir itself has no dose reduction requirement, but companion drug considerations dominate. Protease inhibitors (voxilaprevir, glecaprevir, grazoprevir) are contraindicated in Child-Pugh B or C due to accumulation and worsening decompensation risk. Sofosbuvir + velpatasvir with ribavirin is the preferred regimen based on ASTRAL-4.
Post-liver transplant HCV recurrence
Sofosbuvir-based regimens are highly effective in preventing and treating HCV recurrence after liver transplantation. Immunosuppressant management requires attention: cyclosporine can moderately increase sofosbuvir exposure; tacrolimus interaction is manageable. Coordination with the transplant team is essential.
Hepatocellular carcinoma post-cure surveillance
Patients with cirrhosis at treatment initiation require lifelong twice-yearly ultrasound surveillance for hepatocellular carcinoma even after sustained virologic response. HCV cure reduces but does not eliminate HCC risk in cirrhotic patients.
Hepatic function assessment prior to treatment should include comprehensive metabolic panel with hepatic enzymes and albumin, prothrombin time or international normalized ratio (INR), platelet count, and clinical assessment for ascites and encephalopathy. Non-invasive fibrosis assessment (FibroScan or laboratory-based scoring such as APRI or FIB-4) helps stage disease. Confirmed cirrhosis with signs of decompensation warrants specialist involvement for regimen selection.
Fibrosis regression after cure: substantial evidence indicates that some cirrhotic patients experience fibrosis regression after HCV cure, though established structural changes may persist. Regression is most pronounced in less advanced cirrhosis. Ongoing hepatology follow-up assesses progression versus regression and continues surveillance.
🧬 Drug Interactions and Amiodarone Warning
The drug interaction profile of sofosbuvir is generally favorable due to minimal cytochrome P450 involvement. However, several specific interactions require attention. The most serious is the pharmacodynamic interaction with amiodarone that can cause severe bradycardia. P-glycoprotein and BCRP inducers can reduce sofosbuvir efficacy. And some combination-partner-specific interactions require attention to the full regimen rather than sofosbuvir alone.
⚠️ Serious amiodarone warning
Co-administration of amiodarone with sofosbuvir-based regimens has resulted in severe symptomatic bradycardia and cardiac arrest. Multiple patient deaths have been reported. The mechanism is thought to involve pharmacodynamic interaction on cardiac sodium channels and calcium handling.
If amiodarone therapy cannot be discontinued (long amiodarone half-life means residual effect persists for months after stopping), sofosbuvir should be avoided when possible, or used with intensive cardiac monitoring in specialized settings. Discussion with cardiology and hepatology is essential.
🧬 Interactions requiring attention
| Interacting agent | Mechanism | Clinical guidance |
|---|---|---|
| Amiodarone | Pharmacodynamic - severe bradycardia risk | Avoid; if unavoidable, cardiac monitoring in specialized setting |
| Rifampin, rifapentine | Strong P-gp/BCRP inducers - reduce sofosbuvir exposure | Contraindicated; complete TB treatment first or coordinate |
| St. John Wort | P-gp inducer - reduces sofosbuvir exposure | Contraindicated during therapy; discontinue at least 2 weeks before starting |
| Phenytoin, carbamazepine, phenobarbital | Anticonvulsant enzyme inducers - reduce sofosbuvir exposure | Contraindicated; use alternative anticonvulsants during HCV treatment |
| Oxcarbazepine, primidone | Enzyme inducer effect | Avoid; consider alternative anticonvulsants |
| Tipranavir/ritonavir | Reduces sofosbuvir exposure | Avoid combination |
| Modafinil | P-gp inducer - reduces exposure | Avoid |
| Digoxin | Ledipasvir and velpatasvir (companion drugs) can increase digoxin levels via P-gp inhibition | Monitor digoxin levels; consider dose reduction |
| Acid-suppressing drugs (PPIs, H2-blockers) | Ledipasvir and velpatasvir (companion drugs) require gastric acidity for absorption | Follow specific product labeling for PPI timing; sofosbuvir alone not affected |
Notably manageable: sofosbuvir has no clinically significant interactions with common oral contraceptives, statins (though companion drug ledipasvir does affect some statins), most antihypertensives, oral antidiabetic agents, or the typical medications used in chronic disease management. Most patients on stable medication regimens can add sofosbuvir-based HCV therapy without medication changes.
HIV antiretroviral interactions: most modern integrase inhibitor and NNRTI-based regimens have manageable interactions with sofosbuvir-based HCV therapy. Efavirenz and specific protease inhibitor combinations may need review. Coordination with HIV specialists supports appropriate regimen selection in coinfection.
🤰 Pregnancy Considerations for HCV Treatment
Sofosbuvir pregnancy considerations differ importantly by the specific combination regimen. Sofosbuvir monotherapy or sofosbuvir + ledipasvir or sofosbuvir + velpatasvir have insufficient human pregnancy data but no signals of teratogenicity in animal studies. In contrast, ribavirin (used in some sofosbuvir combinations) is teratogenic and absolutely contraindicated in pregnancy. This distinction is critical for treatment planning in women of childbearing potential.
🤰 Pregnancy considerations for sofosbuvir-based regimens
| Sofosbuvir alone in animals | No adverse developmental effects in reproductive toxicity studies |
| Sofosbuvir human pregnancy data | Limited; no established teratogenicity signal from case reports and pregnancy registries |
| Ribavirin (companion in some regimens) | FDA Category X - absolutely contraindicated in pregnancy and in male partners of pregnant women; teratogenic and embryocidal |
| Ribavirin contraception requirement | Two forms of effective contraception during and for 6 months after ribavirin exposure (both sexes) |
| Preferred approach | Defer HCV treatment until after pregnancy when possible; use ribavirin-free regimens if treatment during pregnancy is essential (rare situations) |
| Post-pregnancy treatment | Standard sofosbuvir-based regimens after delivery; timing relative to breastfeeding decision (see next section) |
Vertical transmission of HCV without treatment is approximately 5-6% in HIV-negative mothers and higher in HIV-coinfected mothers. Currently, HCV treatment is not established as prevention of vertical transmission during pregnancy, though this is an area of active research. In practice, most women defer treatment until after delivery. Newborns of HCV-positive mothers require HCV RNA testing at 2-6 months and antibody testing after 18 months to determine infection status.
The ribavirin distinction is crucial. Ribavirin has demonstrated teratogenicity in multiple animal species including primates. Its long intracellular half-life means the drug persists for months after discontinuation, and both female and male exposure requires strict contraception during and for 6 months after therapy. Any sofosbuvir combination containing ribavirin (some genotype 3 or decompensated cirrhosis regimens) triggers this consideration.
Practical framework: assess pregnancy potential in women aged 15-50 before starting therapy. If pregnancy is planned during the next year, discuss timing options and preferred regimens. For women who become pregnant during therapy, ribavirin must be discontinued immediately and pregnancy registry enrollment considered. Ribavirin-free sofosbuvir combinations (sofosbuvir + velpatasvir, sofosbuvir + ledipasvir standard regimens) do not trigger the same absolute contraindication, though limited pregnancy data still supports post-pregnancy timing when possible.
🍼 Breastfeeding Considerations During HCV Therapy
Breastfeeding during sofosbuvir-based HCV therapy is complicated by limited human data and differing risk profiles for the various combination partners. Sofosbuvir and its major metabolite GS-331007 pass into breast milk to some extent. Practical decision-making balances the benefits of breastfeeding against the theoretical infant exposure risk.
🍼 Breastfeeding considerations framework
Sofosbuvir human milk data
Limited quantitative data. Estimated milk-to-plasma ratios suggest modest transfer. Long-term effects on breastfed infants are unknown due to limited follow-up data.
HCV transmission through breast milk
HCV is not transmitted through intact breast milk in the great majority of cases. Cracked or bleeding nipples may increase risk; some guidelines recommend expressed milk during nipple healing.
Ribavirin absolute contraindication
If the regimen contains ribavirin, breastfeeding must be discontinued during therapy and for a period afterward. This is a firm restriction because ribavirin passes into breast milk and has known toxicity to red blood cells.
Ribavirin-free regimens preferred
Sofosbuvir + velpatasvir or sofosbuvir + ledipasvir without ribavirin present much lower theoretical concern. Some clinicians support continued breastfeeding with these regimens after informed discussion; others recommend deferring treatment to after weaning.
Shared decision-making
Given limited data, decisions balance individual factors including how urgent HCV treatment is, breastfeeding importance to the family, availability of alternative regimens, and infant characteristics. Discussion with pediatric infectious disease specialists can help.
Practical approach in newly diagnosed HCV during breastfeeding: for non-cirrhotic women with well-controlled HCV, deferring treatment until after weaning is reasonable when other risks are low. For women with advanced disease or specific concerns, treatment during ongoing breastfeeding may be initiated with ribavirin-free regimens after individualized risk-benefit assessment. Post-cure follow-up on the infant should include HCV testing to confirm infection status.
📋 Common Adverse Effects and Excellent Tolerability Profile
Sofosbuvir-based regimens have exceptionally favorable tolerability profiles that stand in dramatic contrast to the older interferon-containing therapies they replaced. Most patients report only mild symptoms or none at all, and treatment discontinuation for tolerability is very uncommon. This favorable profile has been a key factor in the successful global scale-up of HCV treatment programs.
📋 Common adverse effects with sofosbuvir-based regimens
| Effect | Frequency | Notes |
|---|---|---|
| Fatigue | Approximately 15-25% | Usually mild; multifactorial; often improves during treatment |
| Headache | Approximately 15-25% | Usually mild; responds to standard analgesics |
| Nausea | 5-10% | Take with food if bothersome |
| Insomnia | 5-10% | Consider morning dosing if problematic |
| Anemia (with ribavirin) | Varies; often 30-50% of ribavirin-treated patients | Ribavirin-specific; not from sofosbuvir itself; may require ribavirin dose reduction |
| Rash | Under 5% | Usually mild; distinguish from hypersensitivity if severe |
| Diarrhea | 5-10% | Usually mild; symptomatic management |
| Elevated bilirubin (with protease inhibitor combinations) | Varies | Often benign; from OATP inhibition by protease inhibitor |
Comparison to interferon era highlights the transformation. Peginterferon plus ribavirin regimens caused fever, myalgias, marked fatigue, hematologic toxicity, depression, and thyroid dysfunction in most patients. Discontinuation for tolerability was common. Sofosbuvir-based regimens produce a fraction of these effects. Patients can typically continue full-time work and normal activities during treatment. This tolerability difference is a major reason why HCV treatment could scale to millions of patients worldwide.
Ribavirin-driven adverse effects deserve separate consideration. When sofosbuvir-based regimens include ribavirin (some genotype 3 or decompensated cirrhosis scenarios), most of the observed hematologic toxicity, teratogenicity concerns, and gastrointestinal effects come from ribavirin rather than sofosbuvir. Ribavirin-free regimens (sofosbuvir + ledipasvir standard, sofosbuvir + velpatasvir standard, sofosbuvir + daclatasvir) have particularly clean profiles.
Discontinuation rates in real-world sofosbuvir experience have been consistently low. Registry and observational cohort studies report tolerability-driven discontinuation rates of 1-3%, much lower than any interferon-based regimen. Serious adverse events are uncommon and mostly attributable to underlying advanced hepatic disease rather than the DAA regimen. This favorable safety signal underlies the very high cure rates achievable in real-world practice.
🚨 Side Effects Overview - Sofosbuvir Safety Profile
The following sections provide detailed coverage of specific adverse effect categories for sofosbuvir-based regimens, from the serious amiodarone interaction and HBV reactivation boxed warning through individual effect categories such as fatigue, anemia (with ribavirin combinations), rash, and hepatic considerations. This overview provides orientation before the detailed coverage that follows in sections 23-33.
🚨 Sofosbuvir safety profile at-a-glance
| Category | Nature | Frequency |
|---|---|---|
| Amiodarone symptomatic bradycardia | Serious pharmacodynamic interaction; deaths reported | Rare but severe when it occurs |
| BOXED: HBV reactivation | HBV replication reactivation in patients with prior or occult HBV | Rare but potentially severe; screen all patients before starting |
| Fatigue | Most common tolerability complaint | 15-25%; mild; improves during treatment |
| Headache | Common tolerability issue | 15-25%; mild; responds to standard treatment |
| Anemia (ribavirin-containing regimens) | Hemolytic anemia from ribavirin; not from sofosbuvir | 30-50% of ribavirin-treated patients |
| Rash | Usually mild non-specific rash | Under 5%; severe reactions rare |
| Gastrointestinal effects | Nausea, diarrhea, abdominal discomfort | 5-10%; mild; symptomatic management |
| Sleep disturbances | Insomnia and disrupted sleep patterns | 5-10%; morning dosing may help |
| Photosensitivity | Enhanced skin sensitivity to sunlight (with some companion drugs) | Uncommon; sun protection counseling standard |
| Bilirubin elevations | From companion protease inhibitors, not sofosbuvir | Often benign OATP inhibition; distinguish from hepatic dysfunction |
| Hematologic effects | Usually reflects underlying disease or ribavirin | Sofosbuvir-specific hematologic effects rare |
| Resistance (S282T) | Very rarely selected; when it occurs, requires alternative therapy | Rare; combination therapy prevents emergence |
Key takeaway for clinicians and patients: sofosbuvir-based regimens are among the best-tolerated antivirals ever developed. The two most important safety considerations are the amiodarone bradycardia interaction and the HBV reactivation boxed warning, both of which are addressed by screening at treatment initiation. Most patients complete the full course without significant adverse effects and achieve sustained virologic response (cure).
How to use the sections ahead: sections 23-33 provide dedicated coverage of specific adverse effects and safety considerations. Sections 34-36 cover monitoring, patient counseling, and contraindications. This structure allows patients and clinicians to focus on the specific concern relevant to their situation. Not every adverse effect discussed occurs in every patient; individual experience varies substantially, and standard monitoring detects problems early when they arise.
🫀 Symptomatic Bradycardia with Amiodarone - Serious Warning
The most serious pharmacodynamic interaction with sofosbuvir-based regimens involves amiodarone, an antiarrhythmic drug used in atrial fibrillation and ventricular arrhythmias. Post-marketing reports have documented symptomatic bradycardia including cardiac arrest and death in patients receiving sofosbuvir together with amiodarone. The mechanism is not fully understood but appears to involve additive effects on cardiac conduction and possible calcium handling changes.
⚠️ Documented cases and severity
Following approval of sofosbuvir-containing regimens, FDA and international regulators received reports of symptomatic bradycardia in patients on amiodarone starting these regimens. Reported cases include:
- Bradycardia in the first hours to days after starting sofosbuvir-based therapy
- Symptomatic events including near-syncope, syncope, dizziness, fatigue, lightheadedness
- Severe cases requiring pacemaker implantation
- Cardiac arrest and fatalities in a small number of reported cases
The risk appears highest when other bradycardia-associated medications (beta-blockers, calcium channel blockers) are also present, and in patients with underlying cardiac disease.
📌 Clinical management framework
Avoid combination if possible
The safest approach is to avoid sofosbuvir-containing regimens in patients on amiodarone. Alternative HCV regimens without sofosbuvir may be considered, particularly glecaprevir/pibrentasvir (Mavyret) which has no reported amiodarone interaction.
Consider amiodarone discontinuation
Where possible in coordination with cardiology, amiodarone may be discontinued before starting HCV therapy. Due to the drug very long half-life (approximately 60 days), residual effect persists for months. Some clinicians recommend a washout period, though clear evidence for optimal timing is limited.
Intensive monitoring if unavoidable
If sofosbuvir must be used with amiodarone, the first dose should ideally be given in a monitored inpatient setting with continuous telemetry for at least the first 48 hours. Ongoing outpatient monitoring should include periodic ECG and heart rate assessment throughout therapy.
Patient education
Patients must understand warning signs of bradycardia including near-syncope, unusual fatigue, lightheadedness, chest discomfort, palpitations, memory or concentration difficulties, and shortness of breath. Immediate medical evaluation is required for these symptoms.
Cardiology coordination
Any HCV treatment planning in patients on amiodarone should involve cardiology consultation. Balancing HCV cure benefits against the interaction risk requires input from both specialties.
Historical context: this interaction was not identified in pre-approval clinical trials because amiodarone-treated patients were largely excluded from HCV DAA studies. Post-marketing surveillance identified the signal, and label updates followed. The lesson highlights the importance of ongoing pharmacovigilance for drugs used in populations broader than trial populations.
🪶 HBV Reactivation Boxed Warning - Screening Essential
The hepatitis B virus reactivation boxed warning was added to sofosbuvir-based regimen labeling in 2016 after post-marketing reports of HBV reactivation, sometimes with severe hepatic consequences including liver failure and death. This warning applies to all direct-acting antiviral regimens for HCV, not just sofosbuvir specifically, but it is a critical consideration for anyone starting HCV treatment.
⚠️ FDA Boxed Warning: HBV reactivation
Test all patients for evidence of current or prior hepatitis B virus (HBV) infection by measuring HBsAg and anti-HBc before initiating HCV treatment with direct-acting antivirals. HBV reactivation has been reported in HCV/HBV coinfected patients who were undergoing or had completed treatment with HCV direct-acting antivirals and who were not receiving HBV antiviral therapy. Some cases have resulted in fulminant hepatitis, hepatic failure, and death. Monitor HCV/HBV coinfected patients for hepatitis flare or HBV reactivation during HCV treatment and post-treatment follow-up. Initiate appropriate patient management for HBV infection as clinically indicated.
🔬 Mechanism of HBV reactivation during HCV cure
Chronic HCV infection creates a complex immunologic environment in the liver. In some patients with both HCV and HBV (either overt HBV or occult HBV where HBsAg is negative but HBV DNA is detectable), the HCV infection actually appears to suppress HBV replication. Removing HCV with successful DAA therapy can:
- Eliminate the HCV-driven suppression of HBV
- Allow rapid HBV DNA increase over weeks to months
- Trigger immune-mediated hepatic inflammation as the immune system responds to the newly detectable HBV antigens
- Result in transaminase elevations, sometimes to marked levels, and in rare cases to hepatic failure
The risk applies to HBsAg-positive patients (overt HBV) and to some HBsAg-negative anti-HBc-positive patients (past infection with possible occult HBV).
📋 Screening and management protocol
| Patient category | Approach |
|---|---|
| HBsAg-positive (chronic HBV) | Start HBV therapy (tenofovir or entecavir) before or concurrent with HCV DAA therapy; continue HBV therapy per HBV guidelines |
| HBsAg-negative, anti-HBc-positive (past HBV) | Monitor for HBV reactivation during and after HCV therapy with HBV DNA and hepatic enzymes; treat reactivation promptly |
| HBsAg-negative, anti-HBc-negative (never infected) | No specific HBV monitoring required; consider HBV vaccination if susceptible |
| Unexplained ALT rise on HCV therapy | Check HBV DNA even if prior HBsAg negative |
| Post-cure surveillance | Continue monitoring for hepatic events for at least several months after HCV DAA completion |
Timing of HBV reactivation events in reported cases has typically been during the first 4-8 weeks of HCV DAA therapy, though later events have also been reported. Screening at treatment initiation and proactive HBV management have essentially eliminated the risk when properly implemented. The boxed warning is a strong reminder that HCV DAA therapy in HCV/HBV coinfected patients requires coordinated antiviral management.
🧠 Fatigue and Headache Management
Fatigue and headache are the two most common tolerability complaints during sofosbuvir-based therapy. Both are typically mild, respond to standard supportive measures, and improve as treatment progresses. They rarely lead to treatment discontinuation but can affect quality of life during the 8-24 week treatment course.
🧠 Understanding fatigue during HCV treatment
Fatigue reported during HCV DAA therapy has multiple contributors. Some patients experienced fatigue from underlying HCV before treatment, and this may take weeks to months to improve after cure. Some fatigue reflects the daily antiviral pressure on cellular metabolism. In some patients, sleep quality changes contribute. And in ribavirin-containing regimens, ribavirin-driven anemia can contribute substantially to fatigue.
Practical approach: reassure patients that fatigue is common but self-limited; encourage regular exercise as tolerated (which paradoxically often improves energy); ensure adequate sleep and hydration; screen for and treat depression or anxiety when present; assess for anemia if ribavirin is part of the regimen.
🧠 Headache during HCV treatment
Headache is reported by approximately 15-25% of patients on sofosbuvir-based therapy. Character is typically mild tension-type or non-specific, usually responds to standard analgesics (acetaminophen, ibuprofen), and often diminishes over the treatment course.
Warning signs requiring evaluation:
- Severe or sudden-onset headache
- Headache with fever, neck stiffness, or altered consciousness
- Headache with focal neurologic symptoms
- Progressive headache pattern change
- Headache with hypertension
Post-cure fatigue improvement: HCV-associated fatigue often reflects chronic inflammatory and immunologic effects of the virus itself. Studies of quality of life after HCV cure consistently show improvement in fatigue, cognitive complaints, and overall wellbeing over the months following sustained virologic response. Patients should understand that treatment fatigue is often transient and often followed by post-cure energy improvement over weeks to months.
🩸 Anemia Considerations with Ribavirin Companion
Ribavirin-driven anemia is the single most common significant hematologic effect during HCV DAA therapy. Sofosbuvir alone does not cause anemia. When ribavirin is added to a sofosbuvir combination for specific scenarios (genotype 3 with cirrhosis, decompensated cirrhosis, some retreatment scenarios), hemolytic anemia occurs commonly and can require intervention.
🩸 Ribavirin-induced hemolytic anemia framework
| Mechanism | Ribavirin accumulates in erythrocytes causing oxidative damage and hemolysis |
| Onset | Usually within first 2-4 weeks; progresses over first 8-12 weeks |
| Frequency | 30-50% of ribavirin-treated patients develop clinically significant hemoglobin drop |
| Typical hemoglobin drop | 2-4 g/dL on average; some patients drop more |
| Nadir timing | Typically weeks 4-12 of treatment |
| Recovery | Hemoglobin recovers over 4-8 weeks after ribavirin discontinuation |
| Reversibility | Fully reversible; no persistent hematologic effect after treatment completion |
📈 Monitoring and management
Baseline and periodic hemoglobin
Baseline CBC with hemoglobin before starting; repeat at week 2, week 4, week 8, and week 12 during ribavirin-containing therapy. More frequent monitoring in patients with baseline anemia or cardiac disease.
Dose reduction guidance
Standard ribavirin dose reduction thresholds: hemoglobin under 10 g/dL - reduce dose; hemoglobin under 8.5 g/dL - discontinue ribavirin; symptomatic anemia at any level - reduce or discontinue. Sofosbuvir is continued at full dose.
Cardiac considerations
Patients with underlying cardiovascular disease tolerate anemia poorly. In this population, tighter hemoglobin thresholds (dose reduce at higher levels) or ribavirin-free regimens may be preferable.
Erythropoiesis-stimulating agents
Occasionally used to maintain hemoglobin during ribavirin therapy in select patients where dose reduction would compromise efficacy. Standard practice varies; specialist involvement supports appropriate use.
Renal impairment amplifies risk
Ribavirin dose adjustment for renal impairment is essential. In severe renal impairment, ribavirin is often contraindicated or requires very careful dosing.
Prefer ribavirin-free when possible: modern practice increasingly uses ribavirin-free sofosbuvir combinations for most patients. Sofosbuvir + velpatasvir standard 12 weeks (Epclusa/Velpanat) and sofosbuvir + ledipasvir standard 12 weeks (Harvoni/Hepcinat LP) achieve excellent cure rates without ribavirin exposure and its hematologic burden. Ribavirin is reserved for specific scenarios where evidence supports its incremental benefit.
🧪 Rash and Cutaneous Effects
Skin reactions during sofosbuvir-based therapy are typically mild and self-limited. Rash is reported in under 5% of patients, and severe cutaneous reactions are rare. Nonetheless, distinguishing between mild non-specific rash and true hypersensitivity reactions remains important because severe reactions require immediate treatment change.
🧪 Cutaneous reactions overview
Mild non-specific rash
Occurs in under 5% of patients on sofosbuvir-based regimens. Typically morbilliform or maculopapular pattern. Onset usually in first 4-6 weeks. Usually self-limited without treatment change. Symptomatic management with antihistamines and topical corticosteroids as needed.
Ribavirin-associated pruritus and rash
Ribavirin causes pruritus and dry skin in a substantial fraction of treated patients. Emollients, antihistamines, and adequate hydration help symptomatic management. Rash from ribavirin is usually mild but occasionally requires dose consideration.
Severe cutaneous reactions (very rare)
Stevens-Johnson syndrome, toxic epidermal necrolysis, and DRESS syndrome have been rarely reported with HCV DAA regimens. Presenting features include mucosal involvement, blistering, systemic symptoms, and rapidly progressive skin findings. Any of these require immediate treatment discontinuation and specialist referral.
Photosensitivity considerations
Ledipasvir and velpatasvir (companion drugs in some regimens) may enhance skin sensitivity to sunlight modestly. Standard sun protection counseling is appropriate. Severe photosensitivity is uncommon.
Distinguishing benign from concerning rash: assess the rash extent, morphology, associated symptoms (fever, mucosal involvement, hepatic transaminase elevation, eosinophilia), and progression. Non-progressive mild rash without systemic features can be observed with symptomatic support. Progressive, systemic, or mucosal-involving rash requires immediate evaluation. Dermatology consultation is helpful for severe or atypical cases.
🫁 Gastrointestinal Effects and Management
Gastrointestinal effects during sofosbuvir-based therapy are generally mild and manageable with standard symptomatic measures. Nausea, diarrhea, and abdominal discomfort are the most common presentations. In ribavirin-containing regimens, gastrointestinal symptoms may be more pronounced due to ribavirin effects. Most patients tolerate the full course without significant intervention.
🫁 Gastrointestinal effects and management
| Effect | Frequency | Management |
|---|---|---|
| Nausea | 5-10% | Take with food; timing before bed; short-term antiemetic if severe |
| Diarrhea | 5-10% | Usually mild; loperamide if bothersome; ensure hydration |
| Abdominal pain | Under 5% | Assess for other causes if persistent or severe |
| Appetite changes | Under 5% | Monitor weight; usually resolves |
| Taste alteration (dysgeusia) | Uncommon | Usually mild and self-resolving |
| Constipation (with velpatasvir combinations) | Under 5% | Hydration and fiber; standard measures |
When to seek further evaluation: persistent or severe abdominal pain warrants workup for hepatic decompensation, pancreatitis, or other causes rather than assumption of drug effect. Bloody or persistent diarrhea suggests other etiologies including infectious causes or inflammatory bowel exacerbation. Weight loss beyond a few pounds should be investigated. Otherwise, mild transient GI effects are common and resolve without intervention.
Pill administration tips: taking the medication with food is not required but may reduce nausea. Some patients prefer bedtime dosing to sleep through any mild nausea. Consistent timing supports adherence more than any specific choice of time.
😴 Sleep Disturbances and Insomnia
Sleep disturbances during sofosbuvir-based therapy are uncommon but occasionally bothersome. Reported patterns include difficulty falling asleep, frequent nocturnal awakening, and non-restorative sleep. Underlying HCV can itself affect sleep quality, and treatment-related fatigue can paradoxically coexist with insomnia. Standard sleep hygiene measures usually suffice for management.
😴 Sleep considerations and management
Timing of medication
If insomnia develops during evening or bedtime dosing, switch to morning dosing to see if symptoms improve. Consistent timing supports adherence more than any specific time choice.
Sleep hygiene measures
Standard recommendations apply: consistent bedtime and wake time, cool dark bedroom, avoid caffeine after mid-afternoon, limit alcohol which fragments sleep, avoid screens for at least an hour before bed, regular daytime exercise, and stress management techniques.
Underlying causes assessment
Poor sleep may reflect depression, anxiety, hepatic encephalopathy (in cirrhotic patients), obstructive sleep apnea (common in patients with metabolic comorbidities), or other conditions unrelated to sofosbuvir directly. Structured assessment when sleep problems persist can identify treatable underlying conditions.
Short-term hypnotic considerations
Occasional use of short-acting hypnotics for symptomatic relief during treatment is reasonable in some patients. Benzodiazepines and Z-drugs interact minimally with sofosbuvir. In cirrhotic patients, cautious dosing is important due to accumulation risk.
Post-cure sleep improvement
Patients cured of HCV often report improved sleep quality over the subsequent months. Chronic HCV appears to impair sleep in ways that improve gradually after viral eradication. This is important context to communicate as patients complete treatment.
Distinguishing insomnia from other symptoms: fatigue with normal sleep, hepatic encephalopathy with altered sleep-wake patterns, and depression with early morning awakening all have distinct clinical patterns and management. When sleep complaints are prominent, structured assessment can differentiate the underlying issue and guide targeted intervention.
☀️ Photosensitivity Considerations
Photosensitivity during sofosbuvir-based therapy is not primarily a sofosbuvir effect but has been reported with the companion NS5A inhibitors ledipasvir and velpatasvir. Absolute risk is low, but patients should be aware of possible enhanced skin sensitivity to sunlight and take reasonable precautions. Severe photosensitive reactions are uncommon.
☀️ Photosensitivity considerations
Presentation
Enhanced sunburn susceptibility, morbilliform rash in sun-exposed areas, or non-specific dermatitis on face, neck, arms, and other sun-exposed skin. Usually mild and self-limited.
Practical prevention
Standard sun protection: broad-spectrum sunscreen SPF 30 or higher, protective clothing including brimmed hats and long sleeves in strong sunlight, sunglasses, and avoiding midday sun exposure when possible. These measures are appropriate for anyone but especially reasonable during HCV DAA therapy.
Symptomatic management
Sunburn or mild photosensitive rash typically responds to standard measures: cool compresses, aloe or moisturizer, topical corticosteroids for inflammation, oral antihistamines for pruritus. Progressive or severe reactions warrant evaluation.
Occupational sun exposure
Patients with outdoor occupations (construction, agriculture, landscaping) should take extra care with sun protection. Occasional adjustment to work timing during the peak treatment months may be appropriate.
Photosensitive reactions from other sources
Some concurrent medications (thiazides, tetracyclines, sulfonamides, some NSAIDs) also cause photosensitivity. Combined exposure may amplify effects. Medication reconciliation identifies patients at higher risk.
Sun protection in cirrhotic patients: patients with advanced hepatic disease may have poor synthetic function affecting skin quality. Standard sun protection is doubly important for this population regardless of any sofosbuvir-related photosensitivity concern. Skin cancer surveillance also applies to patients on chronic immunosuppression such as post-transplant HCV recurrence patients.
💛 Bilirubin Elevations and Hepatic Monitoring
Bilirubin elevations during sofosbuvir-based therapy can arise from several sources. When sofosbuvir is combined with a protease inhibitor (voxilaprevir in Vosevi, glecaprevir in Mavyret, grazoprevir), indirect (unconjugated) bilirubin elevations are relatively common but typically benign, reflecting OATP inhibition rather than hepatic injury. In contrast, direct bilirubin elevations or elevations with concurrent transaminase elevations warrant more careful evaluation for hepatic dysfunction.
💛 Distinguishing benign from concerning bilirubin elevations
| Pattern | Mechanism | Clinical significance |
|---|---|---|
| Indirect bilirubin rise, normal transaminases | Protease inhibitor OATP inhibition prevents bilirubin uptake | Benign; no treatment change; resolves after therapy completion |
| Direct bilirubin rise with transaminase rise | Hepatic injury or biliary process | Evaluate for HBV reactivation, drug-induced liver injury, or biliary pathology |
| Bilirubin rise with new symptoms | May reflect hepatic decompensation in cirrhotic patients | Prompt hepatology evaluation |
| Baseline Gilbert syndrome | UGT1A1 polymorphism causing mild indirect hyperbilirubinemia | Congenital variant; may be more pronounced during treatment; benign |
| Bilirubin rise with anemia (ribavirin regimens) | Hemolysis raising indirect bilirubin | Reflects hemolytic anemia; monitor CBC and consider ribavirin dose |
OATP inhibition explanation: hepatic organic anion transporting polypeptides (OATP1B1, OATP1B3) mediate bilirubin uptake from blood into hepatocytes. Protease inhibitors including voxilaprevir, glecaprevir, and grazoprevir modestly inhibit these transporters. Reduced bilirubin uptake causes a rise in circulating indirect bilirubin without hepatocellular injury. This pattern is characteristic and does not require treatment modification.
Sofosbuvir alone does not raise bilirubin. Elevations in sofosbuvir combinations without protease inhibitors (Harvoni, Epclusa, Hepcinat-Plus) warrant standard evaluation for hepatic dysfunction rather than assumption of drug effect. HBV reactivation, drug-induced hepatic injury, biliary events, and hepatic decompensation should be considered.
🩸 Hematologic Considerations During HCV Therapy
Hematologic effects during sofosbuvir-based HCV therapy vary substantially depending on the regimen. Sofosbuvir alone has minimal hematologic effect. Ribavirin causes hemolytic anemia in a large fraction of patients (discussed in section 26). Underlying cirrhosis contributes to baseline thrombocytopenia in some patients, and this may modestly worsen or remain stable during treatment.
🩸 Hematologic considerations during HCV treatment
Anemia (ribavirin-driven)
The dominant hematologic effect when ribavirin is present. Sofosbuvir alone or in ribavirin-free combinations does not cause meaningful anemia. Full coverage in section 26.
Thrombocytopenia in cirrhosis
Patients with cirrhosis often have baseline thrombocytopenia due to splenomegaly and reduced hepatic thrombopoietin production. Sofosbuvir-based therapy does not typically worsen this. In some cases, HCV cure leads to modest platelet count improvement over the subsequent months.
Neutropenia
Sofosbuvir does not cause meaningful neutropenia. This contrasts with interferon-based regimens where neutropenia was common. Baseline neutropenia in cirrhosis or other comorbid conditions can persist during treatment but rarely worsens on sofosbuvir-based regimens.
Coagulation parameters
Prothrombin time and INR reflect hepatic synthetic function. In cirrhotic patients starting therapy, baseline elevation is common and may improve modestly as hepatic function recovers post-cure. Sofosbuvir does not directly affect coagulation.
CBC monitoring schedule
Baseline complete blood count before starting; repeat at week 4 and week 12 in ribavirin-free regimens; more frequently in ribavirin-containing regimens (week 2, 4, 8, 12). Cirrhotic patients may need additional monitoring.
Comparison to interferon era: interferon-based HCV therapy commonly caused significant hematologic toxicity including neutropenia, thrombocytopenia, and anemia. Growth factors (filgrastim for neutropenia, erythropoiesis-stimulating agents for anemia) were often needed. Sofosbuvir-based regimens have eliminated most of this hematologic burden, contributing substantially to the tolerability improvement that characterizes the modern DAA era.
🔬 Sofosbuvir Resistance - S282T Mutation Framework
Sofosbuvir resistance is unusual due to the high genetic barrier of the drug. The principal resistance mutation is S282T in the HCV NS5B polymerase. This substitution reduces sofosbuvir susceptibility but also substantially reduces viral fitness, which explains why it is rarely selected clinically. Understanding this resistance framework is essential for treatment planning and rare cases of retreatment.
🔬 S282T resistance framework
| Key mutation | S282T (serine to threonine at position 282 of NS5B polymerase) |
| Susceptibility change | Reduces sofosbuvir susceptibility approximately 3-fold in vitro |
| Viral fitness impact | Substantially reduces viral replication capacity - fit-quenching mutation |
| Baseline prevalence | Very rare in treatment-naive patients (under 1%) |
| Treatment-emergent | Rarely observed after sofosbuvir treatment failure; other mechanisms usually account for failure |
| Reversion | Reverts rapidly to wild-type after drug pressure removed (due to fitness cost) |
| Salvage strategy | Vosevi (sofosbuvir + velpatasvir + voxilaprevir) with strong second and third agents; or non-sofosbuvir regimens including Mavyret |
Why sofosbuvir resistance is so rare: the S282T mutation both reduces sofosbuvir susceptibility and substantially cripples viral polymerase function. The virus rarely selects this mutation because the resistant virus replicates poorly, allowing wild-type virus to outcompete it. This intrinsic fitness cost is a design consequence of targeting a highly conserved active site with such stringent substrate requirements.
Treatment failure without S282T: when patients fail sofosbuvir-based therapy, the responsible mechanism is more commonly NS5A resistance mutations (Y93H, L31M, and others depending on the specific NS5A inhibitor) or adherence issues rather than sofosbuvir resistance itself. Resistance testing before retreatment identifies the specific resistance profile and guides regimen selection.
Retreatment strategy: patients who fail sofosbuvir-containing regimens are usually candidates for retreatment with Vosevi (sofosbuvir + velpatasvir + voxilaprevir 12 weeks) based on POLARIS-1 evidence. This salvage regimen works even in most cases where NS5A resistance has emerged. In select scenarios where sofosbuvir cannot be used, Mavyret (glecaprevir/pibrentasvir) provides a non-sofosbuvir alternative. Coordination with hepatology specialists is standard for retreatment planning.
Resistance testing recommendations: baseline resistance testing is not routinely required in treatment-naive patients because the pan-genotypic regimens have excellent activity across natural HCV populations. After treatment failure, resistance testing before retreatment is standard to guide regimen selection. Testing is performed on standard commercial platforms.
📈 Monitoring Parameters and SVR12 Endpoint
Monitoring during sofosbuvir-based HCV therapy is designed around the SVR12 endpoint (sustained virologic response 12 weeks after treatment completion) which defines cure. Additional monitoring assesses tolerability, safety of the specific regimen and combination, and detection of the rare complications discussed in preceding sections. A structured monitoring schedule supports safe, effective treatment and confirms the desired cure outcome.
📈 Baseline assessment before starting
- Complete blood count with platelets
- Comprehensive metabolic panel including hepatic enzymes, bilirubin, albumin, creatinine
- Prothrombin time and international normalized ratio (INR)
- Estimated creatinine clearance
- HCV RNA quantitation and genotype
- HCV resistance testing (for retreatment or specific scenarios)
- HIV serology
- HBsAg, anti-HBc, anti-HBs (mandatory - boxed warning screening)
- HBV DNA if HBsAg positive or anti-HBc positive
- Hepatocellular carcinoma surveillance (ultrasound) in cirrhotic patients
- Fibrosis staging (non-invasive tests such as FibroScan, APRI, FIB-4)
- Pregnancy testing where applicable
- Medication reconciliation for drug interactions (amiodarone screening critical)
- Cardiovascular assessment if amiodarone or other bradycardia-associated drugs
📅 On-therapy monitoring schedule
| Timing | Assessments |
|---|---|
| Week 2 (if ribavirin containing) | Hemoglobin (early anemia detection); tolerability review |
| Week 4 | HCV RNA (early virologic response check); CBC, CMP; adherence review |
| Week 8 (in 12-week regimens) | CBC, CMP; assess tolerability; confirm continued adherence |
| End of treatment | HCV RNA (end-of-treatment response); CBC, CMP; assess for any adverse events |
| 12 weeks after end of treatment | HCV RNA (SVR12 assessment - defines cure) |
| 24 weeks after end of treatment (optional) | HCV RNA (SVR24 - additional confirmation, historically used, now less emphasized) |
| Cirrhotic patients ongoing | Twice-yearly HCC surveillance ultrasound plus alpha-fetoprotein |
SVR12 defines cure. Sustained virologic response 12 weeks after treatment completion (undetectable HCV RNA) is essentially permanent cure of hepatitis C in over 99% of cases. Late relapse after SVR12 is extremely rare. This endpoint replaced the older SVR24 (24 weeks) because studies confirmed 12 and 24 week outcomes are essentially identical, simplifying follow-up.
Post-cure follow-up: cured patients need ongoing hepatology follow-up mainly for cirrhotic sequelae surveillance. Non-cirrhotic patients typically require no ongoing HCV-specific follow-up after SVR12 confirmation. Cirrhotic patients need lifelong hepatocellular carcinoma surveillance every 6 months. Reinfection risk (in people with ongoing exposure) may warrant periodic HCV RNA testing.
📦 Storage and Patient Counseling Essentials
Proper storage and comprehensive patient counseling supports safe, effective sofosbuvir therapy. The tablet formulation has straightforward storage requirements, and counseling essentials cover adherence throughout the treatment course, warning signs of important adverse effects, and expectations for the SVR12 cure assessment after treatment ends.
📦 Storage requirements
| Temperature | Room temperature 20-25 C (68-77 F); brief excursions permitted 15-30 C |
| Container | Original container with tightly closed cap; protect from moisture |
| Avoid | Direct sunlight, high heat, high humidity (avoid bathroom cabinet) |
| Child access | Keep out of reach of children in child-resistant packaging |
| Do not use | Expired medication; damaged tablets; medication with unusual appearance |
🗣️ Essential patient counseling points
Complete the full course
Even if feeling well, take every dose for the full duration prescribed (typically 8-24 weeks). Stopping early substantially reduces cure probability. This is a finite treatment with a specific endpoint.
Take at same time each day
Link to a daily habit (morning coffee, meal, teeth brushing, bedtime). Consistent timing supports adherence better than any specific time choice. Set phone reminders during the treatment period.
Report immediately: heart symptoms if on amiodarone
If taking amiodarone or any bradycardia-associated medication, report near-syncope, unusual fatigue, lightheadedness, chest discomfort, or palpitations immediately. This is a serious safety concern requiring urgent evaluation.
Report severe symptoms of any kind
Contact healthcare provider for severe rash with fever or mucosal involvement, severe abdominal pain, unexplained jaundice, dark urine, or any severe or unusual symptoms.
Do not start new medications without checking
Some medications cannot be safely used with sofosbuvir. Inform all healthcare providers about ongoing HCV therapy. Check with pharmacist before starting any new prescription or over-the-counter medication, especially St. John Wort and other herbal products.
Understand the cure endpoint
Successful treatment is defined by SVR12 - undetectable HCV RNA 12 weeks after finishing therapy. This means the appointment three months after your last dose is critical to confirm cure. Once cured, HCV is essentially permanently eliminated.
Prevent reinfection after cure
HCV cure does not confer immunity. Ongoing exposure to blood-borne infection (needle sharing, tattoo tools not properly sterilized, sexual transmission in high-risk contexts) can result in reinfection. Discuss harm reduction strategies as appropriate.
Post-cure follow-up expectations
Non-cirrhotic cured patients typically need no HCV-specific ongoing follow-up. Cirrhotic patients continue lifelong hepatocellular carcinoma surveillance every 6 months. Post-cure hepatology follow-up assesses fibrosis change and monitors for any complications.
Emotional dimension of HCV cure: for patients who have lived with HCV for decades, cure is a profoundly meaningful event. Some patients report a mix of relief, gratitude, and even mild grief for the years of illness. Post-cure counseling supports emotional processing and can improve overall quality of life outcomes.
🚫 Contraindications - Absolute and Relative Considerations
Contraindications for sofosbuvir are limited but include serious considerations. Absolute contraindications are few; relative contraindications and precautions frame the situations requiring careful evaluation before use. Some contraindications are specific to sofosbuvir combinations rather than sofosbuvir alone.
🚫 Absolute contraindications
Hypersensitivity to sofosbuvir or excipients
Prior severe hypersensitivity reaction attributed to sofosbuvir is a contraindication to rechallenge.
Ribavirin during pregnancy (regimens containing ribavirin)
Ribavirin is teratogenic. Sofosbuvir combinations containing ribavirin are absolutely contraindicated during pregnancy and in male partners of pregnant women. Two forms of effective contraception required during and for 6 months after therapy.
Strong P-gp inducers coadministration
Rifampin, rifapentine, St. John Wort, phenytoin, carbamazepine, phenobarbital, and other strong P-gp/BCRP inducers reduce sofosbuvir exposure to a degree that compromises efficacy. Contraindicated during therapy.
Decompensated cirrhosis with protease inhibitor combinations
Vosevi, Mavyret, Zepatier, and Viekira Pak (which contain HCV protease inhibitors) are contraindicated in Child-Pugh B or C cirrhosis. This is not a sofosbuvir contraindication but restricts specific combination products.
⚠️ Relative contraindications and precautions
Amiodarone concurrent use
Serious bradycardia risk. Avoid combination when possible; if unavoidable, intensive cardiac monitoring in specialized setting. This is arguably the most important interaction to identify before starting sofosbuvir-based therapy.
Untreated HCV/HBV coinfection
HBV reactivation boxed warning. Screen all patients with HBsAg and anti-HBc. HBV-positive patients require concurrent HBV antiviral therapy. Never start sofosbuvir-based therapy without HBV screening.
Severe renal impairment (CrCl under 30 mL/min)
Updated 2019 label permits use with monitoring. Mavyret preferred by many clinicians in severe renal impairment. Specialist involvement standard in this population.
HIV coinfection with regimen conflicts
Some antiretroviral regimens interact with sofosbuvir or its companion drugs. Coordination with HIV specialists supports appropriate regimen selection.
Prior DAA treatment failure
Not a contraindication but requires attention. Resistance testing before retreatment; Vosevi is the standard salvage regimen for most DAA-experienced patients.
Post-liver transplant with immunosuppressant considerations
Not a contraindication but requires coordination with transplant team. Sofosbuvir-based regimens work well post-transplant with attention to cyclosporine and tacrolimus levels.
Pregnancy with sofosbuvir-only regimens
Limited data; typically defer treatment until after pregnancy unless clinically urgent. Not the same absolute contraindication as ribavirin-containing regimens.
Special populations reminders: pediatric patients aged 3 years and older can be treated with weight-based dosing. Elderly patients tolerate sofosbuvir well without dose adjustment. Cirrhotic patients require regimen tailoring and post-cure surveillance. Coinfection scenarios require coordinated specialist involvement.
When in doubt about appropriateness: consult with hepatology specialists. HCV treatment planning benefits from careful consideration of genotype, treatment history, fibrosis stage, coinfections, and concurrent medications. Sofosbuvir-based regimens have transformed hepatitis C care, and appropriate patient selection with attention to the specific contraindications above maximizes both safety and cure rates.
Hepcinat — Frequently Asked Questions
-
What is Hepcinat (Sovaldi)?
Hepcinat, also known by its generic name Sovaldi, is a medication containing sofosbuvir, which is used in the treatment of chronic hepatitis C. -
How Does Hepcinat Work?
Hepcinat works by inhibiting the replication of the hepatitis C virus, preventing its spread in the body and aiding in the clearance of the virus. -
Is Hepcinat a Cure for Hepatitis C?
Hepcinat, when used as part of a combination therapy, has demonstrated high cure rates for certain genotypes of hepatitis C, leading to sustained virologic response (SVR). -
What Genotypes of Hepatitis C Does Hepcinat Treat?
Hepcinat is effective against multiple genotypes of the hepatitis C virus, making it a versatile option in the treatment of the infection. -
Can Hepcinat Be Used Alone for Hepatitis C Treatment?
Hepcinat is typically used in combination with other antiviral medications for a comprehensive approach to hepatitis C treatment. -
What Should I Do If I Miss a Dose of Hepcinat?
If a dose is missed, take it as soon as you remember. If it is almost time for the next dose, skip the missed one. -
Does Hepcinat Have Common Side Effects?
Common side effects may include headache, fatigue, and nausea. These side effects are usually temporary, but consult your doctor if they persist.
See all Hepcinat questions (30)
📚 Drug Description Sources:
The information in this Hepcinat (sofosbuvir) guide is compiled from authoritative pharmaceutical, medical, and regulatory sources covering hepatitis C treatment guidelines, direct-acting antiviral development history, and evidence accumulated across more than a decade of sofosbuvir clinical practice since its transformative 2013 approval.
🏛️ Regulatory and government agencies
- FDA (US Food and Drug Administration) - Sovaldi approval December 2013 for chronic hepatitis C; subsequent approvals for combination products (Harvoni 2014, Epclusa 2016, Vosevi 2017)
- WHO (World Health Organization) - HCV elimination targets 2030; consolidated guidelines on the care and treatment of persons diagnosed with chronic hepatitis C infection; sofosbuvir on Essential Medicines List
- NIH (National Institutes of Health) - HCV treatment guidance and research funding
- EMA (European Medicines Agency) - sofosbuvir European regulatory framework
- Gilead voluntary licensing agreement - permitted Natco Pharma generic Hepcinat production for supply to 91 low- and middle-income countries
- DailyMed (NIH/NLM) - current Sovaldi prescribing information
📚 Professional societies and clinical guidelines
- American Association for the Study of Liver Diseases (AASLD) and Infectious Diseases Society of America (IDSA) - HCV Guidance jointly maintained at hcvguidelines.org, continuously updated
- European Association for the Study of the Liver (EASL) - EASL Clinical Practice Guidelines on hepatitis C treatment
- Asian Pacific Association for the Study of the Liver (APASL) - regional HCV consensus statements
- International Antiviral Society USA (IAS-USA) - HIV/HCV coinfection guidance
- British HIV Association (BHIVA) - HCV/HIV coinfection guidelines
- WHO Guidelines Development Group - global public health-oriented HCV recommendations
🔬 Landmark clinical research
- Sofia et al 2010 sofosbuvir discovery paper - Michael Sofia and Pharmasset colleagues describing PSI-7977 (later sofosbuvir) as clinical candidate
- NEUTRINO study (Lawitz 2013) - pivotal genotype 1 study with sofosbuvir + peg-interferon + ribavirin achieving 90% SVR
- FISSION, POSITRON, FUSION studies - genotype 2/3 sofosbuvir + ribavirin interferon-free trials
- ION-1, ION-2, ION-3 studies - sofosbuvir + ledipasvir (Harvoni) foundational trials
- PHOTON-1, PHOTON-2 - HCV/HIV coinfection with sofosbuvir
- VALENCE study - sofosbuvir + ribavirin for genotypes 2 and 3
- ASTRAL-1, ASTRAL-2, ASTRAL-3 - sofosbuvir + velpatasvir (Epclusa) pivotal trials
- POLARIS-1, POLARIS-2, POLARIS-3, POLARIS-4 - Vosevi (sofosbuvir + velpatasvir + voxilaprevir) trials
- ALLY-1, ALLY-2, ALLY-3 - sofosbuvir + daclatasvir combination evidence
- SOF-C-EDGE, ATOMIC, ELECTRON - early phase sofosbuvir development
📖 Medical references and textbooks
- Mandell Douglas and Bennett Principles and Practice of Infectious Diseases - hepatitis C infection and treatment
- Sherlock and Dooley Diseases of the Liver - hepatology reference
- Zakim and Boyer Hepatology - comprehensive hepatology reference
- Schiff Diseases of the Liver - clinical hepatology
- Goodman and Gilman Pharmacological Basis of Therapeutics - antiviral pharmacology
- Fields Virology - viral pathogenesis and molecular biology
- UpToDate - sofosbuvir and HCV treatment monographs
- Lexicomp and Micromedex - drug interactions and dosing
Note: This information is educational and does not replace consultation with qualified healthcare providers. HCV treatment planning requires specialist involvement, resistance considerations, and adherence to current guidelines. Always follow prescriber instructions and complete the full course of therapy for successful treatment outcomes.
🩺 Medical Expert Review:
Content based on the published research and clinical practice of hepatology and infectious disease authorities with particular expertise in hepatitis C direct-acting antiviral therapy and the transformation of HCV management since 2013. The following experts represent authoritative research and clinical practice perspectives on sofosbuvir-based treatment.
Prof. Raymond T. Chung, MD
Kevin and Polly Maroni Research Scholar; Vice Chief and Director of Hepatology, Division of Gastroenterology, Massachusetts General Hospital; Harvard Medical School — Boston, USA
Prof. Chung is an internationally recognized hepatology authority whose research on hepatitis C treatment and HIV/HCV coinfection has substantially informed AASLD-IDSA HCV Guidance. His work spans clinical trials of sofosbuvir-containing regimens, mechanisms of HCV cure, and post-cure surveillance including hepatocellular carcinoma risk assessment.
Prof. Ira M. Jacobson, MD
Director of Hepatology, NYU Langone Health; Professor of Medicine, NYU Grossman School of Medicine — New York City, USA
Prof. Jacobson is a leading investigator on foundational HCV direct-acting antiviral trials including sofosbuvir-based regimens. Past AASLD President and long-time HCV clinical trial leader, he has contributed substantially to the FDA registration studies establishing sofosbuvir efficacy across genotypes and populations including treatment-experienced and cirrhotic patients.
Prof. Stefan Zeuzem, MD
Chief of Department of Medicine I (Gastroenterology, Hepatology, Pneumology, Endocrinology), Goethe University Hospital Frankfurt — Frankfurt, Germany
Prof. Zeuzem is one of the most cited European hepatologists and a principal investigator on foundational sofosbuvir and combination direct-acting antiviral trials including VALENCE, ASTRAL, and POLARIS studies. Past EASL Governing Board member, he has substantially shaped European HCV Clinical Practice Guidelines and the strategic positioning of sofosbuvir-based regimens.
Prof. Gregory J. Dore, MBBS, PhD, MPH
Head of Viral Hepatitis Clinical Research Program, Kirby Institute, UNSW Sydney; Infectious Diseases Physician, St Vincent Hospital — Sydney, Australia
Prof. Dore is a leading authority on hepatitis C epidemiology, treatment access, and the global effort to eliminate HCV as a public health threat by 2030. His research on sofosbuvir-based treatment scale-up in people who inject drugs and other high-prevalence populations has substantially influenced global HCV public health strategy.
Prof. Graham R. Foster, FRCP, PhD
Professor of Hepatology, Barts and The London School of Medicine, Queen Mary University of London — London, UK
Prof. Foster is a leading UK hepatologist who has served as principal investigator on major sofosbuvir-based clinical trials and the UK HCV Elimination Programme lead. His research on real-world outcomes of direct-acting antiviral therapy has informed both UK NICE guidance and international HCV treatment recommendations.
Disclosure: Expert names and credentials are cited for educational reference. This content is not endorsed by named experts. Content prepared by RXshop editorial team based on published literature and clinical guidelines.
More Antiviral Medications