Buy Norcin (Norfloxacin) Online — Fluoroquinolone Antibiotic for UTI, Bacterial Gastroenteritis & SBP Prophylaxis


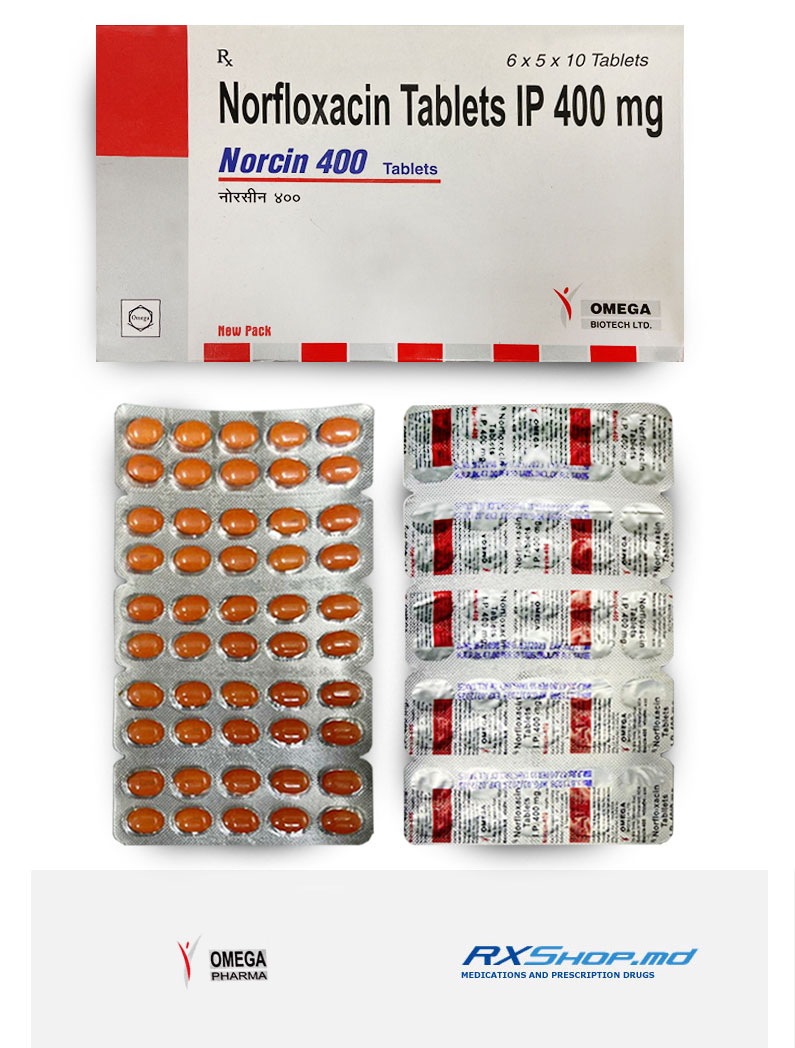
Norcin is the generic version of Norfloxacin — a fluoroquinolone antibiotic primarily used for uncomplicated urinary tract infections, bacterial gastroenteritis, and prevention of spontaneous bacterial peritonitis (SBP) in patients with cirrhosis. Originally introduced as the branded Noroxin (Merck) and FDA-approved in 1986, Norfloxacin was the first quinolone with broad-spectrum antibacterial activity to reach US clinical use. While Noroxin was withdrawn from the US market in 2014, Norcin and other Norfloxacin brands remain widely available internationally.
The active ingredient is Norfloxacin, which works through dual inhibition of bacterial enzymes essential for DNA replication: DNA gyrase (topoisomerase II) and topoisomerase IV. By blocking these enzymes, Norfloxacin prevents bacteria from unwinding and replicating their DNA, leading to bacterial cell death.
Norfloxacin has a distinctive pharmacokinetic profile that limits its clinical applications compared to other fluoroquinolones: low oral bioavailability (~30-40%), poor tissue penetration, but high urinary concentrations. These properties make Norfloxacin uniquely suited for urinary tract infections and gut-related infections, but inappropriate for systemic, respiratory, or deep tissue infections.
Norcin is used for treatment of uncomplicated urinary tract infections, recurrent UTI prophylaxis, bacterial gastroenteritis caused by Salmonella, Shigella, or E. coli, traveler's diarrhea, and as long-term prophylaxis against spontaneous bacterial peritonitis (SBP) in patients with cirrhosis and ascites — a signature unique indication where Norfloxacin's high gut and urinary concentrations are particularly advantageous.
The medication is available as 400 mg tablets. Standard adult dosing for UTI is 400 mg twice daily for 3-10 days. For SBP prophylaxis in cirrhosis, the dose is 400 mg once daily long-term.
Important boxed warnings include risk of tendinitis and tendon rupture (especially Achilles), peripheral neuropathy that can be permanent, CNS effects, aortic aneurysm/dissection, QT prolongation, and C. difficile colitis. Avoid in pregnancy and most patients under 18.
Free prescription
Discrete packaging
Have questions?
Quality Assurance

- Acute Cystitis: For acute bacterial cystitis in women caused by E. coli and other susceptible UTI pathogens;
- Cystitis Female: For female cystitis with short-course twice-daily oral therapy;
- Recurrent UTI Prophylaxis: Low-dose daily prophylaxis for recurrent UTI prevention in women;
- UTI Outpatient Twice Daily: Standard outpatient UTI therapy with twice-daily dosing for 3-10 days;
- UTI Penicillin Allergic: For UTI in penicillin-allergic patients — no β-lactam structure means no cross-reactivity;
- UTI Sulfa Allergic: For UTI in sulfa-allergic patients where Bactrim cannot be used;
- UTI Diabetic Mild: For mild uncomplicated UTI in stable diabetic patients;
- E Coli UTI: For UTI caused by susceptible E. coli — most common urinary pathogen;
- Pyelonephritis Selective: Selective use in pyelonephritis in regions with low resistance — not preferred over Cipro;
- Spontaneous Bacterial Peritonitis Prophylaxis: Long-term prophylaxis against SBP in cirrhotic patients with ascites — signature unique indication;
- SBP Secondary Prevention: For secondary SBP prevention following first SBP episode in cirrhotic patients;
- Cirrhosis Ascites Prophylaxis: For long-term antibiotic prophylaxis in high-risk cirrhotic patients with refractory ascites;
- Bacterial Gastroenteritis: For bacterial gastroenteritis caused by susceptible Salmonella, Shigella, or E. coli;
- Bacterial Gastritis: For selected severe bacterial gastritis cases requiring antibiotic therapy;
- Traveler Diarrhea: Alternative for moderate-severe bacterial traveler's diarrhea caused by E. coli;
- Salmonella Selective: Selective use for severe Salmonella gastroenteritis — not routine due to resistance;
- Shigellosis: For Shigella dysentery caused by susceptible organisms;
- Acute Prostatitis Selective: Selective use for acute prostatitis — less preferred than Cipro due to poorer tissue penetration;
- Gonorrhea Historical: Historical use for gonorrhea — widespread resistance now limits this indication;
- Bacterial Conjunctivitis Chibroxin: Chibroxin ophthalmic solution for bacterial conjunctivitis;
- Catheter Associated UTI Selective: Selective use for catheter-associated UTI in selected patients with susceptible organisms.
- Less Urinary Urgency: Resolution of frequent urination and urgency as UTI clears;
- Better Bladder Comfort: Restoration of normal bladder function as cystitis resolves;
- Less Pelvic Discomfort: Resolution of pelvic discomfort associated with cystitis;
- Less Diarrhea: Resolution of bacterial gastroenteritis and traveler's diarrhea;
- Less Abdominal Pain: Resolution of cramping abdominal pain in bacterial gastroenteritis;
- Less Ascites Infection: Long-term SBP prophylaxis prevents life-threatening peritonitis in cirrhotic patients;
- Better Liver Outcomes: SBP prophylaxis improves overall survival in advanced cirrhosis with ascites;
- Less Fever: Resolution of fever as UTI or gastroenteritis responds to therapy;
- Better Energy: Recovery from systemic infection-related fatigue;
- Better Sleep: Resolution of nighttime urinary symptoms during recovery;
- Faster Recovery: Most UTI patients show clinical improvement within 48-72 hours;
- Better Daily Function: Return to work and normal activities;
- Brand Norcin: Affordable Indian generic Norfloxacin with international quality manufacturing standards;
- Generic Norfloxacin: Affordable generic Norfloxacin expanding global access to fluoroquinolone UTI therapy;
- Noroxin Equivalent: Same Norfloxacin molecule as original Merck brand Noroxin (withdrawn from US market in 2014);
- Utinor Equivalent: Same Norfloxacin molecule as international Utinor brand — widely used in international markets;
- Chibroxin Ophthalmic: Chibroxin ophthalmic 0.3% solution for bacterial conjunctivitis;
- Fluoroquinolone Antibiotic: Original generation fluoroquinolone class antibiotic with established mechanism;
- DNA Gyrase Inhibitor: Inhibits bacterial DNA gyrase essential for DNA supercoiling and replication;
- Topoisomerase IV Inhibitor: Dual-enzyme target reduces resistance development compared to single-target antibiotics;
- High Urinary Concentration FQ: Very high urinary concentrations support effective UTI therapy — uniquely urine-focused;
- Low Oral Bioavailability FQ: ~30-40% oral bioavailability limits systemic use but supports gut-focused therapy;
- Gut Focused FQ: Low absorption supports use in gut-related infections and SBP prophylaxis from intestinal sources;
- SBP Prophylaxis Standard: Standard long-term prophylaxis against spontaneous bacterial peritonitis in cirrhotic patients;
- Cirrhosis Antibiotic Standard: Standard antibiotic prophylaxis in advanced liver disease with refractory ascites;
- UTI Outpatient Therapy: Standard outpatient UTI therapy for adult women with susceptible organisms;
- Twice Daily UTI: Twice-daily dosing supports outpatient UTI therapy in adults;
- Penicillin Allergic UTI: Alternative for UTI in penicillin-allergic patients — no cross-reactivity;
- Sulfa Allergic UTI: Alternative for UTI in sulfa-allergic patients where Bactrim cannot be used;
- WHO Essential Medicine: Listed on the WHO Model List of Essential Medicines for SBP prophylaxis in cirrhosis;
- 35 Plus Year Antibiotic History: Extensive real-world safety and efficacy data since 1986 across decades of clinical use;
- Affordable UTI Therapy: Cost-effective generic UTI therapy globally — supports access in resource-limited settings;
- Avoid In Pregnancy: Contraindicated in pregnancy due to potential cartilage toxicity;
- Avoid Under 18: Generally contraindicated in pediatric patients except for specific approved indications;
- Tendinopathy Risk: Boxed warning for tendinitis and tendon rupture — especially Achilles tendon;
- Aortic Aneurysm Warning: FDA warning for aortic aneurysm and dissection — avoid in high-risk patients;
- Avoid With Antacids: Antacids and mineral supplements (Ca, Mg, Al, Fe, Zn) reduce absorption significantly;
- Take Empty Stomach: Take on empty stomach (1 hour before or 2 hours after meals) for best absorption;
- QT Monitoring: Avoid in patients with QT prolongation risk or on QT-prolonging medications;
- Stable Storage: Tablets stable at room temperature — convenient for home and travel use;
- Globally Available: Widely supplied in international markets (Norcin India, Noroxin retired US, Utinor, Negaflox).
Generic Norcin (Norfloxacin 400 mg) Medication guide:
📖 What is Norcin and where norfloxacin fits in modern practice
Norcin is a Cipla brand of norfloxacin, a second-generation fluoroquinolone antibiotic. Norfloxacin was the first oral fluoroquinolone approved by the FDA in 1986 as Noroxin. Merck discontinued the Noroxin brand in 2014, but generic norfloxacin including the Norcin brand remains widely available internationally.
🔑 Key facts at a glance
- Class: second-generation fluoroquinolone (first oral fluoroquinolone approved)
- Mechanism: DNA gyrase and topoisomerase IV inhibition, bactericidal
- Standard dose: 400 mg twice daily
- Half-life: 3 to 4 hours
- Excretion: mainly renal — concentrated in urine, poor tissue penetration elsewhere
- Main use: uncomplicated urinary tract infection and chronic prostatitis
- Pregnancy: Category C — avoid
⚠️ FDA BLACK BOX WARNINGS
Norfloxacin shares the fluoroquinolone class BLACK BOX WARNINGS:
- Tendon rupture and tendinitis
- Peripheral neuropathy (can be irreversible)
- Central nervous system effects (seizures, psychosis, delirium)
- Exacerbation of myasthenia gravis
- Aortic aneurysm and dissection (FDA 2018)
- Hypoglycemia (FDA 2018)
- Mental health effects (FDA 2018)
🧪 Where norfloxacin fits in modern practice
Because of the growing safety concerns with fluoroquinolone class use, the FDA 2016 Safety Communication restricts fluoroquinolone use for uncomplicated urinary tract infection to situations where alternative agents cannot be used. This has substantially narrowed norfloxacin's modern role. Norfloxacin has additional practical limits: its poor tissue penetration makes it unsuitable for pyelonephritis or systemic infections despite its fluoroquinolone class membership.
✅ Where norfloxacin still fits
Complicated urinary tract infection or acute cystitis where alternative agents cannot be used, chronic bacterial prostatitis where the fluoroquinolone class remains standard, and specific niche uses in developing world settings where other options are limited. Its role is narrower than when it was first approved, but focused urinary use remains legitimate.
🕑 History: 1986 approval as the first oral fluoroquinolone
Norfloxacin was developed by Kyorin Pharmaceutical (Japan) and Merck Sharp and Dohme in the early 1980s. It became the first oral fluoroquinolone approved by the FDA in October 1986. Its approval opened the modern era of oral fluoroquinolone therapy that has shaped antibiotic prescribing ever since.
| Year | Milestone |
|---|---|
| Early 1980s | Kyorin Pharmaceutical Japan and Merck develop norfloxacin as the first orally absorbable fluoroquinolone |
| October 1986 | FDA approves Noroxin for uncomplicated urinary tract infection — first oral fluoroquinolone |
| Late 1980s | Norfloxacin becomes widely used for UTI, gonorrhea, and travelers diarrhea worldwide |
| Late 1980s to 1990s | Ciprofloxacin (1987) and other newer fluoroquinolones with better tissue penetration replace norfloxacin for systemic infections |
| 1990s | Rising gonococcal resistance leads to abandonment of fluoroquinolones for gonorrhea |
| July 2008 | FDA BLACK BOX WARNING for tendon rupture across fluoroquinolone class |
| August 2013 | FDA BLACK BOX WARNING update for peripheral neuropathy |
| 2014 | Merck discontinues Noroxin brand in the US market |
| May 2016 | FDA restricts fluoroquinolone use for uncomplicated UTI, sinusitis, and bronchitis when alternatives available |
| 2018 | FDA hypoglycemia, mental health, and aortic aneurysm safety communications |
| Present | Generic norfloxacin remains available internationally through Cipla Norcin brand and other manufacturers |
🧪 A 40-year arc from breakthrough to reserved agent
Norfloxacin was a genuine breakthrough in 1986 — the first fluoroquinolone that could be taken by mouth for outpatient use. It rapidly became one of the most-prescribed antibiotics globally. Over the following decades, newer fluoroquinolones with better tissue penetration (ciprofloxacin, ofloxacin, levofloxacin) largely replaced it for most systemic uses. Modern safety concerns then further restricted the entire class. Today norfloxacin occupies a narrower urinary-focused role, though its low cost and widespread availability keep it valuable in international markets.
⚙️ Mechanism: DNA gyrase and topoisomerase IV inhibition
Norfloxacin works by blocking bacterial DNA replication. It inhibits two essential bacterial enzymes: DNA gyrase and topoisomerase IV. Both are needed to unwind and manage bacterial DNA during cell division. When both are blocked, bacteria cannot copy their DNA and die.
🧬 The dual-target mechanism
- DNA gyrase (topoisomerase II)
- Main target in gram-negative bacteria. Introduces negative supercoils in DNA so it can be unwound during replication. Blocking this enzyme traps DNA-gyrase complex and creates lethal DNA breaks.
- Topoisomerase IV
- Main target in gram-positive bacteria. Separates linked daughter chromosomes at end of DNA replication. Blocking this prevents proper chromosome segregation.
- Bactericidal action
- Trapped enzyme-DNA-drug complexes create lethal double-strand DNA breaks. Bacterial death is rapid.
🔬 Concentration-dependent killing
Fluoroquinolone effectiveness is concentration-dependent. Higher peak concentrations of the drug produce more effective bacterial killing. This is why fluoroquinolones are dosed less frequently at higher doses rather than more frequently at lower doses. In the urine, norfloxacin achieves extremely high concentrations that reliably kill susceptible uropathogens.
🔴 How bacterial resistance develops
- Chromosomal target mutations
- Point mutations in gyrA, gyrB, parC, parE genes reduce drug binding to DNA gyrase or topoisomerase IV. Stepwise mutations increase resistance level.
- Efflux pumps
- Bacteria upregulate pumps that push fluoroquinolones out of the cell before they can act. Common in Enterobacteriaceae.
- Plasmid-mediated resistance
- Qnr proteins protect DNA gyrase from fluoroquinolone binding. Can spread between bacterial species. Increasingly common globally.
- Porin loss
- Gram-negative bacteria lose outer membrane porins that fluoroquinolones use to enter cells.
📈 Resistance trends
Community E. coli fluoroquinolone resistance now exceeds 20 to 30 percent in many US and international regions. This has driven the modern restrictions on empirical fluoroquinolone use for uncomplicated UTI. Local susceptibility data should inform norfloxacin prescribing.
🧬 Norfloxacin among the fluoroquinolone generations
The fluoroquinolone class has been developed across multiple generations, each adding features but also complications. Understanding where norfloxacin fits helps clarify why newer options have often displaced it.
| Generation | Examples | Distinctive features |
|---|---|---|
| First (quinolone) | Nalidixic acid | Narrow gram-negative activity; UTI only; largely historical |
| Second | Norfloxacin, ciprofloxacin, ofloxacin | Broader gram-negative activity; UTI, GI, some systemic use |
| Third (respiratory) | Levofloxacin, moxifloxacin, gemifloxacin | Added pneumococcal and atypical respiratory coverage |
| Fourth | Trovafloxacin (withdrawn), gatifloxacin (restricted) | Broad including anaerobes; most withdrawn for safety |
🔗 Where norfloxacin sits within the class
- Second generation: broader than nalidixic acid but narrower than later options
- Concentrated in urine: makes it excellent for UTI, poor for systemic infection
- Poor tissue penetration: cannot treat pyelonephritis or systemic infection
- Twice daily dosing (vs newer options that are often once daily)
- Was displaced by ciprofloxacin (better tissue penetration) for most non-UTI uses
- Lower cost keeps it useful in international markets for UTI
🔴 What each generation lost
The fluoroquinolone development history contains multiple withdrawn or restricted agents: temafloxacin (1992 — hemolytic anemia), trovafloxacin (1999 — hepatotoxicity), grepafloxacin (1999 — QT prolongation), gatifloxacin (2006 — hypoglycemia). This history informs the current cautious framework applied to all surviving members of the class including norfloxacin.
🦠 Focused urinary tract activity spectrum
Norfloxacin has a focused gram-negative spectrum that works well for urinary infections but limited for most other bacterial diseases. Its narrower spectrum than newer fluoroquinolones reflects its second-generation origin.
✅ Reliable coverage (when susceptibility confirmed)
- Escherichia coli — the main urinary pathogen
- Klebsiella pneumoniae
- Proteus mirabilis and other Proteus species
- Enterobacter species
- Citrobacter species
- Pseudomonas aeruginosa (moderate activity; rising resistance)
- Neisseria gonorrhoeae (historically; now largely resistant globally)
- Salmonella and Shigella (variable susceptibility)
- Campylobacter jejuni (rising resistance in Asia)
⛔ Poor or no coverage
- Streptococcus pneumoniae — unreliable
- Streptococcal species generally — do not use
- Staphylococcus aureus — unreliable coverage
- Enterococcus faecalis — unreliable
- Enterococcus faecium — unreliable
- Anaerobic bacteria including Bacteroides fragilis
- Atypical intracellular pathogens like Mycoplasma pneumoniae, Legionella pneumophila
- Chlamydia species — poor coverage compared with newer FQs
- Extended-spectrum beta-lactamase producers — increasing co-resistance
- Multi-drug resistant Enterobacteriaceae
🧪 The urinary focus
Norfloxacin's gram-negative activity fits the typical uropathogens (E. coli, Klebsiella, Proteus). This is why it works well for urinary tract infection when the pathogen is susceptible. Its poor tissue penetration means that even for these same organisms, norfloxacin cannot treat pyelonephritis (kidney parenchymal infection) or bacteremia from urinary sources. This limits its role to lower urinary tract infection where high urine concentrations do the work.
📈 Rising resistance restricts empirical use
Community E. coli fluoroquinolone resistance now exceeds 20 to 30 percent in many US and international regions. This means empirical norfloxacin without culture guidance may fail in a substantial fraction of cases. Where local resistance rates are known to exceed 10 percent, alternatives are preferred for empirical treatment.
💉 Concentrated in urine with poor tissue penetration
Norfloxacin's pharmacokinetic profile is its defining feature. It is concentrated in urine at very high levels while achieving only low levels in blood and tissues. This combination explains both its urinary utility and its limitations.
| Feature | Value |
|---|---|
| Oral bioavailability | 30 to 40 percent (lower than newer FQs) |
| Food effect | Take on empty stomach (1 hour before or 2 hours after meals) |
| Time to peak blood level | 1 to 2 hours |
| Serum peak (400 mg dose) | 1 to 2 mcg/mL — relatively low |
| Urine concentration | 100 to 400 mcg/mL — far above serum |
| Protein binding | 10 to 15 percent (low) |
| Half-life (normal kidney function) | 3 to 4 hours |
| Renal excretion | 30 percent unchanged in urine |
| Biliary excretion | Some biliary excretion (contributes to intestinal levels) |
🌐 Where norfloxacin does and does not reach
- Urine (bladder)
- Very high concentrations — foundation of UTI efficacy
- Prostate tissue
- Adequate concentrations — supports prostatitis role
- Intestine (from biliary excretion)
- Adequate for gastrointestinal infection when appropriate
- Kidney parenchyma
- Poor — not usable for pyelonephritis
- Lung tissue
- Poor — not usable for pneumonia
- Skin and soft tissue
- Poor — not usable for skin infection
- Cerebrospinal fluid
- Very poor — not usable for meningitis
- Bone
- Poor — not usable for osteomyelitis
💧 Why kidney function matters
Because norfloxacin depends on renal excretion to concentrate the drug in urine, patients with impaired kidney function cannot achieve therapeutic urinary levels. This makes norfloxacin ineffective in advanced kidney disease. Dose adjustment is required for moderate impairment; severe impairment may make norfloxacin unusable.
🏥 FDA-approved indications
Norfloxacin's original FDA indications were relatively broad by 1986 standards. The 2016 FDA restriction on fluoroquinolone use has substantially narrowed practical use.
🎯 Original FDA-approved indications
- Uncomplicated urinary tract infection caused by susceptible E. coli, Klebsiella, Proteus, and other uropathogens
- Complicated urinary tract infection in adults with susceptible organisms
- Chronic bacterial prostatitis due to susceptible E. coli, Enterococcus (with reservations)
- Uncomplicated gonococcal urethritis (historical; no longer recommended)
⛔ FDA 2016 restriction position
The FDA advises AGAINST using fluoroquinolones for uncomplicated urinary tract infection when other options are available. This substantially limits empirical norfloxacin use.
Preferred alternatives for uncomplicated UTI: nitrofurantoin, TMP-SMX, fosfomycin. Only where these cannot be used should fluoroquinolones (including norfloxacin) be considered.
🩹 Where norfloxacin is currently reasonable
- Chronic bacterial prostatitis (still fluoroquinolone-class standard)
- Complicated cystitis in susceptibility-confirmed cases
- Cystitis where sulfa allergy, previous nitrofurantoin adverse event, or fosfomycin unavailable
- Bacterial travelers diarrhea (declining role due to resistance)
- Specific niche uses in developing world settings
⛔ NOT indicated for
- Pyelonephritis (kidney tissue not adequately penetrated)
- Any respiratory tract infection
- Skin or soft tissue infection
- Bone or joint infection
- Gonorrhea (widespread resistance)
- Any bacteremia or systemic infection (poor blood levels)
- Meningitis (poor CSF penetration)
- Empirical use where susceptibility unknown and safer alternatives exist
🚻 Uncomplicated urinary tract infection role
Uncomplicated urinary tract infection (cystitis) was norfloxacin's original main indication. The 2016 FDA restriction has substantially changed practice, positioning norfloxacin as a reserve option rather than first-line for uncomplicated UTI.
🎯 Definition of uncomplicated cystitis
- Non-pregnant woman with normal urinary tract
- No structural abnormality, catheter, or recent instrumentation
- Normal kidney function
- Dysuria, frequency, urgency, suprapubic discomfort
- No fever, flank pain, or systemic symptoms (which suggest pyelonephritis)
| Uncomplicated cystitis options | Priority under 2016 restriction |
|---|---|
| Nitrofurantoin 100 mg BID for 5 days | First-line |
| TMP-SMX DS BID for 3 days | First-line if regional resistance under 20 percent |
| Fosfomycin 3 g single dose | First-line alternative |
| Cephalexin or amoxicillin | Alternative when susceptibility confirmed |
| Norfloxacin 400 mg BID for 3 days | Reserve only when alternatives unsuitable |
📋 When norfloxacin may still be appropriate for cystitis
- Prior nitrofurantoin severe adverse effect
- Sulfa allergy plus fosfomycin unavailable
- Kidney impairment ruling out nitrofurantoin
- Susceptibility-confirmed norfloxacin coverage
- Regional resistance data supports fluoroquinolone use
- Patient factors where alternatives clearly unsafe or ineffective
⚠️ Not to be used for pyelonephritis
Norfloxacin's poor kidney tissue penetration makes it unsuitable for pyelonephritis, even though ciprofloxacin and levofloxacin work well. If cystitis symptoms include flank pain, fever, or systemic signs suggesting pyelonephritis, norfloxacin is not appropriate. Alternative agents (ceftriaxone IV, oral ciprofloxacin, or others) must be used.
🔴 Complicated urinary tract infection considerations
Complicated urinary tract infection includes cystitis with structural abnormalities, catheters, kidney or ureteral disease, or in male patients. Norfloxacin has a role in complicated cystitis but not in complicated infection with tissue involvement.
👤 What complicated UTI means
- Structural abnormality of the urinary tract
- Indwelling urinary catheter
- Recent urologic instrumentation
- Kidney disease
- Diabetic patient with poor glycemic control
- Male UTI (often has prostatic involvement)
- Immunosuppressed patient
- Pregnant patient (has its own guidelines; norfloxacin not appropriate)
- Elderly with multiple comorbidities
| Complicated UTI scenario | Norfloxacin role |
|---|---|
| Complicated cystitis without tissue involvement | Acceptable when susceptibility confirmed |
| Complicated UTI with pyelonephritis | NOT appropriate — poor tissue penetration |
| Catheter-associated UTI with systemic symptoms | Consider alternative agent with better tissue penetration |
| Male UTI with prostatic involvement | Norfloxacin acceptable given prostate penetration |
| Recurrent cystitis in patient with anatomic abnormality | Consider based on susceptibility |
| Cystitis after failure of first-line agents | Culture-guided; norfloxacin acceptable if susceptible |
📋 Culture-guided prescribing is essential
For any complicated UTI, urine culture and susceptibility testing should guide therapy. Empirical norfloxacin should not be used for complicated infection because of the risk of resistance and treatment failure. When culture confirms norfloxacin activity, it becomes a reasonable oral option for a limited role.
⚠️ When to escalate
Any complicated UTI with fever, flank pain, sepsis physiology, or worsening on oral therapy needs hospitalisation and IV therapy. Ceftriaxone IV is typical first-line for hospital-treated complicated UTI or pyelonephritis. Norfloxacin has no role in these settings.
🍃 Chronic bacterial prostatitis
Chronic bacterial prostatitis is one of norfloxacin's continuing legitimate niches. The prostate is difficult for most antibiotics to reach adequately, and fluoroquinolones including norfloxacin have good prostate tissue penetration relative to alternatives.
| Chronic prostatitis regimen | Details |
|---|---|
| Standard dosing | 400 mg PO twice daily for 4 to 6 weeks |
| Alternative | TMP-SMX 6 to 12 weeks (if susceptible) |
| Failure or recurrence | Consider ciprofloxacin or levofloxacin |
| Confirmed enterococcal prostatitis | Amoxicillin preferred over norfloxacin |
🔬 Why fluoroquinolones fit prostate infection
- Prostate tissue is difficult for most antibiotics due to a physical barrier
- Fluoroquinolones cross this barrier and achieve tissue concentrations near serum levels
- Norfloxacin achieves adequate prostate concentrations for chronic bacterial prostatitis
- Excellent oral bioavailability for outpatient treatment over weeks
- Twice daily dosing feasible for 4 to 6 week courses
⚠️ Extended course amplifies fluoroquinolone risks
- 4 to 6 week courses substantially increase cumulative tendon rupture risk
- Aortic aneurysm concern for older men on prolonged treatment
- Peripheral neuropathy risk with long exposure
- CNS effects concern with cumulative exposure
- QT prolongation risk in patients with cardiac disease
📋 Prescribing framework for prostatitis
- Confirm diagnosis with Meares-Stamey 4-glass or 2-glass test
- Culture-guided drug selection
- Discuss fluoroquinolone risks with patient explicitly
- Screen for tendon history, aortic disease, cardiac issues, mental health history
- Adequate hydration and rest during treatment
- Warning about tendon pain and other class-specific symptoms
🌍 Traveler diarrhea and gastrointestinal infections
Norfloxacin has been used for treating and preventing bacterial travelers diarrhea. However, rising resistance in target organisms (particularly Campylobacter in Asia) has substantially reduced its effectiveness in many regions. Azithromycin has replaced fluoroquinolones as first-line in most guidance.
🌍 Bacterial causes of travelers diarrhea
- Enterotoxigenic E. coli — most common cause; fluoroquinolone-susceptible in many regions
- Shigella species — rising resistance
- Campylobacter jejuni — substantial resistance in Asia (Thailand, India, Nepal)
- Salmonella species — variable susceptibility
- Vibrio species
| Region of travel | Preferred agent |
|---|---|
| South and Southeast Asia | Azithromycin preferred (Campylobacter resistance to FQ) |
| Middle East, Africa | Norfloxacin or ciprofloxacin acceptable |
| Latin America | Norfloxacin or ciprofloxacin acceptable |
| Uncomplicated mild cases | Rehydration only; loperamide for symptomatic relief |
📋 Standard treatment dosing
- Norfloxacin 400 mg twice daily for 1 to 3 days
- Alternative: single 800 mg dose in mild cases
- Reserved for moderate to severe diarrhea (four or more loose stools per day, or dysentery)
- Not for very mild cases where rehydration is sufficient
⛔ Prophylactic use largely discouraged
Routine antibiotic prophylaxis for travelers diarrhea is no longer recommended by most travel medicine authorities. Antibiotic use for a self-limited illness selects for resistant bacteria without proportional benefit. Bismuth subsalicylate (Pepto-Bismol) may reduce risk. Norfloxacin prophylaxis is limited to specific situations like short trips with critical schedules where any diarrhea would be devastating, and even then it is debated.
🧪 Modern travel counselling
Travel medicine practice increasingly emphasises food and water safety education, rehydration therapy, and reserved antibiotic use rather than prophylactic antibiotic distribution. Travelers may carry azithromycin or ciprofloxacin (rather than norfloxacin) for self-treatment of moderate to severe diarrhea should it develop.
🛑 Gonorrhea: the historical use now abandoned
Norfloxacin was widely used for uncomplicated gonorrhea in the late 1980s and 1990s. Rising Neisseria gonorrhoeae resistance to fluoroquinolones led to the abandonment of this indication by the mid-2000s. Fluoroquinolones are no longer recommended for gonorrhea treatment.
⛔ Why fluoroquinolones were abandoned for gonorrhea
- Neisseria gonorrhoeae resistance rose rapidly from 1990s onward
- By 2007, CDC declared fluoroquinolones no longer recommended for gonorrhea in the US
- By 2010, global guidelines followed similarly
- Treatment failure with fluoroquinolones exceeds 5 to 10 percent in most regions
- Alternative drugs (ceftriaxone) remain reliable
✅ Current recommended treatment for uncomplicated gonorrhea
- Ceftriaxone 500 mg intramuscular single dose (CDC 2020 update)
- Higher doses (1 g IM) in some regions with rising ceftriaxone MICs
- Consider concurrent doxycycline or azithromycin for possible chlamydia co-infection
- Test-of-cure not usually required for uncomplicated cases
- Sexual partner notification and treatment
🧪 Antimicrobial resistance in gonorrhea
Neisseria gonorrhoeae has developed resistance to essentially every antibiotic class used against it historically: sulfonamides, penicillins, tetracyclines, fluoroquinolones, and now increasingly to ceftriaxone. This creates ongoing pressure to develop new agents and to use existing ones judiciously. Norfloxacin's abandonment for gonorrhea is a cautionary tale about how rapidly bacterial resistance can end a formerly effective indication.
📋 Historical context
The gonorrhea story is not the only fluoroquinolone indication lost to resistance. Similar patterns have unfolded for shigellosis in many regions, typhoid fever in South Asia, and community UTI. Fluoroquinolone-focused stewardship attempts to preserve remaining effectiveness by narrowing use to situations where these agents genuinely add value.
💊 Adult dosing: 400 mg twice daily
Standard adult dosing for Norcin is 400 mg twice daily. Course length depends on the indication: 3 days for uncomplicated cystitis, 7 to 10 days for complicated UTI, 4 to 6 weeks for chronic prostatitis.
| Indication | Dose | Duration |
|---|---|---|
| Uncomplicated cystitis | 400 mg twice daily | 3 days |
| Complicated cystitis | 400 mg twice daily | 7 to 10 days |
| Chronic bacterial prostatitis | 400 mg twice daily | 4 to 6 weeks |
| Bacterial travelers diarrhea | 400 mg twice daily | 1 to 3 days |
🍴 How to take Norcin correctly
- Take on an empty stomach — 1 hour before or 2 hours after meals
- Take with a full glass of water
- Drink plenty of fluids during the course to reduce crystalluria risk
- Take doses about 12 hours apart (morning and evening)
- Take at least 2 hours before or 2 hours after antacids, iron, calcium, zinc supplements, or dairy products
- Complete the full course even if symptoms improve
- Do not exceed the prescribed dose
⚠️ Warning signs during treatment
- Tendon pain or swelling — especially Achilles — stop drug and rest
- Numbness, tingling, burning in hands or feet
- Sudden severe chest, back, or belly pain — emergency care
- Confusion, hallucinations, unusual thoughts, suicidal thoughts
- Palpitations, dizziness, fainting
- Muscle weakness (myasthenia gravis exacerbation)
- Severe or bloody diarrhea, fever
- Yellow skin or eyes, dark urine
- Low blood sugar symptoms in diabetic patients
- Extensive rash, blistering, mouth sores
- Sudden vision changes or floaters
🔬 Renal impairment: dose adjustment required
Norfloxacin depends on renal excretion to concentrate in urine. Kidney impairment reduces urinary concentrations while raising blood levels, which increases the risk of adverse effects. Dose adjustment is essential.
| Kidney function (CrCl) | Dose adjustment |
|---|---|
| Above 30 mL/min | Standard dose: 400 mg twice daily |
| 10 to 30 mL/min | 400 mg once daily (extend interval) |
| Below 10 mL/min | 400 mg once daily; consider alternative agent |
| Dialysis | 400 mg once daily; poorly cleared by dialysis |
| Mild liver impairment | No adjustment needed |
| Severe liver impairment | Use caution; monitor |
🔴 Why accumulation matters
When norfloxacin accumulates in the blood due to kidney impairment:
- Higher blood levels increase CNS effects (confusion, tremor, seizure risk)
- Increased QT prolongation risk
- Higher tendon rupture risk
- Higher peripheral neuropathy risk
- Higher hypoglycemia risk in diabetic patients
📋 Practical framework
- Every patient starting Norcin needs kidney function assessment
- Estimate creatinine clearance by Cockcroft-Gault formula in adults over 65
- Age-related kidney function decline often unrecognized
- Adjust dosing interval as shown above
- Consider alternative UTI treatment (nitrofurantoin cannot be used in severe kidney impairment, but is preferred for mild)
- Repeat kidney function testing for extended courses (prostatitis)
🟡 The kidney function decline in the elderly
Age-related kidney function decline is common but often not obvious from creatinine alone. A creatinine of 1.0 mg/dL in a healthy 30-year-old means normal function; in an 85-year-old woman with low muscle mass, the same value may correspond to a clearance of 30 to 40 mL/min. Calculating estimated clearance before every fluoroquinolone prescription in adults over 65 is prudent.
💥 Drug interactions: chelation, warfarin, and QT
Norfloxacin has several important drug interactions. Understanding these helps prevent treatment failure and dangerous adverse effects.
🔴 Chelation interactions — absorption destroyed
These cations bind norfloxacin in the gut and prevent absorption. Space at least 2 hours before or 2 hours after:
- Antacids containing aluminum, magnesium, or calcium
- Iron supplements (ferrous sulfate, ferrous gluconate)
- Calcium supplements and dairy products (milk, yogurt, cheese)
- Zinc supplements and multivitamins with minerals
- Sucralfate
- Bismuth-containing products (Pepto-Bismol)
💓 QT prolongation interactions
Concurrent use with other QT-prolonging drugs additively increases torsades risk. Consider alternative or ECG monitoring for:
- Class IA antiarrhythmics: quinidine, procainamide, disopyramide
- Class III antiarrhythmics: amiodarone, sotalol, dofetilide, dronedarone
- Macrolide antibiotics: azithromycin, erythromycin, clarithromycin
- Antipsychotics: haloperidol, ziprasidone, thioridazine, chlorpromazine
- Citalopram, escitalopram at high doses
- Antifungals: fluconazole (dose-dependent), voriconazole
- Ondansetron, methadone
| Other important interaction | Effect and management |
|---|---|
| Warfarin | May increase INR; monitor day 3 to 5 during and after therapy |
| NSAIDs | Additive CNS excitation, seizure risk; avoid combined use |
| Insulin, sulfonylureas | Hypoglycemia risk; monitor blood glucose closely |
| Corticosteroids | Amplified tendon rupture risk; avoid if possible |
| Theophylline | Increased theophylline levels; monitor and reduce theophylline dose |
| Cyclosporine | Elevated cyclosporine levels; monitor |
| Probenecid | Reduces norfloxacin renal excretion; monitor for toxicity |
| Nitrofurantoin | Antagonism at bacterial level; do not combine |
🧪 Practical framework
Review medication list before every norfloxacin prescription. Screen especially for QT-prolonging drugs, warfarin, NSAIDs, and hypoglycemic agents. For patients on multiple interacting medications, consider whether an alternative antibiotic would be safer than adjusting the medication regimen.
🤰 Pregnancy category C and lactation
Norfloxacin is FDA Pregnancy Category C and generally avoided during pregnancy. Fluoroquinolones cause cartilage lesions in animal studies. Human pregnancy data are more reassuring but do not support routine use.
⛔ Pregnancy avoidance
- Category C based on animal cartilage effects
- Crosses the placenta at low concentrations
- Alternative safer agents exist for essentially all pregnancy indications
- Use only for life-threatening infections when no acceptable alternative is available
| Pregnancy indication | Preferred alternative |
|---|---|
| Cystitis in pregnancy | Nitrofurantoin (up to 36 weeks) or beta-lactam |
| Pyelonephritis | IV ceftriaxone or ampicillin-gentamicin (norfloxacin ineffective anyway) |
| Asymptomatic bacteriuria in pregnancy | Nitrofurantoin, amoxicillin, or fosfomycin |
| Complicated UTI in pregnancy | Susceptibility-guided IV therapy |
👶 Lactation
Norfloxacin passes into breast milk in low concentrations. Short courses may be acceptable with infant monitoring. Extended courses are best avoided during breastfeeding. LactMed lists fluoroquinolones as one class where safer alternatives should be preferred for nursing mothers when possible.
👩 Planning pregnancy
Women planning pregnancy should switch to an alternative agent before conceiving. Women who become pregnant while on norfloxacin should discuss with obstetrician; the exposure is unlikely to have caused harm at typical doses but ongoing use should transition to a safer alternative.
🤔 Common adverse effects
Norfloxacin common side effects overlap with other fluoroquinolones. Most are mild and manageable at standard doses.
| Side effect | How often | What to do |
|---|---|---|
| Nausea | 3 to 5 percent | Take with plenty of water; usually mild |
| Diarrhea | 2 to 4 percent | Hydration; watch for CDI signs (see section 20) |
| Headache | 3 to 6 percent | Usually mild; self-limited |
| Dizziness | 2 to 4 percent | Fall precautions; may signal CNS effect |
| Insomnia | 2 to 4 percent | Take earlier in day; may signal CNS effect |
| Anxiety, restlessness | 1 to 3 percent | Report to prescriber |
| Vaginal candidiasis | 2 to 4 percent (women) | Topical azole or oral fluconazole |
| Rash | 1 to 3 percent | Stop and evaluate if extensive |
| Photosensitivity | 1 to 3 percent | Sun protection (see section 21) |
| Crystalluria (crystals in urine) | Uncommon with adequate fluid intake | Drink plenty of water throughout course |
⚠️ Symptoms warranting immediate discontinuation
- Tendon pain or swelling, especially Achilles
- Numbness, tingling, burning in extremities
- Confusion, hallucinations, unusual thoughts, suicidal thoughts
- Sudden severe chest, back, or belly pain
- Palpitations, dizziness, fainting
- Extensive rash, especially with fever or blistering
- Severe or bloody diarrhea (CDI concern)
- Muscle weakness or breathing difficulty (myasthenia)
- Yellow skin or eyes, dark urine
- Symptoms of low blood sugar in diabetic patients
- Sudden vision changes or floaters
🔗 Norcin versus other brands and Noroxin discontinuation
Multiple manufacturers produce generic norfloxacin internationally. The original Merck brand Noroxin was discontinued in 2014, but Cipla Norcin and other generic brands remain widely available.
| Brand | Manufacturer | Status |
|---|---|---|
| Norcin | Cipla | Active in international markets |
| Noroxin | Merck (originally) | Discontinued 2014 in US |
| Utinor | Various | International market brand |
| Chibroxin | Various | European market brand |
| Norfloxacin generic | Multiple international manufacturers | Widely available |
🔗 Why Noroxin was discontinued
Merck discontinued the Noroxin brand in the US in 2014 because of declining use as newer fluoroquinolones (ciprofloxacin, levofloxacin) captured most systemic infection indications. Rising community fluoroquinolone resistance and safety concerns further reduced norfloxacin use. The discontinuation was a business decision reflecting reduced demand, not a safety recall. Generic norfloxacin remained available through other manufacturers.
🌐 Cipla Norcin
Cipla is one of the largest Indian pharmaceutical manufacturers with a strong international generic portfolio. Norcin is their norfloxacin brand, widely distributed to international markets where norfloxacin remains commonly prescribed for UTI and prostatitis. Cipla-brand generics are known for reliable quality and competitive pricing.
✅ Practical brand switching
Patients can switch between norfloxacin brands at the same 400 mg strength without clinical difference. All contain the same active ingredient at the same concentration.
⚠️ Fluoroquinolone class BLACK BOX warnings
The fluoroquinolone class carries several FDA BLACK BOX WARNINGS. These are the most serious safety warnings the FDA issues. They apply to norfloxacin as they do to other fluoroquinolones.
🔴 Complete list of BLACK BOX WARNINGS
- Tendon rupture and tendinitis (2008) — Achilles most commonly, other tendons also. Higher risk in older adults, on corticosteroids, or with organ transplant. Can occur during or up to months after finishing the course. See section 23.
- Peripheral neuropathy (2013) — numbness, tingling, burning, weakness in extremities. Can be irreversible. Can develop rapidly after starting the drug. See section 25.
- Central nervous system effects (2016) — confusion, agitation, tremor, seizures, hallucinations, psychosis, suicidal thoughts. Can develop even at low doses.
- Exacerbation of myasthenia gravis — can worsen muscle weakness, cause respiratory failure. Do not use in known myasthenia gravis.
- Aortic aneurysm and dissection (December 2018) — 2 to 3 fold increased risk shown in multiple large studies. Avoid in patients with known aneurysm, family history, or risk factors. See section 24.
- Hypoglycemia (July 2018) — in diabetic patients on hypoglycemic agents, sometimes severe or fatal.
- Mental health effects (July 2018) — delirium, psychosis, memory impairment.
⚠️ FDA 2016 disabling adverse effects language
"Fluoroquinolones have been associated with disabling and potentially permanent serious side effects that can occur together. These side effects can involve the tendons, muscles, joints, nerves, and central nervous system." This warning applies to all fluoroquinolones including norfloxacin.
🚨 Onset can be unpredictable
- Some effects (peripheral neuropathy, CNS effects) can develop within hours of first dose
- Others (tendon rupture, aortic dissection) can develop weeks after finishing the course
- Some patients have effects on first-ever exposure; others tolerate multiple prior courses
- Duration of exposure does not eliminate risk — even short courses can cause disabling effects
📋 FDA recommendations to prescribers
- Reserve fluoroquinolones for infections where benefit clearly outweighs substantial risk
- Do not use for uncomplicated UTI, sinusitis, or bronchitis when alternatives are available
- Discuss the risks with patients before prescribing
- Discontinue at the first sign of tendon pain, nerve symptoms, or CNS effects
- Report suspected serious adverse events to FDA MedWatch
- Recognize that some effects may persist after drug discontinuation
🧫 Diarrhea and Clostridioides difficile risk
Fluoroquinolones including norfloxacin carry high risk of Clostridioides difficile infection (CDI). Along with clindamycin, cephalosporins, and carbapenems, fluoroquinolones are among the top CDI-triggering antibiotics.
| Antibiotic class | Relative CDI risk |
|---|---|
| Penicillin V | Low |
| Amoxicillin, nitrofurantoin | Low to moderate |
| 1st-generation cephalosporins | Moderate |
| 3rd-generation cephalosporins | High |
| Fluoroquinolones (Norcin) | High |
| Clindamycin | Highest (BLACK BOX) |
🔴 Recognising CDI
- Watery diarrhea 3 or more loose stools per 24 hours
- Abdominal cramping
- Fever (variable, may be absent)
- Bloody diarrhea in severe cases
- Onset during course OR up to 8 weeks after finishing
- Elevated white cell count
- Rising creatinine may indicate severe disease
🩹 Management if CDI develops
- Stop norfloxacin immediately if clinical situation permits
- Send stool for C. difficile toxin PCR or EIA
- Contact precautions if hospitalized
- Do not use loperamide — can worsen toxic megacolon
- Treat per IDSA 2021: fidaxomicin 200 mg twice daily for 10 days or oral vancomycin 125 mg four times daily for 10 days first-line
- Adequate hydration and electrolyte correction
- Surgical consultation for severe or fulminant disease
🧪 Prevention through stewardship
Because fluoroquinolones are a top CDI driver, avoiding unnecessary use has become a central hospital stewardship target. Individual prescribing decisions matter: each avoided fluoroquinolone course reduces institutional and community CDI burden. This is one reason the 2016 FDA restriction on fluoroquinolones for uncomplicated UTI has value beyond individual patient safety.
☀️ Photosensitivity and dermatologic effects
Norfloxacin can cause increased sensitivity to sunlight (photosensitivity). This is a class effect of fluoroquinolones though less severe with norfloxacin than with some earlier agents.
☀️ Photosensitivity presentation
- Exaggerated sunburn from limited sun exposure
- Red, hot, painful skin in sun-exposed areas
- Blistering in severe cases
- Onset within hours of sun exposure
- Sun-exposed areas only (face, arms, hands, neck)
- Improves after sun avoidance and drug discontinuation
🧴 Sun protection strategy
- Minimise direct sun exposure during and for a week after the course
- Broad-spectrum sunscreen SPF 30 or higher when outdoors
- Protective clothing, wide-brim hats
- Avoid tanning beds and phototherapy devices
- Report exaggerated sunburn reactions — may require discontinuation
🔴 Other dermatologic effects
- Rash of any pattern (2 to 3 percent)
- Urticaria — may indicate hypersensitivity, stop drug
- Stevens-Johnson syndrome and TEN — rare but reported, emergency care
- DRESS syndrome — rare
- Erythema multiforme — rare
- Fixed drug eruption — rare
❗ Severe adverse effects reference
Serious side effects with norfloxacin follow the fluoroquinolone class pattern. Awareness of these presentations allows early recognition, immediate drug discontinuation, and prompt evaluation.
🔴 Serious side effects requiring immediate discontinuation
- Anaphylaxis
- Rapid hives, angioedema, wheezing, hypotension. Epinephrine, emergency care.
- Tendon rupture and tendinitis (BLACK BOX)
- Achilles most common; also biceps, rotator cuff. Immediate discontinuation and rest. See section 23.
- Peripheral neuropathy (BLACK BOX)
- Numbness, tingling, pain, weakness in extremities. Can be irreversible. See section 25.
- CNS effects (BLACK BOX)
- Seizures, tremor, agitation, delirium, hallucinations, psychosis, suicidal ideation. See section 25.
- Aortic aneurysm and dissection (FDA 2018)
- Sudden severe chest, back, or belly pain. Emergency imaging. See section 24.
- QT prolongation and torsades
- Palpitations, syncope. Emergency ECG. See section 26.
- Hypoglycemia (FDA 2018)
- Sweating, tremor, confusion in diabetics on hypoglycemic agents. See section 26.
- Myasthenia gravis exacerbation (BLACK BOX)
- Worsening weakness, respiratory failure. Contraindicated in known myasthenia.
- C. difficile colitis
- Severe watery or bloody diarrhea. Can develop up to 8 weeks after course. See section 20.
- Hepatotoxicity
- Rare. Jaundice, LFT elevation. Immediate discontinuation.
- Retinal detachment
- Sudden vision changes, floaters, curtain vision. Emergency ophthalmology.
- SJS, TEN, DRESS
- Rare but reported. Skin sloughing, mucous membrane involvement. Emergency care.
📋 Warning symptoms — counsel every patient
- Tendon pain, swelling, or a "snap" — especially Achilles — stop and rest
- Numbness, tingling, burning in hands or feet — stop drug
- Confusion, hallucinations, unusual thoughts, suicidal ideation — stop and urgent evaluation
- Sudden severe chest, back, or belly pain — emergency care
- Palpitations, dizziness, fainting — ECG evaluation
- Symptoms of low blood sugar in diabetic patients
- Muscle weakness or new breathing difficulty
- Severe watery diarrhea or bloody stools
- Yellowing of skin or eyes, dark urine
- Sudden vision changes or floaters
- Extensive rash, blistering, mouth sores
🧪 Overall safety context
Norfloxacin's serious adverse effect burden is substantially higher than beta-lactams, nitrofurantoin, or TMP-SMX for most outpatient UTI indications. This is the basis for the FDA restriction on fluoroquinolones for uncomplicated UTI. When norfloxacin is prescribed, informed consent about the class-specific risks should be part of every prescription. The risk-benefit calculation should be explicit, not assumed to favour treatment.
🦵 Tendon rupture and tendinitis
Tendon rupture and tendinitis are the original FDA BLACK BOX WARNING for the fluoroquinolone class, added in July 2008. The Achilles tendon is the most commonly affected, but rotator cuff, biceps, hand, and other tendons have all been reported.
🔴 FDA BLACK BOX language (2008)
"Fluoroquinolones are associated with an increased risk of tendinitis and tendon rupture in all ages. This risk is further increased in those over 60 years of age, in kidney, heart, and lung transplant recipients, and with the use of concomitant corticosteroid therapy."
| Risk factor | Effect on tendon rupture risk |
|---|---|
| Age over 60 | 2 to 3 fold increase |
| Concomitant corticosteroid | 4 to 6 fold increase |
| Solid organ transplant recipient | 3 to 5 fold increase |
| Renal impairment | 2 fold increase |
| Prior tendon disorder or rupture | Strong risk factor |
| Physical activity, sports | Moderate additive risk |
| Diabetes mellitus | Modest increase |
| Extended course (prostatitis 4 to 6 weeks) | Cumulative exposure amplifies risk |
🦵 Warning signs and immediate action
- New pain in the back of the heel, calf, shoulder, or upper arm
- Swelling around a tendon
- Feeling of a "snap" or "pop" with sudden pain
- Inability to bear weight on affected leg
- Bruising over the tendon area
- Onset can be during course, days after, or up to several months later
If any tendon warning sign occurs: STOP norfloxacin immediately, avoid weight-bearing and exercise, apply ice, seek urgent orthopedic evaluation.
🔴 Corticosteroid combination — the highest-risk scenario
Concurrent use of norfloxacin and corticosteroids amplifies tendon rupture risk 4 to 6 fold and represents the highest-risk fluoroquinolone-tendon scenario. This combination is particularly problematic in elderly patients on chronic prednisone for autoimmune disease or COPD. Alternative antibiotics should be strongly preferred in this population.
📋 Counselling
Every patient receiving norfloxacin should be counselled about tendon warning signs before starting. Instruct to rest if any joint or tendon discomfort develops during or after the course, and to avoid strenuous physical activity for at least the duration of the course and several days after.
🔴 Aortic aneurysm and dissection risk
The FDA December 2018 Safety Communication added aortic aneurysm and dissection risk to the fluoroquinolone class labeling. Multiple large population cohort studies established the association.
🔴 The evidence base
- Lee CC et al 2015 Taiwan population cohort showed 2-fold increased aortic aneurysm risk within 60 days of fluoroquinolone exposure
- Pasternak B et al 2018 Danish and Swedish cohorts confirmed similar risk elevation
- Etminan M et al 2018 US cohort study replicating the association
- Meta-analyses consistently show 2 to 3 fold elevated risk in fluoroquinolone users versus comparator antibiotics
- Biological plausibility: fluoroquinolones inhibit matrix metalloproteinase collagen turnover in aortic wall
| High-risk population | FDA recommendation |
|---|---|
| Known aortic aneurysm | Avoid fluoroquinolones unless no alternative |
| Family history of aortic aneurysm | Prefer alternative agent |
| Marfan syndrome, Ehlers-Danlos | Avoid unless no alternative |
| Hypertension, atherosclerosis | Weigh risk-benefit carefully |
| Age over 65 | Prefer alternative when possible |
| Prior aortic surgery or endovascular repair | Prefer alternative agent |
🚨 Aortic dissection warning signs
- Sudden, severe pain in the chest, back, or belly — often described as tearing or ripping
- Pain radiating between shoulder blades
- Fainting or syncope
- Sudden shortness of breath
- Weakness or loss of pulse in one arm or leg
- New neurologic deficit
Any of these during or after norfloxacin: EMERGENCY CARE. Do not delay for evaluation of infection.
📋 Practical framework
Before prescribing norfloxacin to any patient over 65 or with cardiovascular risk factors, ask about family history of aortic disease and known aneurysm. In high-risk patients, alternative antibiotics should be strongly preferred. If norfloxacin is necessary despite risk, patient must be explicitly counselled about aortic dissection warning signs and to seek immediate emergency care.
🧠 Peripheral neuropathy and central nervous system effects
Peripheral neuropathy and central nervous system effects are both fluoroquinolone BLACK BOX WARNINGS. Peripheral neuropathy can be irreversible; CNS effects can be severe but usually reversible.
🔴 Peripheral neuropathy
- Numbness or tingling in hands, feet, or both
- Burning pain in fingers and toes
- Weakness of grip, foot drop in severe cases
- Symmetric stocking-glove distribution often
- Can develop within hours of starting or later in a course
- Sometimes appears after a course completes
- Can be irreversible in some patients despite discontinuation
🔴 CNS effects spectrum
- Common (3 to 8 percent)
- Dizziness, headache, insomnia, mild anxiety, restlessness
- Moderate (0.5 to 2 percent)
- Tremor, agitation, nervousness, confusion, memory impairment, nightmares
- Serious (rare but reported)
- Seizures, delirium, hallucinations, psychosis, mania, paranoia, suicidal ideation and behavior
🧬 Mechanisms
Peripheral neuropathy from fluoroquinolones is thought to reflect direct nerve toxicity mediated by mitochondrial dysfunction. CNS effects reflect GABA-A receptor antagonism which lowers seizure threshold and disrupts inhibitory neurotransmission. Concurrent NSAIDs amplify CNS effects — a documented interaction.
👤 Highest-risk populations
- Prior peripheral neuropathy (any cause)
- Diabetes mellitus with existing neuropathy
- Prior seizure disorder
- Prior severe depression or psychiatric hospitalization
- Elderly, especially with cognitive impairment
- Renal impairment (accumulation)
- Concurrent NSAIDs
- Concurrent theophylline
- Alcohol use disorder
🩹 Management
- Stop norfloxacin immediately at first symptoms
- Do not wait to see if symptoms progress
- Switch to alternative antibiotic based on target infection
- Refer to neurology for confirmation and workup
- Psychiatric evaluation for hallucinations, psychosis, or suicidal ideation
- Symptomatic pain management for painful neuropathy (gabapentin, pregabalin)
- Physical therapy for weakness and functional preservation
- Most CNS effects resolve days to weeks after stopping
- Lifetime fluoroquinolone avoidance for confirmed severe events
💓 QT prolongation and hypoglycemia
QT prolongation on the heart and hypoglycemia in diabetic patients are two additional class effects. Both can be severe and require attention to risk factors before prescribing.
💓 QT prolongation and torsades
- Modest QT interval prolongation compared with other fluoroquinolones
- Lower risk than moxifloxacin, higher than ciprofloxacin
- Amplifying factors: baseline QTc above 450 ms in women or 460 ms in men, uncorrected hypokalemia or hypomagnesemia, bradycardia, structural heart disease
- Concurrent QT-prolonging drugs additively increase risk (see interactions section)
- Elderly at higher risk
- Female sex (women have longer baseline QT)
💓 QT warning symptoms
- Palpitations or sensation of racing heart
- Presyncope or syncope (fainting)
- Sudden dizziness with loss of consciousness
- Seizure-like activity (torsades can precipitate)
- Cardiac arrest
Any of these: emergency evaluation. Cardiac monitoring. Correct electrolytes.
🔴 Hypoglycemia (FDA 2018)
- Reported in diabetic patients on hypoglycemic agents
- Some fatal cases reported
- Higher risk with insulin, sulfonylureas, meglitinides
- Higher risk in elderly diabetic patients
- Higher risk with reduced kidney function
🍬 Hypoglycemia recognition
- Sweating, tremor, palpitations
- Confusion, dizziness, difficulty concentrating
- Hunger, weakness
- Loss of consciousness in severe cases
- Seizures in severe cases
- Onset can be within days of starting the drug
📋 Management framework
- Screen for QT risk factors and hypoglycemia risk factors before prescribing
- Baseline ECG in high-risk patients
- Review medications for QT-prolonging co-administrations
- Check baseline potassium and magnesium; correct if low
- In diabetics on hypoglycemic agents: increase blood glucose monitoring frequency
- Consider dose reduction of insulin or sulfonylureas during norfloxacin course
- Ensure patient has fast-acting glucose available
- Consider alternative antibiotic if multiple high risk factors present
⚖️ Norcin versus Cipro and Levaquin
Norfloxacin, ciprofloxacin (Cipro), and levofloxacin (Levaquin) are the three most widely used fluoroquinolones. Understanding their differences helps clarify when each fits.
| Feature | Norfloxacin (Norcin) | Ciprofloxacin (Cipro) | Levofloxacin (Levaquin) |
|---|---|---|---|
| Generation | 2nd | 2nd | 3rd (respiratory) |
| Tissue penetration | Poor | Good | Excellent |
| Pneumococcal coverage | Poor | Poor | Excellent |
| Uncomplicated cystitis | Restricted; reserve | Restricted; reserve | Restricted; reserve |
| Pyelonephritis | Not usable | First-line | First-line |
| Community-acquired pneumonia | Not usable | Not usable | First-line alternative |
| Prostatitis | Established niche | First-line | First-line |
| Dosing frequency | Twice daily | Twice daily | Once daily |
| Class BLACK BOX warnings | All apply | All apply | All apply |
| QT signal | Moderate | Low | Moderate |
| CDI risk | High | High | High |
| Cost | Low | Low | Low (generic) |
🎯 When each fits within the fluoroquinolone class
- Norfloxacin: uncomplicated urinary tract only where alternatives cannot be used; chronic prostatitis; largely narrowed role due to poor tissue penetration
- Ciprofloxacin: pyelonephritis, complicated UTI, prostatitis, GI infection where a fluoroquinolone is genuinely needed
- Levofloxacin: community-acquired pneumonia with comorbidities, nosocomial pneumonia, complicated UTI with pyelonephritis
- All three subject to same 2016 FDA restrictions and class-wide BLACK BOX warnings
⚖️ Norcin versus Macrobid for uncomplicated UTI
For uncomplicated cystitis in non-pregnant adults, Macrobid (nitrofurantoin) is now preferred over norfloxacin because of the FDA 2016 restriction on fluoroquinolone use for this indication.
| Feature | Norcin (norfloxacin) | Macrobid (nitrofurantoin) |
|---|---|---|
| Uncomplicated cystitis first-line | FDA restricted; reserve only | First-line |
| Course length | 3 days | 5 days |
| Dosing frequency | Twice daily | Twice daily |
| Serious side effect risk | Substantial (BLACK BOX warnings) | Rare for short course |
| C. difficile risk | High | Very low |
| Pregnancy | Avoid | First-line most of gestation |
| Kidney impairment (severe) | Adjustment; may still work | Not usable if CrCl below 30 |
| Pyelonephritis | Not usable | Not usable |
| E. coli community susceptibility | 70 to 80 percent (variable) | Over 90 percent |
| Cost | Low | Low |
🎯 Choosing between them
- Macrobid preferred as first-line for uncomplicated cystitis in non-pregnant adults with adequate kidney function
- Norcin acceptable when kidney impairment rules out Macrobid, prior Macrobid adverse effect, or Macrobid unavailable
- Macrobid preferred in pregnancy (until 36 weeks)
- Norcin preferred for chronic prostatitis (Macrobid not effective for prostate)
⚖️ Norcin versus Bactrim for uncomplicated UTI
TMP-SMX (Bactrim) is another IDSA first-line option for uncomplicated cystitis. Choice between Norcin and Bactrim depends on local resistance patterns, sulfa allergy, and patient factors.
| Feature | Norcin (norfloxacin) | Bactrim (TMP-SMX) |
|---|---|---|
| Uncomplicated cystitis first-line | Restricted (FDA 2016) | First-line if regional resistance under 20 percent |
| Course length | 3 days | 3 days |
| E. coli community susceptibility | 70 to 80 percent | 70 to 85 percent (regional) |
| Pyelonephritis | Not usable | Acceptable if susceptible |
| Sulfa allergy | Safe | Contraindicated |
| Warfarin interaction | Modest | Strong (INR rises) |
| Kidney effects | Modest | Creatinine rise, hyperkalemia |
| Serious side effect burden | FQ class BLACK BOX | Skin reactions, blood counts |
| Pregnancy | Avoid | Avoid first trimester and near term |
| Cost | Low | Very low |
🎯 When each fits
- Bactrim preferred for uncomplicated cystitis in most non-pregnant adults with adequate kidney function and no sulfa allergy
- Norcin acceptable when sulfa allergy rules out Bactrim, kidney function ruling out Macrobid, or specific patient factors
- Culture-guided therapy is preferred when resistance patterns are uncertain
⚖️ Norcin in acute pyelonephritis role
Acute pyelonephritis (kidney infection) requires antibiotics that reach kidney tissue at effective concentrations. Norfloxacin's poor tissue penetration makes it unsuitable for pyelonephritis, unlike ciprofloxacin and levofloxacin which are first-line.
⛔ Why norfloxacin fails in pyelonephritis
- Poor kidney parenchymal concentration — drug reaches urine but not kidney tissue
- Low serum concentration — cannot control bacteremia from pyelonephritis
- Cannot penetrate abscess
- Prolonged renal transit time in pyelonephritis reduces urinary concentration further
- Treatment failure rate high in retrospective studies of inadvertent norfloxacin use for pyelonephritis
| Pyelonephritis presentation | Preferred alternative to norfloxacin |
|---|---|
| Outpatient uncomplicated pyelonephritis | Ciprofloxacin 500 mg BID for 7 days or levofloxacin 750 mg daily for 5 days (if susceptibility) |
| Outpatient with GI symptoms preventing oral | Initial IV ceftriaxone, then oral step-down |
| Inpatient pyelonephritis | IV ceftriaxone, then oral step-down |
| Severe pyelonephritis with sepsis | Broad-spectrum IV until susceptibility known |
| Pregnancy pyelonephritis | Hospitalization; IV ceftriaxone or ampicillin-gentamicin |
🔬 Warning signs to escalate care
A patient started on norfloxacin for presumed cystitis should be reassessed if any of the following develop within 48 hours:
- New or worsening flank pain
- Fever developing during therapy
- Nausea or vomiting
- Increasing pain despite treatment
- Systemic illness signs (chills, malaise, tachycardia)
- These may indicate pyelonephritis needing alternative therapy and possibly hospitalization
🧪 Correct diagnosis matters
Distinguishing uncomplicated cystitis from pyelonephritis at the point of care is essential to appropriate antibiotic selection. Cystitis (norfloxacin acceptable): dysuria, frequency, urgency, suprapubic discomfort, no fever, no flank pain. Pyelonephritis (norfloxacin fails): flank pain, fever, systemic symptoms. Male UTI, catheter-associated UTI, and pregnancy UTI often warrant broader-spectrum agents that penetrate tissue.
🔄 When to choose an alternative — increasingly restrictive
Norfloxacin's modern framework starts from the assumption that an alternative should be used whenever one exists. FDA restrictions and stewardship guidance reflect this. The remaining niches are defined and narrow.
⛔ Do not use norfloxacin
- Prior fluoroquinolone-induced tendon rupture or tendinitis
- Prior fluoroquinolone-induced peripheral neuropathy
- Prior fluoroquinolone-induced seizure or severe CNS effect
- Prior fluoroquinolone-induced psychiatric adverse event
- Known myasthenia gravis (BLACK BOX contraindication)
- Prior anaphylaxis to any fluoroquinolone
- Prior QT prolongation with fluoroquinolone exposure
- Pregnancy (Category C)
- Pediatric use (with rare exceptions)
- Pyelonephritis (poor tissue penetration)
- Any respiratory, skin, bone, or systemic infection
🟡 FDA 2016 restricted indications
- Uncomplicated cystitis — use nitrofurantoin, fosfomycin, or TMP-SMX first
- These indications should not use fluoroquinolone unless alternatives are unsuitable
🟡 Reconsider norfloxacin
- Any patient over 65 with cardiovascular risk factors
- Patients on concurrent corticosteroids (tendon risk 4-6x)
- Patients with known aortic aneurysm or family history
- Patients with prior seizure disorder
- Patients with prior severe depression or psychiatric hospitalization
- Patients on multiple QT-prolonging medications
- Diabetics with prior hypoglycemic events on sulfonylureas
- Athletes and physically active adults (tendon rupture risk)
- Patients requiring extended courses (prostatitis 4-6 weeks) where cumulative exposure amplifies risk
✅ Where norfloxacin still fits genuinely
Chronic bacterial prostatitis with confirmed susceptibility, complicated cystitis where alternatives are unsuitable, uncomplicated cystitis in patients with sulfa allergy plus kidney impairment ruling out nitrofurantoin, specific niche uses in developing world settings. Its role is smaller than 30 years ago but focused urinary use remains legitimate when the specific patient situation demands it.
🔄 Common alternatives
For uncomplicated cystitis: nitrofurantoin, fosfomycin, TMP-SMX, cephalexin, amoxicillin. For pyelonephritis: ciprofloxacin, levofloxacin, ceftriaxone. For prostatitis: TMP-SMX, ciprofloxacin, levofloxacin. Culture-guided therapy is preferred when possible.
📦 Storage and stability
Norcin tablets have straightforward storage requirements.
| Formulation | Storage | Shelf life |
|---|---|---|
| 400 mg tablets | Room temperature 15 to 30 C, dry | Until printed expiry |
📦 Storage rules
- Store tablets in original blister or bottle to protect from moisture and light
- Do not refrigerate
- Keep out of reach of children
- Discard past printed expiry date
- Do not use tablets with damaged coating
- In humid climates, be attentive to moisture damage
⏰ Missed dose management
Norfloxacin is twice daily with a 3 to 4 hour half-life. Missed dose management follows standard rules.
⏰ Missed dose rule
- If less than 6 hours late
- Take the missed dose as soon as remembered on an empty stomach. Continue with next scheduled dose at usual time.
- If more than 6 hours late (approaching next dose)
- Skip the missed dose. Take next scheduled dose at usual time. Do not double-dose.
⚠️ Do not double-dose
Taking two doses close together does not improve cure and can amplify tendon, CNS, and QT adverse effects. Continue with regular twice-daily schedule.
💡 Adherence tips
- Take at the same times each day
- Set phone alarms for morning and evening doses
- Take at least 2 hours away from meals and dairy
- Take at least 2 hours from any antacid, iron, calcium, or zinc supplement
- For chronic prostatitis 4-6 week courses: pill organizer and dose tracking
- Contact prescriber if multiple doses missed — may need to restart or modify treatment
👵 Geriatric considerations
Older adults face the highest fluoroquinolone adverse effect burden. Every class-associated risk (tendon rupture, aortic dissection, CNS effects, CDI, QT, peripheral neuropathy, hypoglycemia) rises with age.
🔴 Amplified risks in the elderly
- Tendon rupture risk 2-3x baseline, 4-6x with corticosteroids
- Aortic aneurysm and dissection risk 2-3x baseline
- C. difficile colitis risk amplified in nursing home populations
- CNS effects (delirium, hallucinations, falls) more common
- QT prolongation more likely with baseline cardiac disease and polypharmacy
- Peripheral neuropathy more common with diabetic and other pre-existing neuropathy
- Renal function decline often unrecognized — risk of accumulation
- Hypoglycemia in diabetic elderly on sulfonylureas can be fatal
| Geriatric prescribing check | Action |
|---|---|
| Estimate creatinine clearance before prescribing | Use Cockcroft-Gault; adjust dose per section 14 |
| Screen for aortic disease | Ask about known aneurysm, family history, prior imaging |
| Review corticosteroid use | Concurrent steroids: strongly prefer alternative agent |
| Baseline QT status | ECG in patients with polypharmacy or known cardiac disease |
| Screen for prior tendon problems | Prior tendinopathy or rupture: avoid |
| Assess CDI history | Prior CDI: strongly prefer alternative |
| Review psychiatric and neurological history | Prior seizure, severe depression: avoid or extreme caution |
| Counsel on warning signs | Tendon pain, sudden severe chest/back pain, confusion, palpitations, numbness |
✅ Bottom line for older adults
For older adults with any fluoroquinolone risk factor, alternatives should be strongly preferred. Nitrofurantoin for cystitis (if kidney function permits), ceftriaxone for pyelonephritis, TMP-SMX for cystitis or prostatitis, and amoxicillin for susceptible cases — all avoid the class-specific age-amplified risks. Norfloxacin remains appropriate for specific niches (prostatitis when TMP-SMX not appropriate) but should not be empirical first choice in patients over 65.
💰 Cost, availability, and future outlook
Generic norfloxacin is affordable and widely available internationally. Nadoxin Cipla brand is among the low-cost options.
| Antibiotic (typical UTI course) | Course cost USD |
|---|---|
| Norfloxacin (Norcin, generic) | 5 to 25 |
| Ciprofloxacin generic | 5 to 15 |
| Levofloxacin generic | 10 to 40 |
| Nitrofurantoin (Macrobid) | 10 to 30 |
| TMP-SMX (Bactrim) | 5 to 15 |
| Fosfomycin single dose | 30 to 80 |
🔭 Future outlook
- Continued stewardship pressure
- FDA restrictions and hospital antibiotic stewardship programs continue to narrow fluoroquinolone use for uncomplicated indications. Norfloxacin will remain restricted.
- Rising resistance
- Community E. coli fluoroquinolone resistance continues to rise. Empirical use for community UTI is largely inappropriate in most regions.
- Enduring prostatitis role
- Chronic bacterial prostatitis remains a legitimate fluoroquinolone niche including for norfloxacin when susceptibility permits.
- Preference for newer fluoroquinolones
- For pyelonephritis and complicated infections, ciprofloxacin and levofloxacin are preferred over norfloxacin because of better tissue penetration.
- International markets
- Norfloxacin remains widely used in developing world settings for UTI due to low cost. Rising resistance in some regions is a concern.
✅ Overall value
Norfloxacin remains an inexpensive and effective option for specific niches (chronic prostatitis, complicated cystitis when alternatives unsuitable) but its broad role has substantially narrowed due to safety concerns, rising resistance, and better alternatives for most indications.
⛔ Absolute contraindications and precautions
Final consolidation of all situations where Norcin must not be used, or must be used only with specific safeguards.
⛔ Absolute contraindications
- Prior anaphylaxis to any fluoroquinolone
- Lifetime class avoidance.
- Prior fluoroquinolone-induced tendon rupture or tendinitis
- Lifetime class avoidance.
- Prior fluoroquinolone-induced peripheral neuropathy
- Lifetime class avoidance — risk of irreversible recurrence.
- Prior fluoroquinolone-induced seizure or severe CNS effect
- Lifetime class avoidance.
- Prior fluoroquinolone-induced psychiatric adverse event
- Class caution; alternative preferred.
- Prior fluoroquinolone-induced hepatotoxicity
- Class avoidance.
- Myasthenia gravis (BLACK BOX)
- Absolute class contraindication — exacerbation risk.
- Prior QT prolongation with fluoroquinolone exposure
- Class avoidance.
🟡 Relative contraindications and cautions
- Known aortic aneurysm or family history
- Avoid unless no alternative available.
- Prior C. difficile infection
- Amplified recurrence risk; choose alternative if possible.
- Renal impairment CrCl below 30 mL/min
- Interval extension mandatory (see section 14).
- Concurrent corticosteroid therapy
- Tendon rupture risk 4-6x; strongly prefer alternative.
- Concurrent QT-prolonging drugs
- Class IA/III antiarrhythmics, macrolides, antipsychotics, methadone.
- Prior seizure disorder
- Elevated seizure risk; alternative preferred.
- Diabetes on hypoglycemic agents
- Monitor blood glucose closely; hypoglycemia risk.
- Concurrent NSAIDs
- Additive CNS excitation, seizure risk.
- Concurrent warfarin
- INR monitoring day 3 to 5 during and after therapy.
- Age over 65 with cardiovascular risk factors
- Amplified all-cause adverse effect risk; strongly prefer alternative for indications with options.
- Pregnancy (Category C)
- Avoid except for life-threatening indications without alternatives.
- Pediatric use
- Generally avoided; specific indications only.
| Warning sign during therapy | Action |
|---|---|
| Hives, wheezing, throat tightness, hypotension | Stop drug immediately, epinephrine, emergency care |
| Tendon pain, swelling, or "pop" sensation | Stop drug, avoid weight bearing, orthopedic evaluation |
| Sudden severe chest, back, or belly pain | Emergency care; consider aortic dissection |
| Numbness, tingling, or burning in extremities | Stop drug immediately; neurology referral |
| Confusion, hallucinations, suicidal thoughts | Stop drug; urgent psychiatric evaluation |
| Seizure activity | Emergency care; benzodiazepine acute |
| Palpitations, fainting | ECG evaluation; consider torsades |
| Hypoglycemia symptoms (diabetic patient) | Glucose measurement; treat hypoglycemia |
| Muscle weakness or breathing difficulty | Consider myasthenia exacerbation; emergency care |
| Sudden vision changes, floaters, curtain | Emergency ophthalmology; retinal detachment risk |
| Severe or bloody diarrhea, fever | Stop drug; CDI stool test; avoid loperamide |
| Jaundice, dark urine, right upper belly pain | Stop drug; LFTs; hepatology if severe |
| Any warning sign up to 8 weeks after course | Take fluoroquinolone history seriously |
📋 Populations requiring extra vigilance
- Adults over 65 (all risks amplified)
- Patients on concurrent corticosteroids
- Patients with prior tendon disorder
- Patients with known aortic disease or family history
- Patients with prior seizure or severe psychiatric illness
- Diabetics on sulfonylureas or insulin
- Patients with prior C. difficile infection
- Patients on QT-prolonging medications
- Patients with renal impairment
- Pregnant and lactating women
- Pediatric patients (limited approved indications)
- Athletes and physically active adults
Used within these boundaries, norfloxacin remains a valuable option for specific niches: chronic bacterial prostatitis with confirmed susceptibility, complicated cystitis when alternatives are unsuitable, and specific developing world use where cost is a critical factor. Its role has narrowed substantially due to FDA restrictions, better-tolerated alternatives, rising community resistance, and the class-wide fluoroquinolone safety concerns. When prescribed, informed consent about the class-specific BLACK BOX warnings and adverse effect burden should be explicit and documented.
Norcin — Frequently Asked Questions
-
What is Norcin (Norfloxacin) used for?
Norcin is primarily prescribed to treat bacterial infections such as urinary tract infections, chronic bacterial prostatitis, and gastrointestinal infections including travelers diarrhea. It works by inhibiting bacterial DNA replication, leading to effective infection control. -
How does Norcin work inside the body?
This medication belongs to fluoroquinolone antibiotics and blocks enzymes DNA gyrase and topoisomerase IV. By interfering with bacterial DNA processes, Norcin prevents bacteria from multiplying, allowing the immune system to eliminate the infection. -
Is Norcin effective for urinary tract infections?
Yes, Norcin is highly effective in treating UTIs because it reaches high concentrations in the urinary tract. Patients usually notice improvements in burning sensations, urgency, and frequent urination within a few days of therapy. -
Can Norcin treat chronic prostatitis?
Norcin penetrates prostate tissue well, making it suitable for managing chronic bacterial prostatitis. Long-term courses of 4–6 weeks are often required to achieve symptom relief and prevent recurrence of infection in men. -
Does Norcin help with travelers diarrhea?
Yes, Norcin is commonly used to treat travelers diarrhea caused by contaminated food or water. It provides rapid relief from diarrhea, abdominal cramps, and dehydration, often within 48 hours of starting therapy. -
What bacteria are most sensitive to Norcin?
Norcin is particularly effective against gram-negative organisms like E. coli, Klebsiella, Enterobacter, Salmonella, and Shigella. It also works against some gram-positive pathogens but is not considered a first choice for those. -
How quickly does Norcin start working?
Patients often begin to notice improvements within 24 to 48 hours. Symptom relief includes reduced fever, less abdominal pain, and improved urination comfort, though full eradication of infection requires completing the entire treatment course.
📚 Drug Description Sources:
Evidence supporting Norcin (norfloxacin) draws on FDA regulatory documentation dating to the 1986 approval as the first oral fluoroquinolone, IDSA uncomplicated UTI guidelines, multiple FDA safety communications restricting fluoroquinolone use, urology society prostatitis guidelines, and extensive safety epidemiology on tendon rupture, aortic dissection, peripheral neuropathy, and other class-wide fluoroquinolone concerns. Every citation below documents an aspect referenced in this medication guide.
🏛️ Regulatory documentation and FDA safety communications
- FDA NDA 019384 Noroxin (norfloxacin), Merck Sharp and Dohme, 1986 — the first oral fluoroquinolone.
- FDA 2008 BLACK BOX WARNING for tendon rupture and tendinitis across the fluoroquinolone class.
- FDA 2013 BLACK BOX WARNING update for peripheral neuropathy.
- FDA May 2016 Safety Communication restricting fluoroquinolone use for uncomplicated urinary tract infection when alternatives are available.
- FDA July 2016 label update requiring stronger disabling adverse effects warning.
- FDA July 2018 Safety Communication hypoglycemia and mental health effects.
- FDA December 2018 Safety Communication aortic aneurysm and dissection risk.
- Merck discontinued Noroxin in 2014; international generic norfloxacin remains available including Cipla Norcin brand.
📚 Clinical guidelines
- IDSA Uncomplicated Cystitis Guidelines (Gupta K et al, Clin Infect Dis 2011) — norfloxacin as second-line option only in cases where preferred alternatives cannot be used.
- American Urological Association Chronic Prostatitis Guidance — fluoroquinolone as core therapy for 4 to 6 weeks.
- IDSA Complicated UTI Guidelines — fluoroquinolone role in acute pyelonephritis (though norfloxacin's poor tissue penetration limits pyelonephritis use).
- CDC Sexually Transmitted Infections Guidelines — fluoroquinolones no longer recommended for gonorrhea due to widespread resistance.
- ISTM Traveler Diarrhea Guidelines — fluoroquinolone role in bacterial travelers diarrhea, though shifting toward azithromycin in many regions due to resistance.
🧪 Pharmacology research
- Foundational norfloxacin pharmacokinetic characterisation showing urinary concentration far exceeding serum levels.
- Tissue distribution studies establishing norfloxacin's limited utility outside the urinary tract due to poor systemic tissue penetration.
- Comparative pharmacology studies showing why later fluoroquinolones (ciprofloxacin, levofloxacin) displaced norfloxacin for systemic indications.
- Bioavailability and food effect studies establishing dosing recommendations.
- Renal impairment dose adjustment studies.
🩺 Safety epidemiology research
- Etminan M et al fluoroquinolone class aortic aneurysm risk quantification (JAMA Internal Medicine 2015 and subsequent).
- Lee CC et al Taiwan population registry studies on fluoroquinolone-associated aortic events.
- Pasternak B et al Danish and Swedish cohort studies confirming class-wide tendon rupture epidemiology.
- Etminan M et al retinal detachment risk (JAMA 2012).
- Global E. coli surveillance documenting rising community fluoroquinolone resistance rates.
- Class-wide C. difficile colitis association studies establishing fluoroquinolones as major CDI driver.
🩺 Medical Expert Review:
Below are five clinicians and researchers whose peer-reviewed work directly informs the modern use of norfloxacin and related fluoroquinolones: urinary tract infection stewardship, urologic management, women's UTI, travel medicine, and antimicrobial resistance research.
Dimitri Drekonja, MD, MS
University of Minnesota Medical School, Minneapolis Veterans Affairs Health Care System — Minneapolis, Minnesota, USA
Dr Drekonja is a leading US researcher on urinary tract infection antimicrobial stewardship. His work on treatment duration, appropriate agent selection, and asymptomatic bacteriuria informs the modern framework where fluoroquinolones like norfloxacin are reserved rather than used empirically for uncomplicated UTI, and where safer alternatives are prioritised whenever possible.
Florian M. E. Wagenlehner, MD, PhD
Justus Liebig University Giessen, Department of Urology, Pediatric Urology and Andrology — Giessen, Germany
Prof Wagenlehner is one of Europe's leading urologists and UTI researchers. His research on complicated urinary tract infections, chronic prostatitis, and antimicrobial resistance has shaped European Association of Urology guidance where fluoroquinolones including norfloxacin have narrowing roles due to rising resistance and safety concerns, particularly for complicated UTI.
Jack D. Sobel, MD
Wayne State University School of Medicine, Detroit Medical Center — Detroit, Michigan, USA
Prof Sobel is one of the world's leading authorities on urinary tract infections in women, recurrent UTI, and vulvovaginitis. His research and clinical work over four decades has shaped modern UTI management frameworks where the choice between fluoroquinolones and safer alternatives is informed by resistance patterns and adverse effect profiles.
Bradley A. Connor, MD
Weill Cornell Medicine, New York Center for Travel and Tropical Medicine — New York, New York, USA
Dr Connor is a leading US authority on travel medicine and traveler diarrhea. His research and clinical practice inform the framework where fluoroquinolones like norfloxacin have historically been used for bacterial traveler diarrhea but are increasingly replaced by azithromycin due to rising Campylobacter resistance in Asia and Africa. His work shapes evidence-based traveler counselling.
Cornelius J. Clancy, MD, FIDSA
University of Pittsburgh School of Medicine, VA Pittsburgh Healthcare System — Pittsburgh, Pennsylvania, USA
Prof Clancy directs the VA Pittsburgh antimicrobial stewardship program and researches antimicrobial resistance and stewardship implementation. His work informs the modern framework where fluoroquinolones like norfloxacin are used selectively rather than empirically, with attention to community resistance patterns and the substantial adverse effect burden of the class.
More Antibiotics Medications