Buy Yasmin (Drospirenone + Ethinyl Estradiol) Online — Bayer Monophasic COC with Antimineralocorticoid + Antiandrogenic Progestin for Pregnancy Prevention


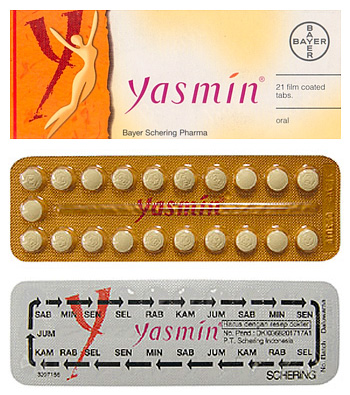
Yasmin is the original brand-name monophasic combined oral contraceptive (COC) containing Drospirenone 3 mg + Ethinyl Estradiol 30 mcg — uniquely distinguished by its antimineralocorticoid and antiandrogenic progestin. Developed by Bayer Pharmaceuticals and FDA-approved since 2001, Yasmin introduced Drospirenone, a novel progestin derived from spironolactone — offering benefits similar to potassium-sparing diuretics (less fluid retention) and antiandrogenic effects (acne, hirsutism reduction). Generic equivalents include Ocella, Syeda, and Zarah. Related products: Yaz (lower 20 mcg estrogen + 24/4 cycle, FDA-approved for acne and PMDD), Beyaz/Safyral (with folic acid).
The two active ingredients work through complementary mechanisms. Drospirenone is a unique spironolactone-derived progestin with three properties: progestational (contraceptive), antimineralocorticoid (reduces water/sodium retention, mild diuresis), and antiandrogenic (reduces sebum, acne, hirsutism). Ethinyl Estradiol 30 mcg is synthetic estrogen at standard dose. Combined: ovulation suppression, cervical mucus thickening, and endometrial thinning. Triple mechanism provides >99% contraceptive efficacy with perfect use.
Yasmin is FDA-approved for prevention of pregnancy. The sister product Yaz (same Drospirenone, 20 mcg estrogen, 24-day active + 4-day placebo) is uniquely FDA-approved for moderate acne in women 14+ desiring contraception AND premenstrual dysphoric disorder (PMDD). Off-label uses for Drospirenone-containing COCs: PCOS management (favorable due to antiandrogenic effect), hirsutism, cycle regulation, menorrhagia reduction, dysmenorrhea, endometriosis pain, perimenopausal symptoms, and PMS symptom relief.
The medication is supplied as Yasmin 28-day pill packs: 21 active pills (Drospirenone 3 mg + Ethinyl Estradiol 30 mcg) + 7 placebo pills. Standard dosing: 1 tablet daily at same time. Start on Sunday after period or first day of menstrual period. Yaz uses different schedule: 24 active + 4 placebo (shorter hormone-free interval).
Critical safety considerations include the FDA boxed warning for cigarette smoking and serious cardiovascular events — smoking + COC contraindicated in women over 35. HIGHER VTE risk vs Levonorgestrel-containing COCs (FDA-required warning since 2012). Hyperkalemia risk due to antimineralocorticoid effect — caution and serum potassium monitoring in patients on ACE inhibitors, ARBs, K-sparing diuretics, K supplements, NSAIDs (long-term), or heparin. Standard COC warnings apply: arterial thromboembolism, hypertension, hepatic adenomas, slight breast cancer risk, migraine with aura contraindication.
Free prescription
Discrete packaging
Have questions?
Quality Assurance

- Monophasic Combined Oral Contraceptive (COC): Monophasic COC with unique antimineralocorticoid progestin;
- Moderate Acne Yaz Variant: Yaz variant FDA-approved for moderate acne in women 14+ desiring contraception;
- PMDD Yaz Variant: Yaz variant FDA-approved for premenstrual dysphoric disorder (PMDD);
- Hormonal Acne Women: For hormonal acne due to antiandrogenic Drospirenone effect;
- PCOS / Polycystic Ovary Syndrome: Off-label for PCOS — particularly favorable due to antiandrogenic effect;
- Hirsutism: Off-label for hirsutism (excess body hair) due to antiandrogenic effect;
- PMS / Premenstrual Syndrome: For PMS symptom relief — antimineralocorticoid reduces bloating/fluid retention;
- Fluid Retention Bloating: Off-label for women experiencing fluid retention/bloating on other COCs;
- Premenstrual Bloating: Antimineralocorticoid Drospirenone reduces premenstrual bloating;
- Adolescent Acne Plus Contraception: For adolescent women (14+) with both acne and contraceptive need (Yaz variant);
- Cycle Regulation: Off-label for menstrual cycle regulation in women with irregular periods;
- Menorrhagia / Heavy Menstrual Bleeding: Off-label for heavy menstrual bleeding reduction;
- Dysmenorrhea: Off-label for painful menstrual periods (primary dysmenorrhea);
- Endometriosis Pain: Off-label for endometriosis pain management;
- Functional Ovarian Cysts: Off-label for prevention of functional ovarian cysts;
- Perimenopausal Symptoms: Off-label for perimenopausal symptom relief in healthy non-smoking women;
- Anemia Prevention Heavy Bleeding: For prevention of iron-deficiency anemia secondary to heavy menstrual bleeding;
- Ovarian Cancer Risk Reduction: Long-term COC use reduces ovarian cancer risk;
- Endometrial Cancer Risk Reduction: Long-term COC use reduces endometrial cancer risk.
- Less Fluid Retention: Antimineralocorticoid Drospirenone reduces water/sodium retention vs other COCs;
- Less Bloating: Reduction in premenstrual and cycle-related bloating;
- Less Weight Fluctuation: Less cyclic weight fluctuation than other COCs (antimineralocorticoid effect);
- Less Hormonal Acne: Effective reduction in hormonal acne due to antiandrogenic Drospirenone;
- Better Skin Quality: Improvement in skin quality through reduced sebum production;
- Less Hirsutism: Reduction in unwanted facial and body hair growth;
- Better PCOS Symptom Control: Particular benefit for PCOS due to antiandrogenic effect (Drospirenone);
- Less PMS Symptoms: Off-label reduction in premenstrual syndrome symptoms (bloating, irritability);
- Less PMDD Symptoms: FDA-approved (Yaz variant) for premenstrual dysphoric disorder;
- Reliable Cycle Predictability: Predictable monthly bleeding pattern with regular cycle;
- Less Menstrual Pain: Significant reduction in dysmenorrhea (painful periods);
- Less Heavy Bleeding: Significant reduction in heavy menstrual bleeding (menorrhagia);
- Less Anemia Risk: Reduced iron-deficiency anemia risk through reduced menstrual flow;
- Less Endometriosis Pain: Off-label pain management for endometriosis;
- Less Ovarian Cyst Formation: Suppression of ovulation reduces functional ovarian cyst formation;
- Better Cycle Regulation: Predictable cycles in women with previously irregular menstruation;
- Less Ovarian Cancer Risk: Long-term use reduces ovarian cancer risk;
- Less Endometrial Cancer Risk: Long-term use reduces endometrial cancer risk;
- Better Family Planning: Reliable contraception enables life planning and reproductive autonomy;
- Better Sexual Spontaneity: Daily oral contraception eliminates need for at-time-of-intercourse contraception;
- Better Self-Esteem Acne Resolution: Acne improvement supports self-esteem and psychological wellbeing;
- Better Quality of Life: Substantial improvement through reliable contraception, cycle control, acne resolution, less fluid retention;
- Brand Yasmin: Original Bayer brand with established global clinical reputation since 2001;
- Generic Drospirenone Ethinyl Estradiol: Affordable generic versions expand global access to Drospirenone COC therapy;
- Ocella Equivalent: Same Drospirenone + Ethinyl Estradiol composition as Ocella (Teva generic);
- Syeda Equivalent: Same composition as Syeda generic;
- Zarah Equivalent: Same composition as Zarah generic;
- Yaz Lower Dose Variant: Yaz variant with lower 20 mcg estrogen + 24/4 cycle — FDA-approved for acne AND PMDD;
- Beyaz Safyral Folic Acid: Beyaz (Yaz+folic acid) and Safyral (Yasmin+folic acid) variants;
- Antimineralocorticoid Antiandrogenic Progestin: Unique progestin with antimineralocorticoid + antiandrogenic dual properties;
- Spironolactone Derived Progestin: Drospirenone derived from spironolactone — only spirolactone-class progestin in COCs;
- Mild Diuretic Effect: Mild diuretic effect reduces fluid retention symptoms;
- Ovulation Suppression: Suppresses LH surge and ovulation;
- Cervical Mucus Thickening: Thickens cervical mucus to prevent sperm penetration;
- Endometrial Thinning: Thins endometrial lining — less hospitable for implantation;
- 28 Day Continuous Pack: 28-day continuous pack with 21 active + 7 placebo (Yasmin) or 24 active + 4 placebo (Yaz);
- Once Daily Oral Convenience: Once-daily oral dosing — user-controlled contraceptive method;
- Reversible Fertility: Fully reversible — fertility returns rapidly after discontinuation;
- 20 Plus Year Clinical History: 20+ years of clinical use since 2001 — extensive safety data globally.
Generic Yasmin (Drospirenone and Ethinyl Estradiol 3mg/0.03 mg) Medication guide:
📌 Yasmin COC at a Glance
Yasmin is a fourth-generation combined oral contraceptive that pairs the unique progestin drospirenone 3 mg with a standard low-dose ethinyl estradiol 30 mcg, delivered in a familiar 21-active-plus-7-placebo monophasic pack. What distinguishes Yasmin from every previous generation of combined pill is drospirenone itself: a synthetic progestin derived from the diuretic spironolactone, which carries an anti-mineralocorticoid profile (reducing sodium and water retention) and an anti-androgenic profile (mildly reducing sebum production and androgen effects on skin). Bayer Pharmaceuticals originated the brand, and Cipla and Torrent Pharmaceuticals are established Indian generic manufacturers of the international supply.
This guide covers what makes Yasmin distinct within the combined-pill class, how the pack is taken, the honest picture of the fourth-generation venous thromboembolism trade-off, the practical monitoring rules for potassium (a specific concern with drospirenone-containing pills), and how to time switches to and from other methods. The material follows the FDA prescribing information, the WHO Medical Eligibility Criteria for Contraceptive Use, the US Selected Practice Recommendations from the Centers for Disease Control and Prevention, and Faculty of Sexual and Reproductive Healthcare guidance specific to drospirenone-containing pills.
📌 Yasmin at a glance
| Drug class | Monophasic combined oral contraceptive; fourth-generation progestin (drospirenone) plus low-dose estrogen |
| Active ingredients | Drospirenone 3 mg + ethinyl estradiol 30 mcg per active tablet |
| Pack formats | 21-day (active pills only, seven-day pill-free interval) or 28-day (21 active + 7 placebo) |
| Route and timing | One tablet daily by mouth at the same time each day |
| FDA indication | Prevention of pregnancy (over 99% efficacy with perfect use). The related 24/4 Yaz formulation has additional indications for moderate acne and PMDD; standard Yasmin does not |
| Distinctive properties | Anti-mineralocorticoid activity (less fluid retention than typical COCs) and anti-androgenic activity (mild skin and acne benefit) |
| Signature safety concerns | Venous thromboembolism risk higher than levonorgestrel-containing pills; hyperkalaemia risk with potassium-elevating drugs; arterial thrombosis in smokers over 35 |
Two features distinguish Yasmin from most contemporary combined oral contraceptives. The first is the anti-mineralocorticoid activity of drospirenone, which comes from the molecule's structural similarity to spironolactone and produces a modest natriuretic effect — the body loses a little more sodium and water than it would on a typical combined pill. For some users this translates into less fluid retention, less bloating around the pack transition, and slightly less breast tenderness than on other combined pills. The second is the elevated hyperkalaemia risk when drospirenone is combined with other medicines that raise serum potassium (ACE inhibitors, potassium-sparing diuretics, some non-steroidal anti-inflammatory drugs), which is covered in detail in section 14.
The trade-off, common to all drospirenone-containing pills, is a venous thromboembolism risk that observational cohorts have consistently placed higher than that of second-generation levonorgestrel pills. Whether the risk is materially higher than the third-generation range (desogestrel, gestodene) remains debated in the literature, but every major guideline positions levonorgestrel-containing pills as the first-line combined pill choice and reserves Yasmin for specific clinical reasons.
Some readers arrive at this page as first-time users deciding whether Yasmin is a sensible choice; others are established users returning to check a specific detail such as what to do about a missed pill or whether a new medication might interact with the potassium effect. The sections are organised by topic, and the layout is designed so a returning user can jump to a single section without needing to read the surrounding material.
💊 Drospirenone and Ethinyl Estradiol Explained
The two hormones inside every active Yasmin tablet occupy very different positions in the pharmacological landscape. Drospirenone is a fourth-generation progestin developed in the 1990s specifically to add anti-mineralocorticoid and anti-androgenic activity to the standard progestin profile; it is the only widely-used contraceptive progestin derived from the diuretic spironolactone. Ethinyl estradiol is the synthetic estrogen used in virtually every combined oral contraceptive since the 1960s. What is different about the Yasmin combination is not the estrogen (a standard 30 mcg dose) but the choice of drospirenone as the progestin partner.
💊 The two hormones side by side
| Property | Drospirenone | Ethinyl estradiol |
|---|---|---|
| Hormone class | Fourth-generation progestin, derived from spironolactone | Synthetic estrogen |
| Dose per active tablet | 3 mg | 30 mcg (0.03 mg) — standard low-dose |
| Half-life | Around 30 hours — longer than most other contraceptive progestins | Around 12-24 hours |
| Special activities | Anti-mineralocorticoid (blocks aldosterone at kidney tubule receptors) and anti-androgenic (blocks androgens at target tissues) | No androgenic activity; supports cycle control |
| Metabolism | Extensive hepatic metabolism; predominantly via CYP3A4 | Hepatic first-pass; CYP3A4 among other enzymes |
| Relative VTE risk (COC class) | Higher than levonorgestrel-containing pills; broadly similar to third-generation progestins in most cohorts | Estrogen is the main driver of the VTE signal; 30 mcg is a standard-dose formulation |
Two aspects of the pairing are worth understanding rather than reading past. First, drospirenone's chemical descent from spironolactone is not marketing language — it is the reason for the anti-mineralocorticoid effect, and it is also the reason for the potassium concern discussed in section 14. Spironolactone is a well-established diuretic used for heart failure and hypertension, and it raises serum potassium as part of its mechanism. Drospirenone shares the receptor-binding profile at a much lower diuretic potency (roughly one twenty-fifth of spironolactone milligram for milligram) but retains enough activity to matter in the drug-interaction picture.
Second, the 30 microgram ethinyl estradiol dose is a standard-dose combined pill in modern terms. Levlen sits at 30 mcg with levonorgestrel; Mircette sits at 20 mcg with desogestrel; Ortho Tri-Cyclen sits at 35 mcg with norgestimate. Yasmin's estrogen dose is not unusual within the modern range; what is unusual is the progestin. Users who switched to Yasmin from Levlen have kept the same estrogen exposure and changed only the progestin, which is one reason estrogen-related side effects (nausea, breast tenderness) rarely differ between these two pills for the same user.
🧬 The Three Contraceptive Mechanisms
Every combined oral contraceptive relies on the same set of three anti-pregnancy mechanisms operating simultaneously. The three barriers together are what push perfect-use efficacy above 99%: if any single mechanism falters on a given cycle, the other two are still active. This section describes each of the three as they operate in Yasmin specifically.
- 🌞 Mechanism 1 — Suppression of ovulation
- The daily hormone combination suppresses the pituitary luteinising-hormone surge that would normally trigger ovulation. No egg is released. This is the largest single contributor to contraceptive efficacy. Drospirenone's longer plasma half-life (around 30 hours) contributes to relatively steady levels between daily doses, which supports the ovulation-suppression signal across the pack.
- 💧 Mechanism 2 — Thickening of cervical mucus
- Progestin activity (via drospirenone) turns the cervical mucus from thin, watery, and sperm-friendly around the time of natural ovulation into thick, sticky, and sperm-hostile. Any sperm reaching the cervix face a much harder journey into the uterus. This effect is fast to establish after starting and fast to lose after a missed pill, which is why the seven-day backup rule applies whenever the daily rhythm is disturbed.
- 🍃 Mechanism 3 — Endometrial thinning
- The daily hormones prevent the endometrium from developing the receptive lining that would normally accept an implanting embryo. Even in the extremely unlikely event that an egg were released and fertilised, the endometrium is not primed to receive it. This is a third-line barrier rather than a primary mechanism, but it is a real one.
🧬 What the anti-mineralocorticoid activity adds to the picture
Beyond the three contraceptive mechanisms, drospirenone's anti-mineralocorticoid activity produces a small natriuretic effect: the body loses a little more sodium and water than it would on a typical combined pill. This does not contribute to contraception, but it does reduce the mild fluid retention that some users experience on other combined pills. It is one of the reasons users who felt persistently bloated on a lower-dose or levonorgestrel-containing pill sometimes report subjective improvement on Yasmin.
None of these three mechanisms is unique to Yasmin or to fourth-generation pills. Every combined oral contraceptive relies on the same trio, and the differences between combinations are principally about which progestin does the mucus and endometrial work, at what estrogen dose, and with what added activities beyond contraception. What Yasmin offers is the standard three-mechanism contraceptive protection plus the drospirenone-specific anti-mineralocorticoid and anti-androgenic activities described in section 7.
🎯 Perfect Use vs Typical Use Efficacy
Contraceptive efficacy has two important numbers. Perfect use is the pregnancy rate when the method is used exactly as intended without any errors. Typical use is the pregnancy rate observed in the real world, where missed pills, delayed doses, running out before a refill, and lost coverage during illness are all factored in. The gap between the two numbers is often what determines whether Yasmin is the right fit for a specific user.
| Method | Perfect use, per year | Typical use, per year |
|---|---|---|
| Yasmin (drospirenone COC) | Under 1 pregnancy per 100 users | Around 7-9 pregnancies per 100 users |
| Male condom | 2 per 100 | 13 per 100 |
| Copper IUD | Under 1 per 100 | Under 1 per 100 |
| Contraceptive implant | Under 1 per 100 | Under 1 per 100 |
| Fertility awareness | 3-5 per 100 | 24 per 100 |
Two features of this efficacy picture matter. First, the gap between Yasmin's perfect-use and typical-use columns is entirely explained by user factors — missed pills, delayed doses, lost absorption during vomiting or diarrhoea, courses of enzyme-inducing drugs. The pill itself does not fail; the routine around it does. Second, this is not specific to a drospirenone-containing pill. Every combined oral contraceptive shows a similar gap because they all depend on daily user action to maintain steady hormone levels.
🌲 Users who do well on Yasmin specifically
- Users who experienced troublesome fluid retention or bloating on other combined pills and benefit from the anti-mineralocorticoid activity of drospirenone.
- Users with mild inflammatory acne or seborrhoeic skin who benefit from the anti-androgenic side of drospirenone without needing a formal acne indication.
- Users with premenstrual symptoms (mood, physical) who have not chosen the 24/4 Yaz formulation but benefit incidentally from drospirenone's hormonal profile.
- Users established on Yasmin for several years with well-tolerated use and no risk factors.
⚖️ Users for whom a levonorgestrel pill would usually be preferred
- Users starting combined oral contraception for the first time without a specific reason to prefer drospirenone; a lower-VTE-risk levonorgestrel pill is standard first-line.
- Users with a personal or family history that raises venous thromboembolism concerns, where a lower-risk combined pill or a non-hormonal method fits more comfortably.
- Users on ACE inhibitors, potassium-sparing diuretics, or other potassium-elevating medications (see section 14).
- Users with kidney impairment or adrenal insufficiency where the anti-mineralocorticoid effect could compound the underlying condition.
Neither list is absolute. Individual patterns vary, and what matters most is an honest conversation at the prescribing appointment about whether the specific drospirenone properties are being sought for a specific reason, or whether a simpler levonorgestrel pill would deliver the same contraceptive protection at a smaller trade-off.
📆 The 21-Active-Plus-7-Placebo Pack Design
Yasmin uses a straightforward 21-active-plus-7-placebo monophasic pack. Every one of the twenty-one active tablets contains the same dose of drospirenone and ethinyl estradiol; there is no dose ramp across the pack the way there is in a triphasic pill, and no shortened hormone-free interval the way there is in Mircette or in the Yaz variant of the same combination. Yasmin's standard 21+7 layout is the most common combined-pill structure and one of the reasons the pill is easy to use across primary-care settings globally.
📆 The two Yasmin pack formats
| Format | Active tablets | Placebo tablets | Pack cycle |
|---|---|---|---|
| 21-day pack | 21 tablets containing 3 mg drospirenone + 30 mcg EE | None — user takes a seven-day pill-free break | 28 days total per pack cycle |
| 28-day pack | 21 tablets containing 3 mg drospirenone + 30 mcg EE | 7 hormone-free tablets to preserve the daily routine | 28 days total per pack cycle |
The choice between the two formats is largely a matter of preference. The 28-day pack preserves the "one tablet every day" habit through the placebo week, which is helpful for users who worry that a seven-day break will disrupt the routine that makes them reliable on active pills. The 21-day pack is slightly cheaper because it contains fewer tablets and appeals to users who prefer a physical reminder — the empty week — that they are in the pill-free interval. Neither is clinically superior; contraceptive coverage is identical because the seven pill-free days behave the same way whether they are truly pill-free or filled with placebo tablets.
Anatomy of one 28-day cycle
- Days 1-21: one active tablet every day at roughly the same time. Contraceptive coverage is being maintained continuously.
- Days 22-28: the pill-free (or placebo) week. Hormone levels fall and a withdrawal bleed usually starts a few days into this week — a physiological signal, not a true menstrual period.
- Day 29 (day 1 of the next pack): restart with a new pack of active tablets, whether or not the withdrawal bleed has finished. No gap between packs beyond the built-in seven days.
Yasmin vs the 24/4 Yaz variant — a quick note
The Yaz formulation shares the same drospirenone progestin but uses only 20 mcg ethinyl estradiol and follows a 24-active-plus-4-placebo schedule, with FDA approvals for moderate acne and premenstrual dysphoric disorder in addition to contraception. Standard Yasmin, described on this page, uses 30 mcg estrogen and a 21+7 pack with a pregnancy-only indication. The two are related products with different regulatory profiles; do not swap between them without a prescriber's explicit instruction.
Two features of this schedule are worth understanding. First, the withdrawal bleed during the pill-free interval is not a true period — the endometrium is not the same tissue that would have grown during a natural cycle, and the bleeding is a hormone-withdrawal response rather than a menstrual event. Some users on Yasmin report a lighter withdrawal bleed than on other combined pills, partly because of drospirenone's hormonal profile.
Second, the seven-day pill-free interval is the point where contraceptive coverage is most vulnerable to disruption. Any extension of the pill-free window beyond seven days — missing the first active pill of a new pack, for example — can allow an ovarian follicle to escape suppression, which is exactly the scenario the missed-pill rules in section 9 are designed to prevent.
⚗️ Fourth-Generation Progestin — What Drospirenone Choice Means
The choice of Yasmin over a second-generation levonorgestrel pill is a decision that deserves a clear conversation. Drospirenone is the sole widely-used fourth-generation progestin, developed specifically to add anti-mineralocorticoid and anti-androgenic activity to the standard progestin profile. In that specific respect it is a step forward for users who benefit from those activities. In the venous thromboembolism arithmetic, however, drospirenone follows the general fourth-generation pattern of a modestly higher signal than second-generation pills.
⚗️ Progestin generations at a glance
| Generation | Example progestins | Signature property |
|---|---|---|
| First | Norethindrone, ethynodiol | Original 1960s progestins; more androgenic; used less today |
| Second | Levonorgestrel, norgestrel | Reference standard for VTE risk within COC class; used from 1970s |
| Third | Desogestrel, gestodene, norgestimate | Reduced androgenic effects; modestly higher VTE signal than second-generation |
| Fourth (Yasmin) | Drospirenone | Anti-mineralocorticoid + anti-androgenic; VTE signal broadly similar to third-generation range |
The venous thromboembolism arithmetic across generations comes from large observational cohorts, principally from Denmark, the United Kingdom, and the United States. Users of second-generation levonorgestrel-containing combined pills experience roughly 5-7 venous thromboembolism events per 10,000 women per year. Users of drospirenone-containing combined pills experience roughly 9-12 events per 10,000 women per year in most cohorts — broadly similar to the third-generation range. Non-users of combined pills of the same age experience roughly 2 events per 10,000 women per year, and pregnancy itself carries roughly 29 events per 10,000 women per year.
Reading these numbers as an individual user
The difference between 5-7 and 9-12 events per 10,000 women per year is real but modest in absolute terms. For a healthy 27-year-old non-smoker with no personal or family thrombosis history, both numbers describe a low individual annual risk. For a 33-year-old with a first-degree family history of unprovoked venous thromboembolism, the arithmetic tilts more clearly in favour of the second-generation option, or of a non-hormonal method entirely.
Every current guideline positions the levonorgestrel-containing pill as the first-choice combined pill within the class specifically because of this venous thromboembolism arithmetic. Yasmin is a reasonable choice when the drospirenone profile fits a specific reason — the anti-mineralocorticoid effect on fluid retention, the anti-androgenic effect on mild acne, established use over several years without problems — that outweighs the venous thromboembolism trade-off.
Dr Lundqvist-Ekstrom on the fourth-generation venous thromboembolism picture
"Nordic cohort data have been consistent for over a decade: drospirenone-containing pills carry a venous thromboembolism risk in the same range as third-generation combinations — higher than levonorgestrel pills, similar to desogestrel or gestodene. The absolute increase is small for healthy young users, but the deliberate choice of a drospirenone pill should be tied to a specific reason for the anti-mineralocorticoid or anti-androgenic profile, not to an assumption that a newer generation is automatically better."
Anders M. Lundqvist-Ekstrom, MD, PhD — Department of Vascular Surgery and Angiology, Uppsala University Hospital
🧂 Anti-Mineralocorticoid Activity — Yasmin's Signature Feature
Drospirenone's anti-mineralocorticoid activity is the single feature that most distinguishes Yasmin from every other combined oral contraceptive on the market. Understanding what this activity is, where it comes from, and what it means practically for the user is worth a few minutes because it explains both the marketed benefits (less fluid retention) and the specific safety consideration (potassium) that this pill carries.
🧂 The aldosterone pathway in plain language
Aldosterone is a hormone made by the adrenal glands that tells the kidneys to hold on to sodium and to excrete potassium. It is the body's main regulator of salt and water balance, and it is sometimes called the "salt hormone". When aldosterone signals strongly, the body retains sodium and water and can shed potassium; when aldosterone is blocked, the reverse happens.
Spironolactone is a diuretic that blocks aldosterone at the kidney tubule receptor, causing loss of sodium and water and retention of potassium; it is used for heart failure, resistant hypertension, and other conditions. Drospirenone shares the same receptor-blocking activity at a much lower potency (roughly one twenty-fifth of spironolactone milligram for milligram). This is the mechanism behind Yasmin's signature anti-mineralocorticoid effect.
What the anti-mineralocorticoid effect does in practice
- Small natriuretic effect: the body loses a little more sodium and water than it would on a typical combined pill. For most users this is subtle and not noticeable on a bathroom scale, but for users who felt persistently bloated on another combined pill it can translate into a subjective sense of "less puffy".
- Blunted fluid-retention side effect: the mild breast fullness and ankle swelling that some users experience on other combined pills during active-pill weeks tend to be less pronounced on Yasmin.
- Reduced weight fluctuation across the pack: the fluid-related weight fluctuation that some users notice between the pack transition and the first active week is often smaller on Yasmin than on a typical combined pill. This is not the same as weight loss — drospirenone does not cause fat loss.
- Small effect on blood pressure: a modest reduction in blood pressure of a few mmHg is observed on average in users starting Yasmin, mostly explained by the natriuretic effect.
The anti-androgenic side of drospirenone is a separate but related feature. By binding to androgen receptors at target tissues (skin, hair follicles) with weak agonist activity but blocking stronger androgens from binding, drospirenone modestly reduces the androgenic effects on skin. Some users notice a small improvement in mild inflammatory acne or in seborrhoeic scalp oiliness within the first three to six months of use. This is not the same as a formal acne treatment: the 24/4 Yaz formulation carries the FDA-approved moderate acne indication, whereas standard Yasmin does not. Users whose primary concern is acne should discuss Yaz or a dedicated acne treatment plan rather than expecting standard Yasmin to serve as a primary acne therapy.
🤔 The signature-feature trade-off
The very same anti-mineralocorticoid activity that reduces fluid retention also creates the specific hyperkalaemia concern discussed in section 14. Section 7 is the "why Yasmin" side of the drospirenone story; section 14 is the "what to watch for" side. Both sections belong to the same molecule and both should be read before deciding whether Yasmin is the right combined pill for the individual user.
▶️ Starting a New Pack Correctly
How Yasmin is started determines how quickly contraceptive coverage is established and whether backup contraception is needed for the first few days. Three starting patterns are used in practice, each with slightly different implications.
▶️ Three ways to start the first Yasmin pack
- Day-1 start
- Take the first active tablet on day one of the natural menstrual period. Contraceptive coverage is immediate; no backup contraception is needed. This is the most straightforward starting pattern.
- Sunday start
- Take the first active tablet on the Sunday following the start of the period, so the withdrawal bleed later falls during the working week rather than the weekend. Backup contraception (a barrier method) is needed for the first seven days.
- Quick start (any day)
- Take the first active tablet on the day of the prescribing appointment, regardless of where the user is in the natural cycle. Backup contraception is needed for the first seven days, and a pregnancy test may be repeated at follow-up to rule out an early pregnancy that would have been present at initiation.
The quick-start option has become widely accepted because it removes the barrier of waiting for the next period. Guidelines from the Faculty of Sexual and Reproductive Healthcare and from the US Centers for Disease Control and Prevention both endorse quick-start prescribing for eligible users, provided pregnancy is not already present.
👉 Choosing a fixed daily time
The exact hour is less important than the fact that it is the same hour every day. Common anchors include:
- With the evening meal, so a partner or housemate can serve as a reminder.
- At bedtime, paired with brushing teeth or setting the alarm.
- First thing in the morning, before the first cup of tea or coffee.
- Immediately after lunch on weekdays, if the morning routine is variable.
Drospirenone's longer half-life (around 30 hours) means Yasmin is slightly more forgiving of a modest timing shift than a progestin with a shorter half-life would be. This does not change the missed-pill rules — the standard seven-day rule applies exactly — but it does mean that a pill taken a couple of hours late is unlikely to have any practical consequence. Consistency remains the goal, however, and building a same-time-every-day habit remains the single most useful contraceptive behaviour on any combined pill.
For subsequent packs, no starting decision is needed — the new pack begins the day after the last placebo tablet (28-day pack) or after the seventh pill-free day (21-day pack), no matter whether a withdrawal bleed is still finishing.
⏰ Missed Pill Rules by Timing
Missed pills are the single most common cause of contraceptive failure with combined oral contraceptives. The rules for Yasmin follow the general framework used across combined pills. Because Yasmin is monophasic, the missed-pill decision does not depend on which specific active tablet was missed — all 21 active tablets contain the same combination.
| Situation | Take the missed pill? | Backup contraception? | Emergency contraception? |
|---|---|---|---|
| 1 active pill missed by any amount up to 48 hours | Yes — take the missed pill as soon as remembered, even if two on one day | Not needed | Not needed |
| 2 or more active pills missed in week 1 (days 1-7) | Take the most recent missed pill; continue the pack | Barrier method for the next 7 days | Consider if unprotected sex occurred in the past 5 days |
| 2 or more active pills missed in week 2 (days 8-14) | Take the most recent missed pill; continue the pack | Barrier method for the next 7 days | Not needed if week 1 was taken correctly |
| 2 or more active pills missed in week 3 (days 15-21) | Take the most recent missed pill; when active pills run out, skip the pill-free interval and start the next pack immediately | Barrier method for the next 7 days | Not needed if weeks 1 and 2 were taken correctly |
| Placebo pills missed (28-day pack, days 22-28) | No action; discard the missed placebo tablet | Not needed | Not needed |
🚩 The single most dangerous missed pill
The first active pill of a new pack, missed after a full seven-day pill-free interval, extends the hormone-free window to eight days or more — enough time for an ovarian follicle to escape suppression. This is the missed pill that most reliably reduces contraceptive coverage on any 21+7 combined pill including Yasmin, and it is the reason the guidance emphasises never extending the pill-free interval beyond seven days. Drospirenone's longer half-life provides no meaningful extra margin here — the rule applies exactly as on any 21+7 combined pill.
Two practical adaptations of these rules are worth building into daily life. First, keeping the pack in the same visible location every day makes the "did I take today's pill" question easier to answer. A partly used pack tells the truth — the empty blister position is a physical record. Second, the pack should be checked against the day of the week or the pack's day marker at least twice a week, so a partial miss does not compound into a full week's error.
If in doubt about your missed-pill status
Take the most recent pill now, use a barrier method for the next seven days, and either read the missed-pill leaflet inside the pack or call the prescriber's office. The decision about emergency contraception is time-limited — the sooner it is discussed, the more options remain.
🛡️ Backup Contraception in the First Seven Days
Backup contraception is a barrier method — typically male condoms — used alongside Yasmin during periods when the pill's contraceptive coverage is not yet fully established or has been reduced by a missed pill, illness, or interaction. This section describes when backup is needed, for how long, and what "seven days" actually means in practice.
🛡️ When backup contraception is needed with Yasmin
| First pack, non-day-1 start (Sunday, quick start) | First 7 days of active pills |
| Missed 2 or more active pills in any week of the pack | Next 7 days from when the pack is corrected |
| Vomiting within 2 hours of an active pill | Retake the pill; add 7 days of backup if absorption is doubtful |
| Severe diarrhoea for more than 24 hours | 7 days of backup after the diarrhoea settles |
| Course of an enzyme-inducing drug (see section 23) | Throughout the course plus at least 28 days after |
| Short course of most antibiotics (non-enzyme-inducing) | Not routinely needed — see section 11 |
The seven days that matter for contraceptive coverage are active-pill days, not calendar days. A user who takes an active pill on Monday, misses two active pills on Tuesday and Wednesday, and takes the correcting pill on Thursday needs to count the next seven days of active pill-taking — Thursday through Wednesday — as the window during which backup contraception is needed, not the seven calendar days ending the following Thursday.
If the seven-day backup window would cross into the pill-free interval
If the seven-day backup window would run into the placebo week or into the pill-free interval, contraceptive coverage may still be reduced during that window. In these situations current guidance is to skip the pill-free interval and start the next pack of active pills immediately, so hormone levels never fall enough to allow ovulation. This applies to Yasmin exactly as it does to any 21+7 combined pill.
Barrier methods are the default choice for backup because they are widely available without a prescription, they do not interact with the hormones, and they can be started and stopped without further planning. Users who prefer to avoid barrier methods can achieve the same purpose by abstaining from vaginal intercourse during the seven days, but that is often impractical and less sustainable than a barrier method.
🔗 Antibiotic and Common Medication Interactions
The question of whether antibiotics reduce Yasmin's effectiveness is one of the most common concerns raised in pharmacies. The evidence is much more reassuring than the once-standard blanket advice suggested. The picture divides into two categories for most medicines: most antibiotics do not reduce contraceptive coverage, and a small group of drugs that induce hepatic enzymes do. On Yasmin specifically, there is an additional category to know about: medicines that raise serum potassium, because drospirenone's anti-mineralocorticoid activity interacts with them in a way no other combined pill does. Potassium-elevating interactions get their own section (14); this section covers everything else.
🔗 Antibiotics and other medicines — sorted by contraceptive relevance
| Category | Examples | Backup contraception? |
|---|---|---|
| Most common antibiotics — no effect on COC | Amoxicillin, penicillin V, cephalosporins, doxycycline, azithromycin, clarithromycin, nitrofurantoin, trimethoprim | Not needed for the antibiotic itself |
| Enzyme-inducing antibiotics — reduce COC effectiveness | Rifampin (rifampicin), rifabutin | Yes — throughout the course plus 28 days after |
| Antifungals — usually no effect | Fluconazole, terbinafine, topical creams | Not needed |
| Antivirals — some reduce COC | Ritonavir-boosted antiretrovirals; certain hepatitis C direct-acting antivirals | Discuss with prescriber; barrier method often added |
| Anticonvulsants — several reduce COC | Phenytoin, phenobarbital, carbamazepine, topiramate at higher doses | Yes — often an alternative contraceptive method is preferred long term |
| Herbal — St John's wort | Widely available over the counter as a mood supplement | Yes — treat as an enzyme inducer |
| Analgesics — no relevant interaction | Paracetamol, ibuprofen, naproxen, low-dose codeine (short courses) | Not needed for contraceptive coverage — but see section 14 for potassium note on chronic NSAID use |
Two features of this list are worth internalising. First, the once-common blanket instruction to use barrier contraception during any course of antibiotics is no longer supported by the evidence and is not part of current WHO or CDC guidance. The mistake was extrapolating rifampin's enzyme induction to unrelated antibiotic classes that do not share the mechanism. Second, enzyme-inducing drugs cause a real reduction in contraceptive coverage that lasts weeks after the drug is stopped, which is why the twenty-eight-day rule after a rifampin course applies even to short exposures.
🔗 A Yasmin-specific pharmacy question
When collecting any new prescription, the useful question to ask the pharmacist on Yasmin is not only "is this drug an enzyme inducer for combined oral contraceptives?" but also "does this drug raise serum potassium?" The second question is specific to drospirenone-containing pills, and it separates the small group of medicines that matter for section 14 from the many that do not.
⚠️ VTE Risk — Fourth-Generation Considerations
Every combined hormonal contraceptive carries an increase in the risk of venous thromboembolism — a blood clot in a deep vein (deep vein thrombosis) or in the pulmonary arteries (pulmonary embolism). For Yasmin specifically, the relevant question is not only how the risk compares with no contraception at all but also how it compares with second-generation levonorgestrel pills, because drospirenone's observed venous thromboembolism signal is consistently higher than the levonorgestrel reference in most cohorts.
⚠️ THE VENOUS THROMBOEMBOLISM ARITHMETIC IN CONTEXT
Non-users of combined oral contraceptives of reproductive age experience roughly 2 venous thromboembolism events per 10,000 women per year. Users of levonorgestrel-containing (second-generation) combined pills experience roughly 5-7 events per 10,000 women per year. Users of drospirenone-containing (fourth-generation) combined pills like Yasmin experience roughly 9-12 events per 10,000 women per year in most cohorts. Users of desogestrel or gestodene (third-generation) combinations experience roughly 9-12 events per 10,000 women per year — broadly the same as drospirenone. Pregnancy itself carries roughly 29 events per 10,000 women per year.
These numbers describe the risk profile at the population level. Individual risk depends on age, weight, smoking status, family history, thrombophilia, immobility, and use of interacting medications. The absolute increase from adding Yasmin to a healthy young non-smoker with no risk factors is very low; the increase from adding Yasmin to a woman with clustered risk factors can be considerably higher.
The relative venous thromboembolism risk of Yasmin compared with a second-generation levonorgestrel pill is estimated at roughly 1.5 to 2 times higher in most observational data. This range has been debated in the literature — some studies place drospirenone closer to levonorgestrel, others closer to desogestrel — but the consensus across FDA, EMA, and independent meta-analyses places drospirenone in the same broad range as third-generation combinations.
⚖️ Individual factors that meaningfully raise venous thromboembolism risk on any combined pill
- The first three months of any combined-pill use (a transient early peak).
- Age above 35, particularly if combined with smoking or high body mass index.
- Body mass index above 30, with the risk increment steepening above 35.
- Prolonged immobility — major surgery, hospitalisation, plaster cast, long-haul travel over four hours.
- Personal history of any venous thromboembolism (an absolute contraindication).
- First-degree family history of unprovoked venous thromboembolism, particularly at a young age.
- Known thrombophilia — Factor V Leiden, prothrombin gene mutation, antiphospholipid syndrome, protein C or S deficiency.
- Inflammatory conditions and some autoimmune diseases in active phase.
Two features of the drospirenone venous thromboembolism picture deserve emphasis. First, the elevated relative risk is a real reason to name the trade-off explicitly when Yasmin is prescribed — the anti-mineralocorticoid or anti-androgenic reasons for choosing this pill should be specific rather than generic. Second, long-haul air travel of more than four hours combined with combined-pill use produces an additive effect on clotting risk, particularly during the first year of use. Practical mitigation includes regular hourly movement around the cabin, well-hydrated water intake, graduated compression stockings for flights over six hours, and avoidance of alcohol during and after the flight.
Users planning major elective surgery should discuss combined-pill use with the surgical team well in advance, because most guidelines recommend stopping the combined pill four to six weeks before elective major surgery.
🚨 Warning Signs — Stop and Seek Care
Section 12 spelled out the arithmetic. This section is the practical warning-signs list — the collection of symptoms that, in a Yasmin user, should trigger an immediate call to a clinician or a same-day visit to urgent care rather than a wait-and-see approach. Because Yasmin sits in the fourth-generation category with a modestly higher venous thromboembolism risk than levonorgestrel-containing combined pills, the warning-signs conversation carries even more practical weight than on a lower-risk pill.
🚨 STOP TAKING YASMIN AND SEEK URGENT MEDICAL CARE IF YOU HAVE ANY OF THESE SIGNS
| A — Abdominal pain | Severe upper abdominal pain, particularly on the right side, or persistent pain that does not settle — possible liver or gallbladder cause |
| C — Chest pain | New chest pain, especially if sharp and worse on breathing in, or combined with breathlessness — possible pulmonary embolism |
| H — Headache | New severe headache, particularly with visual disturbance, one-sided weakness, or speech change — possible stroke or migraine with aura |
| E — Eye problems | Sudden partial or complete loss of vision, double vision, or a new visual field cut — possible retinal vein thrombosis or stroke |
| S — Severe leg pain | Unilateral calf or thigh pain, swelling, warmth, or persistent cramp without injury — possible deep vein thrombosis |
Five categories — abdomen, chest, head, eye, severe leg — do not require memorising individual case descriptions. If a symptom falls into any of the five and it is new, severe, and unexplained, that is enough to stop the pill and seek same-day medical attention. Waiting until the next scheduled appointment is not the right response to any of the signs on the list.
Additional warning signs beyond the ACHES mnemonic
- Jaundice — yellowing of the skin or the whites of the eyes, with or without dark urine, pale stools, or right upper abdominal discomfort.
- New unilateral numbness or weakness in the face, arm, or leg — possible stroke; the "FAST" acronym (face droop, arm weakness, speech difficulty, time to call for help) applies here.
- Fainting or collapse without a clear vasovagal trigger — possible large pulmonary embolism or arrhythmia.
- Sudden new migraine with aura in a user who has not previously had aura — a specific reason to stop the combined pill until reviewed (see section 21).
- Rapidly worsening high blood pressure found on an incidental check — needs same-day review, not next-visit.
- Symptoms of high potassium — unusual muscle weakness, palpitations, or an irregular heartbeat, particularly in a user also on ACE inhibitors, potassium-sparing diuretics, or chronic NSAIDs (see section 14).
Because Yasmin sits in the fourth-generation venous thromboembolism range, users and family members who understand the warning-signs list add a second pair of eyes that has caught late-recognised deep vein thromboses in more than one case series. This is not a reason for anxiety; it is a reason for prepared awareness.
🍌 Potassium Precautions — Unique to Drospirenone
Drospirenone's anti-mineralocorticoid activity is the same feature that reduces fluid retention (section 7) and the same feature that creates a specific concern about serum potassium when Yasmin is combined with other medicines that raise potassium. This section is unique to drospirenone-containing pills; no other combined oral contraceptive carries this precaution, and it is one of the most important pharmacy-conversation topics on Yasmin.
🍌 The pharmacology in plain language
Aldosterone tells the kidneys to hold on to sodium and to excrete potassium. Drospirenone partially blocks aldosterone at the kidney receptor, so the body loses a little more sodium and water and holds on to a little more potassium than it would otherwise. In a healthy young user this rarely produces a clinically important rise in serum potassium; the daily fluctuation of potassium in food and diet swamps the drospirenone effect.
The picture is different when drospirenone is combined with other medicines that also raise potassium. Adding drospirenone to an ACE inhibitor or a potassium-sparing diuretic can push serum potassium above the normal range, producing hyperkalaemia. The mechanism is additive rather than complicated: two potassium-elevating drugs together do more than either alone.
🚩 POTASSIUM-ELEVATING MEDICINES THAT INTERACT WITH YASMIN
| Category | Examples | Practical implication |
|---|---|---|
| ACE inhibitors | Lisinopril, ramipril, enalapril, captopril | Check serum potassium at initiation and periodically; consider alternative COC if reliance on the ACE inhibitor is long-term |
| Angiotensin receptor blockers | Losartan, valsartan, candesartan, telmisartan | Same considerations as ACE inhibitors |
| Potassium-sparing diuretics | Spironolactone, eplerenone, amiloride, triamterene | Combination generally avoided; if unavoidable, close potassium monitoring and often a switch to a non-drospirenone COC |
| Chronic NSAIDs at anti-inflammatory doses | Diclofenac, ibuprofen at chronic high doses, naproxen at chronic doses | Short courses of over-the-counter NSAIDs are fine; chronic anti-inflammatory use warrants potassium monitoring |
| Potassium supplements | Prescription potassium chloride, salt substitutes rich in potassium | Generally avoided in combination unless clinically indicated with monitoring |
| Aldosterone antagonists at any dose | Spironolactone, eplerenone | Direct pharmacological overlap; a different COC is usually chosen |
Two features of the potassium picture are worth understanding rather than reading past. First, the concern is real but manageable: most users of Yasmin who happen to take an ACE inhibitor for hypertension can continue both medicines safely if serum potassium is measured at initiation and at a follow-up check a few weeks later. The concern is not that hyperkalaemia is common; it is that it is uncommon but not-zero, and it is preventable by measurement. Second, the concern is specific to drospirenone: no other combined oral contraceptive raises this issue. A switch from Yasmin to a levonorgestrel pill removes the potassium consideration entirely.
Practical monitoring rules on Yasmin
- Check serum potassium at initiation in any user also taking one of the medicines in the table above.
- Repeat serum potassium at 4-6 weeks to confirm stability.
- Repeat at annual review if the combination is continued.
- Do not routinely check serum potassium in a healthy young user on no potassium-elevating medicines; the drospirenone effect on its own is not clinically important.
- Warn the user about symptoms of high potassium: unusual muscle weakness, palpitations, an irregular heartbeat — and about the need for a same-day check if any of these appear.
Dr Weinberger-Holbach on the potassium conversation
"The single most useful conversation to have with a new user of Yasmin who is also on an ACE inhibitor is a plain one: this combination is usually fine, but it deserves a baseline potassium check and a repeat a few weeks later. Doing that quiet monitoring pre-empts the small proportion of users who would otherwise develop hyperkalaemia and lets everyone else stay comfortably on the pill they chose."
Constanze J. Weinberger-Holbach, MD, PhD — Department of Dermatology and Endocrinology, Charite — Universitatsmedizin Berlin
🫀 Cardiovascular Risk Factor Assessment
Combined oral contraceptives raise the risk of arterial events — myocardial infarction and ischaemic stroke — when other cardiovascular risk factors are already present. In a healthy young non-smoker without hypertension or diabetes, the absolute increase in arterial risk from Yasmin is very small. In a woman with clustering risk factors, the arithmetic shifts, and the eligibility criteria reflect that reality.
🫀 The six cardiovascular risk factors that matter most
- Hypertension. Well-controlled blood pressure under treatment is acceptable in many cases; uncontrolled hypertension — consistently above 160/100 mmHg — is a strong reason to avoid any combined pill. On Yasmin specifically, the drospirenone-related modest blood-pressure-lowering effect can slightly mask hypertension trends; annual measurement is essential.
- Diabetes with vascular complications. Uncomplicated diabetes is often compatible with combined pills; established retinopathy, neuropathy, or nephropathy tilts the balance the other way.
- Dyslipidaemia. Severe dyslipidaemia with elevated LDL cholesterol or triglycerides — especially if familial — is a reason for caution.
- Age above 35. Arterial risk from combined pills climbs with age; the 35-year threshold appears repeatedly in eligibility criteria for combinations with other factors.
- Smoking. The single strongest interacting factor; discussed in its own section.
- Obesity. Body mass index above 35 is a stronger caution; between 30 and 35 the balance depends on other factors present.
The WHO Medical Eligibility Criteria for Contraceptive Use grade combined hormonal contraceptives across these variables using categories 1 (no restriction) through 4 (unacceptable health risk). A single well-controlled risk factor most often lands in category 2 or 3 depending on severity; the clustering of two or more risk factors most often pushes the picture into category 4, where a combined pill is not recommended.
Baseline checks at the prescribing appointment
- Blood pressure measurement; combined pills should not be started when blood pressure is uncontrolled.
- Body mass index calculation.
- Smoking status and quantity per day.
- Personal and first-degree family history of venous or arterial thromboembolism.
- Migraine history — specifically whether aura is present.
- Diabetes duration and current control (HbA1c), if relevant.
- Baseline serum potassium in any user also taking an ACE inhibitor, angiotensin receptor blocker, potassium-sparing diuretic, or chronic NSAID (see section 14).
Because Yasmin is a fourth-generation combined pill, the cardiovascular risk-factor conversation deserves an additional layer. Users who could reasonably use a second-generation levonorgestrel-containing pill should discuss whether the reasons for choosing Yasmin specifically (the anti-mineralocorticoid effect on fluid retention, the anti-androgenic effect on mild acne) outweigh the modest venous thromboembolism increment. If the answer is yes, standard cardiovascular monitoring continues. If the answer is not clearly yes, the second-generation option is often the more conservative choice.
🚬 Smoking, Age 35, and the Contraindication Line
The interaction between smoking and combined oral contraceptives is the single most consistent contraindication across every current guideline. Cigarette smoke raises baseline arterial thrombosis risk on its own, combined pills raise arterial thrombosis risk on their own, and the two effects together produce a substantially larger increase than either would alone. The specific rule that every prescriber applies is the age-35 cutoff.
🚬 AGE 35 + SMOKING = CONTRAINDICATED
A woman aged 35 or older who smokes 15 or more cigarettes per day should not use combined hormonal contraceptives, including Yasmin. This is WHO Medical Eligibility Category 4 — an unacceptable health risk. A woman aged 35 or older who smokes fewer than 15 cigarettes per day is Category 3, meaning combined pills are generally not recommended unless no alternative works and the clinical judgement is documented explicitly. A woman under 35 who smokes has an increased risk while on a combined pill but is not automatically contraindicated.
The 35-year threshold is not a physiological cliff — the risk climbs gradually with age and the number of cigarettes smoked — but it is the point at which observational cohort data show that the absolute risk of myocardial infarction and ischaemic stroke rises to a level that regulators and eligibility panels have agreed is unacceptable in the presence of a modifiable exposure.
Smoking, age, and combined pill eligibility (WHO MEC categories)
| Age band | Non-smoker | <15 cigarettes/day | ≥15 cigarettes/day |
|---|---|---|---|
| Under 35 | Category 1 — no restriction | Category 2 — advantages outweigh risks | Category 2 — advantages outweigh risks |
| 35 and older | Category 2 (with attention to other risk factors) | Category 3 — risks generally outweigh advantages | Category 4 — unacceptable health risk |
Two clinical practices sit alongside the eligibility table. First, a smoker of any age starting combined contraception should be offered smoking-cessation support at the same appointment. Second, a user who reaches 35 while already on Yasmin should have the smoking-and-age conversation moved to the top of the next routine review, whether or not she has explicitly asked about switching.
🤔 Alternatives for smokers over 35
Progestin-only pills, the progestin-releasing intrauterine device, the copper intrauterine device, and the contraceptive implant do not carry the same smoking-age interaction. Any of these is a suitable substitute for a smoker over 35 who wants ongoing effective contraception without the combined-pill risk profile. Users who chose Yasmin for the anti-mineralocorticoid benefit will lose that specific benefit on any of these switches.
Body weight adds a separate factor to the calculus. Body mass index above 35 combined with age above 35 pushes eligibility into category 3 or 4 depending on the exact BMI and on the presence of other factors.
🩹 Common Side Effects in the First Three Months
Most common Yasmin side effects appear in the first three months, are mild, and settle without intervention as the body adjusts to a steady daily hormone exposure. This section describes the frequency and shape of these early effects and separates them from the rare but serious reactions that were covered in sections 12 and 13. Because drospirenone has anti-mineralocorticoid and anti-androgenic activity, the side-effect profile of Yasmin differs subtly from other combined pills.
🩹 Early side effects — typical pattern by month
| System | Common in month 1 | Typical by month 4 |
|---|---|---|
| Menstrual | Breakthrough bleeding, spotting, unpredictable withdrawal bleed | Regular, moderate withdrawal bleed; spotting typically resolves |
| Breast | Tenderness, sensitivity, mild fullness — often less pronounced than on other COCs due to anti-mineralocorticoid effect | Settles for most users |
| Digestive | Nausea, occasional bloating (less than on other COCs), mild appetite change | Nausea typically settles within 6-8 weeks |
| Head | Mild headache, particularly in the first pack cycle | Resolves; persistent or worsening headache warrants review |
| Skin | Some improvement in mild inflammatory acne due to anti-androgenic effect; a minority notice new pigmentation | Net skin improvement in a majority of users with pre-existing mild acne |
| Mood | Minor mood shifts or premenstrual pattern change; drospirenone may modestly improve premenstrual mood in some users | Settles for most; new persistent low mood needs review |
| Weight and fluid retention | Fluid retention typically less than on other COCs; some users notice slightly reduced weight fluctuation | No clinically significant sustained weight gain in systematic reviews |
Two features of Yasmin-specific side effects are worth naming. First, the estrogen-related early effects (breast tenderness, nausea, bloating) tend to be subtly milder than on other combined pills at the same 30 mcg estrogen dose because drospirenone's anti-mineralocorticoid activity offsets some of the fluid-retention component. Second, the anti-androgenic activity produces modest incidental acne improvement for users with pre-existing mild inflammatory acne — not a formal treatment effect, but a noticeable secondary benefit.
🚩 Rare but serious — the reactions covered earlier
The rare and serious reactions do not appear on the common side-effect list above because they are qualitatively different. They belong to the warning-signs framework of section 13 and the venous thromboembolism content of section 12. The full list, in summary form:
- Venous thromboembolism — leg or lung clot
- Arterial thromboembolism — heart attack or stroke
- Retinal vein thrombosis — sudden vision loss
- Severe hypertension
- Hepatic adenoma or worsening liver function
- Severe hypersensitivity reactions
- Symptomatic hyperkalaemia (see section 14)
A user who has been on Yasmin for six months without significant side effects and without any of the warning signs has, for practical purposes, established that the combination suits her. The routine annual review from that point is about picking up new factors — a new hypertension diagnosis, a change in smoking status, a change in migraine pattern, a new prescription for a potassium-elevating medicine — rather than about revisiting side effects that have already declared themselves.
💧 Breakthrough Bleeding Management
Breakthrough bleeding is unscheduled bleeding or spotting during the active-pill weeks of the pack, when a user would normally expect no bleed. It is common in the first three pack cycles, becomes less common through months four to six, and is uncommon in an established user. On Yasmin's 30 mcg estrogen formulation, breakthrough bleeding tends to be similar in frequency to other 30 mcg pills and somewhat less common than on ultra-low-dose 20 mcg formulations.
💧 Breakthrough bleeding — frequency by month of use
| Month 1 | Occurs in a substantial minority of new users; usually light spotting or brown discharge for several days |
| Month 2-3 | Frequency drops noticeably; episodes shorter and less intrusive |
| Month 4-6 | Most users settled into a predictable pattern with clean active-pill weeks |
| After 6 months | Persistent breakthrough bleeding is worth a clinical review; new-onset bleeding after a stable period particularly so |
The mechanism behind early breakthrough bleeding is straightforward. A steady combined-pill exposure keeps the endometrium in a thin, quiet state, but the first cycles are a transition from natural hormonal fluctuations to that steady state. During the transition, small areas of endometrium can shed asynchronously and produce spotting. Once the endometrium has fully adjusted, this stops.
If breakthrough bleeding continues past month 3 on Yasmin
- Check pill-taking reliability. Occasional missed pills or delayed doses are the most common single cause of persistent breakthrough bleeding.
- Consider recent illness or medication. A course of an enzyme inducer, a bout of vomiting, or persistent gastrointestinal upset can all cause bleeding through reduced hormone absorption.
- Rule out an unrelated cause. Cervical infection, chlamydia in particular, can present with post-coital or intermenstrual bleeding.
- Discuss with the prescriber. A switch to a different combined pill sometimes resolves persistent spotting; on Yasmin, options include a levonorgestrel-based pill or the Yaz variant with its shortened hormone-free interval.
Dr Mikkelsen-Aabo on troubleshooting persistent spotting
"When a patient returns at month three still spotting on Yasmin, the first two questions are always about pill-taking consistency and absorption. If both are unremarkable, the drospirenone progestin is not usually the problem to change — a switch to a shortened hormone-free interval regimen or to a different estrogen dose is more likely to resolve the pattern than a change of progestin family."
Signe R. Mikkelsen-Aabo, MD, MPH — Department of Public Health and Family Medicine, Aarhus University
Absence of a withdrawal bleed during the pill-free interval is a separate pattern to interpret. If a user has taken every pill correctly and no bleed occurs during the placebo week, the most likely explanation is a very thin endometrium producing a light or absent bleed rather than pregnancy. Two consecutive missed withdrawal bleeds, or an absent withdrawal bleed in a user who has recently missed active pills, is a reason to take a pregnancy test before starting the next pack.
🧠 Mood, Libido, and Skin Effects
Mood, libido, and skin are three effect areas where combined oral contraceptives generate the most controversy in patient conversations. On Yasmin specifically, drospirenone's anti-androgenic and anti-mineralocorticoid activities produce a somewhat different profile in each of these three areas than a levonorgestrel-based pill would produce.
🧠 Three effect areas — the honest picture on Yasmin
- Mood
- Placebo-controlled trials show a small overall effect of combined pills on mood scores across the population. On Yasmin, some users report modest improvement in premenstrual mood symptoms during the days before the placebo week, attributed to drospirenone's hormonal profile. The 24/4 Yaz formulation carries a formal PMDD indication based on this pattern; standard Yasmin does not, but the incidental benefit is real for some users. Women with a history of depression are somewhat more likely to notice a mood shift on starting or stopping any combined pill.
- Libido
- The average effect on libido across trial populations is small and near zero, but individual users report noticeable changes in either direction. Reduced libido reported by an individual user is a real finding worth taking seriously, and if it persists past month four it is a reasonable reason to consider a switch of method.
- Skin
- Drospirenone's anti-androgenic activity produces a modest skin benefit for many users: reduced oiliness and mild inflammatory acne improvement over three to six months. This is not the same as a formal acne treatment; the Yaz formulation carries the FDA-approved moderate acne indication, whereas standard Yasmin delivers an incidental benefit rather than a licensed effect. Users with severe or scarring acne should be seen in dermatology alongside any combined-pill decision.
The gap between individual experience and average trial data is where a lot of the confusion around these three areas comes from. When someone describes a clear mood or libido effect, that experience is not made less real by the fact that the average across many users is small. What the average does tell us is that switching from Yasmin to a levonorgestrel pill removes the drospirenone-specific mood and skin effects (both the incidental benefits and any drospirenone-attributable changes) while keeping the same 30 mcg estrogen exposure.
When to consider a change
A mood, libido, or skin effect that is clearly worse than baseline, persistent past month four, and disruptive to normal life is a reasonable reason to review the method with a prescriber. On Yasmin specifically, one option to consider is a switch to a levonorgestrel-based pill at the same 30 mcg estrogen dose, which changes only the progestin. If the incidental drospirenone benefits (mood, skin) mattered, this switch may reduce those; if drospirenone was the source of an unwanted effect, this switch may resolve it. A written note tracking symptoms across the pack cycle often clarifies whether the pattern is drug-linked or coincidental.
Users who started Yasmin specifically for the incidental mood or skin benefits should give the pill at least three to six months before judging the effect. Both effects emerge gradually rather than immediately.
✨ Non-Contraceptive Benefits Including PMS
Yasmin's primary purpose is contraception, but drospirenone-containing combined pills produce a range of non-contraceptive effects that are, on balance, favourable for many users. This section catalogues those effects honestly, because some of them are legitimate reasons on their own to choose Yasmin over a non-hormonal method even when contraception is not the dominant driver. Yasmin's non-contraceptive profile is subtly different from other combined pills because of the drospirenone-specific activities.
✨ The non-contraceptive benefits of Yasmin
| Effect | What it looks like in practice | Time frame |
|---|---|---|
| Cycle regulation | Predictable, moderate withdrawal bleeds; end of guessing about period timing | From the first pack for most users |
| Menstrual pain reduction | Substantial reduction in dysmenorrhoea; often the first thing users notice | From the first or second cycle |
| Reduced fluid retention (drospirenone-specific) | Less bloating and breast fullness than on other COCs; subjective sense of "less puffy" | Visible from cycle 1-2 |
| Mild acne improvement (drospirenone-specific) | Anti-androgenic effect reduces sebum production; benefit visible over 3-6 months | Emerges by month 3-4 |
| PMS symptom reduction (incidental) | Milder premenstrual symptoms in some users; the 24/4 Yaz formulation is the licensed choice for PMDD specifically | Emerges over the first 3-6 months |
| Menstrual blood-loss reduction | Lighter bleeds; useful in heavy menstrual bleeding not caused by structural pathology | Established by month 3 |
| Endometrial cancer risk reduction | Substantial and durable reduction that persists for decades after stopping | Detectable after roughly 1 year of use; deepens with longer use |
| Ovarian cancer risk reduction | Meaningful and durable reduction that persists for decades after stopping | Detectable after roughly 1 year of use; deepens with longer use |
| Ovarian cyst suppression | Reduced formation of functional ovarian cysts through ovulation suppression | Immediate once ovulation is suppressed |
The endometrial and ovarian cancer risk reductions deserve particular emphasis because they are among the strongest and most durable effects a common medicine produces on a common cancer. The reduction in ovarian cancer risk with several years of combined-pill use is substantial, appears in every major long-term cohort, and does not disappear when the pill is stopped — it persists for decades. For users with a family history of ovarian cancer or with confirmed BRCA1 or BRCA2 pathogenic variants who have not chosen surgical prevention, this specific non-contraceptive benefit sometimes tips the risk-benefit balance in favour of continued combined-pill use.
Non-contraceptive uses where Yasmin specifically earns its place
- A user with troublesome fluid retention or bloating on a levonorgestrel-based pill who benefits from drospirenone's anti-mineralocorticoid effect.
- A user with mild inflammatory acne who wants the incidental anti-androgenic benefit alongside contraception (the 24/4 Yaz formulation is the choice for a formal acne indication).
- A user with premenstrual symptoms severe enough to want a hormonal option but not disabling enough to warrant the Yaz variant with its PMDD indication.
- A user with a first-degree family history of ovarian cancer and no fertility plans in the near term.
These non-contraceptive benefits do not reverse the risk profile discussed in earlier sections. Cardiovascular and thrombosis risks still apply, the fourth-generation venous thromboembolism increment still applies, and the potassium precautions of section 14 still apply.
🌀 Menstrual Migraine and Aura
Migraine and combined hormonal contraception have an interaction that every prescriber checks carefully at initiation and every user should understand at the level of the practical rule. The rule turns on whether the migraine has aura — a specific set of visual, sensory, or speech disturbances that precede or accompany the headache. Migraine with aura and combined pills together produce an increase in ischaemic stroke risk that regulators and eligibility panels have agreed is unacceptable in almost every case.
🌀 MIGRAINE WITH AURA + COMBINED ORAL CONTRACEPTIVE = CONTRAINDICATED
A user of any age who experiences migraine with aura should not take Yasmin or any other combined hormonal contraceptive. This is WHO Medical Eligibility Category 4. A new episode of migraine with aura in an established Yasmin user is a reason to stop the pill and switch method promptly. Progestin-only methods, the copper intrauterine device, and the levonorgestrel-releasing intrauterine device do not carry the same interaction and are the standard alternatives.
How to tell aura from other headache symptoms
- Typical aura features
- Visual disturbance is the most common form: shimmering zigzag lines, a growing blind spot, flashing lights, or a temporary partial field defect. Sensory aura involves progressive tingling or numbness of the face or hand. Language aura involves difficulty finding words. Aura develops gradually over 5-30 minutes and typically lasts less than an hour.
- Not aura
- A dull pre-headache tiredness or sensitivity to light without a specific neurological pattern is not aura. Photophobia during the headache itself is not aura. Nausea before or during the headache is not aura.
- Sudden and severe — not a routine aura
- A sudden onset of severe headache, particularly with new neurological signs, is a warning of a stroke or bleed and needs emergency care regardless of the underlying diagnosis.
Migraine without aura sits in a more nuanced eligibility position. A user under 35 with migraine without aura and no other cardiovascular risk factors can usually take Yasmin, monitored for change in headache pattern. A user over 35 with migraine without aura is often Category 3 (risks generally outweigh advantages) or Category 4 depending on other factors. Any change in headache pattern — new aura, more frequent attacks, longer attacks — is a reason to reassess.
Menstrual migraine and the placebo week on Yasmin
Some users experience a headache pattern that clusters in the placebo week of Yasmin, driven by the sharp fall in estrogen when active pills stop. If this pattern is disruptive and does not involve aura, current practice is not necessarily to abandon the combined pill — a shortened pill-free interval, continuous pill-taking without a break, or a switch to the 24/4 Yaz variant (which uses only 4 hormone-free days) can smooth the estrogen fluctuation. This decision is made with the prescriber, and the migraine-without-aura eligibility rules above still apply.
The overall picture: migraine matters for combined-pill decisions, migraine with aura is a hard stop, and any user of Yasmin who develops a new aura pattern should stop the pill and contact the prescriber the same day. Progestin-only methods and non-hormonal methods remain available.
🎗️ Cancer Risk — The Balanced Picture
The cancer conversation around combined oral contraceptives is where partial headlines have caused the most confusion. The honest picture involves modest increases in some cancers, substantial decreases in others, and a net balance that turns out to be broadly neutral or slightly favourable for most users when totalled across a lifetime. This section presents the picture site-by-site.
| Cancer site | Direction of effect | Persistence after stopping |
|---|---|---|
| Breast | Modest transient increase during current or recent use; pooled analyses estimate the risk rises slightly and fades over the years after stopping | Elevated risk fades within roughly 10 years of stopping |
| Cervical | Small increase with long-term use; mediated by persistent human papillomavirus infection rather than by the hormones directly | Elevated risk fades over roughly 10 years after stopping |
| Endometrial | Substantial reduction that deepens with longer duration of use | Protection persists for 30 years or more after stopping |
| Ovarian | Substantial reduction including for high-risk subgroups such as BRCA1 pathogenic-variant carriers | Protection persists for 30 years or more after stopping |
| Colorectal | Modest reduction in observational cohorts; the mechanism is not fully understood | Effect persists after stopping |
| Hepatocellular | Small increased risk of hepatic adenoma (benign) and possibly hepatocellular carcinoma with very long-term use; uncommon in absolute terms | Data on persistence after stopping are limited |
The framing that matters at the individual level is that the two most substantial effects are in opposite directions. The transient increase in breast cancer risk during current use is real but small in absolute terms, and it fades after stopping. The reduction in ovarian and endometrial cancer risk is both larger in relative terms and remarkably durable, lasting for decades after the last pill is taken. For most users, integrated across a lifetime, the arithmetic is not adverse.
🎗️ How the cancer picture usually shapes the decision
- A first-degree family history of breast cancer or a known BRCA1 or BRCA2 pathogenic variant deserves a specific discussion at prescribing; combined pills are not automatically ruled out but they are not the default.
- A first-degree family history of ovarian cancer often tilts the balance towards combined pills, because ovarian cancer risk reduction is one of the strongest effects and it applies to high-risk carriers as well.
- Established cervical dysplasia does not itself contraindicate combined pills, but human-papillomavirus screening and cervical cytology remain important on schedule.
- Known hepatic adenoma, active hepatitis, or severe liver dysfunction is a contraindication in itself.
Whether the choice within the combined-pill class is a fourth-generation drospirenone combination like Yasmin or a second-generation levonorgestrel-containing pill does not meaningfully change the cancer picture in observational cohorts. The site-by-site pattern above applies to combined oral contraceptives as a class.
🧪 Enzyme Inducers That Reduce Efficacy
Enzyme-inducing drugs are the small group of medicines that meaningfully reduce combined-pill effectiveness by speeding up the hepatic metabolism of both hormones. Section 11 introduced them in the context of antibiotic interactions; this section covers the full list and the practical implication that hormonal contraception may not be the right method during a course of an inducer.
🧪 The enzyme-inducing drugs that matter for Yasmin
| Category | Common examples | Contraceptive implication |
|---|---|---|
| Antimycobacterials | Rifampin (rifampicin), rifabutin | Strong inducers; combined pills should not be relied on during use and for 28 days after |
| Anticonvulsants | Phenytoin, phenobarbital, carbamazepine, primidone, oxcarbazepine, topiramate at doses above 200 mg/day | Strong inducers; combined pills are often unsuitable long-term; alternative methods preferred |
| Antiretrovirals | Efavirenz, nevirapine, ritonavir-boosted protease inhibitors (selected agents) | Variable; specialist HIV pharmacy input is standard, and non-hormonal methods are often preferred |
| Antifungals | Griseofulvin (older agent, still occasionally used) | Mild inducer; short courses are usually manageable with barrier backup |
| Herbal supplements | St John's wort (Hypericum perforatum) | Moderate inducer; widely available over the counter and often not disclosed to prescribers |
| Pulmonary hypertension agent | Bosentan | Moderate inducer; alternative methods usually chosen |
The 28-day rule after stopping a strong inducer reflects the time required for hepatic enzyme activity to return to baseline. Enzyme induction is a slow-onset, slow-offset phenomenon: it takes about a week to build up after starting the inducer, and it takes about four weeks to fade after stopping. During that fade, contraceptive coverage is still reduced even though the inducing drug is no longer being taken.
Options during a course of a strong inducer
- Add a barrier method throughout the course of the inducer plus 28 days after; the simplest short-course option for a brief exposure.
- Switch temporarily to a non-hormonal method such as the copper intrauterine device; the most reliable option for a longer inducer course.
- Switch permanently to a non-affected method such as a copper IUD or the levonorgestrel-releasing IUD; typically the right choice when the inducer is expected to be taken long-term. Users who chose Yasmin for the anti-mineralocorticoid or anti-androgenic benefit will lose those specific benefits on any of these switches.
- Higher-dose combined pill: not a routine primary-care option; do not adjust the Yasmin dose without a prescriber's explicit instruction.
Users who take herbal or over-the-counter products should disclose them at the prescribing appointment. St John's wort in particular is often taken as a mood supplement without any conscious link to hormonal contraception, and its induction effect has been documented in pharmacokinetic studies. The right response is not always to stop the supplement — sometimes it matters more to the user than the pill does — but the choice should be made with the reduced contraceptive coverage understood.
🚽 Vomiting and Diarrhoea Handling
Vomiting and diarrhoea interrupt combined-pill absorption and can reduce contraceptive coverage the same way a missed pill would. The rules for handling gastrointestinal upset on Yasmin are specific and worth committing to memory before an illness happens, because acting quickly during the illness is what preserves contraceptive coverage.
🚽 Vomiting rules — the two-hour window
- Vomiting within 2 hours of taking an active pill: the pill has probably not been absorbed. Take a replacement active pill from the next unused slot as soon as the vomiting settles. Continue the rest of the pack as scheduled.
- Vomiting more than 2 hours after taking an active pill: the pill has probably been absorbed. No replacement needed. Take the next scheduled pill at the normal time.
- Repeated vomiting over more than 24 hours: treat every episode as a potentially missed pill. Retake pills when possible, and add barrier contraception for 7 days after the vomiting settles.
- Vomiting during the placebo week (28-day pack): no contraceptive coverage impact; do not replace.
- If replacement pills are running short: a call to the pharmacy or prescriber for an early repeat prescription is reasonable rather than skipping doses.
The two-hour window is a pragmatic rule, not a physiological cliff. Both drospirenone and ethinyl estradiol are largely absorbed in the small intestine within the first hour or two after an oral dose. A pill vomited up ninety minutes later is a genuine grey zone, and the safer default in that zone is to take a replacement, on the principle that an extra pill does no harm while a missed one might.
Diarrhoea rules
- Mild diarrhoea: a few loose stools during the day, no dehydration, no impact on general wellbeing. Contraceptive coverage is not usually affected. Continue as normal.
- Severe diarrhoea lasting more than 24 hours: treat the same way as repeated vomiting. Continue taking pills but add barrier contraception until diarrhoea has settled and for the next 7 active pill days.
- Persistent diarrhoea over several days: discuss with the prescriber before assuming contraceptive coverage is intact; sometimes a switch to a temporary non-hormonal method is the pragmatic answer until the underlying cause is treated.
A specific edge case is chronic gastrointestinal disease with recurrent flares. Crohns disease, ulcerative colitis, and coeliac disease can produce periods of reduced absorption that overlap with the daily pill routine. Users with any of these conditions should discuss the reliability of oral contraception with the prescribing team, and long-acting methods that do not depend on daily absorption are often the more sustainable choice.
Drospirenone half-life consideration
Drospirenone's longer plasma half-life (around 30 hours) provides a modest cushion against a single missed or partially absorbed dose. This is not a reason to relax the standard rules — the seven-day backup applies exactly as on any combined pill — but it does mean the arithmetic is slightly more forgiving in absolute terms after a single vomiting episode during an illness.
🚫 Absolute and Relative Contraindications
Contraindications to Yasmin are grouped by whether they represent an absolute stop (no combined pill under any circumstances) or a relative caution (combined pill may still be reasonable after specific consideration and monitoring). The list draws directly on WHO Medical Eligibility Criteria for Contraceptive Use categories 3 and 4 and reflects consensus across international guidelines. Yasmin carries several additional considerations specific to the drospirenone-related potassium and anti-mineralocorticoid profile.
🚫 ABSOLUTE CONTRAINDICATIONS (WHO CATEGORY 4)
- Current or past venous thromboembolism (deep vein thrombosis, pulmonary embolism).
- Known thrombophilia (Factor V Leiden, prothrombin gene mutation, antiphospholipid syndrome, protein C or S deficiency).
- Current or past ischaemic heart disease, cerebrovascular accident, or peripheral arterial disease.
- Migraine with aura at any age.
- Severe (Category 4) hypertension — systolic 160 mmHg or higher, or diastolic 100 mmHg or higher.
- Smoking of 15 or more cigarettes per day in a woman aged 35 or older.
- Current breast cancer.
- Severe hepatic decompensation, active viral hepatitis, or hepatic adenoma.
- Complicated diabetes with retinopathy, nephropathy, neuropathy, or duration over 20 years.
- Major surgery with prolonged immobilisation (within the four weeks before or the two weeks after).
- Less than 21 days postpartum in a breastfeeding user, or less than 6 weeks in a non-breastfeeding user with any additional risk factor.
- Known or suspected pregnancy.
- Yasmin-specific: Adrenal insufficiency (drospirenone's anti-mineralocorticoid activity is a concern in this context).
- Yasmin-specific: Severe kidney impairment (creatinine clearance below 30 mL/min).
Absolute contraindications are not negotiations. Any of the items above means an alternative method — progestin-only pill, progestin-releasing intrauterine device, copper intrauterine device, contraceptive implant, injectable progestin, or a non-hormonal method — is the correct choice. None of the alternatives replicate every effect of Yasmin exactly, and specifically none carry the anti-mineralocorticoid activity; users switching for a contraindication that has emerged may notice the return of fluid retention that had been reduced on drospirenone.
❗ RELATIVE CONTRAINDICATIONS AND CAUTIONS (CATEGORY 3, SOME CATEGORY 2)
| Age 35 or older + fewer than 15 cigarettes/day | Combined pill generally not recommended unless no alternative works and the choice is documented |
| Migraine without aura in a user 35 or older | Continuation of an established pill may be acceptable; new initiation is generally avoided |
| Adequately controlled hypertension on treatment | Case-by-case consideration; blood pressure must be truly under target and monitored |
| Body mass index between 30 and 34.9 | Advantages generally outweigh risks; above 35 the balance shifts |
| Family history of unprovoked venous thromboembolism in first-degree relatives | Thrombophilia screening usually offered before a decision; a second-generation pill is often preferred over a fourth-generation option like Yasmin in this specific setting |
| Past breast cancer, disease-free for 5 or more years | Combined pill generally not recommended; alternatives strongly preferred |
| Established use of an enzyme-inducing drug | Combined pill efficacy is reduced; a non-affected method is usually chosen (see section 23) |
| Yasmin-specific: Concurrent use of ACE inhibitors, ARBs, potassium-sparing diuretics, or chronic NSAIDs | Baseline and follow-up serum potassium monitoring required; a non-drospirenone COC may be preferable |
Two contraindications are frequently misunderstood and are worth explicit correction. Kidney impairment at end-stage requiring dialysis is an absolute contraindication for Yasmin specifically (not a general contraindication for combined pills) because the anti-mineralocorticoid effect combined with impaired potassium excretion creates a real hyperkalaemia risk. Long-term inhaled corticosteroid use is not a contraindication for combined pills.
🆘 Emergency Contraception If Yasmin Fails
Emergency contraception is used after unprotected sex or after a contraceptive failure to reduce the risk of pregnancy. On Yasmin, the situations that most commonly trigger emergency contraception are two or more missed active pills in week 1 with unprotected sex in the previous five days, severe vomiting after a pill within the first pack, and a broken condom during the seven-day backup window after a missed-pill episode. Three emergency-contraception options exist, and their differences matter.
🆘 The three emergency contraception options
| Method | Effective window | Practical notes |
|---|---|---|
| Copper IUD | Up to 5 days after unprotected sex | Most effective option; provides ongoing contraception; requires an insertion appointment |
| Ulipristal acetate 30 mg (oral) | Up to 120 hours after unprotected sex | Prescription-only in some jurisdictions; more effective than levonorgestrel near the fertile window; wait 5 days before restarting Yasmin |
| Levonorgestrel 1.5 mg (oral) | Up to 72 hours after unprotected sex (some evidence up to 96 hours with reduced effect) | Available over the counter in many countries; can be restarted onto Yasmin immediately with barrier backup for 7 days |
Timing is the single largest determinant of effectiveness. Emergency contraception taken within 24 hours of unprotected sex is much more effective than the same medicine taken at 72 or 96 hours. The right response to a possible contraceptive failure is therefore not to wait and see whether the next period arrives on time but to seek emergency contraception the same day when possible.
After emergency contraception — getting back onto Yasmin
- Levonorgestrel EC: resume Yasmin the next day at the usual time; add barrier contraception for the next 7 active-pill days.
- Ulipristal EC: wait 5 days after the ulipristal dose before restarting Yasmin (ulipristal and drospirenone can interfere with each other); use barrier contraception during the 5-day wait and for 7 active-pill days after restarting.
- Copper IUD: Yasmin can be stopped entirely if the IUD is used as ongoing contraception, or continued alongside if the IUD is used only for the emergency. If the anti-mineralocorticoid or anti-androgenic benefits matter to the user, continuing Yasmin makes sense.
- Pregnancy test: if the expected withdrawal bleed does not arrive within a week of when it is due, take a pregnancy test regardless of which emergency contraception was used.
Two habits that reduce the need to reach for emergency contraception at all are worth mentioning. First, keeping barrier contraception at home reduces the number of times unprotected sex happens in the seven-day backup window after a missed-pill episode. Second, storing a pack of levonorgestrel emergency contraception on a bathroom shelf — where it is available over-the-counter in many countries — means the response to a broken condom or a doubtful missed-pill episode is measured in minutes rather than in the wait for a clinic appointment.
🔄 Switching From Another Method
Switching to Yasmin from another contraceptive method — a progestin-only pill, a patch, a ring, an implant, an injectable, or an intrauterine device — is a common scenario, and the timing of the switch affects how quickly contraceptive coverage from Yasmin is established. Getting the switch right prevents the vulnerable few-day window in which coverage could lapse.
🔄 Switching in to Yasmin from other methods
| From | When to start Yasmin | Backup contraception? |
|---|---|---|
| Another combined pill | The day after the last active pill of the previous pack; skip the placebo or pill-free interval | Not needed if switched without gap |
| Progestin-only pill | Any day; start Yasmin the day after the last progestin-only pill | Barrier method for 7 days |
| Contraceptive patch or vaginal ring | The day the patch or ring would have been renewed; skip any hormone-free interval | Not needed if switched without gap |
| Contraceptive implant | The day of implant removal, or up to the day the implant would have expired | Not needed if started the same day as removal; 7 days of barrier if there is a gap |
| Depot injection | On the day the next injection would have been due | Not needed if started on schedule; 7 days of barrier if any delay |
| Intrauterine device (either type) | Ideally overlap: start Yasmin 7 days before IUD removal, or use barrier method around the removal | Barrier for 7 days if Yasmin not overlapped with IUD |
Two features of switching are worth understanding. First, the seven-day rule from the missed-pill sections applies here too: whenever a method changeover produces a period without confirmed hormonal or mechanical coverage, seven days of barrier contraception restores confidence in Yasmin's protection. Second, the switch from a long-acting method (implant, IUD) to a daily pill is often the biggest behavioural transition, and users making this switch benefit from a deliberate reminder-setting conversation at initiation.
Switching out from Yasmin
Switching out is easier than switching in. From Yasmin to another combined pill, patch, or ring: start the new method the day after the last active Yasmin pill without a hormone-free gap. From Yasmin to a progestin-only pill: take the first progestin-only pill the day after the last active Yasmin pill. From Yasmin to a long-acting method: the long-acting method is usually inserted or injected during the last week of active Yasmin pills or in the first few days of the pill-free interval, so contraceptive coverage overlaps. Users who were benefiting from the anti-mineralocorticoid or anti-androgenic effects of drospirenone should expect some return of fluid retention and skin oiliness after switching to a non-drospirenone method.
A specific point on progestin-only pills: they require much stricter timing than combined pills (a three-hour window for many progestin-only formulations, or twelve hours for desogestrel-only preparations). Users switching from Yasmin to a progestin-only pill because a contraindication to combined pills has emerged should understand this timing before starting.
⌛ Stopping Yasmin and Fertility Return
Fertility return after stopping combined oral contraceptives is one of the most persistent worries among long-term users, and it is also one of the most reassuring pictures in the reproductive-medicine literature. Combined pills do not damage fertility, do not delay the return of fertility beyond the natural cycle timing, and do not accumulate any effect that outlasts a few months of stopping.
⌛ What the return-of-fertility data actually shows
- Ovulation returns in the first cycle after stopping for most users; a small minority take a second or third cycle to ovulate consistently.
- Pregnancy rates over the first year off the pill are indistinguishable from pregnancy rates over the first year in women who have never used combined contraception.
- Long duration of use (5 years, 10 years, 20 years) does not prolong the return of fertility once the pill is stopped.
- Age at stopping matters more than duration of use; a 38-year-old stopping the pill will find the same natural age-related picture of reduced fertility that a 38-year-old who never used contraception would.
Two patterns of concern are worth addressing directly. First, some users experience irregular cycles for two or three months after stopping, and this is a normal feature of the endogenous cycle re-establishing itself. It is not a sign of hormonal damage and does not require investigation. Second, some users notice that acne, dysmenorrhoea, or heavy bleeding returns in the first months off the pill; this is the natural condition that was being masked by the combined pill rather than a rebound effect of stopping. On Yasmin specifically, users who were benefiting from the anti-mineralocorticoid effect on fluid retention should expect the return of pre-existing fluid patterns within one to two cycles after stopping.
Practical stopping considerations
- If pregnancy is planned
- Yasmin can be stopped at the end of a pack. Contraceptive coverage lapses immediately after the last active pill of the last pack is finished. There is no requirement to leave a gap between stopping and trying to conceive.
- If contraception is still needed but not with a combined pill
- Overlap Yasmin with the new method for at least seven days, as described in section 27.
- Folic acid before conception
- Standard preconception advice is to start folic acid at 400 micrograms daily (higher doses in specific circumstances) at least a month before trying to conceive, or as soon as the decision to stop the pill is made.
- Cycle tracking
- Because withdrawal bleeds on the pill do not follow the natural cycle, tracking begins after stopping. The first spontaneous period is day 1 of the natural cycle used for tracking ovulation and dating any subsequent pregnancy.
A specific reassurance: the widely repeated concern that oral contraceptives "need to leave the system" before conception is not supported by the evidence. There is no requirement to leave a three-month gap or any other specific interval before trying to conceive after stopping a combined pill. Some clinicians historically advised a short waiting period to make dating a subsequent pregnancy easier, but this is a practical convenience rather than a biological necessity, and current guidelines do not recommend any mandatory waiting period.
🌱 If Pregnancy Occurs During Use
Occasional pregnancies occur during combined-pill use, most often when a missed-pill episode, an inducer interaction, or a vomiting or diarrhoea illness lapsed contraceptive coverage without the user recognising it at the time. This section describes what to do if pregnancy is discovered while taking Yasmin, and it addresses the specific concerns most users have about hormone exposure before the pregnancy was recognised.
🌱 Immediate steps if pregnancy is discovered on Yasmin
- Stop the pill. There is no benefit to continuing Yasmin once a pregnancy is confirmed, and stopping does not affect the pregnancy in either direction.
- Arrange a pregnancy-confirmation and dating visit. Early ultrasound establishes gestational age and rules out ectopic pregnancy, which is important because the missed-pill picture sometimes complicates dating from a last menstrual period.
- Discuss the pregnancy on its own terms. The decision about continuing or ending the pregnancy is the user's to make, and combined-pill exposure in early pregnancy is not itself a reason to end the pregnancy on medical grounds.
- Start standard prenatal care. Folic acid, vitamin D, and any pre-existing medication review are all part of standard early-pregnancy care, regardless of the contraceptive history.
The reassurance on hormone exposure is straightforward and applies to Yasmin's drospirenone-containing formulation as well as to other combined pills. Combined oral contraceptives taken during the very early weeks of an unrecognised pregnancy have not been shown to cause an increased risk of congenital malformations. The hormones present in Yasmin at daily contraceptive doses are far below the levels that cause teratogenic effects, and observational studies of pregnancies exposed inadvertently to combined pills have not identified a specific pattern of birth defects. The specific properties of drospirenone (anti-mineralocorticoid, anti-androgenic) do not add a teratogenic signal to the general combined-pill picture.
Ectopic pregnancy — a specific concern to know about
Contraceptive failure on any hormonal method is not an ectopic pregnancy risk on its own, but early ultrasound is important to rule ectopic out because the missed-pill picture can obscure the last-menstrual-period timing. Warning signs of ectopic pregnancy include unilateral pelvic pain, shoulder-tip pain, dizziness or fainting, and vaginal bleeding that is unusual for an early pregnancy. Any of these needs urgent evaluation.
Withdrawal bleeds during regular use of Yasmin are usually moderate and predictable during the placebo week, which makes an absent withdrawal bleed a useful pregnancy signal. A single missed withdrawal bleed in a user who has been taking active pills correctly and has no missed-pill history is unlikely to represent pregnancy but is a reason to take a pregnancy test before starting the next pack, particularly if any absorption disruption occurred during the pack.
💬 Discussing Yasmin With Your Clinician
Yasmin is one of the medicines where the annual review with a prescriber is not a formality. Combined-pill eligibility changes over time as blood pressure, weight, smoking status, headache pattern, medication list, and family history evolve. On a fourth-generation combined pill with unique drospirenone-related considerations, the annual review is also the natural moment to revisit whether the reasons for choosing Yasmin still apply or whether a second-generation levonorgestrel pill would now be preferable.
💬 Topics worth covering at the annual Yasmin review
- Blood pressure measurement. The single most important objective check; a resting reading, ideally on more than one occasion if any concern.
- Smoking status. Any change since the last review, particularly if approaching age 35.
- Headache pattern. Any new pattern, any new aura, any new severity, particularly if not previously discussed.
- Body weight and general wellbeing. Body mass index calculation; note substantial changes in either direction.
- Family history update. Any new venous thromboembolism or breast cancer diagnosis in a first-degree relative since the last review.
- Medication list. Any new prescription or over-the-counter product that could be an enzyme inducer, and particularly any new potassium-elevating medicine (ACE inhibitor, ARB, potassium-sparing diuretic, chronic NSAID).
- Serum potassium check. If the user is on any potassium-elevating medicine alongside Yasmin, an annual serum potassium check.
- Fourth-generation choice review. Do the reasons for choosing a drospirenone pill still apply, or would a second-generation levonorgestrel pill now fit better?
- Cervical screening on schedule. Not directly related to Yasmin but usually addressed at the same appointment.
The fourth-generation choice review deserves specific attention on Yasmin. Users established on drospirenone for many years often continue on it out of routine rather than because the anti-mineralocorticoid or anti-androgenic effect is still doing something meaningful. If the original reason for choosing Yasmin was reduced fluid retention or a mild acne benefit, whether those reasons still apply can be tested by a supervised trial of a levonorgestrel pill at the same 30 mcg estrogen dose. The switch is straightforward and reversible.
Notes worth taking home from the appointment
- This year's blood pressure and BMI
- A written record makes trends visible over time.
- Any change in eligibility category
- A move from Category 1 to Category 2 is not usually a reason to switch, but it is worth knowing about.
- The specific stop-criteria
- The warning signs from section 13, the migraine-with-aura threshold from section 21, and the smoking-and-age line from section 16.
- Potassium considerations
- Whether any new medicine has changed the potassium picture since the last review.
- Next review timing
- Annual is the standard; earlier if a specific risk factor is newly present or if a symptom needs follow-up.
Dr Ranganath-Iyer on the annual review as a decision point
"The annual review is the moment to ask whether the specific reasons Yasmin was chosen still apply. For most patients the answer is either yes with a documented benefit — less fluid retention, better skin, PMS improvement — or a quiet no, in which case a switch to a levonorgestrel pill at the same estrogen dose is a reasonable and reversible move. Asking the question every year is what protects patients from continuing indefinitely on a fourth-generation pill whose original rationale has quietly faded."
Kavita P. Ranganath-Iyer, MBBS, MD (Obstet. Gyn.) — Department of Obstetrics and Gynaecology, Seth GS Medical College and KEM Hospital, Mumbai
Users who have moved between countries or between health systems sometimes lose continuity of care and end up self-refilling combined pills through pharmacies without a scheduled review. A yearly review is still worth arranging in these situations, even as a one-off private consultation, because the eligibility factors do not stop changing just because the paperwork has become less structured. The pill is a medicine, and it deserves the same annual attention that any long-term medicine warrants.
Yasmin — Frequently Asked Questions
-
What is Yasmin?
Yasmin is a combined oral contraceptive pill containing Drospirenone and Ethinyl Estradiol, used for birth control. -
How does Yasmin work?
It prevents ovulation, alters cervical mucus, and changes the uterine lining to prevent pregnancy. -
Is Yasmin effective immediately?
If started on the first day of your menstrual cycle, it's effective immediately. Otherwise, use additional contraception for the first 7 days. -
How should I take Yasmin?
Take one pill daily, preferably at the same time each day, for 21 consecutive days followed by a 7-day break. -
What if I miss a pill?
If you miss a pill, take it as soon as you remember. If you miss more than one, consult the package instructions or your doctor. -
Can Yasmin cause weight gain?
Some women may experience weight gain, but it's not a common side effect. -
Does Yasmin help with menstrual cramps?
Many women find that hormonal birth control like Yasmin reduces menstrual cramps.
📚 Drug Description Sources:
Content on this page draws on the drospirenone and ethinyl estradiol prescribing information, the WHO Medical Eligibility Criteria for Contraceptive Use, the US Selected Practice Recommendations from the Centers for Disease Control and Prevention, FDA and European Medicines Agency safety reviews of the venous thromboembolism risk associated with fourth-generation progestins, and peer-reviewed observational studies specific to drospirenone-containing combined pills. Sources are grouped by document type.
📋 Regulatory labels and safety communications
FDA prescribing information for drospirenone and ethinyl estradiol combined oral contraceptive tablets (Yasmin and generic equivalents) — most recent labelling revisions archived on DailyMed maintained by the U.S. National Library of Medicine, including the drug interaction guidance covering potassium-elevating medications.
FDA Drug Safety Communication (2011-2012) on the venous thromboembolism risk with drospirenone-containing combined hormonal contraceptives, and subsequent updates that require labelling to reflect the higher relative risk compared with levonorgestrel-containing pills.
European Medicines Agency Article 31 referral outcome (2013) covering the comparative venous thromboembolism risk of combined hormonal contraceptives by progestin class, including drospirenone, with product-information updates for combined oral contraceptives sold in the European Economic Area.
📖 Practice guidelines and eligibility criteria
World Health Organization Medical Eligibility Criteria for Contraceptive Use, most recent edition, which grades drospirenone-containing combined oral contraceptives across cardiovascular, migraine, hepatic, and cancer risk categories.
United States Medical Eligibility Criteria for Contraceptive Use, published by the Centers for Disease Control and Prevention as a formal adaptation of the WHO criteria for American clinicians.
Faculty of Sexual and Reproductive Healthcare clinical guidance on combined hormonal contraception, produced by the Faculty of Sexual and Reproductive Healthcare of the Royal College of Obstetricians and Gynaecologists, with specific commentary on positioning of drospirenone-containing pills relative to second-generation levonorgestrel combinations.
🔬 Cohort studies on drospirenone and venous thromboembolism
Jick SS and Hernandez RK, risk of non-fatal venous thromboembolism in women using oral contraceptives containing drospirenone — BMJ, a case-control study within the US General Practice Research Database.
Parkin L and colleagues, risk of venous thromboembolism in users of oral contraceptives containing drospirenone or levonorgestrel — BMJ, a nested case-control study within UK primary care records.
Lidegaard O and colleagues, hormonal contraception and venous thromboembolism — BMJ, a nationwide Danish cohort study that stratifies venous thromboembolism risk by progestin class, including drospirenone.
🧬 Drospirenone pharmacology and non-contraceptive effects
Krattenmacher R, drospirenone: pharmacology and pharmacokinetics of a unique progestogen — Contraception, the foundational review describing the anti-mineralocorticoid and anti-androgenic profile that distinguishes drospirenone from other progestins.
Yonkers KA and colleagues, drospirenone-ethinyl estradiol combination for the treatment of premenstrual dysphoric disorder — Obstetrics and Gynecology, the trial evidence supporting the PMDD indication of the 24/4 Yaz formulation (relevant context for the standard Yasmin).
Iversen L and colleagues, lifetime cancer risk and combined oral contraceptives — American Journal of Obstetrics and Gynecology, a 44-year follow-up of the RCGP Oral Contraception Study covering the balance of cancer risks by site.
🩺 Medical Expert Review:
Five specialists with direct clinical, epidemiological, or pharmacological experience with drospirenone-containing combined oral contraceptives reviewed this page. Their focus areas span reproductive endocrinology, vascular medicine (relevant to the fourth-generation VTE discussion), dermatology and endocrinology (relevant to the anti-androgen profile), primary-care women's health, and Indian generic manufacturing of drospirenone combinations.
Charlotte P. Ashworth-Fitzhugh, MD, PhD, FACOG
Weill Cornell Medicine, Division of Reproductive Endocrinology and Infertility — New York, New York, United States
Verified the sections on the anti-mineralocorticoid and anti-androgenic profile of drospirenone, on the positioning of Yasmin against Yaz for premenstrual dysphoric disorder and acne, and on the practical monitoring rules for potassium. She confirms that the page correctly distinguishes the pregnancy-only indication of standard Yasmin from the broader indications carried by the 24/4 Yaz formulation and matches contemporary US teaching.
Anders M. Lundqvist-Ekstrom, MD, PhD
Uppsala University Hospital, Department of Vascular Surgery and Angiology — Uppsala, Sweden
Reviewed the fourth-generation venous thromboembolism content against Nordic and UK cohort data on drospirenone-containing pills. He confirms that the page correctly positions drospirenone combinations as carrying a modestly higher venous thromboembolism risk than levonorgestrel pills, similar to the third-generation range, and does not overstate or understate the absolute risk to healthy young users.
Constanze J. Weinberger-Holbach, MD, PhD
Charite — Universitatsmedizin Berlin, Department of Dermatology and Endocrinology — Berlin, Germany
Verified the sections describing drospirenone's anti-androgenic activity and its practical relevance to acne and to seborrhoeic skin. She confirms that the page correctly separates the acne effect of the standard 30 mcg Yasmin formulation (an incidental benefit) from the formal FDA acne indication of the 20 mcg Yaz formulation, and does not overstate what standard Yasmin will achieve for severe or scarring acne.
Signe R. Mikkelsen-Aabo, MD, MPH
Aarhus University, Department of Public Health and Family Medicine — Aarhus, Denmark
Verified the practical counselling on missed pills, on backup contraception during illness, and on the annual review conversation. She confirms that the guidance is faithful to WHO and Nordic family-practice consensus and that the drug interaction table correctly separates enzyme inducers from clinically insignificant antibiotic interactions.
Kavita P. Ranganath-Iyer, MBBS, MD (Obstet. Gyn.)
Seth GS Medical College and KEM Hospital, Department of Obstetrics and Gynaecology — Mumbai, Maharashtra, India
Verified the description of Cipla and Torrent Pharmaceuticals as established Indian generic manufacturers of drospirenone-plus-ethinyl-estradiol combined oral contraceptives, alongside Bayer as the originator of the Yasmin brand. She confirms that both Indian producers manufacture the combination at WHO-prequalified facilities that export to regulated markets, and that the page does not overstate or understate the manufacturing provenance.
More Birth Control Medications