Buy Tretiheal (Tretinoin 0.05% / 0.1% Cream 20g) Online - Healing Pharma Generic Retin-A Topical Retinoid for Acne Photoaging Treatment


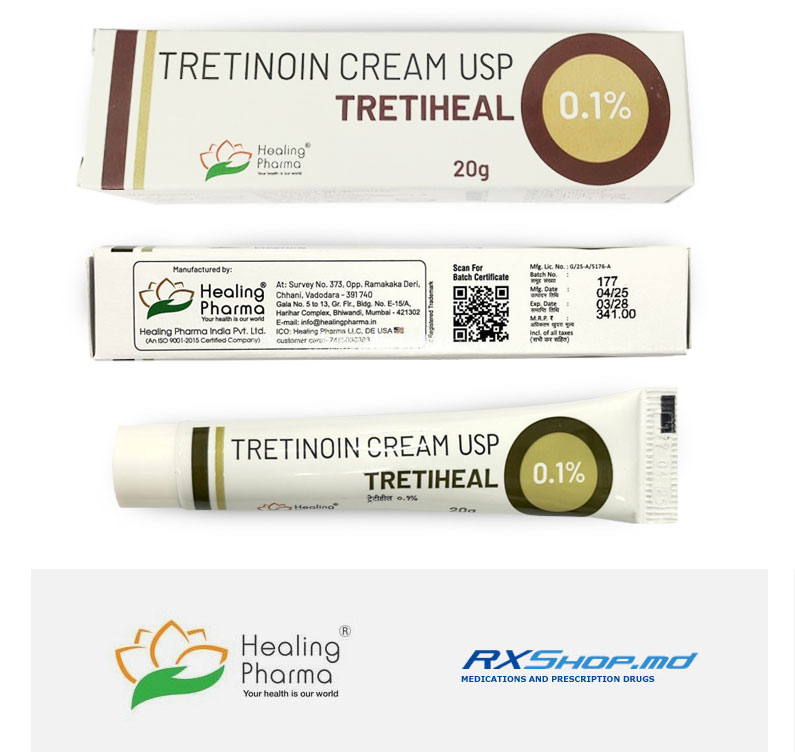
Tretiheal (Tretinoin 0.05% / 0.1% Cream 20g) represents the Healing Pharma India dedicated tretinoin brand providing the same foundational topical retinoid therapy as brand-name Retin-A at accessible cost. Tretinoin (all-trans-retinoic acid, ATRA) is the naturally occurring vitamin A carboxylic acid derivative that established the entire topical retinoid drug class through original Ortho Pharmaceutical (Johnson & Johnson) development and FDA approval as Retin-A in 1971 — with over 50 years of clinical experience defining topical retinoid therapy for acne and photoaging. Manufactured by Healing Pharma India under WHO-GMP quality standards, Tretiheal delivers bioequivalent tretinoin therapy in higher-strength concentrations (0.05% standard and 0.1% high-potency) appropriate for established retinoid users and those requiring higher therapeutic potency. Healing Pharma is the same trusted Indian manufacturer producing multiple other dermatology and general pharmaceuticals available on rxshop.md including Retin-A generic, Accufine (isotretinoin), Zofran (ondansetron), Celeheal (celecoxib), and Dapoforce (dapoxetine).
Tretinoin works through nuclear retinoic acid receptor (RAR) binding producing multiple dermatologic effects. First, tretinoin normalizes follicular keratinization preventing abnormal keratin plug formation creating microcomedones — the earliest acne lesions. Second, it increases epidermal cell turnover accelerating shedding of dead skin cells and comedone contents. Third, tretinoin increases dermal collagen synthesis improving skin texture reducing fine wrinkles and providing anti-aging benefits — the mechanism explaining its dual efficacy for both acne and photoaging management. Fourth, it produces anti-inflammatory effects reducing inflammatory acne lesions. Fifth, tretinoin modulates melanocyte function reducing hyperpigmentation particularly melasma and post-inflammatory pigmentation.
Tretiheal serves multiple dermatologic conditions across acne and anti-aging spectrum. Primary uses include acne vulgaris — comedones, papules, pustules; post-acne hyperpigmentation; fine wrinkles and photoaging; rough uneven skin texture; melasma and pigment disorders; keratosis pilaris (off-label); actinic keratosis (adjunctive); and uneven skin tone from sun exposure.
Tretiheal applied thin layer once daily at bedtime. Broad-spectrum SPF 30+ mandatory during day. 2-6 week retinization period initial. Sibling brand: Retin-A.


Free prescription
Discrete packaging
Have questions?
Quality Assurance
- Post Acne Hyperpigmentation: Persistent dark spots and marks remaining after acne inflammation responding to tretinoin lightening effects;
- Fine Wrinkles and Photoaging: FDA-approved for photoaging improving fine wrinkles skin texture and mottled hyperpigmentation from cumulative sun damage;
- Rough or Uneven Skin Texture: Improves skin surface quality through normalized keratinocyte turnover and dermal collagen enhancement;
- Melasma Treatment: Hormonal facial hyperpigmentation from pregnancy or oral contraceptives responds to melanocyte modulation and cellular turnover;
- Pigment Disorders: Various acquired hyperpigmentation conditions responding to retinoid melanocyte regulation and epidermal renewal;
- Keratosis Pilaris Off Label: Rough bumpy skin on upper arms and thighs from follicular hyperkeratinization responds to topical retinoid;
- Actinic Keratosis Adjunctive: Precancerous sun-damaged lesions respond to tretinoin as part of comprehensive photoprotection management;
- Uneven Skin Tone from Sun Exposure: Mottled sun-induced hyperpigmentation and lentigines respond to prolonged tretinoin therapy;
- Comedones: Blackheads and whiteheads from abnormal follicular keratinization responding to retinoid normalization;
- Inflammatory Papules and Pustules: Red inflamed acne lesions responding to anti-inflammatory retinoid action;
- Skin Rejuvenation Therapy: Overall skin quality improvement through cellular renewal and dermal collagen enhancement;
- Anti Aging Topical Therapy: Long-term topical treatment reversing established photoaging changes and preventing progression;
- Solar Lentigines: Sun-induced dark spots fade with regular tretinoin use through melanocyte modulation;
- Comedone Formation Prevention: Prevents new comedone development through normalized follicular keratinization at cellular level;
- Non Antibiotic Acne Therapy: Effective acne treatment without antibiotic exposure preserving multiple therapy options and preventing resistance;
- Higher Strength Retinoid Option: 0.1% concentration provides substantial efficacy for established users and treatment-resistant cases;
- Topical Retinoid Class: Foundational first-generation topical retinoid establishing over 50 years of dermatologic therapy;
- Dermatologist Recommended Therapy: Standard dermatology first-line topical retinoid for acne and comprehensive anti-aging management;
- Generic Retin-A Alternative: Bioequivalent Healing Pharma tretinoin providing identical therapeutic action at accessible generic cost.
- Less Post Acne Marks: Fades persistent dark spots and hyperpigmentation remaining after acne inflammation through melanocyte modulation;
- Better Anti Aging Effect: Increases dermal collagen synthesis reducing fine wrinkles and improving skin appearance in photoaged skin;
- Better Skin Texture: Normalizes keratinocyte turnover producing smoother more even skin surface and improved overall complexion;
- Better Sun Damage Treatment: FDA-approved for photoaging reversal improving skin quality damaged by cumulative sun exposure over years;
- Less Melasma and Pigmentation Disorders: Brightens hormonal and sun-induced pigmentation through cellular renewal and melanocyte modulation;
- Less Clogged Pores: Prevents pore blockage through normalized follicular keratinization at cellular level preventing comedone formation;
- Better Overall Skin Rejuvenation: Comprehensive skin quality improvement through cellular renewal collagen synthesis and pigment normalization;
- Less Fine Lines and Wrinkles: Increased dermal collagen production visibly reduces fine wrinkles and improves youthful appearance;
- Better Skin Cell Renewal: Enhanced epidermal cell turnover produces fresher healthier skin appearance with improved barrier function;
- Less Uneven Skin Tone: Substantial improvement in mottled sun-damaged pigmentation and solar lentigines with sustained therapy;
- Better Collagen Synthesis: Stimulates dermal fibroblast collagen production improving skin thickness elasticity and youthful appearance;
- Better Melanocyte Regulation: Modulates melanocyte function reducing excessive pigmentation and improving skin color evenness over time;
- Better Non Antibiotic Approach: Effective acne management without antibiotic exposure preventing resistance development and preserving antibiotic options;
- Better Higher Strength Efficacy: 0.1% concentration provides substantial therapeutic efficacy for treatment-resistant cases and established users;
- Better Long Term Skin Health: Sustained use provides ongoing anti-aging and acne-preventive benefits through cellular normalization;
- Better Comedonal Acne Prevention: Effectively prevents blackhead and whitehead formation through normalized follicular keratinization;
- Better Healing Pharma Manufacturing: WHO-GMP manufacturing standards ensure consistent bioequivalent generic quality for reliable therapeutic outcomes;
- Better Generic Affordability: Substantially lower cost than brand-name Retin-A makes proven topical retinoid therapy accessible for long-term use;
- Better Quality of Life: Improved skin appearance dramatically enhances self-esteem and confidence for both acne and photoaging patients.
Generic Tretiheal (Tretinoin 1% 20 g) Medication guide:
💊 Welcome to Tretiheal - Tretinoin at Higher Strength
💊 Tretiheal is tretinoin cream at 0.05 and 0.1 percent, made by Healing Pharma in a 20 gram tube. 🔍 The molecule is the same one that has been prescribed since 1971. 📊 What distinguishes this product is the strength, and strength is the thing most people handle badly.
🤔 The second tile is where the trouble starts. 📊 A jump from 0.025 to 0.1 percent is a fourfold increase in concentration, and skin does not respond to that in proportion. 🔍 The irritation rises steeply while the benefit rises gently, which is the central trade-off this entire guide is about.
| 🔍 What it is | 📋 The detail |
|---|---|
| Active ingredient | Tretinoin, chemically all-trans retinoic acid. The active form itself, requiring no conversion in the skin |
| Strengths supplied | 0.05 and 0.1 percent cream, in a 20 gram tube. Both sit at the upper end of the range used on skin |
| Who it suits | People who have already tolerated a lower-strength retinoid, or who have been put on this strength deliberately by a clinician |
| Who it does not | Anyone using a retinoid for the first time. The adjustment at this concentration defeats most people who start here |
| How it is used | A pea-sized amount for the whole face at night, on dry skin. The quantity does not change with the strength |
| What it is for | Acne, photodamaged skin, and the pigmentation that both sun and old spots leave behind |
📊 One detail in that table is worth pausing on. 💙 The amount applied does not change with the strength. 🤔 People moving up to 0.1 percent frequently also increase the quantity, on the reasoning that more of a better product should work faster, and that combination is the fastest route to a damaged barrier.
A higher strength is not a better version of the same treatment. It is the same treatment delivered faster than most skin can absorb, and the result depends entirely on whether the skin keeps up.
— the idea this guide is built around🔬 There is one genuine argument for the higher strength, and it is the reason 0.1 percent exists. 📊 The 1993 New England Journal of Medicine trial that measured an 80 percent increase in collagen formation in sun-damaged skin was conducted at 0.1 percent over ten to twelve months. 🔍 That is the concentration the strongest evidence for photoageing was generated at, which matters for anyone treating sun damage rather than acne.
💡 Four things to understand before the first application at this strength:
- 📉 Start less often, not less carefully. Two nights a week at 0.1 percent is a sensible beginning even for skin that handled a lower strength nightly
- 💧 The barrier does more of the work than the drug. Moisturiser is not optional support at this concentration, it is what makes the routine survivable
- ☀️ Sun protection becomes a requirement rather than a recommendation. Skin turning over this fast burns more easily and marks more readily
- ⏳ The clock does not speed up as much as the strength does. Acne is still judged at three months and photoageing at twelve, regardless of concentration
📈 What Changes When Tretinoin Strength Goes Up
📈 Doubling the concentration of a topical drug does not double what it does. 📊 Skin absorbs what it can absorb, receptors saturate, and the surplus mainly produces irritation. 🔍 Understanding which effects scale with strength and which do not is what makes the choice rational rather than aspirational.
| 🔍 What changes | 📊 How it scales with strength |
|---|---|
| Irritation | Rises clearly and reliably. This is the effect that scales most directly with concentration |
| Speed of visible change | Reported to be faster for photoageing at the higher strength, with summaries suggesting visible improvement around six months at 0.1 percent against closer to twelve at 0.05 |
| End result at one year | Reported as similar between 0.05 and 0.1 percent. The higher strength appears to arrive sooner rather than go further |
| Effect on blocked pores | Present at every strength. A lower concentration used consistently clears comedones perfectly well |
| Risk of pigmentation from irritation | Rises with strength, and matters most on richly pigmented skin where inflammation leaves marks behind |
| Chance of abandoning treatment | Rises sharply. This is the effect nobody counts, and it is the one that most often decides the outcome |
🤔 Reading the table as a whole, the pattern is that strength buys time rather than ceiling. ⏳ A higher concentration may get somewhere sooner; it does not appear to get somewhere better. 📊 Whether that is worth the extra irritation depends on how much irritation a particular face can absorb without the routine collapsing.
⚠️ One honest caveat applies to the whole section. 🔍 The head-to-head evidence between tretinoin strengths is thinner than the confident claims made about it, in both directions. 📊 There is very little randomised comparison of 0.025, 0.05 and 0.1 percent for acne at all, and the photoageing comparisons come largely from older trials summarised second-hand. 🤔 The clinical convention, that higher strength means more irritation and somewhat faster photoageing results, is reasonable rather than proven.
🎯 Who Should Be on 0.1 Percent and Who Should Not
🎯 The strength written on a tube should follow from who is using it and what for, and in practice it usually follows from what was available or what sounded strongest. 📊 These are the situations where 0.05 or 0.1 percent genuinely earns its place, and the ones where it does not.
| 👤 The situation | ✅ Is a higher strength right |
|---|---|
| Six months at 0.025 percent, tolerated easily, result plateaued | Yes. This is the classic reason to step up, and the skin has already proved it can adapt |
| Treating photodamage, oily resilient skin, long time horizon | Reasonable. The strongest photoageing evidence was generated at 0.1 percent over ten to twelve months |
| Stubborn comedonal acne on the nose, chin and forehead | Sometimes, if a lower strength has been used properly for three months without enough progress |
| First retinoid ever, keen to get results quickly | No. Starting here is the single most reliable way to abandon retinoids entirely within six weeks |
| Dry, sensitive or eczema-prone skin | No, or only after a long period at a lower strength with careful buffering |
| Treating melasma or dark marks on richly pigmented skin | Cautiously, if at all. Irritation at this strength generates the pigmentation being treated |
| Rosacea, or persistent facial flushing not yet diagnosed | No. A diagnosis comes first, and a high-strength retinoid often makes this considerably worse |
🤔 The first row describes the only entirely comfortable case. 📊 Skin that has run at a lower strength for months without trouble has demonstrated that it adapts, and the step up is a measured change rather than a gamble. 🔍 Every other row involves a judgement, and most of them are better made by somebody who can see the skin.
📊 Four questions that settle the strength question.
🔵 Have I used a retinoid consistently for at least three months? If not, the strength is not the variable to change first.
🟢 Was the lower strength comfortable or merely survivable? Skin that still flakes at month four is not ready to go up.
🟡 Am I treating pores, or pigment, or lines? Pores respond at any strength. Photoageing is where the higher concentration has an argument.
🔶 Can I absorb a difficult six weeks? A step up restarts the adjustment, and a wedding or a job interview in week four changes the answer.
💡 One alternative is almost always available and almost never considered. 📅 Using the current strength more often rather than using a higher strength at the same frequency. 📊 Moving from three nights a week to five at 0.05 percent increases total exposure substantially with far less of a shock to the barrier than jumping to 0.1 percent would deliver.
⬆️ Stepping Up to Tretiheal From a Lower Strength
⬆️ Moving up a strength is not a switch, it is a transition, and it deserves the same care the first retinoid did. 📊 Skin that has adapted to one concentration has not adapted to a higher one, and the adjustment period starts again.
🤔 The second step is the one people skip, and it is the one that works. 📊 Running a new higher strength alongside the old lower one, alternating nights, keeps total exposure roughly stable while the skin learns the new concentration. ✅ It converts a step change into a ramp.
💡 That last line deserves emphasis because it contradicts a common assumption. 📊 Nightly use is not the destination. 🤔 Plenty of people run 0.1 percent three or four nights a week indefinitely and get the result they wanted, and the total weekly exposure at that pattern is comparable to a lower strength used every night. ✅ The goal is the most exposure the skin can hold steadily, not the maximum the calendar allows.
⚖️ What the Comparative Evidence Actually Shows
⚖️ Claims about tretinoin strengths are made with much more confidence than the underlying evidence supports, and a guide that repeated them without saying so would be misleading. 📊 Here is what is actually established and what is convention.
There is remarkably little randomised head-to-head comparison between tretinoin strengths, considering the drug has been in use since 1971 and the question comes up at every prescription.
— the honest state of the evidence🔍 What is solid: tretinoin works, at every strength that has been studied, for acne and for photodamaged skin. 📊 The 1993 collagen trial was conducted at 0.1 percent, and the 1995 photoageing approval rests on work with a 0.05 percent emollient cream. 🤔 Both concentrations have real evidence behind them.
📋 What is less solid than it sounds:
- ❓ That 0.1 percent outperforms 0.05 percent at one year. Secondary summaries of the older photoageing trials report similar results at twelve months, with the higher strength arriving sooner rather than going further
- ❓ That 0.05 percent is dramatically harsher than 0.025 percent. At least one comparative summary describes similar irritation profiles between those two, with no significant difference in local side effects
- ❓ That a higher strength clears acne faster. There is very little randomised comparison of strengths for acne at all, and the comedolytic effect is present throughout the range
- ❓ That the strongest available version is the best choice. No trial has tested the thing that actually decides outcomes, which is whether a person is still using the product a year later
🤔 None of that argues against the higher strengths. 📊 It argues against certainty about them, and in favour of a decision made on tolerance rather than on a belief that the number on the tube maps directly onto results. 🔍 A person who is comfortable at 0.1 percent has a defensible reason to use it, and a person who is not has no evidence-based reason to persist.
💡 The practical reading of all this is unglamorous and reliable. ✅ Use the strongest version your skin is genuinely comfortable with, applied as often as it stays comfortable, for as long as possible. 📊 Every piece of evidence in this field points at duration and consistency rather than at concentration, and that is the one conclusion the data supports without argument.
🌙 Applying a High-Strength Tretinoin Cream Correctly
🌙 The application technique for a high-strength tretinoin cream is the same as for a low-strength one, and the margin for error is much smaller. 📊 Mistakes that produce mild flaking at 0.025 percent produce a raw face at 0.1 percent.
| ⚠️ The mistake | 📊 What it costs at this strength |
|---|---|
| Applying to damp skin | Water in the outer layer increases penetration. At 0.1 percent this turns a correct dose into an excessive one |
| Using more than a pea | Double the quantity at double the strength is four times the exposure the skin was prepared for |
| Rubbing it into creases | Product pools beside the nose and at the corners of the mouth, and those areas crack rather than flake |
| Going too close to the eyes | Thin skin plus a high concentration produces swelling and stinging that take days to settle |
| Applying straight after a hot shower | Warm, damp, dilated skin absorbs considerably more. The combination is the commonest cause of a bad first week |
| Adding it to an existing active routine | Acids and a high-strength retinoid together remove the barrier faster than it rebuilds |
🤔 Every row in that table is the same error magnified. 📊 At a low strength these are annoyances; at 0.1 percent they are the difference between a routine that works and one that has to be stopped for a week.
💡 One habit is worth adopting specifically at these strengths. 🧼 Apply a barrier ointment to the creases beside the nose and the corners of the mouth before the tretinoin goes on. 📊 Those are the two places where product collects and where cracking starts, and a thin smear of something greasy beforehand prevents most of it.
🛑 Signs You Have Gone Too Strong With Tretiheal
🛑 There is a line between the ordinary adjustment to a retinoid and a skin barrier that is failing, and at high strength people cross it without noticing. 📊 The signs are specific, and the earlier they are recognised the shorter the recovery.
| ✅ Normal adjustment | 🚨 Gone too far |
|---|---|
| Flaking that comes off with moisturiser | Skin that is shiny, tight and looks like it has been burnt |
| Mild stinging for a few minutes after applying | Stinging from plain water, or from a moisturiser that was previously fine |
| Redness in the evening that has settled by morning | Redness that is present all day and worsening week by week |
| Dryness that moisturiser fixes for several hours | Dryness that returns within minutes no matter what is applied |
| Skin that looks worse in week three and better in week eight | Skin that has been getting steadily worse for six weeks with no turn |
| Occasional small cracks at the nose that heal in a day | Weeping, crusting or open cracks anywhere on the face |
🤔 The second column shares a common feature: things that used to be fine have stopped being fine. 📊 A barrier that is working tolerates water, moisturiser and daylight. 🔍 When those start to sting, the skin is no longer protecting itself, and continuing at the same strength makes a recovery longer rather than teaching the skin anything.
🚨 Stop applying and get it looked at for any of these.
🔴 Weeping, blistering or open cracks. This is past irritation and needs treating before any retinoid goes back on.
🔴 Swelling, particularly around the eyes or lips. At high strength this can be an irritant reaction or an allergic one, and the two need separating.
🔴 Itching that climbs day after day and spreads past the treated area. That pattern suggests allergy rather than irritation.
🔴 Burning and flushing across the central face that worsens steadily. Worth excluding rosacea, which a high-strength retinoid aggravates.
💡 One rule prevents most of this entirely. 🤔 Judge the skin in the morning, not at night. 📊 Evening redness after application is expected at these strengths and tells you very little. ✅ Skin that is still red, tight and stinging twelve hours later is reporting something real, and that is the measurement worth tracking.
🔙 Dropping Back Down Without Losing Ground
🔙 Dropping back to a lower strength feels like failure and is usually the move that saves the treatment. 📊 The goal was never a particular number on a tube; it was cumulative exposure over months, and a strength that the skin can hold delivers more of that than one it cannot.
🔍 How to come down without losing what has been gained:
- 📉 Reduce frequency before reducing strength. Going from five nights to three at 0.1 percent is often enough, and keeps the higher concentration available
- 🧴 Add buffering if it is not already in place. Moisturiser underneath changes tolerability substantially without changing the product
- ⏱️ Give any change four weeks. Skin takes that long to settle, and judging a reduction after five days produces a second change on top of the first
- 💙 Then drop the strength if needed, and treat that as a finished decision rather than a temporary retreat
- 📅 Rebuild slowly if you go back up later, because tolerance fades and the previous frequency will not be comfortable immediately
🤔 The sequence matters because each step is reversible and the last one is the largest. 📊 Most people who think they need a lower strength actually need fewer nights, and most people who think they need fewer nights actually need more moisturiser. 🔍 Working through the small adjustments first usually makes the big one unnecessary.
💡 The order of adjustments, in full:
💧 More moisturiser 🧴 Buffer it 📅 Fewer nights 📉 Lower strength ⏯️ Pause entirely
📊 Pausing sits at the end of that list rather than the beginning for a reason. 🔄 Stopping and restarting repeatedly is the pattern that produces all of the irritation and none of the accumulated benefit, because the skin never passes through the adjustment. ✅ Every option to the left of a pause keeps exposure continuous, which is what the result actually depends on.
🎭 Tretiheal for Melasma and Stubborn Pigment
🎭 Melasma is the hardest pigmentation problem a topical treatment is asked to solve, and tretinoin is one component of the answer rather than the answer itself. 📊 Knowing where it sits prevents both overestimating the cream and abandoning it too early.
| 🧪 Approach | 📊 What the evidence shows |
|---|---|
| Tretinoin alone | Produces a measurable reduction in severity against placebo in controlled studies, but slowly and modestly. It is rarely used alone for melasma |
| Triple combination with hydroquinone and a mild steroid | The best-supported topical option. A systematic review found it lightened melasma more than hydroquinone alone, with a relative risk of about 1.58 |
| The same combination against hydroquinone in a head-to-head trial | 64.2 percent of patients reached none or mild severity at eight weeks, against 39.4 percent on hydroquinone alone |
| Complete clearing | In two pooled eight-week trials covering 641 patients, about 26 percent cleared completely on the triple combination against under 5 percent on the comparators |
| Photoprotection | Carries more of the result than any cream. Without it, every topical approach underperforms and relapse is close to certain |
| Irritation from a high-strength retinoid | Works against the treatment. Inflammation drives pigment production, so an aggressive routine can darken melasma |
🤔 The last two rows explain why melasma frustrates people who approach it as a strength problem. 📊 Pushing to 0.1 percent to clear pigment faster produces irritation, and irritation produces pigment. 🔍 The condition punishes aggression more than almost any other skin problem.
📊 What a realistic melasma plan looks like.
🔵 Photoprotection first and permanently. Melasma has been described as a disorder of photoageing in genetically predisposed skin, which puts light exposure at the centre rather than the edge.
🟢 A combination rather than a single agent, prescribed and supervised, with tretinoin as one component.
🟡 Gentle application, not maximum strength. The goal is the most treatment that does not inflame the skin.
🔶 Expect relapse to be managed rather than avoided. Melasma recurs with sun, pregnancy and hormonal change, and treatment is long-term maintenance rather than a cure.
⚠️ One practical caution belongs here. 💉 The combination described above contains a mild corticosteroid, and it is used in defined courses under supervision rather than continuously, because long-term steroid on facial skin causes its own problems. 🔍 That is a prescribing decision, and it is the reason melasma treatment belongs with a clinician rather than assembled from separate tubes.
🌑 Dark Marks Left by Spots at Higher Strength
🌑 The brown marks left behind after spots heal are a different problem from melasma, they respond better, and they are where a retinoid earns its place most clearly. 📊 They are also the marks most often made worse by the treatment meant to clear them.
| 🔍 What is happening | ✅ How tretinoin affects it |
|---|---|
| Pigment deposited in the upper layers after inflammation | Faster cell turnover clears it more quickly than it would clear on its own. This is the main mechanism |
| New spots continuing to form | Prevented, which matters more than clearing old marks. Every new spot creates a new mark |
| Pigment deposited deeper in the skin | Responds slowly or not at all to a topical. Deeper marks can take a year or more regardless of treatment |
| Marks created by the treatment itself | Entirely possible at these strengths, and the reason a gentler routine often clears pigment faster than an aggressive one |
| Marks darkened by sun exposure | Not addressed by the cream at all. An unprotected mark darkens faster than any retinoid clears it |
🤔 The second row is the one that decides the outcome and gets the least attention. 📊 Somebody with active acne and a face full of old marks is in a race, and clearing marks faster matters far less than stopping new ones from forming. ✅ That is the same comedolytic effect a lower strength delivers, which is worth remembering before escalating.
⏳ Expectations matter here more than product choice. 📊 Marks in the upper layers typically fade over three to six months with treatment and sun protection. 🔍 Deeper pigment, which looks greyish or blue-brown rather than tan, can take a year and sometimes needs a different approach entirely. 📷 A photograph taken at the start is the only reliable way to tell which kind you are dealing with, because progress at this pace is invisible week to week.
💡 One behaviour outranks every product decision in this section. ✋ Not picking. 📊 A squeezed spot leaves a mark that lasts several times longer than one left alone, and on a retinoid the skin heals more slowly than it used to, so the penalty is larger than it was before treatment started.
🧬 Skin Ageing Beyond the Sun - The Exposome
🧬 Sunlight is the largest single thing that ages facial skin, and it is not the only one. 📊 Research into what has been called the skin ageing exposome has put numbers against several other environmental exposures, and they matter for anyone deciding how much a retinoid can realistically achieve.
🔗 What contributes, roughly in order of weight:
🤔 The second and third items are the ones people have not usually heard about. 📊 Work from environmental dermatology research has linked particulate air pollution to visible ageing of facial skin, and more recent work has implicated heat and humidity as independent contributors. 🔍 Neither is addressed by a retinoid, and neither is addressed by sunscreen.
📋 What follows for someone using a high-strength tretinoin:
- ☀️ Sun protection remains the single highest-yield action, larger in effect than the choice between 0.05 and 0.1 percent
- 🧼 Washing the face at the end of the day matters in a polluted city, because particulate matter sits on skin and is not neutral
- 🚬 Smoking accelerates exactly the collagen breakdown being treated. No concentration of retinoid outruns it
- 💡 Expect a ceiling. A retinoid works against a continuous process; it does not stop that process, and the result reflects the balance between them
📊 None of this diminishes the case for the drug. 🤔 It sets the realistic frame: tretinoin is the strongest topical intervention available on one side of an equation that has several terms on the other. ✅ Someone who protects against sun, does not smoke and uses a retinoid consistently is doing everything available, and that combination produces results no single element delivers alone.
☂️ Photoprotection Beyond a Bottle of Sunscreen
☂️ Sunscreen is the baseline rather than the whole of photoprotection, and for anyone treating pigmentation the distinction is not academic. 📊 Research on photodermatology has established that visible light as well as ultraviolet drives pigmentation, and conventional sunscreens are designed for ultraviolet.
| 🛡️ Measure | 🔍 What it protects against | 📊 Why it matters here |
|---|---|---|
| Broad-spectrum SPF 50 | Ultraviolet B and A | The baseline. Skin on a high-strength retinoid burns faster and marks more readily |
| A tinted sunscreen containing iron oxides | Visible light in addition to ultraviolet | The addition that matters specifically for melasma and for pigmentation in darker skin |
| A wide-brimmed hat | Direct overhead light across the whole face | More reliable over a day outdoors than reapplying cream that nobody reapplies |
| Shade and timing | Peak intensity in the middle of the day | Free, and larger in effect than any product decision |
| Window glass | Blocks ultraviolet B, lets ultraviolet A and visible light through | A desk by a window, or a long drive, is real exposure for pigmented skin |
| Screens and indoor lighting | A very small contribution compared with daylight | Worth far less attention than it receives. Daylight through a window matters more |
🤔 The second row is the practical upgrade for anyone treating melasma or dark marks. 📊 Iron oxides give a tinted sunscreen its colour and also absorb visible light, which an untinted mineral or chemical sunscreen largely does not. ✅ For pigmentation specifically, switching from a clear sunscreen to a tinted one is a meaningful change rather than a cosmetic preference.
📋 A workable daily standard:
- 💉 Tinted broad-spectrum SPF 50 every morning, every season, applied generously rather than sparingly
- 👓 A hat for any extended time outdoors, which does more than a second application of sunscreen would
- 🚪 Awareness of the window seat, at a desk and in a car, where ultraviolet A and visible light arrive all day
- 🚫 No sunbeds at any point. There is no sensible version of this alongside a high-strength retinoid
💡 One framing helps people take this seriously who otherwise do not. 📊 The retinoid is working to rebuild collagen and clear pigment, and unprotected light exposure is actively undoing both. 🤔 Someone using 0.1 percent without daily photoprotection is paying the full cost of the drug for a fraction of its benefit.
🎨 Tretiheal on Richly Pigmented Skin
🎨 Tretinoin works equally well on every skin tone, and at these strengths it has to be used differently on richly pigmented skin. 📊 The reason is a single mechanism: inflammation triggers pigment production, so irritation that merely looks red on pale skin leaves lasting brown marks on darker skin.
| 🔍 What is different | ✅ What to do about it |
|---|---|
| Irritation leaves pigment behind | Treat visible irritation as a treatment failure rather than a stage to push through. Reduce frequency immediately |
| Redness is harder to see | Judge by sensation. Stinging from water, tightness lasting all day and a greyish dull look are the signals |
| The target is often pigment itself | Which makes an aggressive routine self-defeating. The gentler protocol usually clears marks faster overall |
| 0.1 percent is often unnecessary | 0.05 percent used consistently and comfortably frequently outperforms a stronger version used intermittently |
| Ashy flaking is more visible | A richer moisturiser, applied twice daily as standard rather than when the skin complains |
| Visible light drives pigmentation | A tinted sunscreen with iron oxides rather than a clear one. This is a specific upgrade, not a preference |
🤔 The third and fourth rows together make the central point. 📊 A high-strength retinoid prescribed for dark marks can produce fresh marks faster than it clears existing ones, and the solution is not a different drug but a slower pace. ✅ The work on dermatology in richly pigmented skin has made this the standard approach rather than a cautious exception.
⚠️ A protocol built for pigmented skin at these strengths.
🟡 Start at 0.05 percent, twice a week, buffered from the first night. Hold there for a month before changing anything.
🔶 Add one night every four weeks, and stop adding as soon as the skin shows any sign of irritation.
🔵 Treat 0.1 percent as optional rather than as the destination. Many people get the result they want without ever moving up.
🟢 Tinted sunscreen daily, without exception. For pigmentation this is doing more work than the cream is.
💡 One further point applies to any skin tone and matters most here. ⏳ Pigment responds slowly: three to six months for superficial marks and longer for deeper ones. 📷 Without a photograph from the start, three months of real progress is indistinguishable from no progress at all, and that is when people escalate the strength and undo the gains.
🧪 Why the Cream Base Matters as Much as the Percentage
🧪 Two creams containing the same percentage of tretinoin can behave very differently on the same face, and the difference is the vehicle. 📊 Formulation research has made this a measurable property rather than a marketing claim, and it explains why someone who could not tolerate one tretinoin product may manage another at the same strength.
| 🧴 What varies | 📊 What it changes |
|---|---|
| Cream against gel | Creams carry moisturising components and are gentler. Gels dry faster, feel lighter and are more drying |
| Alcohol content | Alcohol-based vehicles sting noticeably more on skin that is already irritated |
| Emollients in the base | An emollient cream buffers the drug as it delivers it, which is why that formulation was chosen for the photoageing indication |
| How the drug is held in the base | Some formulations release the drug gradually rather than all at once, which reduces the early irritation peak |
| Preservatives and fragrance | A reaction to a tretinoin product is sometimes a reaction to the base rather than to the drug |
| Stability of the finished product | Tretinoin degrades in light and air, and how well a base protects it determines how much drug is still there at month six |
🤔 The last row has a consequence people rarely consider. 📦 A tube stored badly or kept past its date may contain substantially less active drug than the label says, which looks exactly like a treatment that has stopped working. ✅ Before concluding that a strength is no longer effective, the age and storage of the tube are worth checking.
✅ A base that suits dry or sensitive skin
🧴 Cream rather than gel, with emollient content in the base
💧 No alcohol in the vehicle
💤 Tolerates buffering well, layering over moisturiser without pilling
🧼 Minimal fragrance, which removes one variable from any reaction
💧 A base that suits oily skin
🧭 Lighter texture that absorbs without leaving a film overnight
🌙 Comfortable under nothing, for people who dislike layering
💦 Suits humid climates where a rich cream feels unbearable
⚠️ Less forgiving, so frequency matters more than it does with a cream
💡 The practical conclusion is a useful one for anyone who has had a bad experience. 📊 Not tolerating one tretinoin product does not mean not tolerating tretinoin. 🤔 A different base at the same percentage is a genuine option, and it is a more sensible next step than abandoning the drug or dropping two strengths at once.
🌱 Tretiheal, Pregnancy and Planning Ahead
🌱 The pregnancy question is the same for every tretinoin product regardless of strength, and it is the question most often answered with more alarm than the evidence justifies. 📊 The short version: official advice is to avoid, the human data is reassuring, and the two statements are not in conflict.
| 🔍 Question | ✅ Answer |
|---|---|
| Does strength change the answer? | Not materially. Percutaneous absorption is small at every strength, and the advice to avoid applies across the range |
| What do the human studies show? | Larger cohort studies have not demonstrated an increased risk of congenital malformation after topical tretinoin exposure |
| So why avoid it? | Absorption is small rather than zero, isolated case reports exist, and there is no benefit that justifies any uncertainty for nine months |
| I used it before I knew | Stop and mention it at the next appointment. This is not a reason for alarm and the cohort data is genuinely reassuring |
| Is there a waiting period before conceiving? | No. Unlike the oral retinoids, topical tretinoin does not accumulate systemically, so stopping is sufficient |
| What about melasma in pregnancy? | Common, and treated with photoprotection during the pregnancy. Active topical treatment generally waits until afterwards |
🤔 The last row is worth planning around because pregnancy is when melasma most often appears. ☀️ Photoprotection during those months limits how far it develops, and starting it early is considerably more effective than treating established pigment afterwards. 📊 That is one of the few things that can be done during a pregnancy and it is genuinely worth doing.
🚨 Keeping the topical and the oral retinoids separate.
🔴 Oral isotretinoin and acitretin cause severe birth defects. They are controlled by formal pregnancy prevention programmes with testing and contraception requirements.
🟡 Topical tretinoin is a precautionary avoidance, based on small absorption rather than demonstrated harm.
🟢 High-dose oral vitamin A supplements are a genuine concern in pregnancy, and nobody ever mentions them.
🔵 Breastfeeding: avoided as a precaution, and never applied where a baby presses against the skin.
🩺 Anita Sharma MD FACOG on pigmentation and planning
Two things come up every time. The first is panic about a cream used before a pregnancy was known, and my answer is the same each time: the cohort studies have not shown an increase in malformations, and absorption through skin is a couple of percent. Stop it, and stop worrying about it. The second is melasma, which a lot of people get for the first time during pregnancy and assume they will deal with later. That is the wrong order. Protecting the skin from light during the pregnancy limits how far the pigment goes, and established melasma is far harder to treat than melasma that was never allowed to develop. A tinted sunscreen and a hat for nine months is a smaller job than two years of treatment afterwards.
💤 Night Routine Logistics - Transfer, Pillows and Timing
💤 A night-time prescription has practical consequences nobody mentions at the pharmacy, and at these strengths they matter more. 📊 Where the product ends up, how long it stays on, and what touches the face afterwards all affect both the result and the irritation.
🔍 The logistics worth getting right:
- ⏳ Apply at least thirty minutes before lying down. Product that has not absorbed transfers to a pillow, which wastes some of the dose and spreads the rest to places it was not meant for
- 🛏️ Expect transfer to the pillowcase. Change it more often than usual, because a pillowcase carrying old product and oil against a retinised face is an avoidable irritant
- 😵 Watch the sleeping position. People who sleep face-down on one side often notice more irritation on that side, and the explanation is contact rather than coincidence
- 💅 Keep it away from a partner skin. Transfer onto someone who is not expecting a prescription retinoid is common and occasionally produces a reaction
- 🧼 Wash hands after applying, and avoid rubbing your eyes before they are clean
🤔 The first point is the one with a measurable effect on results. 📊 A product applied immediately before sleep loses a proportion of the dose to bedding, and at a high strength that produces an unpredictable exposure rather than a lower one. ✅ Moving the application to an hour before bed solves it and costs nothing.
💡 A workable evening sequence:
🧼 Cleanse early ⏳ Wait 20-30 min 💙 Apply the pea 💤 Moisturise, then 30 min before bed
📊 One further habit is worth building because it protects the whole routine. 📅 Apply at the same point in the evening every night it is used, rather than as the last action before sleeping. 🤔 Routines attached to a fixed moment survive; routines attached to whatever happens last are the ones that get skipped on busy nights, and skipped nights are what actually decide the twelve-month result.
🔬 What a Failing Skin Barrier Looks Like
🔬 The skin barrier is a physical structure rather than a metaphor: a layer of flattened cells held together by lipids, keeping water in and irritants out. 📊 A high-strength retinoid speeds up how fast that layer is replaced, and if the replacement cannot keep pace the barrier stops working.
| 🔍 What you notice | 💡 What it means |
|---|---|
| Water stings on the face | The clearest single sign. Intact skin does not react to plain water, and skin that does has lost its outer layer |
| Products that were fine now burn | A moisturiser used for a year does not suddenly become irritating. The skin changed, not the product |
| Tight and shiny rather than flaky | Flaking is adjustment. A smooth, taut, glazed look is a barrier that has been stripped |
| Moisturiser stops lasting | Water is escaping faster than any product can replace it, which is the definition of barrier failure |
| New sensitivity to heat, wind or cold | The skin has lost its buffer against ordinary environmental changes |
| Spots appearing in unusual places | A compromised barrier can produce breakouts of its own, which get misread as the retinoid failing |
🤔 The last row causes a particularly unhelpful loop. 📊 Spots appear, they are attributed to the acne rather than to the damaged skin, the response is more treatment, and the barrier gets worse. ✅ Recognising the difference stops that cycle, and the clue is usually that the spots are small, uniform and in areas that never used to break out.
✅ A barrier that is coping
💧 Water feels like water, with no stinging at the sink
🌙 Evening redness that has gone by morning
🧼 Moisturiser holds for several hours and the skin feels comfortable between applications
📉 Flaking that lifts off and leaves intact skin underneath
⚠️ A barrier that is failing
🔥 Stinging from water, moisturiser or sunscreen
☀️ Redness all day that has been building for weeks
💦 Dryness returning within minutes of applying anything
😰 A tight, glazed, shiny look rather than visible flakes
💡 One measurement is more useful than any of these descriptions. 📅 Does the skin feel normal twelve hours after application? 📊 Evening reaction after a high-strength retinoid tells you very little, and morning condition tells you almost everything. ✅ Skin that is comfortable at breakfast is coping, whatever it looked like the night before.
🧰 A Rescue Protocol for Over-Treated Skin
🧰 Once a barrier has been damaged, the answer is not a gentler retinoid, it is a pause and a rebuild. 📊 Trying to continue through genuine barrier failure extends the recovery from two weeks to two months and achieves nothing in between.
🤔 The second step causes the most resistance and does the most work. 📊 People in this situation often add products, reaching for soothing serums, barrier creams and anything marketed for sensitivity, which introduces several new variables into skin that cannot currently tolerate any of them. ✅ Fewer products, used consistently, recovers faster than more products used hopefully.
⚠️ There is a point at which this stops being a routine problem. 🚨 Skin that is weeping, crusted, swollen or open, or that has not improved after two weeks of doing nothing to it, needs a clinician rather than patience. 🔍 Severe irritant dermatitis is treatable, and what it is usually treated with is a short course of a mild topical steroid, which is a prescribing decision rather than something to improvise.
💡 One question is worth answering honestly during the recovery. 🤔 What caused it? 📊 Almost always it is one of four things: too much product, too often, applied to damp skin, or layered with an acid. ✅ Restarting without identifying which one simply schedules the next episode, and in most cases the person already knows the answer.
🩹 Tretiheal Side Effects From Common to Rare
🩹 Topical tretinoin has no systemic side effects worth monitoring at any strength, and a long list of local ones that scale with concentration. 📊 At 0.05 and 0.1 percent the common entries are more common and the uncommon entries become realistic.
| 📊 How often at this strength | 🔍 What happens | ✅ What to do |
|---|---|---|
| Nearly everyone | Dryness, flaking, tightness and redness through the first two months | Expected. Moisturise, buffer, reduce frequency rather than stopping |
| Very common | Stinging on application, increased sun sensitivity, and an early worsening of acne | Apply to fully dry skin, use sunscreen daily, and wait out the flare |
| Common | Cracking at the corners of the nose and mouth, and skin colour changes where the cream is applied | Barrier ointment in the creases beforehand. Colour changes usually settle after stopping |
| Less common | A severe irritant reaction with raw, swollen or weeping skin, usually from layering or overuse | Stop entirely, rebuild the barrier, and restart lower. This becomes realistic at 0.1 percent |
| Less common | Pigmentation caused by the irritation, particularly on richly pigmented skin | Reduce intensity immediately. This is the one side effect that works directly against the treatment |
| Uncommon | Worsening of underlying rosacea, with flushing and burning rather than flaking | Needs a diagnosis. A high-strength retinoid on rosacea usually makes it worse |
| Rare | True allergic contact dermatitis to tretinoin or to a component of the base | Stop and ask about patch testing. Itch that climbs is the pattern, rather than stinging that fades |
🤔 One feature of this list sets topical tretinoin apart from its oral relative and is worth stating plainly. 📊 There are no blood tests, no liver or lipid effects and no pregnancy prevention programme, because absorption is around one to two percent and blood levels stay within the range the body produces naturally. 🔍 Everything above happens on the surface of a face, which is also why every entry is adjustable.
🚨 Stop applying and get it assessed for any of these.
🔴 Weeping, crusting, blistering or open cracks. Past irritation, and the skin needs treating before any retinoid returns.
🔴 Swelling, especially around the eyes or lips. Irritant and allergic reactions both do this and they need separating.
🔴 Itching that increases day on day and spreads beyond the treated area. The signature of contact allergy.
🔴 Central facial burning and flushing that worsens week by week. Worth excluding rosacea before continuing.
💡 One widely believed claim deserves correcting here because it comes up most at high strengths. 📊 Tretinoin does not thin the skin. 🔬 It temporarily thins the outermost dead layer while thickening the living epidermis and increasing collagen in the dermis beneath. 🤔 The belief comes from topical steroids, which genuinely do cause thinning, and the two get conflated because both are prescription creams for the face.
🔁 Plateaus, Tolerance and Why Strength Is Not the Answer
🔁 Somewhere around month six or eight, progress on a retinoid stops being visible. 📊 That plateau is normal, it is not the drug losing effect, and the instinct it produces, to increase the strength, is usually the wrong response.
| ❓ What people conclude | 🤔 What is usually happening |
|---|---|
| The skin has become tolerant to the drug | What has developed is tolerance to the irritation, not to the effect. Less stinging does not mean less action |
| It has stopped working | Most of the fast gains come early. The slower, structural changes continue and are harder to see month to month |
| A higher strength would restart progress | Sometimes true at a genuine plateau after a year. Often it simply restarts the irritation without restarting results |
| Nothing has changed in six months | Without photographs this is an impression rather than an observation, and the impression is unreliable |
| The tube must be weaker than it says | Possible, and worth checking. Tretinoin degrades with light, air and age, and a two-year-old tube delivers less than a new one |
| Something in the routine is working against it | Frequently the answer. Missed nights, a harsh cleanser, or benzoyl peroxide applied at the same time |
🤔 The first row is the most useful correction in this section. 📊 Reduced stinging after several months is skin that has adapted, which is exactly the desired outcome, and it is routinely misread as the drug wearing off. ✅ A comfortable routine at month eight is a working routine, not an exhausted one.
📊 When a genuine plateau has been reached and everything else has been checked, there are three reasonable moves and increasing the strength is only one of them. 📅 More nights per week at the current strength raises total exposure with less barrier shock. 🧴 A different vehicle at the same percentage can change delivery. 💉 Adding a second agent for the specific problem, such as a depigmenting agent for pigment, addresses what a retinoid alone does not.
💡 One realistic expectation underpins all of it. ⏳ The structural changes in sun-damaged skin were measured over ten to twelve months in the original research, and they do not announce themselves monthly. 📷 Someone at month seven who feels nothing is happening and has photographs from month zero is usually in for a surprise, and someone without photographs will simply never know.
🧫 Conditions That Mimic a Retinoid Reaction
🧫 Not every reaction on a face using tretinoin is caused by the tretinoin. 📊 Several common conditions look exactly like retinoid irritation, respond to completely different treatment, and get worse while the strength is being adjusted up and down.
| 🔍 Condition | 👀 How it differs |
|---|---|
| Perioral dermatitis | Small red bumps clustered around the mouth, often sparing a thin border at the lip line, that itch and burn. Needs specific treatment and does not respond to adjusting a retinoid |
| Seborrhoeic dermatitis | Greasy yellowish scale beside the nose, in the eyebrows and at the hairline. It looks like retinoid flaking in exactly the places a retinoid flakes, and it is treated with antifungals |
| Rosacea | Central facial redness with flushing triggered by heat, alcohol or spice, often with visible vessels. Burning rather than flaking is the signature |
| Allergic contact dermatitis | Itch that builds over days and spreads past where anything was applied, sometimes with small blisters. Often to a preservative rather than to the drug |
| Fungal infection on the face | An expanding patch with a defined scaly edge, usually on one side only. Uncommon, and entirely different in treatment |
| Simple over-treatment | Diffuse, symmetrical, confined to where the product goes, and improves within days of stopping. The commonest explanation by far |
🤔 The two most useful distinguishing features are symmetry and response to stopping. 📊 Retinoid irritation is even across both sides of the face and improves within days of a pause. 🔍 A problem that is one-sided, patchy, or that carries on unchanged after a week of doing nothing is pointing at something else.
⚠️ Signs that the problem is not the retinoid.
🟡 It is worse on one side of the face, or confined to one patch with a clear edge.
🔶 A week of stopping changed nothing. Retinoid irritation improves noticeably within days.
🔵 It itches more than it stings, and the itch is building rather than fading.
🔴 It appeared months into a routine that was comfortable, without any change in product or frequency.
💡 One practical rule follows. 📊 A week off answers the question cheaply. 🤔 If the skin improves clearly in that week, the retinoid or the way it was being used was the problem. ✅ If nothing changes, the next step is a diagnosis rather than another adjustment to the strength.
✂️ Procedures and Appointments Around Tretiheal
✂️ Skin running at 0.05 or 0.1 percent is thinner at the surface, heals more slowly and reacts more strongly than untreated skin, which changes how it should be handled in a treatment room. 📊 The pauses below are longer than they would be at a lower strength.
| 🧼 Procedure | ⏱️ Typical pause | 💡 Why |
|---|---|---|
| Facial waxing or threading | One to two weeks before, and until settled afterwards | Wax lifts a layer of skin with the hair. At high strength that layer is thinner and the tear is larger |
| Chemical peel | One to two weeks, as directed by the practitioner | A peel on retinised skin penetrates deeper than intended and the result is unpredictable |
| Laser and energy devices | Decided by the practitioner, often one to two weeks either side | Slower healing and a higher risk of lasting pigment change, particularly in darker skin |
| Microneedling and dermaplaning | About a week either side | Both deliberately injure the surface, which is what a high-strength retinoid handles worst |
| Shaving | None | Fine with a sharp blade and a lubricating product. A blunt razor on dry skin is the problem |
| Injectable treatments | Usually none, unless the skin is actively irritated | These pass beneath the surface rather than removing it |
🤔 The rule behind the table is the same as at any strength and the margins are tighter. 📊 Anything that removes a layer of skin needs a pause; anything that goes underneath it does not. ⚠️ At 0.1 percent the pause is longer because the layer being removed is thinner to begin with.
💡 One point of etiquette saves trouble on both sides. 📞 Mention the strength when booking, not on arrival. 📊 A practitioner who knows there is 0.1 percent tretinoin involved will plan the appointment around it, adjust the intensity of a peel or laser setting, and in some cases decline until there has been a pause. ✅ Discovering it mid-treatment is considerably worse for everybody.
💦 Sweat, Sport and Hot Climates on Tretiheal
💦 Heat, sweat and humidity change how a high-strength retinoid feels and how it behaves, and the effects run in both directions depending on the climate.
🔍 What actually changes:
- 🔥 Heat increases blood flow in the skin, which makes any existing redness more obvious and stinging more noticeable for an hour or two after exercise
- 💧 Sweat does not wash the drug off if it is applied at night, because absorption is largely complete well before morning
- 🏕️ Dry heat and air conditioning increase water loss, which is the main reason a routine that was comfortable in autumn flakes in a heated flat in January
- 💨 Humid climates suit lighter formulations, and a rich cream that worked through a European winter may feel unbearable in a tropical summer
- ☀️ Hot weather usually means more sun, and that is the variable that genuinely matters rather than the temperature itself
🤔 The second point is worth stating clearly because it causes unnecessary anxiety. 📊 Someone who applies tretinoin at night and trains at seven the next morning has not washed off their treatment. ✅ The exposure happened overnight, and sweating afterwards affects comfort rather than efficacy.
💡 Practical adjustments by situation:
❄️ Winter: one night fewer 💦 Humid: lighter base ☀️ Beach holiday: pause 🏃 Training: apply at night
⚠️ One situation deserves a proper pause rather than an adjustment. 🏖️ A holiday with sustained strong sun is the worst possible setting for skin running at 0.1 percent, and the sensible move is to stop a week before and restart at reduced frequency afterwards. 📊 Burning a face that is mid-adjustment sets the routine back further than a two-week pause ever would.
🔗 Combining Tretiheal With Other Treatments
🔗 A high-strength retinoid changes what else can sensibly go on the same face, because the margin for additional irritation has already been spent. 📊 Some combinations are standard practice, some are a matter of timing, and one destroys the drug.
| 🧪 Alongside | ✅ Position | ⏱️ Timing |
|---|---|---|
| Benzoyl peroxide | Useful for inflammatory acne, which a retinoid alone handles less well | Morning only. Applied together it oxidises the tretinoin, with early work reporting around half degraded within two hours |
| Oral antibiotics | Standard for moderate inflammatory acne, such as Vibramycin (doxycycline) | Taken alongside. The retinoid continues after the antibiotic course ends |
| Hormonal treatment | Addresses a driver that a topical cannot reach, such as Aldactone (spironolactone) in some adult women | Alongside, with no interaction between them |
| Oral isotretinoin | For severe or scarring acne, such as Isofair (isotretinoin) | Topical retinoids are stopped during the course and often resumed afterwards as maintenance |
| Acids and exfoliants | Rarely justified at these strengths. The retinoid is already accelerating turnover | Best dropped entirely rather than scheduled around |
| Another retinoid | No. Retinol, adapalene or a second tretinoin product adds irritation and no benefit | One retinoid at a time, and tretinoin is the strongest of the topical options |
🤔 The first row is the one with a mechanism rather than a preference behind it. 📊 Benzoyl peroxide oxidises tretinoin, and the older stability work reported substantial degradation within hours of co-application. ✅ Some newer products are formulated to hold both stably; two separate tubes applied one after the other are not, and separating them by time of day costs nothing.
🩺 Sarah Mitchell PharmD on what people bring to the counter at this strength
Someone on 0.1 percent asking what else they should add is usually asking the wrong question. At this concentration the limiting factor is almost never potency, it is how much the skin can take, and adding anything active spends a margin that has already gone. The request I get most is for an acid to deal with flaking, and that is the one combination that reliably produces a damaged face. What I suggest instead is boring and it works: a heavier moisturiser and one fewer night that week. The other thing I check is where the benzoyl peroxide is in the routine, because if it is going on at the same time as the tretinoin, part of the dose is being destroyed before it does anything, and nobody has noticed.
💡 One structural point applies through all of it. 📊 Whatever is added for a particular phase, the retinoid is the part that continues. 🔍 Antibiotic courses end, hormonal treatment comes and goes with circumstances, and a topical retinoid runs through all of it and afterwards as maintenance.
📆 A Realistic Twelve-Month Plan on Tretiheal
📆 A year is the honest unit for this treatment. 📊 The acne answer arrives in the first quarter, pigment in the middle, and the structural changes in sun-damaged skin are measured at the end, which is where the original research drew its conclusions.
🤔 The first band is where most people make their judgement and it is the one band that contains no information about the outcome. 📊 Weeks two to eight at 0.1 percent are about whether the skin adapts, not about whether the drug works, and those are completely different questions.
| 📅 Checkpoint | ✅ What should be true | 🚨 What is a problem |
|---|---|---|
| Month 1 | Flaking, tightness, perhaps more spots. Two nights a week being tolerated | Water stinging, raw patches, redness all day |
| Month 3 | Skin comfortable at three or four nights, texture visibly smoother, fewer new blackheads | Still peeling constantly, or no change in acne at all with consistent use |
| Month 6 | Dark marks lighter, tone more even, routine running without thought | Pigmentation worse than at the start, which points at irritation driving it |
| Month 9 | A plateau in visible change, which is normal and not a reason to escalate | Nothing, if the earlier checkpoints were met |
| Month 12 | The photoageing comparison against the starting photographs. Texture, tone and fine lines | No photographs, in which case the year cannot be assessed at all |
💡 The last row is the only entry on this page that cannot be fixed retrospectively. 📷 Photographs at the start, in daylight, from a fixed angle. 📊 Everything else in a twelve-month plan can be adjusted along the way; a missing baseline cannot be recreated at month twelve, and without it the result is a matter of opinion.
🍷 Alcohol, Diet and What Matters Less Than You Think
🍷 Alcohol has no interaction with topical tretinoin at any strength. 📊 Absorption is around one to two percent, nothing meaningful reaches the liver, and there is no laboratory value to watch. 🤔 The same goes for most of the dietary advice attached to retinoids online.
✅ What genuinely affects skin on a high-strength retinoid, and what does not.
🟩 Does matter: smoking. It accelerates the collagen breakdown the treatment is working against, and no concentration outruns it.
🟢 Does matter: dehydration. Skin that is already drier than usual handles a heavy night badly, and the flaking the next day is noticeably worse.
🔵 Does matter a little: flushing. Alcohol dilates facial vessels, which is relevant mostly for anyone whose redness is being watched for rosacea.
🔶 Does not matter: vitamin A in food. Dietary vitamin A does not add to or subtract from a topical retinoid, and there is no reason to change what you eat.
🤔 One qualification belongs with the last point. 💉 High-dose oral vitamin A supplements are a different matter from food, and they are worth avoiding, particularly for anyone who might become pregnant. 📊 That caution has nothing to do with the cream and everything to do with the supplement.
💡 Three things outrank every dietary question for anyone on this treatment:
☀️ Daily photoprotection 🚫 Not smoking 📅 Not missing nights
📊 That third item is the one that quietly decides outcomes and never appears in advice about diet. 🤔 A routine applied four nights a week instead of five, across a year, is a twenty percent reduction in cumulative exposure, which is a larger difference than anything on a plate. ✅ Attaching the application to a fixed point in the evening does more for the result than any supplement ever will.
🧊 Keeping a 20 Gram Tube of Tretiheal Potent
🧊 Tretinoin degrades, and a 20 gram tube used at a pea a night lasts long enough for that to matter. 📊 A product kept badly delivers less drug than the label states, which looks exactly like a treatment that has stopped working and is far cheaper to fix.
| ⚠️ What degrades it | ✅ What to do |
|---|---|
| Light, especially daylight | A drawer or a closed cupboard. Never a window sill, an open shelf or a transparent bag |
| Air, once the tube is open | Cap it every night. The cap is not decorative on this particular product |
| Heat and humidity | Room temperature away from radiators. A bathroom that steams up twice daily is the worst common option |
| Time | Check the expiry date before blaming the strength. A 20 gram tube can outlive its date comfortably |
| Separation or colour change | Replace it. A separated cream delivers an unpredictable dose, which at 0.1 percent is a real problem |
🤔 The fourth row produces a specific and avoidable frustration. 📊 Someone two years into a routine notices it has stopped working, increases the strength, gets a face full of irritation, and the original problem was a tube that had quietly lost potency. ✅ Checking the date is free and comes before any escalation.
💡 Storage in three parts:
🌡️ Room temperature 🌑 Dark and closed 🔒 Out of reach of others
✈️ Travelling needs one adjustment and no special measures. 📦 The tube goes in a bag rather than a car, and a tube left in a sunlit hotel bathroom for a fortnight loses potency exactly as it would on a window sill at home. 🗑️ Leftovers go back to a pharmacy, and a prescription-strength retinoid is never passed to someone else for a skin problem nobody has looked at.
💰 How Long a Tube Lasts and What That Tells You
💰 How fast a tube empties is a measurement rather than a detail. 📊 A pea is roughly a quarter of a gram, so a 20 gram tube holds around 80 applications, and that number tells you more about how a routine is actually being run than any description of it would.
🔍 What the arithmetic reveals:
- 📅 Nightly use empties a tube in under three months. About 80 applications at seven a week is eleven weeks
- 📉 Four nights a week stretches it to roughly five months, which is the pattern many people settle at permanently
- ⚠️ A tube gone in six weeks means far more than a pea is being used. That is the single most useful diagnostic in this guide for unexplained irritation
- 📦 A tube lasting over a year means very infrequent use, which is a legitimate maintenance pattern but will not produce the results the trials measured
🤔 The third point is worth acting on directly. 📊 Somebody whose face is constantly irritated at 0.1 percent and whose tube lasts six weeks has answered their own question without realising it. ✅ Correcting the quantity solves the irritation without changing the strength or the frequency, and costs nothing.
💡 The numbers worth remembering:
💙 1 pea ≈ 0.25 g 📦 20 g ≈ 80 nights 📅 4 nights a week ≈ 5 months
📊 One practical consequence follows for anyone planning a long course. 🤔 At four or five nights a week, a year of treatment needs roughly two to three tubes, and running out mid-routine is a common cause of unplanned gaps. ✅ Ordering the next tube before the current one is empty keeps the exposure continuous, which is the thing the whole result depends on.
👁️ High-Strength Tretinoin Near the Eyes and Neck
👁️ A face is not uniform, and at 0.1 percent the differences between areas stop being academic. 📊 The same pea that is comfortable on a cheek produces swelling on an eyelid and lasting irritation on a neck.
| 📍 Area | ✅ At 0.05 and 0.1 percent |
|---|---|
| Eyelids | Avoid. The thinnest skin on the body, and product in the eye stings severely |
| Under the eyes | Not at these strengths without specific direction. Some dermatologists treat this area deliberately, at a lower concentration |
| Creases beside the nose | Product pools here and cracks the skin. A barrier ointment applied first prevents most of it |
| Lips and the lip border | Avoid, and apply balm beforehand so the border is protected from migration overnight |
| Neck | Thinner and more reactive than the face. If treated at all, use the lower strength, less often, and buffered |
| Chest | Heavily sun-damaged in most adults and slow to tolerate. Treat long after the face has settled |
| Backs of the hands | Tolerate it well, show sun damage clearly, and are a reasonable area to extend to |
🤔 The neck is the area where high-strength tretinoin most often goes wrong. 📊 Skin there is thinner than facial skin, has fewer oil glands, and is usually more sun-damaged, so it is simultaneously a worthwhile target and a poor one. ✅ If it is treated at all at this strength, it is treated last, least often and with the most buffering.
💡 One technique prevents most accidental exposure overnight. 📌 Spread outward and upward from the dots, and leave a deliberate margin around the eyes, nostrils and lips. 📊 Most of the stinging people report around the eyes at these strengths comes from product migrating during the night rather than from direct application, and a wider margin at the start removes it entirely.
🚫 Claims About Tretinoin That Do Not Hold Up
🚫 Tretinoin attracts more extravagant claims than any other prescription cream, and at the higher strengths the claims get larger. 📊 Separating what is established from what is assumed is what makes the real benefits credible.
| 💬 The claim | 🔍 What is actually true |
|---|---|
| 0.1 percent works twice as well as 0.05 | Reported results at one year are similar. The higher strength appears to arrive sooner rather than reach further |
| It tightens and lifts the skin | No. It improves quality, texture, tone and fine lines. Laxity and deep folds are structural and unaffected |
| It shrinks pores | Pores look smaller when less congested and the surrounding skin is in better condition. The opening does not change size |
| It removes acne scars | No. Indented and raised scars need resurfacing or surgical techniques. Flat marks are not scars and do fade |
| Peeling means it is working | Peeling means the skin is irritated. The drug works at concentrations that cause no visible peeling at all |
| It thins the skin over years | The opposite. The living epidermis thickens and dermal collagen increases. The myth comes from topical steroids |
| Applying more makes it work faster | Receptors saturate. The surplus produces irritation, and irritation on pigmented skin produces marks |
🤔 The fifth row is the most consequential belief on this list. 📊 People at 0.1 percent frequently treat visible peeling as confirmation that the strength is correct, and it is confirmation of the opposite. ✅ The target is the most exposure the skin absorbs without inflammation, and a comfortable face at month six is a better sign than a flaking one.
💡 What survives all those subtractions is still considerable, and it is worth saying plainly. ✅ Tretinoin clears and prevents blocked pores, fades the marks left by old spots, evens mottled pigmentation, smooths rough texture, softens fine lines and increases collagen formation in sun-damaged skin. 📊 Those effects were measured in controlled trials over decades, and nothing sold as a cosmetic has anything comparable behind it.
⏰ Interruptions, Restarts and Losing Tolerance
⏰ At 0.05 and 0.1 percent, tolerance is something the skin builds and then loses, and restarting after a gap at the previous frequency is one of the commonest ways to produce an avoidable bad fortnight.
| ❓ Length of the gap | ✅ How to restart |
|---|---|
| One or two nights | Carry on as normal. Never apply twice to compensate |
| A week | Restart at the same frequency. Tolerance has not meaningfully faded |
| Two to four weeks | Drop a night or two for a fortnight, then return. At this strength the difference is noticeable |
| Several months | Restart as if beginning: twice a week, buffered, building over eight to twelve weeks |
| Stopped because the skin was damaged | Restart at a lower strength, not the same one. Returning to what caused it repeats the outcome |
| Paused for a procedure or holiday | Planned pauses are fine and lose very little. Restart one night below the previous frequency for a fortnight |
🤔 The fourth row surprises long-term users most. 📊 Skin that ran comfortably at five nights a week for two years will often peel if treatment restarts at that level after a few months away, and the explanation is simply that tolerance is maintained by continued exposure. ✅ Two weeks of rebuilding costs almost nothing against the alternative.
💡 One pattern accounts for most failures at these strengths and is worth naming. 🔄 Three weeks on, a bad week, stop, restart at the same level, another bad week, stop. 📊 That cycle produces every unpleasant aspect of the drug and none of the benefit, because the skin never passes through the adjustment and the cumulative exposure never accumulates. ✅ Reducing frequency without stopping breaks it, and it is almost always available as an option.
💬 What to Tell a Prescriber at a Tretiheal Review
💬 A long-term prescription deserves an occasional review, and at these strengths a review is more useful than at a lower one because there are more variables to adjust. 📊 What makes it useful is turning up with information rather than an impression.
📋 What to bring, and what to ask:
- 📷 Photographs from the start and from now, in the same light and at the same angle. This converts the whole conversation from opinion into comparison
- 📅 How many nights a week, honestly, averaged across the last three months rather than the best week
- 📦 How fast the tube empties, which reveals the quantity being used more reliably than any description of a pea
- 🧴 Everything else that goes on the face, including cleansers and anything bought since the last appointment
- ❓ Whether the strength still fits the goal. Someone whose acne cleared two years ago may be running a concentration chosen for a problem that no longer exists
- ❓ What would make you change the plan? Hearing the specific triggers in advance turns a long routine into one with checkpoints
🤔 The fifth item is the one most worth raising and the one least often raised. 📊 Strengths get chosen for a situation and then persist long after that situation has changed, and someone treating photoageing may reasonably stay at 0.1 percent while someone whose acne resolved years ago may do better on less. ✅ That is a decision to revisit rather than to inherit indefinitely.
💡 One last thing is worth saying to anyone taking this seriously enough to read to the end. 📊 The evidence in this field points consistently at duration and consistency rather than at concentration. 🤔 A person using 0.05 percent four nights a week for five years has accumulated more exposure, with less disruption, than one who cycled through 0.1 percent in bursts. ✅ The strength on the tube is the least important decision in this guide.
⛔ Tretiheal Contraindications and When to Avoid It
⛔ The absolute contraindications for tretinoin are the same at every strength. 📊 What changes at 0.05 and 0.1 percent is the middle band, where a number of situations that would be workable at a lower concentration become reasons to use something gentler.
🚫 Absolute — do not use
Known hypersensitivity to tretinoin or to any ingredient in the cream · in or around the eyes, on the eyelids, on the lips or on any mucous membrane · on broken, sunburnt, eczematous or actively inflamed skin · alongside another topical retinoid on the same area · during a course of an oral retinoid, unless a dermatologist has specifically directed it
⚠️ At these strengths specifically, use something gentler or get direction first
Never having used a retinoid before · dry, sensitive or eczema-prone skin · rosacea or undiagnosed persistent facial flushing · treating melasma or dark marks on richly pigmented skin, where irritation generates pigment · the neck and chest · pregnancy and breastfeeding, where the advice is to avoid as a precaution · the weeks around waxing, peels, laser or microneedling · a holiday with sustained strong sun · anyone who cannot use sunscreen daily · a face that is already red or peeling from anything else
✅ Not contraindications, despite being assumed to be
Using moisturiser, which helps rather than hinders · buffering, which makes the routine survivable · being over fifty · years of previous retinoid use · oily skin · alcohol · exercise and sweating · wearing make-up · winter · any tablet taken by mouth · having reacted badly to a different tretinoin product, since the base may have been the problem · using it three nights a week rather than nightly
🤔 The amber band is longer here than it would be for a lower strength, and that is the honest difference this product carries. 📊 Most of those entries are not bars at all; they are reasons to use 0.025 or a different retinoid rather than reasons to avoid the drug. ✅ The question at 0.1 percent is rarely whether a retinoid is appropriate, and usually whether this concentration of it is.
📋 Four questions settle almost every case:
- 📊 Have I already tolerated a lower strength comfortably? If not, the higher concentration is the wrong starting point regardless of the goal
- 🎯 What am I treating? Pores respond at any strength. The argument for 0.1 percent is strongest for photodamaged skin
- ☀️ Will I protect the skin from light every day? Without that, this strength costs more than it delivers
- 📅 Can I keep it going for a year? The result depends on cumulative exposure, and a gentler routine sustained beats a stronger one abandoned
✅ Used patiently at a concentration the skin can hold, tretinoin at these strengths does everything the lower ones do and reaches it sooner, with the strongest evidence in the field behind it. ⚠️ Used impatiently, in too large a quantity, layered with acids and judged at week four, it produces a damaged barrier, fresh pigmentation and an abandoned prescription. 📊 The difference between those outcomes is decided almost entirely in the first twelve weeks.
Tretiheal — Frequently Asked Questions
-
What is Tretiheal (Tretinoin) cream used for?
Tretiheal cream is primarily used to treat acne, reduce fine wrinkles, smooth rough skin, and improve pigmentation caused by sun exposure. It promotes cell turnover and helps maintain healthier, clearer, and rejuvenated skin with consistent use. -
How does Tretiheal (Tretinoin) work on the skin?
Tretinoin works by increasing the speed of skin cell turnover. This unclogs pores, reduces the formation of acne lesions, stimulates collagen production, and gradually improves skin texture, tone, and overall appearance. -
How long does it take to see results with Tretiheal?
Most patients begin to notice initial improvements within 4 to 6 weeks of consistent use. Significant benefits, such as reduced acne and improved skin texture, may take up to 12 weeks or longer. -
Can Tretiheal help with acne scars?
Yes, Tretiheal can improve the appearance of acne scars over time. By stimulating collagen and promoting skin renewal, it smooths out rough areas and helps fade post-acne marks gradually. -
Is Tretiheal effective for wrinkles and fine lines?
Tretiheal is considered one of the most effective topical treatments for reducing fine lines and wrinkles. It stimulates collagen production and improves skin elasticity, which helps maintain a youthful appearance. -
Does Tretiheal lighten dark spots and pigmentation?
Yes, Tretiheal is clinically proven to reduce hyperpigmentation and dark spots caused by sun damage, aging, or acne. Regular use helps achieve a more even and radiant skin tone. -
What skin types can use Tretiheal safely?
Tretiheal is suitable for oily, acne-prone, and photoaged skin. Sensitive or very dry skin types may experience irritation, so lower concentrations or adjusted usage schedules are often recommended by dermatologists.
See all Tretiheal questions (32)
📚 Drug Description Sources:
The information in this Tretiheal (tretinoin 0.05 percent and 0.1 percent cream) guide is compiled from authoritative pharmaceutical, medical, and regulatory sources covering the licensed product information for topical tretinoin, the comparative evidence between retinoid strengths, the research on pigmentation and melasma in which tretinoin is one component, and the work on environmental skin ageing that explains what a retinoid can and cannot hold back.
🏛️ Regulatory and government agencies
- FDA approved labeling for topical tretinoin cream, 0.025, 0.05 and 0.1 percent - the prescribing information covering once-daily night-time application, the expected early worsening of acne, photosensitivity, and the instruction to avoid the eyes, mouth and mucous membranes
- FDA approved labeling for tretinoin emollient cream 0.05 percent - the 1995 approval for the palliation of fine facial wrinkles, mottled hyperpigmentation and tactile roughness of photodamaged skin
- Medicines and Healthcare products Regulatory Agency guidance on topical retinoids - the United Kingdom regulatory position, including the precautionary advice against use in pregnancy
- UK Teratology Information Service monograph on tretinoin in pregnancy - the summary that no increased risk of congenital malformation has been shown in larger cohort studies, alongside the continuing advice to avoid
- Central Drugs Standard Control Organisation product information for tretinoin cream, India - the regulatory basis for the Indian-manufactured generic supplied as Tretiheal by Healing Pharma
📚 Professional societies and clinical guidelines
- Reynolds RV, Yeung H, Barbieri JS et al. Guidelines of care for the management of acne vulgaris. J Am Acad Dermatol 2024 - the American guideline placing topical retinoids at the base of acne treatment and addressing maintenance after clearance
- European evidence-based (S3) guideline for the treatment of acne - the European position on retinoid selection and on combination treatment
- Pigmentary Disorders Academy and international Delphi consensus statements on melasma management - the expert consensus on where a retinoid fits among depigmenting agents and on the central role of photoprotection
- Skin of Color Society guidance on treating pigmentary disorders in richly pigmented skin - the standard on balancing efficacy against the irritation that itself produces pigmentation
- British Association of Dermatologists patient guidance on topical retinoids - the patient-facing standard on application, irritation and sun protection
🔬 Landmark clinical research
- Griffiths CEM, Russman AN, Majmudar G et al. Restoration of collagen formation in photodamaged human skin by tretinoin. N Engl J Med 1993;329:530-535 - the trial conducted at 0.1 percent, the strength supplied in this product, reporting an 80 percent increase in collagen I formation over 10 to 12 months against a 14 percent fall with vehicle
- Weiss JS, Ellis CN, Headington JT et al. Topical tretinoin improves photoaged skin: a double-blind vehicle-controlled study. JAMA 1988 - the first controlled demonstration that a topical treatment measurably improves sun-damaged skin
- Rivas M, Rendon MI et al. and the Cochrane review of interventions for melasma - the systematic review finding that a triple combination containing tretinoin outperformed hydroquinone alone, with a relative risk of about 1.58 (95 percent confidence interval 1.26 to 1.97)
- Chan R, Park KC, Lee MH et al. A randomized controlled trial of a fixed triple combination (fluocinolone acetonide 0.01 percent, hydroquinone 4 percent, tretinoin 0.05 percent) compared with hydroquinone 4 percent in Asian patients with moderate to severe melasma. Br J Dermatol 2008 - 64.2 percent of patients on the triple combination reached none or mild severity at week 8, against 39.4 percent on hydroquinone alone
- Passeron T, Picardo M. Melasma, a photoaging skin disorder. Pigment Cell Melanoma Res 2018 - the reframing of melasma as a disorder of photoageing in genetically predisposed skin, which explains why photoprotection outweighs every topical agent used for it
- Krutmann J, Bouloc A, Sore G, Bernard BA, Passeron T. The skin aging exposome. J Dermatol Sci 2017 - the account setting out the full set of environmental exposures that age skin, of which ultraviolet light is only the largest single component
📖 Medical references and textbooks
- Fitzpatrick Dermatology in General Medicine, Ninth Edition, McGraw Hill - the chapters on retinoid pharmacology, photoageing and disorders of pigmentation
- Bolognia Dermatology, Fifth Edition, Elsevier - the comparative account of topical retinoids, vehicles and tolerability
- Rook Textbook of Dermatology, Ninth Edition, Wiley Blackwell - the reference material on acne, melasma and post-inflammatory pigmentation
- Martindale: The Complete Drug Reference, Pharmaceutical Press - the tretinoin monograph, including percutaneous absorption and stability data
- Draelos ZD. Cosmetic Dermatology: Products and Procedures, Wiley Blackwell - the reference work on topical vehicles, formulation and how a base changes what a drug does on skin
- DermNet, New Zealand Dermatological Society - the clinical descriptions of retinoid dermatitis, melasma and post-inflammatory hyperpigmentation
Note: This guide covers tretinoin at the higher strengths, 0.05 and 0.1 percent. It assumes a reader who has either used a retinoid before or been prescribed one of these strengths by a clinician, and it does not replace the product information supplied with the tube or the advice of the prescriber who examined the skin.
🩺 Medical Expert Review:
Content reviewed for accuracy against the published work of dermatology authorities with particular expertise in pigmentary disorders, photoprotection, environmental skin ageing, dermatology in richly pigmented skin, and the formulation science behind topical products. The following experts represent authoritative research and clinical practice perspectives relevant to high-strength topical tretinoin.
Prof. Thierry Passeron, MD, PhD
Professor of Dermatology and Head of the Department of Dermatology, University Hospital of Nice, Universite Cote d Azur — Nice, France
Co-author of Melasma, a photoaging skin disorder, the paper that reframed melasma as a condition driven by chronic light exposure in genetically predisposed skin rather than a simple pigment problem. His research covers pigmentary disorders, lasers and melanoma, and he has contributed to the international consensus work on how melasma should be treated. That reframing is the reason photoprotection, rather than any single cream, carries most of the result in pigmentation.
Prof. Henry W. Lim, MD
Senior Vice President of Academic Affairs and Chair Emeritus of the Department of Dermatology, Henry Ford Health — Detroit, Michigan, USA
A world authority on photodermatology and photoprotection, President of the International League of Dermatological Societies, past President of the American Academy of Dermatology, and recipient of the Academy Gold Medal Award for lifetime achievement. His work on how visible light as well as ultraviolet drives pigmentation is the reason modern photoprotection advice for pigmented skin goes beyond a conventional sunscreen.
Prof. Jean Krutmann, MD
Director of the IUF Leibniz Research Institute for Environmental Medicine and Professor of Dermatology and Environmental Medicine, Heinrich Heine University — Dusseldorf, Germany
Lead author of The skin aging exposome, the account setting out the full set of environmental exposures that age human skin, of which ultraviolet light is the largest single component among several. His institute has published on air pollution, heat and humidity as independent contributors to visible ageing. That work sets the realistic ceiling on what any topical retinoid can achieve against the conditions a face is actually exposed to.
Prof. Andrew F. Alexis, MD, MPH
Professor of Clinical Dermatology and Vice-Chair for Diversity and Inclusion, Department of Dermatology, Weill Cornell Medicine — New York, USA
Past President of the Skin of Color Society and director of the Skin of Color Center for more than fifteen years before moving to Weill Cornell. His research addresses the problem that defines retinoid use in richly pigmented skin: irritation itself produces pigmentation, so a treatment prescribed for dark marks can generate them if it is used too aggressively. His work established the gentler protocols that make a high-strength retinoid usable in these patients.
Dr Zoe Diana Draelos, MD
Clinical Faculty, Department of Dermatology, Duke University, and founder of Dermatology Consulting Services — High Point, North Carolina, USA
One of the most prolific clinical investigators in topical formulation and tolerability research, with several hundred studies on how a vehicle changes what an active ingredient does on skin. Author of the reference text on cosmetic dermatology products and procedures, and a past Vice-President of the American Academy of Dermatology. Her work explains why two creams containing the same percentage of tretinoin can behave very differently on the same face.
Disclosure: Expert names and credentials are cited for educational reference. This content is not endorsed by named experts. Content prepared by RXshop editorial team based on published literature and clinical guidelines.
More Skin Care Medications


