Buy Canagliflowin (Canagliflozin) Online - SGLT2 Inhibitor Generic to Lower Blood Sugar & Protect Heart and Kidneys


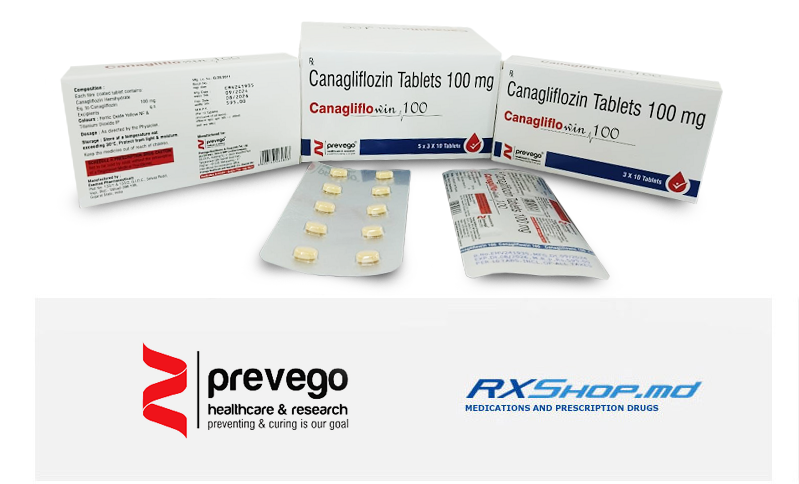
Canagliflowin (Canagliflozin) represents an affordable generic version of brand Invokana, manufactured by Indian pharmaceutical companies as the first widely available SGLT2 inhibitor for type 2 diabetes management. As a selective sodium-glucose cotransporter 2 inhibitor, Canagliflowin works through a unique kidney-based mechanism that excretes excess glucose through urine rather than stimulating insulin or reducing insulin resistance. The 100/300 mg oral tablets deliver consistent blood sugar control with proven cardiovascular and renal protective benefits.
Canagliflozin works by selectively blocking SGLT2 transporters in the proximal kidney tubules, preventing reabsorption of filtered glucose back into the bloodstream. This blockade causes approximately 70-119 grams of glucose to be excreted in urine daily, directly removing blood sugar without depending on insulin pathways. The result: HbA1c drops 0.7-1.1% from baseline, fasting blood glucose decreases 25-40 mg/dL, body weight reduces 2-4 kg through caloric loss in urine, and blood pressure drops 3-5 mmHg through mild diuretic effect.
Canagliflowin benefits from landmark cardiovascular and renal evidence. The CANVAS trial (CANagliflozin cardioVascular Assessment Study) involving 10,142 patients demonstrated 14% reduction in major cardiovascular events including heart attack, stroke, and cardiovascular death. The CREDENCE trial showed 30% reduction in renal events and slowed progression of diabetic kidney disease in patients with diabetic nephropathy. These results established Canagliflowin as first-line therapy for diabetic patients with cardiovascular disease, chronic kidney disease, heart failure with reduced ejection fraction, and diabetic nephropathy.
Canagliflowin offers convenient once-daily dosing taken before the first meal of the day for optimal effect on post-meal glucose absorption. The medication reaches peak blood concentrations within 1-2 hours and shows extended therapeutic action with 11-13 hour half-life. Generic canagliflozin from quality Indian manufacturers provides identical therapeutic effects to original brand Invokana by Janssen/Johnson & Johnson at substantially lower cost. The active ingredient remains chemically identical across both branded and generic versions of this established type 2 diabetes management therapy.
Free prescription
Discrete packaging
Have questions?
Quality Assurance

- Type 2 Diabetes: Most common diabetes form where body resists insulin or makes insufficient amounts gradually;
- Type 2 Diabetes Mellitus: Full medical term for adult-onset diabetes characterized by insulin resistance and hyperglycemia;
- High Blood Sugar: Persistently elevated blood glucose levels above 126 mg/dL fasting causing organ damage;
- Blood Sugar: Glucose circulating in blood that cells use for energy through insulin-regulated uptake;
- Hyperglycemia: Medical term for abnormally elevated blood glucose levels above normal threshold values;
- Insulin Resistance: Body cells respond poorly to insulin requiring higher levels to control blood sugar;
- Diabetic Nephropathy: Progressive kidney damage from diabetes causing protein loss and declining filtration function;
- Diabetic Kidney Disease: Chronic kidney disease specifically caused by diabetes affecting filtration over years;
- Chronic Kidney Disease: Long-term kidney function decline measured by reduced glomerular filtration rate;
- Heart Failure: Condition where heart cannot pump enough blood to meet body needs causing fatigue and edema;
- Heart Failure Reduced Ejection: Heart failure with reduced left ventricular ejection fraction below 40 percent;
- Diabetic Cardiovascular Risk: Elevated heart attack and stroke risk specifically associated with type 2 diabetes;
- Heart Attack Prevention: Reducing risk of coronary artery blockage that permanently damages heart muscle tissue;
- Stroke Prevention: Lowering risk of brain artery blockage causing paralysis speech loss or death;
- Diabetes Monotherapy: Single-drug treatment when type 2 diabetes can be controlled without combination therapy;
- Metformin Combination: Add-on to metformin when blood sugar remains above target on metformin alone;
- Insulin Combination Therapy: Combined with insulin in advanced diabetes when oral therapy alone is insufficient;
- Diabetes Combination Therapy: Used in multi-drug regimens with sulfonylureas DPP-4 inhibitors or GLP-1 agonists;
- Diabetic Obesity: Excess body weight common in type 2 diabetes requiring weight management through medication;
- Diabetic Hypertension: High blood pressure commonly co-existing with type 2 diabetes increasing cardiovascular risk;
- SGLT2 Inhibitor Therapy: SGLT2 drug class treatment offering glycemic cardiovascular and renal benefits in diabetes.
- Lower A1C: HbA1c decreases 0.7-1.1% reflecting better long-term blood sugar control over 3 months;
- Lower Fasting Glucose: Morning blood sugar levels normalize through continuous urinary glucose excretion;
- Lower Post Meal Glucose: Blood sugar spikes after eating flatten through ongoing renal glucose elimination;
- Better Glycemic Control: Overall blood sugar management improves measurably reducing diabetes complication risk;
- Diabetic Weight Loss: Body weight decreases 2-4 kg through caloric loss in urine as excreted glucose;
- Lower Blood Pressure: Systolic blood pressure drops 3-5 mmHg through mild diuretic effect of glucose excretion;
- Less Heart Attack Risk: Cardiovascular event probability drops 14% per CANVAS trial in diabetic patients;
- Less Stroke Risk: Ischemic stroke incidence decreases through improved metabolic and vascular function;
- Less Cardiovascular Death Risk: Fatal cardiac event probability decreases in long-term users with diabetic CV risk;
- Less Heart Failure Hospitalization: Heart failure admission risk reduces 33% in diabetic patients per CANVAS trial;
- Better Kidney Function: Glomerular filtration rate decline slows significantly preserving long-term kidney health;
- Slower Kidney Disease Progression: Diabetic chronic kidney disease advancement slows 30% per landmark CREDENCE trial;
- Less Diabetic Nephropathy: Diabetic kidney damage progression slows preserving filtration function over years;
- Lower Albuminuria: Protein leakage in urine decreases indicating less kidney filtration barrier damage;
- Less Insulin Need: Insulin injection requirement decreases or delays in patients on combination therapy;
- Less Hyperglycemia: Episodes of dangerously high blood sugar reduce significantly with consistent therapy;
- Less Diabetic Complications: Long-term damage to eyes kidneys and nerves decreases through better glucose control;
- Once Daily Convenience: Single tablet taken before first meal of day fits naturally into morning routine;
- Better Quality of Life: Daily wellbeing improves from reduced hyperglycemia symptoms stable energy and weight loss.
Generic Canagliflowin (Canagliflozin 100 mg) Medication guide:
📖 What Canagliflowin Is and How It Works
Canagliflowin is a generic version of canagliflozin, the first sodium-glucose cotransporter 2 (SGLT2) inhibitor approved by the US FDA in March 2013. Originally branded as Invokana by Janssen, canagliflozin represented a novel diabetes therapy class that works through the kidney rather than the pancreas or peripheral tissues. Over the past decade, SGLT2 inhibitors have transformed type 2 diabetes management with proven cardiovascular and renal benefits that redefined the standard of care.
Canagliflowin at a glance
| Class | SGLT2 inhibitor (gliflozin) |
| FDA approval (original brand) | March 2013 as Invokana (Janssen) |
| Available strengths | 100 mg and 300 mg tablets |
| Typical dose | 100-300 mg once daily |
| Half-life | 10.6 hours (100 mg); 13.1 hours (300 mg) |
| HbA1c reduction | 0.7-1.0 percent |
| Weight effect | Modest loss (2-3 kg typical) |
| Blood pressure effect | Modest reduction (3-5 mmHg systolic) |
The mechanism is unusual. Canagliflozin blocks the SGLT2 protein in the proximal renal tubule. Under normal conditions, SGLT2 reabsorbs about 90 percent of glucose filtered into the kidney tubule back into the bloodstream. When blocked, glucose spills into the urine (glucosuria). This lowers blood glucose without pushing insulin release - working entirely through the kidney rather than through pancreatic beta cells.
What canagliflozin does
Increases urinary glucose excretion by 70-100 grams daily. Blood glucose falls. Hypoglycaemia risk is very low when used alone because glucose loss stops when blood levels normalise. Weight decreases modestly from calorie loss in urine. Blood pressure falls modestly from osmotic diuresis effect. Over time, cardiovascular events and kidney disease progression decrease.
Beyond glucose control
The most important clinical developments came from the CANVAS program (Neal et al. NEJM 2017) and the CREDENCE trial (Perkovic et al. NEJM 2019). CANVAS showed 14 percent reduction in major adverse cardiovascular events and heart failure hospitalisations halved. CREDENCE specifically targeted clients with type 2 diabetes and chronic kidney disease, showing 30 percent reduction in kidney disease progression, kidney failure, or death from renal or cardiovascular causes. These findings reshaped diabetes practice - SGLT2 inhibitors including canagliflozin moved from "just another glucose-lowering drug" to first-line addition for clients with cardiovascular or renal disease.
The safety concerns
SGLT2 inhibitors have specific side effects tied to their kidney mechanism. Genital mycotic infections (thrush, balanitis) are common because glucose in urine feeds yeast. Volume depletion can occur with diuretic effect. Urinary tract infections increased modestly. Diabetic ketoacidosis can occur in specific settings including illness, surgery, and low-carbohydrate diets. Canagliflozin specifically had an amputation signal from CANVAS that led to a boxed warning (added 2017, removed 2020 after further data). Bone fractures increased in men in CANVAS - a signal not seen with other SGLT2 inhibitors.
Modern positioning within the SGLT2 class
Empagliflozin (Jardiance) and dapagliflozin (Farxiga) are now more commonly prescribed than canagliflozin. They have similar cardiovascular and renal benefits without the amputation or fracture signals seen with canagliflozin in CANVAS. Canagliflozin remains available and effective but requires attention to these specific safety concerns.
This guide walks through what canagliflozin does, the clear indications where it fits, the once-daily dosing, the cardiovascular and renal outcome evidence, and the safety concerns including genital infections, volume depletion, DKA in specific settings, and the amputation/fracture considerations. Treat this guide as a companion to what your endocrinologist, cardiologist, or nephrologist tells you.
💊 Why Doctors Prescribe Canagliflowin Today
Canagliflozin has three overlapping indications - type 2 diabetes glycaemic control, cardiovascular risk reduction, and kidney disease protection. Modern practice uses these together.
FDA-approved indications
Three approved indications
- Type 2 diabetes glycaemic control - approved 2013; monotherapy or combination
- Cardiovascular risk reduction in type 2 diabetes with established ASCVD - approved 2018 based on CANVAS
- Diabetic kidney disease - approved 2019 based on CREDENCE; reduces progression of nephropathy
Where canagliflozin fits particularly well
Modern diabetes guidelines from ADA, EASD, KDIGO, and cardiology societies have converged on similar recommendations. SGLT2 inhibitors are preferred second-line after metformin (or even alongside metformin as first-line in some scenarios) when the client has any of the following.
Best fit scenarios
- Established atherosclerotic CV disease - MI, stroke, PAD, revascularisation
- Heart failure - especially heart failure with reduced ejection fraction
- High CV risk - multiple risk factors even without established disease
- Chronic kidney disease - especially with albuminuria
- Type 2 diabetes with overweight/obesity where weight loss desired
- Blood pressure needs modest reduction
- Preference for low-hypoglycaemia agent
Where canagliflozin does not fit
Not appropriate for type 1 diabetes (higher DKA risk though sometimes considered off-label). Not effective in advanced kidney disease (eGFR under 30 - glucose lowering effect substantially reduced; though some renal protection maintained). Diabetic ketoacidosis - insulin required, not SGLT2 inhibitor. Volume depleted clients - correct first. Recurrent UTIs or mycotic infections - relative contraindication. Prior amputation or high amputation risk - consider alternative SGLT2 (empagliflozin, dapagliflozin).
Within the SGLT2 class
Modern SGLT2 preference
Empagliflozin and dapagliflozin are now typically preferred over canagliflozin because they have similar cardiovascular and renal outcome data without the amputation signal from CANVAS or the fracture signal. Canagliflozin remains a reasonable choice where these newer agents are unavailable, unaffordable, or when canagliflozin generic offers cost advantage. The CANVAS amputation boxed warning was removed by FDA in 2020 after further data but the historical concern shapes prescribing habits.
The bigger diabetes landscape
Along with GLP-1 agonists (semaglutide, liraglutide, tirzepatide), SGLT2 inhibitors have transformed type 2 diabetes management. Metformin remains standard first-line but SGLT2 inhibitors are now often added early when CV, renal, or heart failure benefit is prioritised. Traditional agents (sulfonylureas, DPP-4 inhibitors, thiazolidinediones) have moved to later positions given the outcome benefits of the modern classes.
Ask your team specifically why canagliflozin was chosen rather than empagliflozin or dapagliflozin (usually cost or availability), what the primary treatment target is (glycaemic, CV, renal), and how it fits with any other diabetes medications you take.
🩸 Canagliflowin for Type 2 Diabetes
Type 2 diabetes glycaemic control was the original FDA-approved indication for canagliflozin. The glycaemic effect is modest but combined with other benefits shapes its role.
What canagliflozin does to diabetes parameters
| HbA1c reduction (100 mg) | 0.7-0.8% |
| HbA1c reduction (300 mg) | 1.0-1.1% |
| Fasting glucose reduction | 25-40 mg/dL |
| Time to meaningful improvement | 1-2 weeks |
| Time to full glycaemic effect | 6-12 weeks |
| Weight loss (typical) | 2-3 kg over 6 months |
Effect is rapid onset - glucose falls within days as urinary glucose loss begins. Full glycaemic effect within 6-12 weeks. Effect diminishes as kidney function declines because filtered glucose load decreases with lower GFR.
Kidney function and glucose lowering
Effect diminishes with lower GFR
Canagliflozin's glucose lowering depends on filtered glucose load reaching the kidney tubule. When GFR is low, less glucose is filtered and canagliflozin's glycaemic effect is smaller. eGFR 60+ - full effect. eGFR 45-60 - reduced but substantial. eGFR 30-45 - modest glycaemic effect but cardiovascular and renal benefits maintained. eGFR under 30 - not effective for glycaemic control.
Which clients respond well
Canagliflozin works particularly well in clients with hyperglycaemia-driven filtered glucose loads - HbA1c above 8 percent tends to show larger absolute reductions. Effect is durable over years unlike sulfonylureas which lose effect. Combination with insulin, metformin, or GLP-1 agonists is straightforward. Weight loss and modest blood pressure reduction are welcome bonuses.
When canagliflozin does not fit type 2 diabetes glycaemic control
Not effective in advanced kidney disease for glycaemic control (though renal protection maintained). Not for type 1 diabetes. Not for diabetic ketoacidosis - requires insulin. Not useful when rapid dramatic glucose reduction needed - insulin or intensification preferred. Not for clients with recurrent genital or urinary infections - these tend to worsen. Not for volume-depleted or dehydrated clients.
Durability advantage
Unlike sulfonylureas which lose glycaemic effect over years, canagliflozin maintains effect as long as kidney function allows. Beta cell status is not the limiting factor - the mechanism does not depend on functional beta cells. This durability parallels metformin and outperforms sulfonylureas or DPP-4 inhibitors.
Combination therapy synergy
Common combinations
- Metformin + canagliflozin - complementary; standard second-line addition
- Metformin + GLP-1 agonist + canagliflozin - triple therapy with excellent glycaemic effect and CV/renal benefits
- Insulin + canagliflozin - canagliflozin reduces insulin requirement and adds CV/renal benefits
- Sulfonylurea + canagliflozin - complementary but need to watch hypoglycaemia risk from sulfonylurea
Set realistic expectations - canagliflozin provides modest glycaemic effect (0.7-1.0 percent HbA1c) alongside cardiovascular protection, renal protection, weight loss, and blood pressure reduction. The combined package is what makes SGLT2 inhibitors preferred second-line in many modern algorithms.
🫀 Canagliflowin for Cardiovascular Protection
Cardiovascular event reduction is one of the most important benefits of canagliflozin. The CANVAS program established this benefit and drove SGLT2 inhibitors into modern cardiovascular practice.
The CANVAS program
CANVAS Program (Neal et al. NEJM 2017)
- 10,142 type 2 diabetes clients across CANVAS and CANVAS-R trials
- 65 percent had established CV disease at baseline
- Randomised to canagliflozin (100 mg or 300 mg) vs placebo
- Median follow-up 3.6 years
- Primary outcome (MACE) reduced 14 percent - cardiovascular death, MI, stroke
- Heart failure hospitalisation halved
- Progression of albuminuria reduced 27 percent
- Amputation risk doubled (2x placebo) - the concerning signal
- Bone fractures increased in men
Cardiovascular event reduction mechanism
The cardiovascular benefits appear to work through multiple mechanisms rather than glucose lowering alone. Modest blood pressure reduction. Weight loss. Preload reduction from diuretic effect. Improved myocardial energetics with ketone body utilisation. Anti-inflammatory effects. Uric acid reduction. Erythropoiesis stimulation. The combined effect appears greater than any single mechanism would predict.
Not just diabetes control
The cardiovascular benefits appear at levels of HbA1c improvement smaller than would explain the CV benefit through glucose alone. Modern understanding is that SGLT2 inhibitors have direct cardiovascular effects independent of glycaemic control. This is why they benefit non-diabetic heart failure clients in trials like DAPA-HF and EMPEROR-Reduced.
Who benefits most
Best CV benefit populations
- Established atherosclerotic CV disease (MI, stroke, PAD, CV revascularisation)
- Heart failure (particularly reduced ejection fraction)
- High CV risk with multiple risk factors
- Kidney disease (compounds CV risk)
- Older adults with multiple comorbidities
Class effects vs canagliflozin-specific
The cardiovascular benefits are a class effect - shared by empagliflozin (EMPA-REG OUTCOME 2015), dapagliflozin (DECLARE-TIMI 58 2019), and to some extent ertugliflozin (VERTIS CV 2020). Among the SGLT2 inhibitors, empagliflozin has arguably the strongest CV data (including CV mortality reduction), dapagliflozin has strong heart failure data (DAPA-HF including non-diabetic clients), and canagliflozin has the CANVAS CV data plus CREDENCE renal data. Choice between agents often depends on cost, availability, and specific comorbidity profile.
Practical positioning
Modern guidelines converge
ADA, EASD, KDIGO, and cardiology society guidelines all now recommend SGLT2 inhibitors including canagliflozin as first-line addition to metformin (or even alongside metformin) in type 2 diabetes clients with established or high CV risk, heart failure, or chronic kidney disease. This represents one of the most substantial guideline convergences in modern medicine.
Non-diabetic use
Empagliflozin and dapagliflozin have expanded FDA indications to include heart failure with reduced ejection fraction regardless of diabetes status. Canagliflozin has this indication indirectly through kidney and diabetes labels but not standalone for heart failure or CKD in non-diabetic clients. For non-diabetic heart failure or CKD, empagliflozin or dapagliflozin preferred.
Canagliflozin provides substantial cardiovascular protection in type 2 diabetes with CV risk. Modern SGLT2 alternatives may be preferred but canagliflozin remains an effective choice where clinically appropriate.
🪩 Canagliflowin for Kidney Protection CREDENCE
Kidney protection is a landmark benefit of canagliflozin established by the CREDENCE trial. This changed how diabetic kidney disease is managed and made SGLT2 inhibitors central to nephrology practice.
The CREDENCE trial
CREDENCE (Perkovic et al. NEJM 2019)
- 4,401 clients with type 2 diabetes and chronic kidney disease
- eGFR 30-90 mL/min with albuminuria (UACR 300-5000 mg/g)
- On ACE inhibitor or ARB (standard care)
- Randomised to canagliflozin 100 mg vs placebo
- Median follow-up 2.6 years - stopped early for efficacy
- Primary composite (kidney failure, doubling creatinine, or renal/CV death) reduced 30 percent
- Kidney failure reduced 32 percent
- Cardiovascular events also reduced
- Amputation risk NOT increased in CREDENCE (unlike CANVAS)
Renal protection mechanism
The renal benefits appear to work through multiple mechanisms. Reduced glomerular hyperfiltration - canagliflozin increases sodium delivery to macula densa which triggers tubuloglomerular feedback and reduces afferent arteriolar dilatation. Blood pressure reduction. Uric acid reduction. Weight loss reducing metabolic burden. Direct anti-inflammatory and anti-fibrotic effects in kidney tissue. The combined effect protects kidney function progression.
The initial eGFR dip is expected
Starting canagliflozin causes an initial 3-5 mL/min eGFR reduction over 2-6 weeks. This is haemodynamic and reversible, not injury. Long-term eGFR slope improves substantially compared with placebo. Do not stop canagliflozin because of this initial dip - it signals the drug is working.
Guidelines and diabetic kidney disease
The KDIGO 2022 guideline for Diabetes Management in Chronic Kidney Disease made SGLT2 inhibitors first-line therapy for diabetic kidney disease alongside ACE inhibitors or ARBs and non-steroidal mineralocorticoid receptor antagonists. This is a major departure from prior practice and reflects the strength of evidence from CREDENCE (and DAPA-CKD for dapagliflozin, EMPA-KIDNEY for empagliflozin).
Who benefits most
Best kidney benefit populations
- Type 2 diabetes with albuminuria (UACR over 300 mg/g)
- Type 2 diabetes with reduced eGFR (30-90 mL/min)
- Established diabetic kidney disease progressing despite ACE inhibitor/ARB
- Combined diabetes and heart failure with kidney concerns
eGFR considerations
Renal function and canagliflozin use
| eGFR 60+ mL/min | Standard 100-300 mg daily |
| eGFR 45-60 mL/min | Continue 100 mg; do not initiate 300 mg |
| eGFR 30-45 mL/min | Continue if tolerated for renal benefit; glycaemic effect reduced |
| eGFR under 30 mL/min | Not for initiation; may continue if already established |
| Dialysis | Not applicable |
Canagliflozin provides substantial kidney protection in diabetic kidney disease. Modern practice makes SGLT2 inhibitors a cornerstone of diabetic CKD care. Consider initiation in any diabetic client with kidney disease unless specific contraindications apply.
💓 Canagliflowin in Heart Failure Context
Heart failure benefits with SGLT2 inhibitors have been a major clinical story. Canagliflozin shares class heart failure benefits though empagliflozin and dapagliflozin have the strongest heart failure trial evidence.
Heart failure evidence for canagliflozin
The CANVAS program showed heart failure hospitalisation halved with canagliflozin in type 2 diabetes clients. The CREDENCE trial also showed reduced heart failure events. These findings support canagliflozin's heart failure benefit within the SGLT2 class.
The dedicated heart failure trials
Class-defining heart failure trials
- DAPA-HF (dapagliflozin, NEJM 2019) - reduced ejection fraction; diabetic AND non-diabetic clients; substantial mortality benefit
- EMPEROR-Reduced (empagliflozin, NEJM 2020) - reduced ejection fraction; similar strong benefit
- DELIVER (dapagliflozin, NEJM 2022) - preserved ejection fraction; benefit confirmed
- EMPEROR-Preserved (empagliflozin, NEJM 2021) - preserved ejection fraction; benefit confirmed
- No dedicated heart failure trial exclusively for canagliflozin
Where canagliflozin fits vs alternatives
SGLT2 choice in heart failure
For clients with type 2 diabetes AND heart failure, any SGLT2 inhibitor provides benefit. However, empagliflozin and dapagliflozin are typically preferred for heart failure specifically because of the dedicated trial evidence. Both are FDA-approved for heart failure regardless of diabetes status. Canagliflozin is not FDA-approved specifically for heart failure - the benefit is inferred from class effect and CANVAS/CREDENCE data.
Guideline-directed medical therapy for HFrEF
Modern guideline-directed medical therapy for heart failure with reduced ejection fraction includes four pillars. ACE inhibitor/ARB/ARNI. Beta-blocker. Mineralocorticoid receptor antagonist. SGLT2 inhibitor. All four should typically be started early. SGLT2 inhibitor addition typically empagliflozin or dapagliflozin per dedicated trial evidence, though canagliflozin provides class benefit if already established or if the client has coexisting kidney disease.
Heart failure with preserved ejection fraction
SGLT2 inhibitors are now the first class shown to reduce events in HFpEF - a population that previously had no proven pharmacotherapy for outcomes. EMPEROR-Preserved (empagliflozin) and DELIVER (dapagliflozin) established this. Canagliflozin does not have a dedicated HFpEF trial but class benefit is inferred.
Practical use in heart failure
Considerations for heart failure clients
- Start early after diagnosis or during hospitalisation
- Effect on symptoms and outcomes visible within weeks
- Monitor volume status - initial diuretic effect
- May need to reduce diuretic doses as canagliflozin adds diuretic effect
- Monitor eGFR - initial dip expected
- Continue through mild acute illness where possible
Class effect vs specific agent
The heart failure benefit is a class effect but the strongest evidence lies with empagliflozin (EMPEROR trials) and dapagliflozin (DAPA-HF, DELIVER). Canagliflozin benefits through class effect and the CANVAS heart failure reduction. If starting SGLT2 for heart failure primarily, empagliflozin or dapagliflozin preferred. If canagliflozin already established, benefit is maintained.
Canagliflozin provides heart failure benefits as part of the SGLT2 class effect. For clients starting therapy with heart failure as primary indication, empagliflozin or dapagliflozin may be preferred. Where canagliflozin is chosen (cost, availability, coexisting kidney disease), heart failure benefits are expected as part of the broader package.
🔬 How Canagliflozin Blocks SGLT2 Mechanism
Understanding how canagliflozin works mechanistically clarifies both its effectiveness and its specific safety considerations.
The molecular target
Canagliflozin blocks the sodium-glucose cotransporter 2 (SGLT2) - a protein in the proximal renal tubule that reabsorbs glucose from the filtrate back into the bloodstream. Under normal conditions, SGLT2 accounts for about 90 percent of renal glucose reabsorption. SGLT1 in the more distal proximal tubule accounts for the remaining 10 percent. Canagliflozin has some SGLT1 activity too, particularly at 300 mg dose.
Sequence of effects after taking canagliflozin
- Canagliflozin binds SGLT2 in proximal tubule
- Glucose reabsorption blocked
- Urinary glucose excretion increases - typically 70-100 g per day
- Blood glucose falls proportionally
- Osmotic diuresis from glucose in urine draws water and sodium
- Modest volume contraction lowers blood pressure
- Glucosuria drives caloric loss - typically 200-400 kcal/day
- Weight decreases modestly over weeks
- Ketone body production shifts modestly
- Tubuloglomerular feedback reduces glomerular hyperfiltration
Key mechanistic feature
Canagliflozin works independently of insulin. Insulin sensitivity is not required. Beta cell function is not required. The mechanism is entirely renal. This distinguishes SGLT2 inhibitors from every other diabetes drug class and explains their unique benefits in heart failure and kidney disease even in non-diabetic clients.
Pharmacokinetics
| Absorption | Bioavailability 65%; unaffected by food |
| Peak plasma concentration | 1-2 hours |
| Half-life (100 mg) | 10.6 hours |
| Half-life (300 mg) | 13.1 hours |
| Protein binding | 99% (mostly albumin) |
| Metabolism | UGT1A9 and UGT2B4 glucuronidation |
| Excretion | Faecal 42%, urinary 33% |
Mechanism-driven benefits
Downstream benefits
- Weight loss - calorie loss in urine (2-3 kg typical)
- Blood pressure reduction - osmotic diuresis (3-5 mmHg systolic)
- Reduced glomerular hyperfiltration - kidney protection
- Uric acid reduction - excretion increased
- Ketone body utilisation - shift toward more efficient cardiac energy substrate
- Erythropoiesis stimulation - modest haemoglobin rise
- Anti-inflammatory effects - reduced kidney and cardiovascular tissue inflammation
Mechanism-driven side effects
Side effect basis
- Genital mycotic infections - glucose in urine feeds yeast (Candida)
- UTI increase (modest) - similar mechanism
- Volume depletion - osmotic diuresis with fluid loss
- Initial eGFR dip - haemodynamic reduction in hyperfiltration
- Diabetic ketoacidosis (rare) - ketone shift can amplify in stress
- Bone density concern - possibly related to phosphate/calcium handling
The elegant renal-focused mechanism defines both canagliflozin's benefits and specific side effects. Understanding this biology explains why the drug behaves as it does clinically and why SGLT2 inhibitors have transformed diabetes, heart failure, and kidney disease care.
⏰ Canagliflowin Dose Schedule and Titration
Canagliflowin dosing is straightforward - once daily with the first meal of the day. Two available strengths cover the range of appropriate uses.
Standard dosing
| Situation | Dose |
|---|---|
| Adult starting (eGFR 60+) | 100 mg once daily before first meal |
| Standard maintenance | 100 mg once daily; may increase to 300 mg |
| Maximum dose | 300 mg once daily |
| eGFR 45-60 mL/min | 100 mg maximum; do not initiate 300 mg |
| eGFR 30-45 mL/min | May continue if already established for renal/CV benefit; do not initiate for glycaemic control |
| eGFR under 30 mL/min | Not recommended for initiation |
| Hepatic impairment (mild-moderate) | No dose adjustment |
| Severe hepatic impairment | Not recommended |
Available strengths
Canagliflowin comes as 100 mg and 300 mg tablets. Original brand Invokana available in same strengths. Fixed-dose combinations with metformin (Invokamet) exist in the original brand though generic versions may vary.
Timing rule
Take before the first meal of the day
This timing optimises glucose excretion after the meal-induced glucose peak. Take approximately 30 minutes before eating. If not taken before the meal, can be taken with the meal. Consistency matters more than exact timing. Take at the same time daily for adherence habit.
Expected effect timeline
- Day 1 - urinary glucose excretion begins
- Week 1-2 - fasting glucose noticeably lower
- Week 4-6 - HbA1c improvement clear
- Week 6-12 - full glycaemic effect
- Months - weight loss develops (2-3 kg over 6 months typical)
- Weeks 2-6 - initial eGFR dip expected then stabilises
- Long term - cardiovascular and renal outcome benefits over years
Titration approach
Start at 100 mg daily. Reassess at 4-6 weeks for tolerability and 8-12 weeks for glycaemic response. If HbA1c not at target and eGFR remains above 60, increase to 300 mg. If already at 300 mg or eGFR under 60, add another agent rather than exceed maximum. Some clients settle at 100 mg with adequate effect; others benefit from 300 mg.
Duration of therapy
Canagliflozin is typically long-term therapy when tolerated. Effectiveness is durable over years. Cardiovascular and renal benefits accrue with continued use. Annual review whether canagliflozin continues to fit - HbA1c, kidney function, cardiovascular status, side effect profile.
Do not stop suddenly without alternative
Glycaemic control worsens within days if canagliflozin discontinued. Cardiovascular and renal protective effects also wane. Plan alternative therapy if stopping. Do not confuse the expected initial eGFR dip with kidney damage - do not stop for this reason.
📅 Starting Canagliflowin - First Weeks
Starting Canagliflowin requires careful baseline assessment, awareness of the expected initial eGFR dip, and vigilance for the specific side effect profile.
Typical initiation experience
Most clients notice glucose falling within days. Urination frequency may increase modestly - the drug puts glucose in urine which draws water. Some clients report increased thirst. Weight begins to fall over weeks. HbA1c improvement clear at 4-6 weeks. Long-term tolerance is excellent in most clients. Initial eGFR dip of 3-5 mL/min is expected and not a sign of harm.
Pre-treatment assessment
Baseline checks before starting
- Diabetes parameters - HbA1c, fasting glucose
- Kidney function - eGFR determines starting dose and appropriateness
- Urine albumin - baseline for kidney protection tracking
- Volume status - correct dehydration first
- Blood pressure - if low, particularly on diuretics, may need diuretic dose reduction
- Foot examination - assess amputation risk
- Genital/urinary infection history - recurrent infections are relative contraindication
- Concurrent medications - insulin or sulfonylurea may need dose reduction; loop diuretics may need reduction
- Discuss DKA awareness - particularly for high-risk clients
Setting expectations
Practical points for new starters
- Increased urination - especially first weeks; usually settles
- Increased thirst - drink adequate fluid
- Modest weight loss welcome for most
- Genital hygiene - reduce mycotic infection risk
- Sick day awareness - may need to hold during severe illness
- Foot care - report any wounds or infections promptly
- Initial eGFR dip is expected - not a sign of harm
Follow-up schedule for initiation
| Timing | Focus |
|---|---|
| Week 2-4 | Tolerability review; volume status; check for infection concerns |
| Week 4-6 | eGFR recheck (initial dip resolving); HbA1c early trend |
| Month 3 | HbA1c response assessment; weight; blood pressure |
| Every 6 months | HbA1c; eGFR; urine albumin; overall assessment |
| Annual | Comprehensive review; foot examination; kidney/CV assessment |
Warning signs during initiation
Contact team promptly if these occur
- Symptoms of dehydration (dizziness, orthostatic symptoms)
- Genital burning, itching, discharge
- Urinary tract infection symptoms
- Fournier gangrene warning signs (rare) - severe genital or perineal pain, swelling, fever
- Any foot wound, sore, or infection
- Symptoms of DKA - nausea, vomiting, abdominal pain, unusual fatigue
- Substantial weight loss beyond expected
- Severe hypoglycaemia if on other diabetes drugs
The first weeks are learning - the client and team calibrate response. Initial eGFR dip should not prompt discontinuation. Prompt attention to concerning signs (particularly infection, foot problems, DKA symptoms) allows appropriate response.
📏 Canagliflowin Dose Adjustments Response
Canagliflowin dose adjustment considers glycaemic response, tolerability, kidney function changes, and specific safety concerns.
What affects individual response
Baseline HbA1c - higher baseline shows larger absolute reduction. Kidney function - lower eGFR reduces glycaemic effect. Concurrent diabetes medications. Volume status. Concurrent CYP modulators (though canagliflozin is mostly UGT-metabolised). Age and frailty. Comorbidities driving CV/renal considerations.
Common adjustments
| Situation | Action |
|---|---|
| HbA1c not at target on 100 mg (eGFR 60+) | Increase to 300 mg after 4-6 weeks; recheck at 12 weeks |
| HbA1c not at target on 300 mg | Add GLP-1 agonist, metformin (if not already), or insulin |
| eGFR falls to 45-60 mL/min | Reduce to 100 mg if on 300 mg |
| eGFR falls to 30-45 mL/min | Continue 100 mg for renal/CV benefit; glycaemic effect reduced |
| eGFR under 30 mL/min | Consider stopping; individual risk-benefit assessment |
| Recurrent genital infections | Reduce dose or switch to alternative SGLT2 |
| Volume depletion symptoms | Reduce loop diuretic; ensure adequate hydration |
| Substantial weight loss beyond target | Reduce dose; assess intake |
| Amputation event | Stop canagliflozin; alternative SGLT2 (empagliflozin/dapagliflozin) if class continued |
Managing the initial eGFR dip
Expected pattern
eGFR typically falls 3-5 mL/min in first 2-6 weeks. Then stabilises. Long-term eGFR slope is improved compared with placebo. Do NOT discontinue for this expected dip. If eGFR falls substantially more (over 10 mL/min) or fails to stabilise, investigate other causes and reassess.
When canagliflozin is not enough
Add-on strategy
- Add metformin if not already (standard first-line)
- Add GLP-1 agonist for further HbA1c and weight loss
- Add basal insulin for substantial HbA1c gap
- Add DPP-4 inhibitor for modest addition (though overlap somewhat with GLP-1 mechanism)
- Sulfonylurea last resort - hypoglycaemia and weight gain contrasts with canagliflozin
Non-response investigation
- Check adherence honestly
- Verify appropriate meal timing with dose
- Consider kidney function - if declined, glycaemic effect reduces
- Assess for concurrent hyperglycaemia drivers (steroids, other medications, illness)
- Endocrinology or diabetes team consultation for refractory cases
Adjustment is guided by HbA1c response, kidney function trajectory, and tolerability. Safety concerns may drive dose reduction or switching to alternative SGLT2 (empagliflozin, dapagliflozin) or class.
💊 How to Take Canagliflowin Tablets
Practical routines around Canagliflowin tablets are simple - once daily before the first meal. The main practical disciplines are hydration awareness and prompt attention to infection or foot concerns.
Daily routine
Take once daily before the first meal of the day. Approximately 30 minutes before eating optimal. Can be taken with the meal if forgotten before. Swallow whole with water. Same time daily supports adherence habit. Refill 2 weeks before running out.
Anchor to a daily habit
Take with the morning routine - before breakfast is ideal. If breakfast pattern varies, take before the first food of the day whenever that is. Weekly pillbox helpful for polypharmacy. Phone alarm labeled "canagliflozin before breakfast" reduces forgetting.
Hydration matters
Drink adequate fluid
Canagliflozin causes osmotic diuresis - the glucose in urine draws water. This means you lose more fluid than usual through urination. Drink adequate water - typically 2-2.5 L daily unless restricted. Watch for dehydration signs particularly in hot weather, illness, or when combined with diuretics. Reduce diuretic dose if volume depletion develops.
Home monitoring priorities
What to track at home
- Fasting glucose regularly
- Weight monthly - modest loss expected
- Blood pressure - modest reduction expected
- Volume status - dizziness on standing suggests dehydration
- Urinary frequency
- Genital symptoms - itching, discharge, discomfort
- Foot condition - any wounds, sores, or infections
Key safety rules
Alert your team about
- Symptoms of dehydration or dizziness
- Any genital burning, itching, or discharge
- Urinary tract infection symptoms
- Any foot wound, sore, ulcer, or discolouration
- Nausea, vomiting, abdominal pain - can signal DKA
- Sudden unusual fatigue with normal glucose - DKA signal
- Fever with genital or perineal pain (rare Fournier gangrene concern)
- Substantial rash
- Planned surgery - may need to hold days before
Foot care awareness
Because of the amputation history
The CANVAS amputation signal (though the FDA boxed warning was removed in 2020) makes attentive foot care important on canagliflozin. Inspect feet daily. Report any wounds, ulcers, or skin colour changes promptly. Well-fitting footwear. Regular podiatry review particularly if peripheral neuropathy or vascular disease present.
Storage
Room temperature under 25 C. Original packaging. Protect from moisture. Not in bathroom or hot car. Out of reach of children. Do not use past expiry. Return unused tablets to pharmacy for disposal.
Once-daily before-breakfast dosing is simple. The core practical rules are adequate hydration, attention to genital and urinary hygiene, foot care awareness, and prompt reporting of concerning symptoms.
🍴 Food and Canagliflowin Absorption
Canagliflozin absorption is not meaningfully affected by food. But taking before the first meal optimises the drug's effect on postprandial glucose.
Food and canagliflozin absorption
Bioavailability approximately 65 percent. Food does not meaningfully reduce absorption. Take before the first meal or with the meal - both work practically. Same time daily supports adherence habit.
Why before the meal is preferred
Taking canagliflozin before the first meal allows the drug to be blocking SGLT2 when the meal-induced glucose surge arrives. This optimises postprandial glucose excretion in the urine. If forgotten, taking with the meal still works well.
Diet for type 2 diabetes
The Mediterranean or DASH eating pattern has best evidence for diabetes and cardiovascular outcomes. Emphasise vegetables, whole grains, legumes, fatty fish, nuts, olive oil. Limit refined carbohydrates, added sugars, processed meats.
Diet considerations for SGLT2 clients
- Adequate hydration - important given osmotic diuresis; 2-2.5 L water daily unless restricted
- Consistent carbohydrate intake - supports steady glycaemic control
- Avoid very low carbohydrate diets - raise DKA risk on SGLT2 inhibitors
- Fatty fish weekly - cardiovascular support
- Vegetables at each meal
- Portion control - supports weight management
The very low-carb / ketogenic diet warning
DKA risk elevated with very low carb intake
Ketogenic or very low carbohydrate diets (under 50g/day) raise the risk of diabetic ketoacidosis on canagliflozin even with normal blood glucose (euglycaemic DKA). The SGLT2 inhibitor mechanism shifts metabolism toward ketone body production. When combined with severe carbohydrate restriction, ketones can rise dangerously. Discuss with your team before starting a low-carb dietary pattern on canagliflozin. Ketone monitoring may be appropriate.
Hydration awareness
Canagliflozin puts glucose in urine which draws water through osmotic effect. You will urinate more than usual and lose more fluid than usual. Drink adequate water throughout the day. This becomes particularly important in hot weather, during exercise, when ill, or when taking diuretics. Watch for dehydration signs - dizziness on standing, dry mouth, dark urine, reduced urine output.
Weight management
Canagliflozin causes 2-3 kg weight loss typically over 6 months. This is welcome for most clients who are overweight. Continue attention to diet and exercise - the drug contribution is modest and best combined with lifestyle measures.
Diet supports diabetes and cardiovascular protection. Adequate hydration is essential on canagliflozin. Avoid very low carbohydrate patterns due to DKA risk. Mediterranean-style eating pattern remains excellent foundation.
🍷 Alcohol Rules During Canagliflowin Therapy
Alcohol has specific considerations on canagliflozin therapy - dehydration risk, DKA risk in specific settings, and general diabetes management concerns.
Why alcohol matters with canagliflozin
Alcohol causes diuresis on its own. Combined with canagliflozin's osmotic diuresis, dehydration risk increases. Heavy alcohol use suppresses hepatic gluconeogenesis and can precipitate hypoglycaemia if combined with insulin or sulfonylureas. Alcohol excess can precipitate euglycaemic DKA on SGLT2 inhibitors. Weight management concerns compound with alcohol calories.
Alcohol concerns on canagliflozin
- Additive dehydration - alcohol plus SGLT2 diuretic effect
- DKA risk in binge drinking or heavy use
- Hypoglycaemia if on insulin or sulfonylurea concurrently
- Liver injury with heavy use
- Blood pressure elevation
- Sleep disruption affecting glucose control
Guidelines by scenario
| Scenario | Alcohol guidance |
|---|---|
| Type 2 diabetes stable on canagliflozin | Moderate at most - 1 drink daily women, 2 daily men max |
| Any liver disease | Avoid or minimal (no more than 1 drink weekly) |
| Heart failure history | Strict limitation |
| Ketogenic or low-carb diet | Strict limitation - DKA risk elevated |
| Concurrent insulin or sulfonylurea | Extra hypoglycaemia caution - eat with alcohol |
| Volume depletion tendency | Avoid alcohol excess |
Standard drink reference
Beer 12 oz / 350 ml at 5 percent alcohol. Wine 5 oz / 150 ml at 12 percent alcohol. Spirits 1.5 oz / 45 ml at 40 percent alcohol. Home pours often exceed standard measures.
Sensible approach if you drink
Practical guidance
- Not more than 2 drinks in one occasion
- Hydration - water alongside alcohol; extra water because of diuretic effect
- Eat with alcohol
- Not before driving
- Consider holding canagliflozin during binge drinking or heavy use
- Be honest with your team about intake
Avoid alcohol entirely if:
- Any hepatitis or active liver disease
- Any heart failure history
- Diagnosed alcohol use disorder
- Prior DKA on canagliflozin
- Volume depletion tendency
- Directed by your team
Alcohol on canagliflozin requires moderation given the additive dehydration and DKA risk. Discuss honestly with your team - realistic guidance beats prohibitions clients ignore.
🚨 Canagliflowin Side Effects Complete Overview and Warnings
Canagliflozin has a distinctive side effect profile tied to its mechanism - glucose in urine drives infection risk, osmotic diuresis drives volume effects, and metabolic shifts can rarely precipitate DKA.
Common effects
Common (over 5 percent)
- Genital mycotic infections - female genital candidiasis 3-11%; male balanitis 3-9%
- Urinary tract infections - modest increase (5-7%)
- Increased urination frequency
- Increased thirst
- Volume-related symptoms - orthostatic dizziness, particularly in elderly or on diuretics
- Elevated LDL cholesterol - modest rise
Uncommon but notable
- Amputation risk - CANVAS 2x placebo (boxed warning added 2017, removed 2020)
- Bone fractures - increased in CANVAS particularly men
- Volume depletion - dehydration, hypotension
- Acute kidney injury - typically in volume depletion contexts
- Rash - hypersensitivity
- Nausea
Rare but serious
Rare serious effects
- Diabetic ketoacidosis - often euglycaemic (normal glucose); triggered by illness, surgery, low-carb diet
- Fournier gangrene - very rare necrotising infection of perineum; medical emergency
- Pyelonephritis or urosepsis - from UTI escalation
- Severe hypersensitivity - angioedema, Stevens-Johnson syndrome
When to seek help urgently
Emergency signals
- Symptoms of DKA - nausea, vomiting, abdominal pain, unusual fatigue (even if glucose normal)
- Severe genital or perineal pain with fever - Fournier concern
- High fever with UTI symptoms - pyelonephritis
- Fainting or severe dizziness - volume depletion
- Substantial rash particularly with mucosal involvement
- Foot wound, ulcer, or infection
- Suspected fracture
- Facial or throat swelling
Managing common effects
| Effect | Action |
|---|---|
| Genital mycotic infection (mild) | Antifungal (topical or oral); improved hygiene; continue canagliflozin |
| Genital mycotic infection (recurrent) | Longer antifungal course; consider switching to alternative agent |
| UTI (uncomplicated) | Antibiotic; hydration; continue canagliflozin |
| UTI (recurrent or pyelonephritis) | Antibiotic; investigate; consider stopping canagliflozin |
| Volume depletion | Hydration; reduce diuretic; may reduce canagliflozin dose |
| Orthostatic dizziness | Adequate hydration; slow position changes; adjust concurrent medications |
| Rash mild | Assess; may continue with monitoring |
Side effect profile is generally tolerable but specific concerns require awareness - infections, volume status, DKA in specific settings, and the historical amputation/fracture signals. The following sections detail the most important individual concerns.
🧫 Genital and Urinary Tract Infections
Genital and urinary tract infections are the most common canagliflozin side effects - direct consequences of glucose spilling into urine.
Why infections occur
Glucose in urine feeds bacteria and yeast. The genitourinary tract normally has minimal glucose - it becomes a favourable environment for infection on SGLT2 inhibitors. Women are affected more often than men because of anatomical factors and higher baseline colonisation. Effects are usually mild but can recur or occasionally escalate to serious infection.
Genital mycotic infections
Genital candidiasis
- Women - vulvovaginal candidiasis; 3-11 percent of clients
- Men - balanitis or balanoposthitis; 3-9 percent of clients; especially uncircumcised
- Symptoms - itching, burning, discharge, redness, discomfort
- Timing - can occur at any time; often first months
- Usually mild and responsive to standard antifungal treatment
Treatment approach
Topical antifungal (clotrimazole cream) or single-dose oral fluconazole 150 mg for uncomplicated genital candidiasis. Recurrent episodes may need longer course or switching to alternative SGLT2 or class. Do not stop canagliflozin for isolated mild infection - treat and continue.
Urinary tract infections
UTI characteristics
- Modest increase - 5-7 percent vs 4-5 percent placebo
- Usually mild lower tract cystitis
- Symptoms - dysuria, urgency, frequency, suprapubic discomfort
- Standard antibiotic treatment
- Rare escalation to pyelonephritis or urosepsis
Fournier gangrene - the rare but serious concern
Very rare necrotising fasciitis of perineum
Fournier gangrene is a rare but life-threatening necrotising infection of the perineum, genitalia, or perianal area. SGLT2 inhibitors show a small increase in Fournier gangrene reports. Warning signs include severe genital or perineal pain, redness, swelling, fever, and progressive symptoms.
Immediate medical attention required - this is a surgical emergency.
Prevention strategies
Reduce infection risk
- Good genital hygiene - regular gentle cleaning
- Adequate hydration - flushes urinary tract
- Wipe front to back (women)
- Post-coital urination
- Loose cotton underwear
- Prompt treatment of any infection
- Circumcision reduces balanitis risk in men (a factor in decisions but not a reason to circumcise)
When to switch or stop
Consider switching to alternative SGLT2 (empagliflozin, dapagliflozin have similar infection rates but individual clients sometimes tolerate one better) or discontinuing SGLT2 class entirely if: recurrent genital infections despite treatment; recurrent UTIs particularly with escalation; Fournier gangrene occurrence; substantial impact on quality of life; client preference.
Genital and urinary infections are the most common canagliflozin side effects but usually manageable. Awareness, hygiene, prompt treatment, and switching agents in refractory cases handle most concerns.
💧 Volume Depletion and Blood Pressure Effects
Volume depletion and blood pressure changes are direct consequences of the osmotic diuresis effect of canagliflozin. Most clients tolerate this well but specific populations need particular attention.
The diuretic effect
Glucose in urine draws water and sodium through osmotic effect. This produces modest but real diuresis - roughly equivalent to a mild loop or thiazide diuretic. Blood pressure falls 3-5 mmHg systolic and 1-3 mmHg diastolic typically. Weight includes early loss of fluid before adipose loss develops.
Who is at risk for volume depletion
Higher risk populations
- Older adults - baseline reduced fluid intake and thirst response
- Clients on loop or thiazide diuretics - additive effect
- Clients on ACE inhibitors or ARBs - complementary blood pressure effect
- Baseline systolic BP under 110 - less reserve
- Reduced eGFR - impaired concentration ability
- Recent surgery or illness - reduced intake
- Hot weather or exercise - additive fluid loss
Symptoms of volume depletion
Signs to watch for
- Dizziness on standing (orthostatic hypotension)
- Lightheadedness
- Fatigue
- Reduced urine output
- Dark urine
- Dry mouth
- Muscle cramps
Management approach
Managing volume-related issues
- Ensure adequate fluid intake - typically 2-2.5 L water daily
- Reduce loop or thiazide diuretic dose if volume depleted
- Slow position changes
- Assess concurrent medications (ACE inhibitors, ARBs, beta-blockers)
- Consider dose reduction of canagliflozin
- Hold canagliflozin during acute illness with dehydration
- Reassess and restart when volume repleted
Blood pressure effects
The BP effect is typically beneficial
The modest blood pressure reduction from canagliflozin (3-5 mmHg systolic) is often welcome in hypertensive diabetic clients. May allow reduction of other antihypertensive medications. But hypotension requires attention in normotensive or already well-controlled clients. Home BP monitoring during initiation useful.
Acute kidney injury risk
Volume depletion is the primary cause of acute kidney injury on canagliflozin. Not a direct drug toxicity but a consequence of reduced perfusion. Preventable with adequate hydration and diuretic dose management. Usually reversible with fluid repletion and drug hold.
Hold canagliflozin during
- Acute severe illness with vomiting or diarrhoea
- Substantial reduction in oral intake
- Major surgery (hold 3+ days prior per FDA guidance)
- Prolonged fasting
- Signs of volume depletion or acute kidney injury
Volume and blood pressure effects are usually beneficial but require attention in specific populations. Adequate hydration, diuretic adjustment, and holding during acute illness prevent most problems.
🔴 Diabetic Ketoacidosis Risk Canagliflowin
Diabetic ketoacidosis (DKA) on SGLT2 inhibitors is uncommon but potentially serious. Understanding when it occurs and how to recognise it is essential for all clients on canagliflozin.
Why SGLT2 inhibitors can precipitate DKA
SGLT2 inhibitors shift metabolism modestly toward ketone body production. Insulin levels drop as glucose falls (particularly if insulin dose reduced). Glucagon rises. Ketone body production increases. In specific settings (illness, surgery, low carbohydrate intake, alcohol excess), this shift can amplify to true ketoacidosis.
The euglycaemic DKA trap
Classic diabetic ketoacidosis has very high glucose (over 250 mg/dL). SGLT2-associated DKA can occur with normal or only modestly elevated glucose (euglycaemic DKA) because canagliflozin removes glucose in urine. This makes diagnosis challenging - clients and doctors may not consider DKA when glucose is normal. Ketone testing rather than glucose testing is essential when DKA is suspected.
Who is at higher risk
Elevated DKA risk situations
- Acute illness - infection, gastroenteritis, surgery
- Prolonged fasting or substantially reduced carbohydrate intake
- Ketogenic or very low-carb diet
- Dehydration
- Insulin dose reduction or omission
- Excess alcohol
- Recent surgery
- Pregnancy (though SGLT2 not used in pregnancy)
- Type 1 diabetes (off-label; higher DKA risk)
Recognising DKA
Symptoms to recognise
- Nausea and vomiting
- Abdominal pain
- Unusual fatigue or weakness
- Fast or deep breathing (Kussmaul respiration)
- Fruity breath odour
- Confusion or drowsiness
- Muscle stiffness or cramps
- Symptoms may occur with normal blood glucose
Prevention strategies
Reduce DKA risk
- Hold canagliflozin during acute illness with vomiting, dehydration, or reduced intake
- Hold canagliflozin 3+ days before major surgery (per FDA guidance)
- Avoid ketogenic or very low-carb diets on canagliflozin
- Do not omit insulin when on canagliflozin plus insulin
- Limit alcohol
- Ensure adequate carbohydrate intake with meals
- Report early DKA symptoms - do not wait
If DKA is suspected
Emergency response
- Seek emergency medical care
- Check blood ketones if available (over 1.5 mmol/L significant; over 3 mmol/L urgent)
- Do not rely on blood glucose alone - can be normal
- Hospital treatment - fluids, insulin, electrolyte correction
- Stop canagliflozin
- Do not restart until fully recovered and cause understood
Consider ketone monitoring
Some clients on canagliflozin benefit from access to home blood ketone testing strips. Not routinely necessary but useful when illness or unusual symptoms occur. Discuss with your team whether this fits your situation.
DKA on canagliflozin is uncommon but requires awareness. The euglycaemic presentation makes it easy to miss. Prevention through appropriate holding during illness/surgery/low-carb periods is the main safeguard. Early symptom recognition allows prompt treatment.
🦶 Amputation Signal and Risk Assessment
The amputation signal from CANVAS was one of the most controversial safety findings in modern diabetes therapy. Understanding the current state clarifies use.
The CANVAS finding
In the CANVAS program, canagliflozin was associated with approximately doubled amputation risk compared with placebo. Absolute rates were low but statistically significant. Most amputations were minor (toe, forefoot) rather than major. Prior amputation or peripheral vascular disease increased risk. This finding shocked the diabetes community and led to a boxed warning in 2017.
Subsequent evidence
Post-CANVAS data
- CREDENCE trial (2019) - no significant amputation signal in this dedicated kidney trial
- Observational post-marketing data - amputation risk less pronounced than CANVAS suggested
- Class effect debate - empagliflozin and dapagliflozin have not shown similar amputation signals in their trials
- FDA removed boxed warning in August 2020 after reviewing accumulated data
- Warning about amputation risk remains in labeling but not as boxed warning
Modern understanding
The current state
The amputation signal was real in CANVAS but appears smaller than originally reported when broader data are considered. It may be specific to canagliflozin or possibly not a true class effect. Most clients face very low absolute risk. Clients with baseline high amputation risk (prior amputation, PAD, active foot problems) warrant particular caution or alternative SGLT2 choice.
Risk factors for amputation
Higher amputation risk if:
- Prior amputation
- Peripheral arterial disease
- Diabetic peripheral neuropathy
- Prior diabetic foot ulcer
- Foot deformities
- Poor glycaemic control long-term
- Smoking
- Older age
Prevention strategies
Foot care on canagliflozin
- Daily foot inspection - look for wounds, sores, discoloration, swelling
- Well-fitting footwear - avoid pressure areas
- Podiatry review annually or more if high risk
- Nail care - straight across; podiatry for problems
- Prompt reporting of any foot problem
- Adequate hydration - support tissue perfusion
- Smoking cessation
- Optimise cardiovascular risk factors
Prescribing considerations
When to prefer alternative SGLT2
- Prior amputation - use empagliflozin or dapagliflozin
- Active foot ulcer - stop canagliflozin; alternative SGLT2 after healing
- Advanced peripheral arterial disease - alternative preferred
- High-risk foot problems - alternative preferred
If foot problem develops
Prompt action for any foot issue
- Report to team immediately
- Stop canagliflozin pending assessment
- Podiatry or vascular assessment
- Wound care
- Consider alternative SGLT2 (empagliflozin, dapagliflozin) after resolution
- Address underlying risk factors
The amputation signal shaped canagliflozin use and remains a consideration despite the boxed warning removal. Attentive foot care, appropriate risk-based prescribing, and prompt action on any foot problem manage this concern.
🦴 Bone Fracture Consideration
Bone fracture risk with canagliflozin is a specific signal identified in CANVAS. Understanding it shapes prescribing in populations at baseline fracture risk.
The CANVAS bone finding
In CANVAS, canagliflozin was associated with increased bone fractures particularly in men. Effect noted in first 6 months. This is unusual - most bone concerns affect postmenopausal women (as with thiazolidinediones). CREDENCE did not confirm this signal. Other SGLT2 inhibitors (empagliflozin, dapagliflozin) have not shown similar fracture signals in their trials.
The fracture signal characteristics
CANVAS showed early fractures (within 6 months) in men more than women - opposite the usual pattern. Sites were varied. Mechanism unclear - possibly related to volume depletion causing falls, or to modest changes in bone mineral metabolism. Not confirmed in subsequent trials.
Possible mechanisms
Proposed mechanisms
- Volume depletion causing falls - orthostatic hypotension especially early
- Modest calcium and phosphate handling changes in kidney
- Modest bone turnover marker changes
- Rapid weight loss - modest bone effect
- Mechanism not definitively established
Prevention strategies
Bone health support
- Fall prevention - adequate hydration; slow position changes; assess home safety
- Weight-bearing exercise - regular activity supports bone
- Calcium and vitamin D - adequate intake
- Address other risk factors - smoking cessation, alcohol moderation
- DEXA scan if baseline high fracture risk
- Bisphosphonate if osteoporosis
Risk-benefit consideration
For clients at baseline high fracture risk (postmenopausal osteoporosis, prior fractures, glucocorticoid use, older frail men), the fracture signal may argue for alternative SGLT2 (empagliflozin, dapagliflozin) without this signal. For lower-risk clients, canagliflozin remains acceptable with attention to fall prevention and bone health.
If fracture occurs
Response to fracture
- Standard fracture treatment
- Consider whether canagliflozin contributed (fall from volume depletion, minor trauma)
- Bone health assessment - DEXA, calcium, vitamin D
- Consider switching to empagliflozin or dapagliflozin
- Address fall risk factors
- Bisphosphonate or other osteoporosis treatment if indicated
Bone fracture signal is a specific canagliflozin concern from CANVAS. Not confirmed in subsequent trials but the early signal in men shapes prescribing. Attentive fall prevention, bone health support, and consideration of alternative SGLT2 in high-risk clients handle this concern.
💉 Canagliflowin Drug Interactions Complete Overview and Warnings
Canagliflozin has relatively few drug interactions compared to many diabetes agents. Metabolism is primarily through UGT enzymes rather than CYP450, so classical CYP interactions are limited.
Canagliflozin metabolism
Metabolised primarily by UGT1A9 and UGT2B4 (uridine diphosphate glucuronosyltransferase enzymes). Minor CYP contributions. Metabolites are inactive. Excretion is mostly faecal (42 percent) and urinary (33 percent). Renal function affects both mechanism and clearance.
UGT enzyme modulators
Interactions of clinical significance
- Rifampicin - potent UGT inducer; reduces canagliflozin levels by approximately 51 percent; may require dose increase or alternative therapy
- Phenytoin, phenobarbital, carbamazepine - UGT inducers; similar effect to rifampicin
- St John's wort - herbal inducer; avoid or monitor
Managing UGT inducer combinations
If rifampicin or similar strong UGT inducer required, consider increasing canagliflozin dose (100 mg to 300 mg if tolerated) or using alternative diabetes therapy during the induction period. Monitor glucose closely. Effect resolves over 2-3 weeks after inducer stopped.
Digoxin
Canagliflozin 300 mg (but not 100 mg) modestly increases digoxin AUC by 20 percent. Consider digoxin level monitoring if concurrent 300 mg canagliflozin. Usually not clinically significant.
Diuretic interactions
Pharmacodynamic effects
- Loop diuretics (furosemide, bumetanide) - additive volume depletion; may need loop dose reduction
- Thiazide diuretics - additive volume depletion; may need reduction
- Mineralocorticoid receptor antagonists (spironolactone, eplerenone) - generally safe combination
- Monitor volume status particularly in older adults or heart failure clients
Blood pressure medications
Additive BP effect
Canagliflozin modestly lowers blood pressure. Combined with ACE inhibitors, ARBs, or calcium channel blockers - the effect is additive. Usually welcome in hypertensive diabetic clients. Monitor for hypotension, particularly at initiation and dose changes. May allow reduction of other antihypertensive medications.
Diabetes medication combinations
Common combinations
- Metformin - excellent combination; no PK interaction
- GLP-1 agonists - excellent combination; complementary mechanisms and additional CV/renal benefits
- DPP-4 inhibitors - safe; modest overlap
- Sulfonylureas - hypoglycaemia risk; consider SU dose reduction
- Insulin - hypoglycaemia risk; consider insulin dose reduction; monitor DKA risk
- Pioglitazone - safe combination; complementary mechanisms
Common medications - usually safe
Safe combinations
Statins (all safe), warfarin (no meaningful interaction), most antibiotics (except UGT inducers), most antifungals, most SSRIs, most cardiac medications, most respiratory medications. Canagliflozin has a favourable drug interaction profile.
Canagliflozin drug interactions are limited compared to many drugs. UGT inducers (rifampicin, some anticonvulsants) reduce effect substantially. Pharmacodynamic overlaps with diuretics, insulin, and sulfonylureas require monitoring. Most common medications are safe.
💊 Insulin Sulfonylurea Diuretics Interactions
Specific attention to insulin, sulfonylurea, and diuretic interactions ensures safe use of canagliflozin in common combinations.
Insulin combination
Canagliflozin plus insulin is a common and effective combination. Canagliflozin adds CV and renal benefits that insulin does not provide, and enables lower insulin doses through improved glycaemic control. But two concerns arise.
Concerns with insulin combination
- Hypoglycaemia risk from insulin - may need insulin dose reduction of 10-20 percent when adding canagliflozin
- DKA risk elevated - do not reduce insulin dose excessively; do not omit insulin doses
- Monitor glucose more frequently at initiation
The DKA insulin balance
Reducing insulin too aggressively when adding canagliflozin can precipitate DKA. The rule - reduce insulin doses modestly, not aggressively. Continue basal insulin at reduced but not absent doses. Do not skip insulin doses. Monitor glucose and be alert for DKA symptoms.
Sulfonylurea combination
Sulfonylurea plus canagliflozin
- Hypoglycaemia risk from sulfonylurea component
- Consider sulfonylurea dose reduction when adding canagliflozin (approximately 25-50 percent)
- Modern practice often prefers to discontinue sulfonylurea when starting SGLT2 inhibitor - reducing hypoglycaemia and simplifying regimen
- If both continued, monitor glucose and hypoglycaemia symptoms
Loop diuretic considerations
Diuretic combinations
- Baseline heart failure on loop diuretic - additive volume effect; monitor volume status; may need loop reduction 10-20 percent
- Volume depletion with canagliflozin - reduce or hold loop diuretic first
- Hyperkalaemia on ACE inhibitor + spironolactone - canagliflozin modestly reduces K+; helpful
- Blood pressure management - canagliflozin lowers BP; may reduce need for other antihypertensives
Digoxin
Canagliflozin 300 mg increases digoxin AUC 20 percent. Consider digoxin level check if concurrent. Usually not clinically significant. Watch for signs of digoxin toxicity - nausea, arrhythmia, visual changes.
Practical adjustment approach
When starting canagliflozin on existing therapy
- On insulin - reduce basal insulin 10-20 percent; monitor glucose
- On sulfonylurea - consider stopping SU or reducing dose 25-50 percent
- On loop diuretic - may reduce 10-20 percent; monitor volume
- On ACE inhibitor/ARB - continue standard; monitor BP
- On digoxin (rare) - level check if 300 mg canagliflozin
Adding new medications - checklist
- Tell prescriber you are on canagliflozin
- Pharmacist check for UGT inducer or fluid interaction
- If starting rifampicin - dose adjustment or alternative
- If new diuretic - monitor volume; may need canagliflozin adjustment
- If starting insulin - close glucose monitoring
- If starting sulfonylurea - hypoglycaemia awareness
Insulin, sulfonylurea, and diuretic combinations require attention but are manageable. Modest dose reductions of insulin/SU and awareness of volume status handle most concerns. Modern practice often discontinues sulfonylureas when starting SGLT2 inhibitors for simplification.
🩸 Rifampicin and CYP Modulators
Rifampicin and other CYP/UGT enzyme modulators can substantially reduce canagliflozin effect. Awareness allows appropriate management.
Rifampicin interaction
Substantial reduction in canagliflozin effect
Rifampicin is a potent inducer of UGT enzymes (and CYP enzymes). Reduces canagliflozin AUC by approximately 51 percent. Glucose control worsens during rifampicin course. Typically used for tuberculosis treatment lasting months. Requires substantive management.
Managing rifampicin combination
- Short course rifampicin (weeks) - intensify other diabetes therapy temporarily
- Long course rifampicin (TB treatment months) - consider alternative diabetes regimen
- Dose increase - increase canagliflozin from 100 mg to 300 mg if not already at maximum; limited additional benefit
- Close glucose monitoring during rifampicin
- After rifampicin stops - canagliflozin levels rise back over 2-3 weeks; adjust accordingly
Anticonvulsant inducers
Phenytoin, phenobarbital, carbamazepine
- Similar UGT and CYP induction effect
- May reduce canagliflozin effect substantially
- Long-term concurrent use - consider dose increase or alternative diabetes therapy
- Newer anticonvulsants (levetiracetam, lamotrigine, lacosamide) generally do not induce UGT
St John's wort
Herbal preparation with UGT and CYP induction effects. Reduces canagliflozin levels. Widely available over-the-counter. Ask clients about herbal supplements. Avoid or discontinue St John's wort during canagliflozin therapy.
Other notable interactions
Less common but worth knowing
- Digoxin - 300 mg canagliflozin raises digoxin 20 percent; level check
- Lithium - possible reduced lithium levels through renal effects; monitor lithium
- Warfarin - no meaningful interaction; safe combination
- NSAIDs - additive risk for kidney injury with volume depletion; short courses generally safe
- Contrast media - hold canagliflozin during contrast studies if kidney function borderline
Contrast studies
Contrast-induced kidney injury
Canagliflozin does not have a specific contrast interaction like metformin (which is held for lactic acidosis concern). However, if kidney function is borderline or dehydration risk is elevated, holding canagliflozin around contrast study is reasonable. Ensure adequate hydration before and after contrast. Recheck kidney function.
Practical drug interaction summary
Key interactions to know
- Rifampicin - substantial dose adjustment or alternative therapy
- Anticonvulsant inducers - similar to rifampicin
- St John's wort - avoid
- Insulin/SU - dose adjustment; monitor hypoglycaemia
- Loop diuretics - additive volume effect; may need dose reduction
- Digoxin - level check if 300 mg canagliflozin
Canagliflozin has relatively few clinically important drug interactions compared with many diabetes medications. Rifampicin is the main pharmacokinetic concern. Diuretics and glucose-lowering medications require monitoring. Most common medications are safe combinations.
⏱️ What to Do If You Miss Canagliflowin
Missed doses of canagliflozin are relatively forgiving in isolation but chronic non-adherence loses glycaemic effect within days.
Missed dose rules
- Missed dose noticed within a few hours - take when remembered, same day (with next meal ideally)
- Missed dose noticed late in day - skip and take tomorrow's dose at usual time
- Never double up - do not take two doses together
- Occasional missed dose - modest immediate impact
- Multiple missed doses - contact prescriber
Impact of missing doses
Glycaemic effect declines quickly
Unlike drugs with long half-lives, canagliflozin's glycaemic effect depends on active drug in the tubule blocking SGLT2. Effect wears off within 1-2 days of stopping. Missing one dose has modest impact. Missing multiple doses substantially reduces glycaemic control. Chronic non-adherence renders the drug ineffective.
Adherence strategies
- Anchor to breakfast habit
- Weekly pillbox visible
- Phone alarm labeled with medication name
- Refill 2 weeks before running out
- 90-day supplies where insurance allows
- Prescription synchronisation with other daily medications
- Travel supply with buffer
Non-adherence signals to your team
Unexpected HbA1c rise. Weight gain (less glucose loss in urine). Blood pressure returning to previous level. Increased thirst reduction. Pharmacy refill records lag. Cost concerns discussed openly. Side effect concerns.
Occasional missed doses are manageable. Chronic adherence over months determines outcomes and long-term CV/renal benefits. Practical routines and honest team discussion support long-term consistent use.
🩺 Canagliflowin Monitoring HbA1c Kidney BP
Canagliflozin monitoring focuses on glycaemic response, kidney function, blood pressure, weight, and specific safety concerns.
Core monitoring schedule
| Assessment | Frequency |
|---|---|
| HbA1c | Every 3-6 months |
| eGFR / creatinine | Baseline; 4-6 weeks after start; then every 6 months |
| Urine albumin-to-creatinine ratio | Annual |
| Weight | Every visit |
| Blood pressure | Every visit |
| Volume status | Every visit |
| Foot examination | Annual; more often if high risk |
| Genital/UTI symptom review | Every visit |
| Lipids | Annual |
| Bone density (high-risk clients) | Baseline; periodic |
| Ketone testing (illness) | As needed if concerning symptoms |
The initial eGFR check
Expect the initial dip
Recheck eGFR at 4-6 weeks after starting canagliflozin. A 3-5 mL/min dip is expected and reversible. Long-term eGFR slope is improved compared with placebo. If dip is over 10 mL/min or fails to stabilise, investigate causes (volume depletion, concurrent medications) and reassess.
Safety-specific surveillance
Priority safety checks
- Volume status - orthostatic vitals if concerns
- Foot examination - baseline and annual; more often if peripheral neuropathy or PAD
- Genital/UTI symptoms - direct enquiry at each visit
- DKA symptom awareness - client education essential
- Bone health if postmenopausal or high fracture risk
- Cardiovascular symptoms
Annual review agenda
Comprehensive yearly assessment
- Effectiveness - HbA1c, weight, BP meeting targets
- Kidney function trajectory
- Cardiovascular status
- Continued need for canagliflozin
- Comparison with alternative SGLT2 (empagliflozin, dapagliflozin)
- Side effect burden
- Foot health
- Bone health if postmenopausal
- Diabetes complication surveillance (eye, foot, kidney, neuropathy)
- Vaccinations up-to-date
- Overall goals aligned with treatment
Monitoring covers glycaemic effectiveness, kidney function trajectory, cardiovascular status, and specific safety concerns. Comprehensive annual review keeps canagliflozin aligned with the client's evolving situation.
👵 Canagliflowin in Older Adults
Older adults benefit substantially from canagliflozin's cardiovascular and renal protective effects. But specific vulnerabilities require attention.
Age-specific considerations
Considerations in older adults
- Higher CV and renal risk - benefit potentially larger
- Volume depletion risk higher - baseline reduced fluid intake, thirst response, and renal reserve
- Polypharmacy common - interactions more likely
- Fall risk higher - orthostatic hypotension concern
- Genital infection risk elevated - baseline colonisation
- eGFR often reduced - shapes dosing and appropriateness
- Foot problems more common - amputation risk consideration
Standard older adult approach
Practical adjustments
- Careful volume assessment before starting
- Reduce loop or thiazide diuretic dose modestly at start
- Emphasise adequate hydration
- Attentive foot care - inspect and address any problems promptly
- HbA1c targets often less strict (7.5-8.5 percent)
- Blood pressure monitoring at initiation
- Fall prevention
- Cognitive assessment for adherence
When to consider alternatives
For older adults with baseline substantial fall risk, prior amputation, or advanced peripheral vascular disease, empagliflozin or dapagliflozin may be preferred over canagliflozin. The amputation and fracture signals from CANVAS are particularly relevant to frailer older clients.
Benefits amplified
Older adults gain most from SGLT2 benefits
Cardiovascular events, heart failure, and kidney disease progression - the three main SGLT2 targets - are all more common in older adults. Absolute benefits from canagliflozin can be substantial. Weigh benefits against age-related vulnerabilities.
Higher stopping threshold in older adults
Lower threshold to discontinue or switch
- Recurrent genital or urinary infections
- Substantial volume depletion or orthostatic symptoms
- Any fracture
- Foot problem developing
- Cognitive decline affecting adherence or symptom recognition
- Any DKA episode
Older adults often benefit substantially from canagliflozin's CV and renal protective effects. Careful attention to volume status, foot care, infection prevention, and fall risk supports safe use. Empagliflozin or dapagliflozin may be preferred in specific high-risk older adult populations.
🤒 Sick Days and Illness on Canagliflowin
Illness disrupts diabetes management. Canagliflozin has specific sick day rules including holding during severe illness to prevent DKA and volume depletion.
General principles
Continue canagliflozin during minor illness if eating and drinking normally. Hold canagliflozin during moderate-severe illness with vomiting, dehydration, or substantially reduced intake. Monitor glucose. Continue other diabetes medications per team direction. Monitor for DKA symptoms even if glucose is normal.
Situations by scenario
| Situation | Approach |
|---|---|
| Minor viral illness, eating normally | Continue canagliflozin; extra hydration |
| Vomiting or unable to eat | Hold canagliflozin; hydration priority; contact team |
| Fever with reduced appetite | Hold canagliflozin; extra hydration; monitor glucose |
| Severe infection with hospitalisation | Hold canagliflozin; hospital diabetes management (often insulin) |
| DKA (any glucose level) | Emergency; stop canagliflozin; hospital treatment |
| Severe dehydration | Hold canagliflozin; IV fluids; monitor kidney and glucose |
| Diarrhoea substantial | Hold if dehydration developing |
| Prolonged fasting | Hold canagliflozin |
Practical sick day rules
Home management during illness
- Home glucose monitoring 3-4 times daily
- Home ketone testing if available - especially with symptoms
- Maintain fluid intake - 3-4 L daily if able
- Small frequent carbohydrate-containing meals if possible
- Do not stop insulin if on insulin - DKA risk
- Contact team if unable to eat/drink, glucose over 250 mg/dL, or DKA symptoms
DKA awareness during illness
Check ketones during illness even if glucose normal
Illness is a common DKA trigger on SGLT2 inhibitors. The euglycaemic presentation means glucose testing alone is not sufficient. If home ketone testing available, check when unwell. If ketones over 1.5 mmol/L, contact team. If over 3.0 mmol/L, emergency assessment.
DKA symptoms - nausea, vomiting, abdominal pain, unusual fatigue - warrant urgent care regardless of glucose level.
Hospital admission
Inform hospital team of canagliflozin use. Usually held during acute illness. Insulin regimen typically substituted. Restart canagliflozin before discharge only when eating normally, kidney function checked, volume repleted, and no DKA risk. Assess for the reason canagliflozin was held before restarting.
Emergency signals during illness
Seek urgent care for
- Persistent vomiting
- Suspected DKA (nausea, vomiting, abdominal pain, fatigue) - any glucose level
- Signs of severe dehydration
- Fainting or severe orthostatic symptoms
- Chest pain
- Confusion
- Shortness of breath
- Severe genital or perineal pain with fever
Canagliflozin sick day management centres on holding during moderate-severe illness, hydration, and DKA awareness. Have a written sick day plan from your diabetes team. Home ketone testing capability helpful in specific clients.
📅 Vaccinations and Immunizations While Taking Canagliflowin
Canagliflozin does not affect vaccine efficacy or safety. All standard immunisations proceed as scheduled. Diabetic clients have specific vaccine priorities.
Vaccine safety on canagliflozin
No known interaction with any vaccine. Immune response unimpaired. All routine and travel vaccines proceed as scheduled. Live vaccines safe. mRNA vaccines safe.
Priority vaccines for adults with diabetes
Recommended for diabetic adults
- Annual influenza vaccine - diabetic clients at higher risk for complications
- Pneumococcal vaccines (PCV20 or PCV15 + PPSV23) - per current schedules
- COVID-19 vaccine and boosters - per current guidance
- Zoster vaccine (Shingrix) - adults 50+ or immunocompromised
- Tetanus/diphtheria/pertussis - every 10 years booster
- Hepatitis B - diabetic adults 19-59 recommended
- RSV vaccine - adults 60+ per current guidance
Timing considerations
Take canagliflozin as usual on vaccination day. Vaccines usually well-tolerated - mild arm soreness, occasional low-grade fever. Post-vaccine fever can transiently affect glucose - monitor. If unable to eat due to vaccine-related nausea (rare), consider holding canagliflozin that day. Ensure hydration.
Travel vaccines
Discuss travel plans with team. Yellow fever, typhoid, hepatitis A - all safe on canagliflozin. Malaria prophylaxis - discuss interactions; most agents safe. Travelers diarrhoea can trigger dehydration on canagliflozin - manage carefully, may need to hold drug during severe diarrhoea.
Vaccines proceed normally on canagliflozin. Prioritise influenza, pneumococcal, COVID-19, and zoster vaccines for diabetic adults. Canagliflozin dosing continues unchanged on vaccination days.
🤰 Canagliflowin in Pregnancy Not Recommended
Canagliflozin is not recommended in pregnancy. Standard pregnancy diabetes management uses insulin (or occasionally metformin). Planning matters if pregnancy is possible.
Pregnancy standard
Canagliflozin is not recommended in pregnancy. Limited human data. Animal studies show renal developmental abnormalities. Standard pregnancy diabetes management is insulin - well-established, safe, effective. If a canagliflozin client becomes pregnant, transition to insulin promptly under specialist guidance. If pregnancy is planned, transition before conception.
Pre-conception planning
Before conception
- Discuss with team when pregnancy considered
- Transition to insulin before conception
- Optimise glycaemic control - HbA1c target 6.0-6.5 percent if achievable safely
- Folic acid 5 mg daily for 3 months before conception (higher dose in diabetes)
- Retinal, renal, cardiac assessment
- Continue other diabetes management
If unplanned pregnancy occurs
- Contact obstetric and diabetes teams promptly
- Do not stop canagliflozin abruptly without alternative in place
- Transition to insulin under specialist guidance
- Antenatal care with combined obstetric-diabetes team
- Detailed anomaly ultrasound
- Retinal and renal assessment
- Fetal surveillance
Contraception considerations
Standard contraception approaches apply. Canagliflozin does not interact with oral contraceptives meaningfully. IUD - copper or hormonal - both good options. Discuss options with team.
Post-pregnancy
Insulin continues immediately postpartum. Consider whether to restart canagliflozin after breastfeeding (Section 29). For clients whose primary indication was cardiovascular or renal protection, resuming SGLT2 therapy after weaning may be important.
Canagliflozin is avoided in pregnancy. Pre-conception transition to insulin is standard. Discuss family planning openly with your team.
🍼 Breastfeeding While Taking Canagliflowin Canagliflozin Safely
Canagliflozin is not recommended during breastfeeding. Alternative diabetes management preferred while nursing.
Breastfeeding considerations
- Human breast milk data limited
- Animal studies suggest excretion in milk
- Potential concern about neonatal renal development
- Standard practice - avoid canagliflozin during breastfeeding
- Alternative diabetes management preferred
Standard breastfeeding diabetes management
Compatible options
- Insulin - safe; does not cross into milk in meaningful quantity
- Metformin - safe; extensive experience
- Other agents - insufficient data or avoid
Decision framework
If breastfeeding, use insulin or metformin. Restart canagliflozin after weaning if still appropriate. If canagliflozin essential for CV/renal protection (rare scenario), formula feeding may be considered after full risk-benefit discussion. Combined diabetes-obstetric team consultation for individualised planning.
Postpartum considerations
Breastfeeding itself supports weight loss and improves insulin sensitivity. Insulin requirements often reduced postpartum. Diabetes management can be optimised for breastfeeding period. Contraception continues to matter. Plan resumption of canagliflozin after weaning if the CV/renal protective benefits are important.
Canagliflozin is avoided during breastfeeding. Insulin and metformin are standard breastfeeding-compatible diabetes agents. Restart canagliflozin after weaning if still clinically appropriate.
⚕️ Canagliflowin Around Procedures and Surgery
Canagliflozin requires specific attention around surgery to reduce DKA risk. FDA guidance recommends holding several days before major surgery.
FDA guidance on surgery
FDA sick-day and surgery guidance
Hold canagliflozin at least 3 days before major elective surgery. Do not restart until eating normally postoperatively, hydrated, and no signs of DKA. This reduces DKA risk during the metabolic stress of surgery and fasting.
Elective surgery management
Standard approach
- Hold canagliflozin 3+ days before major surgery
- Insulin regimen for perioperative period as needed
- Anaesthetist and surgeon should know about canagliflozin
- Restart canagliflozin when eating normally, hydrated, stable
- Minor procedures may not require holding
Emergency surgery
Alert team to canagliflozin use. Insulin perioperatively. Monitor for DKA - ketone check even if glucose normal. Fluid balance careful. Restart canagliflozin only when stable, eating, and no DKA risk.
Common procedures
| Procedure | Canagliflozin approach |
|---|---|
| Colonoscopy/endoscopy | Hold day of procedure if fasting; may resume next day |
| CT with contrast | Consider holding if borderline kidney function |
| Dental procedures (routine) | Continue as normal |
| Cataract surgery | Continue; short procedure |
| Joint replacement | Hold 3+ days prior; insulin coverage perioperatively |
| Cardiac surgery | Hold 3+ days prior; specialist coordination |
| Fasting blood tests | Continue morning dose is fine |
Postoperative restart
Before restarting canagliflozin
- Eating and drinking normally
- Adequate hydration
- Kidney function checked (initial dip should not deter restart)
- No signs of infection or DKA
- Volume status stable
- Wound healing progressing normally
Contrast studies
Canagliflozin does not have a specific contrast interaction like metformin. However, if kidney function is borderline or dehydration risk is elevated, holding canagliflozin around contrast study is reasonable. Ensure adequate hydration before and after contrast.
Canagliflozin management around surgery follows the 3-day pre-hold rule for major surgery to reduce DKA risk. Insulin perioperatively as needed. Restart only when stable and eating. Communicate with anaesthesia and diabetes teams.
🔄 Switching Canagliflozin Modern Alternatives
Modern diabetes therapy has consolidated around SGLT2 inhibitors and GLP-1 agonists. Within the SGLT2 class, empagliflozin and dapagliflozin are typically preferred over canagliflozin.
Reasons to consider switching from canagliflozin
- Foot problem, ulcer, or amputation
- Fracture event
- Recurrent genital or urinary infections
- Substantial volume depletion or orthostatic issues
- DKA episode
- Access to empagliflozin or dapagliflozin becoming available
- Preference for agent with dedicated heart failure or CKD trials in non-diabetic clients
- Cost changes making alternatives affordable
Modern SGLT2 alternatives
| Agent | Key trials | Advantages vs canagliflozin |
|---|---|---|
| Empagliflozin (Jardiance) | EMPA-REG, EMPEROR-Reduced/Preserved, EMPA-KIDNEY | Strongest CV mortality data; HFpEF and HFrEF FDA-approved; no amputation signal |
| Dapagliflozin (Farxiga) | DECLARE-TIMI 58, DAPA-HF, DELIVER, DAPA-CKD | Strong HF and CKD data including non-diabetic clients; no amputation signal |
| Ertugliflozin (Steglatro) | VERTIS CV | CV safety established; less used clinically |
Switching within the class
Straightforward switch
All SGLT2 inhibitors share mechanism. Simply substitute at next dose. No overlap needed. Effect maintained. Approximate equivalents: canagliflozin 100 mg ≈ empagliflozin 10 mg ≈ dapagliflozin 10 mg. Canagliflozin 300 mg ≈ empagliflozin 25 mg ≈ dapagliflozin 10 mg (higher dose within maximum). Monitor HbA1c at 12 weeks to confirm equivalent effect.
Other class alternatives
Non-SGLT2 alternatives
- GLP-1 agonists - substantial weight loss; CV benefit; renal benefit; no infection or volume concerns
- Metformin - first-line standard; cheap; safe
- DPP-4 inhibitors - weight-neutral; safe in elderly; no infection concerns
- Pioglitazone - insulin sensitiser; watch weight and heart failure
- Basal insulin - effective at all HbA1c levels
Where canagliflozin still fits
Specific scenarios
- Long-term stable clients doing well without problems
- Cost-sensitive scenarios where generic canagliflozin cheaper than alternatives
- Empagliflozin or dapagliflozin unavailable or contraindicated
- Client preference
Adding to canagliflozin
Common - add GLP-1 agonist for further HbA1c reduction, weight loss, and additional CV benefit. Add metformin (if not already) as foundational therapy. Add insulin if substantial gap in glycaemic control. As newer therapy establishes, no need to change canagliflozin.
Modern diabetes practice within the SGLT2 class often prefers empagliflozin or dapagliflozin over canagliflozin. Both have similar mechanism and benefits without the amputation and fracture signals from CANVAS. Discuss with your team whether current regimen best fits your situation.
🛑 Canagliflowin Contraindications When to Avoid Canagliflozin
Canagliflozin contraindications reflect the specific safety concerns - kidney function, volume status, DKA risk, and pregnancy.
Absolute contraindications
Do not use canagliflozin if:
- Type 1 diabetes - DKA risk substantially elevated
- Diabetic ketoacidosis - requires insulin, not SGLT2
- Hypersensitivity to canagliflozin or other SGLT2 inhibitors
- End-stage kidney disease or dialysis - not effective, not appropriate
- eGFR under 30 mL/min - do not initiate (though may continue if already established for renal benefit in specific cases)
Relative contraindications
Use only after careful risk-benefit assessment
- Prior amputation - consider alternative SGLT2
- Active foot ulcer - treat first; consider alternative
- Advanced peripheral arterial disease - alternative preferred
- Prior DKA - individual assessment
- Recurrent genital or urinary infections - alternative may fit better
- Substantial volume depletion tendency
- Baseline hypotension
- Pregnancy or planned pregnancy - transition to insulin
- Breastfeeding - use insulin or metformin
- Severe hepatic impairment - not recommended
Use with caution
Older adults - amplified concerns. Baseline reduced eGFR (30-45 mL/min) - continue for renal benefit; glycaemic effect reduced. Chronic loop diuretic therapy - reduce diuretic; monitor volume. Ketogenic or very low-carb diet - DKA risk. Recurrent UTIs - individual assessment. Recent surgery or acute illness - hold and reassess.
Pre-treatment checklist
Before starting Canagliflowin
- Confirm indication (glycaemic, CV, or renal)
- Baseline eGFR and creatinine
- Baseline urine albumin-to-creatinine ratio
- Volume status assessment
- Blood pressure
- Foot examination
- Genital/UTI history
- Medication reconciliation (insulin, sulfonylureas, diuretics, rifampicin)
- Pregnancy status and contraception
- DKA and sick-day education
- Consider whether empagliflozin or dapagliflozin better fits
Stop canagliflozin if these develop
- DKA
- Fournier gangrene (extremely rare)
- Foot ulcer or wound - reassess
- Amputation event
- Fracture
- Substantial volume depletion or AKI
- Severe hypersensitivity reaction
- Recurrent severe genital or urinary infection
- Pregnancy
- eGFR falling below 30 mL/min (individual decision)
Canagliflozin contraindications are focused. Careful baseline screening and ongoing monitoring for developing contraindications keeps the drug safe for appropriate clients. Alternative SGLT2 agents may fit better in specific high-risk scenarios.
📦 Storage Travel and Yearly Review
Practical routines around Canagliflowin support long-term consistent use. Storage is simple. Travel needs planning. Annual review keeps the regimen aligned with the client's situation.
Storage
- Room temperature under 30 C
- Original blister packaging until use
- Protect from moisture
- Not in bathroom or hot car
- Out of reach of children
- Do not use past expiry date
- Return unused tablets to pharmacy for safe disposal
Travel planning
Extra supply - 2-3 weeks beyond trip duration. Original packaging with labels. Prescription copy (paper or digital). Diabetes letter from team if useful. Insurance and pharmacy contact information. Time zone changes - keep taking daily; timing gradual shift. Air travel - carry-on bag; not checked.
Travel with diabetes on canagliflozin
Specific travel considerations
- Hydration priority - flights, hot climates, activities all increase dehydration risk
- Foot care - well-fitting travel shoes; inspect daily
- DKA awareness - travelers diarrhoea, dehydration, unusual eating patterns
- Consider ketone strips for illness during travel
- Genital hygiene - infection prevention
- Fast-acting glucose if on insulin/sulfonylurea concurrently
- Medical alert identification
- Travel insurance covering diabetes
Annual review agenda
Yearly assessment topics
- Effectiveness - HbA1c meeting targets
- Kidney function trajectory (eGFR, UACR)
- Cardiovascular status
- Ongoing need for canagliflozin vs alternatives
- Consider empagliflozin or dapagliflozin as potentially preferred alternatives
- Side effect burden - infections, volume, foot problems
- Foot examination
- Bone health if postmenopausal or high risk
- Other diabetes complication surveillance - eye, foot, neuropathy
- Vaccine status
- Overall goals aligned with treatment
The bigger picture
Canagliflozin is one tool in comprehensive diabetes and cardiometabolic care. Diet, exercise, weight management remain foundational. Blood pressure and lipid control matter for cardiovascular outcomes. Diabetes complication surveillance saves lives. Modern SGLT2 inhibitor class has transformed diabetes care - the choice between agents matters less than ensuring the class is used appropriately.
Practical routines support consistent long-term Canagliflowin use. Storage is simple; travel needs attention to hydration, foot care, and DKA awareness; annual review keeps regimen aligned with evolving needs. This guide is a companion to what your endocrinologist, cardiologist, or nephrologist advises specifically for you.
Canagliflowin — Frequently Asked Questions
-
What is Canagliflowin (Canagliflozin) used for?
This drug is primarily prescribed to adults with type 2 diabetes to help lower blood sugar levels. Beyond glucose control, it also reduces the risk of cardiovascular complications and protects kidney health in patients with diabetic nephropathy. -
How does this medication work in the body?
It belongs to the class of SGLT2 inhibitors, which reduce blood sugar by preventing glucose reabsorption in the kidneys. Excess sugar is eliminated through urine, leading to improved glycemic control and additional benefits such as mild weight loss. -
Is Canagliflowin effective for long-term diabetes management?
Yes, clinical studies show that this treatment provides consistent reductions in HbA1c and fasting glucose over months and years. It also demonstrates long-term protection against kidney decline and cardiovascular events, making it a reliable therapy. -
What makes this drug different from other diabetes medications?
Unlike insulin or drugs that stimulate insulin release, this medication works independently of insulin action. This mechanism lowers the chance of hypoglycemia and offers added benefits like weight reduction and cardiovascular risk reduction. -
Can Canagliflowin help with weight management?
Yes, modest weight loss is often observed in patients taking this medication. By promoting glucose elimination through urine, the body expels calories. This makes it useful for overweight patients managing type 2 diabetes. -
What are the most common side effects of this drug?
The most frequently reported side effects include increased urination, genital yeast infections, and urinary tract infections. These are typically mild and manageable but should be monitored. Proper hydration and hygiene can help reduce their occurrence. -
Are there serious risks associated with Canagliflozin therapy?
Although rare, serious side effects may include diabetic ketoacidosis, kidney problems, bone fractures, or lower limb amputations. Patients at risk should be monitored closely, and any unusual symptoms must be reported to a healthcare provider immediately.
See all Canagliflowin questions (32)
📚 Drug Description Sources:
The information in this Canagliflowin (canagliflozin) guide is drawn from pharmaceutical, endocrinology, cardiology, and nephrology sources. Content reflects over a decade of clinical experience since canagliflozin's FDA approval in 2013 as the first SGLT2 inhibitor in the US market, the pivotal CANVAS program establishing cardiovascular safety and efficacy, the CREDENCE trial demonstrating renal protection, and the substantial modern positioning of SGLT2 inhibitors as a preferred class for type 2 diabetes with cardiovascular and renal comorbidities.
🏛️ Regulatory and government agencies
- FDA (US Food and Drug Administration) - canagliflozin US approval March 2013 as Invokana (Janssen); first SGLT2 inhibitor approved in US; multiple label updates including 2017 boxed warning for amputation (removed 2020 after further data); current DailyMed prescribing information
- EMA (European Medicines Agency) - canagliflozin European authorisation 2013
- MHRA (UK) - canagliflozin summary of product characteristics
- Health Canada - canagliflozin product monographs
- TGA (Australian Therapeutic Goods Administration) - canagliflozin product information
- PMDA (Japan) - canagliflozin regulatory materials
📚 Professional societies and clinical guidelines
- ADA (American Diabetes Association) Standards of Care in Diabetes - SGLT2 inhibitor positioning as first-line addition in diabetes with heart failure, CKD, or ASCVD
- EASD (European Association for the Study of Diabetes) - joint ADA/EASD consensus reports
- AACE (American Association of Clinical Endocrinology) - diabetes algorithms
- NICE (UK) NG28 Type 2 Diabetes in Adults - SGLT2 inhibitor role in NHS practice
- KDIGO Diabetes in CKD Guidelines - SGLT2 inhibitors as first-line for diabetic kidney disease
- ESC (European Society of Cardiology) Heart Failure Guidelines - SGLT2 inhibitors as pillar of guideline-directed heart failure therapy
- AHA/ACC Heart Failure Guidelines
🔬 Landmark clinical research
- CANVAS Program - Neal et al. NEJM 2017 - combined analysis of CANVAS and CANVAS-R trials with 10,142 type 2 diabetes clients; canagliflozin reduced major adverse cardiovascular events by 14 percent; identified amputation and fracture signals
- CREDENCE Trial - Perkovic et al. NEJM 2019 - 4,401 type 2 diabetes clients with chronic kidney disease; canagliflozin reduced kidney disease progression by 30 percent; stopped early for efficacy
- EMPA-REG OUTCOME - Zinman et al. NEJM 2015 - empagliflozin CV outcomes precedent
- DECLARE-TIMI 58 - Wiviott et al. NEJM 2019 - dapagliflozin CV outcomes
- CANVAS Amputation Sub-Analysis - Matthews et al. Diabetes Care 2019 - amputation signal characterisation
- Meta-analyses of SGLT2 class effects - McGuire et al. Circulation 2020 and others; CV, renal, and safety class effects
📖 Medical references and textbooks
- Williams Textbook of Endocrinology - SGLT2 inhibitor pharmacology
- Joslin's Diabetes Mellitus - the standard diabetes reference
- Braunwald's Heart Disease - SGLT2 inhibitors in heart failure
- Brenner and Rector's The Kidney - SGLT2 inhibitors in diabetic kidney disease
- Goodman and Gilman Pharmacological Basis of Therapeutics
- Katzung Basic and Clinical Pharmacology
- UpToDate - canagliflozin clinical monographs
- Lexicomp and Micromedex - canagliflozin drug interactions and dosing databases
- Diabetes Care, Diabetologia, JCEM, JASN, Circulation - specialised research journals
Note: This information is educational and does not replace consultation with an endocrinologist, cardiologist, nephrologist, or general practitioner. Canagliflozin was the first SGLT2 inhibitor approved and has established roles in type 2 diabetes glycaemic control, cardiovascular event reduction, and diabetic kidney disease protection. It has specific safety considerations including genital mycotic infections, volume depletion, diabetic ketoacidosis in specific settings, and the historical amputation signal from CANVAS. Modern practice often uses empagliflozin or dapagliflozin instead where cardiovascular or renal benefits are the primary goal. Always follow the treating team's specific instructions.
🩺 Medical Expert Review:
Content reviewed for accuracy by authorities in endocrinology, cardiovascular medicine, and nephrology - the three disciplines that shape SGLT2 inhibitor practice. The following experts represent authoritative research and clinical practice perspectives on canagliflozin specifically and SGLT2 inhibitors more broadly.
Prof. Bruce Neal, MB, ChB, PhD, FRCP
Executive Director, The George Institute for Global Health Australia; Professor of Medicine, University of New South Wales — Sydney, New South Wales, Australia
Prof. Neal led the pivotal CANVAS Program - the landmark cardiovascular outcomes trials that established canagliflozin's cardiovascular benefits and identified the amputation signal. His scholarship on large-scale cardiovascular outcome trials, blood pressure and dietary sodium, and global cardiometabolic disease shapes clinical practice worldwide.
Prof. Vlado Perkovic, MBBS, PhD, FRACP
Provost and Senior Vice President, University of New South Wales Sydney; Professor of Medicine — Sydney, New South Wales, Australia
Prof. Perkovic was chair of the steering committee for the CREDENCE trial - the landmark trial that established canagliflozin's renal protective effects in diabetic kidney disease. His scholarship on chronic kidney disease, hypertension, and cardiovascular-renal outcomes in diabetes has shaped nephrology and diabetes practice internationally.
Prof. Meg J. Jardine, MBBS, PhD, FRACP
Director, NHMRC Clinical Trials Centre; Professor of Medicine, University of Sydney — Sydney, New South Wales, Australia
Prof. Jardine was co-chair of the CREDENCE steering committee and lead author on numerous SGLT2 inhibitor secondary analyses. Her scholarship on chronic kidney disease trial methodology, cardiovascular-renal endpoints, and translation of trial evidence into practice continues to shape diabetes and kidney care.
Prof. Muthiah Vaduganathan, MD, MPH
Cardiologist, Brigham and Women's Hospital; Assistant Professor of Medicine, Harvard Medical School — Boston, Massachusetts, USA
Prof. Vaduganathan has authored numerous influential meta-analyses and secondary analyses of SGLT2 inhibitor cardiovascular outcomes across diabetes, heart failure, and chronic kidney disease. His scholarship on SGLT2 inhibitor class effects and modern guideline-directed medical therapy continues to shape cardiology and diabetes practice.
Prof. Julio Rosenstock, MD
Director, Velocity Clinical Research at Medical City; Clinical Professor of Medicine, University of Texas Southwestern Medical Center — Dallas, Texas, USA
Prof. Rosenstock has led numerous major diabetes clinical trials including CAROLINA and CARMELINA. His scholarship on comparative effectiveness of diabetes therapies, cardiovascular outcome trials, and clinical trial methodology continues to shape international diabetes practice.
More Diabetes Medications


