Erectile Dysfunction: Causes, What the PDE5 Inhibitors Do and How They Are Dosed

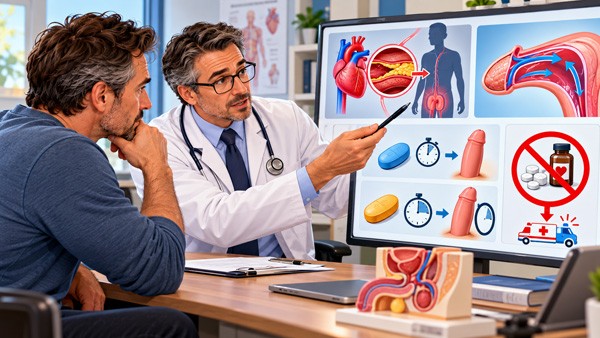

An erection is a vascular event with a nervous system trigger. Sexual stimulation releases nitric oxide in the erectile tissue, nitric oxide produces cyclic GMP, cyclic GMP relaxes the smooth muscle in the arteries, blood floods in faster than it can leave, and the resulting pressure produces rigidity. An enzyme called PDE5 then breaks down cyclic GMP and the erection subsides.
Every modern tablet for erectile dysfunction works at that last step. They block PDE5, so cyclic GMP persists and the relaxation lasts longer. Which explains the most misunderstood point about them: they do nothing without sexual stimulation. There is no nitric oxide to amplify.
Erectile dysfunction means persistent difficulty achieving or maintaining an erection sufficient for satisfactory sex, over at least three months. An occasional failure is not a diagnosis; it happens to everyone.
❤️ The early warning nobody wants to hear
The arteries supplying the erectile tissue are roughly 1 to 2 mm across. The coronary arteries are 3 to 4 mm. When the lining of the blood vessels begins to fail, the narrowest vessels show it first, which is why erectile dysfunction frequently appears three to five years before angina or a heart attack.
🩺 New erectile dysfunction deserves a check-up, not just a prescription. Blood pressure, fasting glucose or HbA1c, lipids, and a testosterone level taken in the morning. Roughly half of men over 50 presenting with erectile dysfunction have undiagnosed cardiovascular risk factors, and a meaningful number have undiagnosed diabetes. Treating the erection and ignoring the signal wastes the warning.
🔍 Organic or psychological: the question that sorts it
| Points to a physical cause | Points to a psychological cause | |
|---|---|---|
| Onset | Gradual, over months or years | Sudden, often traceable to an event |
| Morning erections | Reduced or absent | Preserved |
| With masturbation | Also affected | Usually normal |
| Consistency | Every occasion | Situational, varies by partner or setting |
| Typical age | Over 40 | Any age, common under 40 |
Most cases in practice are mixed: a physical problem appears, a failure produces anxiety, and the anxiety makes the next attempt worse. That loop is why treating the physical side often resolves the psychological side by itself, and why a few successful occasions on medication can rebuild confidence that outlasts the tablets.
🧩 What causes it
- Vascular disease
- The largest group. Atherosclerosis, high blood pressure and raised cholesterol reduce the inflow the erection depends on.
- Diabetes
- Affects both the vessels and the nerves. Erectile dysfunction is around three times more common, appears earlier, and is more resistant to treatment.
- Smoking
- Directly damages the endothelium. Risk roughly doubles, and improvement follows quitting.
- Low testosterone
- Reduces desire more than rigidity. Genuine deficiency is less common than the internet suggests.
- Neurological causes
- Multiple sclerosis, Parkinson disease, spinal injury, and nerve damage after prostate surgery.
- Obstructive sleep apnoea
- Strongly associated and frequently missed. Treating it improves erectile function independently.
- Psychological
- Performance anxiety, depression, relationship difficulty, stress. The dominant cause in men under 40.
💊 Medicines that cause it
This is worth checking before anything else, because the fix may be a conversation with the prescriber rather than a new tablet.
| Drug group | Examples |
|---|---|
| Blood pressure medicines | Thiazide diuretics and older beta-blockers are the main offenders; ARBs and calcium channel blockers much less so |
| 5-alpha reductase inhibitors | Finasteride and dutasteride, used for prostate enlargement and hair loss |
| Antidepressants | SSRIs and SNRIs commonly affect erection, desire and orgasm |
| Antipsychotics | Through raised prolactin |
| Opioids | Long-term use suppresses testosterone |
| Others | Cimetidine, spironolactone, some antihistamines, heavy alcohol, cannabis |
None of these should be stopped without advice. Many have alternatives within the same class that cause fewer sexual side effects.
🚨 The interaction that can kill
⛔ Never combine a PDE5 inhibitor with nitrates. Nitrates release nitric oxide, PDE5 inhibitors amplify its effect, and together they can cause a catastrophic drop in blood pressure. This covers glyceryl trinitrate in any form, including tablets, sprays and patches, isosorbide mononitrate and dinitrate, and amyl nitrite poppers. It also covers riociguat. If chest pain occurs after taking a PDE5 inhibitor, tell the emergency team which tablet was taken and when, because the usual treatment for a heart attack includes a nitrate.
Two further cautions that matter in practice:
- 💊 Alpha-blockers such as tamsulosin, sold here as Flomax (Tamsulosin), also lower blood pressure. The combination is allowed but doses are separated by several hours and the PDE5 inhibitor is started at the lowest strength
- 🍄 Strong CYP3A4 inhibitors including ketoconazole, itraconazole, clarithromycin, erythromycin and ritonavir raise PDE5 inhibitor levels sharply. Doses are reduced, and grapefruit juice has a mild version of the same effect
PDE5 inhibitors are also avoided after a recent heart attack or stroke, in unstable angina, in severe uncontrolled hypertension, in very low blood pressure, and in the rare inherited eye disease retinitis pigmentosa.
📏 The four tablets, and how they differ
| Medicine | Dose | Onset | Duration | Food |
|---|---|---|---|---|
| Sildenafil Citrate | 25, 50 or 100 mg; start at 50 mg | 30 to 60 minutes | 4 to 6 hours | Empty stomach. A fatty meal delays it by up to an hour |
| Cialis (Tadalafil) | 10 or 20 mg on demand, or 2.5 to 5 mg daily | 30 to 120 minutes | Up to 36 hours | Unaffected by food |
| Levitra (Vardenafil) | 10 or 20 mg | 30 to 60 minutes | 4 to 8 hours | Better on an empty stomach |
| Avana (Avanafil) | 50, 100 or 200 mg | 15 to 30 minutes | 4 to 6 hours | Minimal food effect |
The choice is mostly about how a person wants to use it. Tadalafil at 36 hours removes the need to plan, which is why it is nicknamed the weekend tablet, and the low daily dose removes planning entirely while also treating the urinary symptoms of prostate enlargement. Avanafil suits men who want the shortest wait. Sildenafil is the cheapest and the most studied. Generic sildenafil is available here as Kamagra (Sildenafil Citrate) and Caverta (Sildenafil), and the full range is in the men's health category.
🔁 Do not give up after two attempts. Guidelines advise trying a PDE5 inhibitor on at least six to eight occasions at the maximum tolerated dose before calling it ineffective. A large share of apparent treatment failures come down to three fixable things: the dose was too low, it was taken with a heavy meal, or there was no sexual stimulation because the man expected the tablet to work by itself. If one molecule genuinely fails after a proper trial, another often succeeds.
🌡️ Side effects
Most are predictable consequences of vasodilation and settle with use.
- 💥 Headache, the most common, in roughly one in six
- 🥵 Facial flushing and nasal congestion
- 🍴 Indigestion and reflux
- 💪 Back pain and muscle aches, more typical of tadalafil, appearing 12 to 24 hours after the dose
- 🔵 A blue tinge to vision or light sensitivity, specific to sildenafil at higher doses and harmless
🚨 Three situations that need emergency care. Priapism, an erection lasting more than four hours, causes permanent damage to the erectile tissue if untreated and must be treated the same day. Sudden loss of vision in one eye, which may indicate the optic nerve condition NAION. Sudden hearing loss or ringing. In all three, stop the medicine and seek help immediately.
🧪 Testosterone: where it actually fits
Low testosterone reduces desire, morning erections and energy. It is a less common cause of erectile dysfunction than most men assume, and testosterone is not a treatment for erectile dysfunction on its own.
- 🌡️ Diagnosis needs two separate morning samples, taken before 11 am when levels peak, alongside symptoms. A single borderline result means nothing
- 🤝 Where deficiency is confirmed, replacement improves desire and can improve the response to a PDE5 inhibitor that was previously inadequate. Cernos (Testosterone Undecanoate) is the oral option
- ⚠️ Replacement suppresses sperm production and is unsuitable for anyone wanting children. It also requires monitoring of haematocrit and prostate markers, and it is avoided in untreated prostate cancer and severe heart failure
⏱️ Premature ejaculation is a different problem
The two are often confused and sometimes coexist, with a common pattern being a man who rushes because he fears losing the erection. Premature ejaculation means ejaculation within about a minute of penetration, with little control and distress about it.
Priligy (Dapoxetine 30/60 mg) is a short-acting SSRI designed for on-demand use, taken one to three hours before sex rather than daily. It typically increases time to ejaculation about threefold. Nausea and dizziness are the main side effects, and it is not combined with other SSRIs or with MAO inhibitors. Behavioural techniques and thicker condoms work alongside it.
🏃 Lifestyle changes with measured effect
These are not consolation advice. Trials show real improvement in erectile function scores.
- Aerobic exercise
- Around 40 minutes of moderate activity four times a week improved erectile function significantly in randomised trials, with the largest gains in men who had vascular risk factors.
- Weight loss
- Reducing weight improves both testosterone and endothelial function. A third of obese men with erectile dysfunction regain function with weight loss and exercise alone.
- Stopping smoking
- Improvement is measurable within weeks to months, and it is greater in younger men and those with shorter smoking histories.
- Alcohol
- Reducing heavy intake helps. The immediate effect of a large amount of alcohol on erection is familiar to most people; the chronic effect on nerves and hormones is less so.
- Treating sleep apnoea
- Where present, treatment improves erectile function independently of anything else.
⚠️ A word about herbal ED products. Regulatory testing repeatedly finds undeclared sildenafil, tadalafil or their analogues in supplements sold as natural. That means an unknown dose of a prescription vasodilator with no warning about nitrates, which is exactly the combination that causes harm. If a product works, it almost certainly contains a PDE5 inhibitor, and it is safer to take a known dose of a known molecule.
📞 When to see a doctor
- Erectile dysfunction persisting more than three months, particularly with a gradual onset
- Loss of morning erections, which points to a physical cause
- Erectile dysfunction with chest pain, breathlessness or leg pain on walking — assess the arteries before treating the symptom
- Loss of desire, low energy, shrinking testicles — check hormones
- Curvature or pain with erection — possible Peyronie disease
- No response after six to eight properly taken doses at the maximum tolerated strength
- Any episode of an erection lasting over four hours — emergency
❓ Frequently asked questions
Do PDE5 inhibitors cause an automatic erection?
No. They block the enzyme that ends an erection, so they extend a response the body starts. Without sexual stimulation there is no nitric oxide for them to amplify and nothing happens. This is the single most common reason people think the tablet failed.
Can I take a PDE5 inhibitor with heart medication?
Not with nitrates of any kind, including glyceryl trinitrate sprays and patches, isosorbide, poppers, or riociguat. The combination can cause a life-threatening fall in blood pressure. Other heart medicines are usually compatible but need checking with a doctor first.
How long before sex should I take sildenafil?
Thirty to sixty minutes, on an empty stomach. A fatty meal can delay the effect by up to an hour. It lasts four to six hours.
Does tadalafil really last 36 hours?
Yes. A 10 or 20 mg dose remains effective for up to 36 hours, which removes the need to plan around a tablet. Food does not affect it. A lower daily dose of 2.5 to 5 mg is an alternative that also treats the urinary symptoms of prostate enlargement.
The tablet did not work. Does that mean nothing will?
No. Guidelines advise at least six to eight attempts at the maximum tolerated dose before concluding a medicine has failed. Most failures come down to too low a dose, a heavy meal, or no sexual stimulation. If one molecule genuinely fails, another often works.
What do morning erections tell me?
If they are preserved, the plumbing works and the cause is more likely psychological. If they have disappeared gradually, a physical cause such as vascular disease, diabetes or low testosterone is more likely and deserves investigation.
Is erectile dysfunction a sign of heart disease?
It can be an early one. The penile arteries are narrower than the coronary arteries, so they show endothelial damage first, often three to five years before cardiac symptoms. New erectile dysfunction is a reason to check blood pressure, glucose and cholesterol.
When is an erection an emergency?
When it lasts more than four hours. That is priapism, and without treatment the same day it causes permanent damage to the erectile tissue. Sudden vision loss in one eye or sudden hearing loss after a dose also need immediate care.
Will testosterone fix erectile dysfunction?
Only where deficiency is confirmed on two morning blood samples alongside symptoms, and even then it improves desire more than rigidity. It also suppresses sperm production, so it is unsuitable for anyone wanting children.
Can exercise improve erectile function?
Yes, measurably. Around 40 minutes of moderate aerobic activity four times a week improved erectile function scores in randomised trials, with the biggest gains in men who had vascular risk factors. Weight loss and stopping smoking add to it.
📑 Sources and editorial
- Urology guidelines on the diagnosis and management of erectile dysfunction
- Prescribing information for sildenafil, tadalafil, vardenafil, avanafil and dapoxetine, including the nitrate contraindication and CYP3A4 interactions
- Research on erectile dysfunction as a marker of endothelial dysfunction and a predictor of cardiovascular events
- Randomised trials of aerobic exercise and weight loss on erectile function scores
- Guidance on testosterone deficiency diagnosis and the limits of replacement therapy
- Regulatory testing reports on undeclared PDE5 inhibitors in herbal supplements
- Related products: Cialis (Tadalafil), Sildenafil Citrate, Levitra (Vardenafil), Avana (Avanafil), Priligy (Dapoxetine), men's health category
- RXshop Editorial Team — reviewed by Daniel Kim, MD, Endocrinology
Medical Disclaimer: The information in this article is for educational and informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always seek guidance from a qualified healthcare provider with any questions you may have regarding a medical condition, and before starting, stopping or changing any medication.