Pharyngitis: Why Most Sore Throats Need No Antibiotic

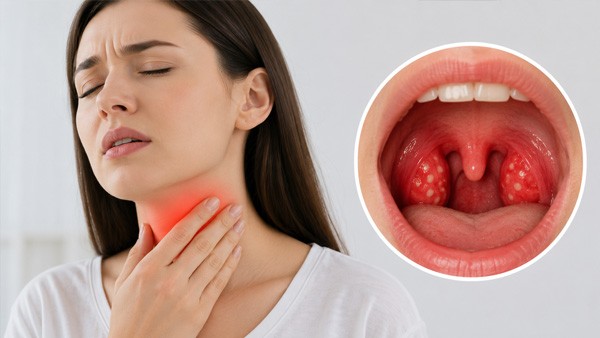
Sore throat is one of the commonest reasons people see a doctor, and one of the commonest reasons they leave with an antibiotic they did not need. The great majority of cases are viral, resolve on their own within a week, and get no benefit whatsoever from antibiotics.
The clinical work is not treating a sore throat. It is identifying the minority that is bacterial, the smaller minority that is something more serious, and giving everyone else the symptom relief that actually helps — which is not what most people are given.
🧠 The number worth knowing: even in confirmed streptococcal sore throat, antibiotics shorten symptoms by roughly sixteen hours on average. They are given for other reasons — preventing rheumatic fever and abscess formation, reducing spread — not because they make the throat feel better quickly. Anyone expecting rapid relief from an antibiotic is expecting the wrong thing, which is one reason people conclude they were given the wrong one.
🔬 What pharyngitis is
Pharyngitis means inflammation of the pharynx, the passage behind the nose and mouth leading to the oesophagus and larynx. Where the tonsils are prominently involved it is often called tonsillitis, and where both are affected, tonsillopharyngitis. The distinction matters less than the cause.
The lining becomes red, swollen and painful, and the lymphoid tissue in the area — the tonsils and the tissue scattered across the back wall of the throat — enlarges as it responds. That combination produces the pain, the difficulty swallowing and the swollen glands in the neck.
🦠 What causes it
| Category | Causes | Share |
|---|---|---|
| Common respiratory viruses | Rhinovirus, coronavirus, parainfluenza, adenovirus, influenza, RSV | The large majority |
| Epstein-Barr virus | Glandular fever — prolonged, with marked fatigue and large glands | Important in teenagers and young adults |
| Group A streptococcus | The bacterium that matters clinically | Roughly one in ten adults, up to a third of children |
| Other bacteria | Fusobacterium necrophorum, groups C and G streptococci, gonorrhoea, diphtheria where unvaccinated | Uncommon but individually significant |
| Non-infectious | Reflux, allergy, dry air, smoking, chemical irritants, persistent cough, mouth breathing | Most chronic cases |
| Fungal | Candida, mainly with inhaled steroids, antibiotics or immune suppression | Uncommon |
Group A streptococcus is the focus of assessment not because it is common but because it is the one that can cause serious complications and the one antibiotics genuinely help.
⚠️ Correcting some persistent misinformation: breathing cold air, getting chilled and being caught in the rain do not cause pharyngitis. Sore throats are caused by infections and irritants. Cold air can dry and irritate an already inflamed throat, and respiratory infections are more common in winter for reasons of indoor crowding and virus behaviour rather than temperature. Attributing a sore throat to a chill is harmless in itself, but it feeds the idea that it can be prevented by wearing a scarf rather than by handwashing.
📊 Telling strep from viral
No single feature distinguishes them reliably, but a scoring system based on four findings works well enough to guide decisions, and it is used worldwide.
| Feature | Points |
|---|---|
| Fever in the history | 1 |
| Absence of cough | 1 |
| Tender swollen glands at the front of the neck | 1 |
| Tonsillar swelling or exudate | 1 |
| Age 3 to 14 | 1 (a modification used in children) |
| Age 45 or over | Minus 1 |
A low score makes streptococcal infection unlikely enough that neither testing nor antibiotics is warranted. A high score justifies testing, and in some settings empirical treatment. The single most useful item is the second one: a cough points away from strep, because streptococcal pharyngitis does not typically cause one. A sore throat with a runny nose, cough and hoarseness is viral, and no score is needed to establish it.
Other features favouring a virus include conjunctivitis, mouth ulcers, diarrhoea and a rash typical of a viral exanthem. Features favouring strep include sudden onset, headache, abdominal pain and vomiting in children, and small red spots on the palate.
🧪 Testing
Rapid antigen tests give a result in minutes and are highly specific — a positive result reliably means group A streptococcus is present. They are less sensitive, so a negative result in a child with a convincing picture is often followed by throat culture, which remains the reference standard but takes a day or two.
Testing everyone with a sore throat is not recommended, and the reason is worth understanding. A substantial proportion of children carry group A streptococcus in the throat without being ill with it. Test such a child during a viral sore throat and the result is positive, leading to an antibiotic that treats nothing, while the actual illness runs its viral course. Testing is therefore directed at people whose clinical picture suggests strep in the first place.
Blood tests are unhelpful for acute sore throat generally, but a specific test for glandular fever is used where that is suspected.
💊 Treating streptococcal sore throat
Penicillin remains the first-line treatment after seventy years of use, and remarkably, group A streptococcus has never developed resistance to it. Where penicillin V is not available or palatability is a problem, amoxicillin is used equivalently and is often preferred in children because it can be given once or twice daily and tastes better.
The course runs ten days, which is longer than symptoms last and longer than people expect. The reason is that shorter courses clear symptoms but fail to eradicate the organism reliably, and eradication is what prevents rheumatic fever. Stopping early because the throat feels better defeats the point of taking it at all.
| Situation | Choice |
|---|---|
| Standard | Penicillin V or amoxicillin for ten days |
| Non-severe penicillin allergy | A cephalosporin such as cephalexin |
| Severe penicillin allergy | A macrolide such as clarithromycin, or clindamycin |
| Recurrent or treatment failure | Amoxicillin with clavulanate or clindamycin |
Azithromycin and other macrolides are not first-line. They are reserved for genuine penicillin allergy, because macrolide resistance in group A streptococcus is now substantial in many regions — unlike penicillin resistance, which does not exist. Using a macrolide as a default choice risks treatment failure for no benefit.
❓ Why treat it at all
Given that antibiotics shorten symptoms by less than a day, the case for treating rests elsewhere.
Rheumatic fever is the historical reason. It is an immune reaction following untreated streptococcal infection that damages heart valves permanently, and antibiotic treatment prevents it. It has become rare in high-income countries and remains a leading cause of heart disease in young people in many others, which is why treatment thresholds differ between settings.
Suppurative complications — peritonsillar abscess, spread to deep neck spaces, sinusitis, ear infection — are reduced by treatment.
Post-streptococcal glomerulonephritis, a kidney complication, is not reliably prevented by antibiotics, and it is worth being accurate about that.
Contagiousness falls quickly. Someone with streptococcal pharyngitis is no longer considered infectious after around twenty-four hours of antibiotics, which matters practically for returning to school or work.
🤧 What actually relieves the symptoms
This is the part that helps everyone, including the large majority whose sore throat is viral, and it is consistently under-emphasised.
Anti-inflammatory painkillers such as ibuprofen work better than paracetamol for sore throat specifically, because inflammation is what causes the pain. Taken regularly rather than occasionally, at proper doses, they make a substantial difference. Under-dosing analgesia while focusing on the antibiotic question is the commonest practical error in managing this condition.
Medicated lozenges containing a local anaesthetic or anti-inflammatory provide genuine short-term relief.
Honey has reasonable evidence for the associated cough and throat discomfort, and outperforms several over-the-counter preparations in trials. It must not be given to infants under one year because of botulism risk.
Salt water gargling is cheap, harmless and modestly helpful.
Fluids and cold foods matter more than they sound, because reduced drinking from pain is a genuine problem, particularly in children.
A single dose of corticosteroid is used in some settings for severe pain and speeds relief measurably. It is a clinical decision rather than something to arrange independently.
Humidified air helps a dry irritated throat. What does not help is steam inhalation for a bacterial throat infection, which was widely recommended and has no effect on the infection.
🔴 Warning signs
Most sore throats are unpleasant and unimportant. A few are neither.
| Sign | What it may indicate |
|---|---|
| Difficulty breathing, noisy breathing, drooling, sitting forward to breathe | Epiglottitis — a medical emergency |
| Inability to open the mouth fully, muffled hot potato voice, uvula pushed to one side | Peritonsillar abscess — needs drainage |
| Severe one-sided pain far exceeding the visible findings | Deep neck space infection |
| Neck swelling, rigors and worsening illness in a young adult | Lemierre syndrome — rare, serious, caused by Fusobacterium |
| Unable to swallow fluids, signs of dehydration | Needs assessment regardless of cause |
| Sore throat lasting more than three weeks, particularly with hoarseness or a neck lump | Requires investigation for throat cancer |
| Rash with strawberry tongue | Scarlet fever — treatable, but needs recognising |
The last row on duration deserves emphasis. Persistent hoarseness or a sore throat lasting beyond three weeks, especially in a smoker or drinker, is not a lingering infection and should be examined properly.
🧫 Glandular fever
Infectious mononucleosis caused by Epstein-Barr virus deserves separate treatment because it is common in teenagers and young adults, it mimics streptococcal infection closely, and one specific error is frequently made.
It presents with a severe sore throat, often with impressive tonsillar exudate, prolonged fever, marked fatigue and widespread swollen glands, sometimes with an enlarged spleen. The fatigue can last weeks and occasionally months, far outlasting the throat symptoms.
🔴 Two things matter practically. First, giving amoxicillin or ampicillin to someone with glandular fever produces a widespread itchy rash in a high proportion of cases — not a true penicillin allergy, but frequently recorded as one, which then restricts that person antibiotic options for life. Second, contact sport must be avoided for several weeks, because an enlarged spleen can rupture from a relatively minor blow. Both are avoidable with the right diagnosis, and both follow from assuming a bad sore throat with exudate must be strep.
🔁 When it will not go away
Persistent or recurrent throat symptoms usually have a cause other than repeated infection, and cycling through antibiotics does not find it.
Reflux is probably the commonest, with acid reaching the throat and producing chronic irritation, a sensation of a lump, throat clearing and morning hoarseness — frequently without heartburn, which is why it goes unrecognised.
Allergic rhinitis with post-nasal drip produces continuous throat irritation and is treated by addressing the nose rather than the throat.
Mouth breathing, from nasal blockage or during sleep, dries the throat overnight and produces a sore throat that is worst on waking and improves through the day.
Smoking, vaping, alcohol and dry indoor air all contribute directly.
Chronic tonsillitis and recurrent streptococcal infection are real but less common than assumed. Tonsillectomy is considered when documented episodes are frequent enough over a sustained period — the usual thresholds are around seven episodes in a year, five a year for two years, or three a year for three years, all properly recorded rather than remembered. Below those thresholds the operation risks generally outweigh the benefit, which reduces over time as episodes naturally become less frequent with age.
🛡️ Reducing the chances
Transmission is by respiratory droplets and contaminated hands and surfaces, so the measures are the familiar ones and they do work: handwashing, not sharing drinks and utensils, covering coughs, and staying away from others during the infectious period.
Someone with streptococcal infection stops being infectious about twenty-four hours after starting antibiotics. Viral sore throats are typically most infectious in the first few days.
Influenza and COVID-19 vaccination reduce episodes of sore throat caused by those viruses. Stopping smoking removes both a direct irritant and a risk factor for more frequent infection. Treating reflux and allergic rhinitis where present addresses the commonest non-infectious causes.
✅ A reasonable summary for anyone with a sore throat right now: if you have a cough, runny nose or hoarseness, it is almost certainly viral and antibiotics will not help — take regular anti-inflammatory pain relief, use lozenges, drink fluids, and expect improvement within a week. If you have fever, no cough, swollen tender neck glands and pus on the tonsils, it is worth being assessed and tested. And if you cannot swallow, cannot open your mouth, are drooling or struggling to breathe, that is not a sore throat question at all — seek urgent care.
Antibiotics used for confirmed bacterial throat infection are stocked in the antibiotics category, with Amoxil (amoxicillin) being the usual choice where treatment is indicated. Because most sore throats do not need one, treatment should follow assessment rather than precede it.
❓ Frequently asked questions
Do I need antibiotics for a sore throat?
Usually not. The great majority of sore throats are viral, resolve within a week and get no benefit from antibiotics. They are indicated for confirmed or strongly suspected group A streptococcal infection, mainly to prevent rheumatic fever and abscess formation rather than to relieve symptoms — even in confirmed strep, antibiotics shorten symptoms by only around sixteen hours on average.
How can I tell if it is strep throat?
Four features raise the likelihood: fever, absence of cough, tender swollen glands at the front of the neck, and tonsillar swelling or pus. Age between three and fourteen adds to it; being over forty-five reduces it. The most useful single item is the cough — streptococcal infection does not typically cause one, so a sore throat with cough, runny nose and hoarseness is viral. A rapid test confirms it where the picture is suggestive.
Why is the antibiotic course ten days?
Because shorter courses relieve symptoms but do not eradicate the organism reliably, and eradication is what prevents rheumatic fever. The throat usually feels better within two or three days, which is when people stop — and stopping early defeats the entire purpose of having taken it. Penicillin and amoxicillin are given for ten full days for this reason.
Why is azithromycin not the first choice?
Because macrolide resistance in group A streptococcus is substantial in many regions, while resistance to penicillin has never developed in over seventy years of use. Macrolides are reserved for genuine severe penicillin allergy. Using one as a default risks treatment failure for no benefit, and treatment failure in this context means the organism is not eradicated.
What relieves the pain most effectively?
Anti-inflammatory painkillers such as ibuprofen work better than paracetamol for sore throat specifically, because inflammation causes the pain, and they need to be taken regularly at proper doses rather than occasionally. Medicated lozenges with a local anaesthetic help in the short term. Honey has reasonable evidence and outperforms several over-the-counter preparations, though never in infants under one year. Salt water gargling is harmless and modestly useful.
Why should everyone not just be tested for strep?
Because a substantial proportion of children carry group A streptococcus in the throat without being ill from it. Testing such a child during a viral sore throat returns a positive result, producing an antibiotic that treats nothing while the actual illness runs its viral course. Testing is therefore directed at people whose clinical picture already suggests streptococcal infection.
What is the rash people get with glandular fever and amoxicillin?
Giving amoxicillin or ampicillin to someone with infectious mononucleosis produces a widespread itchy rash in a high proportion of cases. It is not a true penicillin allergy, but it is frequently recorded as one, which then restricts that person antibiotic options for life. It happens when a severe sore throat with tonsillar exudate is assumed to be strep without considering glandular fever, which is common in teenagers and young adults.
When is a sore throat an emergency?
Difficulty breathing, noisy breathing, drooling or sitting forward to breathe suggest epiglottitis and require immediate emergency care. Inability to open the mouth fully, a muffled voice and the uvula pushed to one side suggest a peritonsillar abscess needing drainage. Severe one-sided pain out of proportion to the findings, or neck swelling with rigors in a young adult, both need urgent assessment.
Does cold air or getting chilled cause a sore throat?
No. Sore throats are caused by infections and irritants. Cold air can dry and irritate a throat that is already inflamed, and respiratory infections are commoner in winter because of indoor crowding and virus behaviour rather than temperature. The belief is harmless in itself but unhelpful, because it directs prevention toward scarves rather than toward handwashing and not sharing drinks.
My throat is always sore. What is going on?
Persistent throat symptoms usually have a cause other than repeated infection. Reflux is probably the commonest, producing chronic irritation, a lump sensation and morning hoarseness, often without any heartburn. Allergic rhinitis with post-nasal drip, mouth breathing from nasal blockage, smoking, vaping and dry indoor air all contribute. Repeated antibiotic courses do not find any of these.
When are tonsils removed?
When documented episodes are frequent enough over a sustained period — the usual thresholds are around seven in a year, five a year for two years, or three a year for three years, properly recorded rather than recalled. Below those levels the risks of surgery generally outweigh the benefit, particularly since episode frequency naturally declines with age. Obstructive sleep apnoea from very large tonsils is a separate and stronger indication.
How long should a sore throat last?
Most viral sore throats improve within three to five days and resolve within a week. Glandular fever lasts considerably longer, with fatigue persisting for weeks. A sore throat continuing beyond three weeks is not a lingering infection and should be examined, particularly alongside hoarseness, a neck lump, unexplained weight loss, or in a smoker or heavy drinker, since throat cancer presents this way.
📑 Sources and editorial
- Infectious Diseases Society of America guideline for the diagnosis and management of group A streptococcal pharyngitis
- NICE guidance on sore throat and antimicrobial prescribing, including the FeverPAIN and Centor scoring approaches
- Cochrane reviews on antibiotics for sore throat and on corticosteroids for symptom relief
- Centor RM and McIsaac WJ — original derivation and modification of the clinical scoring criteria
- Evidence on macrolide resistance in group A streptococcus and the absence of penicillin resistance
- FDA prescribing information for amoxicillin, cephalexin, clarithromycin and clindamycin
- Related products: antibiotics category
- RXshop Editorial Team — reviewed by Emily Chen, MD, MPH, Internal Medicine
Medical Disclaimer: The information in this article is for educational and informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always seek guidance from a qualified healthcare provider with any questions you may have regarding a medical condition, and before starting, stopping or changing any medication.