Urethritis: Symptoms, Causes, Testing and Treatment

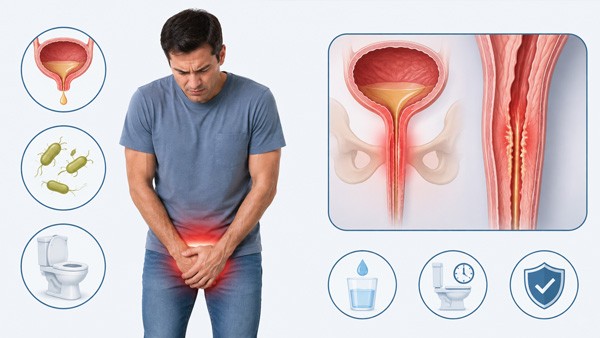
Urethritis is inflammation of the urethra, the tube carrying urine out of the body. It announces itself with burning on urination, discharge, or an irritating urge to pass urine that produces very little — and in the majority of cases it is sexually transmitted, a fact that older writing on the subject tends to bury under talk of chills, spicy food and sitting too long.
It is one of the commonest reasons people attend sexual health services, and it is straightforward to treat once the cause is identified. The difficulties lie elsewhere: it is frequently mistaken for a bladder infection and given the wrong antibiotic, it is often silent in women until complications develop, and it recurs relentlessly when partners are not treated at the same time.
🧠 The distinction that governs everything: urethritis and cystitis are different problems requiring different drugs. A bladder infection is usually caused by gut bacteria and responds to antibiotics that concentrate in urine. Urethritis is usually caused by sexually transmitted organisms living inside the cells lining the urethra, and needs antibiotics that penetrate tissue. Treating one as if it were the other is the single most frequent error in this area.
🔬 What urethritis actually is
The urethra is lined with mucous membrane that reacts to infection or irritation by becoming inflamed, swollen and productive of discharge. Because the tube is short in women — a few centimetres — and long in men, the same infection produces different pictures. Men notice discharge and burning early; women may notice nothing at all, or attribute mild symptoms to a bladder infection that never quite clears.
Clinicians split urethritis into two groups based on a single organism, and that split still drives treatment decisions:
| Category | Cause | Character |
|---|---|---|
| Gonococcal urethritis | Neisseria gonorrhoeae | Typically abrupt, with thick yellow or green discharge and marked burning |
| Non-gonococcal urethritis | Everything else — chlamydia, Mycoplasma genitalium, trichomonas, others | Often milder, with clear or white discharge appearing gradually |
The distinction is useful as a starting point but unreliable as a diagnosis. Plenty of gonococcal infections look mild, plenty of chlamydial ones look florid, and mixed infection with two organisms at once is common. Testing settles it; appearance does not.
🦠 What causes it
Most urethritis is infectious and sexually acquired. A smaller share results from irritation or injury, and a proportion never yields an identified organism at all despite proper testing.
| Cause | Notes |
|---|---|
| Chlamydia trachomatis | The commonest identified cause; frequently silent, especially in women |
| Mycoplasma genitalium | Increasingly recognised; a major cause of persistent and recurrent cases, with growing antibiotic resistance |
| Neisseria gonorrhoeae | Requires injectable treatment; resistance is a serious international concern |
| Trichomonas vaginalis | Parasite rather than bacterium; needs a different drug entirely |
| Herpes simplex virus | Causes urethritis with severe pain, sometimes without visible sores |
| Adenovirus | Usually follows oral sex; often with conjunctivitis |
| Gut and skin bacteria | A minority of cases, more relevant after instrumentation or in men who practise anal sex |
| Trauma and irritation | Catheterisation, instrumentation, vigorous activity, soaps, spermicides, latex sensitivity |
⚠️ Correcting some persistent misinformation. Cold weather, sitting for long periods, spicy food and alcohol do not cause urethritis. They may irritate an already inflamed urethra and make symptoms feel worse, which is presumably how they entered the folklore, but they do not produce the inflammation. Attributing symptoms to a chill delays testing, and delayed testing is how a treatable infection becomes a fertility problem.
🚻 How it presents
Symptoms typically appear somewhere between a few days and a few weeks after exposure, and the interval is longer for chlamydia than for gonorrhoea — which is why the most recent partner is not always the source.
In men, the usual picture is discharge from the tip of the penis, often most noticeable in the morning before the first urination, together with burning or stinging on passing urine and sometimes itching or irritation inside the tube. The discharge may be thick and coloured, or barely more than a crust or a stain on underwear.
In women, urethritis is far more likely to be silent, and when symptoms do occur they are easily attributed to something else: burning on urination, needing to pass urine frequently, vaginal discharge, discomfort during sex, or a low-grade ache in the lower abdomen. Because the presentation overlaps almost entirely with cystitis, women are frequently given a course of a urinary antibiotic, feel briefly better as irritation settles, and remain infected.
| Feature | More suggestive of urethritis | More suggestive of cystitis |
|---|---|---|
| Discharge | Usually present | Absent |
| Burning | At the start of the stream, felt in the tube | Throughout, felt lower and deeper |
| Sexual history | Often a new or changed partner | Not relevant |
| Partner symptoms | Partner may have symptoms too | Not relevant |
| Response to short urinary antibiotic | Poor or temporary | Usually rapid and complete |
Neither list is diagnostic. A urine sample sent for the right test resolves the question in a way that symptom pattern cannot.
🔴 Why it matters if left alone
Untreated urethritis does not simply persist as an annoyance. The organisms causing it ascend, and the consequences differ by anatomy.
In men, infection can spread to the epididymis, producing a painful swollen testicle, and less commonly to the prostate. Repeated or severe infection can leave scarring that narrows the urethra, causing long-term difficulty passing urine.
In women, ascending chlamydial or gonococcal infection causes pelvic inflammatory disease, which damages the fallopian tubes. The damage is frequently silent and shows up years later as infertility or as an ectopic pregnancy — a life-threatening event. This is the single strongest argument for testing rather than guessing, because the women at greatest risk are precisely those with the fewest symptoms.
In both, reactive arthritis can follow, and untreated infection in pregnancy can be transmitted to the baby during delivery, causing eye and lung infection. Gonorrhoea and chlamydia also increase susceptibility to other sexually transmitted infections, which is why testing for one is an argument for testing for the rest.
🧪 Getting the right test
Diagnosis rests on identifying the organism, and modern testing has made this much simpler than the swab-heavy protocols described in older material.
Nucleic acid amplification testing is the standard. It detects the genetic material of chlamydia, gonorrhoea, Mycoplasma genitalium and trichomonas, and it works on a first-catch urine sample in men — the first portion of the stream, which carries urethral material — or a self-collected vaginal swab in women, which performs better than a urine sample. No instrumentation is involved.
Culture retains a role for gonorrhoea specifically, because it allows antibiotic sensitivity to be tested. Given rising resistance, this matters more each year.
Microscopy of a urethral smear can confirm inflammation quickly in a clinic setting and is used to decide whether to start treatment before results return.
✅ Practical points that improve accuracy: hold urine for at least one hour before giving a first-catch sample, use the first portion rather than a midstream sample, and test for the full panel rather than only the organism you suspect. Mixed infection is common enough that finding one organism is not a reason to stop looking. Testing for HIV and syphilis at the same visit is standard practice and worth accepting.
💊 Treatment by cause
Treatment targets the identified organism. Where symptoms are marked and follow-up is uncertain, treatment may be started before results return and then adjusted.
| Cause | Standard approach | Notes |
|---|---|---|
| Chlamydia | Doxycycline for seven days | Now preferred over single-dose azithromycin, which has higher failure rates |
| Non-gonococcal urethritis, organism not identified | Doxycycline for seven days | Covers chlamydia and gives reasonable initial activity against mycoplasma |
| Gonorrhoea | Injectable ceftriaxone, single dose | Cannot be treated with oral tablets; requires a clinic |
| Mycoplasma genitalium | Doxycycline followed by a second agent, guided by resistance testing | The commonest reason a case fails to clear |
| Trichomonas | Metronidazole | Antiparasitic; antibiotics for bacteria have no effect |
| Herpes simplex | Antiviral therapy | Antibiotics are useless; the diagnosis is missed when pain is severe and no sores are visible |
| Non-infectious irritation | Remove the irritant; symptomatic measures | Antibiotics are not indicated and add resistance risk |
🔴 Two things that cannot be fudged. Gonorrhoea requires an injection — oral options have been abandoned because of resistance, and no tablet bought online treats it adequately. And nitrofurantoin, the standard drug for uncomplicated bladder infection, does not treat urethritis: it concentrates in urine but does not achieve useful levels in the tissue where these organisms live, and it has no activity against chlamydia, gonorrhoea or mycoplasma at all. If a course of it has failed to help, that is diagnostic information rather than a reason to repeat it.
💊 Why doxycycline became first choice
For years, chlamydial infection was treated with a single dose of azithromycin, which had the obvious advantage of being taken under observation with no adherence problem. That practice has been reversed in current guidance, and the reasons are worth understanding.
Trials comparing the two found higher microbiological failure rates with single-dose azithromycin, particularly for rectal infection, which is frequently present alongside genital infection and often unsuspected. A seven-day course of doxycycline clears infection more reliably. Single-dose treatment also exerts selection pressure that has contributed to macrolide resistance in Mycoplasma genitalium, now widespread enough to be a routine clinical problem.
Doxycycline is taken twice daily for seven days. Practical points that determine whether it works:
- Complete the full course. Symptoms usually settle within days; the infection is not cleared at that point.
- Take it with food and a full glass of water, sitting upright and not immediately before lying down — the capsule can irritate the oesophagus.
- Separate it from dairy, antacids and iron or calcium supplements by a couple of hours, because these bind the drug and reduce absorption substantially.
- Expect photosensitivity. Skin burns much faster than usual; sun protection during the course is necessary rather than optional.
- Avoid it in pregnancy and in children, where alternatives are used instead.
- No sex until treatment is complete in both partners — a full seven days after both have finished.
🤝 Partners have to be treated
This is where most treatment failure originates, and it is not really a medical problem.
Sexual partners within the preceding period — typically two months, longer if the last contact was further back — need testing and treatment whether or not they have symptoms. The majority of infected women and a substantial proportion of infected men have no symptoms at all, so waiting for a partner to develop something before acting guarantees reinfection.
Health services in many countries provide partner notification support, including anonymous notification where the conversation is impossible. Where partner treatment does not happen, the cycle is entirely predictable: treat, clear, resume sex, reinfect, and interpret the result as the antibiotic having failed.
⚠️ Retesting is not the same as test of cure. A repeat test three months after treatment is recommended for chlamydia and gonorrhoea, not because treatment usually fails but because reinfection is common. Testing too soon — within about four weeks — can detect residual genetic material from dead organisms and return a positive result in someone who is actually cured, prompting unnecessary further antibiotics.
🔁 When symptoms will not settle
Persistent or recurrent urethritis after treatment is common enough to have its own management pathway. Working through the possibilities in order avoids the usual response of cycling through antibiotics.
| Possibility | How to address it |
|---|---|
| Reinfection from an untreated partner | The commonest explanation by a wide margin; check partner treatment actually happened |
| Mycoplasma genitalium, resistant or untested | Specific testing including resistance markers where available |
| Trichomonas, missed on initial testing | Requires an antiparasitic, not an antibiotic |
| Incomplete course taken | Ask directly rather than assuming |
| Herpes simplex | Consider where pain is disproportionate to discharge |
| Non-infectious irritation | Soaps, spermicides, latex, frequent washing, anxious repeated checking for discharge |
| Chronic pelvic pain syndrome | Symptoms persist with no organism; repeated antibiotics do not help and antibiotic courses should stop |
That last row deserves emphasis. A proportion of men end up with persistent urethral discomfort after infection has been fully cleared, and the pattern is then driven by pelvic floor tension, inflammation and anxiety rather than by any surviving organism. Further antibiotics do nothing except cause side effects, and recognising the shift is what allows the right treatment to start.
🛡️ Prevention
Prevention is largely a matter of a few things done consistently rather than anything complicated.
Condoms reduce transmission of chlamydia, gonorrhoea and trichomonas substantially when used consistently, including for oral and anal sex where the organisms are transmitted just as readily and tested for less often.
Regular testing is the measure that catches what condoms miss. Anyone with a new partner or multiple partners benefits from routine screening, and it detects the silent infections that would otherwise be found only when a complication appears. Screening programmes for chlamydia in younger adults exist precisely because so many cases have no symptoms.
Prompt treatment of a diagnosed infection, together with partner treatment, prevents onward transmission and is a public health measure as much as a personal one.
Avoiding urethral irritants matters for the non-infectious cases: harsh soaps and shower gels used internally, spermicides in sensitive individuals, and excessive washing that strips the mucous membrane.
What does not prevent urethritis, despite frequent claims: urinating immediately after sex, which helps with bladder infections but not with organisms that colonise the urethral lining; cranberry products; and douching, which increases rather than decreases the risk of ascending infection.
📋 What to do about symptoms now
If burning, discharge or urethral irritation has appeared, the sequence is straightforward.
Get tested rather than guessing, ideally at a sexual health service where the full panel is standard and partner notification support exists. Avoid sex until the result is known and treatment complete. Do not take leftover antibiotics from a previous course or a friend, which produces partial treatment, masks the diagnosis on subsequent testing and drives resistance. And be honest about exposure history — the type of contact determines which sites need swabbing, and a throat or rectal infection missed because it was not mentioned is a common source of apparent treatment failure.
Seek same-day assessment for fever, testicular pain and swelling, lower abdominal pain in women, blood in the urine, or inability to pass urine, all of which suggest the infection has spread beyond the urethra.
The antibiotic used most often for non-gonococcal urethritis is stocked as Vibramycin (doxycycline 100 mg), with the wider range in the antibiotics category. Treatment should follow a confirmed diagnosis, because the choice of drug depends entirely on which organism is present.
❓ Frequently asked questions
Is urethritis always sexually transmitted?
Not always, but most cases are. Chlamydia, Mycoplasma genitalium, gonorrhoea and trichomonas account for the majority. Non-sexual causes exist — catheterisation, instrumentation, injury, and irritation from soaps or spermicides — and a proportion of cases never yield an identified organism despite proper testing. Because the sexually transmitted causes dominate and have serious complications, testing is appropriate even where a non-sexual explanation seems likely.
How is urethritis different from a bladder infection?
Different site, different organisms, different treatment. Cystitis is infection of the bladder, usually by gut bacteria, and responds to antibiotics that concentrate in urine. Urethritis is inflammation of the urethra, usually caused by sexually transmitted organisms living inside the cells of the lining, and requires antibiotics that penetrate tissue. Discharge points toward urethritis; its absence points toward cystitis. Testing settles it.
Why did nitrofurantoin not help?
Because it is the wrong drug for this condition. Nitrofurantoin concentrates in urine, which makes it effective for uncomplicated bladder infection, but it does not reach useful levels in the tissue where urethritis organisms live and has no activity against chlamydia, gonorrhoea or mycoplasma. A failed course is useful information: it makes a simple bladder infection unlikely and argues for proper testing.
Can urethritis clear up on its own?
Symptoms can settle without treatment, which is misleading, because the infection frequently persists. The organism continues to be transmitted and continues to ascend. In women this leads to pelvic inflammatory disease and tubal damage that shows up years later as infertility or ectopic pregnancy; in men it can lead to epididymitis and urethral scarring. Disappearing symptoms are not evidence of cure.
How soon after exposure do symptoms appear?
Usually between a few days and a few weeks, and the interval is generally shorter for gonorrhoea than for chlamydia. That variability means the most recent partner is not necessarily the source, and it is why partner notification covers a period of roughly two months rather than only the last contact. Many people never develop symptoms at all.
Why is doxycycline preferred over a single dose of azithromycin?
Trials found higher microbiological failure with single-dose azithromycin, particularly for rectal infection, which frequently coexists with genital infection and often goes unsuspected. A seven-day doxycycline course clears infection more reliably. Single-dose macrolide treatment has also contributed to macrolide resistance in Mycoplasma genitalium, now common enough to be a routine clinical problem.
Can gonorrhoea be treated with tablets?
No. Oral regimens have been abandoned because of widespread resistance, and current treatment is a single injection of ceftriaxone given in a clinic. This is one of the situations where no medication ordered online is an adequate substitute. Gonorrhoea also requires culture where possible so that antibiotic sensitivity can be checked, and resistance is monitored internationally as a serious concern.
Do partners need treatment if they have no symptoms?
Yes, and this is where most treatment failure comes from. The majority of infected women and a large proportion of infected men have no symptoms whatsoever. Waiting for a partner to develop something guarantees reinfection once sex resumes. Partners within roughly the preceding two months should be tested and treated, and no sex should occur until seven days after both have completed treatment.
What if symptoms come back after treatment?
Work through the possibilities in order rather than repeating antibiotics. Reinfection from an untreated partner is by far the commonest cause. Next come Mycoplasma genitalium with macrolide resistance, missed trichomonas, an incomplete course, and herpes. Where full testing is negative and symptoms persist, the problem may be chronic pelvic pain rather than infection, and further antibiotics will not help.
How should a urine sample be collected?
For urethritis testing, use a first-catch sample — the first portion of the stream, which carries urethral material — not a midstream sample, which is what bladder infection testing requires. Hold urine for at least an hour beforehand. In women a self-collected vaginal swab performs better than urine and is entirely acceptable as a self-taken sample.
When should I be retested?
Around three months after treatment for chlamydia or gonorrhoea, mainly to detect reinfection rather than treatment failure. Testing sooner than about four weeks can pick up residual genetic material from dead organisms and return a false positive in someone who is cured, leading to unnecessary further antibiotics. A test of cure is done earlier only in specific situations such as pregnancy or persistent symptoms.
Does cold weather or spicy food cause urethritis?
No. Neither cold, sitting for long periods, alcohol nor spicy food produces the inflammation. They can irritate a urethra that is already inflamed and make symptoms feel worse, which is probably how the belief arose. The practical harm is that attributing symptoms to a chill delays testing, and delay is exactly how a straightforward infection turns into a fertility problem.
What should be avoided while taking doxycycline?
Take it with food and a full glass of water while sitting upright, and not immediately before lying down, because the capsule can irritate the oesophagus. Separate it by a couple of hours from dairy, antacids and iron or calcium supplements, which bind the drug and cut absorption considerably. Expect increased sun sensitivity and protect the skin. It is avoided in pregnancy and in young children.
📑 Sources and editorial
- CDC Sexually Transmitted Infections Treatment Guidelines — urethritis and cervicitis
- British Association for Sexual Health and HIV guidelines on the management of non-gonococcal urethritis and on Mycoplasma genitalium
- WHO guidance on gonococcal antimicrobial resistance surveillance
- Trial evidence comparing doxycycline with single-dose azithromycin for chlamydial infection
- FDA prescribing information for doxycycline and metronidazole
- Related products: Vibramycin doxycycline, antibiotics category
- RXshop Editorial Team — reviewed by Emily Chen, MD, MPH, Internal Medicine
Medical Disclaimer: The information in this article is for educational and informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always seek guidance from a qualified healthcare provider with any questions you may have regarding a medical condition, and before starting, stopping or changing any medication.