Organic or Psychogenic ED: How to Tell, and Why It Is Usually Both

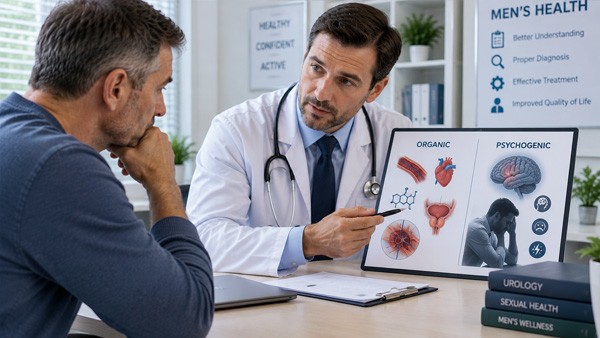
The organic-versus-psychogenic question is the first one most men ask themselves, usually phrased as whether the problem is real or in their head. The framing is understandable and it is the wrong shape, because it implies two boxes and a man belongs in one of them.
In practice the division is a starting point rather than a conclusion. It is genuinely useful for deciding what to investigate, and it stops being useful the moment it is treated as a diagnosis.
💡 Anxiety is not a metaphorical obstacle to an erection. It is a physiological one. An erection requires the parasympathetic nervous system to relax the smooth muscle inside the penis so blood can fill it. The opposite state — the flaccid one — is actively maintained by the sympathetic nervous system through noradrenaline. Anxiety switches the sympathetic system on. So worrying about whether an erection will happen produces exactly the chemical signal that prevents it. This is why a physical cause and a psychological one are not alternatives: any physical cause that produces one failure sets up a psychological mechanism that will produce more, entirely independently.
🧬 What has to work
Understanding the sequence makes the rest of the article easier to follow, and it is short.
Arousal — from touch, thought or sight — triggers nerve endings in the penis to release nitric oxide. That sets off a chain producing a messenger called cGMP, which relaxes the smooth muscle lining the two spongy chambers running the length of the penis. Relaxed muscle lets arteries open, blood floods in, and the expanding chambers compress the veins that would normally drain them. Blood enters easily and cannot leave, which is what produces rigidity.
An enzyme called PDE5 continuously breaks cGMP down, ending the erection. The drugs used for this condition block that enzyme, so cGMP persists longer — which is also why they do nothing without arousal. They extend a signal; they do not create one.
Four systems therefore have to work: the nerves that carry the signal, the arteries that deliver the blood, the veins that must close, and the hormonal and psychological state that permits arousal in the first place. A fault anywhere along that chain produces the same symptom, which is why the symptom alone does not identify the cause.
📊 The classic distinction, and what it is worth
The textbook pattern is real and worth knowing.
| Feature | Suggests physical | Suggests psychological |
|---|---|---|
| How it started | Gradually, over months or years | Suddenly, often traceable to a particular occasion |
| Course | Steadily worse | Variable, with good and bad periods |
| Situational variation | The same in every situation | Fine alone or with one partner, not another |
| Alone versus with a partner | Difficulty in both | Normal alone, difficulty with a partner |
| Morning and night-time erections | Reduced or absent | Preserved |
| Age | More often over forty | More often under forty |
| Associated features | Diabetes, raised blood pressure, smoking, heart disease | Stress, low mood, relationship difficulty, a recent life event |
| Libido | Usually intact | Often reduced alongside |
Used as a guide to what to investigate, this table earns its place. Used as a verdict, it misleads, for three reasons.
Most cases are mixed, particularly after forty. A man with mild arterial disease that would have caused occasional difficulty acquires a substantial anxiety component after the first few failures, and by the time he seeks help the psychological element may be doing more damage than the physical one that started it.
The direction of travel goes both ways. Physical causes generate psychological ones, and psychological ones lead to avoidance, less activity and sometimes to alcohol used to manage the anxiety, which then adds a physical layer.
Medication is a third category that fits neither column and gets filed into both. It has its own section below because it is common, reversible, and regularly missed.
🌅 What morning erections actually tell you
This is the single most used and most over-interpreted sign, so it is worth being precise.
Healthy men have several erections during sleep, occurring during dream sleep. They are involuntary and require no arousal, so they demonstrate that the nerves, arteries and veins can do their job. If they are happening reliably, the machinery is broadly intact and the difficulty is more likely to lie elsewhere.
The problem is the reverse inference. Absent morning erections do not establish a physical cause, because several things suppress them that have nothing to do with blood vessels:
- Poor or fragmented sleep, since these erections occur in dream sleep and no dream sleep means none of them
- Untreated sleep apnoea, which fragments sleep badly and independently damages erectile function
- Alcohol in the evening, which suppresses dream sleep in the first half of the night
- Depression, which alters sleep architecture
- Low testosterone
- Simply waking at a different point in the sleep cycle — you notice them when you wake directly from dream sleep, and not otherwise
So preserved morning erections are informative. Absent ones raise a question rather than answer it, and the first thing to examine is sleep.
💊 The third cause
Medication-induced erectile dysfunction is common, frequently reversible, and often attributed to whichever of the other two categories seems to fit.
| Medicine | Note |
|---|---|
| SSRI and SNRI antidepressants | Among the commonest causes. Affect desire, erection and orgasm. Dose reduction or a switch often resolves it, and the underlying depression also causes it, so this needs untangling rather than guessing |
| Beta blockers | A well-known effect, more with the older non-selective agents. Some newer ones in the class appear considerably better in this respect |
| Thiazide diuretics | A recognised cause; other blood pressure classes are generally kinder |
| Finasteride and dutasteride | Used for prostate enlargement and hair loss. Reduced libido and erectile difficulty in a minority |
| Antipsychotics | Largely through raised prolactin, which suppresses testosterone |
| Opioid painkillers | Long-term use suppresses testosterone production substantially, and this is under-recognised |
| Anabolic steroids | Shut down the bodys own testosterone production, sometimes for a long time after stopping |
| Alcohol and cannabis | Both impair function with regular use, and both are commonly used to manage the anxiety the problem causes |
The practical step is simple and frequently skipped: write down every medicine, including anything bought over the counter, and check the timing against when the problem started. A gap of a few weeks between starting a drug and the onset of difficulty is a strong clue. Nothing on this list should be stopped without advice, since several are treating conditions that themselves cause the problem.
🚩 The warning most men are not given
Erectile dysfunction of physical origin is frequently the first visible sign of arterial disease elsewhere, and it typically appears several years before any cardiac event.
The reason is a matter of plumbing. The same process — damage to the lining of blood vessels from smoking, diabetes, raised cholesterol and raised blood pressure — affects arteries throughout the body at roughly the same rate. But the arteries supplying the penis are considerably narrower than the coronary arteries, so an equal degree of narrowing produces a noticeable effect there first. The symptom appears in the small vessel while the larger ones are still coping.
⚠️ This makes new erectile difficulty in a man over forty a reason to check cardiovascular risk, not merely a reason to request a prescription. Blood pressure, cholesterol, blood glucose, weight and smoking status — a short set of measurements that may matter considerably more over the next decade than the symptom that prompted them. A man who gets a prescription and no assessment has been treated for the inconvenience and left with the underlying process untouched.
🔬 What is worth testing
Assessment is mostly conversation and a small number of blood tests. Elaborate investigation is rarely needed.
The history does most of the work — how it began, whether it varies by situation, what happens alone, whether morning erections occur, what changed around the time it started, and how sleep, mood and the relationship are.
Blood glucose or HbA1c. Diabetes damages both nerves and small vessels, and erectile difficulty is not infrequently the presentation that leads to the diagnosis.
Cholesterol and blood pressure, for the reason above.
Testosterone, measured correctly. This one has a practical trap. Testosterone follows a daily rhythm and is highest in the morning, so the sample must be taken in the morning, ideally before eleven, and fasting. An afternoon sample can read low in a man whose levels are entirely normal, and a low result should always be repeated before it is acted upon. Low testosterone tends to reduce desire more than it impairs erection specifically, and a man whose libido is intact is unlikely to have it as the main problem.
Thyroid function, and prolactin where libido is low or testosterone is low.
An assessment of sleep, particularly for snoring with pauses in breathing, which is common, treatable and independently damaging.
Specialised testing of night-time erections and ultrasound of penile blood flow exist and are reserved for particular situations — a young man after pelvic trauma, or someone being considered for surgery. They are not part of routine assessment.
🔁 How the cycle establishes itself
Worth setting out explicitly, because recognising it is often the point at which men stop blaming themselves.
A first failure occurs, for any reason at all — too much alcohol, exhaustion, an unfamiliar situation, a new medication, early arterial change. It means nothing on its own.
The next occasion carries a question that was not there before. That question is anxiety, and anxiety activates the sympathetic nervous system, which releases noradrenaline, which maintains the smooth muscle in the contracted state that keeps the penis flaccid. The worry produces the outcome directly.
Attention shifts from arousal to monitoring — watching for a response rather than experiencing the situation, which reduces the arousal the response depends on.
Avoidance follows: fewer occasions, more weight on each one, higher stakes each time. The partner, uninformed, often concludes they are no longer wanted, and the tension in the relationship adds to the load.
By this stage the original cause may account for very little of what is happening. This is why a man with mild physical impairment can end up with severe difficulty, and why treating the anxiety component often produces more improvement than the physical findings would predict.
💊 Why the same drugs work for both
PDE5 inhibitors are effective whether the problem started physically or psychologically, and understanding why explains how they should be used.
They preserve the signal that produces an erection, lowering the threshold of arousal needed. In physical causes that compensates for impaired blood flow. In psychological ones it does something subtler and arguably more valuable: it interrupts the cycle. A few successful occasions remove the expectation of failure, the anxiety subsides, and the sympathetic activation that was causing the problem stops. Many men in this position are able to reduce or stop the drug afterwards, which is not generally true of the physical group.
This is why the drugs are appropriate in psychogenic cases rather than being a way of avoiding the real issue, and it is also why combining medication with addressing the psychological element works better than either alone.
| Onset | Duration | Food | Suits | |
|---|---|---|---|---|
| Sildenafil | 30 to 60 minutes | 4 to 6 hours | A heavy or fatty meal delays it considerably | The usual starting point; the most economical |
| Tadalafil | 30 minutes to 2 hours | Up to 36 hours | Unaffected | Anyone wanting spontaneity, or with prostate symptoms too |
| Vardenafil | 30 to 60 minutes | 4 to 6 hours | Fatty food delays it | An alternative where sildenafil disappoints |
| Avanafil | 15 to 30 minutes | About 6 hours | Little effect | Fastest onset; the most expensive here |
🔴 Never with nitrates. Nitrate medicines for angina — and amyl nitrite or related recreational inhalants — taken with any of these drugs can cause a catastrophic fall in blood pressure. This is an absolute prohibition rather than a caution. Tell any prescriber you take one of these before accepting anything for chest pain. Seek emergency care for an erection lasting more than four hours, which damages tissue permanently if untreated, and for sudden loss of vision or hearing.
🛠️ When the tablet does not work
A substantial proportion of apparent treatment failures are avoidable, and the reasons are consistent.
Too few attempts. Response often improves over the first several occasions, partly because confidence returns. Judging a drug on one or two tries is the commonest error, and four to eight attempts is a fairer trial.
The dose was too low and never adjusted.
Nothing happened because nothing was expected to. These drugs require arousal. Taking one and waiting for an erection to arrive unprompted produces disappointment and a false conclusion.
Timing and food. Sildenafil taken immediately after a large meal may take considerably longer than expected, and the occasion has passed by the time it works.
Untreated low testosterone, which blunts the response. Correcting it can restore effectiveness in a man who previously did not respond.
Alcohol. A small amount is neutral; more than that impairs the response directly, and it is frequently being used to manage the anxiety.
The anxiety component was never addressed, so the drug is fighting a mechanism that regenerates each time.
Where these have all been dealt with and the response is still inadequate, other treatments exist — injections, vacuum devices, implants — and are worth asking about rather than concluding that nothing can be done.
🧠 Addressing the psychological side
This is skipped far more often than it is tried, and it works.
Structured psychological therapy aimed at sexual difficulty has good evidence, and combining it with medication outperforms either alone. It is not open-ended talking about childhood; it is a focused, practical approach to the anxiety and the monitoring behaviour.
Involving the partner changes outcomes substantially. Most partners assume the problem reflects their desirability, and correcting that assumption removes a large share of the tension in the room.
Removing performance as the objective. Structured exercises that begin with touch explicitly not leading to intercourse break the monitoring pattern by removing the thing being monitored for. This is a standard and effective technique rather than an evasion.
Treating depression and anxiety in their own right, while being alert to the fact that some antidepressants cause the problem themselves — which is a reason to discuss the choice of drug specifically, not a reason to avoid treatment.
🏃 What changes the underlying picture
These affect the physical side genuinely rather than marginally, and several have been shown to improve erectile function in trials on their own.
Stopping smoking. Direct damage to the small arteries that matter most here, and improvement follows stopping.
Regular aerobic exercise. One of the few interventions with trial evidence of improving erectile function directly, through effects on the blood vessel lining.
Weight loss where relevant. Excess weight lowers testosterone and worsens vascular function together.
Treating sleep apnoea. Common, under-diagnosed, and improvement in erectile function is a well-documented consequence of treating it.
Controlling diabetes, blood pressure and cholesterol — and where a blood pressure drug is itself the cause, asking whether a different class would suit.
Reducing alcohol.
📋 A workable sequence
Answer the discriminating questions honestly — how it began, whether it varies by situation, what happens alone, whether morning erections occur.
Review every medicine against the timing of onset.
Get the basic tests: glucose, cholesterol, blood pressure, and a morning testosterone if libido is reduced.
Look at sleep, particularly for snoring with pauses.
Expect the answer to be both, and treat both. This is the point of the article.
Start a PDE5 inhibitor and give it a proper trial — adequate dose, several attempts, correct timing, arousal present.
Involve your partner, which is uncomfortable and consistently helps.
Address the cardiovascular findings, which may matter more in ten years than the symptom does now.
Treatment is stocked in the mens health category, including Cenforce (sildenafil 100 mg) as the usual first-line option, Cialis (tadalafil) for longer duration, Levitra (vardenafil) and Avana (avanafil) for the fastest onset.
❓ Frequently asked questions
Is it physical or is it in my head?
Usually both, and the question sets up a false choice. Anxiety is a physiological obstacle rather than a metaphorical one — it activates the sympathetic nervous system, which releases noradrenaline, which maintains the muscle contraction that keeps the penis flaccid. So any physical cause producing one failure sets up a psychological mechanism that produces more, entirely on its own. Treating only one side commonly fails.
I still get morning erections. Does that rule out a physical cause?
It is reassuring rather than conclusive. These erections are involuntary and require no arousal, so occurring reliably they show the nerves, arteries and veins can do their job. That points away from a predominantly physical cause but does not exclude a partial one, particularly in a man over forty where mixed pictures are the rule.
I have stopped getting them. Does that mean it is physical?
Not necessarily, and this is the more common error. These erections happen during dream sleep, so anything disrupting sleep suppresses them — poor or fragmented sleep, untreated sleep apnoea, evening alcohol, depression, low testosterone. You also only notice them when you wake directly out of dream sleep. Absent morning erections raise a question rather than answer one, and sleep is the first thing to examine.
Could my medication be causing this?
Quite possibly, and it is a third category that gets misfiled into the other two. SSRI and SNRI antidepressants are among the commonest causes, along with beta blockers, thiazide diuretics, finasteride and dutasteride, antipsychotics, long-term opioids, and anabolic steroids. Write down everything you take, including over-the-counter items, and check the timing against when the difficulty began. Do not stop anything without advice.
Why should I check my heart if the problem is erections?
Because physical erectile difficulty is frequently the first visible sign of arterial disease and typically appears years before any cardiac event. The same damage to blood vessel lining affects arteries throughout the body at a similar rate, but the arteries supplying the penis are much narrower, so equal narrowing shows there first. New difficulty over forty is a reason to check blood pressure, cholesterol and glucose.
When should a testosterone test be taken?
In the morning, ideally before eleven, and fasting, because testosterone follows a daily rhythm and is highest early. An afternoon sample can read low in a man whose levels are entirely normal, and a low result should always be repeated before it is acted on. Low testosterone tends to reduce desire more than it impairs erection specifically, so intact libido makes it an unlikely main cause.
Do tablets work if the cause is psychological?
Yes, and often particularly well. They preserve the signal that produces an erection, which lowers the threshold of arousal needed and, more importantly, interrupts the cycle. A few successful occasions remove the expectation of failure, the anxiety subsides, and the sympathetic activation causing the problem stops. Many men in this position can reduce or stop the drug afterwards, which is less often true of physical causes.
The tablet did nothing. What went wrong?
Usually one of a short list. Too few attempts — response improves over the first several occasions and four to eight is a fair trial. A dose never adjusted upward. No arousal, since these drugs extend a signal rather than creating one. Sildenafil taken straight after a heavy meal, which delays it considerably. Untreated low testosterone, which blunts the response. Alcohol. Or an anxiety component never addressed.
Which of the four drugs should I start with?
Sildenafil is the usual starting point and the most economical. Tadalafil suits anyone wanting spontaneity, since it lasts up to thirty-six hours and food does not affect it, and it also helps prostate symptoms. Vardenafil is a reasonable alternative where sildenafil disappoints. Avanafil has the fastest onset at fifteen to thirty minutes and is the most expensive. Failing on one does not predict failing on another.
Why does it happen with my partner but not alone?
That pattern points strongly toward a psychological mechanism, and the mechanism is physical in its operation. Alone there is nothing to monitor and no consequence to a poor outcome. With a partner, attention shifts from arousal to watching for a response, which itself reduces arousal, while the anxiety activates the nervous system that actively maintains flaccidity. Involving your partner in understanding this changes outcomes substantially.
What actually improves the physical side?
Stopping smoking, since the small arteries that matter most here are directly damaged. Regular aerobic exercise, one of the few things shown in trials to improve erectile function on its own. Weight loss, which raises testosterone and improves vascular function together. Treating sleep apnoea, which is common, under-diagnosed and reliably helps. Controlling diabetes, blood pressure and cholesterol, and reducing alcohol.
What must I never combine these tablets with?
Nitrates. Nitrate medicines for angina, and amyl nitrite or related recreational inhalants, taken with any PDE5 inhibitor can cause a catastrophic drop in blood pressure. It is an absolute prohibition rather than a caution, so tell any prescriber you take one before accepting anything for chest pain. Seek emergency care for an erection lasting over four hours, or sudden loss of vision or hearing.
📑 Sources and editorial
- American Urological Association guideline on the evaluation and management of erectile dysfunction
- European Association of Urology guidance on sexual and reproductive health
- Research on the artery size hypothesis and erectile dysfunction as a predictor of cardiovascular events
- Physiology literature on nitric oxide, cGMP signalling and sympathetic maintenance of detumescence
- Studies of nocturnal penile tumescence and the confounders affecting its interpretation
- Reviews of medication-induced sexual dysfunction, including antidepressants, antihypertensives and 5-alpha reductase inhibitors
- Trials of combined pharmacological and psychological treatment for erectile dysfunction
- Trials of aerobic exercise and of continuous positive airway pressure on erectile function
- Endocrine Society guidance on testosterone measurement timing and interpretation
- FDA prescribing information for sildenafil, tadalafil, vardenafil and avanafil, including nitrate contraindication
- Related reading: is erectile dysfunction age related, psychogenic erectile dysfunction in young men, enlarged prostate
- Related products: mens health category
- RXshop Editorial Team — reviewed by Michael Reeves, MD, FACS, Urologist and Mens Health Specialist
Medical Disclaimer: The information in this article is for educational and informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always seek guidance from a qualified healthcare provider with any questions you may have regarding a medical condition, and before starting, stopping or changing any medication.