Recurrent Cystitis: When Prophylaxis Is Justified and Which Strategy Fits Which Pattern

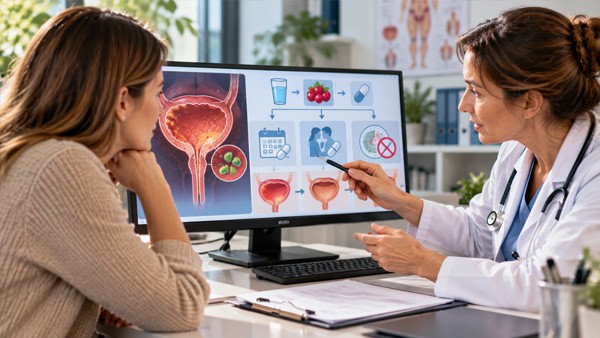
Most cystitis is caused by E. coli that normally lives in the bowel, travelling the short distance to the urethra and up into the bladder. In women that distance is around 4 cm, which is the single biggest reason cystitis is overwhelmingly a female condition and why prevention is largely about interrupting a route rather than boosting immunity.
Recurrence is common and it is not a sign of poor hygiene. Roughly a quarter of women who have one episode have another within six months. What turns a series of episodes into a manageable problem is identifying which route is being used, because each pattern has a different and often non-antibiotic answer.
📏 What counts as recurrent, and why the definition matters. Recurrent cystitis means two or more episodes in six months, or three or more in twelve months, each with symptoms and ideally a positive culture. Below that threshold, prophylaxis is not considered: episodes are treated as they come. Above it, the balance shifts, and a prevention plan becomes worth the trade-offs. Knowing which side of the line you are on is the first decision, not a detail.
🧩 Find the pattern first
Prophylaxis chosen without identifying the pattern tends to mean continuous antibiotics for everyone. Matching it saves months of unnecessary exposure.
| Pattern | The clue | The highest-yield response |
|---|---|---|
| Sex-related | Episodes within 24 to 48 hours of intercourse | Single post-coital antibiotic dose; stop spermicide use |
| Postmenopausal | Recurrence starting after menopause, with dryness | Vaginal oestrogen |
| Incomplete emptying | Hesitancy, double voiding, constipation, prolapse | Treat the constipation and the emptying, not the bacteria |
| Low fluid intake | Under 1.5 litres a day, infrequent voiding | Increase intake to about 2.5 litres; this alone halved episodes in a randomised trial |
| Contraceptive-related | Diaphragm with spermicide, or spermicide-coated condoms | Change method |
| No clear pattern | Random timing | Self-start therapy or continuous prophylaxis |
💧 What the evidence supports, and what it does not
Much of the standard advice is folklore that has never been tested. Being clear about which is which saves effort for the measures that work.
- Drinking more water — strong evidence
- In a randomised trial, women with recurrent cystitis drinking under 1.5 litres a day who increased to around 2.5 litres had roughly half as many episodes over a year. This is the best-evidenced non-drug measure there is.
- Urinating after sex — reasonable
- Biologically sensible and observationally supported, if not proven in trials. Costs nothing.
- Avoiding spermicide — good evidence
- Spermicides kill protective lactobacilli and are consistently associated with more infections. Worth changing.
- Treating constipation — good evidence
- Genuinely underrated. It reduces both bacterial load nearby and incomplete bladder emptying.
- Wiping front to back, avoiding baths, cotton underwear, avoiding tight clothing — weak or absent evidence
- These are repeated everywhere and have never been shown to reduce recurrence. They are harmless, so there is no reason to stop, and they should not be the plan.
- Douching and harsh intimate washes — avoid
- These do disrupt the protective vaginal flora and are associated with more infection, so avoiding them is worth doing.
🌸 Vaginal oestrogen after menopause
After menopause, falling oestrogen thins the tissue of the vagina and urethra and the protective lactobacilli that keep the pH low largely disappear, allowing E. coli to colonise. This is a structural change, and treating it addresses the cause rather than the bacteria.
Local vaginal oestrogen has among the strongest evidence of any preventive measure in postmenopausal recurrent cystitis, with trials showing substantial reductions in episodes. It is applied as a tablet, cream or ring, typically nightly for two weeks and then twice weekly indefinitely, and systemic absorption is minimal, which is why it is not equivalent to hormone replacement therapy and is usable by many women who cannot take systemic oestrogen. It is available as Vagifem (Vaginal Estradiol 25 mcg).
The effect builds over weeks to months rather than immediately, which is the usual reason it is abandoned too early.
💊 Antibiotic prophylaxis: three different strategies
These are genuinely different approaches, and they are frequently conflated. The doses below are for prevention and are not the same as treatment doses.
🔹 1. Post-coital, for sex-related recurrence
A single dose taken within two hours after intercourse. Where episodes reliably follow sex, this works as well as continuous prophylaxis while using a fraction of the antibiotic, because a woman having sex twice a week takes eight tablets a month instead of thirty.
- 💊 Macrobid (Nitrofurantoin) 50 to 100 mg as a single post-coital dose
- 💊 Bactrim (Sulfamethoxazole and Trimethoprim) at a reduced single dose
- 💊 Keflex (Cephalexin) 250 mg as a single dose, often chosen in pregnancy
🔹 2. Continuous low-dose, for unpredictable recurrence
One low dose every night, given for three to six months and then reviewed, not indefinitely. It reduces episodes by around 80 to 95 percent while it is being taken. The important caveat is that the benefit largely disappears within a few months of stopping, so it buys time rather than curing the tendency, and the time is used for the non-antibiotic measures.
- 💊 Nitrofurantoin 50 to 100 mg at night — the usual first choice, because resistance remains low and it does not disturb bowel flora much
- 💊 Trimethoprim 100 mg at night, where local resistance is low
- 💊 Cephalexin 125 to 250 mg at night
🔹 3. Self-start therapy, for reliable self-recognisers
A full treatment course kept at home, started by the patient at the first symptoms without waiting for an appointment. It suits women who recognise their own symptoms accurately, which most with recurrent cystitis do, and it avoids continuous exposure entirely. It requires a prior agreement with a clinician, a clear instruction on when to start and when to seek help instead, and a urine sample sent before starting where possible.
📋 Treatment doses, for contrast. Acute uncomplicated cystitis: nitrofurantoin 100 mg twice daily for 5 days, or trimethoprim 200 mg twice daily for 3 days, or co-trimoxazole twice daily for 3 days where resistance is under 20 percent, or a single 3 g dose of fosfomycin where available. Note that the prophylaxis dose is roughly half the treatment dose, taken once rather than twice, and the two are not interchangeable.
⚠️ What long-term nitrofurantoin requires
Because prophylaxis means months of a drug rather than days, the safety profile matters differently.
- 🍴 Take with food — it improves absorption and markedly reduces nausea
- 🟫 Urine turns dark yellow or brown. Harmless, expected, and alarming if nobody mentions it
- 🩸 It does not work if kidney function is reduced. Nitrofurantoin acts by concentrating in urine, so below an eGFR of about 45 it fails to reach effective levels while systemic exposure rises. It is avoided at that level
- 🫁 Lung and nerve effects with prolonged use — rare but real. A new persistent dry cough or breathlessness on long-term nitrofurantoin needs assessment and stopping the drug, and so does new numbness or tingling in hands or feet. Prophylaxis courses of three to six months with review exist partly for this reason
- 🤰 In pregnancy it is used in the first and second trimesters but avoided from around 38 weeks and at term, because of the risk of haemolysis in the newborn, and it is avoided in G6PD deficiency
Co-trimoxazole has its own considerations: it raises the effect of warfarin, it interacts dangerously with methotrexate, it can raise potassium, and it causes rash including rare severe reactions.
🌿 Non-antibiotic options, ranked honestly
| Option | Evidence | Verdict |
|---|---|---|
| Increased fluid intake | Randomised trial, roughly halved episodes | Do it first |
| Vaginal oestrogen | Strong in postmenopausal women | Do it if applicable |
| Methenamine hippurate | Non-inferior to daily antibiotics in a randomised trial | The best antibiotic-sparing option; not widely stocked |
| D-mannose | Mixed; some positive trials, one large negative | Reasonable to try, low risk, do not expect much |
| Cranberry | Modest at best; depends on proanthocyanidin content, which most juices lack | Marginal. Juice is mostly sugar |
| Probiotics | Weak, strain-dependent | Unproven |
| Urinary alkalinisers | No effect on infection | Only for symptom comfort, and they inactivate nitrofurantoin |
Methenamine hippurate deserves the attention it does not get: it converts to formaldehyde in acidic urine, which is antiseptic rather than antibiotic, so bacteria do not develop resistance to it. In a large randomised comparison it prevented episodes about as well as daily antibiotics.
🚫 The result that must not be treated
⛔ Bacteria in the urine without symptoms is not an infection and is not treated. Asymptomatic bacteriuria is common, particularly in older women, where it is present in a large minority, and in anyone with a catheter. Treating it does not prevent future infection, does not reduce complications, and does cause resistance, Clostridioides difficile and side effects. It is also a major reason women accumulate antibiotic courses.
The exceptions are pregnancy, where it is screened for and treated because it raises the risk of kidney infection and preterm birth, and before urological procedures that breach the urinary tract.
The practical consequence: do not send urine for testing when there are no symptoms, and do not accept a course of antibiotics for a positive dipstick alone. Cloudy or strong-smelling urine without symptoms is usually concentration, not infection, and a test of cure after a treated episode is not needed either.
🧪 When recurrence needs investigating rather than preventing
Most recurrent cystitis in an otherwise healthy woman needs no imaging. Investigation is warranted for:
- Blood in the urine persisting after treatment, or visible blood
- Infections with unusual organisms, or a different bacterium each time
- Two or more kidney infections, or any episode with fever and flank pain
- Symptoms that persist with repeatedly negative cultures — which points towards bladder pain syndrome rather than infection, and repeated antibiotics do harm there
- Cystitis in a man, which is never considered uncomplicated and needs prostate and outflow assessment
- Diabetes, kidney stones, known urinary tract abnormality, or immunosuppression
- Air or faecal material in the urine, or continuous leakage, suggesting a fistula
- New onset after 40 with weight loss
In recurrent cases a culture with sensitivities before each empirical course is worth the effort, because it stops the cycle of prescribing a drug the organism is already resistant to. A dipstick positive for nitrites supports infection; leucocytes alone do not.
🚨 When an episode is no longer simple cystitis
- Fever above 38 ℃, shivering, or pain in the side or back — kidney infection, needs same-day assessment
- Nausea and vomiting, or inability to keep fluids and tablets down
- Confusion or drowsiness, particularly in an older person, which can be the only sign
- No improvement after 48 hours of an appropriate antibiotic
- Pregnancy with any urinary symptoms — treated promptly, never watched
- Visible blood with clots, or inability to pass urine
❓ Frequently asked questions
How many infections count as recurrent?
Two or more in six months, or three or more in twelve months, each with symptoms. Below that threshold episodes are treated individually and prophylaxis is not considered.
Is the prophylaxis dose the same as the treatment dose?
No. Nitrofurantoin for treatment is 100 mg twice daily for five days; for prevention it is 50 to 100 mg once at night, or a single dose after sex. Roughly half the dose, once instead of twice, and the two are not interchangeable.
My infections always follow sex. What helps most?
A single antibiotic dose taken within two hours after intercourse. It works as well as taking a tablet every night while using a fraction of the antibiotic. Stopping spermicide use, if any, adds further benefit.
How long is continuous prophylaxis taken for?
Three to six months, then reviewed, rather than indefinitely. It reduces episodes by 80 to 95 percent while taken, but the benefit largely fades within months of stopping, so the time is used to establish the non-antibiotic measures.
Does drinking more water actually prevent cystitis?
Yes, and it has the best evidence of any non-drug measure. Women drinking under 1.5 litres a day who increased to around 2.5 litres had roughly half as many episodes over a year in a randomised trial.
Why is my urine brown on nitrofurantoin?
That is a harmless expected effect of the drug itself. Take it with food to improve absorption and reduce nausea. A new persistent dry cough, breathlessness, or numbness in the hands or feet on long-term use does need assessment.
Should I take antibiotics for a positive urine test with no symptoms?
No. Bacteria in urine without symptoms is not an infection and treating it causes resistance and side effects without preventing anything. The exceptions are pregnancy and before urological procedures.
Does vaginal oestrogen help recurrent cystitis?
In postmenopausal women, substantially. Falling oestrogen thins the tissue and removes the protective lactobacilli, and local oestrogen restores both. It is applied nightly for two weeks then twice weekly, with minimal absorption, and the effect builds over weeks to months.
Do cranberry or D-mannose work?
Cranberry is modest at best and depends on a proanthocyanidin content most juices lack. D-mannose has mixed results, with some positive trials and one large negative one. Both are low risk and neither should be the whole plan. Methenamine hippurate has stronger evidence than either.
Do I need scans if cystitis keeps coming back?
Usually not, in an otherwise healthy woman. Investigation is warranted for blood in the urine persisting after treatment, two or more kidney infections, unusual organisms, cystitis in a man, diabetes or a known urinary tract abnormality.
📑 Sources and editorial
- Urology and infectious diseases guidance on recurrent uncomplicated urinary tract infection in women
- The randomised trial of increased water intake for recurrent cystitis prevention
- The ALTAR randomised trial of methenamine hippurate compared with daily antibiotic prophylaxis
- Trials of vaginal oestrogen in postmenopausal recurrent urinary tract infection
- Prescribing information for nitrofurantoin, including the renal function threshold, pulmonary and neuropathic reactions and use at term in pregnancy
- Guidance on asymptomatic bacteriuria, including the exceptions for pregnancy and urological procedures
- Related reading: bladder spasms and urgency, urogenital trichomoniasis
- Related products: Macrobid (Nitrofurantoin), Bactrim (Sulfamethoxazole and Trimethoprim), Keflex (Cephalexin), antibiotics category
- RXshop Editorial Team — reviewed by Anita Sharma, MD, FACOG — Obstetrician-Gynecologist & Women's Health Specialist
Medical Disclaimer: The information in this article is for educational and informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always seek guidance from a qualified healthcare provider with any questions you may have regarding a medical condition, and before starting, stopping or changing any medication.