Sinusitis: When It Is Bacterial and When It Is Not

Sinusitis is one of the leading reasons antibiotics are prescribed and one of the leading reasons they are prescribed unnecessarily. The overwhelming majority of cases are viral, most bacterial cases also resolve without treatment, and the whole clinical task is identifying the minority who genuinely benefit.
That identification rests on a small number of specific patterns, one of which is far more useful than the sign most people rely on.
🧠 The misconception that drives most unnecessary prescribing: green or yellow nasal discharge does not indicate bacterial infection. The colour comes from an enzyme released by the white cells that arrive to fight any infection, including an ordinary viral cold, and it typically appears around day three to five of a normal cold regardless of cause. Purulent discharge alone is not a reason for an antibiotic, and the belief that it is accounts for an enormous number of prescriptions.
🔬 What is actually happening
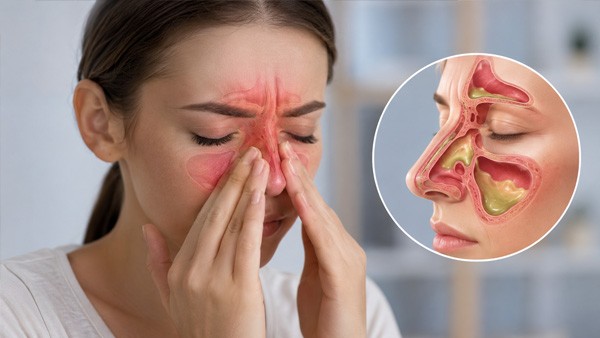
The sinuses are air-filled cavities in the bones of the face, lined with the same mucous membrane as the nose and connected to it through small openings. That lining produces mucus, and tiny hair-like cilia sweep it steadily toward the openings and out into the nose.
A viral infection inflames the lining. It swells, the openings narrow or close, drainage stops, and mucus accumulates in a closed space. That produces the pressure, pain and blockage of sinusitis. In a minority of cases bacteria multiply in the stagnant mucus and a secondary bacterial infection develops on top of the viral one.
Because the nose and sinuses are continuous and inflamed together, the condition is properly called rhinosinusitis — isolated sinus inflammation without nasal involvement essentially does not occur.
⚖️ Viral or bacterial
Three patterns indicate probable bacterial infection, and outside them antibiotics are not warranted.
| Pattern | What it means |
|---|---|
| Persistence | Symptoms lasting ten days or more without any improvement |
| Severity from the outset | High fever together with purulent discharge and facial pain for at least three to four consecutive days at the start of the illness |
| Double sickening | A typical cold that was improving, then worsening again after five or six days with new fever, new pain or increased discharge |
The third pattern is the most useful and the least well known. A viral cold follows a predictable arc — worst around days two to three, improving thereafter. Getting distinctly worse after starting to get better is a genuine signal, and it is worth reporting in those words rather than as a general description of feeling unwell.
By contrast, several things people rely on do not distinguish the two: the colour of mucus, the presence of facial pressure, a headache, or simply having had symptoms for a week. Viral sinusitis routinely produces all of them and lasts up to ten days.
🫠 Symptoms
The core features are nasal blockage or discharge, plus facial pain or pressure, or reduced sense of smell. Blockage or discharge must be present — facial pain alone is more often something else, most commonly a headache disorder.
Other features include a cough, worse when lying down as discharge drains backward; upper toothache, particularly with maxillary sinus involvement; pain worse on bending forward; ear fullness; bad breath; and fatigue.
Pain location follows which sinus is involved: cheeks and upper teeth for the maxillary sinuses, forehead for the frontal, behind and between the eyes for the ethmoid, and a deep central or occipital headache for the sphenoid.
⚠️ One-sided sinusitis with a foul smell or taste deserves a specific thought: a dental origin. Roughly one in ten cases of maxillary sinusitis arises from an infected upper tooth or a dental procedure, the roots of the upper molars sitting immediately below the sinus floor. It will not resolve with sinus treatment alone, and repeated antibiotic courses without a dental assessment are how these cases persist for months.
💉 What actually helps
Most of the useful treatment is not antibiotic, and this holds whether the cause is viral or bacterial.
| Treatment | Evidence and notes |
|---|---|
| Saline irrigation | Genuinely useful, cheap and safe. Rinsing with a saline solution clears mucus, improves drainage and reduces symptoms. Use previously boiled and cooled or distilled water, never straight from the tap |
| Intranasal corticosteroid | Reduces the lining swelling that blocks drainage, with reasonable evidence in acute sinusitis and strong evidence in chronic disease. Takes days to work fully |
| Analgesia | Anti-inflammatory painkillers work well for the pain and pressure, taken regularly rather than occasionally |
| Decongestant spray | Effective for a few days only — see the warning below |
| Steam inhalation and warm compresses | Comfort measures; evidence is limited but they are harmless |
| Adequate fluids and rest | Sensible; no specific evidence |
| Antihistamines | Not helpful unless allergy is contributing; they thicken secretions and may worsen drainage |
🔴 Decongestant nasal sprays must not be used beyond about three to five consecutive days. Beyond that they cause rebound congestion — the lining swells more each time the spray wears off, producing blockage worse than the original problem and driving continued use. This is a genuinely common trap, people remain on these sprays for months or years, and breaking the cycle requires a nasal steroid and an uncomfortable week or two.
💊 When an antibiotic is indicated
Where one of the three bacterial patterns is present, and particularly where symptoms are severe or the person has other health conditions, an antibiotic is reasonable.
Amoxicillin with clavulanate is the usual first choice in adults. The clavulanate component matters here specifically because Haemophilus influenzae and Moraxella catarrhalis, both common in sinusitis, frequently produce an enzyme that destroys plain amoxicillin. Amoxicillin alone remains reasonable in children and in settings with low resistance.
| Situation | Choice |
|---|---|
| Standard adult first-line | Amoxicillin with clavulanate |
| Children, or low-resistance settings | Amoxicillin |
| Non-severe penicillin allergy | A cephalosporin such as cefuroxime |
| Severe penicillin allergy | Doxycycline |
| Treatment failure after several days | Reassessment and a change of agent rather than a repeat of the same |
Two points worth stating. Macrolides such as azithromycin and clarithromycin are not preferred, because resistance in Streptococcus pneumoniae is substantial in many regions and their activity against Haemophilus influenzae is poor. And fluoroquinolones are specifically discouraged for uncomplicated sinusitis by regulators in several countries, because of serious adverse effects including tendon rupture, nerve damage and aortic problems, and should be reserved for situations where nothing else is suitable.
Improvement is expected within three to five days. No improvement by then means reassessment rather than persisting or automatically escalating.
🗓️ Watchful waiting
Even where bacterial infection is likely, guidelines in several countries permit observation for a period rather than immediate treatment, because a substantial proportion resolve without antibiotics.
This works with a safety net: adequate symptomatic treatment from the start, a clear plan for reassessment, and the ability to obtain an antibiotic quickly if things worsen. Many services use a delayed prescription — the person leaves with a prescription and instructions to fill it only if symptoms have not improved within a few days. That approach substantially reduces antibiotic use without increasing complications, and it works considerably better than simply being told no.
🔴 Complications
Serious complications of sinusitis are rare and are the reason it is not entirely ignored. The sinuses sit immediately adjacent to the eye sockets and the brain, separated by thin bone.
| Sign | Concern |
|---|---|
| Swelling or redness around the eye, eye pain, bulging eye | Orbital cellulitis — emergency |
| Double vision, reduced vision, restricted eye movement | Orbital involvement threatening sight — emergency |
| Severe headache, neck stiffness, photophobia, confusion or drowsiness | Intracranial spread or meningitis — emergency |
| Seizure or weakness on one side | Intracranial complication — emergency |
| Swelling over the forehead | Infection of the frontal bone — urgent |
| Very high fever with severe systemic illness | Urgent assessment |
Anything around the eye is the one to act on fastest. Periorbital swelling in a child with sinusitis is a same-hour assessment rather than a same-day one, because orbital cellulitis can threaten sight within a short period.
Separately, in anyone with poorly controlled diabetes or a suppressed immune system, aggressive sinus infection with black or dead-looking tissue inside the nose, facial numbness or rapidly progressive symptoms can indicate invasive fungal sinusitis, which is a surgical emergency with high mortality if delayed.
🔄 When it will not go away
Sinusitis lasting twelve weeks or more is a different condition — chronic rhinosinusitis — and treating it as a series of acute infections with repeated antibiotic courses is the commonest management error in this area.
It divides into two forms with different treatment: with nasal polyps, where blockage and complete loss of smell dominate; and without polyps, where facial pressure and discharge dominate.
The mainstays are quite different from acute treatment:
- Intranasal corticosteroids used long term, which are the core of treatment rather than an addition
- Regular saline irrigation, with better evidence here than in acute disease
- Treating contributing conditions — allergic rhinitis, asthma, reflux, immune deficiency
- Short courses of oral corticosteroid in polyp disease
- Surgery where medical treatment fails, opening the drainage pathways
- Biologic treatments for severe polyp disease, a substantial recent development
Antibiotics have a limited role in chronic rhinosinusitis, and repeated courses are a marker of the wrong diagnosis rather than of resistant infection.
⚠️ Nasal polyps plus asthma plus a reaction to aspirin or anti-inflammatory painkillers is a recognised combination that behaves differently and needs specialist input. Anyone with nasal polyps who has ever had wheezing or a severe reaction after taking aspirin or ibuprofen should mention it specifically, since it changes both what to avoid and what treatment is likely to work.
🖥️ Imaging, and when it is unhelpful
Plain X-rays of the sinuses are of little value and are no longer recommended, since they miss disease and produce misleading findings.
CT scanning shows the anatomy and the extent of disease well, and is used before surgery, where complications are suspected, and in chronic disease. It is not used to diagnose acute sinusitis, for a specific reason: CT scans performed on people with an ordinary viral cold routinely show sinus abnormalities. Scanning during an acute illness therefore produces findings that look impressive and mean nothing, and it drives treatment that is not needed.
Nasal endoscopy, performed by a specialist, is the useful examination in chronic disease.
🛡️ Reducing recurrence
Where sinusitis keeps returning, the contributing factors are worth addressing rather than treating each episode in isolation.
Allergic rhinitis is the commonest contributor, and treating it properly with a regular intranasal corticosteroid reduces sinusitis episodes.
Smoking impairs the cilia that clear mucus, and stopping improves clearance measurably.
Structural problems — a significantly deviated septum, narrowed drainage pathways — are worth assessing where episodes are frequent and one-sided.
Dental health, for the reasons above.
Reflux contributes in some people.
Immune deficiency should be considered where infections are frequent, severe or involve multiple sites, particularly in adults with no previous history.
Vaccination against influenza and pneumococcus reduces the respiratory infections that precede sinusitis.
Humidified air and saline rinsing during winter help those prone to it.
✅ A reasonable approach for someone with sinusitis right now: start saline irrigation and regular anti-inflammatory pain relief today, add an intranasal corticosteroid, use a decongestant spray for no more than three days if blockage is severe, and expect improvement over seven to ten days. Seek assessment if you are not improving by day ten, if you were improving and got distinctly worse again, or if severe symptoms with high fever have persisted three to four days from the start. Seek it immediately for anything involving the eye.
Antibiotics for confirmed bacterial sinusitis are stocked in the antibiotics category, with Augmentin (amoxicillin with clavulanate) the usual first-line choice in adults. Because most sinusitis does not require one, treatment should follow assessment against the patterns above rather than the colour of the discharge.
❓ Frequently asked questions
Does green mucus mean I need an antibiotic?
No, and this misconception accounts for an enormous number of unnecessary prescriptions. The colour comes from an enzyme released by white cells arriving to fight any infection, including an ordinary viral cold, and it typically appears around day three to five of a normal cold regardless of cause. Purulent discharge on its own is not a reason for an antibiotic.
How do I know if it is bacterial?
Three patterns indicate it. Symptoms lasting ten days or more without any improvement. Severe symptoms from the outset — high fever with purulent discharge and facial pain for three to four consecutive days. Or double sickening: a cold that was improving, then getting distinctly worse again after five or six days with new fever or new pain. That third pattern is the most useful and the least well known.
How long should sinusitis last?
Viral sinusitis routinely lasts up to ten days and follows a predictable arc, worst around days two to three and improving thereafter. Having symptoms for a week is not in itself a reason for an antibiotic. Lasting beyond ten days without any improvement is one of the patterns suggesting bacterial infection, and lasting twelve weeks or more makes it a different condition entirely.
What actually helps while I wait?
Saline irrigation, which is cheap, safe and genuinely useful for clearing mucus and improving drainage. An intranasal corticosteroid, which reduces the lining swelling that blocks drainage. And anti-inflammatory pain relief taken regularly rather than occasionally. A decongestant spray helps for a few days only. Antihistamines do not help unless allergy is contributing, and may thicken secretions.
Why can I not keep using the decongestant spray?
Because beyond about three to five days it causes rebound congestion — the lining swells more each time the spray wears off, producing blockage worse than the original problem and driving continued use. People remain trapped on these sprays for months or years. Breaking the cycle usually requires an intranasal corticosteroid and an uncomfortable week or two.
Which antibiotic is used?
Amoxicillin with clavulanate is the usual adult first choice, because the bacteria commonly involved frequently produce an enzyme that destroys plain amoxicillin. Amoxicillin alone remains reasonable in children. Doxycycline or a cephalosporin covers penicillin allergy. Macrolides are not preferred because of resistance, and fluoroquinolones are specifically discouraged for uncomplicated sinusitis because of serious adverse effects.
My sinusitis is on one side and smells bad. Does that mean anything?
It suggests a possible dental origin. Roughly one in ten cases of maxillary sinusitis arises from an infected upper tooth or a dental procedure, since the roots of the upper molars sit immediately below the sinus floor. It will not resolve with sinus treatment alone, and repeated antibiotic courses without a dental assessment are how such cases persist for months.
When is sinusitis an emergency?
Anything involving the eye, fastest of all — swelling or redness around it, eye pain, a bulging eye, double vision, reduced vision or restricted eye movement, since orbital cellulitis can threaten sight within a short period. Also severe headache with neck stiffness, photophobia, confusion or drowsiness, seizure or one-sided weakness, or swelling over the forehead.
Should I have a scan?
Not for acute sinusitis. Plain X-rays are of little value and are no longer recommended. CT scans performed on people with an ordinary viral cold routinely show sinus abnormalities, so scanning during an acute illness produces findings that look impressive, mean nothing, and drive unnecessary treatment. CT is used before surgery, where complications are suspected, and in chronic disease.
I keep getting sinusitis. What is going on?
Something is usually contributing. Allergic rhinitis is the commonest, and treating it properly with a regular intranasal corticosteroid reduces episodes. Smoking impairs the cilia that clear mucus. A significantly deviated septum or narrowed drainage pathways matter where episodes are frequent and one-sided. Dental problems, reflux and, occasionally, immune deficiency also contribute.
What if it has lasted months?
Twelve weeks or more makes it chronic rhinosinusitis, a different condition, and treating it as repeated acute infections with successive antibiotic courses is the commonest error here. Its mainstays are long-term intranasal corticosteroids, regular saline irrigation, treating contributing conditions such as allergy and asthma, and surgery where medical treatment fails. Antibiotics have a limited role.
Is it safe to rinse my nose with tap water?
Use previously boiled and cooled water, or distilled or sterile water, rather than straight from the tap. Tap water is safe to drink but can contain organisms that are harmless swallowed and are not harmless introduced into the nose. Rare but serious infections have followed rinsing with untreated tap water. The rinse device should also be cleaned and dried between uses.
📑 Sources and editorial
- IDSA clinical practice guideline for acute bacterial rhinosinusitis in children and adults
- American Academy of Otolaryngology clinical practice guideline on adult sinusitis
- EPOS European position paper on rhinosinusitis and nasal polyps
- NICE guidance on sinusitis and antimicrobial prescribing
- Cochrane reviews of antibiotics, intranasal corticosteroids and saline irrigation for sinusitis
- Regulatory advisories restricting fluoroquinolone use in uncomplicated infections
- Evidence on odontogenic maxillary sinusitis prevalence
- Related reading: allergies explained, azithromycin
- Related products: antibiotics category
- RXshop Editorial Team — reviewed by Emily Chen, MD, MPH, Internal Medicine
Medical Disclaimer: The information in this article is for educational and informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always seek guidance from a qualified healthcare provider with any questions you may have regarding a medical condition, and before starting, stopping or changing any medication.