Shingles: The 72-Hour Window and the Nerve Pain After


Shingles is unusual among common illnesses in that the outcome depends heavily on what happens in the first three days, and most people spend those three days deciding whether the pain is worth bothering anyone about. By the time the rash makes the diagnosis obvious, the window in which treatment does the most good is often closing.
The illness itself lasts two to four weeks. What matters far more is whether the pain stops when the rash does, and that is where the decisions taken early make a difference.
💡 Two things change the outcome, and neither is well known. First, antiviral treatment started within 72 hours of the rash appearing shortens the illness, reduces the pain and lowers the chance of pain persisting afterwards — started on day five it does considerably less. Second, the modern shingles vaccine prevents the great majority of cases in people over fifty and is the single most effective thing available, yet uptake remains low because most people do not know it exists.
🧬 Why a childhood illness returns fifty years later
Chickenpox and shingles are the same virus. When varicella zoster virus causes chickenpox, usually in childhood, the illness resolves but the virus does not leave. It travels along sensory nerves and settles permanently in the nerve cell clusters beside the spinal cord and at the base of the skull, where it remains dormant and invisible to the immune system.
It stays there because a specific arm of the immune system — cell-mediated immunity directed against this virus — keeps it suppressed. That surveillance is quietly maintained for decades and it weakens with age. From around fifty onward it declines steadily, and at some point in some people it falls below the level needed to hold the virus in check.
The virus then reactivates, travels back down the nerve it has been living in, and produces inflammation along its whole length. This explains everything characteristic about shingles: the rash follows the exact territory of one nerve, it stops abruptly at the midline because nerves supply one side only, and the pain begins before the rash because the nerve is inflamed before the virus reaches the skin.
Roughly one person in three who has had chickenpox develops shingles at some point.
👥 Who is at risk
| Factor | Why |
|---|---|
| Age over 50 | The dominant factor by a wide margin. Incidence rises steeply after fifty and again after seventy as immune surveillance declines |
| Immunosuppressive treatment | Corticosteroids, chemotherapy, biologics, JAK inhibitors and anti-rejection drugs after transplantation |
| Blood cancers | Lymphoma and leukaemia in particular, which affect the immune cells doing the suppressing |
| HIV | Substantially raised risk, and shingles in a younger adult with no other explanation is a recognised prompt to test |
| Autoimmune disease | Partly the condition, largely the treatment |
| Severe physical or emotional stress | A real association, though the effect is smaller than folk wisdom suggests |
| Recent illness or surgery | A period of temporarily reduced immune function |
Two points about that list. Most people who get shingles have no identifiable trigger beyond age, and looking for a cause frequently yields nothing. But shingles in someone under about forty with no obvious reason deserves a question about immune status, since it can be the first sign of something not yet diagnosed.
⏱️ The pain that arrives before the rash
For most people the first symptom is not a rash at all. Days before anything is visible, a band of pain, burning, tingling, itching or extreme skin sensitivity develops in one area on one side of the body. Light touch, clothing or bedsheets can be intensely uncomfortable.
Because there is nothing to see, this prodrome is regularly attributed to something else, and the misdiagnosis depends entirely on which nerve is involved.
| Where the pain is | What it gets mistaken for |
|---|---|
| Left chest | A heart attack or angina — and this is investigated properly, because it must be |
| Flank into the groin | Kidney stone |
| Right lower abdomen | Appendicitis or gallbladder disease |
| Lower back into the leg | Sciatica or a disc problem |
| Face or jaw | Toothache, sinusitis or trigeminal neuralgia |
| Around one eye | Migraine or acute glaucoma |
Alongside the pain there may be mild fever, headache, fatigue and a general sense of being unwell.
The practical lesson is that unexplained burning or shooting pain confined strictly to one side, in a band, in someone over fifty, should raise the possibility of shingles before the rash confirms it — because the antiviral clock starts when the rash appears, and knowing what to look for means starting on day one rather than day four.
🩹 What the rash does
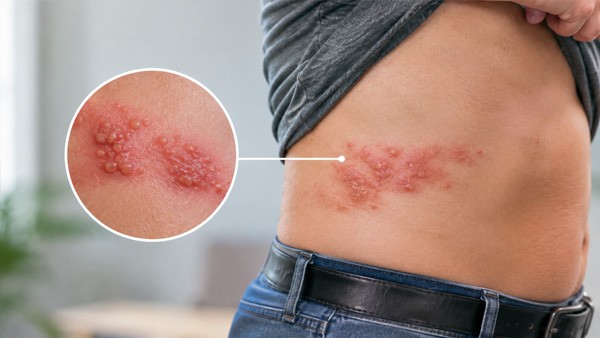
The rash appears as a band or patch on one side, following the territory of the affected nerve. The chest and back are the commonest sites, followed by the face around one eye.
It evolves in a predictable sequence: red patches first, then clusters of small fluid-filled blisters over a day or two, which cloud and become pustular around days three to four, then crust over by days seven to ten. Crusts separate over the following two to three weeks, sometimes leaving pigment change or scarring.
The identifying features are that it is strictly one-sided and does not cross the midline, and that it follows a nerve territory rather than spreading randomly. A rash on both sides is not ordinary shingles and needs a different explanation.
Pain typically accompanies the whole course and is often described as burning, stabbing or electric, punctuated by sudden shocks. Many people find the skin so sensitive that clothing is unbearable, which is a specific feature of nerve pain rather than an exaggeration.
💊 The 72-hour window
Antiviral treatment is the core of management and its value is strongly time-dependent.
Antivirals stop the virus replicating. Once it has finished replicating — which it largely has by the time the rash is fully out and crusting — there is much less for the drug to do. This is why guidelines specify starting within 72 hours of the rash appearing, and why the same prescription given on day six is far less useful.
| Drug | Typical adult regimen | Comment |
|---|---|---|
| Valacyclovir | 1000 mg three times daily, 7 days | Converted to acyclovir in the body with much better absorption, so three doses a day rather than five. The usual first choice |
| Famciclovir | 500 mg three times daily, 7 days | Comparable, also three times daily |
| Acyclovir | 800 mg five times daily, 7 days | Effective and awkward — five doses daily including overnight, which people miss |
The dosing difference is the reason valacyclovir has largely replaced plain acyclovir for this indication. A five-times-daily schedule sustained for a week is genuinely difficult, and doses missed at three in the morning are doses not taken.
What antivirals do: shorten the time to healing, reduce the severity and duration of acute pain, reduce the formation of new lesions, and modestly reduce the chance of pain persisting afterwards.
What they do not do: eliminate the virus, which returns to dormancy afterwards, or reliably prevent persistent nerve pain in someone destined to get it.
⚠️ Past 72 hours, it is still worth asking rather than assuming it is too late. Treatment is still recommended beyond the window where new blisters are still forming, where the eye or ear is involved, in anyone immunosuppressed, where the rash is severe or widespread, and in older adults. The 72-hour rule describes where the benefit is greatest, not a door that shuts.
Corticosteroids are sometimes added to the antiviral. They modestly reduce acute pain and speed healing in selected people. They do not reduce the risk of persistent nerve pain, despite a longstanding belief that they do, and they are not appropriate for everyone. That is a prescribing decision rather than something to arrange oneself.
🔥 Postherpetic neuralgia
This is the reason shingles is taken seriously. The rash heals; in some people the pain does not.
Postherpetic neuralgia is pain persisting beyond about three months from the onset of the rash, caused by lasting damage to the nerve. It can continue for months or years and it can be severe enough to disrupt sleep, appetite, mobility and mood profoundly. In older people it is a recognised cause of depression, social withdrawal and loss of independence.
Risk is tied closely to age. It is uncommon under fifty, becomes appreciable over sixty, and is substantially more likely over seventy.
| Predictor | Effect |
|---|---|
| Older age | The strongest predictor by far |
| Severe pain during the acute episode | Strongly associated with persistence |
| Severe pain before the rash appeared | An intense prodrome predicts a worse outcome |
| Extensive rash | More lesions, more nerve damage |
| Involvement around the eye | Higher risk than trunk involvement |
What treats it
Ordinary painkillers work poorly, because this is nerve pain rather than tissue pain and it responds to different drugs. Treatment is built up in steps and frequently combines more than one approach.
Gabapentin and pregabalin calm abnormal nerve signalling and are usually first line. Both require gradual dose increases over weeks, cause drowsiness and unsteadiness particularly at the start, and need dose reduction where kidney function is reduced. Abandoning them after three days because of dizziness is the commonest reason they fail.
Tricyclic antidepressants such as nortriptyline or amitriptyline work for nerve pain at doses far below those used for depression, and act through a different mechanism than their antidepressant effect. Nortriptyline is generally better tolerated in older people. They are worth persisting with for several weeks.
Topical lidocaine as a plaster applied over the painful area provides local relief without systemic effects, which makes it particularly useful in frail older people taking multiple other medicines.
High-concentration capsaicin applied as a single treatment under supervision can give relief lasting months. The application itself is uncomfortable and it is done in a clinical setting.
Opioids have a limited role and sit late in the sequence.
Combinations are common and often more effective than escalating one drug alone — a gabapentinoid with a topical agent, for instance.
🕓 Persistent nerve pain is treated best early. Established nerve pain becomes progressively harder to control the longer it runs, because the nervous system itself changes in response to sustained pain signalling. Pain still present a month after the rash has healed is worth raising then rather than at six months, and it is worth saying explicitly that the pain is not settling rather than assuming it is expected and will pass.
👁️ Shingles around the eye
When the affected nerve is the ophthalmic division of the trigeminal nerve, the rash appears on the forehead, upper eyelid and around one eye. This accounts for roughly one case in ten and it is the presentation that threatens sight.
The virus can involve the cornea, the inside of the eye and the optic nerve, and can raise pressure within the eye. Consequences range from corneal scarring to chronic inflammation to permanent visual loss, and the eye can be affected before the person notices any visual symptom.
🔴 Blisters on the tip or the side of the nose are the warning sign. The nerve branch supplying the tip of the nose also supplies structures inside the eye, so lesions there indicate that the branch reaching the eye is involved — a finding known as Hutchinson sign, and a strong predictor of eye involvement. Any shingles rash on the forehead, eyelid, around the eye or on the nose needs same-day medical assessment and an eye examination, whether or not vision seems affected. Redness of the eye, pain within the eye, light sensitivity or any change in vision makes it urgent regardless of where the rash is.
👂 Ramsay Hunt syndrome
When the virus reactivates in the nerve ganglion near the ear, it produces a distinctive combination: blisters in the ear canal, on the outer ear or on the roof of the mouth, together with weakness of the face on that side.
It is frequently mistaken for Bell palsy, which matters because it is treated differently and recovers less well. Alongside the facial weakness there may be ear pain, hearing loss, ringing in the ear, vertigo, and altered taste.
Recovery of facial movement is considerably better when antiviral treatment and corticosteroids are started early, so this is a situation where days count. New facial weakness with ear pain, or with any blisters in or around the ear, should be assessed the same day rather than watched.
🧠 Other complications worth knowing
Disseminated shingles occurs when the virus spreads beyond one or two nerve territories, producing widespread lesions and potentially affecting the lungs, liver or brain. It occurs almost exclusively in people with significantly weakened immunity and is treated in hospital with intravenous antiviral treatment.
Raised stroke risk. An association between shingles and an increased risk of stroke in the following weeks to months is well documented, and it is greater after shingles affecting the eye. The mechanism appears to involve inflammation of blood vessels. It is one more argument for prompt treatment and for vaccination.
Shingles without a rash. Occasionally the virus reactivates and causes typical band-like nerve pain that never produces visible lesions. It is difficult to diagnose and worth considering in unexplained one-sided nerve pain following a dermatome.
Motor involvement. Less commonly the virus affects nerves supplying muscle rather than sensation, producing weakness in the affected area — a weak arm, or a bulging abdominal wall where the muscle has lost its supply. Recovery is usual but slow.
💉 The vaccine, which is the main point
Everything above concerns managing an episode. The modern shingles vaccine largely prevents them from happening, and it is the most significant development in this condition in decades.
The current vaccine is a recombinant, non-live vaccine given as two doses a few months apart. Its efficacy in preventing shingles in adults over fifty is above ninety percent, unusually high for a vaccine in older adults, and protection is well sustained over years. It also substantially reduces the risk of persistent nerve pain, both by preventing episodes and by making those that do occur milder.
| Question | Answer |
|---|---|
| Who should have it | Adults from fifty onward, and from a younger age where immunity is weakened by disease or treatment |
| Can it be given after having shingles | Yes. A previous episode does not protect against future ones, and vaccination is recommended, usually after the episode has fully settled |
| Can it be given to immunosuppressed people | Yes — it contains no live virus, which is the key advantage over the older vaccine it replaced |
| What does it feel like | Reactogenic. A sore arm, tiredness, aching and sometimes fever for one to three days is common and expected, and is not an adverse reaction in the concerning sense |
| Does it treat existing nerve pain | No. It is prevention, not treatment |
The second row is the one most often misunderstood. Having had shingles confers no reliable protection against having it again, and people who have experienced it — particularly those who had persistent pain — are precisely the group with most to gain.
🤝 What is actually contagious
This is widely misunderstood and the correction is straightforward.
You cannot catch shingles from someone with shingles. Shingles arises from a virus already inside your own body, reactivating. There is no way to acquire it from outside.
You can catch chickenpox from someone with shingles, if you have never had chickenpox and are not vaccinated. The blister fluid contains live virus, and contact with it can cause chickenpox — not shingles — in a susceptible person.
Consequently:
- The rash is infectious only from when blisters appear until they have fully crusted over, usually seven to ten days
- There is no infectious risk during the prodrome, before any rash
- Ordinary shingles spreads by direct contact with blister fluid, not through the air, so keeping the rash covered largely removes the risk
- Anyone who has had chickenpox or been vaccinated is not at risk
- Avoid contact while the rash is active with pregnant women who have not had chickenpox, newborn infants, and anyone significantly immunosuppressed
- Disseminated shingles in an immunosuppressed person is a different situation and can spread through the air
🛁 Getting through the episode
Keep the rash clean, dry and loosely covered. A non-adherent dressing protects the area, prevents contact spread, and stops clothing rubbing on skin that is often exquisitely sensitive.
Cool compresses soothe more reliably than anything warm.
Loose cotton clothing. When skin sensitivity is at its peak, what touches it matters considerably.
Do not burst blisters, which delays healing, risks bacterial infection and increases scarring.
Treat pain properly and early. Undertreated acute pain is itself a predictor of pain persisting, so this is not stoicism worth practising. If ordinary painkillers are not controlling it, that is worth reporting rather than enduring.
Rest. Shingles is more systemically tiring than the visible rash suggests, and fatigue often outlasts it.
Calamine or a cooling lotion helps the itch during the crusting phase.
🩺 When to seek care urgently
- Any rash on the face, forehead, eyelid, around the eye or on the nose — same day, with an eye examination
- Eye pain, redness, light sensitivity or any change in vision
- Facial weakness, ear pain, hearing change or vertigo — possible Ramsay Hunt syndrome, same day
- Rash appearing within 72 hours — contact a prescriber promptly, since the antiviral window is open
- Widespread rash, or lesions well beyond one band
- Anyone immunosuppressed, at any stage, without waiting
- Severe pain not controlled by ordinary painkillers
- Confusion, severe headache, neck stiffness or weakness
- Pain still present a month after the rash healed — treat it early rather than waiting
- Shingles in someone under forty with no explanation
Treatment is stocked in the antiviral category, including Valtrex (valacyclovir 1000 mg) as the usual first choice, Famvir (famciclovir) as an equivalent alternative, and Zovirax (acyclovir). Nerve pain afterwards is treated with agents from the anticonvulsant category rather than with antivirals.
❓ Frequently asked questions
Why does treatment have to start within 72 hours?
Because antivirals stop the virus replicating, and by the time the rash is fully out and crusting the replication is largely finished, leaving much less for the drug to do. Started within 72 hours of the rash appearing they shorten healing, reduce pain and modestly lower the risk of persistent nerve pain. The same prescription on day six achieves considerably less.
I am past 72 hours. Is there any point?
Often yes, so it is worth asking rather than assuming the chance has gone. Treatment is still recommended where new blisters are still forming, where the eye or the ear is involved, in anyone immunosuppressed, where the rash is severe or widespread, and in older adults. The 72-hour figure marks where benefit is greatest rather than a cut-off.
Can I catch shingles from someone who has it?
No. Shingles comes from a virus already dormant inside your own body reactivating, so there is no way to acquire it from outside. You can catch chickenpox from someone with shingles if you have never had it and are not vaccinated, through direct contact with blister fluid. The rash is infectious only from when blisters appear until they have fully crusted.
Who should I stay away from while I have it?
Pregnant women who have not had chickenpox, newborn infants, and anyone significantly immunosuppressed, until the rash has fully crusted over. Anyone who has had chickenpox or been vaccinated is not at risk. Ordinary shingles spreads by direct contact with blister fluid rather than through the air, so keeping the rash covered removes most of the risk.
Why did I have pain for days before the rash?
Because the virus inflames the nerve before it reaches the skin. That prodrome is regularly mistaken for something else depending on which nerve is involved — a heart attack in the left chest, a kidney stone in the flank, appendicitis in the right lower abdomen, sciatica in the leg, toothache in the jaw. Unexplained burning pain strictly on one side, in a band, is worth taking as a possible warning.
Why is valacyclovir preferred over acyclovir?
Convenience, which translates into effectiveness. Valacyclovir converts to acyclovir in the body but is absorbed far better, so it works at three doses a day rather than five. A five-times-daily schedule sustained for a week, including overnight doses, is genuinely hard to keep, and missed doses are missed treatment. Famciclovir offers the same advantage.
The rash healed but the pain has not. What is happening?
Postherpetic neuralgia — pain persisting beyond about three months, caused by lasting damage to the nerve. It is uncommon under fifty, appreciable over sixty and substantially more likely over seventy, and it is likelier after severe acute pain, an intense prodrome, an extensive rash, or involvement around the eye. It needs specific treatment, and treating it early works better than treating it late.
Why do ordinary painkillers not help the lingering pain?
Because it is nerve pain rather than tissue pain, and it responds to different drugs. Gabapentin and pregabalin calm abnormal nerve signalling and are usually first line, needing gradual dose increases over weeks. Tricyclic antidepressants work for nerve pain at doses well below those used for depression. Topical lidocaine and high-concentration capsaicin help locally, and combinations often outperform escalating a single drug.
There are blisters on my nose. Does that matter?
Considerably. The nerve branch supplying the tip of the nose also supplies structures inside the eye, so lesions there signal that the branch reaching the eye is involved. Any shingles rash on the forehead, eyelid, around the eye or on the nose needs same-day assessment including an eye examination, whether or not vision seems affected, because the eye can be involved before you notice anything.
My face has gone weak and my ear hurts. Is that shingles?
Possibly Ramsay Hunt syndrome, where the virus reactivates in a nerve ganglion near the ear, producing blisters in or around the ear or on the roof of the mouth alongside facial weakness, and sometimes hearing loss, ringing or vertigo. It is often mistaken for Bell palsy, which matters because it is treated differently and recovers less well. Recovery is much better with early antiviral treatment and steroids, so it needs same-day assessment.
Can I be vaccinated if I have already had shingles?
Yes, and you probably should be. A previous episode gives no reliable protection against future ones, and people who have had it — particularly anyone who had lingering nerve pain — are the group with most to gain. Vaccination is usually given once the episode has fully settled. The current vaccine contains no live virus, so it can also be given to people whose immunity is weakened.
Can shingles happen more than once?
Yes. The virus returns to dormancy after an episode rather than being eliminated, so it can reactivate again. Recurrence is not common but it is far from rare, and it is more likely in anyone whose immunity is compromised. This is precisely why having had shingles is a reason to be vaccinated rather than a reason to assume it is finished.
📑 Sources and editorial
- CDC clinical guidance on herpes zoster and on recombinant zoster vaccination
- IDSA and specialty society guidance on the management of herpes zoster
- Pivotal trials of the recombinant zoster vaccine in adults over fifty and over seventy
- Randomised trials of valacyclovir, famciclovir and acyclovir in acute herpes zoster
- Cochrane reviews of antivirals and of corticosteroids for preventing postherpetic neuralgia
- Neuropathic pain guidance on gabapentinoids, tricyclic antidepressants, topical lidocaine and capsaicin
- Ophthalmology literature on herpes zoster ophthalmicus and Hutchinson sign
- Studies of facial nerve outcome in Ramsay Hunt syndrome with early antiviral and corticosteroid treatment
- Epidemiological studies of stroke risk following herpes zoster
- FDA prescribing information for valacyclovir, famciclovir and acyclovir
- Related reading: genital herpes
- Related products: antiviral category
- RXshop Editorial Team — reviewed by Emily Chen, MD, MPH, Internal Medicine
Medical Disclaimer: The information in this article is for educational and informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always seek guidance from a qualified healthcare provider with any questions you may have regarding a medical condition, and before starting, stopping or changing any medication.