Ankylosing Spondylitis: Causes, Early Symptoms, Diagnosis, Life Span and Treatment From NSAIDs to Biologics

🦴 Ankylosing spondylitis usually starts quietly: a dull ache low in the back or deep in the buttocks, stiffness that is worst at dawn, and pain that wakes a young adult in the second half of the night. Because it looks like ordinary back pain, many people wait years before anyone names it. 🔍 This guide explains what causes ankylosing spondylitis, how to tell inflammatory back pain from the mechanical kind, which tests confirm it, what the disease means for life span and daily life, and how treatment works step by step, from exercise and NSAIDs such as indomethacin to biologic medicines when tablets are not enough.
🦴 What ankylosing spondylitis is
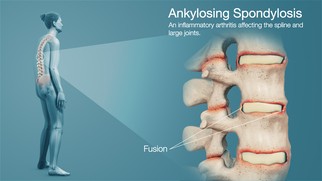
🔥 Ankylosing spondylitis (AS) is a long-term inflammatory disease of the spine and of the sacroiliac joints, where the spine meets the pelvis. Doctors now see it as one end of a wider group called axial spondyloarthritis. When damage already shows on a plain X-ray, it is called radiographic axial spondyloarthritis, the classic AS. When inflammation is visible only on MRI, or not yet visible at all, it is called non-radiographic axial spondyloarthritis. Both forms cause the same pain and respond to the same treatment.
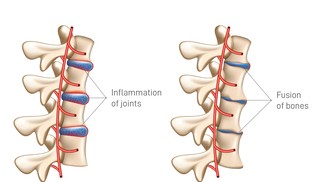
🧩 The inflammation starts where ligaments and tendons attach to bone, a place called the enthesis. Over years, the body tries to repair these spots by laying down new bone. In some people the new bone bridges the vertebrae, and parts of the spine slowly fuse. The word ankylosing means stiffening or fusing, and spondylitis means inflammation of the vertebrae. Fusion is not inevitable: many people never reach it, and modern treatment aims to slow it.
🧬 What causes it: HLA-B27 and beyond
🧪 The exact cause is still not known, but genes carry most of the risk. The strongest link is a gene variant called HLA-B27, part of the system the immune cells use to show pieces of proteins to each other. Most people with AS of European origin carry it, yet only a small minority of HLA-B27 carriers ever develop the disease.
🦠 Something in the environment seems to switch the process on. The gut is the leading suspect. Many people with AS have small patches of gut inflammation without any symptoms, and AS is much more common in people with Crohn disease or ulcerative colitis.
👥 Who gets it and when
📅 AS typically begins in the late teens, twenties or early thirties. A new back pain that starts after 45 is rarely ankylosing spondylitis. Men are diagnosed with the X-ray visible form about two to three times more often than women, while the MRI-only form affects both sexes about equally.
⚖️ Inflammatory or mechanical back pain?
🔎 Most back pain is mechanical: strained muscles, worn discs or joints. It gets worse with use and better with rest. Inflammatory back pain behaves the opposite way, and noticing that difference is the single most useful step towards a diagnosis.
| 🔎 Feature | 🔥 Inflammatory (AS) | 🔧 Mechanical |
|---|---|---|
| Age at start | Usually under 40 to 45 | Any age, more common later |
| How it starts | Slowly, over weeks or months | Often sudden, after lifting or twisting |
| Morning stiffness | Over 30 minutes, often an hour or more | Short, under 30 minutes |
| Exercise | Makes it better | Often makes it worse |
| Rest | Does not help, may worsen it | Helps |
| Night | Wakes you in the second half of the night | Less typical |
| Response to NSAIDs | Often clear relief within 1 to 2 days | Partial relief |
📖 If your pain fits the mechanical column better, the practical plan in back pain reset is a better starting point. If it fits the left column and has lasted three months or more, ask for a referral to a rheumatologist.
📝 Early symptoms checklist
👁️ Beyond the spine: eyes, gut, skin and heart
🌐 AS is a whole-body inflammatory disease. About one in three people with AS has at least one attack of anterior uveitis, an inflammation inside the front of the eye.
📖 If the gut is involved, the choice of AS medicine changes, because some drugs help both conditions and others can upset the bowel. Background on bowel inflammation treatment is in mesalamine in Crohn disease and ulcerative colitis.
📈 How the disease changes over the years
🕰️ The course of AS varies widely. Some people have mild, intermittent flares for life; others develop steady stiffness and fusion. Early, active inflammation on MRI, raised CRP, smoking and existing bony bridges predict faster progression.
Buttock and low back pain, morning stiffness, normal X-ray
Sacroiliac changes on X-ray, flares, heel or eye attacks
Bony bridges in the lumbar spine, less bending
In some people a rigid spine, forward posture, fracture risk
🧭 How the diagnosis is made
🩺 No single test proves AS. A rheumatologist puts the picture together from the story of the pain, the examination, blood tests and imaging. The usual path looks like this.
🧪 The tests explained
| 🧪 Test | ✅ What it shows | ⚠️ Limits |
|---|---|---|
| HLA-B27 | Raises the probability of AS a lot when back pain is inflammatory | Common in healthy people; negative in a minority of patients |
| CRP and ESR | Active inflammation; high CRP predicts faster damage and good response to biologics | Normal in many patients with real disease |
| Pelvic X-ray | Erosions, widening or fusion of sacroiliac joints | Changes can take years to appear |
| MRI of sacroiliac joints | Bone marrow swelling from active inflammation, early erosions | Mild changes also appear after childbirth, in athletes and in heavy workers |
| Spine X-ray | Bony bridges, squared vertebrae, the late bamboo spine picture | Used for monitoring, not early diagnosis |
📊 Doctors also use short questionnaires such as BASDAI, which scores fatigue, spinal pain, joint pain, tender spots and morning stiffness from 0 to 10. A BASDAI of 4 or more despite treatment usually means the disease is active and the plan should be stepped up.
⏳ Why diagnosis takes so long
🤔 The average wait between the first symptoms and a diagnosis is still several years. The main reasons are that back pain is common, young people are not expected to have arthritis, and early X-rays look normal.
❤️ Ankylosing spondylitis and life span
📉 One of the most searched questions about AS is how long people live with it. Most people with ankylosing spondylitis live a normal or nearly normal life span. Large population studies find a modestly higher death rate on average compared with people without AS, but that average is pulled up by a smaller group with long-standing, severe, poorly controlled disease. The extra risk comes from a few specific causes, and most of them can be reduced.
🫀 The biggest one is heart and blood vessel disease. Years of inflammation speed up hardening of the arteries, much as in rheumatoid arthritis. Other contributors are spinal fractures after minor falls in a fused spine, lung problems from a stiff chest, kidney damage, and complications of long-term high-dose painkillers.
📋 What raises or lowers long-term risk
🎯 The goals of treatment
🛠️ There is no cure yet, but treatment changes a lot. The aim is to calm inflammation, keep the spine moving, prevent new damage and keep you working and active. Every plan rests on two pillars that work together: movement and medicine. Neither works as well alone.
💊 NSAIDs: the first-line medicine
💡 Non-steroidal anti-inflammatory drugs are the first medicine for axial spondyloarthritis. They reduce pain and stiffness in most patients, often within two or three days, and a strong response is itself a clue that the pain is inflammatory. No single NSAID has been shown to be better than the others for AS; the choice depends on your stomach, heart, kidneys and how well you tolerate each one. Guidelines suggest trying at least two different NSAIDs at full dose, over a total of about four weeks, before deciding they are not enough.
💊 Indomethacin in ankylosing spondylitis
📜 Indomethacin was one of the first NSAIDs used for AS and is still listed for it. Many patients with severe morning stiffness find it works well, especially as a dose taken in the evening to cover the night and early morning. Its drawback is a higher rate of central nervous system side effects than most NSAIDs: headache, dizziness and light-headedness, which usually show in the first days. For that reason, doctors often start low and raise the dose slowly.
📋 How it is usually taken by adults
💊 25 mg two or three times a day, with food, to start
📈 Raised step by step if needed, usually not above 150 to 200 mg a day in divided doses
🌙 Extended-release 75 mg once or twice a day, often in the evening
⚠️ Side effects to expect
🤕 Headache, dizziness: common at the start
😢 Indigestion, nausea: take with food
🩸 Stomach bleeding: black stools are urgent
💧 Fluid retention, higher blood pressure
😴 Drowsiness: care when driving at first
📌 Indomethacin is not a good choice for older adults, people with a history of depression or confusion, or anyone with kidney problems. If headaches are troublesome, switching to another NSAID is reasonable; the benefit for the spine is similar across the group.
🔄 Daily or only on bad days?
❓ This is a common question, and the answer depends on how active the disease is. When symptoms are present most days, regular full-dose NSAID use controls pain and stiffness better than taking tablets only when it hurts. Some studies suggest daily use may slow new bone formation in people with high CRP, but the evidence is mixed, so the decision balances symptom control against the side-effect risks of years of use.
🛡️ NSAID safety: stomach, heart and kidneys
🧪 Long-term NSAID use is safe for many people with AS, as long as the risks are checked before starting and reviewed over time. The three organs to watch are the stomach, the heart and blood vessels, and the kidneys.
| 🚫 Risk | 📝 What it means | 🛡️ How it is reduced |
|---|---|---|
| Stomach ulcer and bleeding | Higher with age over 65, past ulcer, steroids, blood thinners | Take with food; add a PPI such as omeprazole; prefer celecoxib or etoricoxib |
| Heart attack and stroke | Small rise, higher with diclofenac and high doses | Control blood pressure and lipids; naproxen often preferred |
| Raised blood pressure | Fluid retention, weaker effect of blood pressure pills | Check blood pressure after starting |
| Kidney strain | Higher with dehydration, diuretics, ACE inhibitors | Blood test for creatinine once or twice a year |
| Asthma worsening | A minority of people with asthma react to NSAIDs | Tell the doctor about any past reaction to aspirin |
📖 The trade-offs between COX-2 tablets and older NSAIDs are discussed in detail in celecoxib: stomach, heart and kidney trade-offs. If an ulcer has already happened, see H. pylori treatment for a duodenal ulcer.
⛔ Who should not take indomethacin
💉 When NSAIDs are not enough: biologics and JAK inhibitors
🔬 If the disease stays active after two NSAIDs, or NSAIDs cannot be used safely, the next step is a targeted medicine given by a rheumatologist. These work on the immune signals that drive AS and can bring many patients to low disease activity. They are not sold for self-treatment; they need screening for tuberculosis and hepatitis and regular follow-up.
Adalimumab, etanercept, infliximab, golimumab, certolizumab. The longest experience; antibody forms also help uveitis and bowel disease.
Secukinumab, ixekizumab, bimekizumab. Good for spine and psoriasis; less suitable with active bowel inflammation.
Tofacitinib, upadacitinib. Tablets; used with care in older smokers and people with heart or clot risks.
📌 Methotrexate and leflunomide, so useful in rheumatoid arthritis, do not help spinal disease in AS. The differences between these conditions are explained in psoriatic arthritis vs rheumatoid arthritis and the first DMARDs.
💊 Where sulfasalazine and steroids fit
🧷 Some people with AS also have swollen knees, ankles or other limb joints. Sulfasalazine can help this peripheral arthritis, but it does not improve back pain or stiffness in the spine. It is usually started at 500 mg a day and raised over several weeks to 2 to 3 g a day, with blood counts and liver tests in the first months. Azulfidine (Sulfasalazine) is the usual brand.
💉 Steroid tablets are not a long-term treatment for AS: they help the spine little and cause bone loss. Steroids work best locally: an injection into a single inflamed joint or around a tendon (but never into the Achilles tendon itself), and steroid eye drops for uveitis under an eye doctor.
🏊 Exercise and physiotherapy: treatment, not an extra
🏃 In AS, movement is medicine in the literal sense. Daily exercise eases stiffness, keeps the spine and hips moving, protects posture and breathing, and lowers heart risk.
🏠 Daily life: sleep, work, smoking and diet
🛏️ Small habits shape how AS feels day to day. The one change with the clearest benefit is stopping smoking, which is linked to faster spinal damage, worse function and a weaker response to biologics.
🗿 Myths and facts
🚨 When to see a doctor
⛔ Get urgent help the same day if:
🔹 You have neck or back pain after even a minor fall and a stiff or fused spine. Fractures are easy to miss and can damage the spinal cord; ask for a CT scan.
🔹 One eye becomes painful, red and sensitive to light, with blurred vision. Uveitis needs an eye doctor within 24 hours.
🔹 You have black or bloody stools, vomit blood or have severe stomach pain while taking an NSAID.
🔹 Back pain comes with fever, weight loss, numbness in the groin, or bladder or bowel changes.
🔹 You get chest pain, breathlessness or swelling of the legs.
❓ Frequently asked questions
What is the life span of a person with ankylosing spondylitis?
Most people with ankylosing spondylitis live a normal or nearly normal life span. The extra risk is mainly from heart disease and spinal fractures, and it falls with exercise, no smoking and good control of inflammation.
What causes ankylosing spondylitis?
The exact cause is unknown. Genes, above all HLA-B27, carry most of the risk, and an immune trigger, possibly from the gut, seems to start the inflammation.
What are the first signs of ankylosing spondylitis?
Low back or buttock pain starting before 45, lasting over three months, with long morning stiffness, night pain in the early hours and improvement with exercise.
Can you have ankylosing spondylitis without HLA-B27?
Yes. A minority of patients are HLA-B27 negative. The diagnosis is based on symptoms, examination, CRP and imaging together.
Which test confirms ankylosing spondylitis?
No single test. A pelvic X-ray or an MRI of the sacroiliac joints showing sacroiliitis, combined with typical symptoms, is the usual basis for diagnosis.
Is indomethacin good for ankylosing spondylitis?
Yes, it is an effective NSAID for AS, often taken in the evening for morning stiffness. It causes headache and dizziness more often than other NSAIDs, so some patients switch.
What is the usual indomethacin dose for AS?
Adults usually start with 25 mg two or three times a day with food, raised if needed, usually not above 150 to 200 mg a day, as agreed with a doctor.
When are biologics needed for ankylosing spondylitis?
When the disease stays active after at least two NSAIDs at full dose over about four weeks, or when NSAIDs cannot be used safely. A rheumatologist chooses a TNF, IL-17 or JAK inhibitor.
Can exercise slow ankylosing spondylitis?
Daily exercise keeps the spine and hips moving, eases stiffness and protects posture and breathing. It works best together with medicine that controls inflammation.
Is a red painful eye linked to ankylosing spondylitis?
It can be anterior uveitis, which affects about one in three people with AS at some point. It needs an eye doctor within 24 hours.
📑 Sources and editorial
- 📘 International recommendations for the management of axial spondyloarthritis
- 🧪 Classification criteria for axial spondyloarthritis and reviews of HLA-B27 testing
- 💊 Prescribing information for indomethacin and other NSAIDs
- 🔬 Systematic reviews of NSAIDs, TNF inhibitors, IL-17 inhibitors and JAK inhibitors in axial disease
- ❤️ Population studies of mortality and cardiovascular risk in ankylosing spondylitis
- 🏊 Trials of supervised exercise and physiotherapy in ankylosing spondylitis
- 📖 Related reading: back pain reset, psoriatic arthritis vs rheumatoid arthritis, celecoxib trade-offs, mesalamine in Crohn disease and colitis, H. pylori and duodenal ulcer
- 🛒 Related products: Indocin (Indomethacin), Naprosyn (Naproxen), Celebrex (Celecoxib), Arcoxia (Etoricoxib), Voltaren (Diclofenac), Mobic (Meloxicam), Azulfidine (Sulfasalazine)
- 🩺 RXshop Editorial Team — reviewed by Emily Chen, MD — Internal medicine
Medical Disclaimer: The information in this article is for educational and informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always seek guidance from a qualified healthcare provider with any questions you may have regarding a medical condition, and before starting, stopping or changing any medication.