Degenerative Disc Disease and Spinal Osteochondrosis: Restoring Mobility and Breaking the Pain Cycle


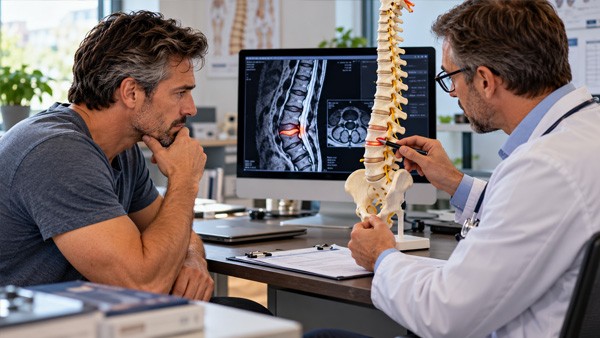
A note on the name first, because it causes real confusion. In Russian and Eastern European medicine, osteochondrosis of the spine describes age-related wear of the intervertebral discs and the joints around them. In English-language medicine the same condition is called degenerative disc disease or spondylosis, while the word osteochondrosis is reserved for a separate group of childhood growth-plate disorders. This article is about the first meaning: the discs, the joints and the back pain that comes with them.
The discs sit between the vertebrae and work as shock absorbers. Each has a tough fibrous outer ring and a gel-like water-rich centre. With age the centre loses water, the disc flattens, and load shifts onto the small facet joints behind. The body responds with bone spurs, the ligaments thicken, and the space available for nerves narrows.
All of that is normal ageing. The difficult part, and the part most articles get wrong, is that it correlates poorly with whether a person is in pain.
🖼️ What a scan does and does not tell you
Imaging studies of people with no back pain at all find degenerative changes at almost every age.
| Age | Disc degeneration on MRI in people without pain |
|---|---|
| 20 years | Around 37 percent |
| 40 years | Around 68 percent |
| 60 years | Around 88 percent |
| 80 years | Around 96 percent |
🧠 Why this matters more than any treatment in this article. Disc bulges, degeneration and mild spurs are ordinary findings, like grey hair on an x-ray. Reading a report full of alarming words and concluding that the spine is crumbling makes pain worse, drives avoidance of movement, and predicts a poorer outcome. Scans are useful for ruling out serious causes and for planning surgery. For ordinary back pain, guidelines advise against imaging in the first six weeks precisely because of this effect.
📍 The three regions and how each presents
| Region | Typical symptoms | Worth knowing |
|---|---|---|
| Cervical, neck | Neck pain and stiffness, headache from the base of the skull, pain or tingling down an arm | Dizziness is often blamed on the neck; in most cases the cause is the inner ear instead |
| Thoracic, mid-back | Stiffness between the shoulder blades, discomfort after long sitting | Least common, because the ribs limit movement. New thoracic pain deserves more attention than lumbar pain |
| Lumbar, lower back | Low back pain, stiffness after sitting or in the morning, pain down the leg | By far the most common; this region carries the load |
The distinction that changes treatment is between mechanical back pain, felt in the back and buttock and varying with position, and radicular pain, which travels below the knee in a narrow band and often comes with numbness or weakness. The second means a nerve root is compressed or irritated, most often by a disc herniation.
🚨 The symptoms that cannot wait
🚑 Cauda equina syndrome is a surgical emergency. A large disc herniation can compress the bundle of nerves at the base of the spinal cord. The warning signs are numbness in the saddle area between the legs, difficulty passing urine or loss of bladder or bowel control, weakness in both legs, and new sexual dysfunction alongside back pain. This needs emergency assessment the same day, not an appointment next week. Surgery performed early preserves function that is otherwise lost permanently.
Other features that call for assessment rather than self-management:
- Back pain with fever, or in someone using intravenous drugs or immunosuppressed
- Unexplained weight loss, or a history of cancer
- Pain after significant trauma, or minor trauma in someone with osteoporosis or on long-term steroids
- Progressive leg weakness, such as a foot that catches when walking
- Constant pain unrelieved by any position, worse at night
- First episode of significant back pain before 20 or after 55
🗓️ What actually happens over the first six weeks
Acute back pain has a good natural history. Most people improve substantially within four to six weeks, and most disc herniations shrink on their own: the body reabsorbs the extruded material over months, often with the largest herniations resolving most completely.
What the first weeks call for:
- Stay active
- This is the single strongest recommendation in every modern guideline, and it reverses the advice given a generation ago. Bed rest beyond a day or two delays recovery and increases stiffness. Ordinary activity, modified to tolerance, is treatment.
- Keep working if you can
- Adjusted duties beat full absence. The longer someone is off work with back pain, the lower the chance of returning at all.
- Use heat early
- Superficial heat has modest evidence for acute pain. Ice suits the first day or two after a clear injury.
- Take pain relief so you can move
- The purpose of medication here is to make activity possible, not to remove pain while lying still.
- Expect flare-ups
- Recurrence is normal and does not mean deterioration. Most people have episodes for years without their spine getting structurally worse.
💊 Medication, in the order it is actually used
🔹 First: anti-inflammatories
NSAIDs are first-line for mechanical back pain, taken at an adequate dose for a short period with food. Options here include Naprosyn (Naproxen), Voltaren (Diclofenac) and Mobic (Meloxicam), with Emulgel (Diclofenac 1%) as a topical option for localised pain. Paracetamol alone performs poorly in back pain trials, which surprises people, but it remains useful in combination or where NSAIDs cannot be used.
🔹 Second: muscle relaxants, briefly
When protective muscle spasm is a clear part of the picture, a short course of a muscle relaxant added to an NSAID improves pain and movement in the first two weeks.
| Medicine | Dose | Notes |
|---|---|---|
| Zanaflex (Tizanidine 2 mg) | 2 mg up to three times daily, increased cautiously; maximum 36 mg daily | Alpha-2 agonist. Causes drowsiness and can lower blood pressure; liver enzymes are checked with longer use |
| Robaxin (Methocarbamol 500 mg) | 1500 mg four times daily for the first 48 to 72 hours, then reduced | Not a controlled substance; less sedating than most alternatives |
| Baclof (Baclofen) | 5 mg three times daily, increased gradually | Mainly for spasticity from neurological disease; never stopped abruptly after long use |
⚠️ Two cautions with tizanidine. It must not be combined with ciprofloxacin or fluvoxamine, which block the enzyme that clears it and can raise levels enough to cause dangerous drops in blood pressure. And it is a short-course medicine: two to three weeks. Sedation, dizziness and dry mouth limit longer use, and the evidence for benefit beyond the acute phase is thin. Do not drive until you know how it affects you.
🔹 Third: nerve pain treatment, with honest expectations
For radicular pain running down the leg, Neurontin (Gabapentin) and Cymbalta (Duloxetine) are the usual options, and Elavil (Amitriptyline) at low doses at night helps some people with chronic pain and disturbed sleep. Gabapentin needs slow upward titration over weeks and is not judged on the first few doses.
Worth saying plainly: the evidence for these in sciatica is modest. They help some people meaningfully and do nothing for others, and they are not a substitute for the exercise and time that do most of the work.
🔹 Where injections fit
Epidural steroid injection can give useful short-term relief of severe radicular pain, buying weeks of function while natural recovery proceeds. It does not change the long-term outcome and does not prevent surgery. Facet joint injections have weaker evidence.
🏋️ Exercise: what the evidence supports
Exercise is the only intervention that reliably reduces recurrence of back pain. The trials are clear on one further point that saves a lot of arguing: no single type of exercise is superior. Core stability work, general strengthening, walking, yoga, Pilates and hydrotherapy all produce similar results. The best programme is the one that gets done consistently.
- 🚶 Walking — the most accessible starting point, and enough on its own for many people
- 💪 Trunk and hip strengthening — the muscles that control the pelvis matter as much as the abdominal ones
- 🧘 Mobility work — useful for the stiffness, less so for the pain
- 🏊 Water-based exercise — suits people whose pain limits weight-bearing
- 🧑🏫 Supervised at first — a physiotherapist-led start improves adherence, which is the variable that decides results
Posture and ergonomics help symptoms but have been oversold as causes. Sitting position, mattress firmness and a perfectly aligned workstation matter far less than how much a person moves during the day. Changing position regularly beats finding the perfect one.
❌ Treatments that do not earn their place
- 🛏️ Prolonged bed rest — actively harmful beyond a day or two
- 🔗 Traction — repeatedly tested, no meaningful benefit
- 🧥 Rigid corsets for ordinary back pain — weaken the muscles that need to work
- 💡 Passive treatments alone — ultrasound, shortwave and similar modalities do little without active exercise
- 💰 Claims to reverse degeneration or rebuild discs — no supplement, device or manual technique does this
Manual therapy and massage are a partial exception: they give short-term relief and are reasonable alongside exercise, but not as the whole treatment.
🩺 When surgery is considered
Surgery is for a minority. The clear indications are cauda equina syndrome, which is an emergency, and progressive neurological weakness. Beyond that, discectomy is considered for severe radicular pain that has not settled after six to twelve weeks of proper conservative treatment, and decompression for spinal stenosis where walking distance is severely limited.
Trials comparing early surgery with conservative care for sciatica find that surgery relieves leg pain faster, while results at one and two years converge. That makes it a decision about how long someone can tolerate the pain rather than about the eventual outcome. Surgery for back pain alone, without leg symptoms, has much weaker support.
❓ Frequently asked questions
My MRI shows disc degeneration. Is my spine damaged?
Not in the way the report sounds. Disc degeneration appears on scans of people with no pain at all in roughly 37 percent of twenty-year-olds and nearly everyone over 70. The findings describe normal ageing, and they correlate poorly with whether someone hurts.
Should I rest or keep moving with back pain?
Keep moving. Bed rest beyond a day or two delays recovery and increases stiffness. Staying active within tolerance, and staying at work with adjusted duties where possible, is the strongest recommendation in current guidelines.
Which symptoms mean I should go to hospital immediately?
Numbness in the saddle area between the legs, difficulty passing urine or loss of bladder or bowel control, weakness in both legs, or new sexual dysfunction with back pain. These suggest cauda equina syndrome and need emergency assessment the same day.
How long does a disc herniation take to heal?
Most improve substantially within six to twelve weeks. The body reabsorbs the extruded disc material over months, and the largest herniations often resolve the most completely.
What is the dose of tizanidine for muscle spasm?
Usually 2 mg up to three times daily, increased cautiously, with a maximum of 36 mg in 24 hours. It is a short-course medicine, generally two to three weeks, because of drowsiness and its effect on blood pressure.
Can I take tizanidine with an antibiotic?
Not with ciprofloxacin, and not with fluvoxamine. Both block the enzyme that clears tizanidine and can raise its level enough to cause a dangerous drop in blood pressure. Tell the prescriber you are taking it.
Which exercise is best for back pain?
The one you will keep doing. Trials find core stability work, general strengthening, walking, yoga and Pilates produce similar results, so adherence matters more than the method. Exercise is the only intervention that reliably reduces recurrence.
Is my dizziness coming from my neck?
Usually not. Dizziness is often attributed to cervical degeneration, but in most cases the cause turns out to be the inner ear, blood pressure or medication. It is worth investigating properly rather than assuming the neck.
Do I need surgery for sciatica?
Most people do not. It is considered for severe leg pain that has not settled after six to twelve weeks of proper conservative treatment, or for progressive weakness. Surgery relieves leg pain faster, but results at one and two years are similar either way.
Can disc degeneration be reversed?
No supplement, device or manual technique rebuilds a disc. What can change is pain and function, through exercise, strength and time, and most people improve considerably without any structural change on imaging.
📑 Sources and editorial
- Clinical guidelines on the assessment and management of low back pain and sciatica
- Systematic reviews of imaging findings in asymptomatic populations by age
- Trials of NSAIDs, muscle relaxants, gabapentin and duloxetine in back and radicular pain
- Prescribing information for tizanidine, methocarbamol and baclofen, including the CYP1A2 interactions
- Studies of spontaneous resorption of lumbar disc herniation, and trials comparing early surgery with conservative care for sciatica
- Related products: Zanaflex (Tizanidine), Robaxin (Methocarbamol), Naprosyn (Naproxen), Neurontin (Gabapentin), muscle relaxers category
- RXshop Editorial Team — reviewed by Daniel Kim, MD, Endocrinology
Medical Disclaimer: The information in this article is for educational and informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always seek guidance from a qualified healthcare provider with any questions you may have regarding a medical condition, and before starting, stopping or changing any medication.