Central Neuropathic Pain: Why Ordinary Painkillers Fail and What Works Instead


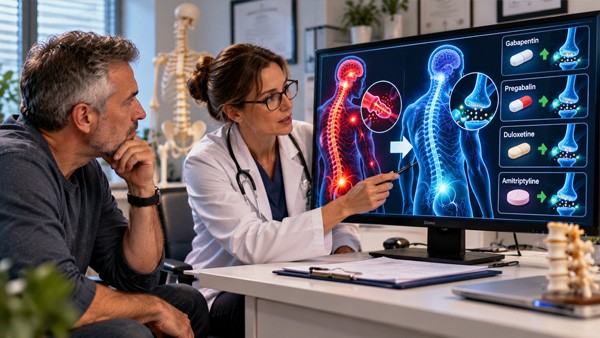
Most pain is a message about tissue. Something is damaged, nerve endings report it, and the pain stops when the tissue heals. Neuropathic pain is different: the messaging system itself is damaged or malfunctioning, so it generates and amplifies signals with nothing to report.
Central neuropathic pain is the version where the fault lies inside the brain or spinal cord, after a stroke, in multiple sclerosis, after spinal cord injury, or from a tumour or trauma. The original lesion may be years old and completely stable while the pain continues, because the pain is no longer about the lesion.
🚫 This is why ordinary painkillers do not work, and it is not a matter of dose. Ibuprofen, diclofenac, naproxen and aspirin work by suppressing inflammation. In neuropathic pain there is no inflammation to suppress, so they have no meaningful effect at any dose. Paracetamol performs little better. People with nerve pain often escalate through stronger and stronger anti-inflammatories, accumulating stomach and kidney risk for nothing, because nobody told them the mechanism is wrong.
The drugs that do work are the ones that calm excitable nerve membranes and strengthen the brain pathways that dampen pain — which is why they come from the anticonvulsant and antidepressant shelves rather than the analgesic one. Being prescribed an antidepressant for pain is not a comment on your mental state.
🧩 Three kinds of chronic pain, three different treatments
Getting this category right is the single biggest determinant of whether treatment works.
| Type | What is wrong | Examples | What helps |
|---|---|---|---|
| Nociceptive | Tissue damage, inflammation | Arthritis, injury, post-surgical | Anti-inflammatories, paracetamol, physical treatment |
| Neuropathic, peripheral | Damage to nerves outside the brain and cord | Diabetic neuropathy, postherpetic neuralgia, sciatica | Gabapentinoids, tricyclics, duloxetine, topical agents |
| Neuropathic, central | Damage inside the brain or spinal cord | Post-stroke pain, multiple sclerosis, spinal cord injury | The same classes, generally with smaller effect and slower response |
| Nociplastic | Altered pain processing without identifiable damage | Fibromyalgia, some chronic widespread pain | Exercise, psychological therapy, duloxetine, amitriptyline; opioids clearly harmful |
🗣️ How to recognise it from the description
Neuropathic pain has a vocabulary of its own, and the words people choose are diagnostic.
- 🔥 Burning, as if sunburnt under the skin
- ⚡ Electric shocks or stabbing bursts lasting seconds
- 🧊 Cold pain, a distinctly unpleasant icy ache, characteristic of post-stroke pain
- 🪡 Pins and needles, crawling or itching alongside the pain
- 🧣 Allodynia — ordinary touch hurting. A shirt, a bedsheet, a breeze, a shower. This is the most specific feature of all
- 📍 Numbness in the same area that hurts, which sounds contradictory and is typical
The distribution follows the nervous system rather than the anatomy of a joint or muscle: one side of the body after a stroke, a level and below after spinal cord injury, a patchy pattern in multiple sclerosis.
🔄 Why it continues after the injury stops changing
The mechanism is central sensitisation: the spinal cord and brain amplify incoming signals and lose the ability to turn the volume back down.
- Inhibition weakens. The braking circuits that normally suppress background activity are damaged
- Neurons become hyperexcitable, firing to stimuli that previously produced nothing
- Descending control fails. The pathways from the brain that dampen incoming pain underperform
- Wiring shifts. Touch-carrying fibres begin feeding into pain pathways, which is literally what allodynia is
This explains the fluctuation that patients find maddening and clinicians sometimes misread: sensitisation is not fixed. Sleep loss measurably lowers pain thresholds, and so do stress and illness, which is why the same activity is tolerable one day and not the next. It is mechanical rather than psychological.
📊 What a successful outcome actually looks like
🎯 Set the target honestly, because the wrong target makes good treatment look like failure. In neuropathic pain, a 30 to 50 percent reduction in pain intensity is the accepted definition of a meaningful response. Complete relief is uncommon.
The numbers behind it: for the best-evidenced drugs, roughly one person in four to one in eight gets that level of benefit compared with placebo. That means several drugs may be tried before one works, and it is a property of the condition rather than of the prescriber or the patient. Alongside the pain score, the outcomes that matter are sleeping through the night, fewer unpredictable spikes, and doing more.
💊 The drugs that work, with doses
Treatment is by sequential monotherapy: one drug titrated to an adequate dose, given a fair trial, and swapped if it fails, rather than layering several at low doses.
🔹 Gabapentinoids
Neurontin (Gabapentin) and the generic Gabatop (Gabapentin) bind a subunit of calcium channels on overexcited nerve endings and reduce the release of excitatory transmitters.
- 📈 Start 300 mg at night, or 100 mg in older or frail patients. Increase to 300 mg twice daily after three days, then three times daily, then upward in 300 mg steps
- 🎯 Effective range is 1800 to 3600 mg daily in three divided doses. Most treatment failures are doses that never reached this range
- ⏳ Allow four to eight weeks at an adequate dose before judging it
- 🩸 Dose is reduced in kidney impairment, substantially so
- 📉 Never stopped abruptly — tapered over at least a week, longer after prolonged use, to avoid anxiety, sweating, insomnia and rebound pain
- 💤 Side effects: drowsiness and dizziness early, which usually settle; ankle swelling, weight gain, and unsteadiness in older patients where falls become the limiting factor
⚠️ Two warnings that arrived after these drugs became routine. Gabapentinoids can cause serious respiratory depression when combined with opioids or other sedatives, and in people with reduced respiratory reserve such as COPD, the elderly and those with kidney impairment. They also carry genuine misuse and dependence potential, more so with pregabalin, which is why both are controlled drugs in a number of countries. Neither is a reason to avoid them; both are reasons not to add them casually on top of an opioid.
🔹 Tricyclics
Elavil (Amitriptyline) strengthens the descending pathways that dampen pain, using noradrenaline and serotonin. It is among the most effective drugs for neuropathic pain and it works at doses far below antidepressant doses.
- 🌙 10 to 25 mg two to three hours before bed, increased in 10 to 25 mg steps to 75 mg as tolerated
- 😴 Taken early in the evening rather than at bedtime, so the sedation has passed by morning. Morning grogginess is usually a timing problem rather than a dose problem
- 💧 Anticholinergic effects: dry mouth, constipation, blurred vision, urinary hesitancy. Avoided in narrow-angle glaucoma and where there is prostatic obstruction
- ❤️ Cardiac caution over 65 or with heart disease; an ECG before starting is usual in those groups
- 🔄 Pamelor (Nortriptyline) is the better-tolerated alternative, with less sedation and fewer anticholinergic effects at similar benefit
🔹 Duloxetine
Cymbalta (Duloxetine) works on the same descending pathways with a cleaner side-effect profile. 30 mg daily for a week, then 60 mg. Nausea in the first week is common and transient, and it is taken with food. It is not stopped abruptly, because discontinuation symptoms are pronounced.
🔹 Carbamazepine, for one specific diagnosis
Tegretol (Carbamazepine) is not a general neuropathic pain drug. It is first-line specifically for trigeminal neuralgia, the condition of brief excruciating electric shocks in the face triggered by touch, chewing or cold air, where its effect is dramatic and close to diagnostic.
- 📈 100 mg twice daily, increased gradually to effect, commonly 600 to 1200 mg daily
- 🧬 HLA-B*1502 testing before starting in people of Han Chinese, Thai or other Southeast Asian ancestry, because that variant carries a high risk of severe skin reactions
- 🩸 Monitoring of sodium, full blood count and liver enzymes; hyponatraemia is common, particularly in older patients
- ⚡ It is a strong enzyme inducer: it reduces the effectiveness of hormonal contraception, and alters levels of warfarin and many other drugs. Any new medicine needs checking against it
Lamictal (Lamotrigine) has some evidence in central post-stroke pain. Its titration is deliberately very slow, because rapid increases carry a risk of severe skin reactions, and any rash means stopping and seeking advice the same day.
🔹 Topical and local options
For pain confined to a defined patch of skin with allodynia, a lidocaine 5 percent plaster worn 12 hours on and 12 off acts locally with essentially no systemic effect, which makes it valuable in older patients on several medicines. High-concentration capsaicin patches are applied in a clinic. Neither is currently in our catalogue.
❌ What to avoid
- 💊 NSAIDs and paracetamol — no meaningful effect on neuropathic pain, with real gastric, kidney and cardiovascular cost
- 🚫 Opioids as a long-term strategy — modest short-term benefit at best in neuropathic pain, tolerance within months, and opioid-induced hyperalgesia, in which the drug itself increases pain sensitivity. In nociplastic pain such as fibromyalgia they are clearly harmful
- 🏃 Boom and bust activity — doing everything on a good day reliably produces a spike the next, and it is the commonest self-inflicted pattern
- 🛏️ Prolonged rest — deconditioning raises sensitivity and lowers tolerance
- 🔄 Changing several things at once — a new drug, a new supplement, a new exercise programme and a new diet in the same fortnight makes the result uninterpretable
- 📱 Chasing a cure online — sensitised systems respond to stability, and constant plan changes are the opposite of stability
🧘 The non-drug half, which is not optional
For sensitised pain, these are not complements to the medication. They act on the same mechanism.
- Sleep, first
- Experimental sleep restriction lowers pain thresholds in healthy people within days. Fixing sleep is the highest-yield intervention available, and it is also why a sedating tricyclic taken in the evening often outperforms a theoretically stronger drug.
- Graded movement
- Starting below the level that provokes a flare and increasing by a small fixed amount weekly, regardless of how good a given day feels. The point is predictability, which is what a sensitised system needs.
- Pain neuroscience education
- Understanding that the pain reflects an amplified signal rather than ongoing damage measurably reduces pain and disability in trials. It works because fear of damage drives protective behaviour that worsens sensitisation.
- Cognitive behavioural therapy and acceptance-based approaches
- Among the better-evidenced treatments for chronic pain, and they are not an implication that the pain is imagined.
- Desensitisation for allodynia
- Graded exposure of the sensitive area to textures, starting with what is tolerable, supervised by a physiotherapist or occupational therapist.
- Mirror therapy and graded motor imagery
- Useful in post-stroke and phantom limb pain, where the body map itself is disturbed.
Where all of this has been tried properly, spinal cord stimulation and other neuromodulation techniques are options through a specialist pain service, with better results in some central pain syndromes than in others.
🚨 When a flare needs assessment rather than management
- Any new neurological sign — new weakness, facial droop, speech or vision change, loss of coordination, numbness in a new area
- Loss of bladder or bowel control, or saddle numbness — emergency
- Fever with worsening pain, particularly after spinal surgery or with an implanted device
- Pain that has changed character or location, rather than intensified
- Rapidly progressive weakness or spasticity
- Confusion, severe drowsiness or falls after a medication change
- A rash on lamotrigine or carbamazepine — stop and seek advice the same day
- Thoughts of self-harm — chronic pain substantially raises this risk, and it is a reason to seek help promptly rather than to wait
❓ Frequently asked questions
Why do painkillers not work on my nerve pain?
Because anti-inflammatories work by suppressing inflammation, and in neuropathic pain there is none to suppress. Ibuprofen, diclofenac and naproxen have no meaningful effect at any dose, and paracetamol little more. The drugs that work calm excitable nerves instead.
Why have I been given an antidepressant for pain?
Because amitriptyline, nortriptyline and duloxetine strengthen the brain pathways that dampen incoming pain, and they do it at doses well below antidepressant doses. It is a comment on the mechanism of your pain, not on your mental state.
What counts as a good result?
A 30 to 50 percent reduction in pain intensity is the accepted definition of a meaningful response, along with better sleep and fewer unpredictable spikes. Complete relief is uncommon, and several drugs may need trying before one works.
What is the dose of gabapentin for nerve pain?
Starting at 300 mg at night and increasing gradually to an effective range of 1800 to 3600 mg daily in three divided doses. Most apparent failures are doses that never reached that range, and it needs four to eight weeks at an adequate dose before judging.
Can I stop gabapentin suddenly?
No. It is tapered over at least a week, and longer after prolonged use, to avoid anxiety, sweating, insomnia and rebound pain. The same applies to duloxetine.
Why does light touch hurt?
That is allodynia, and it happens because touch-carrying nerve fibres begin feeding into pain pathways after the nervous system is sensitised. It is the most specific sign of neuropathic pain, and graded desensitisation with textures helps alongside medication.
Why is the pain worse some days than others?
Sensitisation fluctuates. Sleep loss measurably lowers pain thresholds within days, and stress and illness do the same. This is a mechanical effect on the nervous system rather than a psychological one, which is why protecting sleep is the highest-yield thing you can do.
Are opioids an option?
A poor one. Benefit in neuropathic pain is modest at best, tolerance develops within months, and opioids can cause hyperalgesia, in which the drug itself raises pain sensitivity. In fibromyalgia-type pain they are clearly harmful.
Is carbamazepine used for all nerve pain?
No. It is first-line specifically for trigeminal neuralgia, where brief electric shocks in the face are triggered by touch, chewing or cold air, and its effect there is dramatic. For other neuropathic pain it is not a first choice.
Does exercise help or make it worse?
Graded movement helps, provided it starts below the level that provokes a flare and increases by a small fixed amount each week regardless of how good a day feels. Doing everything on a good day reliably produces a spike the next, and that pattern is the commonest self-inflicted setback.
📑 Sources and editorial
- Neuropathic pain guidelines and the grading system for definite, probable and possible neuropathic pain
- Systematic reviews and meta-analyses of gabapentinoids, tricyclic antidepressants, duloxetine and topical agents, including numbers needed to treat
- Prescribing information for gabapentin, amitriptyline, nortriptyline, duloxetine, carbamazepine and lamotrigine, including renal dosing, HLA-B*1502 testing and titration requirements
- Regulatory safety communications on gabapentinoid respiratory depression and misuse potential
- Experimental studies of sleep restriction on pain thresholds, and trials of pain neuroscience education and graded activity
- Reviews of opioid-induced hyperalgesia and of opioid outcomes in neuropathic and nociplastic pain
- Related reading: shingles and postherpetic neuralgia, fibromyalgia
- Related products: Neurontin (Gabapentin), Elavil (Amitriptyline), Cymbalta (Duloxetine), Tegretol (Carbamazepine), anticonvulsants category
- RXshop Editorial Team — reviewed by James Carter, MD — Neurologist & Sleep Medicine Specialist
Medical Disclaimer: The information in this article is for educational and informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always seek guidance from a qualified healthcare provider with any questions you may have regarding a medical condition, and before starting, stopping or changing any medication.