Warfarin or a Newer Blood Thinner: Who Should Stay on Warfarin, How to Switch Safely and Plan Around Surgery

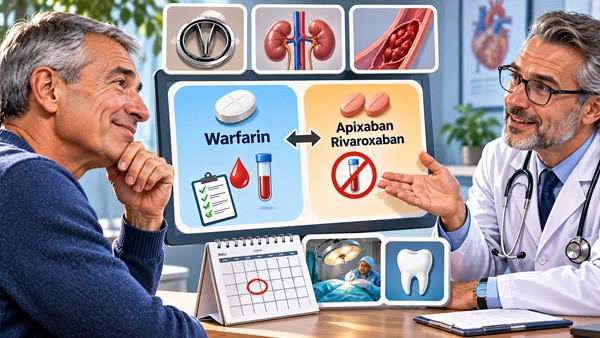

🩸 For more than sixty years warfarin was the only tablet that could thin the blood for the long term. Then apixaban, rivaroxaban, dabigatran and edoxaban arrived, needing no routine blood tests and no attention to greens on the plate, and many people on warfarin started to wonder why they were still taking it. The honest answer is that for most people a newer drug is a reasonable choice, but for some groups warfarin is still the safer or the only correct option. 🔍 This guide explains how the two kinds of blood thinner differ, who should stay on warfarin, how a switch in either direction is done safely, what to do with a missed dose, and how surgery, dental work and emergencies are handled on each drug.
🤔 Why this question comes up so often
💬 People on warfarin hear about the newer drugs from friends, from television and from other patients in the clinic waiting room. The comparison sounds simple: one drug needs blood tests and diet care, the others do not. In practice the choice depends on why you take a blood thinner, how well your kidneys work, which other medicines you use, your weight, your budget and how stable your INR has been. 📖 If you are staying on warfarin and want the day-to-day rules for food, alcohol and INR testing, see warfarin and your INR: diet, interactions and bleeding signs. This article is about the choice itself and about the moments when the drug has to be stopped, changed or restarted.
🧬 Two different ways to slow clotting
🧪 Warfarin works indirectly. It blocks the recycling of vitamin K in the liver, so the liver makes fewer working clotting factors (II, VII, IX and X). Because the factors already in the blood have to wear out first, warfarin takes several days to reach full effect and several days to wear off. The newer drugs, often called DOACs (direct oral anticoagulants), block one clotting protein directly: dabigatran blocks thrombin, while apixaban, rivaroxaban and edoxaban block factor Xa. They start working within a few hours and fade within a day or two.
📏 This difference in speed explains most of the practical rules later in this guide: why warfarin is started with an injection after a new clot, why a missed warfarin dose is less dangerous than a missed DOAC dose, and why warfarin has to be stopped earlier before an operation.
💊 The newer blood thinners at a glance
📋 Each of these drugs has its own dose rules for age, weight and kidney function, so they are not interchangeable milligram for milligram. Warfarin is different again: there is no fixed dose at all, only the dose that gets your INR into range, which can be anything from about 1 mg to well over 10 mg a day. RXshop stocks warfarin as Coumadin (Warfarin); a doctor decides the daily dose from your INR results.
⚖️ Warfarin and DOACs side by side
| 🔎 Feature | 💊 Warfarin | 🆕 DOACs |
|---|---|---|
| Onset | 3 to 5 days or longer | A few hours |
| Wears off | Several days | 1 to 2 days with normal kidneys |
| Routine blood tests | Regular INR checks | Kidney and blood count checks, usually once or twice a year |
| Diet | Keep vitamin K intake steady | No special diet |
| Drug interactions | Many | Fewer, but some are serious |
| Bleeding into the brain | Higher | Roughly half the rate in trials |
| Kidney failure | Usable | Limited or not suitable, depending on the drug |
| Antidote | Vitamin K and clotting factor concentrate | Specific antidotes exist, availability varies |
| Cost | Low | Higher, though generics are spreading |
✅ Where the newer drugs come out ahead
📊 In the large trials in atrial fibrillation, each DOAC prevented stroke at least as well as warfarin. The clearest advantage was a lower rate of bleeding inside the skull, the most feared complication of any blood thinner. They also free people from frequent INR checks and from keeping a close eye on greens, cranberry juice and short courses of antibiotics.
📌 Some DOACs at some doses caused more stomach and bowel bleeding than warfarin, so a history of ulcers or bowel bleeding is part of the discussion. Apixaban had the most favourable bleeding results in its main trial, which is one reason it is often chosen for older people.
🛡️ Where warfarin still wins
🧭 Warfarin is old, but it is not obsolete. There are several situations where guidelines still prefer it, and a few where the newer drugs are clearly wrong. The list below is the one cardiologists check before agreeing to a switch.
⚙️ Mechanical heart valves: no substitute
🫀 A mechanical valve is made of carbon and metal, and blood clots form on it easily. When dabigatran was tested in people with mechanical valves, the trial was stopped early because of more clots and more bleeding than with warfarin. Since then, all DOACs are considered unsuitable for mechanical valves. Warfarin remains the standard, usually with a target INR of 2.0 to 3.0 for many modern aortic valves and 2.5 to 3.5 for mitral valves or higher-risk patients. Your valve team sets the exact target, and it should be written on your anticoagulant record.
🧭 If you have a mechanical valve:
🔹 Never accept a switch to a DOAC from a doctor who may not know about the valve. Mention it every time.
🔹 Carry a card or phone note stating the valve type and your INR target.
🔹 Tissue (biological) valves are different: some people with them can use a DOAC, especially when they also have atrial fibrillation.
🫀 Mitral stenosis and rheumatic heart disease
🌍 Rheumatic fever in childhood can scar the mitral valve years later, narrowing it (mitral stenosis). In this group the left upper chamber swells, atrial fibrillation is common and the clot risk is very high. A large trial in rheumatic heart disease found warfarin worked better than rivaroxaban for preventing stroke and death, so warfarin stays the first choice for moderate or severe mitral stenosis with atrial fibrillation. Milder valve leaks and narrowing of other valves do not carry the same restriction, and a DOAC is often acceptable there.
🧬 Antiphospholipid syndrome
🔬 Antiphospholipid syndrome is an autoimmune condition in which antibodies make the blood clot too readily, in veins, arteries or the placenta. In people who test positive for all three antibody types, rivaroxaban was linked with more arterial clots, including strokes, than warfarin. Current advice is to use warfarin for high-risk antiphospholipid syndrome and for anyone with a history of arterial clots in this condition. If you were started on a DOAC after a clot and later found to have these antibodies, ask whether your treatment should be reviewed.
🧮 Kidneys, weight and age
🫘 Every DOAC is partly cleared by the kidneys, so blood tests for kidney function guide both the choice and the dose. Warfarin is cleared by the liver, which is why it remains usable when the kidneys fail. Body weight and age matter as well, because they change how much drug ends up in the blood.
| 🔎 Factor | 📋 What it changes | 💡 Usual approach |
|---|---|---|
| Reduced kidney function | DOAC levels rise, more bleeding | Dose reduction by label; dabigatran avoided when kidney function is low |
| Dialysis | Most DOACs not studied | Warfarin, or apixaban where local guidance allows |
| Very low body weight | Higher drug levels | Dose adjustment for some DOACs, more careful monitoring |
| Very high body weight | Less data at the extremes | Apixaban or rivaroxaban often acceptable for clots; warfarin if doubt |
| Age over 80 | More falls, kidneys slower | Not a reason to stop; dose and kidney checks reviewed more often |
| Liver disease | Both drug types affected | Specialist decision; advanced cirrhosis limits all options |
👴 Older age on its own is a reason to protect against stroke, not a reason to avoid a blood thinner. Even people who fall now and then usually gain more from stroke prevention than they lose from bleeding risk, a point covered in atrial fibrillation: why stroke prevention comes first.
⚠️ Medicines that decide the choice
📋 Warfarin interacts with a long list of medicines, mostly through the liver enzymes that break it down. The DOACs have fewer interactions, but the ones they have are harder to monitor, because there is no routine blood test to show that the level has changed.
| 💊 Medicine | 🧪 Effect on warfarin | 🆕 Effect on DOACs |
|---|---|---|
| Amiodarone | INR rises, often needs a lower dose | Levels rise modestly; usually manageable |
| Rifampicin, carbamazepine, phenytoin, St John wort | INR falls, dose increased with checks | Levels fall sharply; usually avoided together |
| Some antifungals and HIV medicines | INR rises | Levels rise; some combinations avoided |
| Metronidazole, co-trimoxazole, some quinolones | INR can rise quickly | Little direct effect |
| Ibuprofen, naproxen, other NSAIDs | More bleeding | More bleeding |
| SSRI antidepressants | Slightly more bleeding | Slightly more bleeding |
📌 Paracetamol is the usual painkiller for people on any blood thinner, although regular high doses can push the INR up on warfarin. Always tell a pharmacist which anticoagulant you take before buying anything for pain, colds or sleep.
💓 Rate and rhythm medicines alongside a blood thinner
📈 Most people on long-term anticoagulation for atrial fibrillation also take a medicine to control the heart rate. The common rate drugs can be combined with warfarin or a DOAC, with a few points worth knowing.
💡 Rate control eases palpitations and breathlessness, but it does nothing to prevent the clot that causes a stroke. Feeling better on a rate drug is never a reason to stop the anticoagulant.
🩹 Blood thinner plus an antiplatelet: when two drugs are needed
🧷 Anticoagulants act on the clotting proteins; antiplatelet drugs act on platelets, the cells that plug a damaged artery. Using both together raises the bleeding risk considerably, so it is done only for clear reasons and usually for a limited time. The commonest example is a person with atrial fibrillation who has a coronary stent, covered in after a heart attack or stent: the first year and the medicines.
📅 After a stent, many cardiologists now use an anticoagulant with clopidogrel for up to a year and then the anticoagulant alone. Aspirin is often dropped early in this setting to reduce bleeding. Never add aspirin on your own “for extra protection” while on warfarin or a DOAC.
🤰 Pregnancy and breastfeeding
🚫 Neither warfarin nor the DOACs are suitable in pregnancy for most women. Warfarin can harm the baby, especially between about weeks 6 and 12, and DOACs cross the placenta with too little safety data. Women who need anticoagulation in pregnancy usually take injections of low molecular weight heparin. Women with mechanical valves are the difficult exception and need a specialist plan before conception. After birth the picture changes: warfarin is considered compatible with breastfeeding, while DOACs are generally avoided until more data exist. Anyone on a blood thinner who could become pregnant should discuss contraception and plans in advance.
💵 Cost, access and practical life
🏠 Warfarin is one of the cheapest medicines in cardiology. For people who pay out of pocket, the price gap can be the deciding factor, and a well-managed warfarin course is still good treatment. Practical points also count: some people like the reassurance of a number, some live far from a testing clinic, and some can test at home with a finger-prick INR meter. Twice-daily DOACs suit people who reliably take morning and evening medicines; once-daily options suit those who do not.
Low price, long experience, measurable effect, usable in kidney failure
Regular INR checks, many interactions, slow on and off
Simpler routine, but missed doses matter more and no easy level check
🧭 A simple decision path
🔁 Switching from warfarin to a newer drug
🧪 The aim of any switch is to avoid both a gap without protection and a period with double effect. Because warfarin fades slowly, the newer drug is started only when the INR has fallen enough, and the exact threshold depends on the drug and on the product label used in your country.
↩️ Switching back to warfarin
🔄 People move back to warfarin when kidney function falls, when a new interacting medicine is needed, when a mechanical valve is fitted, or when cost becomes a problem. This direction is trickier, because warfarin needs days to work while the DOAC wears off in hours. The usual answer is an overlap: warfarin is started while the DOAC continues (or an injection is used in its place for some drugs), and the INR is checked until it is in range on two readings, then the DOAC is stopped. The INR is measured just before a DOAC dose, since some DOACs raise the INR reading themselves. Your clinic or prescriber should give you a written day-by-day plan.
⏰ Missed doses: why the rules differ
💡 Warfarin has a long-lasting effect, so a single missed tablet causes only a small dip in protection. DOACs leave the body within a day, so a missed dose means a real gap. The rules below are the general ones; your patient leaflet has the exact wording for your drug.
📱 A weekly pill box, a phone alarm and keeping the pack next to something you do daily solve most missed doses. If you often forget, that is a reason to discuss the choice of drug, because steady protection matters more than which tablet it comes from.
🏥 Surgery: stopping and restarting
🩺 Before a planned operation, the surgeon, anaesthetist and the doctor who prescribes your blood thinner agree on a plan. Warfarin usually needs to stop about 5 days before major surgery; most DOACs need only 1 to 2 days, longer if the kidneys are weak or the operation carries a high bleeding risk. The timeline below shows a common pattern for warfarin.
💉 Bridging injections: who really needs them
📉 “Bridging” means covering the days off warfarin with injections of low molecular weight heparin. It was once routine. A large trial in atrial fibrillation showed that bridging did not reduce strokes but did increase bleeding, so most people with atrial fibrillation now simply pause warfarin without injections. Bridging is kept for those at the highest clot risk: a mechanical mitral valve, an older-type mechanical valve, a clot or stroke within the last three months, or a severe clotting disorder. If you are told you need bridging, it is reasonable to ask which of these reasons applies to you.
🦷 Dental work and minor procedures
🦷 Most dental treatment does not require stopping a blood thinner at all. Stopping for a simple extraction often carries more risk of a clot than the extra bleeding it prevents, and dentists control oozing with stitches, packing and tranexamic acid mouthwash.
🔬 Endoscopy is in between: a simple look with a camera rarely needs a pause, while removing a polyp may. The team doing the procedure sets the plan.
🚨 Reversal when bleeding is serious
🚑 One worry people raise about the newer drugs is the antidote. Today serious bleeding can be treated on either type of blood thinner, though the tools differ and some hospitals stock more options than others.
💳 An anticoagulant card or phone emergency note saying which drug you take, the dose and the time of the last dose speeds this up a great deal, especially after a fall or head injury.
📈 If you stay on warfarin: getting the most from it
🎯 Warfarin works as well as it does only when the INR is in range most of the time. Doctors call this time in therapeutic range, and a good result is roughly two thirds of the time or more. People who reach that level get protection close to the newer drugs.
Tests every 1 to 3 days
Weekly while the dose settles
Every 4 weeks or so
Up to 12 weeks in some clinics
🏡 Taking the dose at the same time each day (often early evening), keeping vitamin K intake steady and recording every dose in a booklet or app help most. Home INR meters suit some people well, after training and with a clinic that reviews the results.
🗿 Myths about warfarin and the newer drugs
🚨 When to get help
⛔ Call emergency services or go to hospital now if, on any blood thinner, you have:
🔹 A head injury, even if you feel fine, or a sudden severe headache.
🔹 Vomiting blood or material like coffee grounds, or black, tarry stools.
🔹 Bleeding that will not stop after 10 minutes of firm pressure.
🔹 Signs of stroke: face drooping, arm weakness, slurred speech.
🔹 New one-sided leg swelling or sudden breathlessness, which can mean a clot despite treatment.
📞 Contact your clinic within a day for frequent nosebleeds, bleeding gums, unusual bruising, pink urine, a missed INR test or several missed doses.
📖 For the symptoms of a new leg or lung clot and how long treatment usually lasts, see thrombosis and embolism: symptoms, treatment length and who needs warfarin. The warning signs of stroke are explained in the 4 types of stroke.
❓ Frequently asked questions
Is warfarin still used today?
Yes. It remains the standard for mechanical heart valves, moderate or severe mitral stenosis with atrial fibrillation and high-risk antiphospholipid syndrome, and it is a good option for many others.
Are the newer blood thinners safer than warfarin?
For most people with atrial fibrillation or a first vein clot they cause less bleeding into the brain and need no INR tests. For some groups, such as people with mechanical valves, warfarin is safer.
Can I switch from warfarin to apixaban myself?
No. A switch needs blood tests, a dose chosen for your kidneys and weight, and a start date set by your INR. It should always be planned with the prescriber.
When can I start a DOAC after stopping warfarin?
When the INR has fallen below 2.0 for apixaban or dabigatran, or below the threshold in the label for rivaroxaban or edoxaban. This usually takes a few days.
What should I do if I miss a warfarin dose?
Take it the same day if you remember. If you remember the next day, skip it and take the usual dose. Never double up, and mention it at your next INR test.
How long before surgery is warfarin stopped?
Usually about 5 days before major surgery, with an INR check the day before. Newer drugs are usually stopped 1 to 2 days before, longer if the kidneys are weak.
Do I need heparin injections when warfarin is paused?
Most people do not. Bridging is kept for the highest clot risk, such as a mechanical mitral valve or a clot or stroke in the last three months.
Do I need to stop warfarin for a tooth extraction?
Usually not. An INR test within 72 hours before treatment and local measures by the dentist are normally enough if the INR is in range.
Can I take warfarin with clopidogrel?
Sometimes, for example after a coronary stent, but only on a doctor plan and usually for a limited time, because the combination raises bleeding risk.
Is there an antidote for the newer blood thinners?
Yes. Dabigatran has a specific antibody antidote, and factor Xa blockers can be reversed with a specific antidote or clotting factor concentrate in hospital.
📑 Sources and editorial
- 📘 Cardiology society guidelines on atrial fibrillation and on valvular heart disease
- 🩸 Clinical guidelines on treatment of venous thromboembolism
- 💊 Product labels for warfarin, apixaban, rivaroxaban, dabigatran and edoxaban
- 🔬 Randomised trials comparing DOACs with warfarin in atrial fibrillation, mechanical valves, rheumatic heart disease and antiphospholipid syndrome
- 🏥 Guidance on peri-operative management of anticoagulants and on bridging
- 🦷 Dental guidance on treating patients taking anticoagulants
- 📖 Related reading: warfarin and your INR, atrial fibrillation and stroke prevention, thrombosis and embolism, after a heart attack or stent, living with heart failure swelling
- 🛒 Related products: Coumadin (Warfarin), Plavix (Clopidogrel), Persantine (Dipyridamole), Pletal (Cilostazol), Lanoxin (Digoxin), Toprol XL (Metoprolol Succinate), Zebeta (Bisoprolol), Cardizem (Diltiazem)
- 🩺 RXshop Editorial Team — reviewed by Robert Hayes, MD — Cardiology
Medical Disclaimer: The information in this article is for educational and informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always seek guidance from a qualified healthcare provider with any questions you may have regarding a medical condition, and before starting, stopping or changing any medication.